This paper presents an explainable CNN-based framework for skin lesion classification that combines high diagnostic accuracy with model interpretability. It classifies lesion images and generates visual explanations for its predictions. Results demonstrate strong performance and improved transparency, supporting clinical decision-making and assisting dermatologists in the early detection of skin diseases.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
An Explainable Computer-Aided Framework for Skin Lesion Classification Using Deep Learning
In This Article
Summary
Abstract
The utilization of deep convolutional neural networks for the purpose of diagnosing diseases in the skin area has proven to yield similar accuracy levels to those obtained by dermatologists in different studies. Nevertheless, many challenges are still present, including underperformance and poor generalization in some cases, as well as low interpretability related to the use of black box models. This creates major obstacles for practical implementation since it requires explainability in addition to accurate diagnostics, making it necessary to find a solution. To overcome the mentioned difficulties, an explainable deep learning framework for skin lesion classification (EDLF-SLC) is developed within this study. The framework makes use of various approaches in machine learning and explainable artificial intelligence (XAI) to ensure improvements in terms of both accuracy and interpretability in a three-stage manner. In the initial stage, deep representations extracted from multiple pretrained CNN architectures are fused to preserve complementary discriminative information learned by different network architectures before classification using an SVM with a radial basis function kernel. Next, Support Vector Machine (SVM) classifiers with a radial basis function kernel are used to classify the obtained features. Finally, the predictions made by the model are interpreted through local interpretable model-agnostic explanations (LIME). Experimental results show that EDLF-SLC reaches 88.0% in accuracy, 89.0% in precision, 87.0% in recall, and 88.0% in F1 score, demonstrating competitive performance compared with several recently reported methods under the experimental conditions considered in this study.
Introduction
Skin lesions are a major concern in dermatology and oncology because they range from benign abnormalities to malignant cancers such as melanoma, the deadliest form of skin cancer. In 2020, melanoma accounted for approximately 325,000 new cases and more than 57,000 deaths worldwide1. Although advances in screening and treatment have improved patient outcomes, delayed diagnosis and limited access to healthcare continue to contribute to high mortality and years of life lost, particularly among younger populations2,3.
Traditional diagnosis relies primarily on visual examination and dermoscopy, making the process dependent on clinicians' expertise and prone to subjectivity, inter-observer variability, unnecessary biopsies, and prolonged examination times4,5,6. To address these limitations, deep learning, particularly CNNs, has emerged as an effective solution for automated skin lesion classification. CNN-based models, including DDCNN-F7, YOLOv7-XAI8, and several other architectures9,10,11,12,13, have demonstrated high diagnostic accuracy by automatically learning discriminative image features. Despite their success, most deep learning models operate as "black boxes," limiting clinicians' trust and hindering their adoption in routine medical practice. Explainable artificial intelligence techniques have therefore been introduced to improve model transparency by providing visual explanations of predictions. Among these methods, Local Interpretable Model-Agnostic Explanations generates interpretable local explanations by identifying the image regions that most influence model decisions14.
Skin lesion classification has evolved from traditional clinical assessment to advanced AI-based diagnostic systems driven by the need for accurate, reliable, and early skin cancer detection. This evolution has progressed through five major stages—traditional diagnostic methods, computer-assisted diagnosis (CAD), ML, DL, and, more recently, XAI and federated learning (FL)—reflecting continuous efforts to improve diagnostic accuracy, consistency, scalability, and clinical trustworthiness while overcoming the limitations of conventional examination. Early computational methods attempted to emulate clinical reasoning through handcrafted image descriptors derived from the ABCD rule, including asymmetry, border irregularity, color variation, and lesion diameter. These features were combined with Bayesian networks, decision trees, expert systems, and fuzzy inference models to support melanoma diagnosis, with several studies reporting classification accuracies exceeding 90%15,16,17. Despite providing an important foundation for computer-aided diagnosis, these methods depended entirely on manually engineered features and predefined diagnostic rules. Consequently, they exhibited limited robustness against variations in image quality, lesion morphology, illumination, and acquisition conditions.
To address these shortcomings, classical CAD systems emerged as an intermediate step between conventional image analysis and modern AI-based frameworks. CAD systems combined handcrafted feature extraction with conventional classifiers to improve diagnostic consistency and assist clinical decision-making. Several hybrid approaches integrated hierarchical clustering with recurrent neural networks and long short-term memory architectures, achieving classification accuracies approaching 99.5%18. Other CAD-based frameworks incorporated gradient boosting classifiers with SHAP-based explanations, demonstrating competitive diagnostic accuracy while improving model transparency19. Although these systems represented a significant improvement over purely rule-based approaches, they continued to rely heavily on handcrafted feature extraction, extensive preprocessing, carefully annotated datasets, and multistage processing pipelines.
Machine learning techniques further advanced automated skin lesion classification by enabling data-driven learning rather than explicit rule design. Hybrid frameworks combining convolutional neural networks with conventional machine learning classifiers, including logistic regression and k-nearest neighbors, demonstrated strong classification performance on benchmark datasets, achieving accuracies exceeding 95%9. Self-supervised multimodal learning further improved feature representation by jointly exploiting dermoscopic and clinical images, thereby reducing dependence on extensive manual annotation while improving classification performance20. Additional studies combined CNNs with generalized discriminant analysis, SURF descriptors, and optimization algorithms to improve feature discrimination and classification accuracy21. Automatic feature selection techniques employing DenseNet-201, InceptionV3, and binary tree optimization algorithms further enhanced feature representation while maintaining competitive diagnostic performance22. Transfer learning approaches utilizing pretrained architectures such as AlexNet and GoogLeNet also demonstrated promising classification capability despite limited training data23. Nevertheless, most ML methods continued to depend on carefully designed preprocessing procedures, handcrafted optimization strategies, balanced datasets, and extensive hyperparameter tuning. Their limited external validation and sensitivity to class imbalance further constrained their practical applicability in diverse clinical settings.
The introduction of DL fundamentally transformed automated skin lesion classification by enabling end-to-end learning directly from raw image data. CNNs eliminated the need for handcrafted feature engineering while substantially improving diagnostic performance across multiple benchmark datasets. Most CNN-based approaches demonstrated significant improvements in lesion classification through increasingly sophisticated architectures. Symmetry-aware CNN models explored clinically meaningful lesion characteristics but achieved only moderate balanced accuracy24. Others integrated EfficientNet architectures with LIME and SHAP explanations to improve interpretability while introducing quantitative trustworthiness measures25. Hybrid DL systems combining lesion segmentation, ensemble learning, and CNNs achieved excellent performance on multiple ISIC datasets but remained sensitive to segmentation quality and class imbalance26.
More recently, increasingly sophisticated hybrid architectures have further improved classification accuracy by integrating complementary DL techniques. Conditional generative adversarial networks combined with YOLOv5 and independent component analysis achieved classification accuracies exceeding 99%, although their computational complexity limited practical deployment 27. Similarly, hybrid LSTM–ResNet architectures effectively learned spatial-temporal representations but required substantially greater computational resources28. Transformer-based models, including Sap-Former, exploited global contextual information to enhance feature representation but required extensive preprocessing, large-scale annotated datasets, and significant computational power29. Lightweight alternatives such as S-MobileNet attempted to balance computational efficiency with diagnostic accuracy30, whereas unsupervised domain adaptation methods improved cross-domain generalization despite reduced effectiveness when only limited training samples were available31. Attention-enhanced hybrid networks incorporating modified convolutional attention modules and snapshot ensemble learning also demonstrated promising performance for monkeypox skin lesion classification, although challenges associated with class imbalance, image diversity, and limited explainability remained unresolved32. Customized residual architectures employing deeper network designs and hybrid loss functions further improved classification accuracy beyond 99% but incurred considerably greater computational overhead and training time33. Comprehensive review studies consistently concluded that DL substantially outperforms traditional handcrafted approaches by automatically learning discriminative image representations, while simultaneously identifying persistent challenges associated with imaging artifacts, illumination variability, computational complexity, and limited clinical generalization34.
Although DL has dramatically improved diagnostic accuracy, concerns regarding model transparency, uncertainty estimation, and trustworthy clinical deployment have stimulated growing interest in XAI and federated learning. Several studies have investigated uncertainty quantification techniques, including conformal prediction, Monte Carlo dropout, and evidential deep learning, demonstrating that reliable confidence estimation can substantially improve decision support despite imposing additional computational and data-related constraints35. Transformer-based mutual learning frameworks have also been proposed to address class imbalance while improving feature learning efficiency36. Other approaches combined full-resolution CNNs with graph-based optimization techniques to improve lesion segmentation and classification37, whereas hybrid deep learning frameworks integrating multiple complementary feature representations achieved classification accuracies approaching 99.5% despite requiring extensive preprocessing38.
Recent research has increasingly focused on integrating explainability directly into DL frameworks to enhance clinician trust and facilitate practical clinical adoption. Explainable systems employing multiple convolutional neural network architectures together with Grad-CAM and Score-CAM successfully localized diagnostically relevant lesion regions while maintaining competitive classification performance on both internal and external datasets39. Hybrid CNN–Transformer frameworks combining dermoscopic images with clinical metadata further improved predictive performance while utilizing SHAP and Grad-CAM to generate clinically meaningful visual explanations40. Additional transformer-based hybrid architectures integrating EfficientNetV2S, Swin Transformers, modified Xception networks, and graph attention mechanisms effectively captured complementary global and local lesion characteristics, although their large parameter counts and limited performance on minority classes restricted practical deployment41. Similarly, hybrid YOLOv8–Vision Transformer frameworks demonstrated improved lesion localization, multiclass classification, and visual interpretability through adaptive augmentation together with SHAP and Grad-CAM explanations; however, these methods continued to rely primarily on benchmark datasets and exhibited limited robustness for minority lesion categories42. Several survey articles have summarized these developments, emphasizing both the remarkable progress achieved by modern deep learning techniques and the persistent challenges associated with computational efficiency, explainability, dataset dependency, and clinical validation43,44,45. Table 1 summarizes some recently published work utilizing deep learning algorithms for Skin lesion classification.
Despite the remarkable advances achieved by recent DL methods in skin lesion classification, most existing approaches remain constrained by high computational complexity, dependence on large annotated datasets, limited model interpretability, and insufficient validation across diverse real-world clinical settings. To overcome these limitations, this paper proposes the EDLF-SLC framework that integrates complementary features extracted from multiple CNN architectures with an SVM classifier for robust and accurate classification. The framework further employs enhanced preprocessing to improve image quality and address class imbalance, while incorporating the LIME technique to provide visual explanations of individual predictions, thereby enhancing model transparency and clinical trustworthiness.
The contributions of this study are threefold. First, the authors propose a robust framework, EDLF-SLC, that integrates advanced convolutional neural networks (CNNs) with a support vector machine (SVM) classifier to achieve accurate and reliable skin lesion classification. Second, the authors implement enhanced preprocessing techniques to address class imbalance and reduce image noise, thereby improving the quality of the input images and the overall performance of the classification model. Third, the authors incorporate the Local Interpretable Model-agnostic Explanations (LIME) method to visualize and interpret individual model predictions by highlighting the image regions that most strongly influence classification decisions, thereby improving the transparency and interpretability of the proposed framework.
Access restricted. Please log in or start a trial to view this content.
Protocol
This study did not involve the recruitment of human participants or the collection of identifiable patient data. All experiments were conducted using the publicly available ISIC 2020 skin lesion dataset obtained from the Kaggle repository; therefore, institutional ethics committee approval and informed consent were not required. All the materials used in this study are in the Table of Materials.
Feature extraction and fusion
Skin lesion images were processed using multiple pretrained CNN models. Deep feature vectors extracted from the selected pretrained CNN architectures are concatenated to construct a unified feature representation for each skin lesion image. The adopted fusion strategy preserves complementary visual information learned by different CNN architectures, allowing the subsequent SVM classifier to exploit both low-level texture characteristics and higher-level semantic representations. Although dimensionality reduction techniques such as principal component analysis or mutual information-based feature selection may reduce feature dimensionality, the complete fused representation was intentionally retained because the fused feature space remains computationally tractable for the employed RBF-SVM classifier while preserving complementary diagnostic information extracted from the heterogeneous CNN backbones.
Classification
The fused feature vectors were used to train an SVM classifier with an RBF kernel. Hyperparameter optimization techniques were employed to determine the optimal classification settings. The classifier then categorized skin lesions into their respective classes.
Explainability
To improve interpretability, LIME was applied to generate visual explanations highlighting the image regions that contribute most significantly to the classification outcomes. These explanations would assist clinicians in understanding and validating the model's decisions.
Evaluation plan
The proposed framework was evaluated using a benchmark skin lesion dataset. Performance was assessed using Accuracy, Precision, Recall, and F1-Score. Comparative experiments were conducted against existing machine learning and deep learning approaches to demonstrate the effectiveness of the proposed framework.
Expected outcomes
The study was expected to produce an accurate and interpretable skin lesion classification system. Preliminary experimental results indicate that EDLF-SLC achieves an accuracy of 88.0%, precision of 89.0%, recall of 87.0%, and F1-score of 88.0%, outperforming several competing methods. The integration of LIME explanations was anticipated to enhance the trustworthiness and facilitate the adoption of AI-assisted diagnostic systems in clinical practice.
Significance
This research contributes to the growing field of explainable healthcare AI by addressing both performance and transparency challenges in skin lesion diagnosis. The proposed framework has the potential to support dermatologists in making more reliable and interpretable diagnostic decisions, ultimately improving patient care. Moreover, in this section, the authors provided information regarding materials and the methodology that has been applied within this research study. Specifically, the authors started with the description of the dataset used for the experiments and moved forward to the detailed discussion of the Explainable Deep Learning Framework for Skin Lesion Classification.
Dataset
The presented work relies on the publicly available ISIC 2020 dataset (International Skin Imaging Collaboration), which can be accessed on the Kaggle website (https://www.kaggle.com/datasets/fanconic/skin-cancer-malignant-vs-benign). The ISIC repository has been recognized as one of the best resources in the field of dermatological imaging, since it provides a large variety of dermoscopic images of different types of skin lesions, as shown in Figure 1. Importantly, the dataset includes images of both benign and malignant conditions, making it useful for performing binary classification tasks for skin cancer 46. There are 3,297 images in the current dataset, out of which 1,800 are benign and 1,497 are malignant. For more efficient experiments, the data had to be split into a training set and a testing set. In particular, there are 2,637 training images, including 1,440 benign and 1,197 malignant, while the testing set consists of 660 images, of which 360 are benign and 300 are malignant. A summary of the dataset is shown in Table 2.
The proposed EDLF-SLC model
In this paper, an efficient and understandable solution for classifying skin lesions into benign and malignant categories has been proposed, using a novel explainable deep learning technique based on a hybrid approach combining the advantages of multiple pre-trained convolutional neural network models. Convolutional neural networks have proven highly effective in extracting high-level semantic features from medical images. Using this capability, the proposed explainable deep learning framework for skin lesion classification (EDLF-SLC) exploits multiple pretrained CNN models to achieve superior performance. To ensure the necessary transparency of the medical decision-making process, LIME has been adopted in the proposed approach to generate local human-readable explanations for the output results. The complete framework can be broken down into three main stages, as illustrated in Figure 2, namely, (1) data preprocessing, (2) feature extraction and classification, and (3) interpretability.
Model architecture and integration
As a preliminary step, seven popular deep learning models (MobileNetV2, ResNet50, EfficientNetB0, Xception, InceptionResNetV2, NASNetLarge, and MobileNet) were selected and evaluated on the validation dataset separately, and the four most effective models (ResNet50, EfficientNetB0, MobileNet, and Xception) have been chosen for the feature extraction stage. In the proposed framework, each input image x has been independently passed through the selected pretrained models. The last fully connected layer has been removed from each of these models, and feature vectors have been obtained from the previous layers. fResNet50(x), fEfficientNetB0(x), fMobileNet(x), and fXception(x) refer to the output feature vectors from each of the above-mentioned models. By concatenating those feature vectors, a new aggregated feature vector F(xi) is obtained:
F(xi) = [f(ResNet50)(xi);f(EfficientNetB0)(xi);f(MobileNet)(xi);f(Xception)(xi)] (1)
Afterward, F(xi) has been passed through an SVM classifier with a radial basis function (RBF) kernel to obtain the classification result. The whole algorithm for the proposed framework is presented in Supplementary File 1.
The proposed framework adopts direct feature-level fusion because each pretrained CNN architecture captures different discriminative characteristics of skin lesions through its distinct network architecture and learned feature hierarchy. Consequently, concatenating these heterogeneous feature representations preserves complementary information that contributes to more comprehensive lesion characterization before classification. Although dimensionality-reduction techniques such as principal component analysis (PCA) or mutual information-based feature selection can reduce the dimensionality of the fused representation, the complete fused feature vector was intentionally retained because its dimensionality remains computationally tractable for the adopted RBF-SVM classifier while preserving complementary diagnostic information extracted by the different CNN backbones. This design, therefore, prioritizes retaining complementary deep representations rather than eliminating potentially informative features before classification.
Data preparation
Data preparation has included preprocessing and splitting the data set into training and testing sets. Preprocessing is aimed at enhancing the quality of data by eliminating inconsistencies, deleting duplicate elements, formatting input images, and performing feature scaling for stable training of a good model. All images have been normalized to the range of [−1, 1] by means of the Z-score normalization:
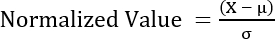 (2)
where µ and σ stand for the mean value and the standard deviation of the corresponding image, respectively. The data set has been divided into two subsets, i.e., a training set (70.0%) and a testing set (30.0%).
Data augmentation
To avoid overfitting and increase the generalization ability of the model, some augmentations have been used for the training set. Image augmentations involve modifying images in order to artificially expand the data set without changing essential features of medical conditions. The augmentation pipeline has been built using the Keras Sequential API. Such transformations as random horizontal flipping, rotation within a small angle, resizing, scaling, brightness/contrast adjustment, zooming, and some minor movements have been used. Representative examples of augmented images are illustrated in Figure 3.
Pretrained models
Several pretrained deep learning models have been adopted in the proposed framework for extracting features from input images. Those models include MobileNet, ResNet50, EfficientNetB0, Xception, NASNetLarge, Inception-ResNet-v2, and MobileNetV2. MobileNet and MobileNetV2 are lightweight deep learning models for efficient computations using depth-wise separable convolutions. ResNet50 employs the mechanism of residual connections for training the model, thus avoiding the problem of vanishing gradients during training. EfficientNetB0 strikes a balance between efficiency and precision through the approach of compound scaling. Xception extends the Inception network using depthwise separable convolutions. NASNetLarge involves the use of neural architecture search to build optimal deep neural network structures, and Inception-ResNet-v2 builds a hybrid of the Inception model and the residual connections mechanism. Feature vectors extracted from ResNet50 (1,024 features), EfficientNetB0 (1,280 features), MobileNet (1,024 features), and Xception (2,048 features) are concatenated to produce a unified 5,376-dimensional representation. This fusion strategy was selected to preserve complementary representations learned by the different CNN architectures rather than reducing the representation prior to classification. The resulting feature vector is subsequently supplied to the RBF-SVM classifier, which determines the optimal nonlinear decision boundary within the fused feature space.
Explainable AI model (LIME)
In order to provide some local interpretability of the model predictions, the authors adopt the method of generating localized human-readable explanations for each particular model prediction, called LIME47. For any input image, LIME first partitions it into smaller units called superpixels. Perturbations are then generated from the original image, and the predictions from the deep neural model are estimated for each of the perturbations. Then, a weighted linear model is fitted on the perturbations using weights depending on their proximity to the original input instance. After fitting the linear model, the feature importance scores are estimated, indicating the role of each superpixel in the prediction of the final label. Those importance scores are visually highlighted in the final explanation image. The LIME algorithm is shown in Supplementary File 2.
Access restricted. Please log in or start a trial to view this content.
Results
Performance assessment of the developed classification framework is based on traditional evaluation measures stemming from the confusion matrix. A confusion matrix allows for obtaining a complete understanding of classifier performance through the representation of the number of right and wrong classifications made for each class defined. In this way, all types of errors can be analyzed. For example, both false positives and false negatives are especially important in the diagnosis of diseases. High values of false posit...
Access restricted. Please log in or start a trial to view this content.
Discussion
The proposed explainable deep learning framework for skin lesion classification (EDLF-SLC) demonstrates that combining complementary deep feature representations with explainable artificial intelligence can improve both classification performance and model transparency. By integrating multiple pretrained CNN architectures (ResNet50, EfficientNetB0, MobileNet, and Xception) for feature extraction and employing a Support Vector Machine (SVM) for final classification, the framework exploits the strengths of different featur...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors declare that there is no conflict of interest.
Acknowledgements
The authors would like to express their sincere appreciation to Taif University for providing the research environment and institutional support that facilitated the completion of this work.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| ISIC 2020 Skin Lesion Dataset | International Skin Imaging Collaboration (ISIC) | ISIC 2020 Challenge Dataset | Dermoscopic image dataset used for model development and evaluation. |
| Keras | Keras Team | Integrated with TensorFlow | Construction and training of deep learning models. |
| LIME (Local Interpretable Model-Agnostic Explanations) | Ribeiro et al. | Python package | Generation of local visual explanations for model predictions. |
| Matplotlib | Matplotlib Developers | Latest compatible version | Visualization of learning curves, confusion matrices, and evaluation plots. |
| NumPy | NumPy Developers | Latest compatible version | Numerical computation and array manipulation. |
| NVIDIA Tesla T4 GPU | NVIDIA Corporation | 16 GB VRAM | Model training and inference acceleration. |
| Pandas | Pandas Development Team | Latest compatible version | Data processing and experimental result management. |
| Pretrained CNN Models | TensorFlow/Keras Applications | ResNet50, EfficientNetB0, MobileNet, Xception | Deep feature extraction from dermoscopic images. |
| Python | Python Software Foundation | Version 3.9 | Programming language used for implementation. |
| PyTorch | PyTorch Foundation | Version 2.3.1 | Deep learning framework used for feature extraction and model implementation. |
| Scikit-learn | Scikit-learn Developers | Latest compatible version | Support Vector Machine (SVM), evaluation metrics, and data preprocessing. |
| Support Vector Machine (RBF Kernel) | Scikit-learn | SVC | Classification of fused deep feature representations. |
| TensorFlow | Google LLC | Version 2.x | Deep learning framework for model training and inference. |
| Ubuntu Operating System | Canonical Ltd. | Ubuntu 20.04 | Experimental operating environment. |
References
- Chan S, Reddy V, Myers B, Thibodeaux Q, Brown-Stone N, Liao W. Machine learning in dermatology: current applications, opportunities, and limitations. Dermatol Ther (Heidelb). 2020;10:365-386.
- Olsen CM. Global trends in melanoma mortality differ by sex and age. Br J Dermatol. 2020;183(6):985-986.
- Sun Y, Shen Y, Liu Q, Zhang H, Jia L, Chai Y, et al. Global trends in melanoma burden: a comprehensive analysis from the Global Burden of Disease Study, 1990-2021. J Am Acad Dermatol. 2025;92(1):100-107.
- Monika MK, Vignesh NA, Kumari CU, Kumar M, Lydia EL. Skin cancer detection and classification using machine learning. Mater Today Proc. 2020;33:4266-4270.
- Hosny KM, Elshora D, Mohamed ER, Vrochidou E, Papakostas GA. Deep learning and optimization-based methods for skin lesions segmentation: a review. IEEE Access. 2023.
- Baghdadi NA, Farghaly Abdelaliem SM, Malki A, Gad I, Ewis A, Atlam ES. Advanced machine learning techniques for cardiovascular disease early detection and diagnosis. J Big Data. 2023;10(1):144.
- Veeramani N, Jayaraman P, Krishankumar R, Ravichandran KS, Gandomi AH. DDCNN-F: double decker convolutional neural network feature fusion as a medical image classification framework. Sci Rep. 2024;14(1).
- Veeramani N, Jayaraman P. YOLOv7-XAI: multiclass skin lesion diagnosis using explainable artificial intelligence with fair decision making. Int J Imaging Syst Technol. 2024;34(6).
- Shetty B, Fernandes R, Rodrigues AP, Chengoden R, Bhattacharya S, Lakshmanna K. Skin lesion classification of dermoscopic images using machine learning and convolutional neural network. Sci Rep. 2022;12(1):18134.
- Ali AR, Li J, Yang G, O'Shea SJ. A machine learning approach to automatic detection of irregularity in skin lesion border using dermoscopic images. PeerJ Comput Sci. 2020;6:e268.
- Pham TTH, Luu TN, Nguyen TV, Huynh NT, Phan QH, Le TH. Polarimetric imaging combining optical parameters for classification of mice non-melanoma skin cancer tissue using machine learning. Heliyon. 2023;9(11).
- Liu N, Rejeesh M, Sundararaj V, Gunasundari B. ACO-KELM: anti coronavirus optimized kernel-based softplus extreme learning machine for classification of skin cancer. Expert Syst Appl. 2023;232:120719.
- Masud M, Almars AM, Rokaya MB, Meshref H, Gad I, Atlam ES. A novel lightweight convolutional neural network model to predict Alzheimer's disease applying weighted loss function. J Disabil Res. 2024;3(4):20240042.
- Kumar A, Veeraiah V, Gongada TN, Ahamad S, Khan H, Gupta A. Explainable machine learning models for clinical decision support systems. In: 2024 15th International Conference on Computing Communication and Networking Technologies (ICCCNT). Piscataway (NJ): IEEE; 2024. p. 1-6.
- Shahzad K, Wasim M, Pires IM, Garcia NM. Multi-classification of skin lesions using a deep learning-based convolutional neural network. Procedia Comput Sci. 2024;241:588-593.
- Celebi ME, Kingravi HA, Uddin B, Iyatomi H, Aslandogan YA, Stoecker WV, et al. A methodological approach to the classification of dermoscopy images. Comput Med Imaging Graph. 2007;31(6):362-373.
- Li CX, Shen CB, Xue K, Shen X, Jing Y, Wang ZY, et al. Artificial intelligence in dermatology: past, present, and future. Chin Med J (Engl). 2019;132(17):2017-2020.
- Ramprasad M, Nagesh S, Sahith V, Lankalapalli RK. Hierarchical agglomerative clustering based skin lesion detection with region-based neural networks classification. Meas Sens. 2023;29:100865.
- Khater T, Ansari S, Mahmoud S, Hussain A, Tawfik H. Skin cancer classification using explainable artificial intelligence on pre-extracted image features. Intell Syst Appl. 2023;20:200275.
- Wang H, Ahn E, Bi L, Kim J. Self-supervised multi-modality learning for multi-label skin lesion classification. Comput Methods Programs Biomed. 2025;265:108729.
- Thapar P, Rakhra M, Alsaadi M, Quraishi A, Deka A, Naga Ramesh JV. A hybrid grasshopper optimization algorithm for skin lesion segmentation and melanoma classification using deep learning. Healthc Anal. 2024;5:100326.
- Kumar S, Nath VK, Hazarika D. Blend of deep features and binary tree growth algorithm for skin lesion classification. Symmetry (Basel). 2023;15(12):2213.
- Chandrahaas BV, Mohanty SN, Panda SK, et al. An empirical study on classification of monkeypox skin lesion detection. EAI Endorsed Trans Pervasive Health Technol. 2023;9:e4.
- Talavera-Martínez L, Bibiloni P, Giacaman A, Taberner R, de Paz Hernando LJD, González-Hidalgo M. A novel approach for skin lesion symmetry classification with a deep learning model. Comput Biol Med. 2022;145:105450.
- Ieracitano C, Morabito FC, Hussain A, Suffian M, Mammone N. TIXAI: a trustworthiness index for explainable artificial intelligence in skin lesion classification. Neurocomputing. 2025;630:129701.
- Hasan MK, Elahi MTE, Alam MA, Jawad MT, Martí R. DermoExpert: skin lesion classification using a hybrid convolutional neural network through segmentation, transfer learning, and augmentation. Inform Med Unlocked. 2022;28:100819.
- Koparde S, Kotwal J, Deshmukh S, Adsure S, Chaudhari P, Kimbahune V. Conditional generative adversarial networks and YOLOv5 Darknet-based skin lesion localization and classification using an independent component analysis model. Inform Med Unlocked. 2024;47:101515.
- Padhy S, Dash S, Kumar N, Singh SP, Kumar G, Moral P. Temporal integration of ResNet features with LSTM for enhanced skin lesion classification. Results Eng. 2025;25:104201.
- Xin C, Liu Z, Ma Y, Wang D, Zhang J, Li L, et al. Transformer-guided self-adaptive network for multi-scale skin lesion image segmentation. Comput Biol Med. 2024;169:107846.
- Sulthana R, Chamola V, Hussain Z, Albalwy F, Hussain A. A novel end-to-end deep convolutional neural network-based skin lesion classification framework. Expert Syst Appl. 2024;246:123056.
- Chamarthi S, Fogelberg K, Brinker TJ, Niebling J. Mitigating the influence of domain shift in skin lesion classification: a benchmark study of unsupervised domain adaptation methods. Inform Med Unlocked. 2024;44:101430.
- Maity S, Paul S, Guha S, Dasgupta S, Ghosh M. Automated classification of monkeypox skin lesions using a hybrid deep learning model. Biomed Signal Process Control. 2026;126:110955.
- Nasir S, Bilal M, Khalidi H. Detection and classification of skin cancer by using CNN-enabled cloud storage data access control algorithm based on blockchain technology. Int J Theor Appl Comput Intell. 2025:145-169.
- Saba T. Computer vision for microscopic skin cancer diagnosis using handcrafted and non-handcrafted features. Microsc Res Tech. 2021;84(6):1272-1283.
- Fayyad J, Alijani S, Najjaran H. Empirical validation of conformal prediction for trustworthy skin lesion classification. Comput Methods Programs Biomed. 2024;253:108231.
- Liu P, Qian W, Li H, Cao J. A relationship-aware mutual learning method for lightweight skin lesion classification. Digit Commun Netw. 2025;11(3):603-612.
- Adla D, Reddy GVR, Nayak P, Karuna G. A full-resolution convolutional network with a dynamic graph cut algorithm for skin cancer classification and detection. Healthc Anal. 2023;3:100154.
- Thamizhamuthu R, Maniraj SP. Deep learning-based dermoscopic image classification system for robust skin lesion analysis. Trait Signal. 2023;40(3).
- Di Giammarco M, Santone A, Cesarelli M, Martinelli F, Mercaldo F. A method for skin lesion detection and localization by means of deep learning and reliable prediction explainability. Image Vis Comput. 2025;162:105675.
- Haq IU, Joarder HA, Khan AA, Shi X, Alsayaydeh JAJ, Yusof MFB, et al. XAAI-ledger: an explainable CNN-transformer-based multimodal deep learning framework for early detection of melanoma and non-melanoma skin cancers using dermoscopic and clinical data. Biomed Signal Process Control. 2026;123:110410.
- Saeed K, Shehzad M, Malik MGA, Ahmed S, Azar AT. TransXV2S-NET: a novel hybrid deep learning architecture with dual-contextual graph attention for multi-class skin lesion classification. Knowl Based Syst. 2026;337:115407.
- AbuAlkebash H, Saleh RAA, Ertunç HM. Automated explainable deep learning framework for multiclass skin cancer detection and classification using hybrid YOLOv8 and vision transformer (ViT). Biomed Signal Process Control. 2025;108:107934.
- Hasan MK, Ahamad MA, Yap CH, Yang G. A survey, review, and future trends of skin lesion segmentation and classification. Comput Biol Med. 2023;155:106624.
- Li H, Pan Y, Zhao J, Zhang L. Skin disease diagnosis with deep learning: a review. Neurocomputing. 2021;464:364-393.
- Wu Y, Chen B, Zeng A, Pan D, Wang R, Zhao S. Skin cancer classification with deep learning: a systematic review. Front Oncol. 2022;12:893972.
- Fanconic. Skin cancer: malignant vs benign dataset. Kaggle; 2023. Available from: https://www.kaggle.com/datasets/fanconic/skin-cancer-malignant-vs-benign
- Ribeiro MT, Singh S, Guestrin C. "Why should I trust you?": Explaining the predictions of any classifier. In: Proceedings of the 22nd ACM SIGKDD International Conference on Knowledge Discovery and Data Mining (KDD '16). New York (NY): ACM; 2016. p. 1135-1144.
- Bassel A, Abdulkareem AB, Alyasseri ZAA, Sani NS, Mohammed HJ. Automatic malignant and benign skin cancer classification using a hybrid deep learning approach. Diagnostics (Basel). 2022;12(10):2472.
- Bhardwaj A, Rege PP. Skin lesion classification using deep learning. In: Advances in Signal and Data Processing: Select Proceedings of ICSDP 2019. Singapore: Springer; 2021. p. 575-589.
- Keerthana D, Venugopal V, Nath MK, Mishra M. Hybrid convolutional neural networks with SVM classifier for classification of skin cancer. Biomed Eng Adv. 2023;5:100069.
- Ahmed A, Siam AI, Atwa MA, Atwa EM, Abdelrahim EM, Atlam ES. An explainable YOLO-based deep learning framework for pneumonia detection from chest X-ray images. Algorithms. 2025;18(11):703.
- Farsi M, ZainEldin H, Sayed RF, El-Agamy ES, Atlam SA, Alsaedi M, et al. Deep learning for pathology: YOLOv8 with EigenCAM for reliable colorectal cancer diagnostics. Bioengineering (Basel). 2025;12(11):1203.
- Atwa EA, Atlam ES, Ahmed A, Atwa MA, Abdelrahim EM, Siam AI. Interpretable deep learning models for arrhythmia classification based on ECG signals using the PTB-XL dataset. Diagnostics (Basel). 2025;15(15):1950.
Access restricted. Please log in or start a trial to view this content.