miR‑486‑3p is downregulated in acute cerebral infarction patients with obstructive sleep apnea syndrome, correlates negatively with disease severity and inflammatory markers, and predicts poor 1‑year prognosis, supporting its potential as a diagnostic and prognostic biomarker.
Research Article
Retrospective Cohort Study of Peripheral Blood miR-486-3p Levels in Patients with Acute Cerebral Infarction and Obstructive Sleep Apnea Syndrome
In This Article
Summary
Abstract
Acute cerebral infarction (ACI) complicated with obstructive sleep apnea syndrome (OSAS) confers a high risk of stroke recurrence and death, yet effective biomarkers for this comorbid condition remain limited. This retrospective cohort study enrolled 270 patients with ACI between November 2020 and December 2023, who were classified into the ACI group (n = 100, apnea‑hypopnea index [AHI] < 5) and the ACI with OSAS group (n = 170, AHI ≥ 5), with the latter further stratified into mild (5 ≤ AHI < 15, n = 60), moderate (15 ≤ AHI < 30, n = 75), and severe (AHI ≥ 30, n = 35) subgroups. Serum miR‑486‑3p expression was measured by RT‑qPCR, and inflammatory markers, including tumor necrosis factor‑α (TNF‑α), C‑reactive protein (CRP), and hypoxia‑inducible factor‑1α (HIF‑1α), were quantified by ELISA. The diagnostic value of miR‑486‑3p was evaluated using receiver operating characteristic curve analysis, and its prognostic significance was assessed through Kaplan‑Meier survival analysis and Cox regression models. miR-486-3p was markedly lower in the comorbid group and demonstrated strong diagnostic ability (AUC = 0.927). Notably, a clear dose‑dependent trend was observed across OSAS severity subgroups, with miR‑486‑3p decreasing progressively and TNF‑α and CRP increasing stepwise from mild to severe OSAS. Spearman correlation analyses revealed that miR‑486‑3p was negatively correlated with AHI, NIHSS score, TNF‑α, and CRP. At 1‑year follow‑up, patients with low miR‑486‑3p expression had significantly worse functional outcomes compared with those with high expression. Multivariate Cox regression confirmed miR‑486‑3p as an independent protective factor for 1‑year prognosis. These findings suggest that miR‑486‑3p may serve as a novel diagnostic and prognostic biomarker for ACI patients with OSAS, potentially through its regulatory role in systemic inflammation, and warrant further validation in larger prospective cohorts.
Introduction
Obstructive sleep apnea syndrome (OSAS) is a common condition characterized by repeated interruptions in breathing during sleep1. OSAS is often associated with comorbidities such as metabolic, cardiovascular, renal, pulmonary, and neuropsychiatric disorders2. Beyond its general associations with cardiovascular and metabolic diseases, OSAS poses a specific and grave threat in acute ischemic stroke, complicating up to 70% of cases and increasing risks of neurological decline, mortality, and recurrent stroke3,4,5. Acute cerebral infarction (ACI) constitutes the most prevalent form of stroke. Although significant progress has been made in ACI treatment in recent years, most patients still suffer from severe disability or even death6. The synergistic interplay between ACI combined OSAS exacerbates ischemic damage and systemic inflammation, substantially elevating risks of stroke recurrence, disability, and mortality. Consequently, identifying reliable biomarkers for the early diagnosis and management of this high-risk comorbid condition is of paramount importance.
MicroRNAs (miRNAs) have shown great promise as biomarkers in recent years. Among them, miR-486-3p is of great significance in neurovascular diseases. Previous research have shown that miR-486-3p expression is inhibited in obstructive sleep apnea (OSA)7. In addition, rabies virus glycoprotein-miR-486-3p-exosome treatment can alleviate neurobehavioral disorders, cerebral edema, blood-brain barrier damage, and neurodegeneration8, indicating that miR-486-3p plays a role in brain injury. After ACI, microglia in the damaged brain tissue are activated, promoting the secretion of inflammatory cytokines5. OSAS causes intermittent hypoxia symptoms, leading to activation of the sympathetic nervous system and oxidative stress, thereby triggering a systemic inflammatory cascade reaction9. miR-486-3p is closely related to inflammation10. These lines of evidence suggest that miR-486-3p may serve as a molecular link between OSAS-related hypoxia, systemic inflammation, and post-stroke recovery.
However, its expression profile, diagnostic accuracy, and prognostic significance in ACI patients combined with OSAS have not been systematically investigated, and whether it correlates with OSAS severity or inflammatory mediators in a dose-dependent manner remains unknown. To address these gaps, this study evaluated the diagnostic value of miR-486-3p for OSAS in ACI patients, examined its dose-dependent relationship with OSAS severity and inflammatory markers (TNF-α, CRP, and HIF-1α), and assessed its prognostic utility for 1-year functional outcomes. To our knowledge, this is the first comprehensive study to demonstrate that miR-486-3p may serve as a novel diagnostic and prognostic biomarker for ACI-OSAS comorbidity, potentially through regulation of systemic inflammation.
Protocol
This study was approved by the Ethics Committee of Affiliated Hospital of Xuzhou Medical University (approval number: XYFY2024-KL238-01) and was exempt from the requirement to obtain additional informed consent from patients. The reagents and the equipment used are listed in the Table of Materials.
Patients and specimens
This study was a retrospective cohort study. From November 2020 to December 2023, a total of 270 patients undergoing ACI from Affiliated Hospital of Xuzhou Medical University were consecutively recruited. The patient selection process is summarized in Supplementary Figure 1. Eligible patients were identified through daily screening of all new admissions to the stroke unit. Symptom onset within 72 h prior to admission was verified by reviewing emergency medical records and confirmed by a certified neurologist through patient history and family interview. The sample size was calculated based on the ability to detect a significant difference in miR-486-3p levels between groups. Assuming an effect size of 0.5, a two-sided α of 0.05, and a power (1-β) of 0.80, a minimum of 64 patients per group was required. The final group sizes reflect the actual recruitment and the higher prevalence of OSAS in the stroke population, not a predetermined allocation. Patients with ACI combined OSAS were followed up on their prognosis for 1 year.
The inclusion criteria were: (1) Acute ischemic stroke with symptom onset within 72 h before admission, confirmed by magnetic resonance imaging. (2) The ability to comprehend and complete the study questionnaires and neurological assessments. (3) The severity of the ACI was assessed by the National Institutes of Health Stroke Scale (NIHSS) at admission. When the NIHSS score is <5, it is classified as mild ACI; when the NIHSS score is between 5 and 20, it is considered moderate ACI. Key exclusion criteria included a history of malignant tumors, pre-existing severe physical disability or psychiatric disorders, severe cardiac, pulmonary, or renal insufficiency, and major surgery or trauma within the preceding 3 months, active infections or autoimmune diseases; previous stroke within 6 months; immunosuppressive therapy; and prior diagnosis or treatment of OSAS (including continuous positive airway pressure therapy).
For MRI confirmation, all patients underwent standard brain MRI on a 3.0-T system, including the following sequences: T1-weighted, T2-weighted, fluid-attenuated inversion recovery (FLAIR), diffusion-weighted imaging (DWI), and apparent diffusion coefficient (ADC) mapping. Acute infarction was defined as the presence of a hyperintense signal on DWI with a corresponding hypointense signal on ADC. All MRI scans were interpreted by two experienced neuroradiologists who were blinded to the clinical data, with discrepancies resolved by consensus. NIHSS scoring was performed at admission by certified neurologists prior to any thrombolytic or endovascular treatment.
Fasting venous blood was collected between 24 h and 48 h after stroke onset, following an overnight fast of at least 8 h. Blood draws were performed between 6:00 AM and 8:00 AM to minimize circadian variation. A total of 5 mL of peripheral venous blood was collected into EDTA-coated vacuum tubes. Within 2 h of collection, blood samples were centrifuged at 1,500 × g for 15 min at 4 °C using a refrigerated centrifuge. The serum supernatant was carefully aliquoted into 1.5 mL RNase-free microcentrifuge tubes and immediately stored at −80 °C until RNA extraction. Repeated freeze-thaw cycles were strictly avoided; all aliquots were subjected to a maximum of one freeze-thaw cycle prior to analysis.
Patient grouping
Participants were grouped based on their AHI scores from polysomnography. All recordings were performed in the hospital sleep laboratory between 10:00 PM and 6:00 AM for a minimum duration of 7 h. The monitored physiological channels included: electroencephalography (EEG; six channels), electrooculography (EOG; two channels), electromyography (EMG; chin and bilateral anterior tibialis), electrocardiography (ECG; single lead), nasal airflow (thermistor and pressure transducer), thoracic and abdominal respiratory effort (respiratory inductance plethysmography), and pulse oximetry (SpO2). The sleep study technician calculated AHI. Scoring of sleep stages and respiratory events was performed manually by a certified sleep technician according to the American Academy of Sleep Medicine (AASM) 2012 scoring manual, using the Somnolyzer 24×7 software. According to the widely accepted diagnostic criteria of the American Academy of Sleep Medicine, an AHI of 5 or more events per hour is the standard threshold for diagnosing OSA. Therefore, participants with an AHI < 5 were classified as the ACI group (n = 100), whereas those with an AHI ≥ 5 were classified as the ACI combined OSAS group (n = 170). Among those with AHI ≥ 5 (ACI combined OSAS group, n = 170), patients were further stratified into three severity subgroups based on established criteria: mild OSAS (5 ≤ AHI < 15, n = 60), moderate OSAS (15 ≤ AHI < 30, n = 75), and severe OSAS (AHI ≥ 30, n = 35). This stratification enabled evaluation of the dose‑dependent relationship among hypoxic burden, miR‑486‑3p expression, and inflammatory markers. Patients with prior OSAS treatment (e.g., CPAP) were not included in the study to avoid confounding of the baseline AHI measurement.
Prognosis assessment
The 1-year timepoint allows acute effects to resolve and the cumulative hypoxic burden of OSAS to manifest, providing a robust window to assess its prognostic impact. The clinical prognosis of patients with ACI combined with OSAS was evaluated by the modified Rankin Scale (mRS) after the onset of the disease. All mRS assessments were performed by certified neurologists who underwent standardized training prior to the study, using the structured mRS interview form. Inter-rater reliability was assessed with a kappa coefficient >0.85. The follow-up assessment was conducted through a scheduled outpatient clinic visit. For patients unable to attend in person, a structured telephone interview was performed by a trained research nurse using a standardized script. All assessors were blinded to the patients’ miR-486-3p levels and OSAS status. To maintain consistency between outpatient and telephone assessments, both formats used the same structured questionnaire, and all assessors completed a pre-study calibration exercise. Patients with scores of 0–2 were placed in the good prognosis group, and those with scores of 3–6 were placed in the poor prognosis group. No patients were lost to follow-up. The SAQLI, ESS, TNF-α, and HIF-1α were evaluated as prognostic variables rather than being used to define prognosis groups. The NIHSS, SAQLI, and ESS were administered by trained research staff. The SAQLI and ESS were administered as interviewer-administered questionnaires in a quiet room.
Scoring index
NIHSS is a quantitative scale for stroke11, with higher scores indicating greater severity of ACI. SAQLI is a quality of life questionnaire for OSA on a scale of 1–7, with higher scores indicating worse quality of life, covering daily activities, social interactions, emotional states, symptoms, and treatment-related symptoms12. ESS is used to examine patients' self-reported daytime sleepiness, with a score range from 0 to 24, and a score > 10 indicates daytime sleepiness13.
RNA extraction and reverse transcription
Total RNA was extracted from 200 µL of serum using TRIzol reagent. Briefly, serum samples were mixed with 800 µL of TRIzol, incubated at room temperature for 5 min, and centrifuged at 12,000 × g for 15 min at 4 °C. Chloroform (200 µL) was added, and the mixture was vigorously shaken for 15 s, incubated for 3 min, and centrifuged at 12,000 × g for 15 min at 4 °C. The aqueous phase was transferred to a fresh tube, and RNA was precipitated with 500 µL of isopropanol, incubated at −20 °C for 1 h, and centrifuged at 12,000 × g for 10 min at 4 °C. The RNA pellet was washed with 75% ethanol, air-dried, and dissolved in 20 µL of RNase-free water. RNA concentration and purity were assessed using a microvolume spectrophotometer, with an A260/A280 ratio between 1.8 and 2.0 accepted for downstream analysis. RNA integrity was verified by agarose gel electrophoresis.
Reverse transcription was performed using 500 ng of total RNA with the Reverse Transcription Kit in a total reaction volume of 20 µL, using random hexamer primers according to the manufacturer's protocol. The reverse transcription reaction was carried out at 25 °C for 10 min, 42 °C for 60 min, and 70 °C for 5 min. The resulting cDNA was stored at −20 °C until use.
RT-qPCR
miR-486-3p expression was detected using a SYBR Green–based real-time PCR kit for microRNA quantification on a real-time quantitative PCR (qPCR) system. The reaction mixture contained 10 µL of 2× SYBR Green Master Mix, 2 µL of cDNA template (diluted 1:5), 1 µL of each primer (10 µM), and nuclease-free water to a final volume of 20 µL. The primer sequences are as follows (from 5'-3'): miR-486-3p-forward: TCGGCAGCGGGGCAGCUCAGU, reverse: CTCAACTGGTGTCGTGGA; and U6-forward: CTCGCTTCGGCAGCACA, reverse: AACGCTTCACGAATTTGCGT. The qPCR cycling conditions were: 95 °C for 2 min, followed by 40 cycles of 95 °C for 30 s, 60 °C for 30 s, and 72 °C for 60 s. Each sample was run in triplicate, and a no-template control was included in each run. Specificity of amplification was confirmed by melting curve analysis from 60 °C to 95 °C. The cycle threshold (Ct) was automatically determined by the QuantStudio 6 Pro software (v1.5) using the default threshold setting. miR-486-3p level was calculated with the 2-ΔΔCT method and normalized to U6. U6 was validated as a stable reference gene in our serum samples using the NormFinder algorithm to ensure consistency across groups. Inter-assay and intra-assay coefficients of variation were <5%.
ELISA
The serum concentrations of C-reactive protein (CRP), TNF-α, and HIF-1α were detected using the ELISA kit. The experimental procedures were carried out in accordance with the manufacturer's instructions. Briefly, serum samples were thawed on ice and diluted 1:2 with the provided dilution buffer. Samples and standards were added to pre-coated 96-well plates (100 µL/well) and incubated for 2 h at 37°C. After washing four times with 300 µL of wash buffer, 100 µL of biotin-conjugated detection antibody was added and incubated for 1 h at 37°C. Following another wash step, 100 µL of horseradish peroxidase-conjugated streptavidin was added and incubated for 30 min at 37°C in the dark. The chromogenic substrate (tetramethylbenzidine, 100 µL) was added and incubated for 15 min at 37°C protected from light. The reaction was terminated with 50 µL of stop solution, and absorbance was measured at 450 nm using a microplate reader. The concentrations were calculated from standard curves generated with known concentrations of recombinant proteins. Each sample was measured in duplicate, and the mean value was used for analysis. Quality control samples provided by the manufacturer were included in each plate; results were accepted only when QC values fell within the manufacturer's specified range.
Quality control and reproducibility
All laboratory assays were performed in accordance with the MIQE (Minimum Information for Publication of Quantitative Real-Time PCR Experiments) guidelines for RT-qPCR and the appropriate reporting standards for ELISA. Major instruments were calibrated according to the manufacturers' schedules. Negative and positive control samples were included in each batch of RT-qPCR and ELISA runs to monitor plate-to-plate variability. All data were recorded and managed using Microsoft Excel, and the corresponding author will provide detailed experimental protocols and raw data upon reasonable request.
Statistical analysis
Data were analyzed using SPSS 23.0 and a statistical and graphing software. Normal distribution was assessed by the Shapiro–Wilk test. Continuous variables are presented as mean ± SD or median (IQR), and were compared by t‑test or Mann–Whitney U test, as appropriate. Categorical variables were compared by the χ2 test. Correlations were examined using Pearson or Spearman analyses based on the data distribution. The predictive value was determined using the ROC curve and verified with 5-fold cross-validation. The optimal cutoff value for miR-486-3p was determined by maximizing the Youden index. Pearson and Spearman correlation analyses were used to assess correlations. For prognostic analysis, patients were stratified by the median miR‑486‑3p expression; Kaplan–Meier curves with the log‑rank test were used to compare survival outcomes between groups. Variables with P < 0.1 in univariate Cox regression were entered into the multivariate Cox model. P < 0.05 was considered statistically significant.
Results
Baseline characteristics in the ACI group and the ACI combined OSAS group
As shown in Table 1, the ACI group consisted of 68 males and 32 females, with an average age of 62.84 ± 12.65 years, and the ACI combined OSAS group included 116 males and 54 females, with an average age of 61.31 ± 11.25 years. The ACI combined OSAS group had significantly higher AHI, NIHSS scores, and CRP levels. However, the two groups showed comparable distributions of age, gender, BMI, hypertension, DM, cardiopathy, dyslipidemia, smoking, drinking, thrombolysis, and TOAST.
Changes in miR-486-3p and inflammatory markers across OSAS severity subgroups
To evaluate the dose-dependent relationship between OSAS severity and molecular changes, we stratified the 170 patients with ACI and OSAS into mild (5 ≤ AHI < 15, n = 60), moderate (15 ≤ AHI < 30, n = 75), and severe (AHI ≥ 30, n = 35) subgroups based on AHI criteria. As shown in Figure 1A–C, a clear graded pattern was observed across the four groups (ACI, mild, moderate, and severe OSAS). Specifically, miR-486-3p expression decreased progressively from the ACI group to the severe OSAS subgroup (Figure 1A, P < 0.001 vs. ACI group). In contrast, serum TNF-α and CRP levels increased stepwise with OSAS severity (Figure 1B,C, P < 0.001 vs. ACI group). These findings indicate that the hypoxic burden imposed by OSAS is associated with a graded suppression of miR-486-3p and a parallel augmentation of systemic inflammation.
Diagnostic value of miR-486-3p for OSAS in ACI patients
miR-486-3p may have significant diagnostic value in ACI combined OSAS, with an AUC of 0.927 (optimal cutoff value was 0.845), and sensitivity and specificity were 92.94% and 79.00% (Figure 1D). To evaluate the robustness of the diagnostic model and rule out potential overfitting, 5‑fold cross‑validation was performed for the ROC analysis of miR‑486‑3p. As shown in Supplementary Table 1, the average AUC across the five folds was 0.928 (ranging from 0.847 to 0.969), which was highly consistent with the apparent AUC of 0.927 from the original analysis. The mean sensitivity and specificity were 88.83% and 87.00%, respectively.
Correlations of miR-486-3p with stroke severity and inflammatory markers in ACI combined OSAS
In the ACI with OSAS group, Spearman correlation analyses revealed that miR-486-3p expression was significantly negatively correlated with NIHSS score (Figure 2A), TNF-α (Figure 2B), and CRP (Figure 2C).
Prognostic indicators in the good and poor prognosis groups
Patients with ACI combined OSAS were divided into a good prognosis group and a poor prognosis group according to mRS scores. As demonstrated in Table 2, mRS score, SAQLI score, ESS score, HIF-1α, and TNF-α were increased in the poor prognosis group.
Prognostic value of miR-486-3p for 1-year outcomes of ACI combined OSAS patients
Kaplan-Meier curve results indicated that high levels of miR-486-3p were associated with a good prognosis, whereas low levels were associated with a poor prognosis (Figure 2D). In the univariate analysis, miR-486-3p expression and NIHSS score were associated with clinical outcomes. Other variables, including SAQLI score (P = 0.078), HIF-1α (P = 0.086), TNF-α (P = 0.072), age (P = 0.082), DM (P = 0.067), cardiopathy (P = 0.065), and AHI (P = 0.069), showed marginally significant associations with prognosis, which were also included in the multivariate Cox analysis. In multivariate analysis, miR-486-3p remained an independent protective factor (HR = 0.437, 95% CI: 0.278–0.684, P < 0.001), while cardiopathy (HR = 1.822, 95% CI: 1.070–3.104, P = 0.027) and NIHSS score (HR = 1.597, 95% CI: 1.008–2.529, P = 0.046) emerged as independent risk factors for poor clinical outcomes (Table 3).
Summary of findings
In summary, the present study demonstrated that miR‑486‑3p is significantly downregulated in ACI patients with comorbid OSAS and exhibits high diagnostic accuracy for identifying OSAS in this population. A clear dose‑dependent relationship was observed across OSAS severity subgroups, with miR‑486‑3p decreasing progressively and inflammatory markers (TNF‑α and CRP) increasing stepwise from mild to severe OSAS. Correlation analyses further confirmed that miR‑486‑3p was negatively associated with both stroke severity (NIHSS) and systemic inflammation. Importantly, low miR‑486‑3p expression predicted poor 1‑year functional outcomes, and multivariate Cox regression identified miR‑486‑3p as an independent protective factor after adjustment for potential confounders, including NIHSS and AHI. Collectively, these findings support the hypothesis that miR‑486‑3p may serve as a novel diagnostic and prognostic biomarker for ACI‑OSAS comorbidity, potentially through its regulatory role in systemic inflammation.
DATA AVAILABILITY:
The raw data supporting the findings of this study are available in Supplementary File 1, which includes baseline characteristics, miR‑486‑3p expression levels, ELISA measurements, and 1‑year mRS follow‑up data for all enrolled patients.
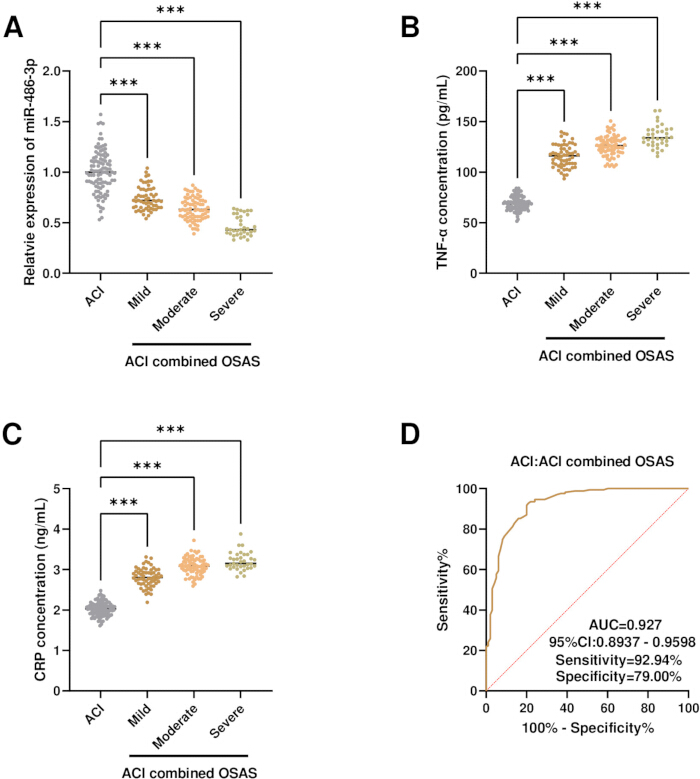
Figure 1: Changes in miR-486-3p and inflammatory markers across ACI combined OSAS severity subgroups and diagnostic performance of miR-486-3p for OSAS. (A) Relative expression of miR-486-3p in the ACI group and ACI combined OSAS subgroups. (B) Serum TNF-α concentration combined. (C) Serum CRP concentration in the ACI group (AHI < 5, n=100) and mild (5 ≤ AHI < 15, n=60), moderate (15 ≤ AHI < 30, n=75), and severe (AHI ≥ 30, n=35) OSAS subgroups. (D) ROC curve of miR-486-3p for discriminating ACI patients with OSAS from those without. ***P < 0.001. Please click here to view a larger version of this figure.
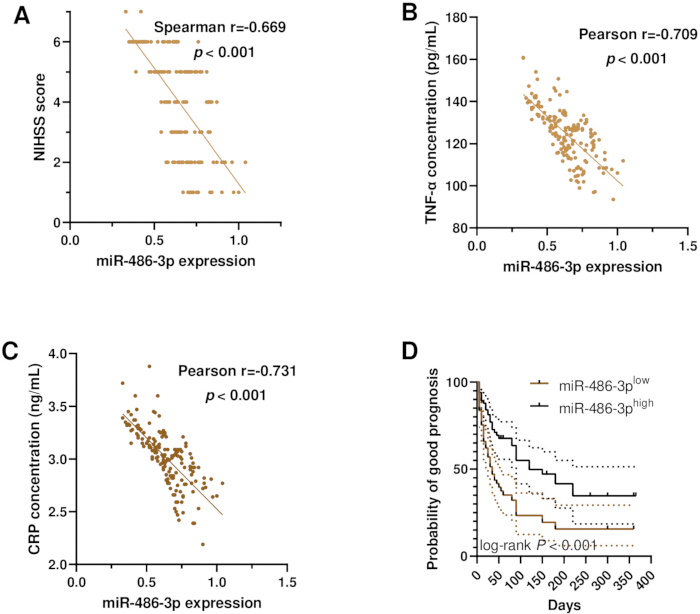
Figure 2: Correlations of miR-486-3p with stroke severity and inflammatory markers, and its prognostic value for 1-year outcomes. (A–C) Spearman correlation analyses of miR-486-3p expression with NIHSS score, TNF-α, and CRP. (D) Kaplan-Meier survival curves for good prognosis probability at 1-year follow-up, stratified by median miR-486-3p expression. ***P < 0.001. Please click here to view a larger version of this figure.
| Variable | ACI (n=100) | ACI and OSAS (n=170) | P value | |
| Age (years) | 62.84 ± 12.65 | 61.31 ± 11.25 | 0.303 | |
| Gender (male/female) | 68/32 | 116/54 | 0.968 | |
| BMI (kg/m2) | 24.74 ± 3.57 | 25.02 ± 3.47 | 0.531 | |
| Hypertension, n (%) | 74 (74%) | 134 (78.82%) | 0.365 | |
| DM, n (%) | 22 (22%) | 43 (25.29%) | 0.543 | |
| Cardiopathy, n (%) | 13 (13%) | 25 (14.71%) | 0.698 | |
| AHI (times/h) | 2.07 ± 1.42 | 19.95 ± 9.19 | < 0.001*** | |
| NIHSS score | 1.70 ± 1.18 | 4.05 ± 1.73 | < 0.001*** | |
| CRP (ng/mL) | 2.03 ± 0.17 | 3.01 ± 0.27 | < 0.001*** | |
| ACI grade (mild/moderate) | 99/1 | 69/101 | < 0.001*** | |
| Dyslipidemia (yes/no) | 52/48 | 96/74 | 0.478 | |
| Smoking (yes/no) | 48/52 | 91/79 | 0.382 | |
| Drinking (yes/no) | 40/60 | 87/83 | 0.076 | |
| Thrombolysis (yes/no) | 38/62 | 81/89 | 0.124 | |
| TOAST | 0.487 | |||
| Cardioembolism (n) | 22 | 36 | ||
| Small vessel occlusion (n) | 18 | 28 | ||
| Large artery atherosclerosis (n) | 13 | 25 | ||
| Stroke of undetermined etiology (n) | 5 | 19 | ||
| Stroke of other determined etiology (n) | 42 | 62 | ||
Table 1: Baseline characteristics of ACI patients with and without OSAS. Data are presented as mean ± SD for continuous variables or n (%) for categorical variables. P values were calculated using the independent t-test for continuous variables and the chi-square test for categorical variables. ACI, acute cerebral infarction; OSAS, obstructive sleep apnea syndrome; BMI, body mass index; DM, diabetes mellitus; AHI, apnea‑hypopnea index; NIHSS, National Institutes of Health Stroke Scale; CRP, C‑reactive protein; TOAST, Trial of Org 10172 in Acute Stroke Treatment.
| Variable | Good prognosis (n=97) | Poor prognosis (n=73) | P value |
| mRS score | 0.88 ± 0.84 | 4.55 ± 1.08 | < 0.001*** |
| SAQIL score | 2.59 ± 1.17 | 3.12 ± 1.48 | 0.009** |
| ESS score | 8.69 ± 2.76 | 10.05 ± 2.79 | 0.002** |
| HIF-1α (pg/mL) | 1159.94 ± 277.86 | 1283.88 ± 445.15 | 0.027* |
| TNF-α (pg/mL) | 121.4 ± 12.87 | 128.4 ± 11.67 | < 0.001*** |
Table 2: Prognostic indicators in the good and poor prognosis groups of ACI patients with OSAS. Patients were divided into good prognosis (mRS 0–2, n = 97) and poor prognosis (mRS 3–6, n = 73) groups based on 1‑year mRS scores. Data are presented as mean ± SD. P values were calculated using the independent t-test. mRS, modified Rankin Scale; SAQLI, Calgary Sleep Apnea Quality of Life Index; ESS, Epworth Sleepiness Scale; HIF‑1α, hypoxia‑inducible factor‑1α; TNF‑α, tumor necrosis factor‑α.
| Variable | HR | Univariate 95%CI | P | HR | Multivariate 95%CI | P | ||
| Lower | Upper | Lower | Upper | |||||
| miR-486-3p | 0.442 | 0.228 | 0.679 | <0.001 | 0.437 | 0.278 | 0.684 | <0.001 |
| SAQLI score | 0.628 | 0.375 | 1.053 | 0.078 | 0.713 | 0.416 | 1.22 | 0.217 |
| ESS score | 0.922 | 0.595 | 1.429 | 0.718 | ||||
| HIF-1α | 0.694 | 0.457 | 1.053 | 0.086 | 0.802 | 0.523 | 1.229 | 0.311 |
| TNF-α | 1.469 | 0.966 | 2.233 | 0.072 | 1.494 | 0.978 | 2.284 | 0.063 |
| Age | 1.445 | 0.955 | 2.188 | 0.082 | 1.29 | 0.845 | 1.97 | 0.238 |
| Gender | 0.829 | 0.534 | 1.285 | 0.401 | ||||
| BMI | 1.196 | 0.786 | 1.821 | 0.402 | ||||
| Hypertension | 0.754 | 0.465 | 1.222 | 0.252 | ||||
| DM | 1.512 | 0.972 | 2.351 | 0.067 | 1.246 | 0.79 | 1.965 | 0.343 |
| Cardiopathy | 1.611 | 0.971 | 2.673 | 0.065 | 1.822 | 1.07 | 3.104 | 0.027 |
| AHI | 1.468 | 0.97 | 2.222 | 0.069 | 1.125 | 0.734 | 1.725 | 0.588 |
| NIHSS score | 1.588 | 1.027 | 2.455 | 0.037 | 1.597 | 1.008 | 2.529 | 0.046 |
| Dyslipidemia | 1.178 | 0.776 | 1.788 | 0.442 | ||||
| Smoking | 0.895 | 0.593 | 1.35 | 0.596 | ||||
| Drinking | 1.116 | 0.738 | 1.689 | 0.603 | ||||
| Thrombolysis | 1.259 | 0.834 | 1.902 | 0.272 | ||||
Table 3: Univariate and multivariate Cox regression analyses for 1‑year poor prognosis in ACI patients with OSAS. HR, hazard ratio; CI, confidence interval; SAQLI, Calgary Sleep Apnea Quality of Life Index; ESS, Epworth Sleepiness Scale; HIF‑1α, hypoxia‑inducible factor‑1α; TNF‑α, tumor necrosis factor‑α; BMI, body mass index; DM, diabetes mellitus; AHI, apnea‑hypopnea index; NIHSS, National Institutes of Health Stroke Scale. Variables with P < 0.1 in univariate analysis were entered into the multivariate Cox model.
Supplementary Figure 1: Flowchart of patient selection and subgroup stratification.Please click here to download this file.
Supplementary Table 1: Five‑fold cross‑validation for internal validation of the diagnostic value of miR‑486‑3p. AUC, area under the curve; CI, confidence interval. The average AUC, sensitivity, and specificity were calculated as the arithmetic mean across the five folds.Please click here to download this file.
Supplementary File 1: The raw data supporting the findings of this study.Please click here to download this file.
Discussion
Patients with OSAS experience repeated airway collapse and obstruction, leading to intermittent hypoxia (IH) and excessive daytime sleepiness (EDS), which can cause neuronal damage14. OSA is highly prevalent after ACI, affecting approximately 72% of patients, and significantly worsens cardiovascular risk15. ACI constitutes a spectrum of neurological deficits arising from localized cerebral ischemia and hypoxia secondary to inadequate perfusion16. The intermittent hypoxia central to OSAS pathology likely synergizes with the ischemic insult of ACI, amplifying brain injury. Nevertheless, research focusing specifically on this high-risk comorbid state is scarce. Accumulating evidence indicates that miRNAs play pivotal roles in the pathogenesis of both OSAS and ACI17,18. It has been noted previously that miR-486-3p may be associated with OSAS and ACI. Therefore, we investigated miR-486-3p as a potential molecular link between OSAS and ACI. Notably, this cohort was enrolled from November 2020 to December 2023, a period covering the COVID-19 pandemic. Accumulated evidence suggests that sustained systemic inflammation triggered by SARS-CoV-2 infection may exacerbate neuronal injury and promote the progression of neurodegenerative lesions19,20. However, the current study does not focus on SARS-CoV-2/COVID-19 infection, and our research objectives and design are unrelated to COVID-19. Significantly lower serum miR-486-3p was found in ACI combined with OSAS, offering initial clinical evidence for its role in this comorbidity and highlighting the need for further study.
The NIHSS score can assess the severity of a stroke11. AHI at polysomnography is commonly used to diagnose OSAS, and the higher the AHI score, the more severe the OSAS21. Given the clinical and logistical challenges of polysomnography, identifying accessible biomarkers for obstructive sleep apnea in patients with stroke is crucial22. The current findings indicated that miR-486-3p holds significant diagnostic promise for ACI combined OSAS, as its levels correlate inversely with both AHI and NIHSS scores, reflecting disease severity.
Methodologically, this study demonstrates the feasibility of integrating molecular profiling with quantitative clinical phenotyping in a single cohort to simultaneously evaluate diagnostic accuracy, dose‑response relationships, and prognostic value. This integrated framework may serve as a reference for future biomarker discovery studies in stroke‑related comorbidities, where complex interactions between multiple pathophysiological pathways often complicate traditional single‑endpoint analyses.
IH is a hallmark of OSAS and induces inflammation and tissue damage by activating proinflammatory signaling pathways23. Critically, this inflammatory state intersects with and exacerbates the pathogenesis of ACI, in which post-ischemic inflammation mediates secondary brain injury24,25. Key inflammatory mediators like TNF-α and CRP are elevated in both conditions, positioned at the nexus of hypoxia-induced and ischemia-triggered inflammatory cascades, making them pivotal molecules in the comorbid pathology of ACI and OSA26,27,28. Therefore, the serum concentrations of TNF-α and CRP in patients with ACI combined OSAS were detected. In this study, the observed negative correlations between serum miR-486-3p levels and TNF-α and CRP levels in ACI-combined OSAS suggest a potential link between this miRNA and the systemic inflammatory state characteristic of this comorbid condition.
OSAS has a very adverse effect on quality of life, and SAQLI is an OSA-specific quality of life questionnaire29. EDS is a common symptom of OSAS, and OSAS accompanied by EDS leads to more adverse events and poorer prognosis30. ESS is commonly used to determine the severity of daytime sleepiness31. In OSAS, recurrent episodes of IH are considered an independent risk factor for vascular disease32. In addition, oxidative stress derived from IH can lead to complications such as osteoporosis, increased cardiovascular risk, and neurological changes33. Therefore, this study also examined HIF-1α expression. The finding of elevated HIF-1α in the poor prognosis group of ACI combined OSAS aligns with the pathophysiology of chronic intermittent hypoxia in OSAS. Moreover, the results showed that miR-486-3p and TNF-α were correlated with prognosis in ACI-combined OSAS, and low levels of miR-486-3p were associated with poor prognosis. This suggests a potential cascade in which IH-induced HIF-1α suppresses miR-486-3p, thereby contributing to the upregulation of inflammatory mediators such as TNF-α, thereby exacerbating brain injury in ACI.
This study still has limitations. This study is limited by the absence of control groups (healthy, OSAS-only), which precludes defining a normal range for miR-486-3p and distinguishing changes specific to comorbidity from those of OSAS alone. Therefore, future work must include these groups to fully map the expression profile of miR-486-3p. Furthermore, it is insufficient to infer the specific regulatory mechanism of miR-486-3p merely based on correlation. We will further verify its molecular mechanism in future experiments.
From a translational perspective, the high diagnostic accuracy and independent prognostic value of miR‑486‑3p suggest several potential clinical applications. As a blood‑based biomarker, it could be integrated into routine stroke workup to identify ACI patients with underlying OSAS, facilitating early referral for polysomnography and timely intervention. Monitoring miR‑486‑3p levels during acute and subacute phases may help track inflammatory dynamics and stratify patients by prognostic risk, enabling personalized rehabilitation strategies. These translational avenues warrant further investigation in prospective, multicenter studies. Overall, miR-486-3p may participate in ACI combined OSAS by regulating inflammatory factors and has diagnostic and prognostic value in ACI combined OSAS.
Disclosures
This study was funded by ‘Research on Stroke Prevention and Treatment Technologies’ (No. WKZX2023CZ0143).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 3.0T MRI Scanner | Siemens Healthineers, Germany | MAGNETOM Skyra | Brain imaging for acute cerebral infarction confirmation |
| 96-well ELISA Microplates | Shenzhen Xinbosheng Biological Co., Ltd., China | XBS-PLATE | Antigen-antibody reaction for ELISA detection |
| AASM Clinical Practice Guidelines for Sleep-Disordered Breathing | American Academy of Sleep Medicine | 2020 full guideline | Standardized AHI diagnostic and OSAS severity stratification criteria |
| Calgary Sleep Apnea Quality of Life Index (SAQLI) Chinese validated version | University of Calgary | 2021 translated edition | Quality-of-life assessment for OSAS complicated ACI patients |
| EDTA-K2 5 mL Vacuum Blood Collection Tubes | BD Biosciences, USA | 367863 | Peripheral venous blood collection for serum separation |
| Epworth Sleepiness Scale (ESS) Chinese validated version | Johns Hopkins University | 2018 revised edition | Evaluation of daytime sleepiness in stroke patients |
| GraphPad Prism 9 | GraphPad Software, USA | Version 9.4.1 | Scatter plots, boxplots, ROC curve visualization |
| Human CRP ELISA Kit | Shenzhen Xinbosheng Biological Co., Ltd., Shenzhen, China | XBS-H001 | Quantitative detection of serum C-reactive protein |
| Human HIF-1α ELISA Kit | Shenzhen Xinbosheng Biological Co., Ltd., Shenzhen, China | XBS-H007 | Quantitative detection of serum hypoxia-inducible factor-1α |
| Human TNF-α ELISA Kit | Shenzhen Xinbosheng Biological Co., Ltd., Shenzhen, China | XBS-H003 | Quantitative detection of serum TNF-α inflammatory factor |
| IBM SPSS Statistics 23.0 | IBM, Armonk, NY, USA | Version 23.0 | All statistical analyses (t-test, correlation, ROC, Kaplan–Meier, Cox regression) |
| Microplate Spectrophotometer | Thermo Fisher Scientific (Waltham, MA, USA) | Multiskan FC | Absorbance reading for ELISA plates at 450 nm |
| miR-486-3p & U6 qPCR Primers | Sangon Biotech, Shanghai, China | Custom synthesis | Target and reference gene amplification for qPCR |
| miScript SYBR Green PCR Kit | Qiagen GmbH, Hilden, Germany | 218073 | Real-time quantitative PCR amplification of miR-486-3p and U6 |
| NIH Stroke Scale (NIHSS) Chinese Validated Version | National Institute of Neurological Disorders and Stroke (NINDS), USA | Standard clinical edition | Baseline neurological severity assessment for ACI patients |
| PSG Sleep Scoring Software | BMC Medical Co., Ltd., China | v3.2 | Automated preliminary scoring of sleep respiratory events |
| QuantStudio 6 Pro Real-Time PCR System | Applied Biosystems, Thermo Fisher Scientific (Waltham, MA, USA) | QuantStudio 6 Pro | RT-qPCR amplification, melting curve acquisition, Ct value recording |
| QuantStudio Real-Time PCR Software | Applied Biosystems, USA | v1.7 | qPCR raw data export, Ct value analysis |
| Refrigerated Bench Centrifuge | Xiangyi Centrifuge Instrument Co., Ltd., Hunan, China | TDZ5-WS | Serum separation from whole blood (2700 × g, 4 °C) |
| RevertAid RT Reverse Transcription Kit | Thermo Fisher Scientific, Waltham, MA, USA | K1691 | Reverse transcription of serum miRNA into cDNA |
| RNase-free 1.5 mL Microcentrifuge Tubes | Axygen, USA | MCT-150-C | Aliquoting and storage of separated serum |
| TRIzol RNA Isolation Reagent | Invitrogen, Thermo Fisher Scientific, Waltham, MA, USA | 15596026 | Total RNA extraction from human serum samples |
| Ultra-low Temperature Freezer | Haier Biomedical, Shandong, China | DW-86L388 | Long-term serum sample storage at −80 °C |
| YH-600B Polysomnography Monitor | BMC Medical Co., Ltd., Beijing, China | YH-600B | Overnight sleep monitoring and AHI calculation for OSAS diagnosis |
References
- Lv R, et al. Pathophysiological mechanisms and therapeutic approaches in obstructive sleep apnea syndrome. Signal Transduct Target Ther. 2023;8(1):218.
- Gleeson M, McNicholas WT. Bidirectional relationships of comorbidity with obstructive sleep apnoea. Eur Respir Rev. 2022;31(164):210256.
- Seiler A, et al. Prevalence of sleep-disordered breathing after stroke and TIA: a meta-analysis. Neurology. 2019;92(7):e648-e654.
- Zhou Y, et al. Correlation between obstructive sleep apnea and hypoperfusion in patients with acute cerebral infarction. Front Neurol. 2024;15:1363053.
- Du W, Fan L, Du J. Neuroinflammation-associated miR-106a-5p serves as a biomarker for the diagnosis and prognosis of acute cerebral infarction. BMC Neurol. 2023;23(1):248.
- Tang Y, et al. Analysis of carotid vulnerable plaque MRI high-risk features and clinical risk factors associated with concomitant acute cerebral infarction. BMC Cardiovasc Disord. 2023;23(1):173.
- Santamaria-Martos F, et al. Circulating microRNA profile as a potential biomarker for obstructive sleep apnea diagnosis. Sci Rep. 2019;9(1):13456.
- Sheng B, et al. Exosome-mediated delivery of miR-486-3p alleviates neuroinflammation via. SIRT2-mediated inhibition of mitophagy after subarachnoid hemorrhage. Stroke Vasc Neurol. 2025;10(3):335-346.
- May AM, Mehra R. Obstructive sleep apnea: role of intermittent hypoxia and inflammation. Semin Respir Crit Care Med. 2014;35(5):531-544.
- Verjans R, et al. Functional screening identifies microRNAs as multicellular regulators of heart failure. Sci Rep. 2019;9(1):6055.
- Kwah LK, Diong J. National Institutes of Health Stroke Scale (NIHSS). J Physiother. 2014;60(1):61.
- Tanellari O, et al. Study on quality of life of patients with obstructive sleep apnea: pilot study. Medicina (Kaunas). 2025;61(7):1234.
- Hajikarim-Hamedani A, Rassa S, Tarjoman T, Shafiei M. Assessment of sleep patterns in migraine sufferers using the Epworth Sleepiness Scale. J Headache Pain. 2025;26(1):58.
- Liu X, et al. The relationship between inflammation and neurocognitive dysfunction in obstructive sleep apnea syndrome. J Neuroinflammation. 2020;17(1):229.
- Dharmakulaseelan L, Boulos MI. Sleep apnea and stroke: a narrative review. Chest. 2024;166(4):857-866.
- Song XD, Li SX, Zhu M. Plasma miR-409-3p promotes acute cerebral infarction via. suppressing CTRP3. Kaohsiung J Med Sci. 2021;37(4):324-333.
- Wu Z, et al. Integrated analysis of competitive endogenous RNA networks in acute ischemic stroke. Front Genet. 2022;13:833545.
- Li K, Wei P, Qin Y, Wei Y. MicroRNA expression profiling and bioinformatics analysis of dysregulated microRNAs in obstructive sleep apnea patients. Medicine (Baltimore). 2017;96(34):e7917.
- Sriram S, Mehkri Y, Quintin S, Lucke-Wold B. Shared pathophysiology: understanding stroke and Alzheimer's disease. Clin Neurol Neurosurg. 2022;218:107306.
- Small C, Mehkri Y, Panther E, Felisma P, Lucke-Wold B. Coronavirus disease 2019 and stroke: pathophysiology and management. Can J Neurol Sci. 2023;50(4):495-502.
- Tamin S, et al. Association between laryngopharyngeal reflux and obstructive sleep apnea in adults. PeerJ. 2022;10:e13303.
- Fabbri M, et al. Measuring subjective sleep quality: a review. Int J Environ Res Public Health. 2021;18(3):1082.
- Song R, Baker TL, Watters JJ, Kumar S. Obstructive sleep apnea-associated intermittent hypoxia-induced immune responses in males, pregnancies, and offspring. Int J Mol Sci. 2024;25(3):1852.
- Liu X, et al. Effects of Kudiezi injection on serum inflammatory biomarkers in patients with acute cerebral infarction. Dis Markers. 2018;2018:7936736.
- Liang Z, et al. Effects of remote ischemic postconditioning on the proinflammatory neutrophils of peripheral blood in acute cerebral infarction. Aging (Albany NY). 2023;15(10):4481-4497.
- Imani MM, et al. Serum and plasma tumor necrosis factor alpha levels in individuals with obstructive sleep apnea syndrome: a meta-analysis and meta-regression. Life (Basel). 2020;10(6):87.
- Bian F, Kang S, Cui H, Wang F, Luan T. The clinical efficacy of compound Danshen injection on acute cerebral infarction and on the changes in the CRP, D-dimer, and IL-6 levels. Am J Transl Res. 2021;13(7):8126-8133.
- Tie YX, Fu YY, Xu Z, Peng Y. Relationship between C-reactive protein levels and obstructive sleep apnea syndrome. Genet Mol Res. 2016;15(2): DOI:10.4238/gmr.15027808.
- Dutt N, Janmeja AK, Mohapatra PR, Singh AK. Quality of life impairment in patients of obstructive sleep apnea and its relation with the severity of disease. Lung India. 2013;30(4):289-294.
- Feng X, et al. Test-retest reliability of Epworth Sleepiness Scale score in patients with untreated obstructive sleep apnea. Nat Sci Sleep. 2024;16:2299-2309.
- Lapin BR, Bena JF, Walia HK, Moul DE. The Epworth Sleepiness Scale: validation of one-dimensional factor structure in a large clinical sample. J Clin Sleep Med. 2018;14(8):1293-1301.
- Zolotoff C, et al. Obstructive sleep apnea, hypercoagulability, and the blood-brain barrier. J Clin Med. 2021;10(14):3099.
- Meliante PG, et al. Molecular pathology, oxidative stress, and biomarkers in obstructive sleep apnea. Int J Mol Sci. 2023;24(6):5478.