This protocol compares diode, thulium, and erbium lasers for intracanal disinfection in an ex vivo Enterococcus faecalis root canal model by evaluating antibacterial efficacy and external root surface temperature to identify safe and effective irradiation parameters.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
Thulium, Erbium, and Diode Lasers for Intracanal Decontamination: Anti-Enterococcus faecalis Activity and Thermal Safety Ex Vivo
60 views
⸱
September 11th, 2026
In This Article
Summary
Abstract
Laser-assisted irrigation has emerged as a promising adjunct for root canal disinfection; however, evidence directly comparing different laser systems under standardized experimental conditions remains limited. This ex vivo study compared the antibacterial efficacy and thermal safety of an 808 nm diode laser, a 1940 nm thulium laser, and a 2940 nm erbium laser for intracanal decontamination against Enterococcus faecalis. Standardized infected human root canal specimens were treated using clinically relevant irradiation parameters. Antibacterial efficacy was evaluated by colony-forming unit (CFU) reduction and bacterial growth curve analysis, while thermal safety was assessed by measuring external root surface temperature changes during laser irradiation. All three laser systems demonstrated greater antibacterial activity than saline-treated controls. The erbium laser achieved the highest mean inhibition rate (99.0%) at 30 mJ for 30 s while maintaining external root surface temperature increases below the accepted 10°C thermal safety threshold. The thulium laser produced comparable antibacterial activity but exceeded the thermal safety threshold at its highest irradiation settings. The diode laser demonstrated lower antibacterial efficacy and greater temperature increases than the thulium and erbium lasers under the tested conditions. Within the limitations of this ex vivo model, the 2940 nm erbium laser demonstrated the most favorable balance between antibacterial efficacy and thermal safety and represents a promising adjunctive approach for intracanal disinfection.
Introduction
The main cause of pulpitis and apical periodontitis is bacterial infection of the root canal system1. According to one study, Enterococcus faecalis has been identified as the leading bacterial isolate in patients with chronic or recurrent infection following endodontic treatment2,3. This bacterium possesses numerous virulence factors, including biofilm formation; it can penetrate the dentinal tubules to depths of up to 800 µm and survive under nutrient-limited conditions2,3. These properties contribute to its resistance to standard intracanal disinfectants used during root canal therapy, as well as to the body’s natural defense mechanisms. Therefore, the inability to eliminate all remaining E. faecalis from the root canal system is a significant cause of endodontic treatment failure4.
Current root canal treatment combines mechanical debridement through instrumentation with chemical irrigation to help eliminate microorganisms from the root canal system5. Although mechanical instrumentation is highly effective at reducing bacterial populations, many areas within the complex root canal anatomy remain inaccessible to instrumentation alone5. Therefore, chemical irrigants play an important role in disinfecting the root canal system. Studies have shown, however, that even the most potent chemical agents fail to completely eliminate bacterial biofilms6. Furthermore, some chemical agents used during endodontic treatment may compromise the structural integrity of dentin6,7. To improve disinfection efficacy and achieve more complete removal of bacterial biofilms from the root canal system, several methods of activating chemical irrigants have been explored. Among these, laser-activated irrigation has emerged as one of the more promising alternatives8. Diode, thulium, and erbium lasers have also been evaluated for their potential to produce photothermal and photomechanical effects capable of disrupting bacterial cell walls and biofilms9.
The interaction between each of these laser types and the tissues with which they interact varies significantly according to wavelength. Diode lasers, which typically emit light at wavelengths ranging from 808 to 980 nm, are absorbed by chromophores in biological tissues, resulting in a photothermal reaction in which proteins are denatured and bacteria are killed10. Thulium lasers operate at 1940 nm and exhibit high absorption by water. Therefore, thulium lasers have been shown to be well suited for wet environments, including root canals filled with irrigating solution11. Due to their high water absorption, thulium lasers can rapidly heat and vaporize fluid when used in irrigated root canals. Vaporization generates shock waves that may help disrupt bacterial biofilms. Erbium lasers, particularly those operating at 2940 nm, have the highest absorption coefficient for water among dental lasers12. In irrigated canals, this property can generate explosive vaporization and shock waves that mechanically detach and kill bacteria while potentially limiting heat transfer to the surrounding dentin13.
Although interest in laser technology for endodontic practice continues to increase, much remains unknown regarding the optimal clinical parameters for different laser systems. Current methods for clinical use are typically based on empirical experience or manufacturer-recommended guidelines, with limited evidence-based support14. In addition, most studies to date have evaluated the antimicrobial effects of lasers; however, an important aspect of laser therapy has received comparatively less attention: the risk of thermal injury to the periodontal tissues. It is generally accepted that an increase in external root surface temperature of more than 10°C may result in permanent damage to the periodontal ligament and surrounding bone15. There appears to be no published head-to-head comparison of different laser systems that systematically evaluates both their antimicrobial efficacy and thermal safety under controlled experimental conditions.
The primary purpose of this ex vivo study was to investigate and compare the antimicrobial efficacy and thermal safety of three laser systems—an 808 nm diode laser, a 1940 nm thulium laser, and a 2940 nm erbium laser—for eliminating E. faecalis biofilm from root canal walls. To identify parameter combinations that achieve effective bacterial elimination while maintaining thermal safety, this study evaluated clinically relevant irradiation parameters. It is anticipated that these findings will help clinicians select safe and effective laser-assisted approaches for endodontic disinfection.
Access restricted. Please log in or start a trial to view this content.
Protocol
This study was conducted in accordance with the ethical standards of Shanghai Fourth People’s Hospital, School of Medicine, Tongji University, and was approved by the Institutional Review Board (Approval No. 2026013-001). The extracted human teeth used in this study were collected from patients who underwent tooth extraction for orthodontic or periodontal reasons. Written informed consent was obtained from all participants before sample collection. No additional clinical intervention was performed for the purpose of this study. The study was conducted in accordance with institutional requirements for the use of extracted human teeth.
Specimen Preparation and Selection Criteria
A total of 141 single-rooted permanent teeth (mandibular incisors and premolars) that had been recently extracted were received from the Stomatology Dept., affiliated with Tongji University at Shanghai Fourth People’s Hospital. All teeth were removed due to orthodontic or periodontal reasons. Informed consent was obtained from each patient. Included in this study were teeth with roots of at least ten millimeters as determined by a periodontal probe, intact teeth with no carious lesions or cracks, complete root formation, and root curvature of less than ten degrees according to Schneider's method. Excluded from this study were teeth with multiple canals, canal calcification, internal resorption, or previous endodontic treatment. Following extraction, all visible calculus and soft tissue remnants were removed using a periodontal scaler. The teeth were then stored in 0.9% saline solution at 4°C until use to prevent dehydration, and all experiments were conducted within three months of extraction. The specimens were assigned to the experimental groups using a predefined alternating allocation sequence. Specifically, specimens were sequentially allocated to each group in an alternating manner until the required sample size for each group was reached. No formal a priori power calculation was performed. The sample size was selected based on previous comparable ex vivo studies, the number of irradiation parameter combinations evaluated, and the availability of eligible extracted teeth.
Root Canal Preparation and Sterilization
Each tooth crown was removed at the cementoenamel junction using a low-speed diamond saw under continuous water cooling to obtain a standardized 10 mm root segment. The working length was determined as 1 mm short of the apical foramen using a size 10 K-file. Root canals were prepared using the ProTaper Universal nickel–titanium rotary system according to the manufacturer’s instructions, following the sequence S1, S2, F1, F2, and F3 until an apical preparation size of F3 was achieved. During instrumentation, the canals were irrigated with approximately 2 mL of 5.25% sodium hypochlorite after the use of each rotary file, resulting in a total irrigation volume of approximately 10 mL per canal. A final rinse was performed with 5 mL of 17% EDTA for 1 min, followed by 5 mL of sterile saline. The apical foramen was sealed with flowable resin composite to create a closed canal system. Prepared roots were sterilized by autoclaving at 121°C for 20 min, stored in sterile phosphate-buffered saline (PBS) at 4°C, and inoculated with bacteria within 24 h after sterilization.
Bacterial Strain and Culture Conditions
E. faecalis ATCC 29212 was used to establish the infected root canal model. The strain was cultured on brain heart infusion (BHI) agar at 37°C for 24 h under aerobic conditions. A single colony was transferred to BHI broth and incubated at 37°C for 18–24 h. The bacterial suspension was adjusted to approximately 1.5 × 10⁸ CFU/mL, equivalent to a 0.5 McFarland standard, using an optical density at 600 nm (OD600) value of 0.08–0.10.
Establishment of E. faecalis Infected Root Canal Model
To establish an infected root canal biofilm model, the external surface of each sterilized root was coated with two layers of clear nail polish to prevent bacterial penetration through the cementum. The apical region was coated after the apical foramen had been sealed with flowable resin composite, whereas the canal orifice was left uncoated to permit bacterial inoculation. Using a sterile micropipette, 10 µL of the E. faecalis suspension was transferred into each individual root canal to fill the entire length of the canal without spilling over. Inoculated samples were then individually placed in sterile 24-well culture plates, with 1.5 mL of BHI broth added to each well. Samples were cultured at 37°C under aerobic conditions for 21 days. The growth medium was removed and replaced with fresh sterile BHI broth every 2 days to provide nutrients for continued bacterial growth and to remove accumulated cellular debris. No additional inoculation with E. faecalis was performed during medium replacement. After completion of the incubation period, all viable samples were washed once with PBS to remove loosely attached planktonic bacteria before experimental testing. Two randomly selected samples were used to visualize mature biofilm formation and bacterial penetration into the dentinal tubules by scanning electron microscopy (SEM). The specimens were fixed in 2.5% glutaraldehyde at 4°C for 24 h, rinsed three times with PBS, dehydrated through a graded ethanol series (30%, 50%, 70%, 80%, 90%, and 100%), with each step lasting 10 min, then split longitudinally, air-dried, mounted on aluminum stubs, sputter-coated with gold, and examined by SEM.
Experimental Groups and Laser Irradiation Protocols
The 135 infected root samples were divided into three primary experimental groups according to the laser system used: the 808 nm Diode Laser Group, the 1940 nm Thulium Laser Group, and the 2940 nm Erbium Laser Group. There were 45 samples in each laser group, which were further subdivided according to the irradiation parameters. The diode laser was operated at average powers of 1.0, 1.5, or 2.0 W, and each power setting was applied for 10, 20, or 30 s, resulting in nine subgroups with three samples per subgroup. The thulium laser was operated at average powers of 1.5, 2.5, or 3.5 W, and each power setting was applied for 10, 20, or 30 s, also resulting in nine subgroups with three samples per subgroup. The erbium laser operated in a super-short pulse mode at a fixed frequency of 15 Hz. Pulse energies of 10, 20, or 30 mJ were applied for 10, 20, or 30 s, generating nine subgroups with three samples per subgroup. Both the 808 nm diode laser and the 1940 nm thulium laser were operated in continuous-wave mode.
In total, six additional samples were included, with three samples each assigned to the negative and positive control groups. The negative control group was treated with sterile saline, whereas the positive control group was treated with 5.25% sodium hypochlorite (NaOCl) for 30 s.
For the laser groups, a standardized irradiation protocol was followed. The optical fiber was introduced into the root canal to the working length and moved in a slow, continuous spiral motion from the apical to the coronal direction throughout the irradiation period. Laser-specific delivery fibers or tips were used rather than a single interchangeable fiber. The 808 nm diode laser was delivered through a 200 µm end-firing fiber, the 1940 nm thulium laser through a 200 µm end-firing fiber, and the 2940 nm erbium laser through a 400 µm radial-firing tip. The delivery fiber or tip was withdrawn at an approximate rate of 1 mm/s. After reaching the canal orifice, it was returned to the working length, and the apical-to-coronal spiral movement was repeated until the assigned irradiation duration was completed.
For the thulium and erbium lasers, the canals were kept filled with sterile saline during irradiation to simulate water-assisted laser activation. Approximately 10 µL of sterile saline was introduced into each canal to fill the canal to the level of the canal orifice before irradiation. The saline was replenished before each irradiation cycle, when necessary, to maintain a fluid-filled canal throughout treatment. For the diode laser group, the canals were dried with sterile paper points before irradiation because the 808 nm diode laser has relatively low absorption in water and was used to produce a direct photothermal antibacterial effect within the canal. By contrast, the 1940 nm thulium and 2940 nm erbium lasers have substantially greater water absorption and were therefore applied in saline-filled canals to facilitate water-mediated photothermal and photomechanical effects. The laser treatment was repeated once daily for three consecutive days.
Measurement of External Root Surface Temperature
Real-time temperature changes on the external root surface were measured during the first day of laser irradiation. Each root specimen was fixed vertically on a retort stand at room temperature (22°C ± 1°C). A K-type thermocouple connected to a digital thermometer was placed in firm contact with the mid-third of the external root surface, perpendicular to the long axis of the root. The thermocouple probe was positioned using an adjustable clamp and secured to the root surface with heat-resistant adhesive tape to maintain firm and consistent contact throughout the measurement. The thermocouple probe was calibrated before each measurement session using boiling water (100°C) and an ice–water mixture (0°C). Temperature readings were recorded at 50 ms intervals throughout the irradiation period (10, 20, or 30 s). Both the baseline temperature and the maximum temperature recorded during or immediately after laser irradiation were measured for each specimen. The temperature increase from baseline to peak temperature was calculated as ΔT. A ΔT exceeding 10°C was considered the threshold for potential damage to the periodontal tissues.
Microbiological Evaluation: Colony Counting and Inhibition Rate
To determine the antibacterial effect of the laser treatments, samples were collected after each laser treatment. The canal was dried with sterile paper points. A new sterile size 40 Hedström file was used for each specimen to obtain dentin chips from the canal walls, thereby preventing cross-contamination between samples. Each dentin chip was transferred into a separate microcentrifuge tube containing 1 mL of sterile PBS. The tubes were vortexed vigorously for 30 s to release bacteria from the dentin chips. Serial 10-fold dilutions ranging from 10−1 to 10−6 were prepared by transferring 100 µL of the bacterial suspension into 900 µL of sterile PBS at each dilution step. Aliquots (30 µL) of each dilution were spread onto separate brain heart infusion agar plates, which were incubated at 37°C for 24 h. Colonies were counted and recorded as colony-forming units (CFU). Each dilution was plated in triplicate, and the mean colony count from the three plates was used for analysis. The plates were coded before counting, and the investigator performing the colony counts was blinded to the treatment assignments.
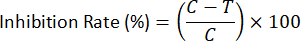
Here, C is the mean CFU count of the negative control (saline) group and T is the mean CFU count of the experimental group.
Bacterial Growth Curve Analysis
The effect of various laser treatments on bacterial growth kinetics was investigated by plotting growth curves. On Day 3 after the final laser treatment, the canals were washed with 5 mL of sterile saline solution. The canal contents were collected using sterile paper points, which were then transferred into a centrifuge tube containing 5 mL of BHI broth. The tube was vortexed to suspend the bacteria in the broth. The bacterial suspension was adjusted to 1 × 10⁶ CFU/mL. The bacterial concentration was adjusted based on OD600 measurements using a previously established calibration curve for E. faecalis ATCC 29212 and was subsequently verified by viable colony counting. An aliquot of 200 µL of the suspension was added to each well of a sterile 96-well microplate. In addition, 20 µL of sterile mineral oil was added to each well to minimize evaporation. The microplate was placed in a spectrophotometer/incubator maintained at 37°C, and OD600 was measured every hour for 24 h. Before each OD600 measurement, the microplate was subjected to orbital shaking at approximately 300 rpm for 10 s to ensure a homogeneous bacterial suspension. Each sample was tested in five replicate wells.
Statistical Analysis
All numerical data are presented as the mean ± standard deviation (SD). Statistical analyses were performed using SPSS Version 26.0. Data distribution was evaluated using the Shapiro–Wilk test. Analysis of variance (ANOVA) was used to compare more than two groups, followed by Tukey's honestly significant difference (HSD) test for pairwise comparisons. Comparisons between two groups were performed using an independent-samples t-test. Homogeneity of variance was assessed using Levene’s test before applying parametric tests. When the assumption of homogeneity of variance was violated, Welch’s correction was applied, as appropriate. Statistical significance was defined as P < 0.05. Graphs were generated using GraphPad Prism Version 9.0.
Access restricted. Please log in or start a trial to view this content.
Results
Antibacterial Activity of Different Laser Treatments Against E. faecalis
The antibacterial effectiveness of the three laser systems against E. faecalis was evaluated by determining CFU counts after three consecutive treatments. The results are shown in Figure 1 and Supplementary Figure 1. The sterile saline negative control group demonstrated substantial bacterial growth, with a mean colony count gray value of 396618.7 ± 67787.5. The 5....
Access restricted. Please log in or start a trial to view this content.
Discussion
The present ex vivo study compared the antibacterial efficacy and thermal safety of 808 nm diode, 1940 nm thulium, and 2940 nm erbium lasers for eliminating E. faecalis biofilms from infected root canals. All three laser systems demonstrated greater bacterial inhibition than 5.25% NaOCl; however, their antibacterial efficacy and thermal profiles differed substantially. The 2940 nm erbium laser achieved the most favorable overall balance, combining the highest antibacterial activity with the smallest increase in ...
Access restricted. Please log in or start a trial to view this content.
Disclosures
Conflict of Interest:
The authors declare that they have no competing interests related to this study. No financial or non-financial conflicts of interest exist, including employment, consultancies, stock ownership, honoraria, or paid expert testimony.
Acknowledgements
This study was supported by the Medical Research Program of the Hongkou District Health Commission.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 0.9% saline solution | Beyotime | ST341-500ml | Tooth storage, irrigation, and negative control |
| 1.5 mL microcentrifuge tube | Axygen | MCT-150-C | Sample collection and serial dilution |
| 24-well culture plate | Corning | 3524 | Biofilm incubation |
| 96-well microplate | Corning | 3599 | Bacterial growth curve assay |
| Autoclave | Tuttnauer | 2540E | Sterilization of prepared roots |
| Brain heart infusion (BHI) agar | BD Biosciences | 211065 | Bacterial culture and CFU enumeration |
| Brain heart infusion (BHI) broth | BD Biosciences | 237500 | Bacterial culture and growth curve analysis |
| Clear nail polish | Beyotime | C0187 | Sealing the external root surface |
| Diamond saw (low-speed) | Buehler | IsoMet Low Speed Saw | Crown sectioning |
| Digital thermometer (K-type thermocouple compatible) | OMEGA Engineering | HH802U | External root surface temperature measurement |
| Enterococcus faecalis ATCC 29212 | American Type Culture Collection (ATCC) | ATCC 29212 | Bacterial strain |
| Ethylenediaminetetraacetic acid (EDTA), 17% | Sigma-Aldrich | E9884 | Final canal rinse |
| Flowable resin composite | 3M ESPE | 6031A2 | Sealing the apical foramen |
| GraphPad Prism | GraphPad Software | Version 9.0 • RRID: SCR_002798 | Graph generation |
| Hedström file, size 40 | Dentsply Maillefer | 80603010042 | Dentin chip collection |
| K-file, size 10 | Dentsply Maillefer | 800-0210 | Working length determination |
| Laser system, 1940 nm thulium-doped fiber | Menovex Medical Technology (Shenzhen) Co., Ltd. (Arpadent) | TN20 | Laser irradiation |
| Laser system, 2940 nm Er:YAG | PointNix Co., Ltd. | Modular-beam | Laser irradiation |
| Laser system, 808 nm diode | elexxion AG | Claros Nano | Laser irradiation |
| Micropipette | Eppendorf | 3123000063 | Sample inoculation |
| Mineral oil (sterile) | Sigma-Aldrich | M5904 | Prevention of evaporation during bacterial growth curve assay |
| Nickel-titanium rotary file system (F3 preparation) | Dentsply Sirona | ProTaper Gold | Root canal preparation |
| Optical fiber for 1940 nm thulium-doped fiber laser | Menovex Medical Technology (Shenzhen) Co., Ltd. (Arpadent) | 400 µm diameter | Laser irradiation |
| Optical fiber for 2940 nm Er:YAG laser | PointNix Co., Ltd. | 600 µm diameter | Laser irradiation |
| Optical fiber for 808 nm diode laser | elexxion AG | elexxion longlife 200, 200 µm (Art. No. 10063) | Laser irradiation |
| Periodontal probe | Hu-Friedy | PCPUNC156 | Root length measurement |
| Periodontal scaler | Hu-Friedy | SJ34-35 | Removal of calculus and soft tissue |
| Phosphate-buffered saline (PBS) | Gibco / Thermo Fisher Scientific | 10010023 | Washing and bacterial dilution |
| Pipette tips (10 µL, 200 µL, 1000 µL) | Axygen | T-300 / T-200-Y / T-1000-B | Liquid handling |
| Retort stand | Biosharp | BS-IT-01 | Root specimen fixation |
| Scanning electron microscope (SEM) | Hitachi High-Technologies | TM4000Plus | Biofilm imaging |
| Shaking incubator | Thermo Fisher Scientific | MaxQ 4000 | Broth culture incubation |
| Sodium hypochlorite (NaOCl), 5.25% | Sigma-Aldrich | 425044 | Canal irrigation and positive control |
| Spectrophotometer/incubator (microplate reader) | BioTek / Agilent Technologies | Epoch 2 | Optical density at 600 nm (OD600) measurements |
| SPSS | IBM | Version 26.0 • RRID: SCR_002865 | Statistical analysis |
| Sterile paper points | Dentsply Maillefer | Absorbent Paper Points, ISO 20, 0.02 taper, 28 mm | Canal drying and bacterial sampling |
| Thermocouple probe (K-type) | OMEGA Engineering | 88000 | Temperature measurement |
| Vortex mixer | Scientific Industries | Vortex-Genie 2 | Mixing bacterial suspensions |
References
- Stuart CH, Schwartz SA, Beeson TJ, Owatz CB. Enterococcus faecalis: its role in root canal treatment failure and current concepts in retreatment. J Endod. 2006;32(2):93-98.
- Love RM. Enterococcus faecalis: a mechanism for its role in endodontic failure. Int Endod J. 2001;34(5):399-405.
- Sedgley CM, Lennan SL, Appelbe OK. Survival of Enterococcus faecalis in root canals ex vivo. Int Endod J. 2005;38(10):735-742.
- Siqueira JF Jr, Rôças IN. Clinical implications and microbiology of bacterial persistence after treatment procedures. J Endod. 2008;34(11):1291-1301.
- Peters OA. Current challenges and concepts in the preparation of root canal systems: a review. J Endod. 2004;30(8):559-567.
- Zehnder M. Root canal irrigants. J Endod. 2006;32(5):389-398.
- Marending M, et al. Effect of sodium hypochlorite on human root dentine: mechanical, chemical and structural evaluation. Int Endod J. 2007;40(10):786-793.
- de Groot SD, et al. Laser-activated irrigation within root canals: cleaning efficacy and flow visualization. Lasers Med Sci. 2009;24(6):1017-1024.
- Schoop U, et al. Innovative wavelengths in endodontic therapy: a comparative study of Er:YAG and diode laser for bacterial reduction. Lasers Surg Med. 2006;38(5):432-437.
- Gutknecht N, et al. Bactericidal effect of a 980-nm diode laser in the root canal wall dentin of bovine teeth. J Clin Laser Med Surg. 2004;22(1):9-13.
- Hin R, Klinke T, Gutknecht N. Antibacterial effect of a 1940-nm thulium laser in root canal treatment. Lasers Med Sci. 2018;33(5):1051-1056.
- Hibst R, Keller U. Experimental studies of the application of the Er:YAG laser on dental hard substances: I. Measurement of the ablation rate. Lasers Surg Med. 1989;9(4):338-344.
- DiVito E, Peters OA, Olivi G. Effectiveness of the erbium:YAG laser and new design radial and stripped tips in removing the smear layer. J Endod. 2012;38(6):763-766.
- Meire MA, et al. Effectiveness of different laser systems to kill Enterococcus faecalis in aqueous suspension and in an infected tooth model. Int Endod J. 2009;42(4):351-359.
- Eriksson AR, Albrektsson T. Temperature threshold levels for heat-induced bone tissue injury: a vital microscopic study in the rabbit. J Prosthet Dent. 1983;50(1):101-107.
- Stabholz A, Sahar-Helft S, Moshonov J. Lasers in endodontics. Dent Clin North Am. 2004;48(4):809-832.
- Gutknecht N, et al. Temperature evolution on human teeth root surface after diode laser irradiation. J Oral Laser Appl. 2005;5(2):75-80.
- Schoop U, et al. Bactericidal effect of different laser systems in the deep layers of dentin. Lasers Surg Med. 2004;35(2):111-116.
- Fried NM, Murray KE. High-power thulium fiber laser ablation of urinary tissues at 1.94 µm. J Endourol. 2005;19(1):25-31.
- Hmud R, et al. Cavitational effects in aqueous endodontic irrigants generated by near-infrared lasers. J Endod. 2010;36(2):275-278.
- Matsumoto H, Yoshimine Y, Akamine A. Visualization of irrigant flow and cavitation induced by Er:YAG laser within a root canal model. J Endod. 2011;37(6):839-843.
- George R, Walsh LJ. Thermal effects of Er:YAG laser on dentin: an in vitro study. J Oral Laser Appl. 2007;7(3):155-159.
- Siqueira JF Jr, et al. Bacteriologic investigation of the effects of sodium hypochlorite and chlorhexidine during the endodontic treatment of teeth with apical periodontitis. Oral Surg Oral Med Oral Pathol Oral Radiol Endod. 2007;104(1):122-130.
- Zou L, et al. Penetration of sodium hypochlorite into dentin. J Endod. 2010;36(5):793-796.
- Peters OA, et al. Disinfection of root canals with photon-induced photoacoustic streaming. J Endod. 2011;37(7):1008-1012.
- Attrill DC, et al. Thermal effects of the Er:YAG laser on a simulated dental pulp: a quantitative evaluation of the effects of a water spray. J Dent. 2004;32(1):35-40.
- Shen Y, Stojicic S, Haapasalo M. Antimicrobial efficacy of chlorhexidine against bacteria in biofilms at different stages of development. J Endod. 2011;37(5):657-661.
- Kimura Y, et al. Histopathological changes in dental pulp irradiated by Er:YAG laser: a preliminary report. J Clin Laser Med Surg. 2002;20(4):203-207.
- Olivi G, et al. Disinfection efficacy of photon-induced photoacoustic streaming on root canals infected with Enterococcus faecalis: an ex vivo study. J Am Dent Assoc. 2014;145(8):843-848.
Access restricted. Please log in or start a trial to view this content.