This bibliometric study uses CiteSpace to compare publication growth, collaboration networks, research hotspots, and emerging themes in Web of Science Core Collection-indexed English-language and China National Knowledge Infrastructure-indexed Chinese-language prehabilitation literature.
Research Article
Global and Chinese Research Trends in Preoperative Prehabilitation: A CiteSpace Bibliometric Analysis
* These authors contributed equally
In This Article
Summary
Abstract
Preoperative prehabilitation seeks to improve patients’ functional reserve before surgery and support postoperative recovery. This bibliometric study mapped publication growth, collaboration patterns, research hotspots, and emerging themes in Web of Science Core Collection-indexed English-language literature and China National Knowledge Infrastructure-indexed Chinese-language literature. Both databases were searched from January 1, 2016, through December 21, 2024, using database-specific terms for prehabilitation and related preoperative rehabilitation concepts. After eligibility screening and duplicate removal, 1,757 English-language and 490 Chinese-language records were analyzed with CiteSpace. Publication output increased over the study period; however, 2024 estimates may be affected by database indexing lag and should be interpreted with caution. English-language research emphasized surgery, outcomes, quality of life, exercise, complications, randomized trials, prostate cancer, pulmonary rehabilitation, and noncardiac surgery, whereas Chinese-language research emphasized nursing, lung cancer, reviews, perioperative care, and nutrition. The English-language author network was larger than the Chinese-language network, while institutional collaboration was denser in the English-language corpus. Prehabilitation has developed into a multidisciplinary field, but future work should strengthen multicenter collaboration, standardize intervention components and outcomes, and evaluate individualized multimodal strategies.
Introduction
More than 313 million surgical procedures are performed annually worldwide1, making postoperative recovery a major concern for patients, families, and clinicians. The term prehabilitation appeared in the British Medical Journal in 1946 in the context of pre-enlistment training2 and entered perioperative medicine in the late 1990s and early 2000s as a strategy to improve patients' condition before surgery3,4. Contemporary prehabilitation commonly combines exercise, nutritional optimization, psychological support, and other measures intended to increase physiological reserve and promote postoperative recovery5.
Surgical trauma provokes physiological and metabolic stress responses that may impair recovery. Outcomes depend not only on intraoperative and postoperative management but also on patients' preoperative functional, nutritional, and psychological status6. Postoperative complications and mortality are associated with baseline health, the quality of perioperative care, and the magnitude of surgical stress7; therefore, the preoperative period represents an opportunity for risk assessment and targeted optimization.
Although clinical reviews have evaluated the effectiveness of prehabilitation, comparative mapping of the structure, hotspots, and evolution of English- and Chinese-language research remains limited. Therefore, this study used CiteSpace to characterize publication trends, author and institutional collaboration, keyword co-occurrence, keyword clusters, and citation bursts in Web of Science Core Collection (WOSCC)-indexed English-language and China National Knowledge Infrastructure (CNKI)-indexed Chinese-language literature published from January 1, 2016, through December 21, 2024. The analysis was intended to identify differences in research emphasis and provide a reproducible overview to inform future perioperative research and practice.
Protocol
Ethics statement: Institutional ethics committee approval and informed consent were not applicable because this bibliometric study analyzed published bibliographic records and involved no human participants, identifiable personal data, animals, or biological specimens.
Data sources, search period, and eligibility
WOSCC was selected because it provides standardized cited-reference and affiliation metadata compatible with CiteSpace and broad coverage of international scholarly literature. CNKI was selected to capture Chinese-language publications that may not be represented in international citation databases. The final search was conducted on December 21, 2024, and covered publications dated from January 1, 2016, through December 21, 2024. Eligible records were articles or reviews written in English for WOSCC or Chinese for CNKI, focused on preoperative or perioperative prehabilitation in surgical patients, and contained sufficient bibliographic information for analysis. Records were excluded if they were outside the date or language limits, were not articles or reviews, addressed postoperative rehabilitation without a preoperative component, concerned nonclinical uses of prehabilitation, were clearly unrelated to the topic, lacked essential bibliographic fields, or were duplicates.
Database-specific search strategy
WOSCC was searched in the Topic field as follows: TS=(prehabilitation OR "pre-habilitation" OR "preoperative rehabilitation" OR "pre-operative rehabilitation" OR "perioperative rehabilitation" OR "preoperative exercise" OR "pre-operative exercise" OR "preoperative training" OR "pre-operative training"). Results were limited to English-language Articles and Review Articles published in 2016-2024. CNKI was searched in the Subject field using: 主题=("预康复" (prehabilitation) OR "术前预康复" (preoperative prehabilitation) OR "术前康复" (preoperative rehabilitation) OR "围术期康复" (perioperative rehabilitation) OR "预康复护理" (prehabilitation nursing) OR "术前运动" (preoperative exercise) OR "术前训练" (preoperative training)), limited to Chinese-language journal articles and reviews published in 2016–2024. MeSH and Emtree headings were not applicable because PubMed/MEDLINE and Embase were not searched. The use of WOSCC and CNKI was intended to support a parallel comparison of two database-defined corpora rather than an exhaustive systematic search of all available databases.
Record screening and duplicate removal
Search results were exported with full records and, where available, cited references. Two authors screened titles and abstracts for eligibility. Within each database, records were sorted and compared using DOI, title, first author, and publication year; exact duplicate exports were retained once. Ambiguous records were reviewed through discussion. Because WOSCC and CNKI were analyzed as separate corpora, records were not deduplicated across the two databases. The final datasets contained 1,757 WOSCC records and 490 CNKI records.
Data export and preprocessing
For WOSCC, records were exported as plain-text files containing full records and cited references. CNKI records were exported in a CiteSpace-compatible format. Author names, affiliations, keywords, publication year, and cited-reference information were checked for completeness. English- and Chinese-language records were imported into separate CiteSpace projects and analyzed independently to avoid conflating database-specific metadata and language variants.
CiteSpace configuration
CiteSpace version 6.4.R1 (64-bit) was used8. For both corpora, the time span was set to 2016-2024 with 1-year slices. Node selection used the g-index with k = 25, as shown in the software output; the other displayed settings were: link-retaining factor (LRF) = 2.5, maximum links per node (L/N) = 10, look-back years (LBY) = 5, and e = 1.0. The g-index retains influential nodes within each annual slice, and k controls the number of nodes retained: larger k values generate denser networks, whereas smaller values produce more selective maps. The same settings were used across corresponding analyses to facilitate comparison.
Network and keyword analyses
Separate node types were selected for author, institution, and keyword analyses. In network maps, node size represents occurrence or publication frequency; links represent coauthorship, interinstitutional cooperation, or keyword co-occurrence, depending on the analysis; and betweenness centrality reflects the extent to which a node connects otherwise separate parts of a network rather than simple productivity9. Network density is calculated as the observed number of links divided by the maximum possible number of links. Keyword clusters were evaluated with modularity Q and mean silhouette S; Q > 0.3 indicates a meaningful community structure, while S > 0.5 indicates acceptable within-cluster consistency and S > 0.7 indicates high consistency10. Citation-burst strength quantifies the magnitude of a temporary increase in keyword use, and burst duration is the interval between the detected beginning and end of that increase.
Descriptive analysis and interpretation
Annual publication counts and keyword frequencies were summarized descriptively in a spreadsheet. The author networks contained N = 431 nodes and E = 691 links for WOSCC (density = 0.0075) and N = 236 nodes and E = 238 links for CNKI (density = 0.0086). The institutional networks contained N = 337 nodes and E = 926 links for WOSCC (density = 0.0164) and N = 202 nodes and E = 123 links for CNKI (density = 0.0061). These metrics were interpreted together with network size, connectivity, and fragmentation; density was not treated as a direct measure of research quality. Counts for 2024 were considered provisional because records published late in the year may not have been fully indexed by the search date.
Results
Analysis of annual publication volume (Figure 1)
By December 21, 2024, the final dataset comprised 2,247 records: 1,757 from WOSCC and 490 from CNKI. Annual publication output increased in both corpora over the study period. Growth in WOSCC-indexed English-language publications accelerated after 2018, while growth in CNKI-indexed Chinese-language publications became more pronounced after 2020. The largest observed annual counts occurred in 2024; however, these values should not be interpreted as a definitive peak because late-2024 publications may not yet have been fully indexed at the time of the search.
Author analysis
The author was selected as the node type in CiteSpace. Larger nodes indicate greater publication frequency, and links represent coauthorship. Betweenness centrality reflects a bridging position between otherwise separate parts of the network and should not be interpreted simply as a measure of collaboration strength. The WOSCC author network contained 431 nodes and 691 links (density = 0.0075), whereas the CNKI author network contained 236 nodes and 238 links (density = 0.0086). Thus, the English-language network was larger and had more collaborative links, while the Chinese-language network was smaller and visually more fragmented; its slightly higher normalized density does not support describing it as uniformly weaker. Figure 2 and Figure 3 show the respective networks.
Institutional analysis
The institution was selected as the node type. The WOSCC institutional network contained 337 nodes and 926 links (density = 0.0164), with prominent nodes including McGill University, Maastricht University, Harvard University, and the University of Toronto (Figure 4). The CNKI institutional network contained 202 nodes and 123 links (density = 0.0061) and showed substantially lower interinstitutional connectivity. Figure 5 also includes department-level and working-group names, reflecting incomplete standardization of affiliations in the source records; therefore, institutional comparisons should be interpreted cautiously.
Keyword co-occurrence analysis
The keyword was selected as the node type to construct separate co-occurrence networks. Node size represents keyword frequency, links indicate co-occurrence within the same records, and betweenness centrality reflects a keyword's bridging role between thematic areas. Generic search terms representing the field itself, including prehabilitation and pre-rehabilitation, were excluded from the ranking to improve discrimination. Table 1 presents the leading keywords separately for the WOSCC and CNKI corpora.
Keyword cluster analysis
Modularity Q describes the extent to which a network separates into distinct clusters, while mean silhouette S measures internal consistency of cluster membership. Values of Q > 0.3 generally indicate meaningful community structure; S > 0.5 indicates acceptable homogeneity, and S > 0.7 indicates high homogeneity. The WOSCC keyword network yielded 11 clusters (Q = 0.4341, S = 0.6935), indicating a meaningful structure with acceptable cluster consistency (Figure 6). The CNKI network yielded 10 clusters (Q = 0.6135, S = 0.8552), indicating clearer separation and high within-cluster consistency (Figure 7).
Keyword burst analysis
Citation-burst analysis detects keywords whose use increases sharply during a specific period. Burst strength quantifies the magnitude of the increase, whereas burst duration is the interval from the detected start year to the end year. In the WOSCC corpus, the strongest bursts were randomized controlled trial (5.58), prostate cancer (5.43), and pulmonary rehabilitation (5.07); noncardiac surgery remained active through 2024 (Figure 8). In the CNKI corpus, the strongest bursts included guideline (2.07), colorectal cancer (1.94), and nutritional support (1.87), while colorectal cancer, rehabilitation therapy, and influencing factors remained active through 2024 (Figure 9).
DATA AVAILABILITY:
The bibliographic records analyzed in this study were retrieved from WOSCC and CNKI under institutional subscription and remain subject to the licensing conditions of the respective databases; therefore, the original database exports are not redistributed publicly. The derived keyword tables, network metrics, and CiteSpace output files underlying the figures are publicly available in Figshare at https://doi.org/10.6084/m9.figshare.33394492. The complete database-specific search strategies, eligibility criteria, and analysis settings are reported in the Protocol to permit retrieval of comparable records.
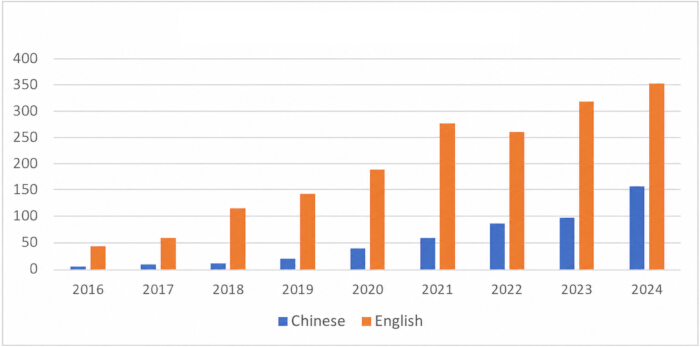
Figure 1. Publication trends in WOSCC-indexed English-language and CNKI-indexed Chinese-language prehabilitation research from 2016 to 2024. Bars show the annual number of included records in each database-defined corpus. The largest observed counts occurred in 2024, but final-year values should be interpreted cautiously because publications appearing late in the year may not have been fully indexed by the search date of December 21, 2024. Please click here to view a larger version of this figure.
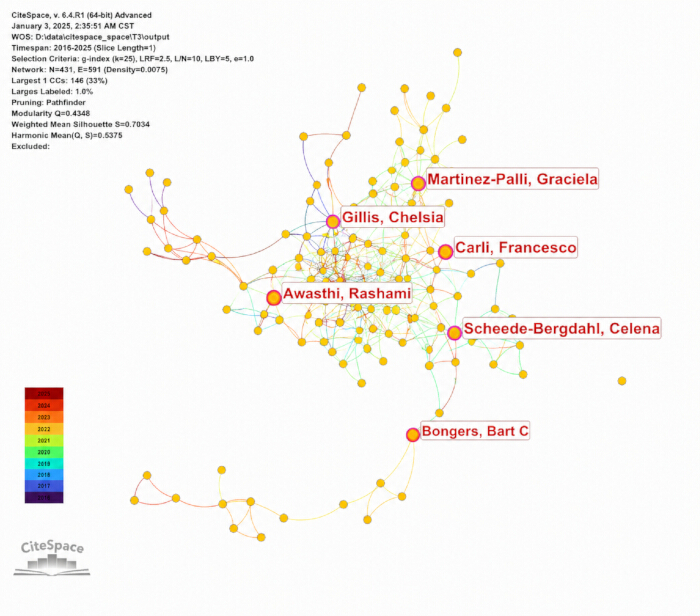
Figure 2. Author coauthorship network in WOSCC-indexed English-language literature. Node size represents publication frequency, links represent coauthorship, and nodes with high betweenness centrality occupy bridging positions. The network contained 431 nodes and 691 links (density = 0.0075); prominent authors included Martinez-Palli G, Gillis C, Carli F, Scheede-Bergdahl C, and Bongers BC. Please click here to view a larger version of this figure.
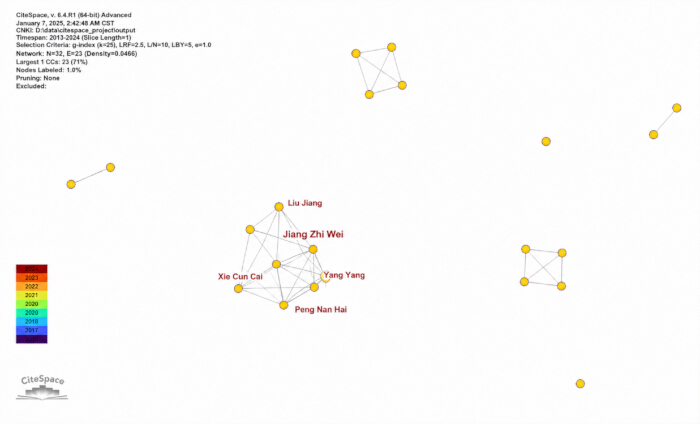
Figure 3. Author coauthorship network in CNKI-indexed Chinese-language literature. Node size represents publication frequency, and links represent coauthorship. The network contained 236 nodes and 238 links (density = 0.0086) and was characterized by several small, separated author groups; frequently appearing authors included Jiang Zhiwei, Yang Yang, and Peng Nanhai. Please click here to view a larger version of this figure.
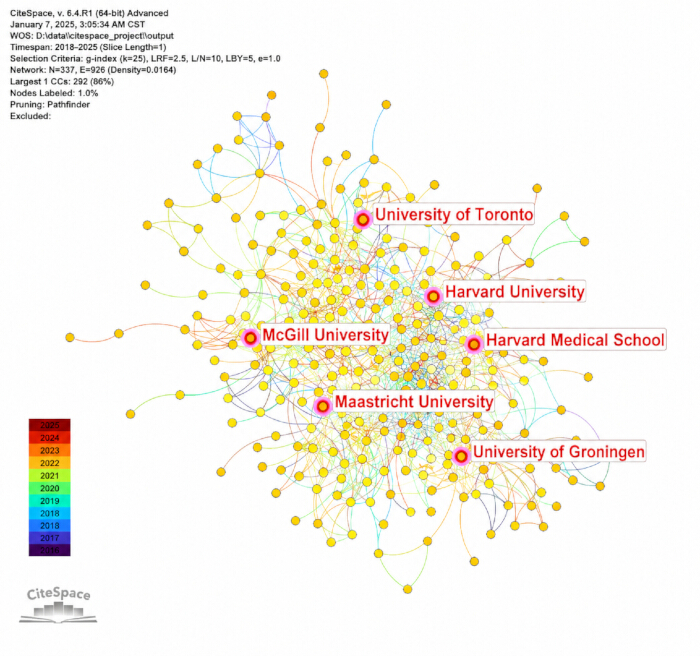
Figure 4. Institutional collaboration network in WOSCC-indexed English-language literature. Node size represents publication frequency, and links represent interinstitutional collaboration. The network contained 337 nodes and 926 links (density = 0.0164); prominent institutions included McGill University, Maastricht University, Harvard University, and the University of Toronto. Please click here to view a larger version of this figure.

Figure 5. Institutional collaboration network in CNKI-indexed Chinese-language literature. Node size represents publication frequency, and links represent collaboration among institutional entities. The network contained 202 nodes and 123 links (density=0.0061); department-level and working-group labels in the source records should be considered when interpreting institutional connectivity. Please click here to view a larger version of this figure.
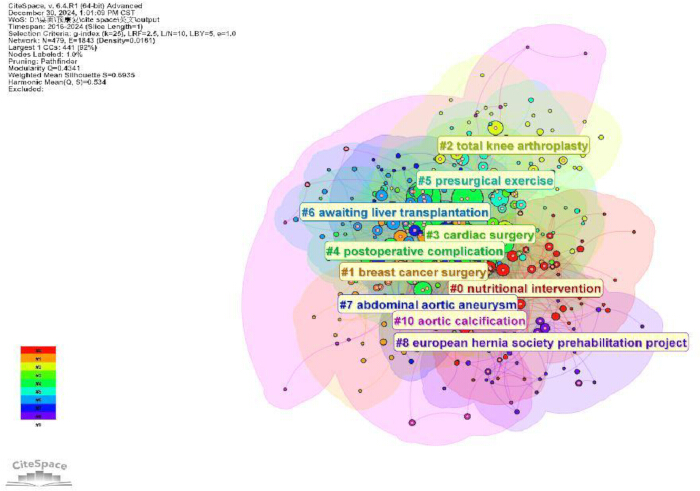
Figure 6. Keyword clustering network in WOSCC-indexed English-language literature. Colors and labels distinguish the 11 keyword clusters. Modularity Q was 0.4341, and mean silhouette S was 0.6935, indicating a meaningful cluster structure with acceptable internal consistency. Please click here to view a larger version of this figure.
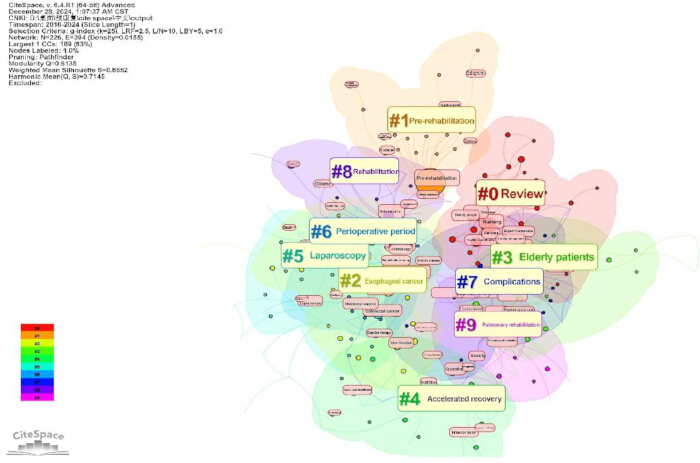
Figure 7. Keyword clustering network in CNKI-indexed Chinese-language literature. Colors and labels distinguish the 10 keyword clusters. Modularity Q was 0.6135, and mean silhouette S was 0.8552, indicating clear separation and high within-cluster consistency. Please click here to view a larger version of this figure.
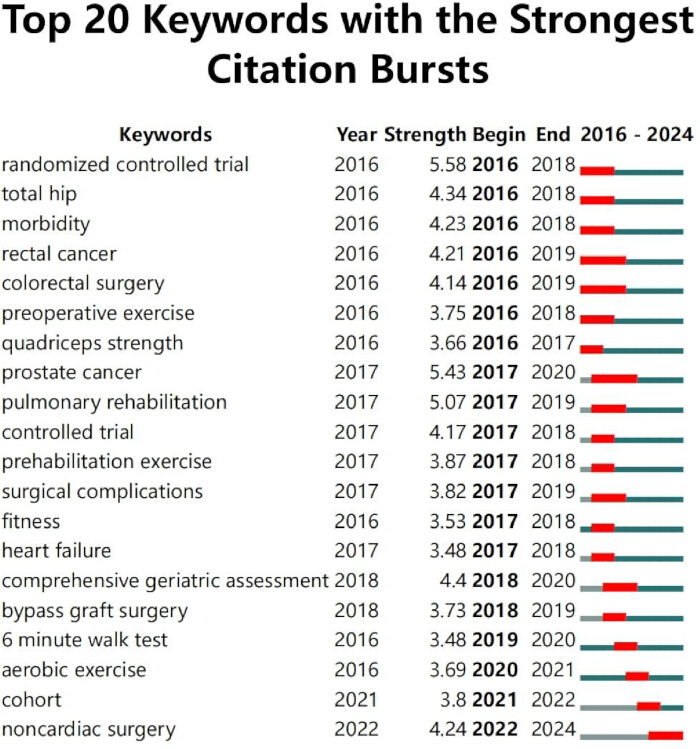
Figure 8. Keyword bursts in WOSCC-indexed English-language literature. Red bars indicate the active burst interval, and strength quantifies the magnitude of the increase in keyword use. The strongest bursts were randomized controlled trial, prostate cancer, and pulmonary rehabilitation; noncardiac surgery remained active through 2024. Please click here to view a larger version of this figure.
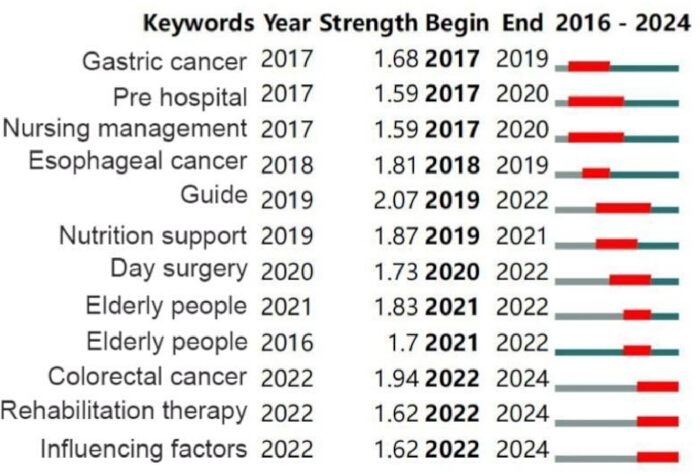
Figure 9. Keyword bursts in CNKI-indexed Chinese-language literature. Red bars indicate the active burst interval, and strength quantifies the magnitude of the increase in keyword use. The strongest bursts included guideline, colorectal cancer, and nutritional support; colorectal cancer, rehabilitation therapy, and influencing factors remained active through 2024. Please click here to view a larger version of this figure.
| WOSCC-indexed English-language keywords | ||||
| Rank | Keyword | Frequency | Betweenness centrality | First occurrence year |
| 1 | Surgery | 340 | 0.00 | 2016 |
| 2 | Outcome | 338 | 0.01 | 2016 |
| 3 | Quality of life | 297 | 0.02 | 2016 |
| 4 | Exercise | 215 | 0.01 | 2016 |
| 5 | Complications | 211 | 0.03 | 2016 |
| CNKI-indexed Chinese-language keywords | ||||
| Rank | Keyword | Frequency | Betweenness centrality | First occurrence year |
| 1 | Nursing | 42 | 0.13 | 2018 |
| 2 | Lung cancer | 33 | 0.11 | 2019 |
| 3 | Review | 29 | 0.13 | 2020 |
| 4 | Perioperative period of the Nuss procedure for pectus excavatum | 28 | 0.24 | 2017 |
| 5 | Quality of life | 25 | 0.05 | 2019 |
Table 1: High-frequency keywords in WOSCC-indexed English-language and CNKI-indexed Chinese-language literature related to prehabilitation. Five leading keywords in the WOSCC corpus, and five leading keywords in the CNKI corpus, after field-defining terms were excluded. Frequency, betweenness centrality, and first-occurrence year are reported for each keyword.
Discussion
This study provides a parallel bibliometric view of WOSCC-indexed English-language and CNKI-indexed Chinese-language prehabilitation research from 2016 to 2024. Both corpora showed sustained growth and a shift from isolated exercise-based interventions toward multimodal perioperative optimization. The contribution of this analysis lies in combining publication trends, collaboration metrics, keyword co-occurrence, cluster structure, and burst detection to distinguish shared priorities from database- and language-specific patterns. The findings complement clinical reviews that evaluate intervention effectiveness5,6,7 by showing how the research field itself has developed and where evidence-generating activity is concentrated.
The collaboration results require more nuance than a simple domestic-versus-international comparison. The WOSCC author network was larger and contained substantially more links, whereas the CNKI author network had a similar normalized density but was divided into smaller components. At the institutional level, density was clearly lower in CNKI than in WOSCC, supporting limited cross-institutional connectivity. This pattern may reflect the concentration of Chinese prehabilitation studies within individual tertiary hospitals, nursing-led implementation within local clinical pathways, uneven adoption of enhanced recovery after surgery (ERAS) programs, and incomplete normalization of department and hospital names. Future bibliometric studies should standardize affiliations prior to network construction, and future clinical programs should prioritize multicenter protocols, shared outcome sets, and prospective registries rather than relying primarily on single-center experience.
Exercise, pulmonary rehabilitation, complications, and quality of life formed a coherent clinical theme in the WOSCC corpus. These topics are mechanistically linked: improving aerobic capacity, respiratory muscle performance, and functional reserve may reduce vulnerability to postoperative pulmonary and functional decline. Personalized prehabilitation has shown potential in high-risk patients undergoing major abdominal surgery11, while disease-specific approaches have expanded to swallowing preservation in head and neck cancer12. More recent evidence published after the bibliometric search cutoff and therefore used only for interpretation rather than to populate the analyzed corpus, supports preoperative respiratory training in thoracic surgery13 and ERAS-based care in patients undergoing video-assisted thoracoscopic lobectomy14. Together, these findings support future trials that define intervention dose, duration, adherence, and objective functional outcomes rather than treating all exercise-based programs as equivalent.
Nutrition, perioperative nursing, and multimodal care were particularly prominent in the CNKI corpus. Their clinical importance extends beyond descriptive frequency. Malnutrition, frailty, and reduced physiological reserve frequently coexist in older adults and patients undergoing cancer or major abdominal surgery, making nutritional screening and correction integral to risk-stratified prehabilitation. ERAS guidance emphasizes coordinated preoperative assessment, nutrition, mobilization, and perioperative care15,16. Chinese studies have also evaluated nutritional prehabilitation during esophageal cancer treatment17 and multimodal prehabilitation during breast cancer chemotherapy18. Recent clinical reports further link early enteral nutrition with gastrointestinal and immune recovery after gastric cancer surgery19 and targeted perioperative nursing with reduced stress responses and improved recovery after colorectal cancer surgery20. These post-search publications reinforce the clinical relevance of the detected themes but were not included in the bibliometric dataset.
The next phase of prehabilitation research should move from broad proof-of-concept studies toward implementation-ready programs. Priorities include multicenter collaboration, consensus on core intervention components, patient-specific risk stratification, objective functional and patient-reported outcomes, and explicit reporting of adherence and intervention fidelity. Digital tools may support remote assessment, reminders, symptom reporting, and adaptive exercise or nutrition plans, particularly when travel to specialist centers is difficult. Evidence from adjacent perioperative digital interventions, such as telemonitored ankle-pump systems21, demonstrates the feasibility of remote monitoring, although direct evidence for digitally delivered prehabilitation remains limited. Digital strategies should therefore be evaluated prospectively for accessibility, data quality, safety, and their ability to improve adherence rather than being assumed to be effective.
This study has several limitations. WOSCC was selected for standardized citation metadata and compatibility with CiteSpace, while CNKI was selected to capture Chinese-language publications; consequently, the two corpora support a structured comparison but do not constitute an exhaustive global search. Relevant records indexed only in PubMed, Embase, Scopus, CINAHL, the Cochrane Library, or other databases may have been missed, potentially affecting publication counts, country and institutional rankings, keyword frequencies, and burst patterns. Database-specific indexing practices, language restrictions, affiliation-name variation, keyword extraction, and parameter selection may also influence the generated networks. In addition, 2024 records may be incomplete because of an indexing lag. These limitations should be considered when interpreting differences between the WOSCC and CNKI corpora.
In conclusion, preoperative prehabilitation research expanded substantially between 2016 and 2024, with shared emphasis on exercise, complications, quality of life, nutrition, nursing, and multimodal perioperative care. The data support five actionable directions: build multicenter research networks, standardize intervention components and core outcomes, stratify patients by functional and nutritional risk, use objective and patient-reported measures, and evaluate digital tools for adherence and remote monitoring. Progress in these areas is necessary to translate bibliometric growth into reproducible clinical benefit.
Disclosures
The authors have no conflicts of interest to declare.
Acknowledgements
The authors thank all colleagues who contributed to the preparation and review of this manuscript.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| China National Knowledge Infrastructure | CNKI | Bibliographic database; final access: December 21, 2024 | Source of CNKI-indexed Chinese-language records |
| CiteSpace | Chaomei Chen / CiteSpace | Version 6.4.R1, 64-bit | Bibliometric network visualization and burst analysis |
| Java runtime environment | Oracle or OpenJDK | Version not retained in the archived study files | Runtime environment required by CiteSpace |
| Web of Science Core Collection | Clarivate | Bibliographic database; final access: December 21, 2024 | Source of WOSCC-indexed English-language records |
| WPS Office | Kingsoft Office | Version not retained in the archived study files | Descriptive summaries of annual output and keyword frequency |
References
- Weiser TG, et al. Size and distribution of the global volume of surgery in 2012. Lancet. 2015;385 Suppl 2:S11.
- Prehabilitation, rehabilitation, and revocation in the army. Br Med J. 1946;1:192-7.
- Weiner P, et al. The effect of incentive spirometry and inspiratory muscle training on pulmonary function after lung resection. J Thorac Cardiovasc Surg. 1997;113(3):552-7.
- Arthur HM, et al. Effect of a preoperative intervention on preoperative and postoperative outcomes in low-risk patients awaiting elective coronary artery bypass graft surgery: a randomized controlled trial. Ann Intern Med. 2000;133(4):253-62.
- Perry R, et al. Pre-admission interventions (prehabilitation) to improve outcome after major elective surgery: a systematic review and meta-analysis. BMJ Open. 2021;11(9):e050806.
- Gillis C, Ljungqvist O, Carli F. Prehabilitation, enhanced recovery after surgery, or both? A narrative review. Br J Anaesth. 2022;128(3):434-48.
- McIsaac DI, et al. Prehabilitation in adult patients undergoing surgery: an umbrella review of systematic reviews. Br J Anaesth. 2022;128(2):244-57.
- Chen C. Searching for intellectual turning points: progressive knowledge domain visualization. Proc Natl Acad Sci U S A. 2004;101 Suppl 1:5303-10.
- Yang K, Gan L, Guo C. Visual analysis of peptic ulcer research based on CiteSpace software. J Pract Clin Med. 2021;25(5):1-6.
- Chen Y, et al. The methodology function of mapping knowledge domains: by reading 555 CiteSpace papers. Stud Sci Sci. 2015;33(2):242-53.
- Barberan-Garcia A, et al. Personalized prehabilitation in high-risk patients undergoing elective major abdominal surgery: a randomized blinded controlled trial. Ann Surg. 2018;267(1):50-6.
- Kuenzel J, et al. The effects of phoniatric prehabilitation in head and neck cancer patients on aspiration and preservation of swallowing (PREHAPS): study protocol of a monocentric prospective randomized interventional outcome-blinded trial. Trials. 2024;25(1):211.
- Zhu Y, Du Y, Zhang M. Effect of preoperative respiratory training on perioperative outcomes in thoracic surgery: a systematic review and meta-analysis. Ann Ital Chir. 2025;96(9):1135-45.
- Xu Y, et al. Clinical effects of enhanced recovery after surgery in perioperative-period patients undergoing video-assisted thoracoscopic lobectomy. Ann Ital Chir. 2024;95(4):583-92.
- Batchelor TJP, et al. Guidelines for enhanced recovery after lung surgery: recommendations of the Enhanced Recovery After Surgery Society and the European Society of Thoracic Surgeons. Eur J Cardiothorac Surg. 2019;55(1):91-115.
- Hübner M, et al. Guidelines for perioperative care in cytoreductive surgery with or without hyperthermic intraperitoneal chemotherapy: Enhanced Recovery After Surgery Society recommendations. Part I: preoperative and intraoperative management. Eur J Surg Oncol. 2020;46(12):2292-310.
- Yu J, et al. Application of nutritional prehabilitation in patients with esophageal cancer during radiotherapy and chemotherapy. Mod Med. 2021;49(2):193-8.
- Zhang J, et al. Application effect of multimodal prehabilitation during the chemotherapy interval in postoperative patients with breast cancer. Chin Nurs Res. 2024;38(12):2225-9.
- Wang Z, Peng W, Zhang J. The effect of early enteral nutrition under the ERAS model on gastrointestinal and immune function recovery in patients undergoing gastric tumor surgery. Ann Ital Chir. 2024;95(6):1147-54.
- Zeng Q, et al. The impact of perioperative comfort nursing combined with targeted operating-room nursing on postoperative stress response and nursing satisfaction in patients with colorectal cancer. Ann Ital Chir. 2025;96(8):1089-102.
- Ge Y, et al. Digital therapeutic intervention for venous thromboembolism prevention: efficacy evaluation of a telemonitored ankle-pump system in patients with tibial plateau fractures. Ann Ital Chir. 2025;96(10):1409-19.