Rifampicin markedly reduces warfarin anticoagulant effects through enzyme induction, requiring careful dose adjustment and INR monitoring. This case report describes pharmacist-guided management of a patient receiving concurrent rifampicin and warfarin therapy, highlighting practical strategies for maintaining therapeutic anticoagulation during this clinically challenging drug interaction.
Case Report
Warfarin Dose Adjustment During Rifampicin Therapy: A Case Report with Practical Monitoring Implications
In This Article
Summary
Abstract
Warfarin management is challenging because its anticoagulant effect is influenced by drug-drug interactions and individual variability. Rifampicin is a potent inducer of cytochrome P450 enzymes and can substantially reduce warfarin efficacy, making structured monitoring and individualized dose adjustment necessary.
This report aimed to describe the clinical management strategy for maintaining therapeutic anticoagulation in a patient receiving concurrent warfarin and rifampicin therapy, with a focus on International Normalized Ratio (INR) monitoring, dose adjustment, and pharmacist-led management.
We present a clinical case of a 64-year-old Chinese male with chronic thromboembolic pulmonary hypertension who required long-term warfarin therapy and subsequently received rifampicin-containing antituberculosis treatment. The patient's clinical course, INR values, warfarin dose adjustments, and safety outcomes were retrospectively reviewed. A structured pharmacist-supported monitoring approach was applied during rifampicin co-administration.
After rifampicin initiation, the patient's warfarin requirement increased from 1.5 mg/day to 4.5 mg/day, representing an approximately 200% increase. INR was monitored twice weekly during the initial phase and subsequently weekly until stabilization. A therapeutic INR range (2–3) was achieved after approximately 2 months without thromboembolic events or major bleeding complications.
Rifampicin-warfarin co-administration requires individualized management rather than fixed dose adjustment strategies. Frequent INR monitoring, timely dose modification, and pharmacist involvement may facilitate safe maintenance of anticoagulation during this clinically significant drug–drug interaction.
Introduction
Warfarin is an anticoagulant drug that belongs to the class of coumarin derivatives. It works by interfering with the conversion of vitamin K to its 2,3-epoxide form (which is the vitamin K epoxide) and thereby decreasing the production of vitamin K-dependent coagulation factors (coagulation factors II, VII, IX, and X)1. Warfarin has become one of the most frequently prescribed oral anticoagulants in clinical practice because it can be taken orally and is effective in treating thromboembolic disease (venous thromboembolism), as well as in treating patients who require heart valve replacement surgery and patients with atrial fibrillation. Due to warfarin's narrow window of therapeutic efficacy, it is also subject to many drug-food interactions, and the dose required for therapeutic effectiveness can vary greatly (up to 10-fold) among patients2. In addition, polymorphisms in cytochrome P450 2C9 (CYP2C9) and vitamin K epoxide reductase complex subunit 1 (VKORC1) are responsible for some of the differences in required warfarin dose because they affect warfarin's metabolism and sensitivity; they are at least partially responsible for some populations requiring lower baseline doses of warfarin than do other populations3. The pharmacogenetic factors mentioned previously mainly affect warfarin dosing determination at baseline rather than the qualitative effect of warfarin on the drug-drug interaction.
Rifampicin (or rifampin) is a first-line antibiotic used to treat tuberculosis (TB)4. As a strong inducer of hepatic cytochrome P450 enzymes (especially CYP3A4 and CYP2C9) and P-glycoprotein transporters, rifampicin increases the rate of elimination of many drugs taken concomitantly with rifampicin5. A common occurrence of clinically significant drug-drug interactions is that rifampicin is often used with other medications that have narrow therapeutic windows, such as warfarin. The clinical management of patients with concomitant TB and thromboembolic disease in China presents significant complexities. In usual practice, many prescribers choose to manage patients on low-molecular-weight heparin rather than an oral anticoagulant due to concerns about reduced anticoagulant exposure when concomitant rifampicin therapy is used. Although direct oral anticoagulants (DOACs), such as apixaban and rivaroxaban, are attractive alternatives to warfarin in many clinical settings, their use with rifampicin is problematic because rifampicin strongly induces both cytochrome P450 3A4 (CYP3A4) and P-glycoprotein (P-gp), which are important pathways involved in DOAC metabolism and transport. This interaction may substantially reduce DOAC plasma concentrations and potentially increase thromboembolic risk. Unlike warfarin, DOACs currently lack a routinely available monitoring parameter equivalent to the international normalized ratio (INR), making individualized dose adjustment during rifampicin co-administration challenging.
Ethnic and pharmacogenetic characteristics contribute to differences in baseline warfarin dose requirements among individuals; however, these factors should not be interpreted as evidence of population-specific differences in rifampicin-mediated enzyme induction. Therefore, this report does not aim to compare ethnic variations in the rifampicin–warfarin interaction. Instead, we present a real-world case of a patient receiving long-term warfarin therapy who developed tuberculosis requiring rifampicin-containing treatment, with the objective of describing pharmacist-supported strategies for managing this clinically significant drug–drug interaction, including INR monitoring frequency, warfarin dose adjustment, timing of enzyme induction, and transition management after rifampicin discontinuation.
Case Presentation
A 64-year-old Chinese man with chronic thromboembolic pulmonary hypertension (CTEPH) following pulmonary endarterectomy, persistent atrial fibrillation, hypertension, and long-term stable warfarin therapy was admitted with exertional dyspnea and chest tightness. His medical history included cerebellar atrophy for decades, hypertension for more than 40 years, persistent atrial fibrillation for more than 30 years, and chronic thromboembolic pulmonary hypertension (CTEPH). He was diagnosed with CTEPH in January 2020 and underwent pulmonary endarterectomy (PEA) with hypothermic cardiopulmonary bypass on June 15, 2020. Following surgery, his symptoms of chest tightness and dyspnea improved substantially. Evaluation identified newly diagnosed pulmonary tuberculosis, requiring rifampicin-containing antituberculosis therapy, while lifelong anticoagulation remained necessary because of CTEPH and atrial fibrillation. Baseline renal and hepatic function were normal, and warfarin was temporarily interrupted for planned procedures before being restarted with enoxaparin bridging.
Following initiation of rifampicin, the patient underwent intensive pharmacist-led INR monitoring with individualized warfarin dose adjustment. Despite a progressive increase in warfarin dose from 1.5 to 4.5 mg/day and transient INR fluctuations, therapeutic anticoagulation was successfully maintained without thromboembolic or bleeding events. The patient remained clinically stable throughout follow-up.
Diagnosis, Assessment, and Plan
The primary clinical challenge was managing the well-recognized interaction between rifampicin and warfarin, which substantially reduces anticoagulant activity through hepatic enzyme induction. Warfarin contains two enantiomers, with S-warfarin primarily metabolized by CYP2C9 and R-warfarin metabolized by CYP1A2 and CYP3A4. Rifampicin induces these metabolic pathways, resulting in increased warfarin clearance and reduced anticoagulant effect6,7,8. Alternative anticoagulants were considered but were not selected because rifampicin also reduces direct oral anticoagulant exposure, and warfarin allows individualized dose adjustment using INR monitoring. Although direct oral anticoagulants (DOACs), such as apixaban and rivaroxaban, are widely used alternatives to warfarin, their efficacy may be compromised during rifampicin therapy because rifampicin induces CYP3A4 and P-glycoprotein (P-gp), leading to reduced DOAC exposure and potentially impaired anticoagulant efficacy8,9. Moreover, evidence from post-PEA patients with CTEPH suggests a higher risk of recurrent VTE with DOACs than with VKAs, supporting the choice of warfarin in this case6.
The patient was assessed as requiring continued long-term anticoagulation with an acceptable bleeding risk. The management plan, therefore, emphasized continuation of warfarin with frequent INR monitoring, pharmacist-guided dose titration, and ongoing clinical surveillance to maintain therapeutic anticoagulation throughout rifampicin treatment.
Protocol
All procedures performed in this case report involving human participants were conducted in accordance with the ethical standards of the institutional and/or national research committee and with the 1964 Helsinki Declaration and its later amendments or comparable ethical standards. The institutional review board waived ethical approval because this report described routine clinical care without experimental intervention. Written informed consent for publication of this case report and any accompanying data was obtained from the patient.
1. Baseline patient assessment
- Evaluation of anticoagulation status
- Before initiating rifampicin-containing antituberculosis therapy, the patient's baseline anticoagulation status was assessed, including the stable warfarin maintenance dose, recent INR values, target INR range, thromboembolic history, and bleeding risk factors.
- A pharmacist-supported anticoagulation management strategy was subsequently implemented based on previous reports describing rifampicin-associated reductions in warfarin effect and the need for individualized dose adjustment10,11,12. The patient had maintained stable anticoagulation control for more than two years with warfarin 1.5 mg/day, with a target INR range of 2–3.
- Baseline laboratory assessments, including liver function, renal function, hemoglobin concentration, and coagulation parameters, were evaluated before treatment adjustment. The patient's INR was 1.97 at admission, and liver and kidney function tests were within normal limits.
- Clinical factors that could influence warfarin response, including concomitant medications, dietary vitamin K intake, and acute illness status, were also reviewed.
- The patient's thromboembolic and bleeding risks were assessed using validated clinical scoring systems.
NOTE: His CHA2DS2-VASc score was 2 points, and his HAS-BLED score was 1 point, supporting the continuation of long-term anticoagulation therapy.
- Evaluation of interaction risks
- The potential interaction between rifampicin and warfarin was evaluated before initiation of antituberculosis therapy. Rifampicin was recognized as a potent inducer of cytochrome P450 enzymes, particularly CYP2C9 and CYP3A4, which could increase warfarin metabolism and reduce anticoagulant efficacy.
- Alternative anticoagulation strategies were evaluated. Direct oral anticoagulants (DOACs), including apixaban and rivaroxaban, were considered less suitable because rifampicin-mediated induction of CYP3A4 and P-glycoprotein could reduce DOAC exposure. In contrast, warfarin allowed direct assessment of anticoagulant intensity through INR monitoring and individualized dose adjustment.
- Pharmacogenetic factors, including CYP2C9 and VKORC1 variants, were recognized as potential contributors to baseline warfarin dose requirements. However, they were not used to estimate the magnitude of rifampicin-mediated enzyme induction in this patient.
2. Periprocedural anticoagulation management
- Warfarin interruption
- Warfarin therapy was temporarily interrupted on April 14, 2022, because invasive procedures were planned during hospitalization. The anticoagulation status was monitored during the interruption period to minimize thromboembolic risk.
- Because the patient had persistent atrial fibrillation and a history of chronic thromboembolic pulmonary hypertension requiring long-term anticoagulation, temporary anticoagulation bridging was implemented during warfarin interruption.
- Enoxaparin bridging
- Therapeutic bridging anticoagulation was performed using enoxaparin sodium. Considering the patient's body weight of approximately 60 kg, enoxaparin was administered at 6000 IU (equivalent to 60 mg) every 12 h, corresponding to approximately 1 mg/kg twice daily.
- Following completion of the invasive procedures, warfarin therapy was restarted at 2.25 mg/day. Enoxaparin was continued concurrently as bridging therapy until INR returned to the therapeutic range.
- Enoxaparin was discontinued 24 h later after adequate anticoagulation control was achieved, and warfarin was subsequently titrated to 3 mg/day at discharge.
3. INR monitoring during rifampicin therapy
- Early induction phase
- After initiation of rifampicin-containing antituberculosis therapy (rifampicin 0.45 g/day, isoniazid 0.3 g/day, ethambutol 0.75 g/day, and pyrazinamide 0.5 g three times daily), structured INR monitoring was performed.
- During the first 2 weeks after rifampicin initiation, INR measurements were performed twice weekly because rifampicin-mediated enzyme induction was expected to progressively reduce warfarin anticoagulant effects during this period.
- The INR results were reviewed, anticoagulation status was evaluated, and dose adjustment recommendations were communicated by the clinical pharmacy team to the treating physicians.
- Dose adjustment phase
- Warfarin dose adjustments were performed according to serial INR measurements and clinical response. When INR values remained below the therapeutic range (INR <2.0), the weekly warfarin dose was increased by approximately 10–20%.
- When INR values exceeded the therapeutic range, dose reduction or temporary dose withholding was performed according to the degree of INR elevation and bleeding risk.
- After the initial 2-week monitoring period, INR assessments were performed weekly until stable anticoagulation was achieved. The patient's warfarin dose was gradually increased from 3 mg/day at discharge to 4.5 mg/day during rifampicin co-administration.
- In this patient, when INR briefly rose to 4.68 during routine monitoring, warfarin was withheld for 1 day and resumed at the same daily dose (4.5 mg) the following day after repeat INR measurement showed a decline to 3.21.
- No vitamin K supplementation was administered, and no bleeding events occurred. Conservative management was opted because the INR spike was transient, and the patient had no bleeding symptoms or high-risk factors such as advanced age, renal insufficiency, or concomitant antiplatelet use.
4. Management after rifampicin discontinuation
- After rifampicin discontinuation, continued INR surveillance was planned because the resolution of enzyme induction could increase warfarin exposure and result in excessive anticoagulation.
- Warfarin dose requirements were reassessed according to INR trends, and dose reduction was performed when necessary to maintain the target INR range of 2–3.
NOTE: Throughout the entire management period, pharmacist involvement supported INR interpretation, dose adjustment, patient education, and monitoring for anticoagulation-related complications.
Results
Anticoagulation response during rifampicin therapy
Before rifampicin initiation, the patient had maintained stable anticoagulation with warfarin at 1.5 mg/day (10.5 mg/week), with a target INR of 2.0–3.0. After rifampicin-containing antituberculosis therapy was initiated, the patient's warfarin requirement gradually increased, reflecting reduced anticoagulant exposure associated with rifampicin-mediated enzyme induction.
The maintenance warfarin dose increased to 4.5 mg/day (31.5 mg/week), representing an approximately 200% increase compared with the baseline dose before rifampicin exposure. Following pharmacist-supported INR monitoring and individualized dose adjustment, the INR gradually returned to and remained within the therapeutic range (2.0–3.0) after approximately 2 months of concomitant rifampicin therapy (Figure 1).
Figure 1 demonstrates the temporal relationship between rifampicin initiation, warfarin dose escalation, and INR changes during follow-up. The observed pattern was consistent with the expected delayed onset of rifampicin-induced enzyme induction and the gradual stabilization of anticoagulant response.
INR variability and safety outcomes
During the follow-up period, INR values showed temporary fluctuations after rifampicin initiation. The lowest recorded INR was 1.42, whereas the highest INR reached 4.68. These fluctuations were managed through individualized warfarin dose adjustments according to serial INR measurements.
Despite INR variability during the interaction period, no thromboembolic events or major bleeding complications occurred. Safety assessments, including serial hemoglobin measurements, fecal occult blood testing, and clinical evaluation according to the World Health Organization (WHO) bleeding scale, did not identify clinically significant adverse events.
The patient remained clinically stable during continued rifampicin therapy and maintained therapeutic anticoagulation with a final warfarin maintenance dose of 4.5 mg/day under pharmacist-supported follow-up.
Validation of the management protocol
Our experience suggests that this monitoring protocol is feasible in clinical practice. The gradual increase in warfarin requirements following rifampicin initiation and subsequent stabilization of INR values reflected the expected pharmacokinetic characteristics of rifampicin-mediated enzyme induction.
The successful maintenance of therapeutic anticoagulation despite a clinically significant drug-drug interaction demonstrated that structured INR surveillance, individualized warfarin titration, and pharmacist involvement provided a feasible approach for managing patients requiring concurrent rifampicin and warfarin therapy.
Furthermore, the absence of thromboembolic and major bleeding events during follow-up suggested that the protocol was effective in balancing anticoagulation efficacy and safety in this complex clinical setting.
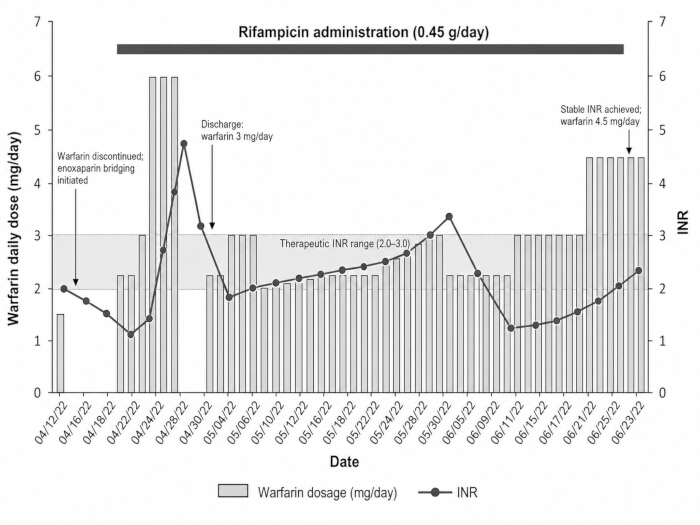
Figure 1: Timeline of rifampicin-associated changes in warfarin dose and INR during follow-up. The figure shows serial changes in daily warfarin dose (solid line, left y-axis, mg/day) and INR values (dashed line with circles, right y-axis) from admission to 3 months of follow-up. The gray shaded area indicates the target INR range (2.0–3.0). Key events are marked: (A) rifampicin initiation; (B) pyrazinamide discontinuation due to hepatotoxicity (day 19); (C) peak INR of 4.68; (D) INR stabilization within the target range on maintenance warfarin 4.5 mg/day. Warfarin dose was escalated from 3 mg/day at discharge to 4.5 mg/day during rifampicin co-administration, representing a 200% increase from the pre-admission maintenance dose of 1.5 mg/day. Please click here to view a larger version of this figure.
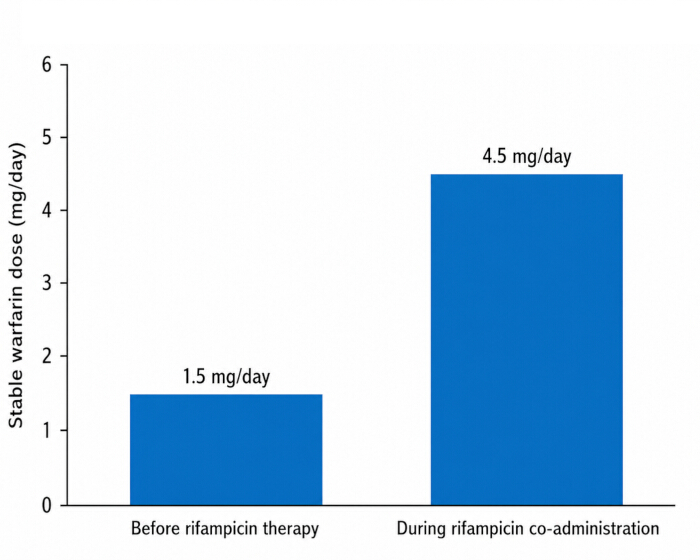
Figure 2: Comparison of stable warfarin dose before and during rifampicin therapy. The x-axis represents treatment phases (before rifampicin therapy and during rifampicin co-administration), and the y-axis represents the stable daily warfarin dose (mg/day). The figure demonstrates the increase in maintenance warfarin dose from 1.5 mg/day before rifampicin initiation to 4.5 mg/day during rifampicin co-administration. Please click here to view a larger version of this figure.
| Case | Reference | Country | Number of patients | Sex | Age | Warfarin dose before rifampicin (mg·week⁻¹) | Stable warfarin dose during rifampicin co-administration (mg·week⁻¹) | Time required for INR to reach therapeutic range during rifampicin co-administration | Stable warfarin dose after discontinuation of rifampicin (mg·week⁻¹) | Time required for INR to reach therapeutic range after stopping rifampicin |
| Case 1 | Hu et al., 2021 (Ref 10) | China | 1 | M | 64 | 10.5 | 31.5 | Approximately 2 months | NR | NR |
| Case 2 | Fahmi et al., 2016 (Ref 11) | Qatar | 1 | M | 55 | 35 | 140 | Approximately 4 weeks | 35 | Approximately 4 weeks |
| Case 3 | Salem et al., 2021 (Ref 12) | Qatar | 1 | M | 56 | 35 | 105 | Approximately 6 weeks | NR | NR |
| Case 4 | Self et al., 1975 (Ref 14) | USA | 1 | M | NR | NR | Increased requirement (dose increased) | NR | NR | NR |
| Case 5 | Krajewski, 2010 (Ref 15) | USA | 1 | M | NR | NR | Unable to achieve therapeutic INR despite dose escalation | NR | NR | NR |
| Case 6 | Martins et al., 2013 (Ref 16) | Brazil | 1 | M | 70 | 35 | 70 | Approximately 4 weeks | 35 | NR |
| Case 7 | Maina et al., 2013 (Ref 17) | Kenya | 8 | Mixed | NR | Variable | Increased by approximately 50%–200% | Variable | Variable | Variable |
| Case 8 | Dawson et al., 2016 (Ref 18) | Australia | 1 | M | 57 | 45 | 150 | Approximately 5 weeks | 45 | Approximately 2 months |
| Case 9 | Meng et al., 2015 (Ref 19) | China | 1 | M | 62 | 21 | 63 | Approximately 2 months | NR | NR |
| Case 10 | Yang et al., 2021 (Ref 20) | Canada | 10 | Mixed | NR | Variable | Increased by 50%–600% | Variable | Variable | Variable |
| Case 11 | Current case | China | 1 | M | 64 | 10.5 | 31.5 | Approximately 2 months | 31.5 | Ongoing monitoring |
Table 1: Time required to regain therapeutic INR after rifampicin discontinuation reported previously and in this study.
| Clinical phase | Recommended monitoring and management |
| Before rifampicin initiation | Review stable warfarin dose, recent INR values, concomitant medications, bleeding/thrombotic risks, and potential pharmacogenetic factors (e.g., CYP2C9 and VKORC1 variants when available). |
| First 1–2 weeks after rifampicin initiation | Monitor INR approximately twice weekly because rifampicin-induced enzyme induction usually develops during this period. If INR falls below the therapeutic range (INR < 2.0), consider individualized warfarin dose escalation, generally by approximately 10–20% of the weekly dose. |
| INR stabilization phase | Once INR approaches or reaches the therapeutic range (target INR 2–3), gradually reduce monitoring frequency to weekly intervals until stable anticoagulation is maintained. |
| After rifampicin discontinuation | Continue frequent INR monitoring for at least 2 weeks because enzyme induction gradually resolves. Prompt downward adjustment of warfarin dose may be required to avoid excessive anticoagulation. |
| Throughout treatment | Pharmacist involvement is recommended to support INR interpretation, dose adjustment, patient education, and prevention of anticoagulation-related complications. |
Table 2: Clinical practice summary on the practical management of warfarin during co-administration with rifampicin.
Discussion
Rifampicin-warfarin interaction represents a clinically important challenge because rifampicin can substantially reduce anticoagulant efficacy through enzyme induction. Warfarin consists of two enantiomers, with S-warfarin primarily metabolized by CYP2C9 and R-warfarin metabolized mainly by CYP1A2 and CYP3A4. Rifampicin induces these metabolic pathways, resulting in increased clearance of warfarin and reduced anticoagulant activity6,7,8. The onset of enzyme induction generally occurs within 1–2 weeks after rifampicin initiation and gradually resolves after discontinuation as enzyme turnover returns to baseline9,13.
In this case, the patient's warfarin dose increased from 1.5 mg/day before rifampicin initiation to 4.5 mg/day during concomitant therapy, representing an approximately 200% increase. The timing of dose escalation and subsequent INR stabilization was consistent with the expected pharmacokinetic characteristics of rifampicin-mediated enzyme induction rather than a population-specific effect.
However, it should be noted that INR stabilization in this case required approximately 2 months, which is longer than the typically reported 2–4 weeks for rifampicin enzyme induction to reach steady state9,13. This prolonged course may be partly explained by an intervening clinical event: pyrazinamide was discontinued on day 19 of antituberculosis therapy because of drug-induced hepatotoxicity (alkaline phosphatase increased from 117 IU/L to 193 IU/L). Hepatic dysfunction and subsequent recovery during this period could have introduced additional variability in warfarin metabolism, potentially confounding the time course of INR stabilization. Therefore, the 2-month timeline observed in this case should not be interpreted as a typical or expected duration of rifampicin-warfarin interaction, but rather as a reflection of the complex clinical context involving concurrent hepatotoxicity and medication adjustment.
Previous management approaches for patients requiring rifampicin therapy often involve switching from oral anticoagulation to parenteral anticoagulation because of concerns regarding reduced anticoagulant efficacy. However, long-term low-molecular-weight heparin therapy may be associated with practical limitations, including daily injections, treatment burden, and reduced feasibility for prolonged outpatient management.
Compared with DOACs, warfarin offers a unique advantage in this setting because anticoagulant intensity can be directly assessed via INR monitoring, enabling individualized dose adjustment. Although DOACs are effective alternatives for many indications, their exposure may be significantly reduced during rifampicin therapy due to CYP3A4 and P-glycoprotein induction, and routine monitoring equivalent to INR is generally not available8,9. Therefore, in selected patients requiring prolonged rifampicin treatment, carefully monitored warfarin therapy may represent a practical alternative when frequent INR assessment and clinical follow-up are feasible.
The literature on the increase in warfarin dosage during co-administration with rifampicin shows considerable heterogeneity in the magnitude of the required increase. The degree of increase in warfarin dosage ranged from approximately 50% to more than 600%. The time required to regain therapeutic INR after rifampicin discontinuation also varied, often taking between one and five months10,11,12,14,15,16,17,18,19,20 (Table 1, Figure 2). A clinical practice summary on the practical management of warfarin during co-administration with rifampicin is shown in Table 2.
Pharmacogenetic factors contribute substantially to baseline warfarin dose requirements. CYP2C9 and VKORC1 polymorphisms account for a considerable proportion of interindividual variability in warfarin dosing, with some studies suggesting that these genetic factors may explain up to approximately 50% of dose variation19,20. Reduced-function CYP2C9 alleles decrease warfarin clearance and are associated with lower dose requirements21,22. The CYP2C9*3 allele has been reported to occur in approximately 3%–5% of individuals of Chinese ancestry, although the frequency varies among different Chinese cohorts and geographic regions3,21,22,23. In contrast, CYP2C9*2 is uncommon among Chinese populations, whereas VKORC1 sensitivity-associated variants, particularly VKORC1 −1639G>A and VKORC1 1173T, are highly prevalent in East Asian populations17,18.
These pharmacogenetic characteristics, especially the higher prevalence of VKORC1 sensitivity-associated variants, may partially explain why many East Asian patients require lower baseline warfarin maintenance doses compared with individuals of European ancestry23,24. However, these genetic differences primarily influence baseline warfarin sensitivity and dose requirements rather than indicating a different susceptibility to rifampicin-mediated enzyme induction. Therefore, pharmacogenetic and ethnic characteristics should not be used to infer the magnitude of the rifampicin-warfarin interaction, which remains highly individualized and requires patient-specific monitoring and dose adjustment25,26.
This case provides practical evidence supporting a structured pharmacist-supported approach for managing warfarin therapy during rifampicin treatment. The main contribution of this report is not to establish population-level estimates of rifampicin-warfarin interaction but to illustrate how intensive INR monitoring and individualized dose adjustment can maintain safe anticoagulation in a clinically challenging situation.
Future prospective studies involving larger cohorts are needed to better characterize predictors of warfarin dose escalation during rifampicin therapy, including pharmacogenetic markers, inflammatory status, concomitant medications, and clinical characteristics. Development and validation of evidence-based dosing prediction models may further improve individualized anticoagulation management.
This report has several limitations. First, it represents a single patient experience and cannot determine interindividual or population variability. Second, pharmacogenetic testing was not performed; therefore, the contribution of CYP2C9 and VKORC1 variants could not be directly assessed. Third, the independent effects of isoniazid could not be completely separated from those of rifampicin. Fourth, INR variability during hospitalization may have been partially influenced by bridging anticoagulation, as warfarin interruption and enoxaparin overlap may affect early INR interpretation. Therefore, this case should be considered a practical clinical example rather than evidence for population-specific differences in rifampicin–warfarin interaction.
This report highlights the need for frequent monitoring of INR levels and prompt dose adjustments (increase) when co-administering rifampicin with warfarin. An increase in the patient's maintenance warfarin dose was observed (approximately 200%), and a therapeutic INR was achieved after approximately 2 months, which was longer than the typically reported 2–4 weeks, likely due to confounding factors such as concurrent hepatotoxicity during the enzyme induction period. The most important elements of this report are the importance of structured INR monitoring, recognition of the timing of enzyme induction and de-induction, and pharmacist involvement to ensure safe management of this type of drug-drug interaction. Although pharmacogenetic and ethnic status may affect the base warfarin dose requirement(s), this report provides no support for making population-based inferences regarding the strength or magnitude of the rifampicin and warfarin interaction. This case is an illustration of clinical management rather than a comparative ethnic study. Additional studies with larger patient populations are needed to characterize variability in warfarin dose requirements when used concurrently with rifampicin and to develop improved evidence-based monitoring guidelines.
Disclosures
The authors declare that they have no conflicts of interest related to this work. During manuscript preparation, the authors used artificial intelligence (AI)-assisted tools solely for language refinement and improvement of readability. All scientific content, data interpretation, and conclusions were independently reviewed and verified by the authors.
Acknowledgements
The authors would like to thank the patient and his family for providing consent for publication of this case report. The authors also acknowledge the support of the clinical pharmacy team involved in patient monitoring and anticoagulation management.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| CHA2DS2-VASc score | European Society of Cardiology guideline resource | https://www.escardio.org | Assessment of thromboembolic risk in atrial fibrillation |
| Computed tomography scanner | China–Japan Friendship Hospital Radiology Department | Institutional equipment | Diagnosis and follow-up evaluation of pulmonary tuberculosis |
| Enoxaparin sodium injection | Sanofi | Product information: https://www.sanofi.com | Bridging anticoagulation during temporary warfarin interruption |
| GraphPad Prism | GraphPad Software LLC | https://www.graphpad.com | Figure preparation and visualization |
| HAS-BLED score | European Society of Cardiology guideline resource | https://www.escardio.org | Assessment of bleeding risk |
| International normalized ratio (INR) measurement | Laboratory Department, China–Japan Friendship Hospital | Institutional laboratory procedure | Monitoring anticoagulation intensity |
| Microsoft Excel | Microsoft Corporation | https://www.microsoft.com | Data recording and clinical timeline organization |
| Rifampicin capsules | Zhejiang Shapuaisi Pharmaceutical Co., Ltd., China | Product information available from manufacturer | Antituberculosis therapy and enzyme induction exposure |
| Sputum culture for Mycobacterium tuberculosis | Clinical Microbiology Laboratory, China–Japan Friendship Hospital | Institutional laboratory procedure | Confirmation of tuberculosis diagnosis |
| Warfarin sodium tablets | Orion Corporation, Finland | Product information: https://www.orionpharma.com | Long-term anticoagulation and dose adjustment |
| WHO bleeding scale | World Health Organization | >https://www.who.int | Evaluation of bleeding complications |
References
- Hirsh J, et al. American Heart Association/American College of Cardiology Foundation guide to warfarin therapy. J Am Coll Cardiol. 2003;41(9):1633-52.
- International Warfarin Pharmacogenetics Consortium. Estimation of the warfarin dose with clinical and pharmacogenetic data. N Engl J Med. 2009;360(8):753-64.
- Johnson JA, et al. Clinical Pharmacogenetics Implementation Consortium guidelines for CYP2C9 and VKORC1 genotypes and warfarin dosing. Clin Pharmacol Ther. 2011;90(4):625-9.
- Falzon D, et al. WHO guidelines for the programmatic management of drug-resistant tuberculosis: 2011 update. Eur Respir J. 2011;38(3):516-28.
- Kim KY, Epplen K, Foruhari F, Alexandropoulos H. Update on the interaction of rifampin and warfarin. Prog Cardiovasc Nurs. 2007;22(2):97-100.
- Bunclark K, et al. A multicenter study of anticoagulation in operable chronic thromboembolic pulmonary hypertension. J Thromb Haemost. 2020;18(1):114-22.
- Ageno W, et al. Oral anticoagulant therapy: Antithrombotic Therapy and Prevention of Thrombosis, 9th ed: American College of Chest Physicians evidence-based clinical practice guidelines. Chest. 2012;141(2 Suppl):e44S-e88S.
- US Food and Drug Administration. Drug development and drug interactions: Table of substrates, inhibitors, and inducers. 2023. Available from: https://www.fda.gov/drugs/drug-interactions-labeling/drug-development-and-drug-interactions-table-substrates-inhibitors-and-inducers.
- Heimark LD, et al. The mechanism of the warfarin-rifampin drug interaction in humans. Clin Pharmacol Ther. 1987;42(4):388-94.
- Hu YN, et al. Effect of rifampicin on anticoagulation of warfarin: A case report. World J Clin Cases. 2021;9(5):1087-95.
- Fahmi AM, Abdelsamad O, Elewa H. Springerplus. 2016;5:8.
- Salem M, et al. Genetic polymorphism effect on warfarin-rifampin interaction: A case report and review of literature. Pharmgenomics Pers Med. 2021;14:149-56.
- Ohno Y, Hisaka A, Ueno M, Suzuki H. General framework for the prediction of oral drug interactions caused by CYP3A4 induction from in vivo information. Clin Pharmacokinet. 2008;47(10):669-80.
- Self TH, Mann RB. Interaction of rifampin and warfarin. Chest. 1975;67(4):490-1.
- Krajewski KC. Inability to achieve a therapeutic INR value while on concurrent warfarin and rifampin. J Clin Pharmacol. 2010;50(6):710-3.
- Martins MA, et al. Rifampicin-warfarin interaction leading to macroscopic hematuria: A case report and review of the literature. BMC Pharmacol Toxicol. 2013;14:27.
- Maina MW, et al. Describing the profile of patients on concurrent rifampin and warfarin therapy in western Kenya: A case series. Drugs R D. 2013;13(3):191-7.
- Dawson J, et al. Prolonged induction of warfarin metabolism and a paradoxical INR response in a mitral valve replacement patient receiving rifampicin for infective endocarditis. Biomed Res Clin Pract. 2016;1:DOI: 10.15761/BRCP.1000112.
- Meng H, J. Rifampin and increase of warfarin dose: A case report and review of the literature. Chin Pharm J. 2015;50(6):550-3.
- Yang CS, Boswell R, Bungard TJ. A case series of the rifampin-warfarin drug interaction: Focus on practical warfarin management. Eur J Clin Pharmacol. 2021;77(3):341-8.
- Zhang X, Li G. Clinical pharmacist participated in anticoagulation treatment of a patient with nonvalvular atrial fibrillation and tuberculous pleurisy. 15th Forum on the Way to Success for Chinese Young Pharmacists. 2016;1–5.
- Lee CR, Thrasher KA. Difficulties in anticoagulation management during coadministration of warfarin and rifampin. Pharmacotherapy. 2001;21(10):1240-6.
- Wei M, et al. A new algorithm to predict warfarin dose from polymorphisms of CYP4F2, CYP2C9, and VKORC1 and clinical variables: Derivation in Han Chinese patients with nonvalvular atrial fibrillation. Thromb Haemost. 2012;107(6):1083-91.
- Takeuchi F, et al. A genome-wide association study confirms VKORC1, CYP2C9, and CYP4F2 as principal genetic determinants of warfarin dose. PLoS Genet. 2009;5(3):e1000433.
- Leveque D, et al. Mechanisms of pharmacokinetic drug-drug interactions. Rev Med Interne. 2010;31(2):170-9.
- Nishimura Y, et al. Inhibitory effect of antituberculosis drugs on human cytochrome P450-mediated activities. J Pharmacol Sci. 2004;96(3):293-300.