This review examines diabetes-associated enteric neuropathy as a segment-specific, multicellular injury linking metabolic stress, redox imbalance, immune and glial remodeling, trophic failure, and disrupted neuromuscular coordination to gastrointestinal dysfunction.
Review Article
Diabetes-Associated Enteric Neuropathy: An Overlooked Driver of Gastrointestinal Dysfunction
In This Article
Summary
Abstract
Diabetes mellitus is frequently accompanied by gastrointestinal symptoms, but these symptoms are not fully explained by extrinsic autonomic neuropathy and should not be equated with a single enteric lesion. Human biopsy and motility studies, complemented by experimental models, indicate that the enteric nervous system (ENS) and its neuromuscular niche can be injured in segment- and cell-specific ways. Human evidence supports gastric changes in interstitial cells of Cajal (ICC) and macrophages, and colonic enteric neuronal loss associated with oxidative stress; plexus-resolved and repair mechanisms are derived mainly from animal or in vitro studies. Recurrently implicated pathways include redox imbalance, immune remodeling, impaired glial cell line-derived neurotrophic factor (GDNF)-phosphoinositide 3-kinase (PI3K)/Akt signaling, enteric glial stress, and microbiota-metabolite signaling. Myenteric injury is most directly linked to dysmotility, whereas submucosal injury may alter secretion, barrier function, and local neuroimmune control. Current care remains symptom-directed. Heme oxygenase-1, interleukin-10, neurotrophic rescue, nicotinamide riboside, 5-hydroxytryptamine 4 receptor agonism, microbiota-derived butyrate, and extracellular vesicles are investigational rather than established disease-modifying therapies. Segment-specific biomarkers and human translational models are needed to connect cellular injury with symptoms and treatment response.
Introduction
Gastrointestinal symptoms in diabetes are common, prolonged, and often poorly matched to routine clinical tests. They are frequently described as diabetic autonomic neuropathy or diabetic gastroenteropathy, terms that are clinically convenient but biologically incomplete. Recent reviews have placed enteric neuropathy within the spectrum of diabetic gastrointestinal disorders and argue that damage to enteric circuits should be considered alongside vagal and sympathetic injury1,2,3,4,5.
Gastrointestinal symptoms are more prevalent in adults with diabetes than in population controls, particularly when glycemic control is poor, but symptom prevalence is not the same as confirmed gastroparesis or histological enteric neuropathy6. In a community cohort, the 10-year cumulative risk of rigorously defined gastroparesis was 5.2% in type 1 diabetes and 1.0% in type 2 diabetes, compared with 0.2% in controls7. This epidemiological distinction prevents common upper- or lower-gastrointestinal symptoms from being interpreted as evidence of a single neuropathic lesion.
Gastroparesis illustrates the problem. It is defined by upper gastrointestinal symptoms, delayed gastric emptying, and absence of mechanical obstruction8. Yet symptoms, emptying rate, and histology do not always move together. Patients with type 1 and type 2 diabetes can differ in symptom severity and longitudinal outcomes9. Wireless motility capsule studies further show that dysmotility may extend beyond the stomach to involve small-bowel and colonic transit as well as contractility10,11. Diarrhea is also multifactorial, reflecting neuropathic secretion or motility in some patients and medication effects, infection, bile-acid malabsorption, small-intestinal bacterial overgrowth, pancreatic insufficiency, or mixed causes in others12.
This review focuses on diabetes-associated enteric neuropathy as a cell- and circuit-level phenomenon rather than as a complete catalog of diabetic gastrointestinal disease. Metabolic injury can alter enteric neurons, enteric glia, immune cells, ICC, and smooth muscle in region-specific ways. Diabetes-associated enteric neuropathy should therefore be considered a multicellular neuromuscular disorder and not merely a late manifestation of autonomic neuropathy. Figure 1 summarizes this evidence-aware framework and distinguishes established human observations from mechanisms and repair strategies supported mainly by experimental models.
Review and Perspective
Clinical phenotype: more than delayed gastric emptying
Diabetic gastroparesis is often the starting point for discussions of diabetic gastrointestinal disease. Nausea, vomiting, early satiety, postprandial fullness, bloating, pain, and unstable glycemic fluctuations are commonly attributed to gastric dysfunction. The American College of Gastroenterology guideline defines gastroparesis by symptoms plus objective delayed gastric emptying in the absence of mechanical obstruction8. For an ENS-oriented review, that diagnosis is descriptive rather than explanatory. A delayed-emptying test shows abnormal gastric motor output, but it does not identify whether the defect lies primarily in enteric neurons, ICC, macrophages, smooth muscle, extrinsic nerves, pyloric function, glucose fluctuations, or a combination of these factors.
Bowel phenotypes are similarly diverse. Constipation in diabetes is often linked to slow colonic transit, but capsule-based motility studies show that contractility and transit can vary by gut region, so a single pattern should not be assumed11. Diabetic diarrhea is also mechanistically mixed. The label may include neuropathic secretion or motility, treatment effects, and other diabetes-associated disorders12. A segmental view is therefore necessary. The ENS is continuous along the gut, but enteric neurons reside in different local environments in the stomach, small intestine, colon, and rectum.
Symptoms should not be used as a direct index of enteric neuronal loss. A patient with severe nausea may have delayed, normal, or rapid gastric emptying. A patient with constipation may have slow transit, weak contractility, disordered evacuation, drug effects, or multiple simultaneous causes. Diabetes-associated enteric neuropathy is best viewed as one pathology within the broader spectrum of diabetic gastrointestinal disease, not as a diagnosis that explains every symptom.
Regional and plexus-specific heterogeneity
The ENS is organized mainly into myenteric and submucosal plexuses. The myenteric plexus lies between the circular and longitudinal muscle layers and primarily coordinates propulsive and sphincter motor patterns. The submucosal plexus more directly regulates mucosal secretion, absorption, local blood flow, and barrier-neuroimmune signaling. Diabetes may affect both plexuses, but the evidence is uneven: human studies have mainly sampled gastric muscularis and colonic full-thickness tissue, whereas most plexus-resolved comparisons derive from experimental models13,14,15.
Neuronal vulnerability is not restricted to a single chemical class. In human diabetic colon, loss of peripherin-, neuronal nitric oxide synthase (nNOS)-, neuropeptide Y (NPY)-, and choline acetyltransferase (ChAT)-positive neurons coexisted with oxidative stress and impaired contraction and relaxation, whereas vasoactive intestinal peptide staining was relatively preserved13. In diabetic rodents, oxidative and nitrosative stress is associated with changes in HuC/D-, nNOS-, and calretinin-positive myenteric populations along the duodenum-jejunum-ileum axis14, and submucosal vasoactive intestinal peptide-positive neurons and calcitonin gene-related peptide fibers can also remodel15. Nitrergic neurons are recurrently implicated, but susceptibility varies by region, disease duration, model, and marker; current evidence does not support labeling a single 'most affected' neuronal population.
These differences have functional implications. Gastric myenteric-ICC-macrophage injury may impair antral-pyloric coordination and accommodation; small-intestinal myenteric injury may alter peristalsis, whereas submucosal injury may modify secretion and barrier function; and colonic myenteric neuronal loss may impair contraction and relaxation and contribute to constipation or abnormal transit. Experimental data show segment-specific interleukin-1 beta induction in nNOS-positive colonic versus calcitonin gene-related peptide-positive ileal myenteric neurons16, reinforcing the notion that diabetes-associated enteric neuropathy is a family of regional lesions rather than a uniform pan-enteric process. Direct human comparisons across plexuses and gut segments remain a major gap.
Human tissue evidence: a mixed cellular lesion
Human tissue studies have shifted diabetic gastroparesis from a purely functional label toward a cellular disorder. Full-thickness gastric biopsies from patients with diabetic and idiopathic gastroparesis showed reduced ICC, enteric nerve abnormalities, and immune-cell changes17. Subsequent clinical-histological analysis by the Gastroparesis Clinical Research Consortium linked cellular findings to symptoms and gastric emptying, but the associations were not specific enough to support a single histologic marker of disease severity18.
Macrophages are probably not bystanders. Low numbers of CD206-positive cells in the gastric body were associated with ICC loss in diabetic gastroparesis19. A similar loss of CD206-positive macrophages was later reported in the gastric antrum of patients with diabetic and idiopathic gastroparesis20. These findings are consistent with animal data linking macrophage phenotype to ICC integrity and gastric emptying, and they suggest a neuromuscular niche in which immune regulation may influence neuronal survival.
Smooth muscle and stromal components may also be involved. In surgical specimens from patients with diabetes, investigators reported alterations in smooth muscle, enteric nerves, ICC, and platelet-derived growth factor receptor-alpha-positive fibroblast-like cells21. These observations do not imply that all patients share the same lesion. Rather, they show that the diabetic stomach can be damaged through several interacting cell types. Enteric neurons are part of this multicellular network and are shaped by nearby ICC, glia, macrophages, and muscle.
Metabolic injury and redox stress
Hyperglycemia does not damage the ENS through a single pathway. Oxidative stress is a shared feature across models and human tissue. Loss of heme oxygenase-1 (HO-1) in diabetic mice has been associated with oxidative stress, ICC depletion, and delayed gastric emptying, whereas HO-1 induction protected ICC and reversed delayed emptying22. Carbon monoxide, a product of HO-1 activity, has shown protective effects in non-obese diabetic mice23. Interleukin-10 (IL-10) promotes a cytoprotective macrophage program and HO-1 expression; in diabetic mice, this pathway restored gastric emptying, electrical activity, and ICC networks24. Later mouse data further supported the concept that shifts in the macrophage population can promote delayed gastric emptying25.
Human colonic data extend the redox story beyond the stomach. Colonic samples from individuals with diabetes showed motor dysfunction associated with enteric neuronal loss, apoptosis, and elevated oxidative stress markers13. This study did not prove that oxidative stress is the only cause of neuronal loss. It did show that neuronal injury, oxidative stress, and colonic motor defects can occur together in people with diabetes.
Redox injury may also help explain why ENS dysfunction can persist. Once neuronal signaling, ICC networks, macrophage phenotype, and muscle contractility are imbalanced, a transient metabolic insult may leave a longer functional imprint. This does not make the disease irreversible, but it suggests that glycemic control alone may be insufficient after the neuromuscular niche has been remodeled.
Neurotrophic failure and neuronal plasticity
Glial cell line-derived neurotrophic factor (GDNF) has protective effects in metabolically stressed enteric neurons. In primary enteric-neuron cultures, GDNF inhibited hyperglycemia-induced neuronal loss through activation of the phosphoinositide 3-kinase (PI3K)/Akt pathway26. Diabetic rats also exhibit enteric neuronal loss, decreased GDNF expression, and reduced PI3K/Akt pathway activity27. These experimental studies support a testable chain in which high glucose reduces survival signaling and increases neuronal vulnerability, but they do not establish the efficacy of GDNF-based therapy in humans.
Evidence for enteric neural protection and repair remains predominantly preclinical. High-frequency electroacupuncture at ST36 induced regeneration of lost enteric neurons in diabetic rats through GDNF-PI3K/Akt signaling28. Nicotinamide riboside reduced enteric neuropathy in streptozotocin-induced diabetic rats by protecting the myenteric plexus29, and a 5-hydroxytryptamine 4 (5-HT4) receptor agonist attenuated diabetic enteric neuropathy in mice by suppressing receptor-interacting protein kinase 3-mediated cell death30. Bone marrow-derived mesenchymal stem cell microvesicles improved enteric neural precursor cell survival, ENS structure, and motility in diabetic mice; the same study documented delayed transit and altered ENS structure in patients but did not test microvesicle treatment in humans31.
These studies have not established routine clinical treatments for diabetic enteric neuropathy. They do, however, challenge the view that the adult ENS is purely degenerative once injured. Enteric neurons and their precursor cells may respond to trophic, metabolic, inflammatory, and vesicle-mediated signals. The next step is to develop human biomarkers that can show whether a repair signal reaches the ENS and whether it alters symptoms or motility.
Glia, microbiota, and regional vulnerability
Enteric neurons do not fail independently. Enteric glia regulate epithelial barrier function, neurotransmission, immune signaling, and neuronal support. Diabetes-related changes in the ENS microenvironment include altered trophic support, nitrergic neuronal vulnerability, region-dependent neuronal loss, and changes in the local cellular niche32. A microenvironmental perspective helps explain why different gut segments can respond differently to the same systemic metabolic disease.
Recent work in type 1 diabetes models suggests that intestinal length and segment-specific structure influence how hyperglycemia alters enteric neurons33. This helps explain why gastric emptying, small-bowel transit, colonic transit, and anorectal function may be abnormal in different combinations in the same patient. A single biopsy site, motility test, or animal gut segment should therefore not be treated as representative of the entire gastrointestinal tract.
Glial and immune changes remain less clearly defined than neuronal and ICC abnormalities. Some studies emphasize macrophage differentiation; others examine glial cell number, trophic factors, and oxidative stress. These are not competing explanations but different windows into the same neuromuscular niche. Current evidence indicates that diabetes modifies the environment that sustains and coordinates enteric neurons, and that this environment varies along the gut.
The intestinal microbiota is a plausible modifier rather than an established cause of diabetes-associated enteric neuropathy. In non-diabetic antibiotic-treated mice, microbial depletion caused neuronal loss from both myenteric and submucosal plexuses in the ileum and proximal colon; microbiota reconstitution or short-chain fatty acids restored neuronal numbers and aspects of intestinal function34. More directly, a 2026 integrated human and mouse study found dysbiosis associated with gastrointestinal-autonomic-neuropathy severity; fecal microbiota transfer from affected patients aggravated dysmotility and apoptosis of ChAT-positive and nNOS-positive myenteric neurons in db/db mice, whereas Faecalibacterium prausnitzii-derived butyrate was neuroprotective in experimental systems35. These findings support a microbiota-ENS axis, but human causality and therapeutic benefit remain unproven, and diet, medications, diabetes phenotype, and transit itself are important confounders.
Treatment implications
Current treatment still begins with symptom management. Dietary adjustment, glycemic regulation, antiemetics, prokinetics, constipation management, diarrhea assessment, and nutritional support remain essential8,36,37,38. Pylorus-directed therapy, device therapy, and pharmacological options may help selected patients with gastroparesis, although the quality of evidence and response are variable8,39. These approaches can improve care, but they do not directly assess or correct ENS injury.
An ENS-based plan would add three questions to the routine assessment. First, which gut segment is responsible for the patient's primary disability? Second, is the dominant mechanism motor failure, sensory dysfunction, secretion, immune activation, medication effect, or a combination? Third, does a proposed intervention only relieve symptoms, or does it also support restoration of the affected neuromuscular system? These questions are less simple than the broad label diabetic gastroenteropathy, but they are closer to the biological problem.
Several experimental repair directions have emerged. The heme oxygenase-1 (HO-1) and interleukin-10 (IL-10) pathways support redox control and macrophage reprogramming in diabetic mice22,23,24,25. GDNF-PI3K/Akt data support neurotrophic rescue in cell and rodent models26,27,28. Nicotinamide riboside, 5-HT4 receptor signaling, extracellular vesicles, and microbiota-derived butyrate suggest metabolic support, regulation of cell death, precursor-cell protection, and neuroimmune modulation29,30,31,35. None is an established disease-modifying treatment for human diabetes-associated enteric neuropathy. Future studies should pair symptom and regional motility outcomes with biomarkers of neural, glial, ICC, immune, and microbial-metabolite injury.
Open questions
Several gaps limit the field. Human tissue is difficult to obtain and is mostly gastric. Motility tests identify regional dysfunction but do not reveal the cellular lesion. Symptoms are essential for clinical care but weak indicators of ENS structure. Animal models reproduce selected features of diabetic enteropathy but differ in diabetes type, disease duration, microbiota, diet, and sex. These differences may explain why a mechanism appears strong in one model and less consistent in another.
The major translational need is biomarker development. Blood markers of oxidative stress and inflammation are unlikely to be specific enough on their own. Imaging, mucosal or full-thickness tissue readouts, circulating extracellular vesicle signatures, transit phenotyping, and neurophysiological testing may all be needed. The goal is not a perfect diagnostic index, but a practical way to classify patients by treatment-relevant biology: dominant gastric neuromuscular injury, pan-intestinal dysmotility, colonic neuropathic dysfunction, or mixed disease not primarily driven by neural injury.
Conclusions
Diabetes-associated enteric neuropathy offers a focused way to understand part of diabetic gastrointestinal disease. Human tissue studies, segmental motility data, and experimental models link hyperglycemia to oxidative stress, macrophage shifts, ICC disruption, impaired neurotrophic signaling, changes in glial and microbiota metabolites, and enteric neuronal loss. The available evidence supports a family of regional lesions affecting myenteric and, less well characterized, submucosal circuits rather than a uniform pan-enteric neuropathy. Not every gastrointestinal symptom in diabetes is caused by ENS damage, and symptoms alone cannot define the lesion. An ENS-centered framework nevertheless encourages precise regional phenotyping and direct measurement of neuromuscular injury. The field now needs clinically usable biomarkers, paired sampling across gut regions and plexuses, better human models, and trials that determine whether protecting or restoring enteric neural circuits improves patient-relevant outcomes.
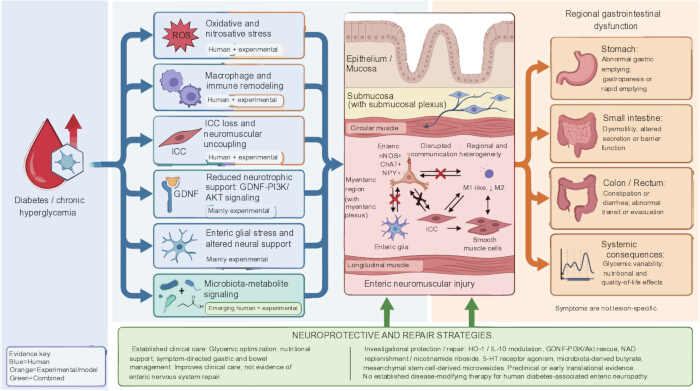
Figure 1: Segment- and evidence-aware framework of diabetes-associated enteric neuropathy. Chronic hyperglycemia and diabetes-associated metabolic stress converge with oxidative and nitrosative stress, immune and macrophage remodeling, ICC loss, impaired GDNF-PI3K/Akt signaling, enteric glial stress, and microbiota-metabolite signaling. Human evidence is strongest for gastric ICC/macrophage abnormalities and colonic neuronal loss associated with oxidative stress; most pathway-specific and repair evidence derives from experimental models. The diagram places the submucosal plexus within the submucosa and the myenteric plexus between the circular and longitudinal muscle layers, with ICC forming a neuromuscular network adjacent to neurons and smooth muscle. Regional injury may contribute to abnormal gastric emptying, small-intestinal dysmotility or secretory-barrier dysfunction, colonic transit disorders, diarrhea, constipation, and glycemic variability. Established care remains symptom-directed, whereas HO-1/IL-10 modulation, GDNF-PI3K/Akt rescue, NAD replenishment, 5-HT4 receptor activation, microbiota-derived butyrate, and extracellular-vesicle approaches remain investigational. Please click here to view a larger version of this figure.
Disclosures
The authors have no conflicts of interest to declare. Figure 1 was generated with assistance from FigureLabs (https://chat.figurelabs.ai), an AI-assisted scientific illustration platform. The authors reviewed and approved the final figure.
AUTHOR CONTRIBUTIONS:
Zhu Y conceived the review, performed the literature search, drafted the manuscript, and prepared the figure. Jiao Y contributed to the conceptual design, critically revised the manuscript for important intellectual content, and supervised the study. Liu Q conceived the study, supervised the overall project, critically revised the manuscript, and approved the final version. All authors reviewed, revised, and approved the final manuscript and agree to be accountable for all aspects of the work
References
- Abdalla, M. M. I. Enteric neuropathy in diabetes: Implications for gastrointestinal function. World J. Gastroenterol. 30 (22), 2852-2865 (2024).
- Bharucha, A. E., Kudva, Y. C. & Prichard, D. O. Diabetic gastroparesis. Endocr. Rev. 40 (5), 1318-1352 (2019).
- Chandrasekharan, B. & Srinivasan, S. Diabetes and the enteric nervous system. Neurogastroenterol. Motil. 19 (12), 951-960 (2007).
- Yarandi, S. S. & Srinivasan, S. Diabetic gastrointestinal motility disorders and the role of enteric nervous system: Current status and future directions. Neurogastroenterol. Motil. 26 (5), 611-624 (2014).
- Azpiroz, F. & Malagelada, C. Diabetic neuropathy in the gut: Pathogenesis and diagnosis. Diabetologia. 59 (3), 404-408 (2016).
- Bytzer, P. et al. Prevalence of gastrointestinal symptoms associated with diabetes mellitus: A population-based survey of 15,000 adults. Arch. Intern. Med. 161 (16), 1989-1996 (2001).
- Choung, R. S. et al. Risk of gastroparesis in subjects with type 1 and 2 diabetes in the general population. Am. J. Gastroenterol. 107 (1), 82-88 (2012).
- Camilleri, M. et al. ACG clinical guideline: Gastroparesis. Am. J. Gastroenterol. 117 (8), 1197-1220 (2022).
- Koch, K. L. et al. Baseline features and differences in 48-week clinical outcomes in patients with gastroparesis and type 1 versus type 2 diabetes. Neurogastroenterol. Motil. 28 (7), 1001-1015 (2016).
- Sangnes, D. A. et al. Wireless motility capsule compared with scintigraphy in the assessment of diabetic gastroparesis. Neurogastroenterol. Motil. 32 (4), e13771 (2020).
- Sangnes, D. A. et al. Gastrointestinal transit and contractility in diabetic constipation: A wireless motility capsule study on diabetes patients and healthy controls. United Eur. Gastroenterol. J. 9 (10), 1168-1177 (2021).
- Selby, A., Reichenbach, Z. W., Piech, G. & Friedenberg, F. K. Pathophysiology, differential diagnosis, and treatment of diabetic diarrhea. Dig. Dis. Sci. 64 (12), 3385-3393 (2019).
- Chandrasekharan, B. et al. Colonic motor dysfunction in human diabetes is associated with enteric neuronal loss and increased oxidative stress. Neurogastroenterol. Motil. 23 (2), 131-138, e26 (2011).
- Ferreira, P. E. B., Beraldi, E. J., Borges, S. C., Natali, M. R. M. & Buttow, N. C. Resveratrol promotes neuroprotection and attenuates oxidative and nitrosative stress in the small intestine in diabetic rats. Biomed. Pharmacother. 105, 724-733 (2018).
- Tashima, C. M., Hermes-Uliana, C., Perles, J. V. C. M., de Miranda Neto, M. H. & Zanoni, J. N. Vitamins C and E (ascorbate/alpha-tocopherol) provide synergistic neuroprotection in the jejunum in experimental diabetes. Pathophysiology. 22 (4), 241-248 (2015).
- Al Doghmi, A. et al. Gut region-specific interleukin-1 beta induction in different myenteric neuronal subpopulations of type 1 diabetic rats. Int. J. Mol. Sci. 24 (6), 5804 (2023).
- Grover, M. et al. Cellular changes in diabetic and idiopathic gastroparesis. Gastroenterology. 140 (5), 1575-1585.e8 (2011).
- Grover, M. et al. Clinical-histological associations in gastroparesis: Results from the Gastroparesis Clinical Research Consortium. Neurogastroenterol. Motil. 24 (6), 531-539, e249 (2012).
- Bernard, C. E. et al. Association of low numbers of CD206-positive cells with loss of ICC in the gastric body of patients with diabetic gastroparesis. Neurogastroenterol. Motil. 26 (9), 1275-1284 (2014).
- Grover, M. et al. Diabetic and idiopathic gastroparesis is associated with loss of CD206-positive macrophages in the gastric antrum. Neurogastroenterol. Motil. 29 (6), e13018 (2017).
- Park, K. S. et al. Characterization of smooth muscle, enteric nerve, interstitial cells of Cajal, and fibroblast-like cells in the gastric musculature of patients with diabetes mellitus. World J. Gastroenterol. 22 (46), 10131-10139 (2016).
- Choi, K. M. et al. Heme oxygenase-1 protects interstitial cells of Cajal from oxidative stress and reverses diabetic gastroparesis. Gastroenterology. 135 (6), 2055-2064.e2 (2008).
- Kashyap, P. C. et al. Carbon monoxide reverses diabetic gastroparesis in NOD mice. Am. J. Physiol. Gastrointest. Liver Physiol. 298 (6), G1013-G1019 (2010).
- Choi, K. M. et al. Interleukin-10 restores gastric emptying, electrical activity, and interstitial cells of Cajal networks in diabetic mice. Cell Mol. Gastroenterol. Hepatol. 2 (4), 454-467 (2016).
- Cipriani, G. et al. Change in populations of macrophages promotes development of delayed gastric emptying in mice. Gastroenterology. 154 (8), 2122-2136.e12 (2018).
- Anitha, M. et al. GDNF rescues hyperglycemia-induced diabetic enteric neuropathy through activation of the PI3K/Akt pathway. J. Clin. Invest. 116 (2), 344-356 (2006).
- Du, F., Wang, L., Qian, W. & Liu, S. Loss of enteric neurons accompanied by decreased expression of GDNF and PI3K/Akt pathway in diabetic rats. Neurogastroenterol. Motil. 21 (11), 1229-e114 (2009).
- Du, F. & Liu, S. Electroacupuncture with high frequency at acupoint ST36 induces regeneration of lost enteric neurons in diabetic rats via the GDNF and PI3K/Akt signaling pathway. Am. J. Physiol. Regul. Integr. Comp. Physiol. 309 (2), R109-R118 (2015).
- Costa, C. J., Cohen, M. W., Goldberg, D. C., Mellado, W. & Willis, D. E. Nicotinamide riboside improves enteric neuropathy in streptozotocin-induced diabetic rats through myenteric plexus neuroprotection. Dig. Dis. Sci. 68 (7), 2963-2974 (2023).
- Cheng, Y. et al. 5-Hydroxytryptamine 4 receptor agonist attenuates diabetic enteric neuropathy through inhibition of the receptor-interacting protein kinase 3 pathway. Am. J. Pathol. 194 (5), 785-795 (2024).
- Shi, H. et al. BM-derived mesenchymal stem cell microvesicles protect enteric neural precursor cells and alleviate diabetes-associated enteric neuropathy. J. Clin. Invest. 136 (6), e192437 (2026).
- Bagyánszki, M. & Bódi, N. Diabetes-related alterations in the enteric nervous system and its microenvironment. World J. Diabetes. 3 (5), 80-93 (2012).
- Bagyánszki, M. & Bódi, N. Key elements determining the intestinal region-specific environment of enteric neurons in type 1 diabetes. World J. Gastroenterol. 29 (18), 2704-2716 (2023).
- Vicentini, F. A. et al. Intestinal microbiota shapes gut physiology and regulates enteric neurons and glia. Microbiome. 9 (1), 210 (2021).
- Guo, L. et al. Neuroprotective role of Faecalibacterium prausnitzii-derived butyrate in diabetic gastrointestinal autonomic neuropathy. J. Genet. Genomics. In press (2026). doi: 10.1016/j.jgg.2026.06.005.
- Meldgaard, T. et al. Diabetic enteropathy: From molecule to mechanism-based treatment. J. Diabetes Res. 2018, 3827301 (2018).
- Meldgaard, T. et al. Pathophysiology and management of diabetic gastroenteropathy. Ther. Adv. Gastroenterol. 12, 1756284819852047 (2019).
- Törnblom, H. Treatment of gastrointestinal autonomic neuropathy. Diabetologia. 59 (3), 409-413 (2016).
- Grover, M., Farrugia, G. & Stanghellini, V. Gastroparesis: A turning point in understanding and treatment. Gut. 68 (12), 2238-2250 (2019).