This in vitro study compared four static surgical guide designs and dynamic navigation for mandibular free-end implant placement. Progressive guide-design modifications reduced most placement deviations, while dynamic navigation demonstrated selected advantages in angular and apical control at the distal #37 site.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
In Vitro Evaluation of Digitally Designed Surgical Guides for Free-end Mandibular Implants: Accuracy and Stability of Non-cross-arch Designs
In This Article
Summary
Abstract
Digital surgical guides are widely used in implant dentistry, but implant placement in mandibular free-end regions remains challenging because distal tooth support is limited and guide displacement may occur during drilling. This in vitro study evaluated the placement accuracy and stability of four digitally designed static surgical guide configurations and compared static computer-assisted implant surgery with dynamic navigation in a standardized mandibular distal-extension resin model. A partially edentulous mandibular model involving implant sites #36 and #37 was generated from intraoral scan and cone-beam computed tomography data. Four static guide designs were tested: a conventional unilateral cross-arch tooth-supported guide (GT I), two compact non-cross-arch guides with different supporting-tooth configurations (GT II and GT III), and a non-cross-arch guide with distal micro-screw fixation (GT IV). Postoperative scan data were superimposed onto the virtual plan to quantify angular, coronal, apical, depth, and lateral deviations. Progressive modification from GT I to GT IV reduced most angular and linear deviations at both implant sites. GT IV showed the lowest angular deviation and a favorable overall accuracy and stability profile in most comparisons, although GT III showed a slightly lower apical three-dimensional deviation at site #37. In the static-versus-dynamic comparison, dynamic navigation showed site-specific advantages in angular deviation and apical global deviation at #37, whereas static guidance showed comparable or better values for several measurements at #36. The combined-site comparison did not support uniform superiority of either modality. These findings indicate that guide-support configuration and distal stabilization influence placement accuracy and guide stability in a mandibular free-end resin model. Clinical validation is required before routine treatment recommendations can be made.
Introduction
Dental implant restoration has become an established treatment option for partial and complete tooth loss, and the accuracy of implant placement remains a key determinant of prosthetic fit, peri-implant safety, and long-term functional outcomes1. The development of cone-beam computed tomography (CBCT), intraoral scanning, three-dimensional planning, and additive manufacturing has supported the broader use of computer-assisted implant surgery (CAIS) in clinical implantology2,3. By integrating radiographic and surface-scan data, static surgical guides allow the planned implant position to be transferred to the operative field, providing improved control over drilling direction, depth, and three-dimensional implant placement4.
Two major forms of CAIS are currently used: static computer-assisted implant surgery (S-CAIS) and dynamic navigation. Static guides are widely adopted because they are relatively accessible, do not require real-time tracking, and can be incorporated into routine implant procedures with limited changes to the surgical workflow5. Dynamic navigation, by contrast, provides real-time visual feedback on drill position and angulation, allowing the operator to adjust the trajectory during osteotomy preparation6. Recent systematic reviews have reported favorable accuracy for both static and dynamic approaches, although neither technique eliminates placement deviation entirely, particularly in anatomically restricted sites or regions with limited support7. Prospective clinical evidence also suggests that combined static and dynamic assistance may be useful in selected complex cases, but the relative benefit of dynamic feedback depends on anatomical site, operator control, registration accuracy, and the stability of the baseline guide design8.
Despite these digital advances, the accuracy of static guides remains strongly influenced by support type, guide geometry, sleeve tolerance, printing accuracy, and intraoperative seating stability. Tooth-supported guides generally show favorable accuracy when stable seating is achieved, but mandibular free-end regions remain mechanically challenging because the lack of distal tooth support can permit guide rotation or vertical displacement during drilling9. This problem can be understood as cantilever-related instability, in which a unilateral distal-extension guide is exposed to rotational forces around the remaining supporting teeth. Even small seating errors may be amplified at the apical region, producing angular, coronal, apical, depth, or lateral deviation10.
Several design strategies have been proposed to improve free-end guide stability, including increasing the number of supporting teeth, extending the guide base, enlarging the occlusal support area, using cross-arch stabilization, or adding auxiliary fixation elements11. However, large cross-arch guides may reduce visibility, limit surgical access, complicate insertion and removal, and increase chairside handling difficulty. Mucosa-supported designs may also be less reliable in partially edentulous posterior regions because soft tissue deformation can introduce unpredictable displacement under load12. These limitations have encouraged interest in compact non-cross-arch guide designs that preserve local surgical access while improving resistance to lifting, rotation, and distal micromotion.
In this study, the compact non-cross-arch designs were not intended to create a mechanically locked undercut or snap-fit mechanism. Instead, the modified occlusal support geometry was designed to increase localized contact with occlusal fossae and cusp inclines of the remaining posterior teeth, thereby improving seating support without extending the guide across the full arch. Related non-cross-arch designs incorporating tooth-supported retention and screw-assisted stabilization have been reported previously. Therefore, the present study does not claim to introduce a wholly new category of surgical guide. Its contribution lies in evaluating, under a standardized mandibular free-end resin model, how stepwise changes in supporting-tooth configuration and distal micro-screw fixation affect implant placement accuracy and guide stability.
The inclusion of dynamic CAIS in the same experimental setting provided a reference comparison for real-time navigation under the same mandibular distal-extension conditions. Static guide accuracy in free-end regions depends heavily on guide seating, local support, fabrication accuracy, and mechanical stability. Dynamic navigation, by contrast, relies on registration, calibration, real-time trajectory monitoring, and operator response during osteotomy preparation. Comparing these two approaches within the same standardized model allowed the study to examine whether dynamic feedback produced site- or metric-specific accuracy differences, particularly at the more distal #37 site where guide instability was expected to be greater. This comparison was experimentally linked to the GT I-GT IV design analysis by evaluating two strategies for managing the same free-end accuracy problem: mechanical stabilization via guide design and intraoperative correction via navigation.
Accordingly, this in vitro study evaluated four static surgical guide designs for mandibular free-end implant placement: a conventional unilateral cross-arch tooth-supported guide, two compact non-cross-arch guides with different supporting-tooth configurations, and a non-cross-arch guide incorporating distal micro-screw fixation. Implant placement accuracy was assessed at sites #36 and #37 using angular deviation, coronal and apical three-dimensional deviation, depth deviation, and lateral deviation. Static CAIS and dynamic navigation were also compared at the same implant sites to determine whether navigation produced site- or metric-specific differences under the same experimental conditions. The null hypothesis was that there would be no significant differences in implant placement accuracy among the four static guide designs and no significant differences between static and dynamic CAIS at the mandibular free-end sites.
Access restricted. Please log in or start a trial to view this content.
Protocol
The mandibular model was generated from anonymized intraoral scan and cone-beam computed tomography data obtained from one adult volunteer. The use of human-derived imaging data was reviewed and approved by the Human Research Ethics Committee, Universiti Sains Malaysia (JEPeM-USM; USM/JEPeM/PP/23110816). Written informed consent was obtained from the volunteer for the use of anonymized intraoral scan and CBCT data for in vitro model fabrication, surgical guide design, and accuracy analysis. All identifying information was removed before data processing, and only anonymized STL and DICOM files were used in the experiment. The chemicals, reagents, and tools used in the protocol are listed in the Table of Materials.
1. Study design
This in vitro experimental study evaluated the placement accuracy and mechanical stability of four static surgical guide configurations for mandibular free-end implant placement and compared static computer-assisted implant surgery with dynamic navigation. Two implant sites were evaluated in the left posterior mandible, corresponding to FDI #36 and #37. The overall experimental workflow is shown in Figure 1.
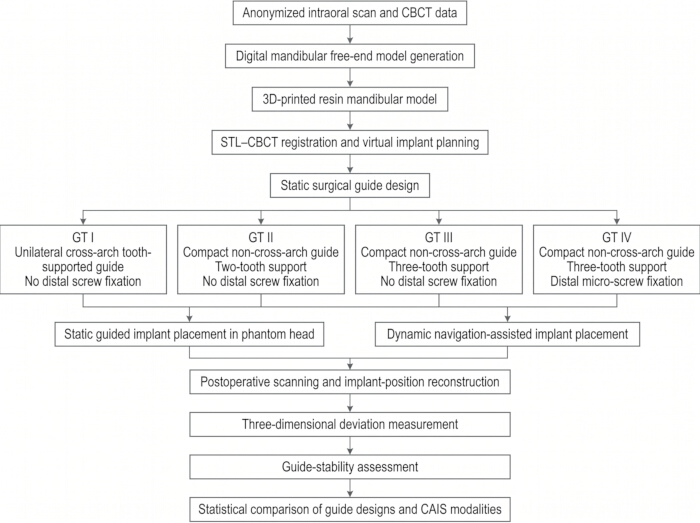
Figure 1: Study design. Schematic overview of the in vitro experimental workflow, including anonymized scan-data processing, resin mandibular model fabrication, STL–CBCT registration, virtual implant planning, static guide design, static and dynamic CAIS implant placement, three-dimensional deviation measurement, guide-stability assessment, and statistical analysis. Please click here to view a larger version of this figure.
Four static guide designs were tested. GT I was a conventional unilateral cross-arch tooth-supported guide and served as the control design. GT II was a compact non-cross-arch guide supported by two adjacent teeth. GT III was a compact non-cross-arch guide supported by three adjacent teeth. GT IV used the same three-tooth non-cross-arch support configuration as GT III and added distal micro-screw fixation at the free-end region.
For the static-versus-dynamic CAIS comparison, the static CAIS arm used the GT I conventional unilateral cross-arch tooth-supported guide. GT I was selected as the static comparator because it represented the conventional tooth-supported static guide configuration against which dynamic navigation could be compared under the same mandibular distal-extension conditions. The GT I-GT IV comparison was treated as a separate guide-design optimization experiment.
2. Experimental unit, replication structure, and sample-size basis
For the static guide-design comparison, the experimental unit was one implant placement performed at one implant site using one independently printed mandibular model and one independently fabricated guide. For each guide design, 20 implant placements were performed at site #36 and 20 at site #37. Thus, n = 20 referred to 20 independent model-guide-placement assemblies per guide design per implant site, not repeated measurements of the same implant.
For the static-versus-dynamic CAIS comparison, 20 implant placements were included per modality at each implant site. Each model was used for only one implant-placement condition. Repeated measurements of the same implant were averaged and were not treated as independent observations.
The sample size was based on previous in vitro CAIS accuracy studies using angular and linear implant-placement deviations as primary outcomes13. An expected between-group difference of approximately 0.35 mm in apical three-dimensional deviation or 1.0° in angular deviation was used. Assuming a standard deviation of 0.35-0.50 mm for linear deviation and 0.8-1.0° for angular deviation, α = 0.05, and 80% power, at least 16 implant placements per group were required. Twenty placements per group were used to allow for unusable scans or guide misfit.
3. Randomization, operator control, and blinding
Two operators performed all implant-placement procedures. Both operators had prior training in static guided implant placement and dynamic navigation. Before formal data collection, each operator completed five non-study training runs for static guidance and five for dynamic navigation.
The testing order of GT I-GT IV, implant site order, and static-versus-dynamic procedure order were randomized using computer-generated sequences. Operator assignment was balanced across guide designs, implant sites, and CAIS modalities, so that each operator completed an equal number of placements within each experimental condition. The allocation sequence was generated before model preparation and was followed during implant placement to reduce operator-related learning, fatigue, and modality-preference effects.
Postoperative STL files and planning files were coded before measurement. The assessors who measured implant deviations were blinded to guide design, implant site, CAIS modality, and operator identity.
4. Digital model acquisition and resin model fabrication
A full-arch mandibular intraoral scan was obtained using a chairside optical intraoral scanner with nominal trueness below 20 µm, and the scan was exported as an STL file. CBCT data were acquired using a dental CBCT unit with the following parameters: 90 kVp, 8 mA, 8 cm × 8 cm field of view, 0.20 mm voxel size, and 14 s exposure time. DICOM files were exported for implant planning.
The mandibular STL file was imported into three-dimensional modeling software. Scan artifacts were removed, open mesh areas were repaired, and the left posterior mandibular region was standardized as a distal-extension edentulous condition involving #36 and #37. The adjacent teeth were preserved for guide support.
The mandibular model was fabricated using a stereolithography three-dimensional printer and rigid dental model resin. The model was printed at a 50 µm layer thickness, with the occlusal plane oriented approximately 30° to the build platform. After printing, the model was washed twice in 95% isopropyl alcohol for 5 min each, air-dried for 20 min, and post-cured for 30 min at 405 nm. Support structures were removed only from non-contact surfaces.
Each printed model was scanned with a desktop optical laboratory scanner with a nominal accuracy of 10 µm. The printed-model STL file was compared with the original design file using three-dimensional inspection software. The model was accepted when the mean surface deviation was below 0.10 mm and the maximum local deviation at guide-supporting tooth surfaces was below 0.20 mm. The printed mandibular model is shown in Figure 2A, and the standardized free-end region used for guide support and implant placement is shown in Figure 2B.
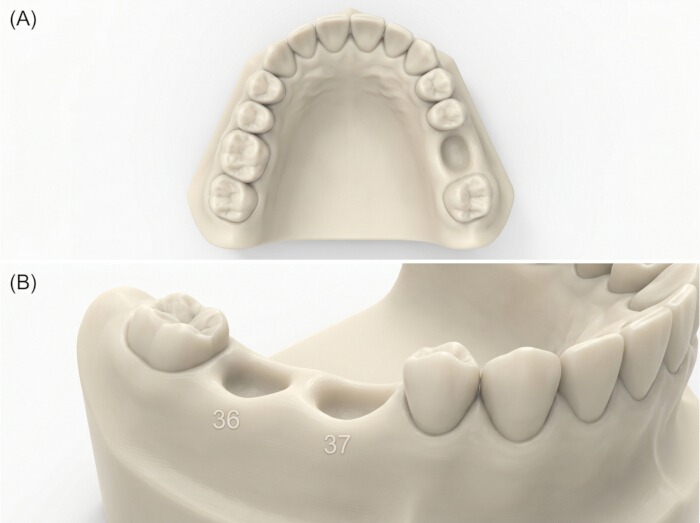
Figure 2: Mandibular resin model used in the in vitro experiment. (A) Three-dimensional printed mandibular resin model with standardized implant sites at #36 and #37. (B) Close-up view of the left mandibular free-end region showing the edentulous implant area and adjacent teeth used for guide support. Please click here to view a larger version of this figure.
5. STL-CBCT registration and virtual implant planning
The verified model STL file and CBCT DICOM dataset were imported into implant planning software. Registration was performed using tooth-surface-based best-fit alignment. Stable dental landmarks were used for initial alignment, followed by surface-based registration of the dental arch. The edentulous implant-bed region and artifact-prone surfaces were excluded from final registration.
Registration was checked in axial, coronal, sagittal, and cross-sectional views. Registration was accepted only when the mean alignment error was ≤0.25 mm. Registration was repeated if this threshold was exceeded. This threshold was used for preoperative STL-CBCT registration because this step involved cross-modality alignment between surface-scan and CBCT-derived geometry. A registration error at this stage could be transferred to implant planning, guide design, and subsequent deviation measurement.
Two tissue-level implants were planned at sites #36 and #37. The planned implants had a diameter of 4.1 mm and a length of 10 mm. The same planned implant positions were used for all static guide groups and for the dynamic navigation comparison. The virtual implant plan was controlled for mesiodistal spacing, buccolingual position, implant depth, parallelism, and distance from the mandibular canal.
6. Static surgical guide design
Four guide designs were created using dental guide-design software. The same implant positions, sleeve system, sleeve height, and drilling trajectory were used for all guide groups. The guide body thickness was set at 2.5 mm, the tooth-surface relief space at 0.05 mm, the sleeve inner diameter at 5.0 mm, the sleeve height at 5.0 mm, and the sleeve offset from the implant platform at 9.0 mm. All guides were designed for fully guided sequential drilling.
The 0.05 mm tooth-surface relief was used to standardize close guide-tooth adaptation in the rigid resin model. It was not intended to create a snap-fit mechanism, force the guide beyond the height of contour, or produce true mechanical locking into undercuts. Full seating was verified before implant placement, and no guide was forcibly seated.
GT I was designed as a unilateral cross-arch tooth-supported guide without distal screw fixation. GT II was designed as a compact non-cross-arch guide supported by two adjacent teeth mesial to the free-end region. GT III was designed as a compact non-cross-arch guide supported by three adjacent teeth. GT IV used the same three-tooth support configuration as GT III and included one distal micro-screw fixation channel. The buccolingual cross-sectional structure of GT I is shown in Figure 3A, and the corresponding non-cross-arch GT II-GT IV design concept is shown in Figure 3B.
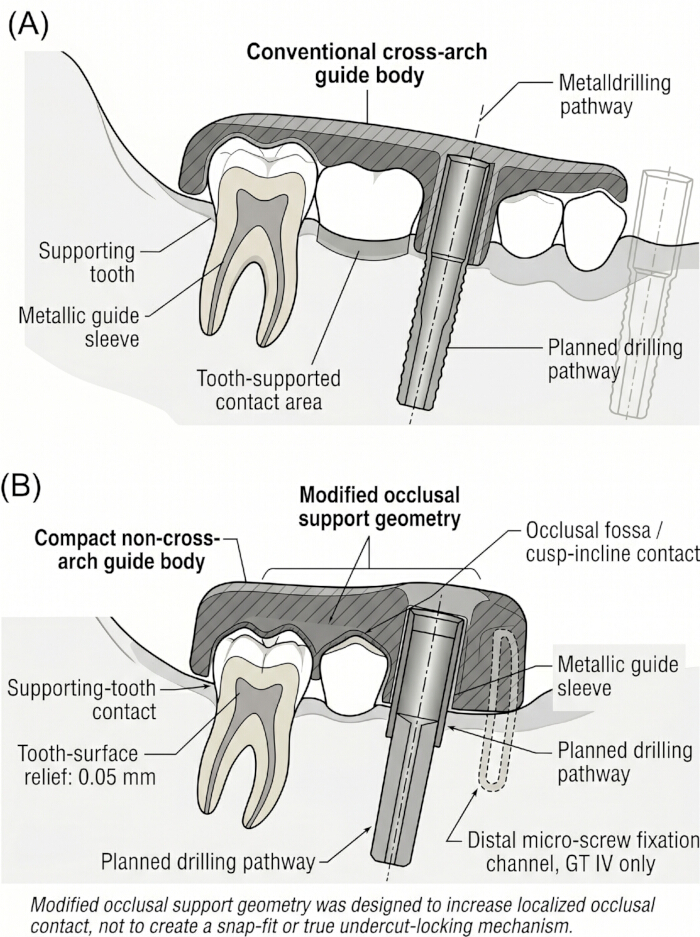
Figure 3: Buccolingual cross-sectional comparison of static guide-design concepts. (A) Conventional unilateral cross-arch tooth-supported guide design without distal screw fixation. (B) Compact non-cross-arch guide-design concept showing modified occlusal support geometry, localized occlusal-fossa and cusp-incline contact, supporting-tooth contact, tooth-surface relief, and the guide-sleeve pathway. The modified occlusal support geometry was designed to improve seating support and resistance to lifting or rotation and was not intended as a snap-fit or true undercut-locking mechanism. Please click here to view a larger version of this figure.
For GT IV, the micro-screw channel diameter was set at 1.5 mm for a 1.5 mm × 8.0 mm fixation screw. The channel was positioned distal to the planned implant sites and angled approximately 20° relative to the occlusal plane to avoid interference with the implant osteotomy path and guide sleeve.
The compact non-cross-arch guides used a modified occlusal support geometry designed to increase localized contact with occlusal fossae and cusp inclines of the remaining posterior teeth. This geometry was used to improve resistance to lifting and rotation without extending the guide across the full arch. It was not designed or interpreted as true undercut locking.
7. Surgical guide fabrication and seating verification
All surgical guides were printed using a stereolithography printer and biocompatible surgical-guide resin. Guides were printed at a 50 µm layer thickness, washed in 95% isopropyl alcohol for 5 min, dried for 20 min, and post-cured for 30 min at 405 nm. Metallic sleeves were inserted according to the sleeve system specification and checked for full seating.
The conventional GT I guide body is shown in Figure 4A, and the metallic guide sleeve used to standardize the drilling path is shown in Figure 4B. Representative compact guide structures are shown for GT II in Figure 5A, GT III in Figure 5B, and GT IV in Figure 5C.
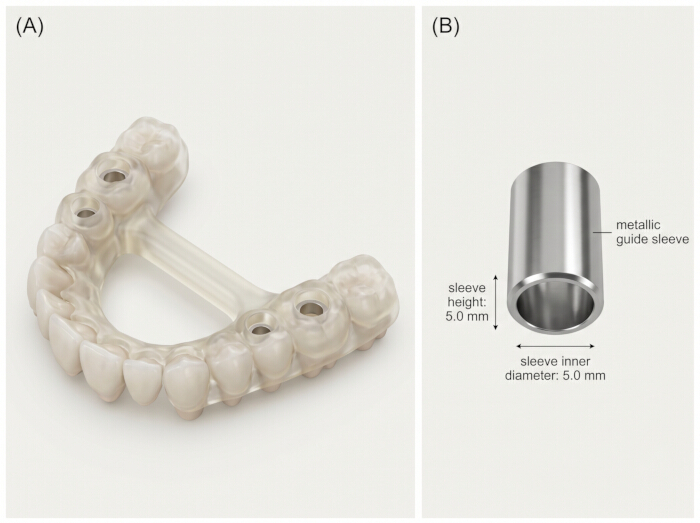
Figure 4: Structural components of the static guided implant system. (A) GT I conventional unilateral cross-arch tooth-supported guide body. (B) Metallic guide sleeve used to standardize the drilling pathway, sleeve diameter, and sleeve height across guide designs. Please click here to view a larger version of this figure.
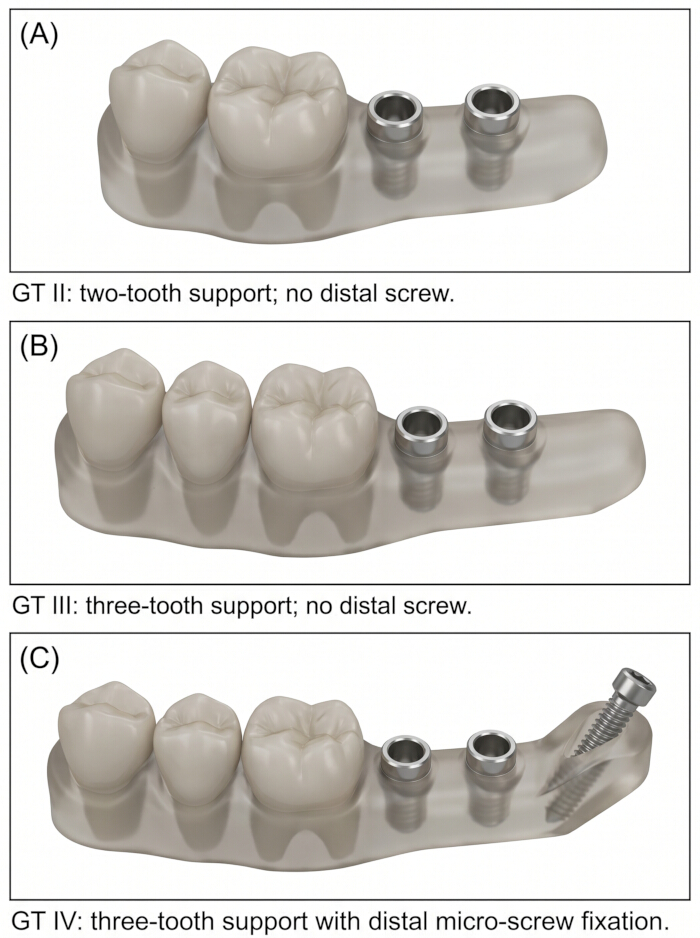
Figure 5: Compact non-cross-arch guide designs. (A) GT II guide with two-tooth occlusal support and no distal screw fixation. (B) GT III guide with three-tooth occlusal support and no distal screw fixation. (C) GT IV guide with three-tooth occlusal support and distal micro-screw fixation. Please click here to view a larger version of this figure.
No uncontrolled finishing of the intaglio surface was performed. Only printing supports outside tooth-contact surfaces and sleeve-contact areas were removed. Tooth-contact areas, modified occlusal support areas, and sleeve channels were not manually adjusted.
Before implant placement, each guide was seated on the corresponding model. Full seating was confirmed visually, by tactile inspection, and with a 50 µm fit-checking silicone layer. Guides showing rocking, incomplete seating, sleeve deformation, visible cracks, or misfit greater than 0.20 mm were excluded and reprinted.
8. Dynamic navigation setup and calibration
Dynamic navigation-assisted implant placement was performed using an optical tracking navigation system with a tracking camera, model tracker, handpiece tracker, calibration tool, and planning-navigation software. The same locked virtual implant plan used for the static guide groups was imported into the navigation software. Dynamic navigation was included because real-time tracking may provide additional intraoperative control over entry point, angulation, and depth, although its accuracy can vary by site and metric.
The mandibular model was fixed in a dental phantom head, and a rigid tracking marker was attached to the model base. The model was registered using tooth-surface tracing and predefined fiducial landmarks. Registration was verified by touching five anatomical landmarks on the printed model and comparing them with the corresponding virtual positions. Registration was accepted when the system-reported error was ≤0.50 mm. This acceptance threshold followed the navigation system workflow and was distinct from the stricter postoperative scan-registration threshold used for deviation measurement. Across the 40 dynamic navigation placements, the mean system-reported registration error was 0.34 ± 0.07 mm, with a range of 0.21-0.48 mm. No registration exceeded the predefined 0.50 mm acceptance threshold. Two registrations approached the acceptance limit and were repeated before osteotomy preparation until the system-reported registration error returned below the threshold.
The handpiece and drill axis were calibrated before each drilling sequence. Calibration was repeated if the drill-axis verification error exceeded 0.30 mm. During osteotomy preparation, the navigation display was monitored for entry point, angulation, and depth.
9. Implant placement procedure
The printed mandibular model was secured in a dental phantom head with a mechanical clamp. Model stability was checked before drilling. The phantom-head setup is shown in Figure 6. No artificial mucosa layer was used; therefore, the experiment simulated a rigid resin mandibular model rather than biological soft tissue.
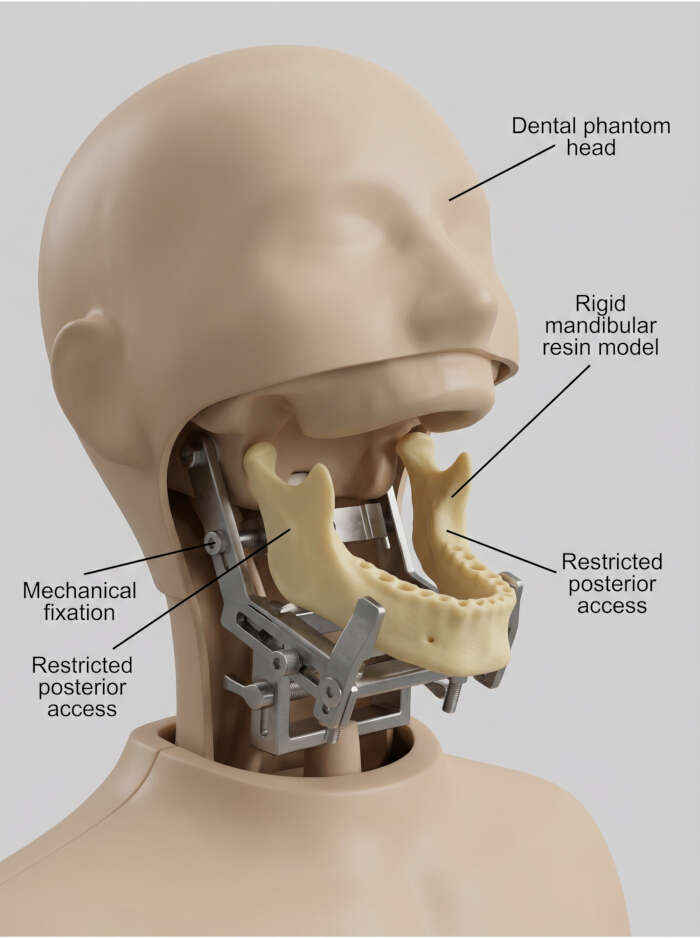
Figure 6: Phantom-head setup for implant placement. A three-dimensional printed mandibular resin model secured in a dental phantom head to provide standardized model fixation and restricted posterior access during in vitro implant placement. No artificial mucosa layer was used. Please click here to view a larger version of this figure.
For static CAIS, the assigned guide was seated, and a complete fit was verified before drilling. For GT IV, the distal micro-screw was inserted through the fixation channel and tightened to 8 N·cm using a calibrated torque wrench. Screw fixation was performed only for GT IV. The GT IV-guided drilling and implant-placement procedure is illustrated in Figure 7A–E.
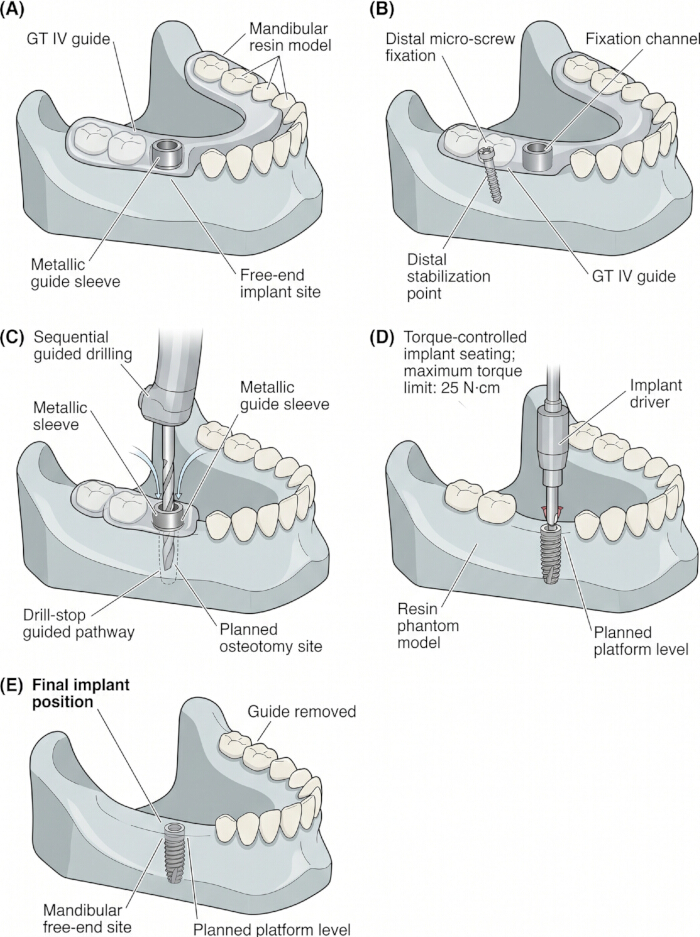
Figure 7: GT IV-guided implant-placement procedure. (A) Seating of the GT IV guide on the mandibular resin model. (B) Distal micro-screw fixation through the guide channel. (C) Sequential guided drilling through the metallic sleeve. (D) Torque-controlled implant seating at the planned mandibular free-end site, with the driver set to a maximum torque limit of 25 N·cm. (E) Final implant position after guide removal. Please click here to view a larger version of this figure.
A fully guided drilling protocol was used. Sequential drilling was performed with a pilot drill, intermediate drill, and final drill. Drilling was performed at 800 rpm under continuous external saline irrigation. Depth was controlled using the guide sleeve and drill-stop system.
After osteotomy preparation, the implant was inserted using a calibrated torque-controlled driver set to a maximum torque limit of 25 N·cm. This value was used as a standardized procedural limit for seating the implant in the resin phantom model, not as evidence of biological primary stability or as a direct simulation of clinical insertion torque in human bone. The final implant platform was seated to match the planned platform level. After placement, the osteotomy site and surrounding resin were inspected for socket stripping, resin cracking, perforation, deformation, or abnormal drill resistance.
For dynamic CAIS, the implant osteotomy was prepared under real-time navigation without a static guide. The same drilling sequence, drilling speed, irrigation condition, implant system, and torque-controlled seating protocol were used. Entry point, angulation, and depth were controlled using the navigation display.
Because the models were resin-based and did not reproduce cortical or cancellous bone architecture, viscoelasticity, periodontal ligament behavior, blood, saliva, or soft-tissue deformation, biological primary stability was not interpreted. Insertion torque was recorded only as a procedural consistency indicator.
10. Postoperative scanning and implant-position acquisition
Scan bodies compatible with the implant system were attached after implant placement and checked for full seating. Each model was scanned using a desktop optical laboratory scanner with a nominal accuracy of 10 µm. The postoperative scan was exported as an STL file.
The postoperative STL file was imported into deviation-analysis software. The scan-body library was used to reconstruct the actual implant position. The postoperative model was superimposed onto the preoperative planned model using a two-step workflow: initial landmark-based alignment using stable tooth surfaces, followed by best-fit alignment using the remaining dental arch. Implant sites, scan bodies, sleeve-contact areas, and damaged regions were excluded from registration.
Files were accepted when the mean postoperative registration error was ≤0.10 mm. Files exceeding this value were rescanned. If the second scan still exceeded the threshold, the implant placement was excluded and documented. This stricter threshold was used at the postoperative deviation-measurement stage to reduce measurement error that could enter the final planned-versus-placed implant calculation.
11. Three-dimensional deviation measurement
Implant deviation was measured using three-dimensional inspection software. The planned implant position was obtained from the locked virtual plan, and the actual implant position was reconstructed from the postoperative scan-body file. The planned and actual implant axes were extracted and visually confirmed before measurement. The deviation-measurement workflow is shown in Figure 8.
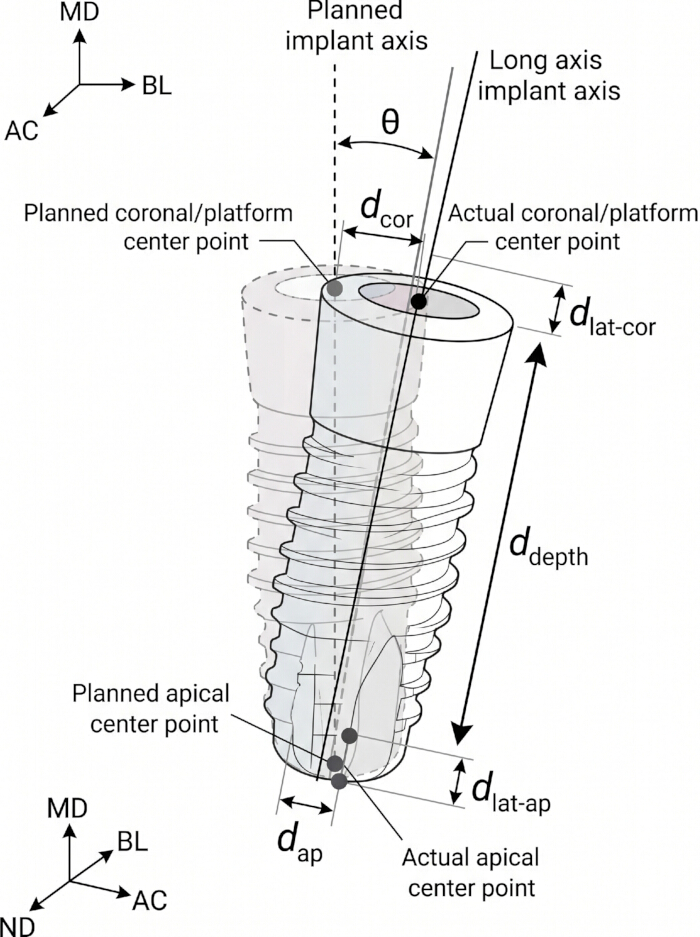
Figure 8: Deviation measurement between planned and placed implants. Schematic illustration of planned-versus-placed implant deviation analysis. θ indicates angular deviation; d_cor indicates coronal three-dimensional deviation; d_ap indicates apical three-dimensional deviation; d_depth indicates depth (apicocoronal) deviation; d_lat-cor indicates coronal lateral deviation; and d_lat-ap indicates apical lateral deviation. Please click here to view a larger version of this figure.
Angular deviation, coronal three-dimensional deviation, apical three-dimensional deviation, depth deviation, mesiodistal deviation, buccolingual deviation, and apicocoronal deviation were measured. These outcomes are standard metrics for evaluating planned-versus-placed implant accuracy in static and dynamic CAIS studies14.
Angular deviation was defined as the angle between the planned and placed implant axes. Coronal three-dimensional deviation was defined as the Euclidean distance between the planned and actual implant-platform center points. Apical three-dimensional deviation was defined as the Euclidean distance between the planned and actual implant-apex center points. Depth deviation was defined as vertical displacement along the implant-axis direction. Mesiodistal and buccolingual deviations were calculated by decomposing positional differences along the corresponding coordinate axes.
Two trained assessors independently measured all outcomes. Each outcome was measured three times per implant, and the mean value was used for statistical analysis. Interobserver reliability was evaluated using the intraclass correlation coefficient. If assessor differences exceeded 0.20 mm for linear deviation or 0.40° for angular deviation, a third assessor repeated the measurement, and the final value was determined by consensus.
12. Guide-stability assessment
Guide stability was evaluated using micromotion testing, insertion-removal cycling, and screw-fixation testing. Stability testing was performed on model-guide assemblies separate from those used for the primary implant-placement accuracy analysis, so that repeated guide insertion, screw fixation, and removal did not introduce wear into the assemblies used for deviation measurement.
For micromotion testing, the guide was seated on the printed mandibular model, and the model-guide assembly was fixed in a mechanical testing device. A digital displacement gauge with 1 µm resolution was positioned at the distal end of the guide. Three standardized low-magnitude loads were applied: a horizontal shear force of 5 N, a vertical axial pressure of 10 N, and a mesiodistal interference force of 3 N. These magnitudes were selected after pilot testing to detect guide micromotion without producing visible resin damage, guide fracture, or permanent deformation. They were not intended to reproduce full intraoperative masticatory loading, but to provide comparable stress conditions across guide designs. Each load was applied 10 times per guide, and the mean displacement was recorded in micrometers.
For repetitive-use stability, 30 insertion-removal cycles were performed for each guide. One cycle consisted of complete guide seating, visual confirmation of fit, screw locking for GT IV, and guide removal. After 30 cycles, micromotion testing was repeated. The guides were inspected for cracks, sleeve loosening, sleeve enlargement, deformation, tooth-contact wear, and loss of seating stability.
For screw-fixation stability, only GT IV was evaluated because distal micro-screw fixation was incorporated only in this design. The fixation screw was tightened to 8 N·cm before testing. Removal torque was measured after micromotion testing and after insertion-removal cycling. The difference between insertion torque and removal torque was recorded. Visible thread damage, resin damage around the screw hole, or guide fracture was recorded as mechanical failure.
13. Statistical analysis
Data were analyzed using commercial statistical software and an open-source statistical computing environment. Normality was assessed using the Shapiro-Wilk test, and homogeneity of variance was assessed using Levene’s test. Continuous variables were summarized as mean ± standard deviation or median and interquartile range according to distribution. Two-tailed tests were used, and statistical significance was set at P < 0.05.
For the GT I-GT IV static guide-design comparison, one-way ANOVA with Bonferroni post-hoc correction was used when assumptions were satisfied. Welch ANOVA with Games-Howell post-hoc testing was used when variance was unequal. Kruskal-Wallis testing with Dunn’s post-hoc comparison was used for non-normally distributed data. Effect sizes were reported as η2 for ANOVA-based comparisons and ε2 for non-parametric comparisons.
For the static-versus-dynamic CAIS comparison, independent-samples t-tests or Mann-Whitney U tests were used according to data distribution. Because the static and dynamic groups were generated from separate model assemblies, they were analyzed as independent groups. For combined-site analyses, the pooled mean and standard deviation were recalculated from the final site-specific datasets with n = 20 per site and n = 40 per modality. Combined values were not taken from an earlier spreadsheet version and were checked against the site-specific means before reporting.
For the #36-versus-#37 site comparison, paired t-tests or Wilcoxon signed-rank tests were used according to distribution. Site comparisons were reported separately for static CAIS and dynamic navigation.
For micromotion and insertion-removal cycling data, pre-cycling and post-cycling displacement values were compared using paired t-tests or Wilcoxon signed-rank tests. Differences among GT I-GT IV were analyzed using one-way ANOVA or Kruskal-Wallis tests. Because screw fixation was present only in GT IV, screw removal torque was analyzed descriptively and was not compared across all four guide designs.
Interobserver reliability was assessed using a two-way random-effects intraclass correlation coefficient. ICC values of 0.75-0.89 were interpreted as good reliability, and values ≥0.90 were interpreted as excellent reliability.
Access restricted. Please log in or start a trial to view this content.
Results
This in vitro study evaluated implant placement accuracy and guide stability in a standardized mandibular free-end resin model. The primary accuracy outcomes were angular deviation, coronal three-dimensional deviation, apical three-dimensional deviation, depth deviation, and lateral deviation. Analyses were performed at implant sites #36 and #37. The static guide-design comparison included GT I, GT II, GT III, and GT IV, while the modality comparison included static CAIS and dynamic navigation.
Access restricted. Please log in or start a trial to view this content.
Discussion
This in vitro study evaluated the effects of static guide-design optimization and dynamic navigation on implant-placement accuracy and guide stability in a standardized mandibular free-end resin model. The main finding was that progressive modification from GT I to GT IV generally reduced angular, coronal, depth, lateral, and micromotion values. However, the improvement was not uniform across all outcomes. GT IV showed the most favorable overall profile in most measured parameters, but GT III showed a slightly l...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors have nothing to disclose.
Acknowledgements
This research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Calibrated torque wrench | Straumann | Ratchet / torque control device | Used for 8 N·cm GT IV micro-screw fixation and 25 N·cm implant insertion. |
| Dental model resin | Formlabs | Model Resin V3 | Used for printing rigid mandibular resin models. |
| Dental phantom head | Nissin Dental Products | Simple Manikin III | Used for standardized fixation of the mandibular resin model and restricted posterior access simulation. |
| Desktop laboratory scanner | 3Shape | E4 Lab Scanner | Used for printed-model verification and postoperative STL scanning. |
| Digital displacement gauge | Mitutoyo | ABS Digimatic Indicator, Series 543, 0.001 mm resolution | Used for guide micromotion measurement. |
| Digital force gauge | Mark-10 | Digital force gauge, 0–50 N range | Used to verify 5 N, 10 N, and 3 N loads during stability testing. |
| Dynamic navigation system | ClaroNav | Navident EVO | Used for dynamic navigation-assisted implant placement. |
| Fit-checking silicone | GC Corporation | Fit Checker Advanced Blue | Used to verify surgical guide seating and detect high-contact areas. |
| Guided implant driver | Straumann | Tissue Level RN guided implant driver | Used for implant insertion to the planned platform level. |
| Guided surgery drill handles | Straumann | Guided drill handles, Ø2.2–4.2 mm | Used with the Ø5 mm guide sleeve during sequential guided drilling. |
| Guided surgery drill set | Straumann | Straumann Guided Surgery Instruments / VeloDrill system | Used for pilot, intermediate, and final drilling. |
| Implant planning and guide-design software | Straumann / Dental Wings | coDiagnostiX | Used for STL–CBCT registration, virtual implant planning, and guide design. |
| Isopropyl alcohol | Sigma-Aldrich / Merck | 2-Propanol, ≥99.5% | Used for washing printed resin models and guides; prepared as 95% isopropyl alcohol for protocol use. |
| Mechanical model clamp | Generic laboratory fixture | Stainless-steel adjustable clamp | Used for rigid fixation of the resin mandibular model. |
| Mechanical testing frame | Mark-10 / Instron | Manual force test stand | Used for standardized loading during micromotion testing. |
| Metallic guide sleeve | Straumann | T-sleeve, Ø5 mm, H5 mm, REF 034.053 | Used for all static guide designs to standardize the drilling path. |
| Navigation calibration kit | ClaroNav | Navident calibration kit | Used for handpiece and drill-axis calibration. |
| Navigation tracker set | ClaroNav | Navident model tracker and handpiece tracker | Used for model and handpiece tracking during dynamic navigation. |
| Open-source statistical environment | R Foundation | R version 4.3 or later | Used for supplementary statistical checks and effect-size calculations. |
| Resin curing station | Formlabs | Form Cure | Used for 405 nm post-curing. |
| Resin washing station | Formlabs | Form Wash | Used for isopropyl alcohol washing after printing. |
| Scan body | Straumann | RN scanbody compatible with Tissue Level RN platform | Used for postoperative implant-position reconstruction. |
| Spreadsheet software | Microsoft | Excel 365 | Used for data organization and table preparation. |
| Statistical software | IBM | IBM SPSS Statistics 29.0 | Used for normality tests, ANOVA, t-tests, non-parametric tests, and ICC analysis. |
| Surgical guide resin | Formlabs | Surgical Guide Resin | Used for printing GT I–GT IV surgical guides. |
| Surgical motor and handpiece | NSK / W&H | Implant surgical motor with 20:1 contra-angle | Used for guided drilling at 800 rpm under continuous external saline irrigation. |
| Three-dimensional inspection software | ZEISS | ZEISS INSPECT Optical 3D | Used for surface-deviation inspection and planned-versus-placed implant analysis. |
| Three-dimensional modeling software | Materialise | 3-matic Medical 19.0 | Used for STL cleanup, mesh repair, and mandibular model preparation. |
| Three-dimensional printer | Formlabs | Form 3B+ | Used for stereolithography printing of mandibular resin models and surgical guides. |
| Tissue-level implant | Straumann | Standard Plus Implant, Ø4.1 mm RN, SLActive, 10 mm, REF 033.562G | Used at sites #36 and #37 in all groups. |
| Titanium micro-screw | Dentium / Jeil Medical | Orthodontic micro-screw, 1.5 mm × 8.0 mm | Used only for distal fixation of GT IV. |
| Table note: Equivalent products may be used if they provide the same technical function and measurement precision. Scanner accuracy, printer layer thickness, sleeve dimensions, implant dimensions, guide resin type, navigation registration threshold, torque settings, and displacement-gauge resolution should remain consistent with the protocol. |