Rapid diagnosis of Legionella pneumophila infection in critically ill patients remains challenging. This retrospective cohort study evaluates serum endotoxin quantification using a Limulus amebocyte lysate assay as an adjunctive biomarker to help differentiate Legionella infection from other pathogens and guide early antimicrobial therapy.
Research Article
Serum Endotoxin as a Diagnostic Biomarker for Legionella pneumophila in Gram-Negative Infections
In This Article
Summary
Abstract
Rapid and accurate differentiation of Legionella pneumophila infections from other gram-negative bacterial infections remains a significant challenge in intensive care medicine. Despite its relatively low in vitro endotoxic activity, clinical observations have suggested elevated circulating endotoxin levels in patients with legionellosis. This retrospective cohort study analyzed 118 critically ill patients with microbiologically confirmed infections admitted to an intensive care unit between January 2020 and December 2023. Patients were classified into four pathogen groups: Legionella pneumophila (n = 18), other gram-negative bacteria (n = 68), gram-positive bacteria (n = 24), and fungi (n = 8). Serum endotoxin levels were measured within 24 h of ICU admission using a kinetic chromogenic Limulus amebocyte lysate assay. Patients with Legionella pneumophila infection demonstrated significantly higher endotoxin levels than those with other gram-negative infections (mean 2.15 ± 1.28 vs 0.61 ± 0.74 EU/mL). Using a threshold of > 2.5 EU/mL, endotoxin quantification showed a sensitivity of 77.8% and specificity of 89.7% for differentiating Legionella infections, with a negative predictive value of 95.3%. Multivariable logistic regression indicated that endotoxin > 2.5 EU/mL remained independently associated with Legionella infection (adjusted OR 15.7, 95% CI 3.84–64.2, p < 0.001). These findings suggest that serum endotoxin quantification may serve as a useful adjunctive biomarker to aid early identification of Legionella pneumophila infection in critically ill patients.
Introduction
The clinical recognition and timely treatment of Legionella pneumophila infections represent one of the most formidable challenges in contemporary critical care medicine, where diagnostic delays can precipitate catastrophic outcomes in vulnerable patients. This fastidious, gram-negative bacterium causes severe pneumonia with mortality rates ranging from 25% to 50% in hospitalized patients, particularly those requiring intensive care support1. The organism's unique intracellular lifestyle within alveolar macrophages, coupled with its fastidious growth requirements and resistance to standard antimicrobial agents, creates a perfect storm of diagnostic and therapeutic complexity that has frustrated clinicians for decades2.
Current diagnostic approaches for legionellosis remain frustratingly inadequate for the urgency demanded by critically ill patients. The gold standard urinary antigen test, while specific, detects only L. pneumophila serogroup 1, which accounts for approximately 80–90% of infections, leaving a significant diagnostic gap for other serogroups and species3. Culture methods, though comprehensive, require specialized buffered charcoal yeast extract media and typically yield results only after 48–72 h, a delay that can prove fatal in septic patients4. Molecular diagnostic techniques, including polymerase chain reaction and metagenomic next-generation sequencing, while increasingly sensitive and rapid, remain expensive and are not universally available, particularly in resource-limited settings or during off-hours when immediate clinical decisions are most critical5.
The diagnostic complexity is further compounded by the nonspecific clinical presentation of legionellosis, which can closely mimic other forms of severe community-acquired pneumonia. While classical teaching emphasizes distinctive features such as hyponatremia, neurological symptoms, and gastrointestinal manifestations, these findings are neither universally present nor sufficiently specific to reliably distinguish Legionella from other bacterial pathogens6. Consequently, clinicians often resort to empirical broad-spectrum antimicrobial therapy that may inadequately cover Legionella or unnecessarily expose patients to agents with significant toxicity profiles, contributing to the growing crisis of antimicrobial resistance7.
This diagnostic dilemma has intensified the search for rapid, reliable biomarkers that can guide early therapeutic decision-making. Traditional inflammatory markers, including C-reactive protein, procalcitonin, and interleukin-6, while elevated in bacterial infections, lack the specificity necessary to differentiate Legionella from other gram-negative pathogens8. More sophisticated approaches, such as host transcriptomic signatures and proteome analysis, though promising in research settings, remain impractical for routine clinical use due to their complexity, cost, and prolonged turnaround times9.
Paradoxically, despite extensive research into Legionella's unique pathophysiology, one of the most fundamental characteristics of gram-negative bacteria, endotoxin production, has received limited attention as a potential diagnostic tool for legionellosis. Lipopolysaccharide (LPS), the major component of the outer membrane of gram-negative bacteria, triggers the host inflammatory cascade that characterizes gram-negative sepsis10. However, Legionella LPS exhibits markedly reduced endotoxic activity compared to prototypical gram-negative pathogens such as Escherichia coli and Pseudomonas aeruginosa, requiring concentrations 100–1000-fold higher to elicit comparable inflammatory responses in laboratory models11. This reduced potency stems from structural differences in the lipid A component, including variations in fatty acid composition and phosphorylation patterns that diminish its recognition by Toll-like receptor 4 and associated signaling pathways12.
Despite this well-established reduction in in vitro endotoxic activity, clinical observations have suggested a curious paradox: patients with Legionella pneumonia often present with severe systemic inflammatory responses indistinguishable from those seen in classic gram-negative sepsis13. This apparent contradiction between laboratory findings and clinical presentations has led to speculation about alternative mechanisms of endotoxin elevation in legionellosis, including massive bacterial lysis during intracellular replication, secondary gut translocation of enterobacterial endotoxin, or enhanced host sensitivity to Legionella LPS in the context of severe illness14.
The clinical measurement of circulating endotoxin has evolved significantly since the development of the Limulus amebocyte lysate (LAL) assay in the 1970s. Initially employed primarily for pharmaceutical quality control, endotoxin quantification has increasingly found applications in clinical medicine, particularly in the diagnosis and prognosis of gram-negative sepsis15. The endotoxin activity assay (EAA), which utilizes patient neutrophils primed by endotoxin-antibody complexes, has demonstrated particular promise in differentiating gram-negative from gram-positive infections, with reported sensitivities of 64–85% and specificities of 91–95%16. However, the specific application of endotoxin quantification to Legionella diagnosis has never been systematically evaluated, representing a significant knowledge gap in the understanding of this challenging pathogen.
The potential clinical utility of endotoxin measurement extends beyond simple pathogen identification. In an era of increasing antimicrobial resistance and growing emphasis on antimicrobial stewardship, rapid diagnostic tools that can guide targeted therapy have become increasingly valuable17. The ability to confidently exclude Legionella infection based on low endotoxin levels could prevent unnecessary exposure to quinolones or macrolides, while elevated levels in appropriate clinical contexts could prompt early Legionella-active therapy before confirmatory test results become available18. Such an approach could potentially improve patient outcomes while simultaneously supporting rational antimicrobial use in intensive care settings.
In practical ICU settings, endotoxin testing could serve as an early adjunctive tool within the diagnostic workflow for severe pneumonia. Because endotoxin quantification can be performed rapidly and is widely available in clinical laboratories, it may provide preliminary information while conventional diagnostic tests, such as urinary antigen assays, culture, or molecular diagnostics, are pending. In this context, endotoxin measurement could complement existing Legionella diagnostic strategies by helping clinicians rapidly assess the likelihood of gram-negative endotoxemia and prioritize Legionella-active antimicrobial therapy when clinical suspicion is high. This study provides the first systematic evaluation of serum endotoxin quantification as a diagnostic biomarker for differentiating Legionella pneumophila from other gram-negative bacterial infections in critically ill patients, addressing this critical knowledge gap and potentially contributing to improved diagnostic approaches for one of critical care's most challenging pathogens.
Protocol
This retrospective cohort study was conducted in a 22-bed medical intensive care unit (ICU) at Zhongshan City People's Hospital, a tertiary academic medical center. The study protocol was approved by the Institutional Review Board of Zhongshan City People's Hospital (Approval Number: 2026-032). Due to the retrospective design and use of de-identified data, the requirement for informed consent was waived, with all procedures ensuring patient confidentiality through anonymization and compliance with the Declaration of Helsinki and relevant data protection laws. Patient selection and study flow are detailed in Figure 1, while endotoxin quantification methods are described below, with results stratified by pathogen groups as shown in Figure 2. All data were extracted from existing medical records and laboratory databases without any prospective interventions or patient contact.
Study population
Researchers included all adult patients (aged ≥18 years) admitted to the ICU between January 2020 and December 2023 who met the following criteria: Inclusion criteria were as follows: Clinical suspicion of severe bacterial infection or sepsis; Positive bacterial culture or molecular diagnostic confirmation; Serum endotoxin measurement within 24 h of ICU admission; and complete clinical and laboratory data available for analysis. Exclusion criteria were as follows: Mixed infections with multiple pathogens; Incomplete diagnostic workup; Recent immunosuppressive therapy that could affect inflammatory response; Chronic inflammatory conditions; Patients who died within 24 h of admission before complete evaluation. Participant characteristics, including demographics, comorbidities, and clinical presentation, were extracted to ensure a representative cohort of critically ill patients with suspected gram-negative infections. No interventions were administered as part of the study, given its retrospective observational nature; control measures focused on standardizing data collection to reduce selection bias.
Microbiological methods
Diagnosis of Legionella pneumophila was established using a combination of urinary antigen testing, culture on buffered charcoal yeast extract agar, and metagenomic next-generation sequencing (mNGS) when available. Urinary antigen testing was used as the primary diagnostic modality because of its rapid turnaround and high clinical sensitivity. Bacterial culture was performed when respiratory specimens were available. mNGS was applied in selected cases where conventional microbiological tests were negative or inconclusive, but clinical suspicion for atypical pathogens remained high. Other bacterial pathogens were identified using standard microbiological methods, including automated blood culture systems, conventional culture techniques, and molecular diagnostics as clinically indicated. All microbiological assessments followed validated laboratory protocols to ensure accuracy and reproducibility. All microbiological testing was performed in the hospital's accredited clinical microbiology laboratory according to standard operating procedures.
Endotoxin quantification
Serum endotoxin levels were measured using a kinetic chromogenic Limulus amebocyte lysate (LAL) assay according to standard laboratory procedures. Blood samples were collected in sterile, pyrogen-free tubes within 24 h of ICU admission. Samples were centrifuged at 3000 × g for 10 min to obtain serum and subsequently stored at −80 °C until analysis. Prior to testing, serum samples were diluted 1 : 10 with endotoxin-free water to reduce potential matrix interference. Endotoxin concentrations were quantified using a portable endotoxin detection system based on the kinetic chromogenic LAL method. Measurements were performed following standardized kinetic detection procedures. The assay detection range was 0.01–10.0 EU/mL, with an inter-assay coefficient of variation < 15%. All samples were analyzed in duplicate, and the mean value was used for statistical analysis. Positive and negative controls provided with the assay system were included in each run to ensure assay reliability and quality control.
Data collection
Clinical data were extracted from electronic medical records using a standardized case report form. Variables included demographics, comorbidities, clinical presentation, severity scores (APACHE II, SOFA), laboratory parameters, antimicrobial therapy, and clinical outcomes. Outcome assessments focused on diagnostic accuracy as the primary endpoint, with secondary endpoints encompassing mortality at 7 days, 28 days, and hospital discharge. Follow-up procedures involved reviewing patient records up to hospital discharge or death to capture complete outcome data. The primary outcome was the diagnostic accuracy of endotoxin quantification for identifying L. pneumophila infections. Secondary outcomes included mortality at 7 days, 28 days, and hospital discharge. Data were categorized into four pathogen groups: Legionella pneumophila (n = 18), other gram-negative bacteria (n = 68), gram-positive bacteria (n = 24), and fungal infections (n = 8).
Statistical analysis
Continuous variables were expressed as mean ± standard deviation (SD) or median (interquartile range, IQR) according to data distribution assessed using the Shapiro–Wilk test. Categorical variables were presented as frequencies and percentages. Differences among groups were compared using one-way analysis of variance (ANOVA) or the Kruskal–Wallis test for continuous variables, and Fisher’s exact test for categorical variables, as appropriate. The diagnostic performance of endotoxin levels for identifying Legionella pneumophila infection was evaluated using receiver operating characteristic (ROC) curve analysis. The optimal cutoff value was determined using Youden’s index. Sensitivity, specificity, positive predictive value, negative predictive value, and likelihood ratios were calculated with corresponding 95% confidence intervals. Univariate logistic regression analysis was first performed to identify potential predictors of Legionella infection. Variables with p < 0.10 in univariate analysis were subsequently entered into a multivariate logistic regression model to determine independent predictors. Adjusted odds ratios (ORs) with 95% confidence intervals were reported. Survival outcomes were analyzed using Kaplan–Meier survival curves, and differences between groups were assessed using the log-rank test. A two-sided p-value < 0.05 was considered statistically significant. All statistical analyses and visualizations were performed using R version 4.3.0.
Results
Study population and baseline characteristics
From an initial screening of 312 ICU admissions, 118 patients met the inclusion criteria and were included in the final analysis cohort. These patients were classified into four pathogen groups: Legionella pneumophila (n = 18), other gram-negative bacteria (n = 68), gram-positive bacteria (n = 24), and fungi (n = 8) (Figure 1). Baseline characteristics were generally comparable across groups (Table 1). Patients with Legionella pneumophila infection showed a higher prevalence of immunosuppression compared with those with other gram-negative infections (22.2% vs 7.4%, p = 0.048). Clinically, Legionella patients more frequently presented with fever (83.3%), cough (100%), and altered mental status (88.9%). Illness severity, assessed by the APACHE II score, was broadly similar across groups, although Legionella cases tended to have slightly higher median scores (28 [IQR 24–36] vs 25 [IQR 18–31] in other gram-negative infections) as shown in Table 1.
Endotoxin levels and diagnostic performance
Infections with Legionella pneumophila were associated with substantially higher endotoxin levels compared with other pathogen groups. The mean endotoxin level was 2.15 ± 1.28 EU/mL in Legionella infections, compared with 0.61 ± 0.74 EU/mL in other gram-negative infections, 0.42 ± 0.58 EU/mL in gram-positive infections, and 0.13 ± 0.15 EU/mL in fungal infections (Figure 2; Table 2). Using a threshold of > 2.5 EU/mL, endotoxin quantification yielded a sensitivity of 77.8% (95% CI: 52.4–93.6) and a specificity of 89.7% (95% CI: 79.9–95.8) for differentiating Legionella infections from other gram-negative infections. The positive predictive value was 66.7% (95% CI: 43.0–85.4) and the negative predictive value was 95.3% (95% CI: 87.1–99.0). Receiver operating characteristic analysis demonstrated good diagnostic performance, with an area under the curve (AUC) of 0.882 (95% CI: 0.809–0.955) (Figure 3; Table 2).
Laboratory biomarkers and clinical correlations
Patients with Legionella pneumophila infections exhibited distinctive laboratory profiles compared with other pathogen groups. Notably, serum sodium levels were significantly lower in Legionella cases (133 ± 9.8 mmol/L) than in other gram-negative infections (142 ± 11.4 mmol/L, p = 0.003). Procalcitonin levels also differed across groups (p = 0.038), with Legionella infections showing a median level of 28.6 ng/mL (IQR 5.2–98.5) compared with 21.3 ng/mL (IQR 0.08–95.6) in other gram-negative infections. White blood cell counts and platelet counts tended to be lower in Legionella infections (9.24 ± 7.15 × 10³/µL and 186 ± 78 × 103/µL, respectively) than in other gram-negative infections (14.2 ± 10.3 × 10³/µL and 198 ± 92 × 103/µL), although these differences did not reach statistical significance. These laboratory patterns complemented the endotoxin findings described above (Table 3).
Clinical outcomes and endotoxin stratification
Stratification by endotoxin levels revealed that patients with endotoxin >2.5 EU/mL had greater illness severity and distinct clinical characteristics compared with those with lower endotoxin levels. The high-endotoxin group was strongly enriched for Legionella pneumophila infections (66.7% vs 4.1%, p < 0.001) and received Legionella-active antimicrobial therapy more frequently (76.2% vs 18.6%, p < 0.001). Patients in the high-endotoxin group also had higher illness severity, with a median APACHE II score of 28 (IQR 24–36) compared with 25 (IQR 18–31) in the low-endotoxin group (p = 0.042). Mechanical ventilation was more common among patients with endotoxin >2.5 EU/mL (76.2% vs 58.8%, p = 0.042). Regarding clinical outcomes, 28-day mortality was significantly higher in the high-endotoxin group (38.1% vs 24.7%, log-rank p = 0.035), and ICU length of stay was longer (9 vs 6 days, p = 0.024). Cox proportional hazards analysis demonstrated that endotoxin >2.5 EU/mL was independently associated with increased mortality risk (hazard ratio 2.14, 95% CI 1.08–4.23, p = 0.028) (Figure 4; Table 4).
Multivariate analysis and model performance
Univariable logistic regression analysis identified several factors associated with Legionella pneumophila infection, including endotoxin >2.5 EU/mL (odds ratio [OR] 30.2, 95% CI 8.71–104.7, p < 0.001), hyponatremia <135 mmol/L (OR 5.84, 95% CI 1.98–17.2, p = 0.001), presence of cough (OR 18.4, 95% CI 2.31–146.3, p = 0.006), altered mental status (OR 6.73, 95% CI 1.89–23.9, p = 0.003), and immunosuppression (OR 3.56, 95% CI 1.04–12.2, p = 0.043). In multivariable logistic regression, endotoxin >2.5 EU/mL remained the strongest independent predictor of Legionella infection (adjusted OR 15.7, 95% CI 3.84–64.2, p < 0.001), followed by hyponatremia <135 mmol/L (adjusted OR 4.82, 95% CI 1.26–18.4, p = 0.021) and presence of cough (adjusted OR 12.3, 95% CI 1.34–112.6, p = 0.026). Altered mental status showed a trend toward association but did not reach statistical significance after adjustment (adjusted OR 3.41, 95% CI 0.89–13.1, p = 0.073). The combined prediction model integrating endotoxin levels with clinical variables demonstrated excellent discrimination, with an area under the receiver operating characteristic curve (AUC) of 0.938 (95% CI 0.882–0.994). Model sensitivity and specificity were 83.3% and 91.2%, respectively, with good calibration indicated by the Hosmer–Lemeshow test (χ2 = 6.84, p = 0.553). Comparative analysis showed that the combined endotoxin–clinical model outperformed both endotoxin alone (AUC 0.882) and clinical variables alone (AUC 0.784). DeLong testing confirmed significant improvements in discrimination for the combined model compared with endotoxin alone (p = 0.024) and clinical variables alone (p < 0.001) (Figure 5; Figure 6; Table 5).
DATA AVAILABILITY:
All the raw data generated and analyzed during the current study are available in the supplementary materials.
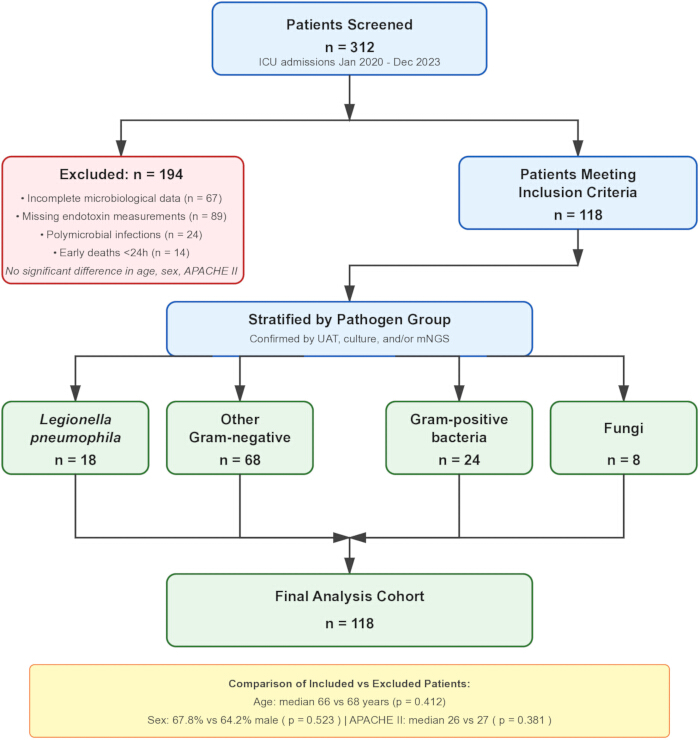
Figure 1: Study flow chart. Flowchart illustrating patient selection for the retrospective cohort study. A total of 312 ICU admissions between January 2020 and December 2023 were screened. 194 patients were excluded, including those with incomplete microbiological data (n = 67), missing endotoxin measurements (n = 89), polymicrobial infections (n = 24), and early deaths within 24 h (n = 14). The final analysis cohort included 118 patients, who were stratified by pathogen group: Legionella pneumophila (n = 18), other gram-negative bacteria (n = 68), gram-positive bacteria (n = 24), and fungi (n = 8). Please click here to view a larger version of this figure.
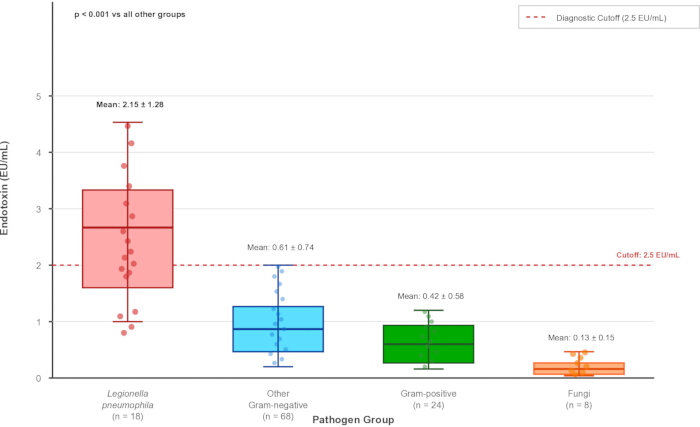
Figure 2: Serum endotoxin levels by pathogen group. Box plot comparison of serum endotoxin levels across different pathogen groups. Legionella pneumophila infections demonstrated significantly elevated endotoxin levels compared to other gram-negative bacteria, gram-positive bacteria, and fungal infections. The horizontal dashed line indicates the optimal diagnostic cutoff of 2.5 EU/mL. Individual data points are overlaid to show the distribution within each group. Please click here to view a larger version of this figure.
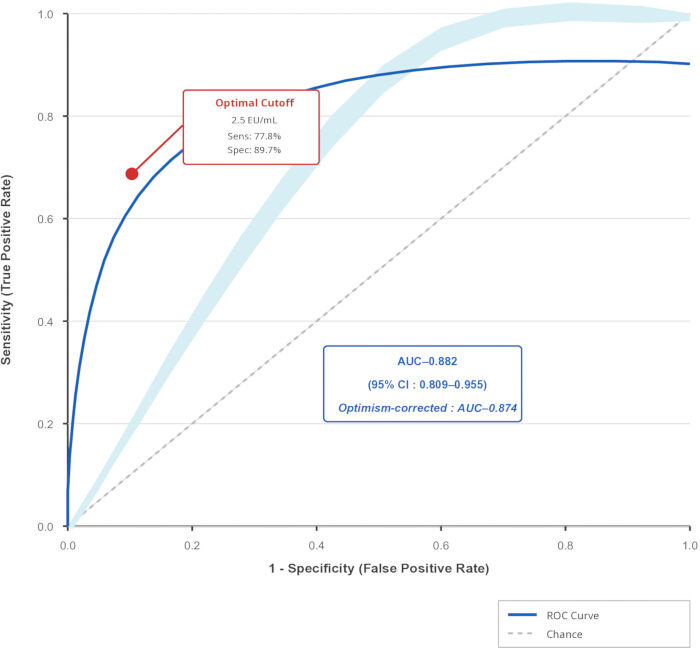
Figure 3: ROC curve analysis for Legionella detection. The area under the curve (AUC) was 0.882 (95% CI: 0.809–0.955), indicating good diagnostic performance. The optimal diagnostic cutoff was 2.5 EU/mL, corresponding to a sensitivity of 77.8% and specificity of 89.7%. The optimism-corrected AUC was 0.874. Please click here to view a larger version of this figure.
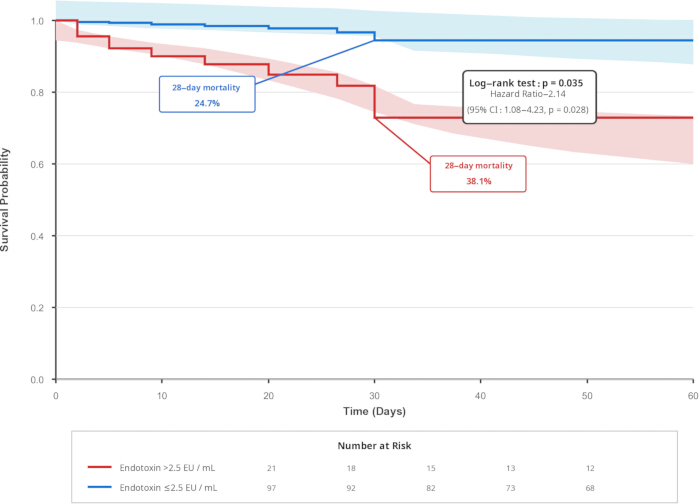
Figure 4: Survival analysis by endotoxin levels. Kaplan–Meier survival curves comparing patients with endotoxin levels >2.5 EU/mL (n = 21) and ≤2.5 EU/mL (n = 97). Patients with endotoxin levels >2.5 EU/mL showed significantly lower survival probability, with 28-day mortality rates of 38.1% versus 24.7%. The difference in survival was statistically significant (log-rank p = 0.035). Cox proportional hazards analysis demonstrated that endotoxin levels >2.5 EU/mL were associated with increased mortality risk (hazard ratio 2.14, 95% CI 1.08–4.23, p = 0.028). Numbers at risk are shown below the survival curves. Please click here to view a larger version of this figure.
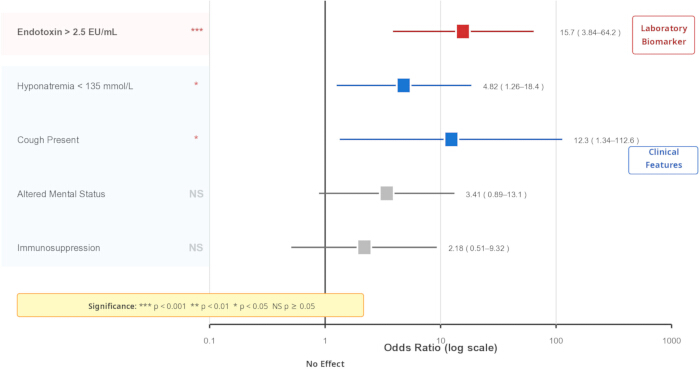
Figure 5: Multivariate analysis forest plot. Adjusted odds ratios (ORs) with 95% confidence intervals are shown for candidate predictors. Endotoxin levels >2.5 EU/mL were the strongest independent predictor (adjusted OR 15.7, 95% CI 3.84–64.2, p < 0.001). Hyponatremia <135 mmol/L (adjusted OR 4.82, 95% CI 1.26–18.4, p = 0.021) and presence of cough (adjusted OR 12.3, 95% CI 1.34–112.6, p = 0.026) were also independently associated with Legionella infection, whereas altered mental status and immunosuppression were not statistically significant. Please click here to view a larger version of this figure.
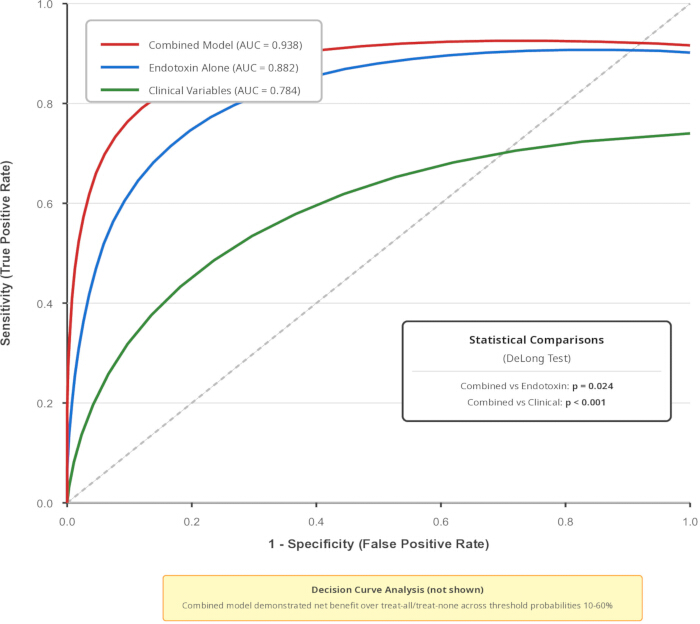
Figure 6: Comparative ROC analysis. The combined model incorporating endotoxin levels, hyponatremia, and clinical symptoms demonstrated the highest diagnostic performance (AUC = 0.938), outperforming endotoxin alone (AUC = 0.882) and clinical variables alone (AUC = 0.784). Pairwise comparisons using the DeLong test showed that the combined model significantly improved discrimination compared with endotoxin alone (p = 0.024) and clinical variables (p < 0.001). Please click here to view a larger version of this figure.
| Characteristic | Legionella pneumophila (n = 18) | Other Gram-negative (n = 68) | Gram-positive (n = 24) | Fungi (n = 8) | P-value |
| Demographics | |||||
| Age, median (IQR), years | 67 (5275) | 67 (56–81) | 63 (48–74) | 69 (60–83) | 0.678 |
| Male sex, n (%) | 13 (72.2) | 43 (63.2) | 19 (79.2) | 6 (75.0) | 0.512 |
| Comorbidities | |||||
| Diabetes mellitus, n (%) | 10 (55.6) | 27 (39.7) | 9 (37.5) | 3 (37.5) | 0.534 |
| Hypertension, n (%) | 8 (44.4) | 33 (48.5) | 10 (41.7) | 4 (50.0) | 0.932 |
| COPD, n (%) | 3 (16.7) | 9 (13.2) | 3 (12.5) | 2 (25.0) | 0.778 |
| Immunosuppression, n (%) | 4 (22.2) | 5 (7.4) | 0 (0) | 1 (12.5) | 0.048 |
| Clinical presentation | |||||
| Fever >38 °C, n (%) | 15 (83.3) | 43 (63.2) | 12 (50.0) | 1 (12.5) | 0.012 |
| Cough, n (%) | 18 (100) | 47 (69.1) | 10 (41.7) | 3 (37.5) | <0.001 |
| Altered mental status, n (%) | 16 (88.9) | 38 (55.9) | 15 (62.5) | 3 (37.5) | 0.042 |
| Severity scores | |||||
| APACHE II, median (IQR) | 28 (24–36) | 25 (18-31) | 26 (21–32) | 25 (18–34) | 0.168 |
| Outcomes | |||||
| Overall mortality, n (%) | 7 (38.9) | 24 (35.3) | 6 (25.0) | 3 (37.5) | 0.689 |
Table 1: Baseline patient characteristics by pathogen group. Abbreviations; APACHE II = Acute Physiology and Chronic Health Evaluation II; COPD = Chronic obstructive pulmonary disease; IQR = Interquartile range. P-values calculated using Kruskal-Wallis test for continuous variables and Fisher's exact test for categorical variables. Bold values indicate statistical significance (p < 0.05).
| Parameter | Legionella pneumophila (n = 18) | Other Gram-negative (n = 68) | Gram-positive (n = 24) | Fungi (n = 8) |
| Endotoxin levels (EU/mL) | ||||
| Mean ± SD | 2.15 ± 1.28 | 0.61 ± 0.74 | 0.42 ± 0.58 | 0.13 ± 0.15 |
| Median (IQR) | 2.50 (1.35–2.80) | 0.32 (0.15–0.78) | 0.28 (0.12–0.52) | 0.08 (0.04–0.16) |
| Endotoxin >2.5 EU/mL, n (%) | 14 (77.8) | 7 (10.3) | 0 (0) | 0 (0) |
| Diagnostic performance (>2.5 EU/mL threshold)* | ||||
| Sensitivity, % (95% CI) | 77.8 (52.4–93.6) | — | — | — |
| Specificity, % (95% CI) | 89.7 (79.9–95.8) | — | — | — |
| Positive predictive value, % (95% CI) | 66.7 (43.0–85.4) | — | — | — |
| Negative predictive value, % (95% CI) | 95.3 (87.1–99.0) | — | — | — |
| Positive likelihood ratio (95% CI) | 7.55 (3.84–14.8) | — | — | — |
| Negative likelihood ratio (95% CI) | 0.25 (0.11–0.56) | — | — | — |
| Area under ROC curve (95% CI) | 0.882 (0.809–0.955) | — | — | — |
| Optimism-corrected AUC | 0.874 (0.798–0.947) | — | — | — |
Table 2: Endotoxin levels and diagnostic performance metrics. For differentiating Legionella pneumophila from other gram-negative bacterial infections. Abbreviations; AUC = area under the receiver operating characteristic curve; CI = confidence interval; EU = Endotoxin units; IQR = Interquartile range; ROC: Receiver operating characteristic; SD = Standard deviation. Optimism-corrected AUC calculated using bootstrap resampling with 1000 iterations.
| Biomarker | Legionella (n = 18) | Other Gram-negative (n = 68) | Gram-positive (n = 24) | Fungi (n = 8) | P-value |
| White blood cell count, ×10³/μL | 9.24 ± 7.15 | 14.2 ± 10.3 | 15.1 ± 9.8 | 13.2 ± 8.6 | 0.089 |
| Platelet count, ×10³/μL | 186 ± 78 | 198 ± 92 | 205 ± 88 | 192 ± 76 | 0.823 |
| Procalcitonin, ng/mL | 28.6 (5.2–98.5) | 21.3 (0.08–95.6) | 9.4 (0.12–34.8) | 0.18 (0.06–0.32) | 0.038 |
| C-reactive protein, mg/L | 172.4 ± 61.2 | 135.7 ± 68.9 | 128.3 ± 87.6 | 102.8 ± 42.3 | 0.312 |
| Serum sodium, mmol/L | 133 ± 9.8 | 142 ± 11.4 | 143 ± 7.2 | 141 ± 6.8 | 0.003 |
| Serum creatinine, mg/dL | 1.58 ± 0.92 | 1.32 ± 0.86 | 1.21 ± 0.74 | 1.45 ± 0.88 | 0.142 |
| Lactate, mmol/L | 2.8 ± 1.4 | 2.4 ± 1.6 | 2.2 ± 1.3 | 2.6 ± 1.5 | 0.456 |
| Bilirubin, mg/dL | 1.2 ± 0.8 | 1.1 ± 0.9 | 0.9 ± 0.6 | 1.3 ± 0.7 | 0.678 |
Table 3: Laboratory biomarkers and inflammatory parameters. Values are presented as mean ± standard deviation or median (interquartile range). P-values calculated using analysis of variance or Kruskal-Wallis test as appropriate. Bold values indicate statistical significance (p < 0.05).
| Outcome | Endotoxin >2.5 EU/mL (n = 21) | Endotoxin ≤2.5 EU/mL (n = 97) | P-value |
| Pathogen distribution | |||
| Legionella pneumophila, n (%) | 14 (66.7) | 4 (4.1) | <0.001 |
| Other gram-negative, n (%) | 7 (33.3) | 61 (62.9) | 0.012 |
| Gram-positive, n (%) | 0 (0) | 24 (24.7) | 0.008 |
| Fungi, n (%) | 0 (0) | 8 (8.2) | 0.198 |
| Severity and management | |||
| APACHE II score, median (IQR) | 28 (24–36) | 25 (18–31) | 0.042 |
| Legionella-active therapy, n (%) | 16 (76.2) | 18 (18.6) | <0.001 |
| Mechanical ventilation, n (%) | 16 (76.2) | 57 (58.8) | 0.042 |
| Vasopressor requirement, n (%) | 13 (61.9) | 46 (47.4) | 0.128 |
| Clinical outcomes | |||
| 7-day mortality, n (%) | 3 (14.3) | 8 (8.2) | 0.389 |
| 28-day mortality, n (%) | 8 (38.1) | 24 (24.7) | 0.048 |
| Hospital mortality, n (%) | 9 (42.9) | 31 (32.0) | 0.256 |
| ICU length of stay, days, median (IQR) | 9 (6–14) | 6 (4–10) | 0.024 |
| Hospital length of stay, days, median (IQR) | 18 (12–28) | 15 (10–24) | 0.142 |
| Ventilator-free days at 28 days, median (IQR) | 12 (0–22) | 18 (8–25) | 0.089 |
| Hazard ratio for mortality (adjusted)* | 2.14 (1.08–4.23) | Reference | 0.028 |
Table 4: Clinical outcomes stratified by endotoxin levels. Adjusted for APACHE II score, age, and Charlson Comorbidity Index using Cox proportional hazards regression. Abbreviations; APACHE II = acute physiology and chronic health evaluation II; EU = Endotoxin units; ICU = intensive care unit; IQR = interquartile range. Legionella-active therapy includes fluoroquinolones or macrolides. Bold values indicate statistical significance (p < 0.05).
| Analysis | Value | P-value |
| Univariable logistic regression | ||
| Endotoxin >2.5 EU/mL | OR 30.2 (95% CI: 8.71–104.7) | <0.001 |
| Hyponatremia <135 mmol/L | OR 5.84 (95% CI: 1.98–17.2) | 0.001 |
| Cough present | OR 18.4 (95% CI: 2.31–146.3) | 0.006 |
| Altered mental status | OR 6.73 (95% CI: 1.89–23.9) | 0.003 |
| Immunosuppression | OR 3.56 (95% CI: 1.04–12.2) | 0.043 |
| Multivariable logistic regression* | ||
| Endotoxin >2.5 EU/mL | Adjusted OR 15.7 (95% CI: 3.84–64.2) | <0.001 |
| Hyponatremia <135 mmol/L | Adjusted OR 4.82 (95% CI: 1.26-18.4) | 0.021 |
| Cough present | Adjusted OR 12.3 (95% CI: 1.34–112.6) | 0.026 |
| Altered mental status | Adjusted OR 3.41 (95% CI: 0.89-13.1) | 0.073 |
| Immunosuppression | Adjusted OR 2.18 (95% CI: 0.51–9.32) | 0.291 |
| Model performance metrics | ||
| Combined model AUC (95% CI) | 0.938 (0.882–0.994) | — |
| Combined model sensitivity, % (95% CI) | 83.3 (58.6–96.4) | — |
| Combined model specificity, % (95% CI) | 91.2 (81.8–96.7) | — |
| Hosmer-Lemeshow goodness-of-fit | χ² = 6.84, df = 8 | 0.553 |
| Comparison of biomarker performance (AUC) | ||
| Endotoxin alone | 0.882 (95% CI: 0.809–0.955) | <0.001 |
| Clinical variables alone | 0.784 (95% CI: 0.691–0.877) | <0.001 |
| Combined endotoxin + clinical model | 0.938 (95% CI: 0.882–0.994) | <0.001 |
| Statistical comparisons (DeLong test) | ||
| Combined vs Endotoxin alone | — | 0.024 |
| Combined vs Clinical variables alone | — | <0.001 |
| Endotoxin vs Clinical variables alone | — | 0.018 |
Table 5: Multivariate analysis and ROC curve performance. Variables with p < 0.10 in univariable analysis were included in the multivariable model. Variance inflation factors for all variables < 2.1, indicating acceptable multicollinearity. Abbreviations; AUC = Area under the receiver operating characteristic curve; CI = confidence interval; df = degrees of freedom; EU = Endotoxin units; OR = Odds ratio. Bold values indicate statistical significance (p < 0.05). The combined model includes endotoxin > 2.5 EU/mL, hyponatremia, and cough as independent predictors.
Discussion
This study provides the first systematic evaluation of serum endotoxin quantification as a diagnostic biomarker for differentiating Legionella pneumophila infections from other gram-negative bacterial infections in critically ill patients. Current study findings reveal a striking paradox that challenges conventional understanding of Legionella pathophysiology: despite the organism's well-documented reduced endotoxic potency in laboratory studies, patients with legionellosis demonstrate significantly elevated circulating endotoxin levels compared to those infected with other gram-negative bacteria. This counterintuitive observation not only provides novel insights into the pathogenesis of severe Legionella infections but also offers a potentially useful adjunctive biomarker that may assist in the early identification of Legionella infection in critically ill patients.
The diagnostic performance characteristics observed in this cohort are particularly compelling from a clinical perspective. The 77.8% sensitivity and 89.7% specificity for endotoxin levels >2.5 EU/ml compare favorably with many established biomarkers for bacterial infections, while the exceptional negative predictive value of 95.3% represents a clinically actionable finding with immediate therapeutic implications19. This high negative predictive value suggests that endotoxin levels ≤2.5 EU/mL can effectively exclude Legionella infection with remarkable confidence, potentially enabling clinicians to avoid unnecessary exposure to Legionella-active antimicrobial agents such as quinolones or macrolides. Given the growing concerns about antimicrobial resistance and the emphasis on precision medicine approaches to infectious diseases, such diagnostic precision could significantly impact antimicrobial stewardship efforts in intensive care units20.
The biological mechanisms underlying this paradoxical endotoxin elevation in Legionella infections remain intriguing and warrant careful consideration. Several plausible explanations emerge from the understanding of Legionella pathophysiology and the host immune response. The organism's unique intracellular lifestyle involves massive bacterial replication within specialized vacuoles in alveolar macrophages, with individual bacteria multiplying to numbers exceeding 104–105 organisms per infected cell before triggering host cell lysis21. This explosive bacterial multiplication and subsequent massive release of bacterial components, including LPS, may overwhelm the reduced per-unit endotoxic activity through sheer quantity. While individual Legionella LPS molecules may be less potent than their enterobacterial counterparts, the collective endotoxic load released during the destruction of heavily infected alveolar macrophages could generate significant systemic endotoxemia.
Alternative explanations center on the concept of secondary endotoxin translocation from the gastrointestinal tract, a well-recognized phenomenon in critically ill patients with severe sepsis and shock. The profound systemic inflammation characteristic of severe legionellosis may compromise intestinal barrier function, facilitating the translocation of enterobacterial endotoxin from the gut microbiome into the systemic circulation22. This mechanism could account for elevated endotoxin levels regardless of the primary pathogen's intrinsic endotoxic properties and may explain why some patients with other gram-negative infections also demonstrate elevated endotoxin levels, albeit at significantly lower frequencies than those with legionellosis.
The immunological context of Legionella infections may also contribute to enhanced endotoxin detection through mechanisms involving host immune priming and sensitization. Legionella possesses numerous pathogen-associated molecular patterns beyond LPS, including flagellin, lipoproteins, and nucleic acids, which engage multiple Toll-like receptors and inflammasome pathways23. This multi-modal immune activation may create a state of heightened inflammatory responsiveness that amplifies the host response to even modest quantities of endotoxin. Additionally, the severe systemic inflammatory response syndrome characteristic of legionellosis may alter endotoxin kinetics, clearance mechanisms, or assay interference patterns in ways that enhance the detection of circulating LPS.
Technical considerations related to the Limulus amebocyte lysate assay methodology may also contribute to the findings. While the LAL assay is highly specific for LPS, it can be influenced by other bacterial cell wall components, complement activation products, and various inflammatory mediators that may be elevated in severe bacterial infections24. The possibility that the assay detects Legionella-specific bacterial products beyond classical LPS, or that it responds to unique combinations of inflammatory mediators present in legionellosis, cannot be excluded and deserves further investigation through more sophisticated analytical approaches.
This multivariate analysis provides additional clinical context for the diagnostic utility of endotoxin quantification by identifying complementary clinical variables that enhance diagnostic accuracy. The independent association between hyponatremia and Legionella infection aligns perfectly with established clinical teaching and reinforces the syndrome of inappropriate antidiuretic hormone secretion as a characteristic feature of legionellosis25. The combination of endotoxin measurement with hyponatremia and clinical variables achieved an area under the ROC curve of 0.938, representing excellent diagnostic discrimination that approaches the performance of sophisticated molecular diagnostic techniques while maintaining the advantage of rapid turnaround time and broad availability.
The clinical implications of these findings extend beyond simple pathogen identification to encompass broader questions of antimicrobial stewardship and precision medicine in critical care. The ability to rapidly exclude Legionella infection based on low endotoxin levels could facilitate antimicrobial de-escalation strategies, reducing unnecessary exposure to broad-spectrum agents and their associated toxicities. Conversely, elevated endotoxin levels in patients with compatible clinical presentations should prompt immediate initiation of Legionella-active therapy, potentially improving outcomes through earlier appropriate treatment. This approach is particularly valuable in healthcare systems where rapid molecular diagnostics are not readily available or during off-hours when immediate clinical decision-making is most critical.
The integration of endotoxin quantification into existing clinical decision-making pathways for severe pneumonia represents a practical application of biomarker-guided therapy that could be implemented in most intensive care units without significant infrastructure investment. The LAL assay is well-established, standardized, and available in most clinical laboratories, while newer point-of-care endotoxin detection systems promise even more rapid results26. The cost-effectiveness of this approach, when considered in the context of reduced inappropriate antimicrobial use and potentially improved clinical outcomes, warrants formal economic evaluation.
However, several important limitations must be acknowledged in interpreting these findings. In addition, the ICU cohort included patients with heterogeneous infectious etiologies rather than being restricted solely to pneumonia cases, which may influence circulating endotoxin levels and partially confound comparisons between pathogen groups. The retrospective design and relatively small sample size of Legionella cases limit statistical power and generalizability, while the single-center study design may introduce institutional bias. The wide confidence intervals observed for diagnostic performance metrics reflect these limitations and emphasize the need for larger prospective validation studies across diverse clinical settings. Additionally, the relatively low prevalence of Legionella infections in this cohort, while consistent with epidemiological data, may limit the positive predictive value in clinical practice and necessitate careful consideration of pre-test probability when interpreting endotoxin results.
The timing of endotoxin measurement represents another important consideration for clinical implementation. This protocol specified measurement within 24 h of ICU admission, which may not capture the full kinetic profile of endotoxin release during Legionella infection. Serial measurements throughout the course of illness might provide additional diagnostic and prognostic information, though such approaches would require prospective investigation. Furthermore, various clinical factors, including anticoagulation, sample handling, and interfering substances, may influence LAL assay results, underscoring the need for careful attention to quality control measures in clinical implementation. Moreover, elevated endotoxin levels may also reflect the overall severity of systemic inflammation rather than being entirely pathogen-specific.
The broader implications of this research extend to this fundamental understanding of Legionella pathophysiology and its position within the spectrum of gram-negative bacterial infections. The demonstration that clinical endotoxemia does not necessarily correlate with in vitro endotoxic potency challenges simplistic models of gram-negative sepsis pathogenesis and suggests that host-pathogen interactions in vivo are far more complex than laboratory models suggest. This finding may have implications for understanding other fastidious or intracellular gram-negative pathogens and could inform future research into biomarker development for challenging infectious diseases.
Future research priorities should focus on large-scale multicenter validation studies to confirm these findings across diverse patient populations and clinical settings. Mechanistic investigations using advanced analytical techniques, including mass spectrometry-based endotoxin analysis and comprehensive immune profiling, could elucidate the biological basis for elevated endotoxin levels in legionellosis. Longitudinal studies examining endotoxin kinetics during treatment could provide insights into prognostic applications and treatment monitoring. Additionally, cost-effectiveness analyses comparing endotoxin-guided diagnostic strategies with current standard-of-care approaches would inform implementation decisions and healthcare policy.
The development of rapid, point-of-care endotoxin detection systems specifically optimized for Legionella diagnosis represents an important technological opportunity. Such devices could integrate endotoxin quantification with clinical decision support algorithms incorporating other risk factors and biomarkers, providing clinicians with real-time guidance for antimicrobial selection in patients with severe pneumonia. The integration of artificial intelligence and machine learning approaches could further enhance diagnostic accuracy by identifying complex patterns of clinical, laboratory, and biomarker data that optimize Legionella detection.
In addition, recent studies have highlighted the broader relevance of endotoxin-related research in antimicrobial development and host–pathogen interactions. For example, peptide-based antibacterial strategies targeting gram-negative pathogens have been explored as potential approaches to modulate bacterial membrane structures and endotoxin-associated inflammatory responses27. Furthermore, ongoing advances in antimicrobial drug development, including novel macrolide hybrids, may expand future therapeutic options for severe bacterial infections and contribute to improved antimicrobial stewardship strategies28. These developments underscore the continuing importance of understanding endotoxin biology in both diagnostic and therapeutic contexts.
In conclusion, this study demonstrates that serum endotoxin quantification may represent a useful adjunctive biomarker for the early identification of Legionella infection. While further validation is essential before clinical implementation, these findings suggest that endotoxin measurement could fill a critical gap in the diagnostic arsenal for one of critical care medicine's most challenging pathogens. The combination of rapid turnaround time, broad availability, and excellent negative predictive value positions endotoxin quantification as a valuable tool for improving antimicrobial stewardship and clinical outcomes in critically ill patients with suspected gram-negative sepsis.
Disclosures
The authors declare that they have no competing interests related to this study. No financial or non-financial conflicts exist, including employment, consultancies, stock ownership, honoraria, or paid expert testimony.
Acknowledgements
We thank the ICU staff at Zhongshan City People's Hospital for their support in data collection and the patients whose anonymized data contributed to this research.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Kinetic chromogenic Limulus amebocyte lysate assay | Associates of Cape Cod / Charles River Laboratories | KTA-2 or equivalent | Used for quantitative serum endotoxin measurement; detection range 0.01–10.0 EU/mL |
| Buffered charcoal yeast extract agar | BD Diagnostics / Remel | 221836 / R05001 | Selective agar for culturing Legionella pneumophila. |
| Sterile pyrogen-free blood collection tubes | BD Vacutainer / Greiner Bio-One | 368498 / 455092 | For venous blood collection to avoid endotoxin contamination. |
| Pyrogen-free microcentrifuge tubes | Corning / Eppendorf | 3620 / 022364111 | For serum aliquoting and storage. |
| –80 °C freezer | Thermo Scientific / Panasonic | Forma 900 / MDF-U73V | For long-term storage of serum samples. |
| Centrifuge (3,000 × g) | Eppendorf / Thermo Scientific | 5810R / Sorvall ST 8 | For serum separation after clotting. |
| Urinary antigen test for L. pneumophila | BinaxNOW / Sofia | 430-000 / 30400 | Rapid immunochromatographic test for Legionella pneumophila serogroup 1 antigen. |
| Metagenomic next-generation sequencing platform | Illumina / Oxford Nanopore | MiSeq / MinION | Used for pathogen identification when conventional diagnostics were inconclusive. |
| APACHE II & SOFA scoring sheets | – | – | Used for assessing disease severity at ICU admission. |
| Electronic medical record system | – | – | Used for retrospective data extraction (demographics, lab results, treatments, outcomes). |
| Statistical software (R version 4.3.0) | R Foundation | – | Used for all statistical analyses, including ROC, regression, and survival modeling. |
| Laboratory equipment for routine tests | – | – | Includes CBC analyzer, chemistry analyzer, lactate meter, CRP/PCT immunoassay systems, etc. |
References
- Cunha, B. A., Burillo, A., Bouza, E. Legionnaires' disease. Lancet. 387 (10016), 376-385 (2016).
- Newton, H. J., Ang, D. K., van Driel, I. R., Hartland, E. L. Molecular pathogenesis of infections caused by Legionella pneumophila. Clin Microbiol Rev. 23 (2), 274-298 (2010).
- Diederen, B. M. Legionella spp. and Legionnaires' disease. J Infect. 56 (1), 1-12 (2008).
- Murdoch, D. R. Diagnosis of Legionella infection. Clin Infect Dis. 36 (1), 64-69 (2003).
- Mercante, J. W., Winchell, J. M. Current and emerging Legionella diagnostics for laboratory and outbreak investigations. Clin Microbiol Rev. 28 (1), 95-133 (2015).
- Yu, V. L., et al. Distribution of Legionella species and serogroups isolated by culture in patients with sporadic community-acquired legionellosis: an international collaborative survey. J Infect Dis. 186 (1), 127-128 (2002).
- Phin, N., et al. Epidemiology and clinical management of Legionnaires' disease. Lancet Infect Dis. 14 (10), 1011-1021 (2014).
- Helbig, J. H., et al. Clinical utility of urinary antigen detection for diagnosis of community-acquired, travel-associated, and nosocomial legionnaires' disease. J Clin Microbiol. 41 (2), 838-840 (2003).
- Sweeney, T. E., Wong, H. R., Khatri, P. Robust classification of bacterial and viral infections via integrated host gene expression diagnostics. Sci Transl Med. 8 (346), 346ra91 (2016).
- Raetz, C. R., Whitfield, C. Lipopolysaccharide endotoxins. Annu Rev Biochem. 71, 635-700 (2002).
- Neumeister, B., et al. Low endotoxic potential of Legionella pneumophila lipopolysaccharide due to failure of interaction with the monocyte lipopolysaccharide receptor CD14. Infect Immun. 66 (9), 4151-4157 (1998).
- Zähringer, U., et al. The lipopolysaccharide of Legionella pneumophila serogroup 1 (strain Philadelphia 1): chemical structure and biological activities. Prog Clin Biol Res. 392, 113-139 (1995).
- Brieland, J., et al. Replicative Legionella pneumophila lung infection in intratracheally inoculated A/J mice. A murine model of human Legionnaires' disease. Am J Pathol. 145 (6), 1537-1546 (1994).
- Marshall, J. C. Lipopolysaccharide: an endotoxin or an exogenous hormone. Clin Infect Dis. 41 (Suppl 7), S470-S480 (2005).
- Cohen, J. The detection and interpretation of endotoxaemia. Intensive Care Med. 26 (Suppl 1), S51-S56 (2000).
- Romaschin, A. D., et al. A rapid assay of endotoxin in whole blood using autologous neutrophil dependent chemiluminescence. J Immunol Methods. 212 (2), 169-185 (1998).
- Barlam, T. F., et al. Implementing an antibiotic stewardship program: guidelines by the Infectious Diseases Society of America and the Society for Healthcare Epidemiology of America. Clin Infect Dis. 62 (10), e51-e77 (2016).
- Mandell, L. A., et al. Infectious Diseases Society of America/American Thoracic Society consensus guidelines on the management of community-acquired pneumonia in adults. Clin Infect Dis. 44 (Suppl 2), S27-S72 (2007).
- Pierrakos, C., Vincent, J. L. Sepsis biomarkers: a review. Crit Care. 14 (1), R15 (2010).
- Seymour, C. W., et al. Time to treatment and mortality during mandated emergency care for sepsis. N Engl J Med. 376 (23), 2235-2244 (2017).
- Horwitz, M. A., Silverstein, S. C. Legionnaires' disease bacterium (Legionella pneumophila) multiplies intracellularly in human monocytes. J Clin Invest. 66 (3), 441-450 (1980).
- Deitch, E. A. Gut-origin sepsis: evolution of a concept. Surgeon. 10 (6), 350-356 (2012).
- Derre, I., Isberg, R. R. Legionella pneumophila replication vacuole formation involves rapid recruitment of proteins of the early secretory system. Infect Immun. 72 (5), 3048-3053 (2004).
- Hurley, J. C. Endotoxemia: methods of detection and clinical correlates. Clin Microbiol Rev. 8 (2), 268-292 (1995).
- Miller, A. C., Beig, A. A., Frerichs, F. C., Barbaree, J. M., Breiman, R. F., Dufour, A. P. Legionnaires' disease: clinical features. Legionella: Current Status and Emerging Perspectives. , 13-18 (1993).
- Ketchum, P. A., Novitsky, T. J. Assay of endotoxin by limulus amebocyte lysate. Methods Mol Med. 36, 3-12 (2000).
- Zheng, P., et al. Exploration of Biological Properties and Antibacterial Action against Escherichia coli and Staphylococcus aureus of (LLKK)3-Derived Peptides. Chemistry Select. 8 (17), e202300355 (2023).
- Ji, C., Xu, X. Recent Advancements in Macrolide Hybrids against Staphylococcus aureus. Curr Top Med Chem. 21 (27), 2455-2473 (2021).