This study aims to determine whether serum inhibin B can serve as a biomarker to evaluate the efficacy of orchiopexy in boys with cryptorchidism.
Research Article
Changes in Serum Inhibin B Following Orchiopexy for Cryptorchidism: A Systematic Review and Meta-Analysis of Endocrine Recovery
In This Article
Summary
Abstract
This study evaluated the effects of pediatric orchiopexy on serum inhibin B concentrations, confirmed postoperative changes in endocrine parameters, and explored the potential utility of serum inhibin B as a marker of postoperative endocrine recovery. A systematic search of PubMed, Cochrane Library, Embase, Scopus, and Web of Science databases was conducted to identify self-controlled studies of boys with cryptorchidism who underwent orchiopexy. Relevant reference literature, related journals, and conference proceedings were also manually screened. Following quality assessment and data extraction, six studies involving 394 boys were included in the meta-analysis. In the primary analysis of studies reporting 6-month follow-up, serum inhibin B concentrations were significantly higher after orchiopexy than before surgery (MD, 14.03 pg/mL; 95% CI, 4.05–24.01 pg/mL; P = 0.014). Moderate-to-substantial heterogeneity was observed (I2 = 67.5%). Evidence from 1- and 12-month follow-up studies was limited and yielded inconsistent findings. No significant postoperative changes were observed in follicle-stimulating hormone (FSH) (MD, −0.03 IU/L; 95% CI, −0.30 to 0.24 IU/L) or luteinizing hormone (LH) (MD, −0.02 IU/L; 95% CI, −0.07 to 0.04 IU/L). Orchiopexy was associated with a significant early increase in serum inhibin B, suggesting postoperative Sertoli cell recovery. Serum inhibin B may represent a potential short-term marker of endocrine recovery following orchiopexy, although further validation is required.
Introduction
Cryptorchidism is among the most common congenital abnormalities in boys, affecting approximately 2% to 4% of term infants and a substantially higher proportion of preterm infants. In addition to congenital cryptorchidism, acquired (or ascending) cryptorchidism, where a previously scrotally positioned testis gradually ascends out of the scrotum during childhood, represents a clinically relevant entity with a distinct natural history that may also warrant surgical correction1. Persistence of the testis outside the scrotum is associated with impaired germ cell development, reduced fertility potential, testicular atrophy, and an increased risk of testicular malignancy later in life. Current guidelines therefore recommend orchiopexy during early childhood, preferably before 12 to 18 months of age, to preserve testicular development and optimize long-term reproductive outcomes2,3,4.
Despite the widespread use of orchiopexy, assessment of postoperative testicular recovery remains challenging. Histological parameters obtained from testicular biopsy, including gonocyte and spermatogonial counts and the spermatogonia-to-tubule ratio, are considered important indicators of fertility potential4. However, testicular biopsy is invasive, unsuitable for routine follow-up, and may be associated with procedural complications. Consequently, there is considerable interest in identifying noninvasive biomarkers that reflect testicular function after surgical correction.
Inhibin B is a dimeric glycoprotein hormone composed of an α-subunit and a βB-subunit, produced predominantly by Sertoli cells. It represents the principal circulating marker of Sertoli cell function in prepubertal boys. Serum inhibin B concentrations correlate with seminiferous tubule development and are reduced in boys with cryptorchidism compared with healthy controls5. As a result, changes in serum inhibin B following orchiopexy have been proposed as a potential indicator of postoperative endocrine recovery. However, studies evaluating serum inhibin B before and after orchiopexy have reported inconsistent findings, and the magnitude and temporal pattern of postoperative changes remain uncertain6,7.
This meta-analysis aims to quantify the effect of orchiopexy on serum inhibin B concentrations as a primary endpoint of Sertoli cell recovery. Its secondary objective is to explore whether the observed postoperative changes support the potential utility of inhibin B as a non-invasive marker for monitoring surgical efficacy, while acknowledging that current evidence remains insufficient to validate it as a surrogate for long-term fertility.
Protocol
This systematic review and meta-analysis was prospectively registered in the PROSPERO International Prospective Register of Systematic Reviews (registration number: CRD420261428789). This analysis was conducted in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) reporting guidelines.
Search strategy
A systematic search of PubMed, Embase, Cochrane Library, Scopus, and Web of Science was conducted from database inception through March 2025. The search strategy included the terms “cryptorchidism,” “undescended testis,” “orchiopexy,” “inhibin B,” “INHB,” “follicle-stimulating hormone,” “FSH,” “luteinizing hormone,” and “LH”.
Study eligibility criteria
The review was structured according to the PICO framework: Population—boys diagnosed with cryptorchidism; Intervention—orchiopexy; Comparator—preoperative baseline status (self-controlled); Outcome—changes in serum inhibin B concentrations.
Studies were eligible if they met the following criteria: (1) included boys diagnosed with cryptorchidism who underwent orchiopexy; (2) reported serum inhibin B concentrations before and after surgery; (3) provided sufficient data for quantitative synthesis; and (4) were prospective or retrospective cohort studies. Studies were eligible regardless of cryptorchidism laterality, surgical approach, or postoperative follow-up duration, provided they reported the required endocrine data pre- and post-surgery.
Studies were excluded if they were reviews, editorials, letters, case reports, conference abstracts without sufficient data, animal or laboratory studies, studies involving adult populations, non-English publications, or duplicate publications.
The reference lists of included studies and relevant review articles were screened to identify additional eligible studies. Two investigators independently conducted the literature search and data extraction. Disagreements were resolved through discussion or consultation with a third reviewer.
Data extraction
Two reviewers independently screened studies and extracted data using a standardized form. Extracted information included study characteristics, participant characteristics, orchiopexy method, follow-up duration, postoperative complications, and endocrine outcomes. The primary outcome was serum inhibin B concentration. For each study, serum inhibin B concentrations before and after orchiopexy, together with measures of variability, were extracted. Data on serum follicle-stimulating hormone and luteinizing hormone concentrations were also collected when available.
Quality assessment
Nonrandomized studies were evaluated using the Methodological Index for Non-Randomized Studies instrument8, whereas the randomized controlled trial was assessed using the Cochrane Risk of Bias 2 tool9. MINORS scores of 13–16 were considered high quality, 9–12 moderate quality, and ≤8 low quality. The certainty of evidence for the primary outcome was assessed using the Grading of Recommendations Assessment, Development and Evaluation framework10.
Statistical analysis
The primary outcome was the mean difference in serum inhibin B concentration before and after orchiopexy. Pooled mean differences with corresponding 95% confidence intervals were calculated using a random-effects model. For the primary analysis, the mean and standard deviation of paired differences were extracted when directly reported. For studies reporting only separate preoperative and postoperative summary statistics, the standard deviation of the mean change was calculated using the following equation:
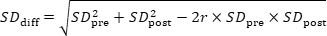
Where SDdiff is the standard deviation of the paired difference, SDpre and SDpost are the standard deviations of the preoperative and postoperative measurements, respectively, and r is the within-subject correlation coefficient. A conservative value of r = 0.5 was assumed when the actual correlation was not reported.
Heterogeneity was assessed using the I2 statistic. Because of the limited number of included studies, formal subgroup analyses and meta-regression were not performed. Publication bias was not formally assessed because fewer than 10 studies were available. Leave-one-out sensitivity analyses were performed to evaluate the influence of individual studies on the pooled effect estimate.
All statistical analyses were performed using R version 4.4.1. Statistical significance was defined as a two-sided P value < 0.05.
Results
Study selection and search results
A total of 789 records were identified through the database searches (PubMed, Cochrane, Embase, Scopus, and Web of Science). After removing 446 duplicate records, 343 articles remained for initial screening. Two reviewers independently screened the titles and abstracts of these 343 articles and excluded 306 records that were clearly irrelevant to the study topic or did not meet the eligibility criteria (e.g., animal experiments, case reports, reviews, conference abstracts). The remaining 37 full-text articles were assessed for eligibility. Of these, 31 were excluded for the following reasons: (1) incomplete or non-extractable data that could not be used to calculate pre- and postoperative levels of INHB, FSH, or LH (n = 18); (2) non-English publications (n = 5); (3) not a self-controlled study design (n = 6); and (4) duplicate data from overlapping patient cohorts (n = 2). Ultimately, six studies11,12,13,14,15,16 met all inclusion criteria and were included in the final meta-analysis. The literature screening process is summarized in Figure 1, prepared in accordance with the PRISMA 2020 guidelines.
Characteristics of included studies
Regarding the type of cryptorchidism, two studies included only unilateral cases (Cao et al.11 and Huang et al.12), while the remaining four studies included both unilateral and bilateral cases, with the proportion of unilateral cases ranging from 64.0% to 92.6%. Age at surgery also varied across studies: two studies restricted enrollment to infants under 12 months of age (Cao et al., 6–12 months; Huang et al., 6–12 months), whereas the other four studies included older children, with mean ages ranging from 4.8 to 4.9 years (Irkilata et al.13,14), a median age of 24 months (Raman et al.16), and an age range of 6 to 24 months (Ma et al.15). Follow-up duration was relatively consistent, with most studies reporting a 6-month postoperative assessment; two studies (Ma et al. and Huang et al.) also provided 12-month follow-up data. Surgical approaches differed across studies, including inguinal orchiopexy, scrotal orchiopexy, laparoscopic orchiopexy, and unspecified approaches (Table 1).
Serum Inhibin B outcomes
In the primary analysis of studies reporting a 6-month follow-up, orchiopexy was associated with a significant increase in serum inhibin B concentrations compared with preoperative levels. The pooled mean difference was 14.03 pg/mL (95% CI, 4.05–24.01 pg/mL; P = 0.014) under a random effects model (Figure 2). Moderate to substantial between-study heterogeneity was observed (I2 = 67.5%; P = 0.005), which may reflect differences in patient age, cryptorchidism laterality, surgical approach, and baseline serum inhibin B concentrations across studies. Despite the observed heterogeneity, the direction of effect was consistent across all studies: every included comparison reported higher postoperative serum inhibin B concentrations than preoperative values. Leave-one-out sensitivity analyses confirmed that the overall findings were generally robust, and no single study disproportionately influenced the pooled estimate.
Data on postoperative serum inhibin B concentrations at time points other than 6 months were limited. At 1 month after orchiopexy, Ma et al.15 reported a modest increase in serum inhibin B compared with preoperative levels (MD, 11.0 pg/mL; 95% CI, −21.25 to 43.25 pg/mL). At 12 months, findings were less consistent. Ma et al.15 observed lower serum inhibin B concentrations relative to baseline (MD, −62.0 pg/mL; 95% CI, −89.76 to −34.24 pg/mL), whereas Huang et al.12 reported sustained increases in both the scrotal orchiopexy cohort (MD, 31.23 pg/mL; 95% CI, 22.78–39.68 pg/mL) and the inguinal orchiopexy cohort (MD, 31.06 pg/mL; 95% CI, 22.70–39.42 pg/mL). Given the limited number of studies reporting outcomes beyond 6 months, quantitative synthesis was not performed for these follow-up intervals (Supplementary Figure 1).
Three studies reported age-stratified outcomes following orchiopexy (Supplementary Figure 2). As age categories varied across studies, there is no pooled estimate. Also, three studies reported outcomes according to surgical approach (Supplementary Figure 3). Postoperative serum inhibin B concentrations were generally higher than preoperative levels following both inguinal and scrotal orchiopexy. Mean differences ranged from 15.4 to 52.1 pg/mL after inguinal orchiopexy and from 15.8 to 24.0 pg/mL after scrotal orchiopexy.
Quality assessment of included studies
Five nonrandomized studies were evaluated using the Methodological Index for Non-Randomized Studies (MINORS) instrument8, and 1 randomized controlled trial was assessed using the Cochrane Risk of Bias 2 tool9 (Supplementary Table 1). MINORS scores ranged from 12 to 16, indicating overall moderate to high methodological quality among the included observational studies. The most common methodological limitations were the absence of prospective sample size calculations and the lack of blinded outcome assessment. The randomized controlled trial by Huang et al. was judged to have some concerns overall, primarily because insufficient information was available regarding allocation concealment and prespecified outcome reporting. No study was considered to be of low methodological quality.
According to the GRADE framework10, the certainty of evidence for the primary outcome of serum inhibin B concentrations at 6 months after orchiopexy was judged to be low. Evidence was derived primarily from observational studies and was downgraded for inconsistency because of substantial between-study heterogeneity.
Serum follicle-stimulating hormone and luteinizing hormone concentrations
Three studies reported serum FSH and LH concentrations before and 6 months after orchiopexy (Supplementary Figure 4). No significant changes were observed in serum FSH concentrations (MD, −0.03 mIU/mL; 95% CI, −0.30 to 0.24 mIU/mL) or serum LH concentrations (MD, −0.02 mIU/mL; 95% CI, −0.07 to 0.04 mIU/mL) following orchiopexy. These findings should be interpreted cautiously, given the limited number of studies available.
DATA AVAILABILITY:
All data generated or analyzed during this study are included in this published article and Supplementary File 1.
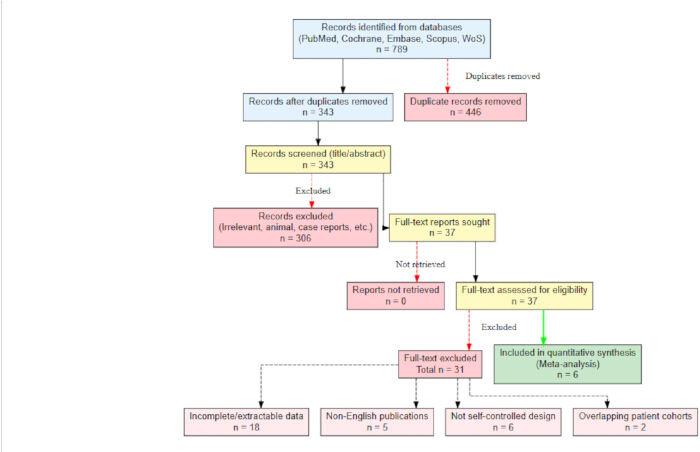
Figure 1: Flowchart of the literature search and study selection process, adapted from the PRISMA statement. PRISMA 2020 flow diagram illustrating the identification, screening, eligibility assessment, and inclusion of studies in the systematic review and meta-analysis. The diagram summarizes the number of records identified, screened, excluded, and ultimately included in the quantitative synthesis. Please click here to view a larger version of this figure.
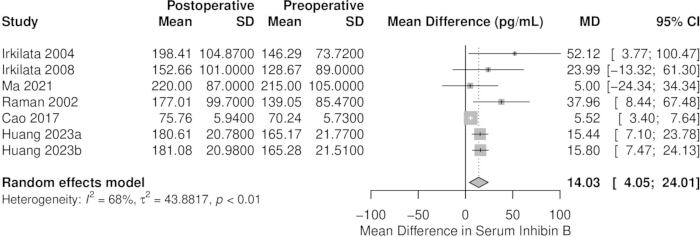
Figure 2: Change in Serum Inhibin B concentrations 6 months after orchiopexy. Forest plot of mean differences in serum inhibin B concentrations comparing postoperative and preoperative measurements at 6 months after orchiopexy. Squares indicate study-specific estimates, horizontal lines indicate 95% confidence intervals, and the diamond indicates the pooled effect estimate. Positive values favor higher postoperative serum inhibin B concentrations. Please click here to view a larger version of this figure.
| Study | Study design | Country | Sample Size, n | Age | Cryptorchidism Type | Surgical Approach | Follow Up | Postoperative Complications |
| Irkilata et al., 2004 | Prospective cohort study | Turkey | 27 | 6 months to 11 years (mean, 4.8 years) | 25 unilateral, 2 bilateral | Inguinal orchiopexy | 6 months | Not reported |
| Irkilata et al., 2008 | Prospective cohort study | Turkey | 50 | 6 months to 12 years (mean, 4.9 years) | 32 unilateral, 18 bilateral | Scrotal orchiopexy | 6 months | No postoperative testicular atrophy or high scrotal/inguinal testicular position reported |
| Cao et al., 2017 | Prospective cohort study | China | 58 | <12 months | Unilateral cryptorchidism | Orchiopexy (approach not specified) | 6 months | Not reported |
| Ma et al., 2021 | Prospective cohort study | China | 83 | 6 to 24 months | 60 unilateral, 23 bilateral | Conventional open orchiopexy (n = 49) or laparoscopic orchiopexy (n = 34) | 1, 6, and 12 months | Not reported |
| Raman et al., 2022 | Prospective cohort study | India | 76 | 6 to 98 months (median, 24 months) | 64 unilateral, 12 bilateral | Orchiopexy (approach not specified) | 6 months | Wound infection (n = 3); scrotal hematoma (n = 2) |
| Huang et al., 2023 | Randomized controlled trial | China | 100 | 6 to 12 months | Unilateral inguinal cryptorchidism | Scrotal orchiopexy (n = 50) or inguinal orchiopexy (n = 50) | 6 and 12 months | Inguinal group: wound extravasated blood (n = 3) and wound infection (n = 1); scrotal group: wound extravasated blood (n = 1) |
Table 1: Characteristics of the included studies. Summary of the six studies included in the systematic review and meta-analysis. The table presents study design, country, sample size, participant age, cryptorchidism laterality, surgical approach, duration of follow-up, and the endocrine outcomes evaluated (serum inhibin B, follicle-stimulating hormone, and luteinizing hormone).
Supplementary Figure 1: Association between orchiopexy and serum inhibin B concentrations according to follow-up duration. Forest plot of mean differences in serum inhibin B concentrations between postoperative and preoperative assessments stratified by follow-up duration. Positive mean differences indicate higher postoperative serum inhibin B concentrations. Squares indicate individual study estimates, horizontal lines indicate 95% confidence intervals, and diamonds indicate pooled estimates. Please click here to download this file.
Supplementary Figure 2: Serum Inhibin B concentrations following orchiopexy according to age at surgery. Forest plot of mean differences in serum inhibin B concentrations comparing postoperative and preoperative measurements stratified by age at orchiopexy. Age categories were defined according to the original study reports. Squares indicate study-specific estimates and horizontal lines indicate 95% confidence intervals. No pooled estimate was generated because of heterogeneity in age stratification across studies. Please click here to download this file.
Supplementary Figure 3: Serum Inhibin B concentrations following orchiopexy according to surgical approach. Forest plot of mean differences in serum inhibin B concentrations comparing postoperative and preoperative measurements stratified by surgical approach. Squares indicate study-specific estimates and horizontal lines indicate 95% confidence intervals. No pooled estimate was generated because of the limited number of studies available for each surgical approach. Please click here to download this file.
Supplementary Figure 4: Changes in serum follicle-stimulating hormone and luteinizing hormone concentrations following orchiopexy. Forest plots showing mean differences in serum follicle-stimulating hormone (FSH) and luteinizing hormone (LH) concentrations between postoperative and preoperative assessments following orchiopexy. Squares indicate study-specific effect estimates, horizontal lines indicate 95% confidence intervals, and diamonds indicate pooled effect estimates. Negative mean differences indicate lower postoperative hormone concentrations compared with preoperative values. Please click here to download this file.
Supplementary Table 1: Quality assessment of included studies. MINORS scores for noncomparative studies range from 0 to 16, with higher scores indicating better methodological quality. Studies scoring 0–8 were considered low quality, 9–12 moderate quality, and 13–16 high quality. The randomized controlled trial was assessed using the Cochrane Risk of Bias 2 (RoB 2) tool and categorized as low risk, some concerns, or high risk of bias. Please click here to download this file.
Supplementary File 1: Raw extracted data used for the meta-analysis. Please click here to download this file.
Discussion
In this systematic review and meta-analysis, serum inhibin B concentrations at 6 months after orchiopexy were significantly higher than preoperative levels in boys with cryptorchidism. Although the magnitude of change varied across studies, the overall findings indicate that postoperative increases in inhibin B are consistently observed following surgical correction. These results provide quantitative evidence that orchiopexy is associated with favorable changes in a circulating marker of Sertoli cell function and testicular development.
The observed increase in serum inhibin B following orchiopexy is consistent with the current understanding of testicular development in cryptorchidism. Histological studies have demonstrated that undescended testes exhibit reduced germ cell numbers, impaired maturation of the seminiferous epithelium, and abnormalities in Sertoli cell development, changes that become more pronounced with increasing duration of maldescent17. In prepubertal boys, serum inhibin B has been shown to correlate with Sertoli cell number and histological markers of testicular development, and lower inhibin B concentrations have consistently been reported in boys with cryptorchidism than in healthy controls18. Consequently, restoration of the testis to the scrotum would be expected to attenuate ongoing testicular injury and promote more favorable testicular development, providing a biological rationale for the postoperative increase in inhibin B observed across the included studies.
The available evidence also suggests that postoperative changes in serum inhibin B may vary according to the timing of assessment. In the present study, the 1-month follow-up data demonstrated a modest early increase that did not reach statistical significance, consistent with an initial period of Sertoli cell recovery following surgery. By contrast, the limited data available at 12 months showed inconsistent findings across studies. These discrepant results may reflect differences in patient age at surgery, baseline germ cell reserve, laterality of cryptorchidism, duration of maldescent, and surgical technique.
Previous histological studies support the concept that preoperative testicular status influences postoperative recovery. Verkauskas et al.19 demonstrated that 48% of undescended testes in boys with unilateral cryptorchidism lacked adult dark spermatogonia and that histological abnormalities correlated with findings in the contralateral descended testis, suggesting that unilateral cryptorchidism may represent a bilateral disorder affecting overall testicular development. Accordingly, boys with more severe baseline histological impairment may exhibit different postoperative inhibin B trajectories than those with relatively preserved germ cell populations, although this patient-level variability cannot be evaluated using aggregate meta-analytic data. Similarly, Thorup et al.20 reported that the number of adult dark spermatogonia and the presence of placental-like alkaline phosphatase-positive gonocytes were positively associated with both serum inhibin B concentrations and fertility potential at the time of orchiopexy. These observations support the biological relationship between histological maturation and endocrine recovery. Prospective studies incorporating serial inhibin B measurements throughout childhood and puberty, along with semen analyses and long-term fertility outcomes, are needed to determine whether postoperative changes in inhibin B predict future reproductive function.
Although orchiopexy is performed primarily to preserve future reproductive potential, direct assessment of treatment efficacy during childhood remains challenging. Histological evaluation provides valuable information regarding testicular development, but it is invasive and unsuitable for routine follow-up. In contrast, serum inhibin B can be measured repeatedly using a minimally invasive approach. The consistent postoperative increase observed across the included studies suggests that inhibin B may provide an objective indicator of endocrine recovery following orchiopexy and may complement anatomical assessment of surgical success. Nevertheless, its clinical utility should be interpreted cautiously. At present, there is insufficient evidence to establish clinically meaningful postoperative thresholds or determine whether postoperative increases in inhibin B predict long-term fertility. Therefore, serum inhibin B should currently be regarded as a potential short-term marker of postoperative endocrine recovery, rather than a validated surrogate marker of future fertility.
This study has several limitations. First, only six studies were eligible for inclusion, limiting statistical power and precluding meaningful subgroup analyses according to patient age, cryptorchidism laterality, surgical technique, and duration of follow-up. Second, most included studies were observational self-controlled studies without external control groups, limiting the ability to distinguish treatment effects from spontaneous age-related endocrine changes. Third, methodological quality was moderate to high, with MINORS scores ranging from 12 to 16, and common limitations included the absence of prospective sample size calculations and limited reporting of blinded outcome assessment. Fourth, heterogeneity among studies may reflect differences in patient characteristics, baseline testicular function, surgical techniques, and follow-up duration. Finally, for studies that did not directly report paired differences, a conservative within-subject correlation coefficient (r = 0.5) was assumed to estimate the standard deviation of the mean change. Although this approach is widely accepted for paired-data meta-analyses, it may have influenced the precision of the pooled estimates.
In conclusion, this systematic review and meta-analysis demonstrate that orchiopexy is associated with a significant increase in serum inhibin B concentrations at 6 months post-surgery, suggesting improved postoperative Sertoli cell function. In contrast, serum follicle-stimulating hormone and luteinizing hormone concentrations did not change significantly following orchiopexy. Serum inhibin B may be a potential short-term marker of postoperative endocrine recovery; however, additional prospective studies with standardized methodologies, longer follow-up periods, and long-term fertility outcomes are required before its clinical utility can be fully established.
Disclosures
The authors declare no conflict of interest.
Acknowledgements
The authors thank all the participants of the studies included in the present study. No funding for this study.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Cochrane RoB 2 Tool | Higgins et al., 2011 | N/A | Risk of bias assessment tool for randomized controlled trials |
| FSH ELISA Kit | N/A | N/A | For quantitative measurement of serum follicle-stimulating hormone |
| GRADE Framework | Izcovich et al., 2023 | N/A | Certainty of evidence assessment framework |
| Human serum samples | N/A | N/A | Collected from pediatric patients pre- and post-orchiopexy |
| Inhibin B ELISA Kit | N/A | N/A | For quantitative measurement of serum inhibin B |
| LH ELISA Kit | N/A | N/A | For quantitative measurement of serum luteinizing hormone |
| MINORS Instrument | Slim et al., 2003 | N/A | Methodological quality assessment tool for non-randomized studies |
| R software | R Foundation for Statistical Computing | Version 4.4.1 | Statistical analysis software for meta-analysis |
References
- Barthold JS, González R. The epidemiology of congenital cryptorchidism, testicular ascent and orchiopexy. J Urol. 2003;170(6 Pt 1):2396-401.
- Shin J, Jeon GW. Comparison of diagnostic and treatment guidelines for undescended testis. Clin Exp Pediatr. 2020;63(11):415-421.
- Wood HM, Elder JS. Cryptorchidism and testicular cancer: separating fact from fiction. J Urol. 2009;181(2):452-461.
- Akre O, Pettersson A, Richiardi L. Risk of contralateral testicular cancer among men with unilaterally undescended testis: a meta-analysis. Int J Cancer. 2009;124(3):687-689.
- Andersson A-M, Müller J, Skakkebæk NE. Different roles of prepubertal and postpubertal germ cells and Sertoli cells in the regulation of serum inhibin B levels. J Clin Endocrinol Metab. 1998;83(12):4451-4458.
- Radicioni AF, Anzuini A, De Marco E, Nofroni I, et al. Changes in serum inhibin B during normal male puberty. Eur J Endocrinol. 2005;152(3):403-409.
- Braga LH, Lorenzo AJ. The changing elaboration of inhibin B in patients with unilateral testicular maldescent versus vanished testis. J Urol. 2015;193(5):1465-1466.
- Slim K, et al. Methodological index for non-randomized studies (MINORS): development and validation of a new instrument. ANZ J Surg. 2003;73(9):712-716.
- Higgins JPT, et al. The Cochrane Collaboration's tool for assessing risk of bias in randomized trials. BMJ. 2011;343:d5928.
- Izcovich A, Chu DK, Mustafa RA, Guyatt G, et al. A guide and pragmatic considerations for applying GRADE to network meta-analysis. BMJ. 2023;381:e074495.
- Cao S-S, Hu Y-Y, Nan C-J. Orchidopexy increases the levels of serum anti-Müllerian hormone and inhibin B in patients with cryptorchidism. Zhonghua Nan Ke Xue. 2017;23(8):713-716.
- Huang W-H, et al. The effect of scrotal versus inguinal orchiopexy on the testicular function of children with clinically palpable, inguinal undescended testis: a randomized controlled trial. Asian J Androl. 2023;25(6):745-749.
- Irkilata HC, et al. Effect of scrotal incision orchiopexy on serum inhibin B levels and comparison with classic inguinal orchiopexy. Urology. 2008;72(3):525-529.
- Irkilata HC, et al. The influence of orchiopexy on serum inhibin B level: relationship with histology. J Urol. 2004;172(6 Pt 1):2402-2405.
- Ma D, Yao ZG, Guo YP, Wu RF. Dynamic changes in serum inhibin B levels in 6- to 24-month-old children receiving cryptorchidism surgery. Int J Gen Med. 2021;14:1173-1177.
- Raman VS, Khanna S, Verma V. A prospective observational study to evaluate the change in inhibin B as a marker of Sertoli cell function in children subjected to surgical correction for undescended testes. Afr J Paediatr Surg. 2022;19(4):233-237.
- Hutson JM, et al. Germ cell development in the postnatal testis: the key to prevent malignancy in cryptorchidism? Front Endocrinol (Lausanne). 2012;3:176.
- Esposito S, et al. Inhibin B in healthy and cryptorchid boys. Ital J Pediatr. 2018;44(1):81.
- Verkauskas G, Malcius D, Dasevicius D, Hadziselimovic F. Histopathology of unilateral cryptorchidism. Pediatr Dev Pathol. 2019;22(1):53-58.
- Thorup J, et al. The relation between adult dark spermatogonia and other parameters of fertility potential in cryptorchid testes. J Urol. 2013;190(4 Suppl):1566-1571.