This protocol aims to evaluate the ability of the plasma atherosclerosis index (AIP) to differentiate hypertension in patients with obstructive sleep apnea-hypopnea syndrome (OSAHS) using retrospective clinical data and analysis of the subject's operation characteristic curve.
Research Article
Association between Atherogenic Index of Plasma and Hypertension in Patients with Obstructive Sleep Apnea-Hypopnea Syndrome—A Retrospective Study
In This Article
Summary
Abstract
This study aimed to investigate the relationship between the atherogenic index of plasma (AIP) and hypertension in patients with obstructive sleep apnea-hypopnea syndrome (OSAHS). A total of 381 OSAHS patients admitted to the hospital from January 2023 to December 2025 were retrospectively enrolled and divided into a hypertension group (n = 161) and a non-hypertension group (n = 220). Univariate and binary logistic regression analyses were performed to identify influencing factors. The Receiver Operating Characteristic (ROC) curve is used to evaluate the discriminative ability of the identified hypertension indicators. Significant differences between the two groups were observed in coronary heart disease, chronic obstructive pulmonary disease, Gastric Burning, chronic rhinitis, chronic pharyngitis, alcohol consumption, smoking, sedative use, strong tea consumption, family history, neck circumference, red cell distribution width-standard deviation (RDW-SD), aspartate aminotransferase (AST), blood urea nitrogen (BUN), and AIP (P < 0.05). Binary logistic regression indicated that both Coronary Heart Disease and AIP were independent factors for hypertension (P < 0.05). ROC analysis results showed that the AUC for AIP was 0.813 (95%CI: 0.767~0.859), with a standard error of 0.023 and Youden's index of 0.52, resulting in a sensitivity of 77.02% and specificity of 75.00%. These findings suggest that AIP was independently associated with the presence of hypertension in patients with OSAHS and showed moderate discriminatory ability for identifying patients with concomitant hypertension. However, the single-center design and limited sample size of this study warrant caution when generalizing the results.
Introduction
Obstructive sleep apnea-hypopnea syndrome (OSAHS), as a common respiratory system disorder, is characterized by recurrent collapse of the pharyngeal airway leading to intermittent reduction in airflow within the chest cavity during sleep. It not only results in periodic hypoxemia, sympathetic nervous system excitation, decreased sleep quality, and daytime sleepiness but is also closely associated with various cardiovascular abnormalities, particularly hypertension. The two conditions exhibit a bidirectional relationship, where the presence of one disease increases the risk of developing the other1,2. Currently, hypertension is a major risk factor for diseases such as coronary heart disease and stroke, significantly impacting the health of a large population worldwide. In OSAHS patients, the prevalence of hypertension is higher, and some patients do not receive timely diagnosis and treatment, thereby increasing the likelihood of early-onset preventable cardiovascular diseases3,4.
Atherogenic index of plasma (AIP), as an indicator reflecting lipid abnormalities and the degree of atherosclerosis, holds significant importance in cardiovascular disease research. Previous studies have indicated5,6 its association with the occurrence, progression, and mortality of cardiovascular-related diseases. However, research on the association between AIP and hypertension in patients with OSAHS is currently insufficient. Delving deeper into the connection between these two factors can help further elucidate the pathogenesis of hypertension in OSAHS, providing new insights and targets for clinical prevention, diagnosis, and treatment. This exploration holds crucial value for improving patient outcomes, reducing the burden of cardiovascular diseases, and offering valuable insights into the mechanisms underlying OSAHS-related hypertension.
This study hypothesized that (1) AIP is independently associated with hypertension in OSAHS patients, and (2) AIP showed discriminatory ability for identifying OSAHS patients with concomitant hypertension.
Protocol
This study has been approved by the Ethics Committee of the First Affiliated Hospital of Dalian Medical University (ethics approval number: PJ-KS-KY-2-25-1247, approval number: 2025.12.25). As this study is a retrospective study, informed consent is exempted. The reagents and the equipment used are listed in the Table of Materials.
1. Research object
381 patients diagnosed with OSAHS and admitted to the hospital from January 2023 to December 2025 were selected for this study. Patients were categorized into hypertensive (n = 161) and non-hypertensive (n = 220) groups based on the presence of hypertension, as defined by7: a diagnosis of hypertension was established when systolic blood pressure (SBP) ≥ 140 mmHg and/or diastolic blood pressure (DBP) ≥ 90 mmHg in three separate office measurements on different days in the absence of antihypertensive medications. Blood pressure was measured using a validated automated oscillometric device after the patient had rested in a seated position for at least 5 min, with the arm supported at heart level. Three readings were taken at 1 min intervals, and the average was recorded. Patients with a prior diagnosis of hypertension who were currently on antihypertensive medication were also included, irrespective of their current blood pressure values.
Inclusion criteria
(1) Patients meeting the diagnostic criteria for OSAHS with complete overnight polysomnography (PSG) showing an apnea-hypopnea index (AHI) ≥ 5 events/h8; (2) Patients with complete clinical data; (3) Patients aged >18 years.
Exclusion criteria
(1) Severe heart failure: New York Heart Association (NYHA) functional class III-IV; (2) Severe liver or kidney dysfunction; (3) Patients with malignant tumors; (4)The use of lipid-lowering medications (including statins and fibrates) within the 3 months prior to hospital admission.
2. General data collection
In this study, a comprehensive approach was employed to collect relevant information. This included patient demographics such as gender, age, coronary heart disease, chronic obstructive pulmonary disease (COPD), asthma, thyroid disease, Gastric Burning, chronic rhinitis, chronic pharyngitis, upper airway surgery, alcohol consumption, smoking, sedative use, strong tea consumption [Strong tea consumption was defined as drinking tea (any type) that was brewed with ≥3 g of tea leaves per 200 mL of water (or tea bags steeped for ≥5 min), consumed at least 5 days per week, and with a usual daily intake of ≥500 mL], coffee consumption, family history (Family history of OSAHS), body mass index (BMI), neck circumference, waist circumference, hip circumference, AHI, OSAHS severity, Apnea–Hypopnea Index(AHI)(REM), AHI (NREM), minimum oxygen saturation, hypoxemia, mean oxygen saturation, oxygen desaturation index, respiratory arousal index, arousal index, T90 percentage, longest apnea duration, slow wave sleep percentage, blood pressure patterns, among others.
3. Collection of laboratory-related indicators
Additionally, laboratory data were collected and measured in the fasting state in the morning, including white blood cell count (WBC), hemoglobin (Hb), platelet count (PLT), neutrophil count (NEU), lymphocyte count (LYM), red blood cell count (RBC), hematocrit (HCT), red cell distribution width-standard deviation (RDW-SD), mean corpuscular volume (MCV), platelet distribution width (PDW), mean platelet volume (MPV), monocyte count (MONO), plateletcrit (PCT), alanine aminotransferase (ALT), aspartate aminotransferase (AST), gamma-glutamyl transferase (γ-GT), blood urea nitrogen (BUN), uric acid (UA), creatinine (Cr), total cholesterol (TC), triglycerides (TG), high-density lipoprotein cholesterol (HDL-C), low-density lipoprotein cholesterol (LDL-C), fasting blood glucose (GLU), and others.
4. Quality control
All indicators are standardized laboratory processes, including indoor quality control (daily testing of high- and low-value quality controls) and inter-laboratory quality evaluation (regular participation in external proficiency testing) to ensure testing accuracy and reliability.
5. Biosafety and waste management
All blood samples were collected and handled in accordance with the institutional biosafety guidelines. Venipuncture was performed using sterile, single-use needles and vacuum tubes. After sample collection, needles were immediately discarded into puncture-proof sharps containers. All contaminated materials (e.g., gloves, gauze, used tubes, pipette tips) were disposed of as clinical biohazardous waste in labeled, leak-proof bags. Waste containers were sealed and incinerated by an authorized biomedical waste company. Work surfaces were decontaminated with 70% ethanol or 0.5% sodium hypochlorite solution before and after each procedure. Any accidental spill of blood or body fluids was covered with absorbent material, disinfected with 1% sodium hypochlorite for 30 min, and cleaned up using disposable forceps and absorbent pads; all cleaning materials were then discarded as biohazardous waste. Laboratory personnel wore appropriate personal protective equipment (PPE), including disposable gloves, lab coats, and face shields, during all sample processing steps. Hand hygiene was performed immediately after the removal of gloves.
6. The calculation method for AIP
AIP = log10(TG/HDL-C), using TG and HDL-C values in mmol/L9.
7. Statistical analysis
The collected experimental data were analyzed using SPSS software. Normality was assessed using the Shapiro-Wilk test. Normally distributed continuous data were presented as EQUATION ± S, compared using independent sample t-tests. Non-normally distributed data were represented by MQ2 (Q1, Q3) and analyzed using the Mann-Whitney U test. Categorical data were expressed as counts or percentages and compared using the χ2 test or Fisher's exact test. Factors influencing hypertension were analyzed using univariate and binary logistic regression. The Identification ability of indicators for hypertension in OSAHS patients was evaluated using receiver operating characteristic (ROC) curves, with P < 0.05 considered statistically significant differences.
Results
Comparison of clinical indicators between two groups of patients
Statistically significant differences were observed in the comparison of clinical indicators, including coronary heart disease, COPD, Gastric Burning, chronic rhinitis, chronic pharyngitis, alcohol consumption, smoking, sedative use, strong tea consumption, family history, and neck circumference between the two groups (P < 0.05), as shown in Table 1.
Comparison of laboratory parameters between the two groups of patients
Significant differences were also noted in the comparison of laboratory indicators, including RDW-SD, AST, BUN, and AIP between the two groups (P < 0.05), as presented in Table 2.
Binary logistic regression analysis of influencing factors
In the aforementioned analysis, significant variables were assigned values with [categorical variables set as (1 for "yes" and 0 for "no" ), and continuous variables retaining their original values]. TG, HDL-C, and AIP show high collinearity, and a more comprehensive AIP value is taken for calculation, excluding TG and HDL-C. Using hypertension as the dependent variable (hypertensive = 1, non-hypertensive = 0), binary logistic regression analysis results indicated that Coronary Heart Disease and AIP were influencing factors for hypertension in OSAHS patients (P < 0.05), as detailed in Table 3.
ROC curve analysis index prediction value
ROC analysis results showed that the AUC for Coronary Heart Disease was 0.570 (95%CI: 0.511~0.629), with a standard error of 0.030 and Youden's index of 0.14, yielding a sensitivity of 16.77% and specificity of 97.27%. For AIP, the AUC was 0.813 (95%CI: 0.767~0.859), with a standard error of 0.023 and Youden's index of 0.52, resulting in a sensitivity of 77.02% and specificity of 75.00%, as detailed in Table 4 and Figure 1.
DATA AVAILABILITY:
Data supporting the findings of this study are provided in Supplementary File 1.
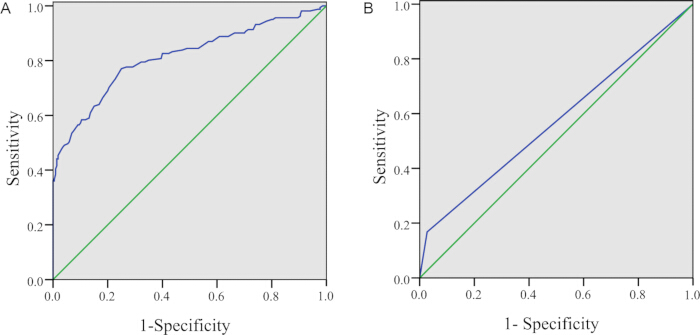
Figure 1: ROC Curves for Various Indicators. (A) represents the ROC curve for AIP, while (B) represents the ROC curve for coronary heart disease. Please click here to view a larger version of this figure.
| Indicator | Hypertension Group (n=161) | Non-Hypertension Group (n=220) | Z/t/χ2 Value | P Value | |
| Age (years) | 51.13±13.66 | 47.68±13.43 | 2.459 | 0.014 | |
| Gender | Male | 113 | 161 | 0.413 | 0.52 |
| Female | 48 | 59 | |||
| Coronary Heart Disease | Yes | 27 | 6 | 23.174 | <0.001 |
| No | 134 | 214 | |||
| COPD | Yes | 18 | 9 | 7.096 | 0.008 |
| No | 143 | 211 | |||
| Asthma | Yes | 12 | 10 | 1.445 | 0.229 |
| No | 149 | 210 | |||
| Thyroid Disease | Yes | 9 | 4 | 2.95 | 0.086 |
| No | 152 | 216 | |||
| Gastric Burning | Yes | 45 | 27 | 14.909 | <0.001 |
| No | 116 | 193 | |||
| Chronic Rhinitis | Yes | 52 | 44 | 7.46 | 0.006 |
| No | 109 | 176 | |||
| Chronic Pharyngitis | Yes | 58 | 38 | 17.344 | <0.001 |
| No | 103 | 182 | |||
| Upper Airway Surgery | Yes | 8 | 7 | 0.785 | 0.376 |
| No | 153 | 213 | |||
| Alcohol Drinking | Yes | 66 | 37 | 27.545 | <0.001 |
| No | 95 | 183 | |||
| Smoking | Yes | 59 | 36 | 20.432 | <0.001 |
| No | 102 | 184 | |||
| Sedative Use | Yes | 10 | 4 | 3.904 | 0.048 |
| No | 151 | 216 | |||
| Strong Tea Consumption | Yes | 23 | 15 | 5.774 | 0.016 |
| No | 138 | 205 | |||
| Coffee Consumption | Yes | 13 | 12 | 1.041 | 0.308 |
| No | 148 | 208 | |||
| Family History | Yes | 44 | 32 | 9.514 | 0.002 |
| No | 117 | 188 | |||
| BMI (kg/m2) | 29.15±4.77 | 29.05±5.22 | 0.191 | 0.848 | |
| Neck Circumference (cm) | 41.05±3.71 | 39.86±6.14 | 2.184 | 0.03 | |
| Waist Circumference (cm) | 80.56±8.82 | 79.75±10.76 | 0.782 | 0.435 | |
| Hip Circumference (cm) | 93.44±5.35 | 93.45±5.18 | 0.018 | 0.985 | |
| AHI | 47.00(25.70,66.30) | 45.80(22.63,73.45) | -0.215 | 0.83 | |
| OSA Severity | 1 | 14 | 31 | 3.882 | 0.144 |
| 2 | 38 | 39 | |||
| 3 | 109 | 150 | |||
| AHI (REM) | 50.30(29.90,68.70) | 51.90(27.68,69.38) | -0.182 | 0.856 | |
| AHI (NREM) | 47.00(25.10,66.50) | 44.70(19.55,75.45) | -0.026 | 0.979 | |
| Lowest Oxygen Saturation (%) | 83.00(76.50,87.00) | 81.00(72.00,87.00) | -1.159 | 0.246 | |
| Hypoxemia | None | 13 | 24 | 4.85 | 0.183 |
| Mild | 53 | 57 | |||
| Moderate | 38 | 41 | |||
| Severe | 58 | 98 | |||
| Mean Oxygen Saturation (%) | 94.00(93.00,96.00) | 95.00(92.25,96.00) | -0.281 | 0.778 | |
| Oxygen Desaturation Index | 34.70(17.35,58.35) | 34.50(14.98,66.60) | -0.15 | 0.881 | |
| Respiratory Arousal Index | 29.70(14.10,46.25) | 26.25(10.53,52.98) | -0.035 | 0.972 | |
| Arousal Index | 34.35(20.25,49.50) | 33.90(19.03,55.90) | -0.471 | 0.638 | |
| T90 Percentage | 2.40(0.30,12.75) | 3.80(0.20,16.25) | -0.657 | 0.511 | |
| Longest Apnea Time (s) | 50.00(35.00,76.00) | 53.00(36.00,70.00) | -0.01 | 0.992 | |
| Slow Wave Sleep Percentage | 12.20(5.10,20.00) | 10.85(3.10,19.48) | -1.12 | 0.263 | |
| Note: OSA Severity 1, 2, and 3 represent light, medium, and heavy, respectively | |||||
Table 1: Comparison of clinical indicators between two patient groups. Please click here to download this Table.
| Indicator | Hypertension Group (n=161) | Non-Hypertension Group (n=220) | Z Value | P Value |
| WBC (×109/L) | 6.92(5.68,8.43) | 6.81(5.44,8.85) | -0.404 | 0.686 |
| Hb (g/L) | 148.00(137.00,158.00) | 149.00(134.25,157.00) | -0.647 | 0.518 |
| PLT (×109/L) | 231.00(198.00,282.25) | 240.50(200.00,270.00) | -0.456 | 0.649 |
| NEU (×109/L) | 4.19(3.19,5.16) | 4.19(3.06,5.27) | -0.22 | 0.826 |
| LYM (×109/L) | 2.02(1.65,2.60) | 2.09(1.58,2.57) | -0.06 | 0.952 |
| RBC (×1012/L) | 4.85(4.51,5.17) | 4.91(4.51,5.22) | -0.292 | 0.77 |
| HCT ( %) | 43.55(40.33,46.68) | 44.20(40.50,46.45) | -0.024 | 0.981 |
| MCV (fL) | 89.55(87.35,92.68) | 90.00(88.00,92.60) | -0.317 | 0.751 |
| RDW-SD (fL) | 41.50(39.60,43.40) | 42.70(40.60,45.15) | -3.048 | 0.002 |
| PDW (fL) | 11.70(10.43,16.10) | 12.60(10.50,16.10) | -0.806 | 0.42 |
| MPV(fL) | 9.90(9.30,10.50) | 10.00(9.35,10.60) | -0.701 | 0.483 |
| PCT (%) | 0.23(0.19,0.27) | 0.24(0.20,0.26) | -0.697 | 0.486 |
| MONO(×109/L) | 0.44(0.34,0.59) | 0.45(0.35,0.55) | -0.23 | 0.818 |
| ALT (U/L) | 28.50(19.25,41.00) | 32.50(21.00,50.50) | -1.824 | 0.068 |
| AST (U/L) | 22.50(18.00,29.75) | 26.00(20.25,34.00) | -2.547 | 0.011 |
| γGT (U/L) | 37.00(24.00,59.00) | 37.50(24.75,65.25) | -1.116 | 0.264 |
| BUN (mmol/L) | 5.77(4.71,7.08) | 5.29(4.51,6.41) | -2.098 | 0.036 |
| Cr (μmol/L) | 73.50(62.75,85.25) | 70.50(62.00,81.00) | -1.154 | 0.249 |
| UA (μmol/L) | 401.00(287.00,465.00) | 377.00(323.00,433.00) | -0.504 | 0.614 |
| TC (mmol/L) | 4.76(4.22,5.57) | 4.70(4.06,5.75) | -0.002 | 0.998 |
| TG(mmol/L) | 2.32(1.74,3.44) | 1.43(0.98,1.81) | -10.292 | <0.001 |
| HDL-C(mmol/L) | 1.32(1.01,1.55) | 1.47(1.13,1.72) | -4.403 | <0.001 |
| AIP | 0.27(0.10,0.47) | -0.01(-0.15,0.13) | -10.029 | <0.001 |
| LDL-C (mmol/L) | 2.78(2.20,3.30) | 2.77(2.27,3.44) | -0.164 | 0.87 |
| GLU(mmol/L) | 5.60(4.98,6.35) | 5.31(4.93,6.09) | -1.435 | 0.151 |
Table 2: Comparison of laboratory indicators between two patient groups. Please click here to download this Table.
| Factor | β | Standard Error | Wald | P | Exp(β) | 95%CI |
| Coronary Heart Disease | 2.133 | 0.95 | 5.042 | 0.025 | 8.437 | 1.311~54.284 |
| COPD | 0.252 | 0.826 | 0.093 | 0.761 | 1.286 | 0.255~6.487 |
| Gastric Burning | 0.78 | 0.642 | 1.478 | 0.224 | 2.182 | 0.620~7.679 |
| Chronic Rhinitis | -0.273 | 0.623 | 0.192 | 0.662 | 0.761 | 0.224~2.582 |
| Chronic Pharyngitis | -0.526 | 0.717 | 0.538 | 0.463 | 0.591 | 0.145~2.409 |
| Alcohol Drinking | 0.672 | 0.776 | 0.75 | 0.386 | 1.958 | 0.428~8.958 |
| Smoking | -0.321 | 0.682 | 0.222 | 0.638 | 0.725 | 0.191~2.759 |
| Sedative Use | 1.219 | 1.191 | 1.047 | 0.306 | 3.382 | 0.328~34.927 |
| Strong Tea Consumption | 0.066 | 0.838 | 0.006 | 0.937 | 1.068 | 0.207~5.523 |
| Family History | 0.499 | 0.757 | 0.434 | 0.51 | 1.647 | 0.374~7.262 |
| RDW-SD | -0.009 | 0.04 | 0.052 | 0.819 | 0.991 | 0.915~1.072 |
| AST | -0.044 | 0.025 | 3.118 | 0.077 | 0.957 | 0.911~1.005 |
| AIP | 0.81 | 0.152 | 28.432 | <0.001 | 2.249 | 1.670~3.029 |
| Neck Circumference | 0.109 | 0.079 | 1.9 | 0.168 | 1.115 | 0.955~1.302 |
| BUN | 0.24 | 0.142 | 2.883 | 0.089 | 1.272 | 0.964~1.679 |
| Age | 0.02 | 0.023 | 0.708 | 0.4 | 1.02 | 0.974~1.067 |
| constant | -6.775 | 4.204 | 2.597 | 0.107 | 0.001 | - |
Table 3: Binary logistic regression analysis of influencing factors. Please click here to download this Table.
| Indicator | AUC | Standard Error | 95%CI | Youden | Sensitivity | Specificity |
| Coronary Heart Disease | 0.57 | 0.03 | 0.511~0.629 | 0.14 | 16.77 | 97.27 |
| AIP | 0.813 | 0.023 | 0.767~0.859 | 0.52 | 77.02 | 75 |
Table 4: ROC analysis results. Please click here to download this Table.
Supplementary File 1: Data supporting the findings of this study.Please click here to download this file.
Discussion
Numerous studies have confirmed a close association between OSAHS and hypertension. It has been reported1 that approximately 30%–50% of OSAHS patients also suffer from hypertension, with at least 30% of hypertensive patients having concurrent OSAHS. In OSAHS patients, repeated collapse of the airway during sleep leads to episodes of apnea or hypopnea, triggering heightened sympathetic nervous system activity. This state of sympathetic excitation counteracts the natural nocturnal decrease in blood pressure, maintaining elevated intravascular pressure and contributing to non-dipper hypertension. Prolonged hypertension not only accelerates the progression of atherosclerosis but also increases the risk of cardiovascular diseases.
This study found that AIP was independently associated with the presence of hypertension in patients with OSAHS and showed moderate discriminatory ability for identifying patients with concomitant hypertension. The rationale behind this finding may be attributed to the abnormal respiratory patterns in OSAHS patients during sleep, leading to intermittent hypoxemia and hypercapnia. Such respiratory abnormalities disrupt lipid metabolism, resulting in elevated TG levels and decreased HDL-C levels10. Elevated TG levels promote lipid deposition in the vascular wall, while HDL-C plays a protective role against atherosclerosis; thus, reduced HDL-C levels weaken vascular protection. AIP integrates these changes and more accurately reflects the degree of lipid metabolism disruption, a crucial factor in atherosclerosis development, which is closely linked to the occurrence and progression of hypertension11,12. In terms of neuroendocrine aspects, the periodic hypoxemia induced by OSAHS activates the sympathetic nervous system, leading to increased secretion of catecholamines and other hormones. These hormones not only directly affect blood vessels, causing vasoconstriction and increased blood pressure, but also impact lipid metabolism, exacerbating lipid abnormalities. AIP, as an indicator of lipid metabolism, indirectly reflects the impact of this neuroendocrine disruption on the cardiovascular system, thereby predicting the occurrence of hypertension to a certain extent and providing clues for predicting hypertension in OSAHS patients13,14. Higher AIP values indicate a greater risk of atherosclerosis. Compared to solely examining TG or HDL-C levels, the advantage of AIP lies in its ability to comprehensively reflect the complexity of lipid metabolism in the body, revealing many health issues related to cardiovascular diseases. Previous studies15 have validated its association with stroke risk, and in this study, AIP was independently associated with the presence of hypertension in patients with OSAHS and showed moderate discriminatory ability for identifying patients with concomitant hypertension, further emphasizing the crucial role of lipid metabolism abnormalities in the development of atherosclerosis associated with OSAHS-related hypertension.
The results of this study demonstrate that when predicting hypertension in patients with OSAHS, the AUC for AIP alone was 0.813 (95% CI: 0.767~0.859). The specificity (77.02%) and sensitivity (75.00%) of using AIP alone to identify hypertension indicate that AIP results are more supportive of the existence of hypertension. If AIP is used as the only screening tool, some hypertensive patients may be missed, and special attention should be paid to this. This suggests that in assessing the risk of hypertension in OSAHS patients, reliance on a single indicator may not be sufficient. OSAHS is a multifactorial disease, where the process leading to hypertension and subsequent atherosclerosis involves disruptions in multiple physiological systems, including the neuroendocrine system, cardiovascular system, and respiratory system. The periodic hypoxemia and hypercapnia caused by OSAHS lead to sympathetic nervous system activation, promoting elevated blood pressure. Additionally, the hypoxic state activates the renin-angiotensin-aldosterone system, increasing peripheral resistance, vascular constriction, and sodium and water retention, further exacerbating hypertension. Lipid metabolism abnormalities, reflected by the imbalance in TG and HDL-C as indicated by AIP, promote atherosclerosis formation, acting in conjunction with hypertension to accelerate the occurrence and progression of cardiovascular diseases16,17. Therefore, a comprehensive assessment using multiple indicators can more comprehensively reflect the pathophysiological status of hypertension in OSAHS patients, enhancing the accuracy and reliability of predictions. Prior studies by Mo D et al.18 have elucidated the relationship between AIP and hypertension, further validating the findings of this study. In addition to AIP, this study also identified factors such as AST that are related to hypertension in OSAHS patients. These indicators reflect the patients' physical condition and disease risks from different perspectives. Their combined use can provide clinicians with richer information, aiding in the formulation of more precise personalized treatment plans.
The findings of this study hold significant implications for clinical practice. Firstly, for OSAHS patients, especially those with concomitant hypertension, monitoring of lipid indicators such as AIP should be prioritized. Regular monitoring of AIP can provide timely insights into the patient's lipid metabolism status, allowing for the assessment of their risks for atherosclerosis and cardiovascular diseases19. In cases where elevated AIP levels are identified, physicians can further investigate other cardiovascular disease-related indicators in patients, such as blood pressure, blood sugar, and lipid profiles, as well as conduct atherosclerosis-related examinations like pulse wave velocity and dynamic arterial stiffness index to detect potential cardiovascular risks early. Secondly, based on the study results, comprehensive intervention measures should be implemented for OSAHS patients with high AIP values or other cardiovascular disease risk factors20. Regarding lifestyle modifications, patients should be advised to maintain a healthy diet by reducing saturated fats, trans fats, and cholesterol intake while increasing dietary fiber, fruits, vegetables, and whole grains intake. Weight control is crucial, emphasizing the reduction of abdominal fat accumulation. Smoking cessation and alcohol moderation are recommended to mitigate adverse effects on lipid metabolism and the cardiovascular system. Moderate exercise involving aerobic, strength, flexibility, and balance training should be integrated to enhance overall physical fitness. In terms of pharmacological treatment, physicians can choose suitable antihypertensive medications like ACE inhibitors and/or ARBs based on individual patient profiles, as these medications have blood pressure-lowering effects across all sleep stages. For patients with lipid abnormalities, statins may be considered to lower LDL cholesterol and triglycerides while increasing HDL cholesterol, thereby improving AIP values.
While this study has achieved certain results, it also has some limitations. Firstly, it is a single-center study with a relatively limited sample size, which may introduce some selection bias and restrict the generalizability of the research findings. Future studies should be conducted with a multi-center approach and larger sample sizes to further validate the reliability and universality of the results obtained in this study. Secondly, this study only observed the value of indicators like AIP in predicting hypertension in OSAHS patients, without delving into the underlying molecular biology mechanisms. Future research could delve into basic research to explore the molecular signaling pathways and cellular mechanisms underlying OSAHS, hypertension, lipid metabolism abnormalities, and atherosclerosis, providing a more profound theoretical basis for clinical treatment. Additionally, this study did not conduct long-term follow-up observations on patient prognosis. Prospective cohort studies could be conducted in the future to observe the relationship between indicators like AIP and the occurrence of cardiovascular events in OSAHS patients with hypertension, assessing the effects of comprehensive intervention measures on improving patient outcomes to provide more comprehensive evidence-based support for clinical practices.
In conclusion, this study found that AIP was independently associated with the presence of hypertension in patients with OSAHS and showed moderate discriminatory ability for identifying patients with concomitant hypertension. This result offers new perspectives and methods for clinically assessing the risk of hypertension in OSAHS patients, aiding in the early detection of potential cardiovascular risks, the implementation of effective intervention measures, and the improvement of patient prognosis. Future research should further expand sample sizes, delve into mechanisms, and observe long-term outcomes to provide more scientifically and comprehensively guided directions for clinical practice.
Disclosures
The authors declare that they have no conflicts of interest relevant to this work.
Acknowledgements
The authors would like to thank the clinical staff at the First Affiliated Hospital of Dalian Medical University for their assistance during the study, as well as all the participants involved. This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Flow cytometer | Beckman Coulter | CytoFLEX | Classify and count cells |
| Fully automated biochemical analyzer | Roche | Cobas c702 | Analyze liver and kidney function, blood lipids, and other indicators |
| Fully automated blood analyzer | Sysmex Corporation | XN - 9000 | Measure cell volume distribution, hemoglobin, hematocrit |
| SPSS 27.0 | International Business Machines Corporation | 27 | Analyze all data |
| Vacuum blood collection tubes (with EDTA anticoagulant) | BD Biosciences | 367863 | Used for collecting venous blood |
Reprints and Permissions
This article has been published
Video Coming Soon