This study evaluated whether lifestyle and gynecologic oncology nursing interventions improve quality of life in women with gynecologic cancers. A significant improvement was observed only in the ovarian cancer subgroup at 6 months, while the overall evidence remained very uncertain because of substantial heterogeneity, small subgroup sizes, and methodological limitations.
Research Article
A Meta-Analysis of the Impact of Lifestyle and Gynecologic Oncology Nursing Interventions on the Enhancement of Quality of Life
* These authors contributed equally
In This Article
Summary
Abstract
This meta-analysis evaluated the impact of lifestyle and gynecologic oncology nursing interventions on quality of life (QoL). A systematic search conducted through June 2026 identified 1,123 records. Thirteen randomized controlled trials involving 915 women with gynecologic cancer were included. The impact of lifestyle and gynecologic oncology nursing interventions on QoL was evaluated using pooled mean differences (MDs) with 95% confidence intervals, using random-effects models for the general analyses and fixed-effect models for the cancer-specific subgroup analyses. Compared with controls, interventions significantly improved QoL in women with ovarian cancer (MD 4.28, 95% CI: 0.45–8.10, p = 0.03; I2 = 0%). No significant differences emerged for 6-month QoL in mixed cancers (MD 2.11, 95% CI: -0.90–5.12, p = 0.17; I2 = 71%), endometrial cancer at 6 months (MD 2.00, 95% CI: –1.49–5.49, p = 0.26; I2 = 0%) or mixed cancers at 3 months (MD 6.43, 95% CI: –0.16–13.01, p = 0.06; I2 = 74%). However, marked heterogeneity, varied designs and interventions, small sample sizes, and variable risk of bias limit the certainty of the findings, which warrant cautious interpretation and confirmation through robust, standardized trials. Lifestyle and gynecologic oncology nursing interventions significantly improved QoL only in women with ovarian cancer at 6 months. However, substantial heterogeneity, methodological limitations, and very low-certainty evidence warrant cautious interpretation, and larger standardized trials are needed.
Introduction
Cancer originating in the female reproductive organs is termed gynecologic cancer. Gynecologic cancers, encompassing cervical, ovarian, uterine, vaginal, and vulvar malignancies, remain a substantial public health concern, affecting millions of women globally1. These tumors are not only physically devastating but also cause significant emotional and psychological distress. Despite advancements in treatment, the global frequency of these tumors is increasing, and the overall prognosis remains unfavorable in several regions, particularly where healthcare access is restricted. Studies on gynecologic oncology nursing care underscore the need for comprehensive, interdisciplinary strategies in patient management, given the significant impact of these malignancies on women's quality of life2. Conversely, successful nurse interventions extend beyond managing physical symptoms such as pain and nausea; they also include emotional support, psychological counseling, patient education, and comprehensive symptom management. These interventions are crucial for improving patient outcomes, helping women navigate the complexities of treatment protocols, and ensuring holistic care.
The role of nursing interventions in quality of life warrants further investigation, particularly regarding how different facets of nursing care affect physical, emotional, and psychological well-being across varied patient demographics3. Effective nursing care for cancer patients can improve their overall well-being. Gynecologic oncology nursing care is a specialized nursing discipline focused on providing comprehensive support to women diagnosed with gynecologic cancer. Gynecologic cancer encompasses granulosa cell tumors, genital tract melanoma, cervical cancer amenable to fertility-sparing surgery, and endometrial cancer4. The prevalence of cervical cancer has decreased throughout Europe; however, it continues to pose a considerable public health challenge. This is emphasized by 2018 statistics indicating 61,000 new cases and 25,800 fatalities. Survival results demonstrate regional inequalities, with a five-year relative survival rate of 62% from 2000 to 2007, varying from 57% in Eastern Europe to 67% in Northern Europe.
Cervical cancer continues to be a major worldwide health concern despite progress in prevention and treatment. These inequalities highlight the need for targeted nurse interventions to improve patient outcomes and address care inequities across different settings. Additional gynecologic malignancies, such as ovarian, uterine, and vulvar tumors, pose considerable health difficulties. Ovarian cancer is the predominant cause of gynecologic cancer-related death globally, with more than 300,000 new cases and 185,000 deaths per year. The survival rates for ovarian and uterine malignancies typically surpass those of cervical cancer; nonetheless, notable discrepancies persist among countries and regions. Like cervical cancer, these disparities are affected by healthcare accessibility, early detection methodologies, and treatment options. Targeted nursing interventions are essential for these cancers to improve outcomes and enhance the quality of life for women worldwide5.
Gynecologic oncology nurses deliver holistic, patient-focused care that extends beyond emotional support. In addition to providing emotional support, they facilitate treatment planning, advocate for patients' needs, and guide them through the therapy process. Effective therapies encompass symptom management, including pain alleviation, fatigue reduction, and nausea control, psychological therapy, and educational programs for patients that enhance both emotional and physical outcomes6. Multidisciplinary treatment strategies that include psychological support with physical therapy have been particularly beneficial in improving quality of life. Consequently, gynecologic oncology nurses are integral to symptom management, patient education, and comprehensive treatment, thereby enhancing patient outcomes6. This specialist nursing care includes delivering chemotherapy, monitoring and interpreting vital signs, analyzing treatment responses, and providing comprehensive support, all of which necessitate particular training and skill in cancer nursing7.
Nursing care significantly enhances individuals' well-being in diverse healthcare environments. Hospitals provide treatment, monitor patients' conditions, and collaborate with the medical team. Nurses in home-care centers deliver continuous support, oversee chronic diseases, and assist patients in preserving their independence8. Quality of life includes physical, mental, emotional, and social well-being. Nursing care is essential in improving these facets through specific interventions. Continuous care for patients with chronic diseases encompasses monitoring vital signs, administering medications, and instructing in self-management techniques8. These nursing interventions effectively manage chronic diseases, reducing symptoms and improving physical health, thereby increasing overall quality of life.
Gynecologic cancers constitute a substantial public health concern for women worldwide, with over 1 million diagnoses per year, resulting in considerable physical impairments and psychosocial disorders, thereby diminishing quality of life9. Research indicates that as many as 40% of women diagnosed with gynecologic cancers endure considerable mental anguish, while 60% indicate a deterioration in health-related quality of life during treatment (Global Cancer Statistics and Reports)10. Smits et al. found no significant effects from similar treatments, underscoring the importance of participant engagement and implementation quality in determining outcomes11. The study underscores the critical role of nurses in sickness prevention, promoting healthy lifestyles, and addressing patients' physical and emotional needs.
The present study seeks to assess the effects of lifestyle interventions and gynecologic oncology nursing care on enhancing the quality of life of women diagnosed with gynecologic malignancies, using a systematic review and meta-analysis. The study aims to assess the impact of specific lifestyle interventions and gynecologic oncology nursing care on essential quality-of-life aspects, including physical, emotional, and social well-being. Focusing on standardized quality-of-life measurements and explicitly specified intervention strategies provides practical data on the effectiveness of these methods. This study specifically examines the short-term effects (within six months) of intensive psychological nursing care on emotional and social well-being. This targeted methodology provides a comprehensive analysis of the impact of specific interventions on quality-of-life outcomes and offers evidence to guide personalized care strategies.
Previous systematic reviews, including that by Smits et al.11, primarily evaluated lifestyle interventions in women with endometrial and ovarian cancer, and included relatively few studies. Since then, additional evidence has become available, and no systematic review has comprehensively evaluated both lifestyle interventions and gynecologic oncology nursing care across a broader range of gynecologic malignancies. Therefore, this systematic review and meta-analysis aimed to synthesize the current evidence regarding the effects of these interventions on quality of life.
Protocol
Eligibility criteria
Studies were eligible if they met all of the following criteria: (1) included women with any gynecologic malignancy; (2) evaluated a defined lifestyle intervention or a nursing‑led intervention; (3) reported quantitative quality‑of‑life data; and (4) were either comparative (intervention vs. control) or observational trajectory studies that provided relevant descriptive QoL data (5) were published in English. . For the quantitative meta‑analysis of intervention versus control, a concurrent comparator group was required12. Two studies without a comparator were retained for narrative synthesis only13. No geographic restrictions were applied.
Information sources
The full study selection process is shown in Figure 1 as a PRISMA flow diagram. The Cochrane Library, Embase, Google Scholar, OVID, and PubMed were searched from database inception through June 2026. Retrieved records were imported into EndNote 20, and duplicate records were removed. Two reviewers independently screened titles and abstracts, followed by full-text assessment of potentially eligible studies. Disagreements were resolved by discussion. Only English-language publications were considered for inclusion, consistent with the prespecified eligibility criteria.
Search strategy
The search strategy was developed using the PICOS framework: Population—women with gynecologic oncology; Intervention—lifestyle or nursing interventions; Comparison—usual care or alternative interventions; Outcome—quality of life; Study design—no restrictions14. A comprehensive set of keywords and controlled vocabulary terms was used across all databases; the detailed search strings for each database are provided in Table 113.
Selection process
Following full‑text retrieval, two reviewers independently verified that each report met all eligibility criteria. They additionally cross‑checked author lists, trial names (e.g., SUCCEED, WALC, BENITA, TOPCAT‑G), recruitment periods, and study centers to identify overlapping patient cohorts. Potentially overlapping patient cohorts were identified and documented. When overlapping reports contributed to the primary analysis, their influence was evaluated in a prespecified sensitivity analysis that excluded the overlapping dataset.
Data extraction and outcome measures
Two reviewers independently extracted data from all 15 included reports using a standardized, piloted data‑extraction form. Disagreements were resolved by consensus with the corresponding author. For each study, the following information was recorded: first author, publication year, country, study design, cancer type, intervention description, comparator description, sample size per group, participant age and disease stage, quality‑of‑life (QoL) instrument, time points assessed, and all numerical QoL data (means, measures of dispersion, and sample sizes per arm)15.
Quantitative pooling (13 comparative studies)
For the meta‑analysis of intervention versus control, post-intervention final scores (means and standard deviations) were extracted at the prespecified time points (3 and 6 months) for both groups. Where a study reported both final and change scores, only final scores were extracted16. The methodological approach to meta-analysis and assessment of study quality followed established Cochrane guidance17. The choice of meta-analytic model considered anticipated clinical and methodological heterogeneity across studies18, and statistical heterogeneity was quantified using the I2 statistic as described by Higgins et al.19. The 13 comparative studies included in the quantitative synthesis are summarized in Table 220,21,22,23,24,25,26,27,28,29,30,31,32.
Quality‑of‑life outcome measures, alignment, and effect metric
The specific QoL instrument used in each study was recorded. The identified scales included the Functional Assessment of Cancer Therapy – General (FACT‑G), FACT‑Ovarian (FACT‑O), FACT‑Endometrial (FACT‑En), the European Organization for Research and Treatment of Cancer Quality of Life Questionnaire Core 30 (EORTC QLQ‑C30), the Short Form‑36 (SF‑36), and condition‑specific scales. For all instruments, higher scores indicated better quality of life, and no reverse‑scored instruments were included. All extracted QoL data were therefore aligned to the same metric, with a positive mean difference (MD) consistently favoring the intervention group.
For the primary meta‑analysis, post-intervention final scores were extracted rather than change‑from‑baseline scores. This decision was based on: (i) not all studies reported change scores or their standard deviations; (ii) final scores reflect the absolute post‑treatment QoL status, which is clinically meaningful; and (iii) using final scores maximized the number of studies that could be pooled. When a study reported multiple QoL subscales, the global QoL score or total FACT-G score was prioritized as the primary outcome; if unavailable, the physical-function subscale was used, with this deviation explicitly footnoted in Table 2.
The raw MD was used as the effect measure rather than the standardized mean difference (SMD) because all included instruments are validated to measure the same underlying construct—health-related quality of life—on conceptually similar scales (total scores range 0–100 or 0–148). The MD is directly interpretable in the original units of these scales and is more clinically meaningful than an SMD expressed in standard‑deviation units. Adjusted estimates (e.g., ANCOVA‑adjusted means) were not used because the adjustment covariates varied widely across studies, compromising comparability.
Standard deviation conversions
When studies reported standard errors (SEs) or 95% confidence intervals instead of standard deviations, they were converted to SDs using standard formulas: SD = SE × √n for SEs, and SD = √n × (upper CI – lower CI) / (2 × 1.96) for 95% CIs. For studies presenting medians with interquartile ranges (IQR), means, or SDs were not imputed; such data were extracted narratively and were not included in the pooled MD calculations. No such imputation was required for the 13 studies that contributed to the quantitative synthesis.
Missing data handling
Intention-to-treat (ITT) estimates were preferentially extracted when explicitly reported, as they provide the most conservative and unbiased estimate of the treatment effect. Where ITT data were unavailable, per-protocol or complete-case data were extracted as reported by the original authors. Missing means, SDs, or outcome values were not imputed; missingness was recorded for each study and accounted for in the sensitivity analysis. Studies with unreported SDs for key time points were noted, and the corresponding authors were contacted by email to request the missing statistics. If no response was received within two weeks, the most conservative available data were used (e.g., pooled baseline SD if post‑intervention SD was missing) or the specific time point was excluded from pooling.
Multiple intervention arms and shared controls
No included study presented more than one active lifestyle/nursing intervention arm compared with a single shared control group, which would have required splitting the control sample for analysis. In the one factorial‑designed study (McCloy et al.30), data were extracted from the combined exercise-and-mindfulness arm and the usual‑care control arm to simplify pooling and avoid double‑counting. For the overlapping SUCCEED trial cohorts (Von Gruenigen et al.21 and McCarroll et al.23), both reports were retained in the extraction table. For the primary meta‑analysis, both datasets were included (as they reported QoL at the same time point). In a prespecified sensitivity analysis, the latter report was excluded to assess the impact of cohort duplication on the pooled estimate; results are reported in the text.
Non‑comparative observational studies
For two reports (Budisan et al.33 and Betea et al.34), which lacked a concurrent control group, intervention-versus-control comparative data were not extracted (i.e., no MD could be computed). Instead, descriptive QoL trajectory data were extracted (within‑group changes over time) and presented narratively in the text and in Table 2. They were not included in any forest plot or pooled quantitative synthesis.
Risk of bias assessment
Potential publication bias and other small‑study effects were assessed using both visual inspection of funnel plots and Egger's linear regression test (which regresses the standardized intervention effect on its precision). Because Egger's test has limited statistical power when the number of studies is small (generally <10), funnel plots and Egger's tests were prespecified and would be performed only for meta‑analyses comprising 10 or more studies. For outcomes with fewer than 10 contributing studies, funnel plots and Egger p-values are not reported, as such tests are underpowered and may yield misleading results17.
Two reviewers independently assessed the methodological quality of the 15 included reports, and disagreements were resolved through discussion with the corresponding authors. Because the included studies comprised both randomized controlled trials (RCTs; n = 13) and non‑randomized observational cohort studies (n = 2; Budisan et al.33; Betea et al.34), design-specific tools were applied.
For RCTs (13 studies), the Cochrane RoB 2.0 tool was used (revised version), evaluating each study across five domains17: (1) Randomization process -- sequence generation and allocation concealment; (2) Deviations from intended interventions -- blinding of participants and personnel, and whether the analysis was intention‑to‑treat; (3) Missing outcome data -- completeness of follow‑up and handling of dropouts; (4) Measurement of the outcome -- blinding of outcome assessors (particularly relevant for self‑reported QoL, where blinding is less feasible but still considered); (5) Selection of the reported result -- risk of selective outcome reporting (checked against trial registries or published protocols where available).
Each domain was rated as low risk, some concerns, or high risk. An overall risk‑of‑bias judgment was then assigned for each study: low (all domains low), some concerns (one or more domains with some concerns), or high (any domain rated high risk or multiple domains with some concerns). For self‑reported outcomes such as quality of life, blinding participants is often infeasible; a high-risk judgment was therefore not automatically assigned for lack of participant blinding. Instead, lack of blinding was explicitly noted as a potential source of performance bias in the domain 2 assessment.
For non-randomized observational cohort studies (2 studies), Budisan et al.33 and Betea et al.34 did not include a concurrent comparator group and were not pooled in the quantitative meta‑analysis. For these, the Newcastle-Ottawa Scale (NOS) was used, adapted for cohort studies, to assess selection, comparability (not applicable due to the lack of a comparator), and outcome ascertainment. However, because they lacked a control arm, they were judged to be at high risk of confounding and selection bias in any causal inference. They were retained only for descriptive purposes; their risk-of-bias profiles do not affect the pooled effect estimates, but they are documented in Table 2.
Summary of risk of bias
A risk-of-bias summary figure (traffic-light plot) was created, displaying domain‑level judgments for each RCT. In brief, the most common concerns across RCTs were: (i) lack of blinding of participants and personnel to lifestyle interventions (domain 2 – some concerns/high risk in 9 of 13 studies), and (ii) incomplete outcome data due to attrition (domain 3 – some concerns in 4 studies). No study was rated as low risk across all domains; the majority (8/13) had some concerns, and 5/13 were rated high risk overall, primarily due to lack of blinding and small sample sizes leading to imprecision.
Certainty of evidence (GRADE)
The overall certainty of the body of evidence was assessed for each pooled outcome using the Grading of Recommendations Assessment, Development and Evaluation (GRADE) framework, following the GRADE Handbook and using GRADEpro GDT software. Certainty was rated as high, moderate, low, or very low across five domains: risk of bias, inconsistency, indirectness, imprecision, and publication bias. Outcomes assessed include (1) QoL at 6 months – general Gynecologic Oncology (pooled MD from 9 comparative studies); (2) QoL at 6 months – ovarian cancer (pooled MD from 2 comparative studies); (3) QoL at 6 months – endometrial cancer (pooled MD from 4 comparative studies, including overlapping SUCCEED cohorts); (4) QoL at 3 months – general Gynecologic Oncology (pooled MD from 6 comparative studies).
Effect measure and meta‑analysis model
Random-effects inverse-variance models were used for the general 6-month and 3-month analyses because substantial clinical and methodological heterogeneity was anticipated across studies, including differences in cancer types, intervention components, intensity, duration, and control conditions18. Fixed-effect inverse-variance models were used for the ovarian and endometrial cancer subgroup analyses, for which no statistical heterogeneity was observed (I2 = 0%). Heterogeneity was assessed using the I2 statistic19.
Heterogeneity was quantified using the I2 statistic, with thresholds of 25%, 50%, and 75% representing low, moderate, and high heterogeneity, respectively. In addition to I2, τ2 was reported for random-effects analyses to quantify the absolute magnitude of between-study variance. All analyses were performed using the meta and metafor packages in R (version 4.3.1).
Justification for pooling despite substantial heterogeneity and handling of heterogeneity
For the primary 6-month analysis, I2 = 71% indicated substantial heterogeneity. Pooling was considered appropriate under the random-effects model for the following reasons: (i) the pooled estimate represents the average effect across a range of interventions and populations, which is a legitimate summary question; (ii) the random-effects model explicitly incorporates between‑study variance (τ2) into the standard error, reducing the risk of falsely narrow confidence intervals; (iii) prespecified subgroup analyses were conducted by cancer type (ovarian, endometrial) to explain clinical sources of heterogeneity; (iv) influence and sensitivity analyses were performed to assess the robustness of the pooled estimate.
The decision to pool studies despite substantial statistical heterogeneity was guided by the following principles: I2 interpretation — I2 values of 25%, 50%, and 75% were prespecified to represent low, moderate, and high heterogeneity, respectively. An I2 exceeding 75% indicates considerable heterogeneity, which may make pooling inappropriate if the heterogeneity cannot be meaningfully explained by clinical or methodological factors. For the primary 6‑month general analysis (I2 = 71%), subgroup analyses by cancer type (ovarian, endometrial) were prespecified to explore clinical sources of heterogeneity. Subgrouping substantially reduced I2 to 0% in both ovarian and endometrial subgroups, suggesting that a major portion of the overall heterogeneity is attributable to differences in cancer type and associated intervention targets. However, because these subgroups contain very few studies, it cannot be reliably concluded that heterogeneity is fully explained.
Proceeding with pooling was considered justified for the general 6‑month analysis because: (i) it provides a summary average effect across a broad range of interventions, which is a legitimate meta‑analytic question; (ii) τ2 is explicitly reported to quantify between‑study variance; (iii) influence analyses were performed to check for outlier‑driven results; and (iv) the pooled estimate is not treated as definitive or clinically actionable — it is interpreted as hypothesis‑generating and is heavily caveated in the discussion.
In alignment with the Cochrane Handbook, when I2 exceeds 75%, and subgroup analyses do not convincingly explain the heterogeneity, pooled estimates should be interpreted with extreme caution. Given the small number of studies in the subgroups, it cannot be confidently asserted that heterogeneity is fully explained. Therefore, the primary pooled estimate is presented primarily for descriptive and exploratory purposes and does not form the basis for clinical recommendations. All heterogeneity statistics (I2, τ2) and sensitivity analyses are reported transparently, allowing readers to assess the stability of the estimates themselves.
Subgroup, sensitivity, and influence analyses
To explore sources of heterogeneity, the following prespecified analyses were performed, without conducting meta‑regression: 1) For subgroup analyses, the general 6-month outcome was stratified by cancer type (ovarian, endometrial) to examine whether the effect differed by tumor site; 2) Sensitivity analysis (overlapping cohorts): To assess the impact of the overlapping SUCCEED trial cohorts (Von Gruenigen et al.21 and McCarroll et al.23), the endometrial subgroup analysis was repeated excluding McCarroll et al.23. 3) Leave‑one‑out influence analysis: Each study was sequentially removed, and the pooled MD and I2 were recalculated for the general 6‑month outcome to identify whether any single study disproportionately drove the results or the heterogeneity; 4) Fixed‑effect model comparison: For completeness, pooled estimates were also computed under a fixed‑effect model (inverse‑variance weighting) to compare with the random‑effects results; any substantial discrepancy would indicate that between‑study heterogeneity meaningfully influences the estimate.
Meta-regression was not performed to explore continuous covariates (e.g., age, baseline QoL, intervention duration) because the number of studies per subgroup (≤9 for the general 6‑month outcome) is insufficient to yield reliable regression coefficients. With <10 studies per covariate, meta‑regression is highly underpowered and prone to type I errors, and the available covariate data were inconsistently reported across studies.
Publication bias
None of the pooled outcomes included 10 or more studies. Therefore, funnel plots and Egger's regression tests were not performed because these assessments would be underpowered and potentially misleading given the number of studies available.
Results
Study selection
A systematic literature search of PubMed, Embase, Cochrane Library, Ovid, and Google Scholar through June 2026 identified 1,123 records. After removing 897 duplicates, 226 records underwent title and abstract screening. Of these, 124 records were excluded based on the eligibility criteria. Full-text assessment was performed for 102 reports, of which 89 were excluded with reasons documented in the PRISMA flow diagram (Figure 1; Supplementary File 1). Ultimately, 15 reports met the inclusion criteria and were included in the systematic review, comprising 13 comparative randomized controlled trials and 2 non-comparative observational studies. Thirteen randomized controlled trials provided extractable intervention-versus-control data for quantitative meta-analysis, while two observational studies were retained for narrative synthesis only20,21,22,23,24,25,26,27,28,29,30,31,32.
Figure 1 presents the PRISMA 2020 flow diagram detailing the screening and selection process. The 13 were randomized controlled trials provided extractable intervention-versus-control data for quantitative meta-analysis20,21,22,23,24,25,26,27,28,29,30,31,32.
Study characteristics
The characteristics of the 15 included reports are summarized in Table 2. Thirteen comparative RCTs contributed data to the quantitative synthesis, whereas two observational studies were retained for narrative synthesis only. Across the 13 comparative RCTs, 915 women were included, with 468 participants allocated to lifestyle or nursing intervention groups and 447 to control groups as originally reported.
For the quantitative meta-analyses, the 13 comparative RCTs contributed 915 participants (468 intervention, 447 control). The included RCTs were published between 2009 and 2025 and were conducted across multiple countries, including the United States, Denmark, the United Kingdom, China, Egypt, and Romania. Cancer types included ovarian cancer (2 studies), endometrial cancer (4 studies), and mixed gynecologic cancers (7 studies). The interventions varied widely and included: structured exercise programs, dietary modification, weight-loss counseling, psychoeducational sessions, nurse-led follow-up, patient-initiated care, app-based mindfulness, and combined lifestyle interventions. Follow-up durations ranged from 3 to 6 months.
Quality-of-life assessment instruments included: Functional Assessment of Cancer Therapy–General (FACT-G), FACT-Ovarian (FACT-O), FACT-Endometrial (FACT-En), European Organization for Research and Treatment of Cancer Quality of Life Questionnaire Core 30 (EORTC QLQ-C30), Short Form-36 (SF-36), and condition-specific scales. All instruments were scored such that higher values indicated better quality of life.
Risk of bias assessment
Risk of bias was assessed using the Cochrane RoB 2.0 tool for the 13 RCTs and the Newcastle-Ottawa Scale for the 2 observational cohort studies. A summary of domain-level judgments is presented in the risk-of-bias traffic-light plot. For the RCTs, the most common methodological concerns were: (1) Domain 2 (Deviations from intended interventions): Blinding of participants and personnel to lifestyle interventions was not feasible in any study; 9 of 13 studies (69%) were rated as having "some concerns" or "high risk" in this domain; (2) Domain 3 (Missing outcome data): Four studies (31%) had incomplete outcome data due to attrition rates exceeding 20%, rated as "some concerns"; (3) - Domain 1 (Randomization process): Seven studies (54%) adequately described sequence generation and allocation concealment; the remainder had unclear or inadequate reporting; (4) Domain 4 (Measurement of the outcome): All studies used validated self-reported QoL instruments; however, blinding of outcome assessors was not consistently reported; (5) Domain 5 (Selection of the reported result): Six studies (46%) had protocols registered prospectively; the remaining studies lacked available protocols, raising concerns about selective outcome reporting.
Overall risk-of-bias judgments: No study was rated as low risk across all domains. Eight studies (62%) were judged to have "some concerns" overall, and five studies (38%) were rated as "high risk" overall, primarily due to a lack of blinding and small sample sizes, which led to imprecision.
For the two observational cohort studies (Budisan et al.33; Betea et al.34), the absence of a concurrent comparator group resulted in a high risk for confounding and selection bias for any causal inference. These studies were retained only for narrative synthesis and did not contribute to the pooled effect estimates.
Primary outcomes
Quality of life at 6 months – general gynecologic oncology
Nine comparative RCTs contributed data at the 6-month time point, comprising 693 participants (358 intervention and 335 control). The pooled mean difference (MD) using a random-effects model showed no statistically significant improvement in quality of life at 6 months compared with the control group (MD = 2.11; 95% CI: –0.90 to 5.12; p = 0.17).
Figure 2 presents the forest plot for this analysis. Heterogeneity was substantial: I2 = 71%, τ2 = 10.60.
Quality of life at 6 months – ovarian cancer subgroup
Two studies (Zhou et al.25; Maurer et al.29) provided data specifically for ovarian cancer, contributing 124 participants (66 intervention, 58 control). The pooled MD indicated a statistically significant improvement in quality of life favoring the intervention group (MD 4.28; 95% CI 0.45–8.10; p = 0.03). Figure 3 presents the forest plot for this analysis. Heterogeneity was low: I2 = 0%, τ2 = 0.
Quality of life at 6 months – endometrial cancer subgroup
Four studies (Von Gruenigen et al.21; McCarroll et al.23; Rossi et al.24; Jeppesen et al.26) contributed data for endometrial cancer, comprising 172 participants (92 intervention, 80 control). To assess the impact of the overlapping SUCCEED trial cohorts, the endometrial subgroup analysis was repeated, excluding McCarroll et al.23. The pooled MD changed marginally from 2.00 (95% CI: –1.49–5.49) to 1.87 (95% CI: –1.62–5.36), and I2 remained 0%. Excluding McCarroll et al. did not materially alter the pooled estimate; the effect remained statistically non-significant, and heterogeneity remained absent (I2 = 0%). Figure 4 presents the forest plot for this analysis. Heterogeneity was low: I2 = 0%, τ2 = 0.
Quality of life at 3 months – general gynecologic oncology
Six comparative studies (Von Gruenigen et al.21; Donnelly et al.22; McCarroll et al.23; Maurer et al.29; Elzeblawy Hassan et al.32; McCloy et al.30) reported 3-month outcomes, contributing 275 participants (140 intervention and 135 control). The pooled MD showed no statistically significant difference between intervention and control groups (MD 6.43, 95% CI: −0.16 to 13.01, p = 0.06). Figure 5 presents the forest plot for this analysis. Heterogeneity was substantial (I2 = 74%, τ2 = 42.53).
Subgroup analyses
Prespecified subgroup analyses by cancer type were performed to explore sources of heterogeneity. For the 6-month general Gynecologic Oncology outcome: (1) Ovarian cancer subgroup (2 studies): I2 = 0%, τ2 = 0; MD 4.28 (95% CI 0.45–8.10); (2) Endometrial cancer subgroup (4 studies): I2 = 0%, τ2 = 0; MD 2.00 (95% CI: –1.49–5.49)
Subgrouping by cancer type substantially reduced heterogeneity from I2 = 71% in the overall analysis to 0% within each subgroup. However, the small number of studies within each subgroup (2 and 4, respectively) limits the precision of these subgroup estimates.
Formal interaction testing between subgroups was not performed because the number of studies per subgroup (<10) was insufficient to yield reliable interaction estimates. The apparent differences in statistical significance between ovarian and endometrial subgroups should not be interpreted as evidence of differential treatment effects by cancer type.
Similarly, no formal time-by-interaction test was performed between the 3-month and 6-month results.
Sensitivity analyses
Exclusion of overlapping cohorts
To assess the impact of the overlapping SUCCEED trial cohorts (Von Gruenigen et al.21 and McCarroll et al.23), the endometrial subgroup analysis was repeated, excluding McCarroll et al.23.
The pooled MD changed marginally from 2.00 (95% CI: –1.49–5.49) to 1.87 (95% CI: –1.62–5.36), and I2 remained 0%. This indicates that the duplicate cohort did not materially affect the point estimate or the conclusion that there is no significant effect.
For the general 6-month outcome, excluding McCarroll et al. changed the pooled MD from 2.11 (95% CI: −0.90–5.12) to 2.33 (95% CI: −1.16–5.82), with I2 changing from 71% to approximately 72%. The effect remained statistically non-significant, indicating that exclusion of the overlapping cohort did not materially alter the overall conclusion.
Leave-one-out influence analysis
Sequential removal of individual studies yielded pooled MDs ranging from approximately 1.29 to 4.33. Heterogeneity generally remained substantial after the exclusion of most studies; however, excluding McCorkle et al.20 reduced I2 to 0%, indicating that this study contributed substantially to the observed between-study heterogeneity. The overall findings should therefore be interpreted cautiously.
Fixed-effect model comparison
Under a fixed-effect model, the pooled MD for the general 6-month outcome was 3.80 (95% CI: 2.97–4.62), whereas the random-effects model yielded an MD of 2.11 (95% CI: −0.90–5.12). The difference in statistical significance between the two models indicates that between-study heterogeneity materially affects the pooled inference. Given the substantial heterogeneity (I2 = 71%), the random-effects estimate was considered more appropriate for interpretation.
Publication bias
None of the pooled outcomes included 10 or more studies. Therefore, funnel plots and Egger's regression tests were not performed because these assessments would be underpowered and potentially misleading given the number of studies available.
Although a formal assessment was not performed because of the small number of studies, publication bias and selective reporting cannot be excluded. The possibility that negative or null findings remain unpublished should therefore be considered when interpreting the evidence.
Data Availability
The dataset analyzed during the current study is available from 10.5281/zenodo.21777130 (https://doi.org/10.5281/zenodo.21777130).
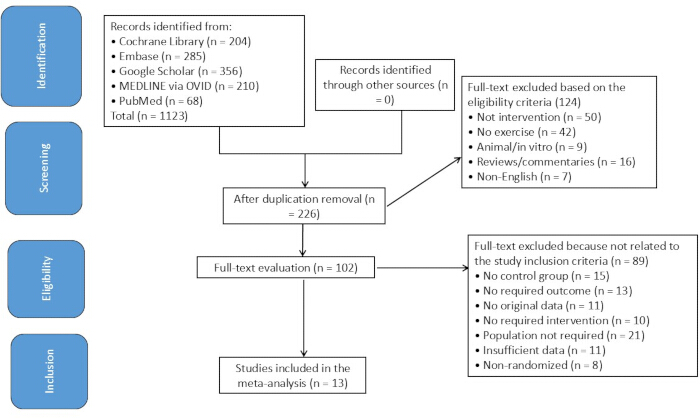
Figure 1: PRISMA 2020 flow diagram of study selection. Flow diagram illustrating the identification, screening, eligibility assessment, and inclusion of studies evaluating lifestyle and gynecologic oncology nursing interventions on quality of life in women with gynecologic cancers. Please click here to view a larger version of this figure.
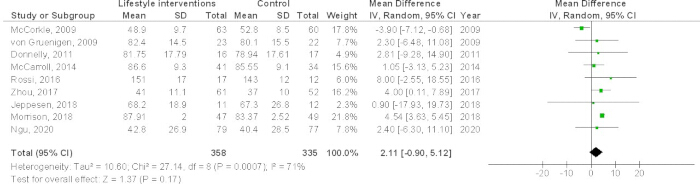
Figure 2: Forest plot of quality of life at 6 months in women with gynecologic cancers. Forest plot comparing lifestyle and Gynecologic Oncology nursing interventions with control groups for quality of life at the 6-month follow-up. Results are presented as mean differences (MDs) with 95% confidence intervals (CIs) using a random-effects model. Positive MD values favor the intervention group. Heterogeneity is reported using the I2 statistic. Please click here to view a larger version of this figure.
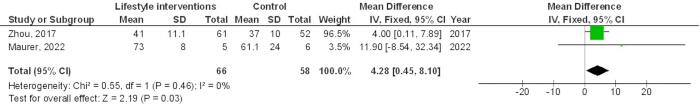
Figure 3: Forest plot of quality of life at 6 months in women with ovarian cancer. Forest plot showing the effect of lifestyle and Gynecologic Oncology nursing interventions on quality of life at the 6-month follow-up among women with ovarian cancer. Results are presented as mean differences (MDs) with 95% confidence intervals (CIs). Positive MD values favor the intervention group, and heterogeneity is summarized using the I2 statistic. Please click here to view a larger version of this figure.
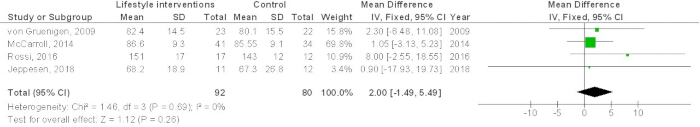
Figure 4: Forest plot of quality of life at 6 months in women with endometrial cancer. Forest plot comparing lifestyle and Gynecologic Oncology nursing interventions with control groups for quality of life at the 6-month follow-up among women with endometrial cancer. Results are expressed as mean differences (MDs) with 95% confidence intervals (CIs). Positive MD values favor the intervention group, and heterogeneity is reported using the I2 statistic. Please click here to view a larger version of this figure.
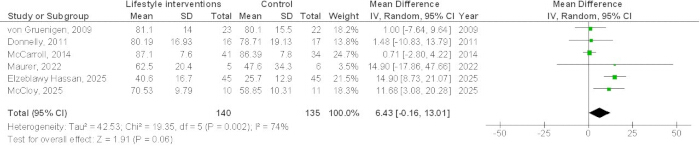
Figure 5: Forest plot of quality of life at 3 months in women with gynecologic cancers. Please click here to view a larger version of this figure.
Forest plot comparing lifestyle and Gynecologic Oncology nursing interventions with control groups for quality of life at the 3-month follow-up. Results are presented as mean differences (MDs) with 95% confidence intervals (CIs) using a random-effects model. Positive MD values favor the intervention group. Heterogeneity is reported using the I2 statistic.
Table 1: Database search strategies used for the literature search. Comprehensive search strategies were used to identify eligible studies in PubMed, Embase, Cochrane Library, Ovid, and Google Scholar. The search terms combined controlled vocabulary and free-text keywords related to gynecologic cancers, lifestyle interventions, oncology nursing, and quality of life. Please click here to download this Table.
Table 2: Characteristics of included RCTs. Summary of the characteristics of the included studies, including study design, cancer type, intervention and comparator, sample size, quality-of-life assessment instrument, follow-up duration, and eligibility for inclusion in the quantitative meta-analysis. Studies without a suitable comparator group were included only in the qualitative synthesis. Please click here to download this Table.
Supplementary File 1: PRISMA 2020 Checklist. Completed PRISMA 2020 checklist indicating the manuscript page numbers corresponding to each reporting item, in accordance with the PRISMA 2020 Statement for reporting systematic reviews and meta-analyses.Please click here to download this file.
Discussion
The primary 6-month analysis showed no statistically significant improvement in QoL for mixed gynecologic cancers (MD 2.11, 95% CI: −0.90 to 5.12, p = 0.17), whereas a significant improvement was observed in the ovarian cancer subgroup (MD 4.28, 95% CI: 0.45–8.10, p = 0.03). No significant effect was observed for endometrial cancer at 6 months (MD 2.00, 95% CI: −1.49 to 5.49, p = 0.26) or for mixed cancers at 3 months (MD 6.43, 95% CI: −0.16 to 13.01, p = 0.06).
These findings do not demonstrate a significant overall QoL benefit at 6 months, although a significant improvement was observed in the ovarian cancer subgroup. The primary 6-month analysis exhibited substantial heterogeneity (I2 = 71%), and the GRADE certainty of evidence for all pooled outcomes was rated as very low. Consequently, these results should be considered hypothesis-generating rather than practice-changing.
Crucially, the apparent differences in significance between cancer types and time points were not formally tested for interaction and should not be interpreted as evidence of differential effectiveness. The observed patterns may reflect differences in study populations, intervention components, sample sizes, or chance, rather than true biological or temporal differences. Any conclusions about timing or tumor-specific effects are speculative and require confirmation in future head-to-head trials.
Comparison with previous studies
The present findings partly align with the earlier systematic review by Smits et al.10 which evaluated lifestyle interventions in women with endometrial and ovarian cancer and found limited evidence for significant QoL improvements. However, the broader inclusion of nursing interventions and additional studies published since 2015 provides a more current, though still uncertain, picture. The very low GRADE certainty in this review is substantially more cautious than the conclusions of some primary studies, reflecting the stricter methodological appraisal applied in the present review and explicit acknowledgment of the limitations inherent in the evidence base11.
The observed benefit in the ovarian cancer subgroup is consistent with previous research by Zhou et al.25 and Maurer et al.29, who reported that structured exercise interventions improved physical functioning and overall well-being in ovarian cancer survivors. This may be explained by the significant physical deconditioning, chemotherapy-induced neuropathy, and abdominal complications that affect mobility in this population, making exercise interventions particularly beneficial. However, the small number of studies (n = 2) precludes robust conclusions.
In contrast, the null finding for endometrial cancer at 6 months contradicts some earlier positive reports from individual trials (e.g., Von Gruenigen et al.21; Rossi et al.24). The pooling of these studies, including overlapping cohorts from the SUCCEED trial, revealed no significant effect, suggesting that earlier positive findings may have been overestimated due to small sample sizes or publication bias. The absence of a significant effect may also reflect the heterogeneous nature of endometrial cancer survivors, who often present with obesity and metabolic syndrome, requiring more intensive or tailored interventions to achieve measurable QoL improvements.
The present findings also resonate with Mokhtari-Hessari and Montazeri35, who reported substantial QoL enhancements from nursing interventions in breast cancer patients. Similarly, Aktas and Terzioglu36 found that home-based nursing care markedly improved QoL in women receiving treatment for gynecologic oncology, and Ma et al.37 demonstrated that intensive psychological nursing care alleviated negative moods and improved QoL in cervical cancer patients. These consistent signals across different cancer types and settings underscore the potential value of comprehensive nursing care, although the methodological quality of the supporting evidence remains a concern.
Plausible mechanisms
Although the pooled estimates cannot establish causality, several pathways may explain the observed QoL signals. Structured exercise and dietary modification reduce pro‑inflammatory cytokines (e.g., IL‑6, TNF‑α) and C‑reactive protein, which are linked to cancer‑related fatigue, pain, and depression. In endometrial and breast cancer survivors, weight loss and exercise also lower estrogen and IGF‑1 levels, potentially influencing tumor metabolism and systemic energy balance. Psychosocially, nurse‑led psychoeducation, counseling, and regular follow‑up may enhance self‑efficacy, reduce fear of recurrence, and improve treatment adherence. The more consistent 6‑month (versus 3‑month) effects (though not formally tested) may reflect the time needed for behavioral changes to become habitual and for biological adaptations to accumulate. However, none of these mechanisms were directly measured in the included studies; this discussion is speculative and intended to guide future mechanistic research.
Methodological limitations
Lack of prospective protocol registration: A primary limitation is the absence of registration with a prospective registry (e.g., PROSPERO, INPLASY, or OSF Registries). Without a publicly accessible preregistered protocol, there is a potential for reporting or selective outcome bias, as the study selection, data extraction, and analysis decisions cannot be independently verified against a pre-specified plan. Readers should interpret the pooled estimates with this in mind.
High heterogeneity: The primary 6-month analysis exhibited I2 = 71%, which, under Cochrane guidance, is considered "considerable" and often a criterion for not pooling. Although subgrouping by cancer type reduced I2 to 0% for both ovarian and endometrial subgroups, each subgroup contained only a few studies (2 and 4, respectively), rendering these estimates imprecise. The heterogeneity cannot be confidently attributed solely to cancer type. Other plausible sources—differences in intervention intensity, duration, delivery mode, control conditions, baseline participant characteristics, and outcome measurement—were not formally investigated due to insufficient covariate data. Given these considerations, the pooled MD for the primary analysis should be treated as a mathematically generated summary rather than a clinically meaningful estimate.
Risk of bias: No RCT was rated as low risk across all domains of the Cochrane RoB 2.0. The majority were rated as having "some concerns" or "high risk," primarily due to lack of participant blinding (unavoidable for lifestyle interventions) and incomplete outcome data. The inclusion of overlapping cohorts from the SUCCEED trial artificially inflates the weight of that specific intervention in the endometrial subgroup; sensitivity analysis excluding the duplicate did not materially change the point estimate, but it remains a structural limitation.
Inclusion of observational studies: Two of the 15 included reports lacked a comparator group entirely (Budisan et al.33; Betea et al.34). While these studies were retained for narrative synthesis to avoid selection bias, they could not be included in the pooled intervention effects and were judged to be at high risk of confounding and selection bias.
Intervention and outcome diversity: The comparative studies encompassed a wide range of interventions—structured exercise programs, dietary modification, weight-loss counseling, psychoeducational sessions, nurse-led follow-up, patient-initiated care, and app-based mindfulness. Pooling such diverse interventions under the umbrella term "lifestyle/nursing intervention" provides an estimate of the average effect, but this average may not apply to any specific intervention type. Similarly, although all studies measured health-related QoL, they used different instruments (FACT-G, FACT-O, FACT-En, EORTC QLQ-C30, SF-36), which may introduce indirect heterogeneity.
Publication bias could not be reliably assessed because none of the pooled outcomes included 10 or more studies. Funnel plots and Egger's regression tests were therefore not performed. The small sample sizes and predominance of positive studies in the literature raise the possibility that negative or null findings remain unpublished.
Short follow-up and lack of subgroup analyses: Most studies included brief follow-up periods (3–6 months), constraining understanding of the long-term sustainability of QoL enhancements. The absence of comprehensive subgroup analyses (e.g., by age, disease stage, socioeconomic status) hindered the identification of specific patient categories that may derive the greatest benefit.
GRADE certainty
The formal GRADE assessment rated the overall certainty of the evidence for all four pooled outcomes as VERY LOW. This judgment reflects: (i) serious to very serious risk of bias across the included RCTs; (ii) very serious inconsistency for the primary 6-month outcome (I2 = 71%); (iii) indirectness for the endometrial subgroup, which predominantly enrolled overweight/obese survivors, limiting generalizability; and (iv) serious to very serious imprecision due to small total sample sizes per subgroup and wide confidence intervals that often cross the null. Consequently, confidence in the effect estimates is very limited; the true effects are likely to be substantially different from the reported point estimates.
Clinical implications
Given the very low certainty of evidence and substantial heterogeneity, these findings are hypothesis‑generating rather than practice‑changing. Clinicians should not alter routine supportive care based on these pooled estimates. However, a few cautious observations may inform patient discussions: (i) supportive care decisions should be individualized to patient preferences and clinical context; (ii) the ovarian cancer subgroup showed the only statistically coherent signal (MD 4.28, 95% CI: 0.45–8.10), suggesting this population may particularly benefit from exercise interventions, though this is based on only two small studies. The consistent positive signals across studies underscore the importance of comprehensive nursing care, including pain management, emotional support, patient education, and care coordination, as a core component of multidisciplinary cancer care. Crucially, the apparent differences between cancer types and time points were not formally tested for interaction and should not be overinterpreted.
Future research
This review exposes critical evidence gaps that future research must address. High‑quality, multicenter RCTs are urgently needed, with standardized and manualized interventions, published protocols, intention‑to‑treat analyses, longer follow‑up (≥12 months), and prespecified subgroup analyses with formal interaction testing. Mechanistic studies should incorporate biomarker assessments (inflammatory cytokines, hormonal profiles) and validated psychosocial mediators (self‑efficacy, social support) to identify which intervention components are most efficacious and which patient subgroups benefit most. Economic evaluations are also needed to assess cost‑effectiveness and inform resource allocation. Future systematic reviews with a larger evidence base should consider whether meta‑analysis remains appropriate for such diverse interventions, or whether narrative synthesis would be more informative. Finally, patient‑centered outcomes—including domain‑specific QoL measures and patient‑reported experience measures—should be prioritized, with patient and public involvement in study design to ensure research addresses what matters most to women with gynecologic malignancies.
This meta-analysis found no statistically significant improvement in overall QoL at 3 or 6 months among women with gynecologic cancers. A significant improvement was observed in the ovarian cancer subgroup at 6 months, whereas no significant effect was observed in the endometrial cancer subgroup. However, substantial heterogeneity, methodological limitations, small subgroup sizes, and very low-certainty evidence warrant cautious interpretation. Larger, well-designed trials with standardized interventions and longer follow-up are needed to clarify the effects of lifestyle and nursing interventions on QoL in women with gynecologic malignancies.
Disclosures
The authors have no conflicts of interest to disclose.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| EndNote | Clarivate Analytics | https://endnote.com | Reference management, deduplication, citation formatting |
| GRADEpro GDT | McMaster University and Evidence Prime | McMaster University / Evidence Prime; https://gradepro.org | GRADE certainty assessment (Online version) |
| PRISMA 2020 Checklist | PRISMA Statement | PRISMA Statement; https://www.prisma-statement.org | Reporting compliance |
| R | R Foundation for Statistical Computing | R Foundation; https://cran.r-project.org | Statistical analysis, sensitivity analyses, influence analyses, figures (Version 4.3.1 or higher) |
| R package: meta | CRAN | CRAN; https://cran.r-project.org/package=meta | Meta-analysis functions (pooling, heterogeneity, forest plots, funnel plots) version 6.0.0 or higher |
| R package: metafor | CRAN | CRAN; https://cran.r-project.org/package=metafor | REML estimation, influence diagnostics, additional meta-analytic functions (4.0.0 or higher) |
| Review Manager | RevMan | Cochrane Collaboration; https://training.cochrane.org/online-learning/core-software-cochrane-reviews/revman[reference:14] | Meta-analysis (pooling, forest plots, heterogeneity, risk-of-bias assessment) Version 5.4 |
References
- Ackroyd SA, Shih YCT, Kim B, Lee NK, Halpern MT. A look at the gynecologic oncologist workforce – are we meeting patient demand Gynecol Oncol. 2021;163(2):229-36.
- Williams N, et al. The supportive care needs of women experiencing gynaecological cancer: a Western Australian cross-sectional study. BMC Cancer. 2018;18(1):912.
- Bizzarri N, et al. Building a personalized medicine infrastructure for gynecological oncology patients in a high-volume hospital. J Pers Med. 2022;12(1):3.
- Buckley L, Robertson S, Wilson T, Sharpless J, Bolton S. The role of the specialist nurse in gynaecological cancer. Curr Oncol Rep. 2018;20(10):83.
- Parkinson N, Pratt H. Clinical nurse specialists and the psychosexual needs of patients with gynaecological cancer. Br Menopause Soc J. 2005;11(1):33-5.
- Kobleder A, Mayer H, Gehrig L, Senn B. “Promoting continuity of care”—specialist nurses’ role experiences in gynaecological oncology: a qualitative study. J Clin Nurs. 2017;26(23-24):4890-8.
- Cook O, McIntyre M, Recoche K, Lee S. “Our nurse is the glue for our team”—multidisciplinary team members' experiences and perceptions of the gynaecological oncology specialist nurse role. Eur J Oncol Nurs. 2019;41:7-15.
- Lavdaniti M, et al. Factors influencing quality of life in breast cancer patients six months after the completion of chemotherapy. Diseases. 2019;7(1):26.
- Perry S, Kowalski TL, Chang CH. Quality of life assessment in women with breast cancer: benefits, acceptability and utilization. Health Qual Life Outcomes. 2007;5(1):24.
- Chhikara BS, Parang K. Global cancer statistics 2022: the trends projection analysis. Chem Biol Lett. 2023;10(1):451.
- Smits A, et al. The effect of lifestyle interventions on the quality of life of gynaecological cancer survivors: a systematic review and meta-analysis. Gynecol Oncol. 2015;139(3):546-52.
- Stroup DF, et al. Meta-analysis of observational studies in epidemiology: a proposal for reporting. JAMA. 2000;283(15):2008-12.
- Page MJ, et al. The PRISMA 2020 statement: an updated guideline for reporting systematic reviews. BMJ. 2021;372:n71.
- Liberati A, et al. The PRISMA statement for reporting systematic reviews and meta-analyses of studies that evaluate health care interventions: explanation and elaboration. J Clin Epidemiol. 2009;62(10):e1-34.
- Gupta S, et al. Efficacy of generic oral directly acting agents in patients with hepatitis C virus infection. J Viral Hepat. 2018;25(7):771-8.
- Adeiza SS, Aminul I. Meta-meta-analysis of the mortality risk associated with MRSA compared to MSSA bacteraemia. Infez Med. 2024;32(2):131-7.
- Higgins J, et al., editors. Cochrane handbook for systematic reviews of interventions. 2nd ed. Wiley & Sons; Chichester, UK; 2019.
- Sheikhbahaei S, et al. FDG-PET/CT and MRI for evaluation of pathologic response to neoadjuvant chemotherapy in patients with breast cancer: a meta-analysis of diagnostic accuracy studies. Oncologist. 2016;21(8):931-9.
- Higgins JP, Thompson SG, Deeks JJ, Altman DG. Measuring inconsistency in meta-analyses. BMJ. 2003;327(7414):557-60.
- McCorkle R, et al. Effects of a nursing intervention on quality of life outcomes in post-surgical women with gynecological cancers. Psychooncology. 2009;18(1):62-70.
- Von Gruenigen VE, et al. A randomized trial of a lifestyle intervention in obese endometrial cancer survivors: quality of life outcomes and mediators of behavior change. Health Qual Life Outcomes. 2009;7(1):17.
- Donnelly CM, et al. A randomised controlled trial testing the feasibility and efficacy of a physical activity behavioural change intervention in managing fatigue with gynaecological cancer survivors. Gynecol Oncol. 2011;122(3):618-24.
- McCarroll ML, et al. Self-efficacy, quality of life, and weight loss in overweight/obese endometrial cancer survivors (SUCCEED): a randomized controlled trial. Gynecol Oncol. 2014;132(2):397-402.
- Rossi A, et al. Feasibility of a physical activity intervention for obese, socioculturally diverse endometrial cancer survivors. Gynecol Oncol. 2016;142(2):304-10.
- Zhou Y, et al. Randomized trial of exercise on quality of life in women with ovarian cancer: Women’s Activity and Lifestyle Study in Connecticut (WALC). J Natl Cancer Inst. 2017;109(12).
- Jeppesen M, Jensen P, Hansen D, Christensen R, Mogensen O. Patient-initiated follow up affects fear of recurrence and healthcare use: a randomised trial in early-stage endometrial cancer. BJOG. 2018;125(13):1705-14.
- Morrison V, et al. Trial of optimal personalised care after treatment—gynaecological cancer (TOPCAT-G): a randomized feasibility trial. Int J Gynecol Cancer. 2018;28(2):401-11.
- Ngu SF, et al. Nurse-led follow-up in survivorship care of gynaecological malignancies—a randomised controlled trial. Eur J Cancer Care (Engl). 2020;29(6):e13325.
- Maurer T, et al. Randomised controlled trial testing the feasibility of an exercise and nutrition intervention for patients with ovarian cancer during and after first-line chemotherapy (BENITA-study). BMJ Open. 2022;12(2):e054091.
- McCloy K, et al. Management of fatigue in gynaecological cancer: a feasibility study of an app-based exercise and mindfulness intervention. Gynecol Oncol Rep. 2025;60:101807.
- Darwish EAF, Tayel SEA, Meleis MEH, Abou Elwafa HE, Shaaban Marouf FSA. A randomized controlled trial of the effect of a psychoeducational intervention program on quality of life of patients with gynecological cancers. Alex J Med. 2025;61(1):6-14.
- Elzeblawy Hassan H, Khalaf Gooda W, Ragabahmed T, Shehta Said Farag D. Marital, sexual satisfaction and quality of life among post-hysterectomy women: impact of nursing counseling guided by BETTER model. Egypt J Health Care. 2025;16(1):99-116.
- Budisan C, et al. Physical, emotional, and stress-related dynamics over six months in newly diagnosed epithelial ovarian cancer survivors. J Clin Med. 2025;14(14):5087.
- Betea R, et al. Quality-of-life trajectories and perceived stress in women treated for uterine cancer: a six-month prospective study. Healthcare (Basel). 2025;13(15):1787.
- Mokhtari-Hessari P, Montazeri A. Health-related quality of life in breast cancer patients: review of reviews from 2008 to 2018. Health Qual Life Outcomes. 2020;18(1):338.
- Aktas D, Terzioglu F. Effect of home care service on the quality of life in patients with gynecological cancer. Asian Pac J Cancer Prev. 2015;16(9):4089-94.
- Ma Y, Kamalibaike M, Xin C, Li L. Effect of the intensive psychological nursing on adverse mood and quality of life in patients with cervical cancer. Am J Transl Res. 2021;13(8):9633-8.