This randomized controlled study evaluates whether the topical Huzhang Sanhuang formula added to standard nursing care improves symptom resolution, inflammation, and safety outcomes in patients with chemotherapy-induced phlebitis.
Method Article
Effectiveness of Topical Huzhang Sanhuang with Standard Nursing for Chemotherapy-Induced Phlebitis: Randomized Controlled Study
23 views
⸱
September 11th, 2026
In This Article
Summary
Abstract
Chemotherapy-induced phlebitis (CIP) is a common complication of peripheral intravenous chemotherapy that can cause pain, local inflammation, treatment interruption, and diminished quality of life. This randomized controlled trial evaluated the efficacy and safety of the topical Huzhang Sanhuang (HZSH) formula, combined with standard nursing care, in managing CIP. Ninety-four hospitalized patients with CIP (grade I or higher) were randomly assigned in a 1:1 ratio to receive either topical HZSH formula plus standard nursing care (experimental group, n = 47) or 50% magnesium sulfate wet dressing plus standard nursing care (control group, n = 47) for 14 days. Prespecified outcomes included phlebitis grade, visual analog scale (VAS) pain score, high-sensitivity C-reactive protein (hs-CRP), interleukin-6 (IL-6), symptom resolution time, and safety indicators. By Day 14, patients in the experimental group demonstrated significantly greater improvement in phlebitis severity than those in the control group (risk ratio for grade ≥ II, 0.42; 95% confidence interval, 0.20–0.87; P = 0.012). The experimental group also showed significantly larger reductions in VAS pain scores, hs-CRP levels, and IL-6 concentrations (all P < 0.01). Kaplan–Meier analysis further demonstrated faster resolution of multiple local symptoms in the experimental group. Treatment adherence was high in both groups, and no serious adverse events or major safety concerns were observed. These findings indicate that the topical HZSH formula, combined with standard nursing care, is a safe and effective integrative nursing intervention that accelerates clinical recovery, alleviates local symptoms, and reduces the inflammatory burden in patients with chemotherapy-induced phlebitis.
Introduction
Chemotherapy-induced phlebitis (CIP) is one of the most common complications in patients with malignancies receiving peripheral intravenous chemotherapy1. Although central venous catheters and implantable ports are increasingly used in oncology care, peripheral venous access remains common in short-course chemotherapy and primary healthcare settings because of cost constraints, procedural convenience, and patient-specific vascular conditions. In this setting, cytotoxic agents such as vincristine, oxaliplatin, and docetaxel may cause substantial endothelial injury due to high osmolarity, pH imbalance, and direct vascular toxicity, thereby triggering local inflammatory responses2,3. Clinically, CIP may present with pain, erythema, swelling, and induration; in severe cases, it may progress to local tissue necrosis. These complications may interrupt treatment schedules, delay antitumor therapy, and increase patient distress related to repeated puncture and vascular injury, ultimately reducing quality of life4.
Current nursing management of CIP mainly follows intravenous infusion therapy standards and routine supportive care, including limb elevation, local cold or warm compresses, and standardized management of peripheral indwelling needles5. Common topical interventions include magnesium sulfate wet dressings, mucopolysaccharide polysulfate ointment, and hydrocolloid dressings6,7. However, these approaches have practical limitations. Magnesium sulfate dressings may reduce edema through osmotic effects, but they often require frequent replacement and may cause skin dryness or pruritus. Conventional topical agents may improve local circulation to some extent, but their effects are often limited in patients with marked burning pain, persistent induration, or more severe inflammatory reactions. Available evidence also suggests that single-modality nursing measures or topical chemical agents may be insufficient to fully support endothelial recovery and reduce downstream vascular complications, including thrombotic risk8,9. Therefore, a practical, clinically applicable integrated nursing strategy is needed to reduce inflammation, relieve pain, and support local vascular repair10.
In traditional Chinese medicine (TCM), chemotherapy-associated vascular injury is commonly understood as a condition involving heat-toxin accumulation and blood stasis, with local vessel damage and impaired circulation, as key pathological features11,12. The Huzhang Sanhuang formula includes herbs such as Polygonum cuspidatum, Rheum palmatum, Phellodendron amurense, and Scutellaria baicalensis, and is traditionally used for heat-clearing, detoxification, blood-activating, stasis-dispersing, swelling reduction, and pain relief. Modern pharmacological studies provide a plausible biological basis for these effects. Active constituents in Polygonum cuspidatum (including resveratrol-related compounds) have been reported to suppress inflammatory signaling and reduce oxidative stress-associated endothelial injury, while Rheum palmatum may support local microcirculation and tissue repair13. In addition, compounds from Phellodendron amurense and Scutellaria baicalensis, such as berberine and baicalin, have been documented to have anti-inflammatory and antimicrobial effects. When used topically, this herbal compound formulation may help establish a localized anti-inflammatory microenvironment at the lesion site while avoiding systemic adverse effects associated with certain oral or injectable medications14.
Against this background, the present randomized controlled study was designed to evaluate the clinical effectiveness and safety of the topical Huzhang Sanhuang formula combined with standard nursing care in hospitalized patients with CIP15. Patients were randomly assigned to a control group receiving standard nursing care plus routine topical treatment, or to an experimental group receiving the Huzhang Sanhuang topical formula in addition to the same standard nursing care. The primary expectation was that the combined intervention would reduce the severity of phlebitis and accelerate the resolution of pain, redness, and swelling. By using a controlled design and prespecified outcome measures, this study aims to provide stronger evidence for an integrated nursing approach to CIP and to support the standardized application of TCM-based topical care in modern oncology supportive nursing practice.
Protocol
Approval was obtained from the Ethics Committee of the Second Affiliated Hospital of Nanjing University of Chinese Medicine (Jiangsu Provincial Second Traditional Chinese Medicine Hospital) before initiating participant recruitment (Approval no. 2025SEZKY-033-02). All study procedures were conducted in accordance with the Declaration of Helsinki. The study purpose, procedures, potential benefits, and possible risks were explained to each eligible participant, and written informed consent was obtained before enrollment.
1. Protect participant confidentiality
- Assign study identification codes
- Assign a unique study identification code to each participant immediately after enrollment. Use the assigned code throughout the study.
- Enter the study identification code on all case report forms, intervention records, laboratory records, and study databases. Do not record participant names in the analysis dataset.
- Secure personally identifiable information
- Store participant names, contact information, hospital identification numbers, and consent forms separately from coded research data. Link identifiable information to the study identification code only through a secure participant-code list.
- Limit access to personally identifiable information to authorized research personnel. Store paper records in locked cabinets and protect electronic records with passwords and access controls.
- Do not disclose participant-identifying information in study reports, statistical outputs, presentations, or publications. Use coded or aggregated data when reporting study findings.
- Document study events prospectively
- Document each protocol deviation when it occurs. Record the date, nature, reason, corrective action, and effect on study participation.
- Document each participant's withdrawal prospectively in the case report form and study log. Record the withdrawal date and reason without altering previously collected data.
- Record all adverse events in the case report forms and nursing records. Document the onset, severity, duration, management, outcome, and assessed relationship to the study intervention.
2. Study design and participant enrollment
- Study design
- Conduct a prospective, randomized, controlled, single-center clinical trial at the Second Affiliated Hospital of Nanjing University of Chinese Medicine from January 2025 to December 2025. Compare topical Huzhang Sanhuang formula plus standard nursing care with 50% magnesium sulfate wet dressing plus the same standard nursing care.
- Initiate the assigned intervention immediately after confirming chemotherapy-induced phlebitis (CIP) and completing baseline assessment. Continue treatment for 14 consecutive days and perform outcome assessments on Day 0, Day 7, and Day 14.
- Identify hospitalized patients who develop CIP after peripheral intravenous chemotherapy during routine chemotherapy infusion rounds and intravenous therapy rounds. Evaluate each patient for study eligibility.
- Explain the study objectives, procedures, risks, and benefits to each eligible participant. Obtain written informed consent before enrollment.
- Collect demographic information, tumor treatment status, phlebitis grade, visual analog scale (VAS) pain score, and inflammatory biomarker measurements before randomization.
- Participant screening
- Calculate the sample size using the primary endpoint, defined as the proportion of participants with persistent grade II or higher phlebitis at Day 14. Assume an event rate of 45% in the control group and 15% in the experimental group with a two-sided α of 0.05 and 80% statistical power.
- Require at least 36 participants per treatment group based on the sample size calculation. Increase the target sample size by approximately 20% to compensate for anticipated withdrawals or protocol deviations and enroll 94 participants (47 per group).
- Include adults aged 18 years or older who develop grade I or higher phlebitis at the peripheral intravenous catheter insertion site during chemotherapy. Confirm that each participant is conscious, capable of reporting symptoms, and able to complete scheduled follow-up assessments.
- Obtain written informed consent from each eligible participant before enrollment. Assign each participant a unique study identification number.
- Exclude patients with a known allergy to either topical preparation, severe contact dermatitis, skin ulceration or infection at the treatment site, severe eczema, or extensive local skin damage. Exclude patients with severe systemic infection, unstable organ failure, cognitive impairment, communication difficulties, or concurrent topical treatments that could influence study outcomes.
- Withdraw participants who revoke consent, miss more than 20% of scheduled topical applications, or receive prohibited topical medications during the study. Withdraw participants who develop severe local skin reactions requiring discontinuation or who cannot complete follow-up because of transfer or hospital discharge.
- Record the reason, date, and timing of each withdrawal in the study records. Document all protocol deviations and adverse events before study completion.
3. Randomization, allocation concealment, and blinding
- Randomization and allocation concealment
- Ask an independent researcher who is not involved in participant recruitment, intervention delivery, or outcome assessment to generate a computer-based random allocation sequence before participant enrollment. Allocate participants to the experimental or control group in a 1:1 ratio.
- Place each treatment assignment in a sequentially numbered, opaque, sealed envelope. Seal each envelope securely before participant enrollment begins.
- Ask trained research nurses to screen potential participants according to the eligibility criteria. Confirm eligibility and obtain written informed consent before enrollment.
- Collect all baseline demographic and clinical data before revealing the treatment allocation. Verify that all required baseline assessments have been completed.
- Ask the study coordinator to open the next sequentially numbered envelope only after participant enrollment and completion of the baseline assessment. Record the envelope number and treatment assignment in the study records.
- Communicate the assigned treatment to the intervention nurse immediately after opening the allocation envelope. Begin the assigned intervention according to the study schedule.
- Record the allocation date, envelope sequence number, assigned treatment group, and responsible study personnel in the study documentation.
- Blinding and bias control
- Assign different study personnel to deliver the topical interventions and perform outcome assessments. Prevent outcome assessors from participating in treatment administration.
- Use identical assessment forms and standardized evaluation procedures for all scheduled study visits. Apply the same assessment criteria to both treatment groups.
- Keep outcome assessors unaware of participant treatment allocation whenever feasible. Avoid discussing treatment assignments during outcome assessments.
- Replace treatment groups with coded identifiers before statistical analysis. Keep the treatment code concealed until completion of the primary statistical analyses.
- Perform all efficacy and safety assessments according to the predefined protocol. Record all observations immediately after each assessment without reference to previous results.
NOTE: Do not blind participants because the Huzhang Sanhuang formula and 50% magnesium sulfate dressing differ in appearance, texture, and odor. Limit blinding to outcome assessment and statistical analysis whenever feasible.
4. Topical intervention procedures
- Overall intervention framework
- Provide all participants with the same standard nursing care throughout the study. Vary only the assigned topical treatment between the two groups.
- Begin the assigned topical treatment immediately after confirming grade I or higher chemotherapy-induced phlebitis and completing the baseline assessment. Continue treatment for 14 consecutive days.
- Administer the assigned topical treatment twice daily, once in the morning and once in the evening, at approximately fixed times each day. Where clinically feasible, maintain an interval of approximately 12 h between the two applications. Perform outcome assessments on Day 0, Day 7, and Day 14 before the morning application.
- Standardize treatment delivery across participants by using the same predefined procedures for skin preparation, treatment coverage, dressing retention, documentation, and safety monitoring. Maintain an application thickness of approximately 2 mm for the Huzhang Sanhuang paste, extend both topical treatments approximately 1 cm beyond the visible lesion margin, and leave each dressing in place for 4 h. Record the actual application and removal times after each treatment.
- Prepare the Huzhang Sanhuang formula
- Obtain 100 g each of Polygonum cuspidatum (Huzhang), Rheum palmatum (Dahuang), Phellodendron amurense (Huangbai), and Scutellaria baicalensis (Huangqin). Verify each herb according to the Chinese Pharmacopeia before preparation.
- Record the supplier, batch number, authentication result, and quality certificate for each herbal ingredient before use.
- Add 4,000 mL of purified water to the herbal mixture at a crude herb-to-water ratio of 1:10 (w/v). Soak the mixture for 30 min before extraction.
- Heat the soaked herbal mixture to gentle boiling (approximately 95–100 °C). Continue decoction for 30 min.
- Filter the decoction through an appropriate filter. Concentrate the filtrate at 70–80 °C until a homogeneous, semisolid paste suitable for topical application is obtained.
- Inspect the paste for uniform appearance and absence of visible contamination or phase separation. Confirm that the paste has a consistent semisolid consistency suitable for topical application.
- Transfer the paste into sterile sealed containers. Store the preparation at 2–8 °C and prepare a fresh batch every 48 h.
- Apply approximately 0.20 g/cm2 of herbal paste to achieve a layer approximately 2 mm thick. Extend the application approximately 1 cm beyond the visible lesion margin.
- Administer the Huzhang Sanhuang formula (Experimental group)
- Inspect the affected skin before each application. Assess erythema, swelling, pain, papules, blistering, exudation, and pruritus.
- Clean the treatment site gently with sterile normal saline. Dry the skin using sterile gauze before applying the herbal paste.
- Spread the Huzhang Sanhuang paste evenly over the inflamed area to a thickness of approximately 2 mm. Extend the application approximately 1 cm beyond the visible lesion margin.
NOTE: Do not apply pressure directly over the inflamed vein during application. Ensure complete coverage of the affected area. - Cover the treated area with sterile gauze. Secure the dressing using hypoallergenic tape without applying compression.
- Leave the topical preparation in place for 4 h. Remove the dressing at the end of the treatment period.
- Remove any remaining herbal paste with sterile normal saline. Dry the skin gently using sterile gauze.
- Repeat the application twice daily for 14 consecutive days. Administer treatments at approximately the same time each day.
- Record the application time, treatment completion, skin tolerance, and protocol deviations after each application. Report any clinically significant local reactions immediately.
- Administer the control treatment
- Inspect, clean, and dry the affected area using the same procedure applied to the experimental group.
- Soak sterile gauze thoroughly with 50% magnesium sulfate solution. Remove excess solution before application.
- Place the soaked gauze over the inflamed area. Extend the dressing approximately 1 cm beyond the lesion margin.
- Cover the wet dressing with dry sterile gauze. Secure the dressing using hypoallergenic tape without compression.
- Leave the dressing in place for 4 h. Remove the dressing at the end of the scheduled treatment period.
- Clean the skin gently with sterile normal saline after dressing removal. Dry the area with sterile gauze.
- Repeat the treatment twice daily for 14 consecutive days. Maintain the same treatment schedule used in the experimental group.
- Record treatment completion, dressing tolerance, local skin reactions, and protocol deviations after each application. Use identical documentation procedures for both treatment groups.
5. Standard nursing care
- Train the nursing staff
- Train all participating nurses before enrolling the first participant using the same written protocol and standardized demonstration. Review the phlebitis grading criteria, skin preparation, treatment coverage, dressing application and removal, 4-h retention requirement, safety monitoring, adverse-event reporting, and documentation procedures.
- Require each participating nurse to perform the study-related procedures under supervision before independently administering study treatment. Confirm procedural competency using the same predefined treatment checklist and correct any deviations before independent participant care is permitted.
- Provide standard nursing care
- Inspect the peripheral intravenous catheter insertion site during each nursing shift. Assess pain, erythema, swelling, induration, burning sensation, and catheter patency using the standardized phlebitis grading criteria16.
- Monitor participants for worsening phlebitis, suspected extravasation, local infection, or other infusion-related complications. Report clinically significant deterioration promptly to the responsible investigator or treating physician.
- Instruct participants to protect the affected limb and avoid pressure, scratching, or unnecessary manipulation of the inflamed area. Advise participants to report worsening pain, swelling, redness, blistering, exudation, or other new symptoms immediately.
- Record phlebitis grade, nursing interventions, participant tolerance, and clinically significant findings during each scheduled assessment. Apply identical nursing procedures to both treatment groups throughout the study.
6. Outcome assessment and measurements
- Assess all study outcomes at baseline (Day 0), Day 7, and Day 14. Complete each assessment before the morning topical application using standardized assessment forms.
- Assess phlebitis severity
- Evaluate phlebitis severity using the predefined Grade 0–IV classification. Assess pain, erythema, swelling, burning sensation, induration, and exudation before assigning the phlebitis grade17.
- Determine whether participants have persistent Grade II or higher phlebitis on Day 14. Record phlebitis grades at each scheduled assessment.
- Ask participants to rate pain using a 10-cm visual analog scale (VAS), where 0 indicates no pain, and 10 indicates the worst imaginable pain. Record the VAS score at each scheduled assessment.
- Measure inflammatory biomarkers
- Collect fasting venous blood samples between 06:00 and 08:00 at baseline (Day 0) and Day 14 using the same sampling procedure at both time points. Label each specimen with the participant study identification code, collection time, and transport the samples promptly to the central laboratory.
- Allow the collected blood samples to clot at room temperature for approximately 30 min. Process all specimens within 2 h of collection. Centrifuge the samples at 1,500 × g for 10 min at 4 °C using a refrigerated benchtop centrifuge.
- Separate the serum immediately after centrifugation and inspect each specimen for hemolysis, lipemia, or other visible abnormalities that could interfere with analysis. Analyze the separated serum on the day of collection; do not subject samples to long-term frozen storage or repeated freeze–thaw cycles.
- Measure interleukin-6 (IL-6) using an electrochemiluminescence immunoassay according to the manufacturer's instructions. Perform a high-sensitivity C-reactive protein (hs-CRP) measurement using the validated assay routinely employed by the central laboratory.
- Use the same sampling, processing, and analytical procedures for baseline and Day 14 specimens. Perform instrument calibration and internal quality control in accordance with the manufacturer's instructions and the central laboratory's standard operating procedures. Record biomarker results only after the corresponding analytical run satisfies the predefined laboratory quality-control criteria.
- Calculate the number of days from treatment initiation until pain decreases to a VAS score of ≤1 and redness and swelling remain absent or mild without progression for at least 24 h. Record the time to symptom resolution for each participant.
- Evaluate Traditional Chinese Medicine (TCM) syndrome scores at each scheduled assessment using the predefined scoring criteria. Calculate the total score for each participant.
- Calculate the efficacy index according to changes in the total TCM syndrome score. Classify treatment responses using the predefined efficacy categories and calculate the total effective rate.
- Standardize outcome assessment
- Train both outcome evaluators before participant enrollment using the predefined Grade 0-IV phlebitis criteria and TCM syndrome scoring criteria. Review the definitions of pain, erythema, swelling, burning sensation, induration, and exudation to establish a consistent interpretation of each grading category.
- Ask the two trained evaluators to independently assess phlebitis grade and TCM syndrome score using identical standardized assessment forms. Whenever feasible, maintain the same evaluator pair across scheduled assessments. Keep the evaluators unaware of treatment allocation whenever possible.
- Resolve discrepant assessments by discussion and consensus. If consensus cannot be reached, request adjudication by a senior investigator who is not involved in treatment administration. Record the final adjudicated score in the case report form.
7. Data collection and quality control
- Collect study data
- Collect baseline demographic and clinical information immediately after enrollment and before randomization. Record participant characteristics, tumor treatment status, phlebitis grade, VAS pain score, inflammatory biomarker levels, TCM syndrome score, and other relevant clinical variables using standardized case report forms.
- Complete follow-up assessments on Day 7 and Day 14 according to the study schedule. Record treatment completion, outcome measures, nursing observations, adverse events, and protocol deviations at each assessment.
- Manage study data
- Enter all study data into the electronic database using independent double-data entry. Compare the two datasets and resolve discrepancies by reviewing the original source documents.
- Review completed case report forms for completeness and consistency before database entry. Correct identified errors promptly and document all modifications according to the study data-management procedures.
- Maintain data quality
- Review study records regularly to identify missing, inconsistent, or implausible data. Verify questionable entries against the original case report forms and nursing records.
- Resolve all outstanding data queries before the database lock. Finalize the verified dataset before initiating the statistical analysis.
8. Safety monitoring
- Monitor treatment safety
- Inspect the treatment area before each topical application and at each scheduled assessment. Evaluate erythema, swelling, blistering, dermatitis, exudation, pruritus, pain, and other local skin reactions.
- Document the onset, severity, duration, management, outcome, and relationship of each adverse event to the study intervention. Record all findings in the case report form.
- Manage adverse events
- Classify adverse events as mild, moderate, or severe according to the predefined study criteria. Refer clinically significant events to an independent investigator for review.
- Stop the assigned topical treatment if severe irritation, suspected infection, allergic reaction, or other clinically significant intolerance develops. Provide appropriate medical management and document the reason for treatment discontinuation.
- Reassess the treatment site after completion of the 14-day intervention. Document any persistent or delayed adverse reactions before study completion.
9. Statistical analysis
- Prepare the study dataset
- Perform the primary efficacy analysis according to the intention-to-treat principle. Perform supportive analyses using the per-protocol population and evaluate safety in all participants who receive at least one topical treatment.
- Present continuous variables as mean ± standard deviation or median (interquartile range), as appropriate. Present categorical variables as frequencies and percentages.
- Compare continuous variables using the independent-samples t-test or Mann–Whitney U test, as appropriate. Compare categorical variables using the chi-square test or Fisher's exact test.
- Compare the proportion of participants with persistent grade II or higher phlebitis on Day 14 between treatment groups. Report effect estimates with 95% confidence intervals and corresponding P values.
- Compare VAS pain scores, hs-CRP concentrations, IL-6 concentrations, TCM syndrome scores, and clinical efficacy between groups using appropriate parametric or nonparametric statistical tests. Analyze time-to-symptom resolution using Kaplan–Meier survival analysis with the log-rank test.
- Perform additional analyses
- Adjust for clinically relevant baseline variables when appropriate using multivariable regression models18. Include prespecified variables such as baseline phlebitis grade, puncture site, and chemotherapy-drug irritability when applicable19. Report adjusted effect estimates with 95% confidence intervals.
- Compare the results of the intention-to-treat and per-protocol analyses to evaluate the robustness of the study findings.
- Handle missing data and statistical significance
- Handle missing outcome data using the predefined statistical analysis plan. Perform sensitivity analyses when missing data are present.
- Perform all statistical analyses using SPSS Statistics version 26.0. Use two-sided statistical tests and consider P < 0.05 statistically significant.
Results
A total of 94 participants were randomized equally to the experimental and control groups (47 participants per group). Participant screening, randomization, follow-up, and analysis are summarized in Figure 1. The standardized intervention workflow, including topical treatment, standard nursing care, scheduled assessments, and safety monitoring, is illustrated in Figure 2. Baseline phlebitis grade, visual analog scale (VAS) pain score, high-sensitivity C-reactive protein (hs-CRP), interleukin-6 (IL-6), and Traditional Chinese Medicine (TCM) syndrome score were comparable between groups (all P > 0.05; Table 1).
Phlebitis severity improved progressively in both groups; however, participants receiving the Huzhang Sanhuang formula demonstrated greater improvement, with a larger proportion achieving grade 0–I during follow-up (Figure 3; Table 2). At Day 7, persistent grade ≥II phlebitis was observed in 25.5% of the experimental group and 44.7% of the control group (RR, 0.57; 95% CI, 0.32–1.02; P = 0.052). By Day 14, the incidence decreased to 17.0% and 40.4%, respectively (RR, 0.42; 95% CI, 0.20–0.87; P = 0.012; Table 2). Complete phlebitis grade distributions at Day 7 and Day 14 are presented in Table 2, demonstrating that persistent grade ≥II phlebitis, indicative of a suboptimal treatment response, occurred less frequently in the experimental group.
Pain intensity decreased throughout the intervention in both groups, with significantly greater improvement in the experimental group (Figure 4). Mean VAS scores were significantly lower in the experimental group than in the control group at both Day 7 (2.8 ± 0.9 vs. 3.6 ± 1.0; P < 0.001) and Day 14 (1.4 ± 0.7 vs. 2.2 ± 0.8; P < 0.001; Table 3).
Inflammatory biomarkers also declined more markedly following treatment with the Huzhang Sanhuang formula (Figure 5). At Day 14, mean hs-CRP concentrations were 8.7 ± 3.1 mg/L in the experimental group and 11.7 ± 3.4 mg/L in the control group (P < 0.001). Mean IL-6 concentrations were 4.9 ± 1.8 pg/mL and 6.1 ± 2.0 pg/mL, respectively (P = 0.003; Table 3).
Kaplan–Meier analyses demonstrated faster resolution of erythema, swelling, burning sensation, cord-like induration, pain, and the composite symptom endpoint in the experimental group (Figure 6; Table 4). Median remission times were shorter for erythema (4.8 vs. 6.7 days), swelling (5.8 vs. 8.1 days), burning sensation (3.6 vs. 5.4 days), cord-like induration (7.2 vs. 10.1 days), and pain (3.8 vs. 6.1 days). Hazard ratios consistently favored the experimental intervention (HR, 1.48–1.71; all P < 0.05). Integrated treatment effects across phlebitis severity, pain, inflammatory biomarkers, and symptom resolution are summarized in Table 3.
Both groups exhibited reductions in TCM syndrome scores by Day 14, with greater improvements in erythema, swelling, burning sensation, pain or tenderness, cord-like induration, and total syndrome score in the experimental group (Table 5A). The experimental group also demonstrated a higher proportion of cured and markedly effective cases, resulting in a numerically higher overall effective rate than the control group (95.7% vs. 85.1%; RR, 1.12; 95% CI, 0.98–1.29; P = 0.080) (Table 5B). These findings were consistent with the improvements in the integrated efficacy outcomes summarized in Table 3.
Safety and implementation outcomes are presented in Table 6 and Figure 7. No serious treatment-related adverse events were observed. Local adverse events were infrequent and comparable between groups (10.6% vs. 12.8%; P = 1.000). Reported events were predominantly mild and reversible, including pruritus, rash or erythema, burning or stinging sensations, and occasional contact dermatitis or blistering.
Treatment adherence remained high in both groups, reaching 95.6% ± 4.8% in the experimental group and 92.4% ± 5.9% in the control group (P = 0.005; Table 6; Figure 7). High adherence (≥90%) was achieved by 89.4% of participants in the experimental group and 78.7% in the control group (P = 0.260). These findings indicate that the intervention was implemented consistently, with excellent treatment adherence and no evidence of clinically significant local intolerance.
Multivariable analysis demonstrated that assignment to the experimental group remained independently associated with greater odds of improvement in phlebitis after adjustment for prespecified covariates (adjusted OR, 2.64; 95% CI, 1.21–5.74; P = 0.015; Table 7). Sensitivity analysis produced similar findings (adjusted OR, 2.31; 95% CI, 1.08–4.96; P = 0.032), supporting the robustness of the treatment effect. Baseline phlebitis grade ≥II was independently associated with a lower probability of improvement, whereas age, sex, body mass index, diabetes, smoking status, baseline VAS score, chemotherapy irritability, catheter gauge, infusion duration, and previous phlebitis history were not significantly associated with treatment response (Table 7).
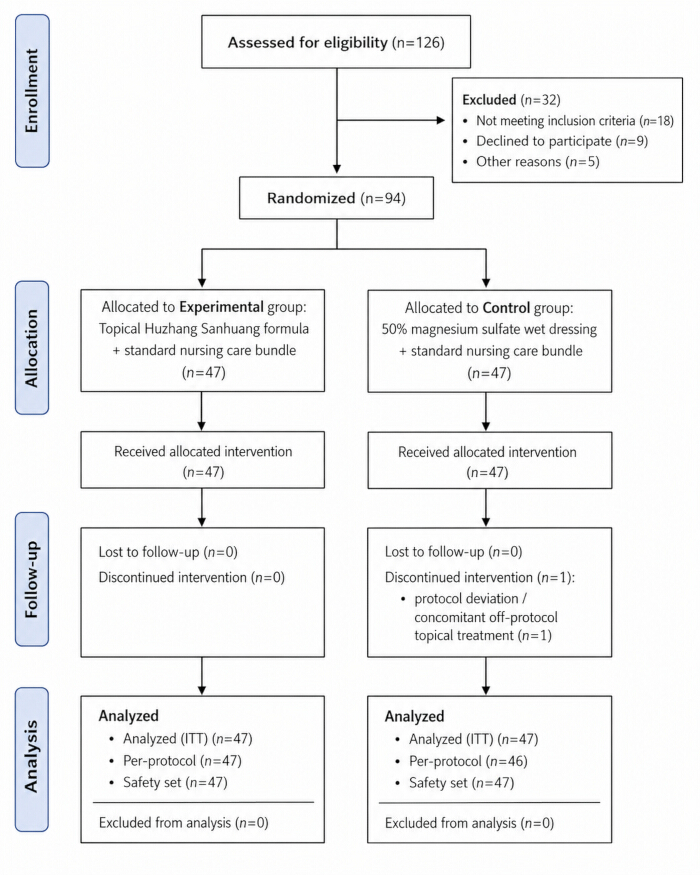
Figure 1: CONSORT flow diagram of participant enrollment, randomization, follow-up, and analysis sets. Flowchart showing screening, eligibility assessment, randomization (1:1), group allocation, follow-up, and analysis populations in the study. The diagram identifies participant counts in the experimental group (topical Huzhang Sanhuang formula plus standard nursing care) and the control group (50% magnesium sulfate wet dressing plus standard nursing care), and specifies the intention-to-treat (ITT), per-protocol, and safety analysis populations. Please click here to view a larger version of this figure.
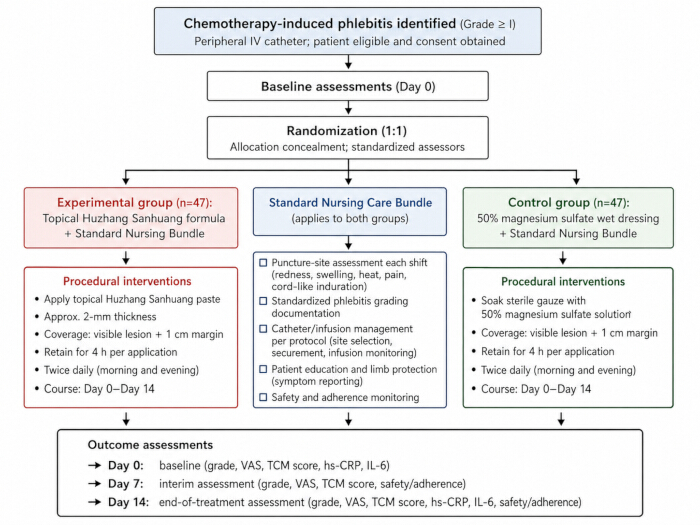
Figure 2: Standardized intervention workflow for topical Huzhang Sanhuang formula application within the nursing care bundle. Procedural schematic of the intervention pathway, including baseline assessment, group allocation, topical treatment, standardized nursing care, scheduled assessments, and safety/adherence monitoring. The experimental group received topical Huzhang Sanhuang formula, and the control group received 50% magnesium sulfate wet dressing, both extending 1 cm beyond the lesion margin, retained for 4 h per application, and administered twice daily for 14 days. Assessments were performed on Day 0, Day 7, and Day 14. Please click here to view a larger version of this figure.
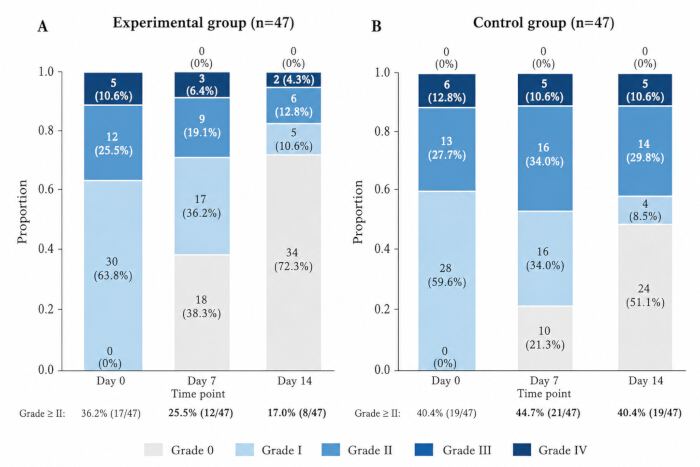
Figure 3: Distribution of phlebitis grades (0–IV) at baseline, Day 7, and Day 14 in the experimental and control groups. (A) Experimental group. Distribution of phlebitis grades (0–IV) at baseline, Day 7, and Day 14. (B) Control group. Distribution of phlebitis grades (0–IV) at baseline, Day 7, and Day 14. Please click here to view a larger version of this figure.
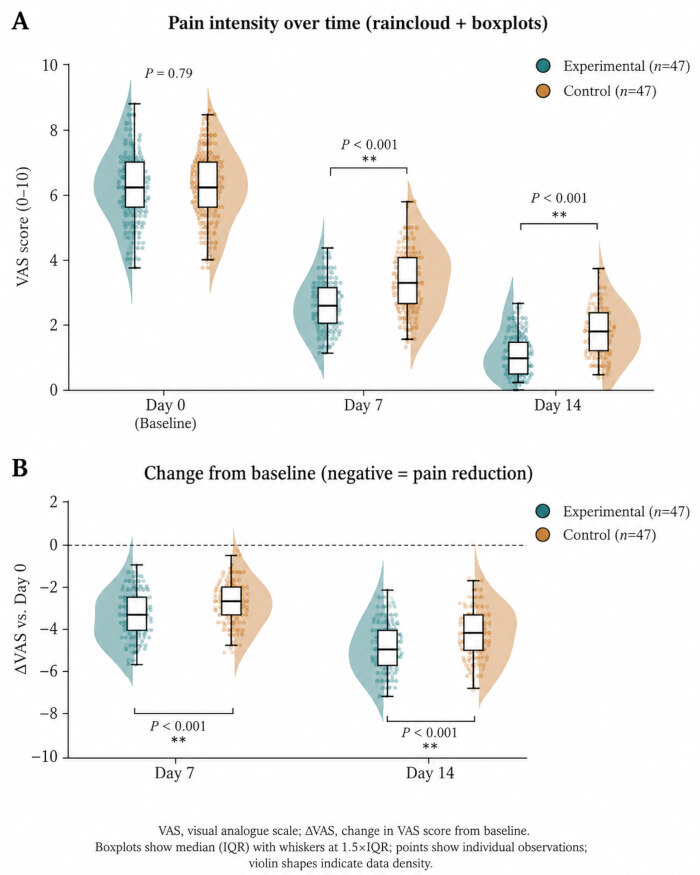
Figure 4: Time-course trajectories of pain intensity (VAS) during treatment (Day 0, Day 7, and Day 14) by group. Longitudinal visualization of pain scores measured by the Visual Analog Scale (VAS, 0–10). The figure shows within-group pain reduction over time and between-group separation in pain trajectories, with the experimental group demonstrating earlier and larger pain relief. Please click here to view a larger version of this figure.
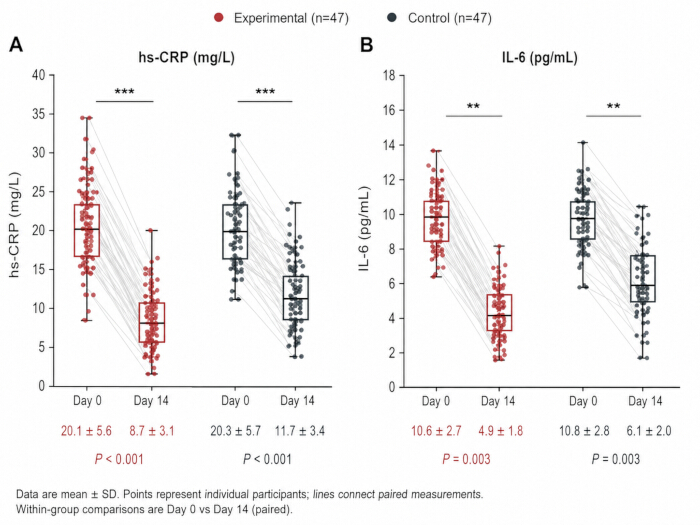
Figure 5: Pre-post changes in inflammatory biomarkers (hs-CRP and IL-6) in the experimental and control groups (Day 0 vs. Day 14). Paired or grouped visualization of hs-CRP and IL-6 levels at baseline and end of treatment. The figure shows biomarker reduction in both groups, with a greater decrease in the experimental group, supporting the intervention's anti-inflammatory effect. Please click here to view a larger version of this figure.
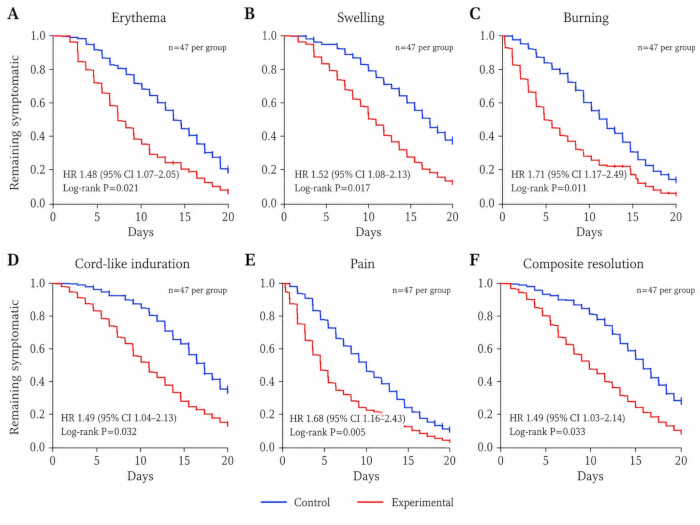
Figure 6: Kaplan–Meier curves for time to symptom resolution by group. Kaplan–Meier plots showing time to resolution of erythema, swelling, burning sensation, cord-like induration, pain, and the composite symptom endpoint in the experimental and control groups. Curves are compared using the log-rank test, and earlier separation between curves indicates faster symptom remission in the experimental group. Please click here to view a larger version of this figure.
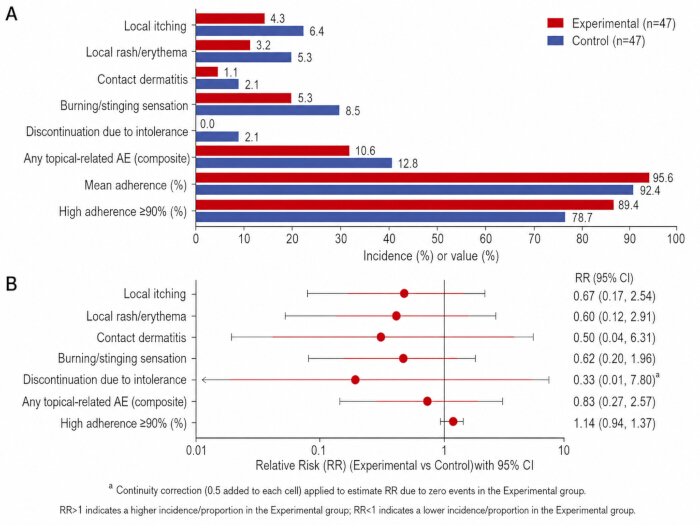
Figure 7: Safety profile, tolerability, and adherence outcomes for topical therapy in both groups. Summary visualization of safety and process outcomes. (A) Mean adherence to the prescribed topical applications, presented descriptively. (B) Safety and categorical adherence outcomes, including the incidence of local topical treatment-related adverse events, discontinuation due to intolerance, and the proportion of participants achieving high adherence (≥90%), were summarized as relative risks (RRs) with 95% confidence intervals (CIs). Please click here to view a larger version of this figure.
Table 1: Baseline demographic and clinical characteristics of participants in the experimental and control groups. Continuous variables are presented as mean ± standard deviation (SD), and categorical variables are presented as number (%). Between-group comparisons were performed using the independent-samples t test for continuous variables and the chi-square test or Fisher's exact test for categorical variables, as appropriate. P values are two-sided. Please click here to download this Table.
Table 2: Changes in phlebitis severity over time and prespecified between-group comparisons. (A) Distribution of phlebitis grades (0–IV) at baseline (Day 0), Day 7, and Day 14 in the experimental and control groups, including the proportion of participants with moderate-to-severe phlebitis (Grade ≥II). (B) Between-group comparisons of overall phlebitis grade distributions using the Mann–Whitney U test and comparisons of Grade ≥II incidence using relative risks (RRs) with 95% confidence intervals (CIs). Please click here to download this Table.
Table 3: Integrated summary of primary and secondary efficacy outcomes at baseline, Day 7, and Day 14. Outcomes include phlebitis severity, pain intensity, inflammatory biomarkers, time to symptom resolution, TCM syndrome scores, and clinical efficacy. Effect estimates are reported as relative risks (RRs), mean differences (MDs), hazard ratios (HRs), or Mann–Whitney U comparisons, as appropriate, with corresponding 95% confidence intervals (CIs) and P values. Please click here to download this Table.
Table 4: Time to resolution of individual phlebitis symptoms and overall composite resolution. Median time to symptom resolution is presented with the interquartile range (IQR). Between-group comparisons were performed using Cox proportional hazards models and summarized as hazard ratios (HRs) with 95% confidence intervals (CIs). P values were derived from log-rank tests. Please click here to download this Table.
Table 5: Traditional Chinese medicine (TCM) syndrome score components and clinical efficacy outcomes. (A) Mean TCM syndrome component scores at baseline and Day 14 in the experimental and control groups, with between-group comparisons at Day 14. (B) Clinical efficacy categories based on percentage reduction in total TCM syndrome score and comparison of overall treatment effectiveness between groups. Continuous variables are presented as mean ± SD and categorical variables as number (%). Please click here to download this Table.
Table 6: Safety, tolerability, adherence, protocol deviations, and concomitant treatments during the study period. Local treatment-related adverse events, discontinuations, adherence outcomes, protocol deviations, and concomitant therapy use are presented as counts (%) or means ± SD. Between-group comparisons are summarized using relative risks (RRs) or mean differences (MDs) with 95% confidence intervals (CIs), together with corresponding P values. Please click here to download this Table.
Table 7: Multivariable logistic regression analysis of treatment response at Day 14. Adjusted odds ratios (ORs) with 95% confidence intervals (CIs) are presented for the primary intention-to-treat (ITT) and per-protocol (PP) sensitivity analyses. Treatment response was defined as phlebitis grade 0–I at Day 14, whereas persistent grade ≥II was classified as non-response. Covariates included baseline demographic and clinical characteristics specified a priori. Please click here to download this Table.
Discussion
The principal methodological finding of this study is that the topical Huzhang Sanhuang formula can be reproducibly integrated into a standardized nursing pathway for chemotherapy-induced phlebitis20. Successful implementation of the method is best demonstrated by concordant improvements in phlebitis severity, pain, symptom resolution, inflammatory biomarkers, treatment adherence, and safety. In the present study, participants receiving the Huzhang Sanhuang formula showed a lower incidence of persistent grade ≥II phlebitis at Day 14, faster symptom resolution, greater reductions in pain intensity, and lower hs-CRP and IL-6 concentrations than those receiving conventional topical treatment. These benefits were achieved while maintaining high treatment adherence and a low incidence of local adverse events.
In addition to statistical significance, the observed treatment effects may be clinically meaningful. The 0.8-point reduction in VAS pain score represents a modest but potentially important improvement in patient comfort, whereas the reductions in hs-CRP and IL-6 suggest attenuation of the local inflammatory response. More importantly, shortening symptom remission by approximately 1.8–2.9 days may reduce patient discomfort and facilitate uninterrupted peripheral intravenous chemotherapy.
Several procedural steps are critical for ensuring reproducibility. Apply the topical preparation uniformly over the visible inflammatory area, extending the application approximately 1 cm beyond the lesion margin. Maintain a consistent application thickness, retain each dressing for 4 h, and administer treatment twice daily for 14 consecutive days. Standardize puncture-site assessment, catheter management, symptom monitoring, patient education, and outcome assessment across both study groups. Variability in herbal preparation, application coverage, retention time, or nursing procedures may reduce treatment consistency and complicate interpretation of the intervention effect21.
Troubleshooting should focus primarily on local tolerance and protocol adherence. Inspect the application site during every dressing change for worsening erythema, pruritus, papules, exudation, blistering, increased pain, or signs of infection. Discontinue topical treatment and arrange clinical evaluation if marked irritation or suspected infection develops, and document missed applications or other protocol deviations promptly. Persistent grade ≥II phlebitis despite treatment should be considered a suboptimal response requiring clinical reassessment rather than automatic continuation of topical therapy alone.
Compared with conventional topical management with 50% magnesium sulfate wet dressings, the Huzhang Sanhuang regimen resulted in faster symptom resolution and greater improvement in multiple clinical and inflammatory outcomes. Previous randomized studies have also demonstrated that topical sesame oil can reduce pain severity in chemotherapy-induced phlebitis22, supporting the potential role of topical complementary therapies23. Unlike these predominantly symptom-focused approaches, the present regimen demonstrated consistent benefits in phlebitis severity, pain, inflammatory biomarkers, and symptom resolution. Nevertheless, successful implementation requires standardized herbal preparation, batch consistency, storage conditions, and application procedures to ensure reproducibility.
The method also offers several practical advantages. It is noninvasive, can be readily incorporated into routine nursing care, and does not require a separate treatment pathway. The twice-daily application schedule resulted in high treatment adherence, indicating that the protocol is feasible for hospitalized patients receiving repeated peripheral intravenous chemotherapy. Faster improvement in pain, erythema, swelling, and cord-like induration may also reduce patient discomfort and decrease the need for unscheduled nursing interventions.
Several limitations should be considered when applying this method. The study was conducted at a single center with a moderate sample size. Participant blinding was not feasible because the topical preparations differed in appearance and odor, and follow-up was limited to short-term outcomes. In addition, some participants continued to exhibit grade ≥ II phlebitis on Day 14, suggesting that the intervention may be less effective in more severe or persistent cases. The study was not powered to determine whether treatment efficacy differed by chemotherapy-induced irritability, catheter characteristics, or individual skin sensitivity.
Future multicenter studies should validate the preparation and application protocol using standardized batch-quality criteria and longer follow-up periods. Particular attention should be given to patients with persistent high-grade phlebitis, delayed symptom resolution, or local intolerance. Overall, the topical Huzhang Sanhuang formula appears to be a practical and reproducible adjunct to standardized nursing care, with its effectiveness dependent on consistent preparation, standardized application, systematic safety monitoring, and timely reassessment of suboptimal responses.
In this prospective randomized controlled study involving 94 participants, the topical Huzhang Sanhuang formula combined with standardized nursing care demonstrated superior clinical performance compared with conventional topical treatment administered within the same nursing care pathway for chemotherapy-induced phlebitis. The intervention was associated with greater improvement in phlebitis severity, faster pain relief, shorter symptom-resolution time, and larger reductions in hs-CRP and IL-6 concentrations. It also produced greater improvement in TCM syndrome scores, a numerically higher overall effective rate, high treatment adherence, and a favorable safety profile.
These findings support the use of the topical Huzhang Sanhuang formula as a feasible adjunct to standardized nursing care for chemotherapy-induced phlebitis. The regimen represents a practical, well-tolerated, and clinically meaningful approach for improving symptom control and accelerating recovery in oncology supportive care. Additional multicenter studies are warranted to confirm its generalizability and to optimize patient selection and implementation strategies.
Disclosures
DeepSeek was used only for language polishing during manuscript preparation. It was not used for study design, data analysis, interpretation of results, or development of conclusions. All scientific content was reviewed and approved by the authors, who take full responsibility for the manuscript.
Acknowledgements
The authors thank all patients and their families for participating in this randomized controlled trial. We also acknowledge the nursing staff for their contributions to recruitment, implementation of standard care and topical intervention, follow-up, and data collection. We appreciate the support from the statistics and study management personnel for assistance with randomization, data management, and quality control.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 100-mesh stainless-steel filtration sieve | Hospital Pharmacy, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-FLT-100 | Used to filter the decoction before concentration. Use the same 100-mesh specification for every preparation batch. |
| 50% magnesium sulfate solution | Hospital Pharmacy, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-MGSO4-2025-01 (simulated in-house batch) | Control intervention. Prepare as a 50% w/v solution; soak sterile gauze, cover the visible lesion plus a 1-cm margin, retain for 4 h, and apply twice daily for 14 days. |
| Case report forms, intervention logs, and nursing checklists | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-CIP-CRF-V1.0 | Study-specific forms used to record screening, randomization, topical applications, nursing-bundle completion, adherence, protocol deviations, outcomes, and adverse events. |
| Chinese Pharmacopoeia | Chinese Pharmacopoeia Commission | 2020 Edition, Part I | Reference standard for authentication and quality assessment of Polygonum cuspidatum, Rheum palmatum, Phellodendron amurense, and Scutellaria baicalensis. |
| Digital temperature measuring instrument | Testo SE & Co. KGaA | testo 925, 0563 0925 | Used to monitor decoction temperature at approximately 95–100 °C and concentration temperature at 70–80 °C. |
| Electronic analytical balance | Mettler-Toledo International Inc. | ME204E | Used to weigh 100 g of each crude herbal drug and to verify the final concentrated paste mass. Readability: 0.1 mg. |
| High-sensitivity C-reactive protein assay and analyzer | Roche Diagnostics | Tina-quant Cardiac hs-CRP III, 09188240190; cobas c 702 | Used to measure hs-CRP in fasting venous blood on Day 0 and Day 14. Use the same analyzer and reagent lot whenever possible. |
| Huzhang Sanhuang topical paste application measuring guide | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-AG-01 | Standardized guide for applying approximately 0.20 g/cm² as an approximately 2-mm-thick layer over the visible inflammatory area and 1 cm beyond the lesion margin. |
| Hypoallergenic paper surgical tape | 3M Company | 3M Micropore 1530-1, 2.5 cm × 9.1 m | Used to secure sterile gauze without compression during both experimental and control topical applications. |
| IBM SPSS Statistics | IBM Corporation | Version 26.0 | Statistical software used for the prespecified analyses, including chi-square/Fisher exact tests, t tests, nonparametric tests, linear mixed models, Kaplan–Meier/log-rank analysis, Cox regression, and logistic regression. |
| Interleukin-6 assay and analyzer | Roche Diagnostics | Elecsys IL-6, 07027532190; cobas e 801 | Used to measure IL-6 in fasting venous blood on Day 0 and Day 14. Use the same analyzer and reagent lot whenever possible. |
| Peripheral intravenous catheter, 22G | Becton, Dickinson and Company | BD Insyte Autoguard 22G × 1.00 in, 381423 | Peripheral venous indwelling catheter used for chemotherapy administration; record insertion site, side of cannulation, and dwell time. |
| Peripheral intravenous catheter, 24G | Becton, Dickinson and Company | BD Insyte-N Autoguard 24G × 0.56 in, 381411 | Peripheral venous indwelling catheter used for chemotherapy administration; record insertion site, side of cannulation, and dwell time. |
| Pharmacy refrigerator | Qingdao Haier Biomedical Co., Ltd. | HYC-310 | Store the prepared Huzhang Sanhuang paste at 2–8 °C. Use each batch within 48 h and prepare a fresh batch every 2 days. |
| Phellodendron amurense bark (Huangbai) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot HB20250115 | Use 100 g per preparation batch. Authenticate according to the Chinese Pharmacopoeia; record supplier, lot number, authentication result, and certificate of analysis. |
| Polygonum cuspidatum root and rhizome (Huzhang) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot HZ20250112 | Use 100 g per preparation batch. Authenticate according to the Chinese Pharmacopoeia; record supplier, lot number, authentication result, and certificate of analysis. |
| Purified water system | Merck KGaA | Milli-Q IQ 7000 | Supply 4,000 mL purified water for each 400-g herbal mixture, corresponding to a crude-drug-to-water ratio of 1:10 (w/v). |
| Rheum palmatum root and rhizome (Dahuang) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot DH20250110 | Use 100 g per preparation batch. Authenticate according to the Chinese Pharmacopoeia; record supplier, lot number, authentication result, and certificate of analysis. |
| Scutellaria baicalensis root (Huangqin) | Anhui Xiehecheng Pharmaceutical Decoction Pieces Co., Ltd. | Simulated lot HQ20250118 | Use 100 g per preparation batch. Authenticate according to the Chinese Pharmacopoeia; record supplier, lot number, authentication result, and certificate of analysis. |
| Sealed wide-mouth storage bottle, 500 mL | Thermo Fisher Scientific | Nalgene HDPE bottle, 2114-0016 | Used to store the concentrated Huzhang Sanhuang paste. Label each bottle with preparation date, batch number, storage temperature, and expiry time. |
| Sterile gauze swab, 10 cm × 10 cm, 8-ply | Winner Medical Co., Ltd. | Simulated item code WN-GS1010-8 | Used to cover the Huzhang Sanhuang paste and to prepare the 50% magnesium sulfate wet dressing. |
| Sterile normal saline, 0.9% sodium chloride, 500 mL | Baxter Healthcare Corporation | VIAFLEX container, simulated reference 2B1323Q | Used to clean the affected skin before topical application and after dressing removal. |
| Temperature-controlled concentration apparatus | Shanghai Yarong Biochemical Instrument Factory | RE-52AA rotary evaporator | Used to concentrate the filtered decoction at 70–80 °C to approximately 1,000 g of homogeneous paste, equivalent to approximately 0.40 g crude drug/g paste. |
| Traditional Chinese medicine syndrome score form | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-TCM-01 | Standardized form covering local redness/erythema, swelling, burning sensation, pain/tenderness, and cord-like induration; each item is scored from 0 to 3. |
| Visual analog scale ruler | Study Team, The Second Affiliated Hospital of Nanjing University of Chinese Medicine | HZSH-VAS-01, 10-cm scale | Used to assess pain intensity from 0 (no pain) to 10 (worst imaginable pain) at Day 0, Day 7, and Day 14. |
| Water-based decoction apparatus | Beijing Donghuayuan Medical Equipment Co., Ltd. | YJX20/1+1D | Used to soak the 400-g herbal mixture in 4,000 mL purified water for 30 min and decoct at gentle boiling (approximately 95–100 °C) for 30 min. |
References
- Hou JW, Hu ZY. Efficacy of Sihuang Zijin powder colloid in treating infusion phlebitis in patients with tumors: a randomized controlled study. J Inflamm Res. 2025;18:8119-8129.
- Li J, et al. Development and validation of a nomogram for predicting intravenous amiodarone-induced phlebitis: a prospective cohort study. Health Sci Rep. 2025;8(11):e71557.
- Li F, et al. Severe phlebitis and cutaneous necrosis following peripheral administration of high-concentration potassium chloride: a case report and vascular access management implications. Sci Prog. 2025;108(1):368504251314081.
- Henedy WM, et al. A quasi-experimental study on conservative nursing measures for preventing phlebitis in chemotherapy patients. Sci Rep. 2025;15(1):45226.
- Nasiri M, et al. Is the topical application of sesame oil (Sesamum indicum L.) combined with standard care valuable and safe for managing infusion-related phlebitis: evidence from a systematic review with meta-analysis of randomized controlled trials. Complement Ther Med. 2025;88:103122.
- Zhao Y, et al. Effect of external application of Chinese medicine liquid on preventing phlebitis caused by intravenous indwelling needle: a retrospective study. Biotechnol Genet Eng Rev. 2024;40(3):2862-2873.
- Safikani Mohammadzadeh N, et al. Comparing the effects of sesame oil vs. nitroglycerin ointment on the incidence of chemotherapy-induced phlebitis: a single-blind clinical trial. Asian Pac J Cancer Prev. 2023;24(4):1113-1117.
- Sakakida T, et al. Midline catheter use for cancer patients receiving 5-FU chemotherapy: prospective study of safety and outcomes. Oncologist. 2025;30(5):oyaf108.
- Cernuda-Martínez JA, et al. Clinical-epidemiological predictors of phlebitis associated with peripheral intravenous catheters in Spanish hospitals: results of a national cohort study. Int J Nurs Stud Adv. 2025;9:100355.
- Amble K, et al. Implementation of an infection prevention care bundle for peripheral intravenous catheters (PIVCs): a quality improvement study to enhance PIVC quality and reduce complications. Nurs Rep. 2025;15(11):379.
- Okyay B, Basak T. The effect of cold gel pack application in the prevention of amiodarone-related phlebitis. Nurs Crit Care. 2024;29(6):1739-1743.
- Aksoy F, Bayram SB. The effect of warm moist compresses in peripheral intravenous catheter-related phlebitis. Eur J Oncol Nurs. 2023;67:102438.
- Nickel B, et al. Infusion therapy standards of practice, 9th edition. J Infus Nurs. 2024;47(1 Suppl 1):S1-S285.
- Li J, et al. Implementation of a peripheral intravenous catheter bundle to reduce phlebitis and hospital-onset Staphylococcus aureus bacteremia: a quality improvement project. Infect Prev Pract. 2025;7(4):100495.
- Seid K, et al. Incidence of peripheral intravenous cannula-induced phlebitis and its determinants among admitted patients in Ethiopia: systematic review and meta-analysis. Discov Med. 2024;1:89.
- El-Sayad HE, Aboalizm SE, Abd Elhy AH. Effect of preventive measures on chemotherapy-induced phlebitis among patients with cancer. Menoufia Nurs J. 2023;8(1):187-202.
- Torné-Ruiz A, et al. Assessment, treatment, and follow-up of phlebitis related to peripheral venous catheterisation: a Delphi study in Spain. Healthcare (Basel). 2024;12(3):378.
- Ertaş Akyüz G, Turan N. Association between peripheral intravenous catheters and clinical characteristics in the development of phlebitis. J Vasc Access. 2024;26(2):540-546.
- Beyene Z, et al. Time to phlebitis onset and its predictors among admitted patients with peripheral intravenous cannulas at Debre Markos Comprehensive Specialized Hospital, Northwest Ethiopia, 2024/2025: a prospective follow-up study. PLoS One. 2025;20(11):e0336176.
- Zhang Y, et al. Sanhuang ointment prolongs indwelling time and promotes vein injury repair in patients receiving intravenous infusion via peripheral venous indwelling needles. Pak J Pharm Sci. 2024;37(5).
- Brørs G, et al. Amiodarone-induced phlebitis: incidence and adherence to a clinical practice guideline. Eur J Cardiovasc Nurs. 2023;22(8):824-831.
- Shamloo MBB, et al. Effects of topical sesame (Sesamum indicum) oil on the pain severity of chemotherapy-induced phlebitis in patients with colorectal cancer: a randomized controlled trial. Complement Ther Clin Pract. 2019;35:78-85.
- Gülşen M, Arslan S. Effects of open-label sesame oil applied to cardiac surgery patients in preventing amiodarone-induced phlebitis: a randomized controlled trial. Nurs Crit Care. 2025;30(2):e13085.