This protocol describes a standardized, one-stop cardiovascular magnetic resonance (CMR) procedure for characterizing the structure, function, and myocardial tissue properties of the left atrium and left ventricle in patients with atrial fibrillation (AF). It covers patient preparation, image acquisition, and post-processing, together with representative imaging findings in patients with AF.
Method Article
Assessment of Left Ventricular Myocardial Fibrosis and Edema in Atrial Fibrillation Using Cardiovascular Magnetic Resonance
In This Article
Summary
Abstract
Progressive population aging has driven a steady rise in the incidence of atrial fibrillation (AF), making the management of its long-term prognosis an increasingly important clinical concern. In addition to forming a vicious cycle with progressive atrial dysfunction, AF promotes adverse remodeling and functional impairment of the ventricles, thereby increasing the risk of heart failure. Cardiovascular magnetic resonance (CMR), as the gold standard for evaluating cardiac function, cannot only accurately assess functional abnormalities of the atria and ventricles, but also its quantitative assessment techniques, including T1 mapping, T2 mapping, and extracellular volume (ECV) fraction, enable early and precise quantification of ventricular myocardial pathology. The principal aim of this study is to provide a comprehensive assessment of the left atrium and left ventricle in patients with AF using a one-stop CMR protocol based on multi-parametric quantitative myocardial analysis, providing reliable data for clinical treatment decisions, preoperative assessment, and long-term follow-up.
Introduction
Atrial fibrillation (AF), the most common form of sustained arrhythmia, is rising steadily in incidence1. This progressive disorder typically begins with structural and functional derangement of the left atrium (LA) and ultimately leads to left ventricular (LV) dilation and impaired systolic and diastolic function, commonly evolving from a paroxysmal to a persistent form2. AF is characterized by structural, electrical, and contractile remodeling of the atrium. It is also associated with systemic inflammation and diffuse fibrosis, which eventually give rise to fibrotic and inflammatory changes in the ventricle as well3. A growing body of evidence indicates that myocardial fibrosis and inflammation are closely linked to the pathogenesis of AF4. Pathological studies have confirmed that patients with AF exhibit diffuse myocardial fibrosis of the left ventricle5.
Cardiovascular magnetic resonance (CMR) offers multi-parameter, multi-plane, and multi-sequence imaging, enabling comprehensive evaluation of the heart's structure, function, blood flow, and tissue characteristics. Its clinical application value is receiving increasing attention. Conventional imaging techniques (late gadolinium enhancement and T2WI) are mostly qualitative or semi-quantitative and are helpful for evaluating focal myocardial lesions. However, they have significant limitations for diffuse lesions and early micro-lesions6. The CMR quantitative techniques (T1 mapping, T2 mapping, and ECV) have effectively addressed this deficiency. T1 and T2 mapping are inherent properties of the tissue, representing the longitudinal and transverse relaxation times of the tissue, respectively. The extracellular volume fraction (ECV) refers to the percentage of the extracellular matrix volume in the total myocardial volume7. Theoretically, normal myocardial tissue has fixed values of T1, T2 mapping, and ECV under the same conditions. In disease states, pathological changes occur in the myocardial cells and/or the interstitial matrix, and these values will also change accordingly. T1 mapping, T2 mapping, and ECV of CMR allow quantitative assessment of myocardial fibrosis and inflammation8,9.
Studies have shown that quantitative CMR techniques were significantly influenced by factors such as the manufacturer of the scanning equipment, field strength, and even the sequence, and it is recommended to establish normal reference values suitable for this center based on different equipment, field strengths, and sequences7. Studies10have shown that the normal global T1 and T2 reference values on a 3.0T MR scanner were 1193 ms ± 34 ms and 36 ms ± 2.5 ms, respectively. Another meta-analysis11 on native T1 and ECV in the normal population showed that the pooled mean of native T1 was 976 msec (95% confidence interval [CI]: 969 ms, 983 ms) at 1.5 T and 1159 ms (95% CI: 1143 ms, 1175 ms) at 3.0 T; the pooled mean of ECV was 25.9% at 1.5 T (95% CI: 25.5%, 26.3%) and 3.0 T (95% CI: 25.4%, 26.5%). An inverse linear relationship has been reported between the post-contrast native T1 time of the LV myocardium and the overall degree of myocardial fibrosis12,13. LV T1 mapping can serve as a quantitative indicator of increased myocardial fibrosis in patients with hypertrophic cardiomyopathy14, non-ischemic dilated cardiomyopathy15, and acute or chronic myocardial infarction16. Studies have further shown that LV myocardial interstitial fibrosis in patients with AF is closely related to cardiac dysfunction17,18, and that patients with AF display higher T1 and T2 mapping values than those without AF19. The present study quantitatively analyzed atrial and ventricular function, along with tissue characteristics (T1 mapping, T2 mapping, and ECV), in patients with AF, providing comprehensive quantitative data to inform treatment strategies.
Protocol
This study enrolled consecutive patients with paroxysmal atrial fibrillation who underwent CMR examination at the China-Japan Union Hospital of Jilin University between January 2024 and September 2025. The study was approved by the Ethics Committee of the China-Japan Union Hospital of Jilin University (approval number: 2021092704) and was conducted in accordance with the Declaration of Helsinki. Confidentiality of patient data was strictly maintained throughout the research.
1. Preparation before scanning
- Accurately record the heart rate, blood pressure, weight, and height.
- Exclude contraindications to magnetic resonance imaging (MRI), including renal insufficiency, implanted cardiac electronic devices, other implanted metal devices in the body, cochlear implants, etc.
- Explain the relevant precautions before the examination, and instruct the participant to remain still throughout the scan.
- Instruct the participant to hold their breath at end-expiration and maintain a consistent respiratory amplitude so that the imaging position remains reproducible across acquisitions.
2. CMR scanning
NOTE: Perform all CMR examinations on a 3.0 T CMR system equipped with a dedicated cardiac phased-array surface coil and an MR-compatible electrocardiography (ECG) gating unit.
- Cardiac cine imaging
- Acquire cine images with a balanced steady-state free precession (bSSFP) sequence during an end-expiratory breath-hold using retrospective ECG gating.
- Include three standardized long-axis views (2-, 3-, and 4-chamber views) together with 12–14 short-axis slices covering the entire ventricle, and reconstruct 25 frames per cardiac cycle.
- Use the following main scanning parameters: matrix 216 × 256, FOV 340 mm × 340 mm, TR 3.0 ms, TE 1.7 ms, flip angle 45°–55°, temporal resolution 30–55 ms, slice thickness 8 mm, and slice gap 2 mm.
- Late gadolinium enhancement (LGE)
- Use a two-dimensional phase-sensitive inversion recovery rapid small-angle excitation sequence.
- Inject the gadolinium-based contrast agent (GBCA) through the median cubital vein at a flow rate of 2 mL/s and a dose of 0.2 mmol/kg. Ensure that the flow rate is not too rapid, as this may cause contrast agent leakage. Acquire LGE images 10–15 min after GBCA injection.
- Include LV short-axis and 2- and 4-chamber views. Use the following main scanning parameters: TR 4.1 ms, TE 1.6 ms, TI 300 ms, flip angle 20°, FOV 260 mm × 350 mm, matrix 130 × 256, and slice thickness 8 mm.
- Pre-contrast T1 mapping
- Acquire native T1 maps using the motion-corrected spin-echo real steady-state free precession (SSFP)-based modified Look-Locker inversion recovery (MOLLI) sequence.
- Scan three LV short-axis slices (basal, mid, and apical segments).
- Use the following main scanning parameters: TR 2.8 ms, TE 1.18 ms, flip angle 35°, FOV 270 mm × 320 mm, matrix 144 × 256, and slice thickness 10 mm.
- Post-contrast T1 mapping
- Repeat post-contrast T1 mapping of the previously acquired short-axis slices approximately 15 min after intravenous injection of the contrast agent. Use the same scanning planes and parameters as those used for pre-contrast T1 mapping.
NOTE: Immediately review each T1 mapping image during the examination and repeat the acquisition without delay if artifacts are present. Acquire pre- and post-contrast T1 maps at identical slice locations. Ensure that the myocardium in the basal and apical slices is displayed completely and clearly. Collect venous blood on the same day before the MR examination to determine the hematocrit.
- Repeat post-contrast T1 mapping of the previously acquired short-axis slices approximately 15 min after intravenous injection of the contrast agent. Use the same scanning planes and parameters as those used for pre-contrast T1 mapping.
- Native T2 mapping
- Acquire native T2 maps using the steady-state free precession (SSFP) sequence based on T2-preparation pulses. Use a single breath-hold acquisition mode and enable motion correction (MOCO) to reduce cardiac pulsation and respiratory motion artifacts.
- Scan three LV short-axis slices corresponding to those used for T1 mapping.
- Use the following main scanning parameters: TR 207.5 ms, TE 1.3 ms, flip angle 12°, FOV 360 mm × 360 mm, slice thickness 8 mm, and matrix 256 × 166. Acquire the original images with three different T2 preparation times (TET2P = 0 ms, 30 ms, 55 ms), and use these images for subsequent fitting to calculate native T2 values.
3. CMR image analysis
NOTE: Use the cvi42 CMR analysis software to perform CMR post-processing. Transfer the imaging data to the CMR analysis software.
- Analyze the left atrium and bilateral ventricular volumes and functions.
- Bilateral ventricular volumes and functions
- Use the Function SAX module (ventricular function analysis using short-axis images) to analyze bilateral ventricular function.
- Select the ventricular short-axis cine images and click Detect LV/RV Contours at ED/ES Phases. Allow the software to automatically delineate the left ventricular endocardial and epicardial borders and the right ventricular endocardial border. Manually adjust the contours if the automatic delineation is inaccurate.
- Obtain the automatically calculated biventricular functional parameters, including left ventricular ejection fraction (LVEF), left ventricular end-diastolic volume (LVEDV), left ventricular end-diastolic volume index (LVEDVI), left ventricular end-systolic volume (LVESV), left ventricular end-systolic volume index (LVESVI), right ventricular ejection fraction (RVEF), right ventricular end-diastolic volume (RVEDV), right ventricular end-diastolic volume index (RVEDVI), right ventricular end-systolic volume (RVESV), and right ventricular end-systolic volume index (RVESVI).
NOTE: Ensure that the difference between the left and right ventricular stroke volumes is within 5 mL.
- Left atrial volumes and functions
- Use the Strain module to measure left atrial (LA) volumes from the LV 2- and 4-chamber cine images. Manually delineate the LA endocardial and epicardial borders at end-systole and end-diastole. Exclude the pulmonary vein ostia and the left atrial appendage from the contours.
- Allow the software to automatically propagate the LA contours across all cardiac phases and generate the LA volume (LAV) curve (Figure 1). Identify the three cardiac phases corresponding to end-LV systole, early diastole before active LA contraction, and end-LV diastole. Obtain the maximum LA volume (Vmax), pre-atrial contraction LA volume (Vpre-a), and minimum LA volume (Vmin).
- Calculate the left atrial ejection fractions (LAEF), including total LAEF (LAEFtotal), passive LAEF (LAEFpassive), and active LAEF (LAEFactive), using the following formulas:
Calculation formulas:
LAEF total= (Vmax-Vmin) /Vmax;
LAEF passive= (Vmax-Vpre-a) /Vmax;
LAEF active=(Vpre-a- V min) /Vpre-a
- Bilateral ventricular volumes and functions
- Quantitative analysis of T1 mapping
- Use the Tissue T1 module to acquire pre- and post-contrast T1 values. Manually delineate the left ventricular endocardial and epicardial borders on each pre- and post-contrast image. Click Create T1 Map to generate the pre- and post-contrast T1 maps. Enter the hematocrit value in the T1 Options menu, and click Create ECV Map to generate the extracellular volume (ECV) map.
NOTE: Avoid including regions that may bias the measurements, such as the LV blood pool adjacent to the endocardium and pericardial fat adjacent to the epicardium.
- Use the Tissue T1 module to acquire pre- and post-contrast T1 values. Manually delineate the left ventricular endocardial and epicardial borders on each pre- and post-contrast image. Click Create T1 Map to generate the pre- and post-contrast T1 maps. Enter the hematocrit value in the T1 Options menu, and click Create ECV Map to generate the extracellular volume (ECV) map.
- Quantitative analysis of T2 mapping
- Use the Tissue T2 module to acquire native T2 maps. Manually delineate the left ventricular endocardial and epicardial borders on each image. Click Create T2 Map to generate the T2 map.
NOTE: Avoid including regions that may bias the measurements, such as the LV blood pool adjacent to the endocardium and pericardial fat adjacent to the epicardium.
- Use the Tissue T2 module to acquire native T2 maps. Manually delineate the left ventricular endocardial and epicardial borders on each image. Click Create T2 Map to generate the T2 map.
Results
Statistical analyses
All analyses were performed with SPSS 29. For the baseline information and quantitative parameters of CMR, if the indicators followed a normal distribution, they were expressed as mean ± standard deviation; if they did not follow a normal distribution, they were represented by median and interquartile range. The comparison of measurement data or count data between the two groups was conducted using the two-independent-sample t-test or the χ2 test. P < 0.05 was considered statistically significant.
Typical imaging features of atrial fibrillation
Typical CMR findings in AF include an enlarged left atrium with weakened and dys-synchronous atrial contraction and relaxation; a thin line of enhancement is occasionally seen along the posterior wall of the LA roof. LV diastolic function is markedly impaired, and in severe cases, global LV systolic function may be reduced. Late gadolinium enhancement generally shows no significant delayed enhancement of the LV wall; however, in some patients, the LV T1, T2 mapping, and ECV values are elevated (Figure 2).
Representative imaging findings and interpretation
Between January 2024 and September 2025, 1376 patients undergoing MRI scans at our hospital were screened, and 134 patients with AF were ultimately included in this study. The exclusion criteria were non-ischemic cardiomyopathy(n = 23); myocardial infarction (confirmed by CMR examination) (n = 14); unqualified image quality because of severe CMR artifacts (n = 2); persistent AF (n = 24), and AF during the CMR (n = 3). Finally, we enrolled 68 patients with atrial fibrillation as the paroxysmal AF group and 34 individuals with normal CMR findings as the control group. The patient selection flow diagram of our analysis is shown in Figure 3.
All CMR data were transferred to a cardiovascular post-processing workstation and analyzed by two radiologists, each with more than 5 years of cardiovascular post-processing experience. Measurements from the two readers were averaged, and cases with substantial discrepancies were re-measured. Previous studies7 have shown that quantitative CMR analysis has good repeatability. Therefore, in this study, inter-observer/intra-observer consistency assessments were not conducted.
The baseline characteristics and CMR parameters of the AF and control groups are summarized in Table 1 and Table 2.
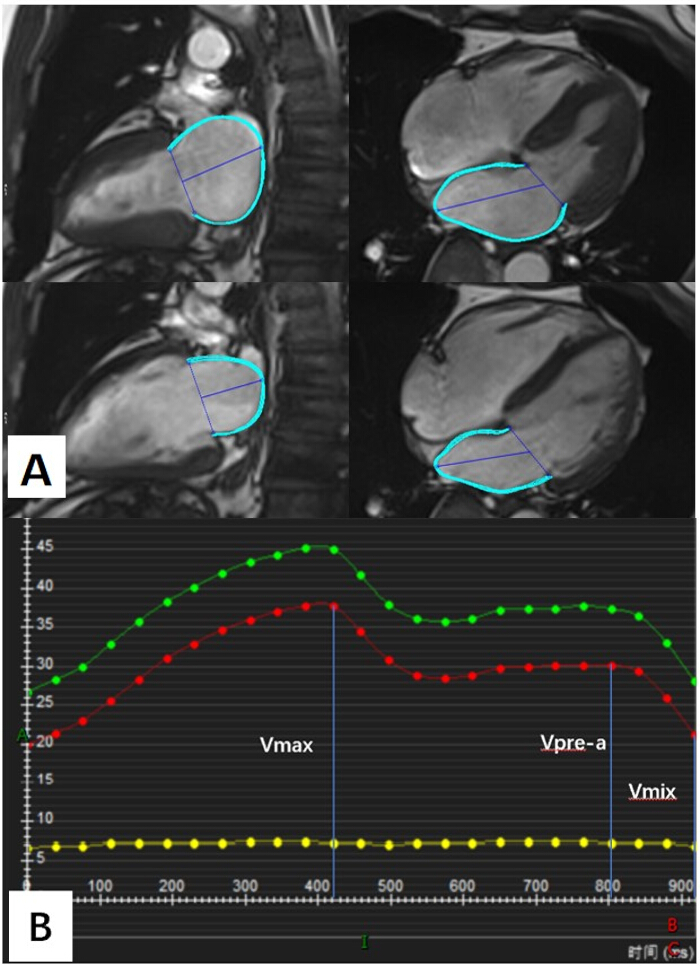
Figure 1: Post-processing of left atrial volume and function by cardiovascular magnetic resonance. (A) Left atrial endocardial contours traced at left atrial end-systole and end-diastole on the four-chamber and two-chamber cine images for left atrial volume and functional analysis. (B) Representative left atrial volume–time curves. The green line represents the epicardial volume curve, and the red line represents the endocardial volume curve. Abbreviations: Vmax, maximum left atrial volume; Vmin, minimum left atrial volume; Vpre-a, left atrial volume immediately before atrial contraction. Please click here to view a larger version of this figure.
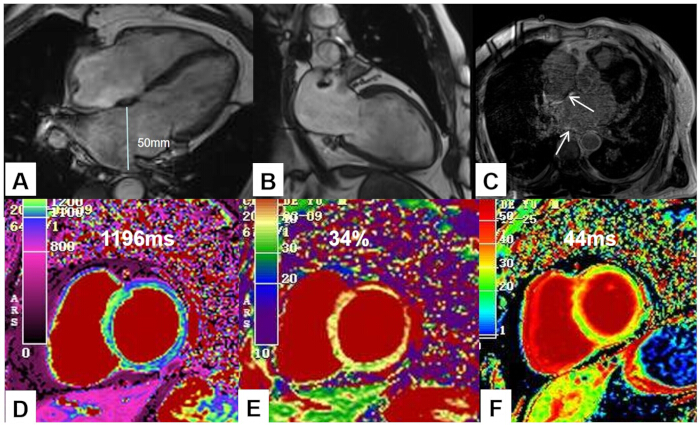
Figure 2: Representative cardiovascular magnetic resonance findings in a 65-year-old man with atrial fibrillation. Four-chamber (A) and two-chamber (B) cine images demonstrating left atrial enlargement. (C) Late gadolinium enhancement image showing linear enhancement of the left atrial roof and interatrial septum. (D,E) Native T1 and T2 mapping images showing values within the normal range. (F) Extracellular volume (ECV) map demonstrating an increased ECV, suggestive of myocardial fibrosis and inflammation. If myocardial fibrosis and inflammation were not confirmed histologically or by another reference standard, consider replacing "indicating" with "suggestive of" or "consistent with", as imaging findings alone cannot definitively establish these pathological processes. Please click here to view a larger version of this figure.
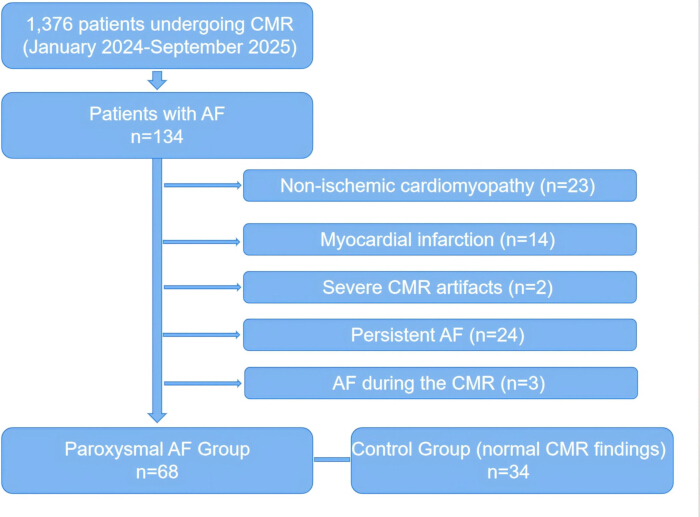
Figure 3: Flow diagram of patient selection. Abbreviations: CMR, cardiovascular magnetic resonance; AF, atrial fibrillation. Please click here to view a larger version of this figure.
| Baseline characteristics | AF group | Control group | P-value |
| (n = 68) | (n = 34) | ||
| Age (years) | 63.37±16.16 | 36.31±15.33 | <0.0001* |
| Sex(male, %) | 38, 55.88% | 18, 52.94% | 0.231 |
| BMI(kg/m2) | 26.38±5.13 | 25.62±3.14 | 0.742 |
| Hypertension (n, %) | 16, 23.53% | 0,0 | - |
| Diabetes (n, %) | 19, 27.94% | 4, 11.76% | <0.05* |
| CHD (n, %) | 18, 26.47% | 0, 0 | - |
| Calcium blockers (n, %) | 23, 33.82% | 0, 0 | - |
| Betablockers (n, %) | 40, 58.82% | 0, 0 | - |
| Renin–angiotensin system medication (n, %) | 16, 23.53% | 0, 0 | - |
| Antiarrhythmia drug (n, %) | 35, 51.47% | 0, 0 | - |
| Data represent mean ± standard deviation. AF, atrial fibrillation; BMI, body mass index; CHD, coronary heart disease; *: P<0.05. | |||
Table 1: Baseline characteristics of the atrial fibrillation and control groups.
| CMR parameters | AF group | Control group | P-value |
| (n = 68) | (n = 34) | ||
| LVEF (%) | 48.72±15.52 | 61.09±4.96 | <0.0001* |
| LVEDV (ml) | 149.69±49.30 | 134.58±25.47 | 0.052 |
| LVEDVI(ml/m2) | 81.68±22.20 | 75.66±11.53 | 0.085 |
| LVESV (ml) | 80.54±51.00 | 52.23±11.18 | 0.0001* |
| LVESVI(ml/m2) | 43.53±24.08 | 29.46±5.94 | <0.0001* |
| LAEFtotal (%) | 50.61±14.50 | 64.27±6.76 | <0.0001* |
| LAEFpassive (%) | 26.08±9.42 | 32.28±9.33 | 0.003 |
| LAEFactive (%) | 33.87±13.84 | 47.07±8.51 | <0.0001* |
| RVEF(%) | 49.65±14.10 | 57.04±4.79 | 0.0003* |
| RVEDV(mm3) | 143.11±42.49 | 143.96±30.15 | 0.911 |
| RVEDVI(ml/m2) | 78.05±19.13 | 80.77±13.34 | 0.421 |
| RVESV (ml) | 73.47±39.83 | 62.10±15.72 | 0.051 |
| RVESVI(ml/m2) | 40.05±17.92 | 34.81±7.42 | 0.048 |
| LV T1(ms) | 1221.81±83.28 | 1203.25±69.09 | 0.253 |
| LV T2(ms) | 42.76±3.50 | 41.31±4.13 | 0.108 |
| LV ECV(%) | 31.67±4.75 | 30.78±2.56 | 0.241 |
| Data represent mean ± standard deviation.CMR, cardiovascular magnetic resonance; AF, atrial fibrillation; LVEF, left ventricular ejection fraction; LVEDV, left ventricular end-diastolic volume; LVEDVI, left ventricular end-diastolic volume index; LVESV, left ventricular end-systolic volume; LVESVI, left ventricular end-systolic volume index; LAEFtotal, the total left atrial ejection fraction; LAEFpassive, the passive left atrial ejection fraction; LAEFactive, the active left atrial ejection fraction; RVEF, right ventricular ejection fraction; RVEDV, right ventricular end-diastolic volume; RVEDVI, right ventricular end-diastolic volume index; RVESV, right ventricular end-systolic volume; RVESVI, right ventricular end-systolic volume index; ECV, extracellular volume fraction. *:P<0.05. | |||
Table 2: Baseline cardiovascular magnetic resonance parameters of the atrial fibrillation and control groups.
Discussion
Atrial fibrillation (AF) is among the most common arrhythmias, and its principal pathological basis is well recognized to be structural, electrical, and functional remodeling of the left atrium. For this reason, attention has traditionally centered on structural and functional changes of the atrium. The major adverse consequence of AF is the induction of new heart failure or the aggravation of pre-existing heart failure, a process that may be mechanistically linked to left ventricular interstitial fibrosis and inflammation20. Because ventricular diastolic dysfunction may be reversible in the early stages of the arrhythmia21, early noninvasive identification of myocardial fibrosis and inflammation is of considerable importance. T1 mapping, T2 mapping, and ECV derived from CMR allow quantitative assessment of myocardial fibrosis and inflammation8,9 and an inverse linear relationship has been reported between the post-contrast native T1 time of the left ventricular myocardium and the overall degree of myocardial fibrosis12,13. By enabling a one-stop examination, CMR provides comprehensive information on the structure, function, and myocardial tissue characteristics of both the atrium and the ventricle, thereby offering favorable conditions for individualized treatment and prognostic assessment in patients with AF.
Although the relationship between AF and myocardial fibrosis and edema, and the direction of causality between them, remains unresolved, myocardial fibrosis and edema are established independent predictors of adverse events in AF22,23. In the present study, LVEF, RVEF, LAEFtotal, and LAEFactive were significantly lower in the AF group than in the control group (p < 0.05), consistent with previous reports. In contrast, native T1, T2 mapping, and ECV did not differ significantly between groups, which diverges from some earlier studies. This discrepancy may reflect the small sample size and consequent selection bias, as well as the possibility that most patients had not yet developed structural pathology and exhibited only functional, potentially reversible, changes. Notably, in individual analyses, patients with more severe atrial and ventricular dysfunction showed elevated T1, T2 mapping, and ECV. Incorporating T1 mapping, T2 mapping, and ECV into the clinical evaluation of patients with AF is therefore likely to provide more reliable data for individualized treatment and prognostic assessment.
During the CMR examination, the patient's heart rate and rhythm should be controlled, as the occurrence of AF can degrade image quality and affect measurement results. Pre- and post-contrast T1 mapping must be acquired at consistent slice positions, and the myocardium in the basal and apical slices should be displayed completely and clearly. The hematocrit should be obtained on the same day, before the MR examination.
When analyzing ventricular function, the difference in stroke volume between the left and right ventricles should be kept within 5 mL. When analyzing atrial function and morphology, the left atrial contour should exclude the pulmonary vein ostia and the left atrial appendage to ensure reproducibility. When analyzing T1 and T2 mapping, regions that may bias the measurement, such as the left ventricular blood pool (adjacent to the endocardium) and pericardial fat (adjacent to the epicardium), should be avoided. In the presence of artifacts, contours should be drawn to exclude affected regions and preserve the reliability of the overall result.
Several practical problems may arise during acquisition and post-processing, and anticipating them improves data quality. During the CMR examination, monitor the patient's heart rate and rhythm, as an AF episode during scanning degrades image quality and biases mapping values. When the rhythm is irregular, use arrhythmia-rejection or real-time triggering and, where clinically appropriate, defer mapping acquisition until rate control is achieved. Acquire pre- and post-contrast T1 maps at identical slice positions and ensure that the basal and apical myocardium are displayed completely and sharply, repeating any slice affected by through-plane motion. Obtain the hematocrit on the same day and before the examination, because a temporally mismatched hematocrit is a common source of erroneous ECV values.
Beyond image artifacts, common pitfalls include incomplete breath-holds, off-resonance and susceptibility effects near the posterolateral wall and cardiac veins, inaccurate motion correction, and errors in inline map reconstruction. Mitigate breath-hold failure by coaching the patient and by using motion-corrected sequences; suspect off-resonance when regional T1 or T2 values deviate abruptly from neighboring segments, and repeat acquisition after shimming when necessary. During post-processing, verify that automatic contour propagation has not drifted across slices or phases, correct partial-volume contamination from the blood pool and pericardial fat, and confirm that the hematocrit and native/post-contrast blood-pool T1 values entered into the ECV calculation are internally consistent.
When analyzing ventricular function, keep the difference in stroke volume between the left and right ventricles within 5 mL as an internal consistency check. When analyzing atrial function and morphology, exclude the pulmonary vein ostia and the left atrial appendage from the left atrial contour to preserve reproducibility. When analyzing T1 and T2 maps, avoid regions that bias the measurement, such as the left ventricular blood pool adjacent to the endocardium and pericardial fat adjacent to the epicardium. In the presence of residual artifacts, draw contours that exclude the affected regions while preserving the reliability of the overall result.
The CMR mapping technique carries intrinsic technical limitations that are independent of this study's design. Absolute T1, T2, and ECV values are sensitive to field strength, vendor, pulse-sequence implementation, and post-processing software, so reference ranges are not directly transferable between platforms and site-specific normal values are required. Native T1 and ECV reflect a combination of diffuse fibrosis, edema, and expansion of the extracellular space rather than any single tissue process, which limits their pathological specificity. Mapping also has finite spatial resolution and is susceptible to partial volume effects in the thin atrial wall, making characterization of atrial tissue more challenging than that of ventricular tissue. Finally, ECV quantification depends on stable contrast kinetics and an accurately timed hematocrit, and its accuracy may be reduced in patients with abnormal renal function or altered hemodynamics.
Compared with echocardiography, which remains the first-line imaging modality for AF, CMR carries several inherent practical drawbacks despite its superior image quality, tissue characterization, and reproducibility. The examination is considerably more time-consuming, typically requiring 30–60 min of table time together with repeated breath-holds and electrocardiographic gating, whereas a focused echocardiogram can be completed within minutes at the bedside. The confined bore, acoustic noise, and prolonged immobility adversely affect the patient's subjective experience and are poorly tolerated by claustrophobic, dyspneic, or critically ill patients, and image quality is particularly vulnerable to irregular RR intervals during AF. CMR is also more expensive, less widely available, and non-portable, and it is contraindicated or limited in patients with certain implanted devices, severe renal impairment precluding gadolinium administration, or an inability to sustain breath-holds. These limitations mean that CMR is best positioned as a complementary, problem-solving modality for individualized tissue characterization rather than as a routine replacement for echocardiography in the general AF population.
A key strength of this protocol is that it integrates structural, functional, and tissue characterization assessment of both atria and ventricles into a single, one-stop CMR examination, improving workflow efficiency by avoiding repeated or complementary imaging studies. The acquisition follows a standardized, reproducible sequence, and the use of dedicated post-processing software for contour delineation, semi-automatic contour propagation, and inline map generation reduces operator dependence and shortens analysis time. Standardized region-of-interest placement and the internal consistency checks described above further enhance inter- and intra-observer reproducibility. Because the workflow relies on widely available mapping sequences and commercial analysis software, it is readily transferable to other centers once site-specific reference values have been established.
Looking ahead, this protocol offers several avenues for future application and methodological development. Prospective, adequately powered, multicenter studies with standardized reference ranges are needed to clarify the temporal and causal relationship between AF and myocardial fibrosis and edema, and to test whether serial mapping can track reverse remodeling after rhythm-control therapy or catheter ablation. Combining ventricular mapping with dedicated atrial T1 mapping, late gadolinium enhancement, and strain analysis may improve individualized risk stratification, while emerging techniques such as free-breathing, motion-corrected, and accelerated mapping sequences could broaden applicability to patients who cannot sustain breath-holds. Integration of machine-learning-based segmentation and automated quality control is likely to further improve reproducibility and efficiency, supporting the incorporation of CMR mapping into routine, individualized management of patients with AF.
In conclusion, the comprehensive and accurate assessment of both the atria and the ventricles afforded by CMR is expected to play an important role in the individualized prediction, diagnosis, and prognostic evaluation of atrial fibrillation.
Disclosures
The authors declare no conflicts of interest.
Acknowledgements
This research was funded by the Health Science and Technology Innovation Project of the Jilin Provincial Health Commission (grant number 2020J044). The funder had no role in the design, execution, or reporting of the study.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| cvi42 CMR Analysis Software | Circle Cardiovascular Imaging (Canada) | www.circlecvi.com | Image post-processing, ventricular function, atrial strain, T1/T2 mapping, and ECV analysis |
| Dedicated cardiac phased-array surface coil | Siemens Healthineers | www.siemens-healthineers.com | Cardiac imaging surface coil |
| Gadolinium-based contrast agent (GBCA) | Manufacturer not specified | N/A | Intravenous contrast agent for LGE imaging and post-contrast T1 mapping |
| IBM SPSS Statistics version 29 | IBM | www.ibm.com/products/spss-statistics | Statistical analysis |
| MAGNETOM Spectra 3.0 T Magnetic Resonance Imaging System | Siemens Healthineers | www.siemens-healthineers.com | 3.0 T cardiovascular magnetic resonance scanner |
| MR-compatible electrocardiography (ECG) gating unit | Siemens Healthineers | www.siemens-healthineers.com | ECG gating during CMR acquisition |
References
- Lippi G, Sanchis-Gomar F, Cervellin G. Global epidemiology of atrial fibrillation: an increasing epidemic and public health challenge. Int J Stroke. 2021;16(2):217-221.
- Kato T, Yamashita T, Sagara K, et al. Progressive nature of paroxysmal atrial fibrillation: observations from a 14-year follow-up study. Circ J. 2004;68(6):568-572.
- Dzeshka MS, Lip GYH, Snezhitskiy V, et al. Cardiac fibrosis in patients with atrial fibrillation: mechanisms and clinical implications. J Am Coll Cardiol. 2015;66(8):943-959.
- Oikonomou E, Zografos T, Papamikroulis GA, et al. Biomarkers in atrial fibrillation and heart failure. Curr Med Chem. 2019;26(5):873-887.
- Frustaci A, Caldarulo M, Buffon A, et al. Cardiac biopsy in patients with "primary" atrial fibrillation: histologic evidence of occult myocardial diseases. Chest. 1991;100(2):303-306.
- Flett AS, Hayward MP, Ashworth MT, et al. Equilibrium contrast cardiovascular magnetic resonance for the measurement of diffuse myocardial fibrosis: preliminary validation in humans. Circulation. 2010;122(2):138-144.
- Messroghli DR, Moon JC, Ferreira VM, et al. Clinical recommendations for cardiovascular magnetic resonance mapping of T1, T2, T2* and extracellular volume: a consensus statement by the Society for Cardiovascular Magnetic Resonance (SCMR) endorsed by the European Association for Cardiovascular Imaging (EACVI). J Cardiovasc Magn Reson. 2017;19(1):75.
- Robinson AA, Chow K, Salerno M. Myocardial T1 and extracellular volume measurement: underlying concepts and technical considerations. JACC Cardiovasc Imaging. 2019;12(11 Pt 2):2332-2344.
- O'Brien AT, Gil KE, Varghese J, et al. T2 mapping in myocardial disease: a comprehensive review. J Cardiovasc Magn Reson. 2022;24(1):33.
- Xu Z, Li W, Wang J, et al. Reference ranges of myocardial T1 and T2 mapping in healthy Chinese adults: a multicenter 3T cardiovascular magnetic resonance study. J Cardiovasc Magn Reson. 2023;25(1):64.
- Gottbrecht M, Kramer CM, Salerno M. Native T1 and extracellular volume measurements by cardiac MRI in healthy adults: a meta-analysis. Radiology. 2019;290(2):317-326.
- Iles L, Pfluger H, Phrommintikul A, et al. Evaluation of diffuse myocardial fibrosis in heart failure with cardiac magnetic resonance contrast-enhanced T1 mapping. J Am Coll Cardiol. 2008;52(19):1574-1580.
- Sibley CT, Noureldin RA, Gai N, et al. T1 mapping in cardiomyopathy at cardiac MR: comparison with endomyocardial biopsy. Radiology. 2012;265(3):724-732.
- Amano Y, Takayama M, Kumita S. Contrast-enhanced myocardial T1-weighted scout (Look-Locker) imaging for the detection of myocardial damage in hypertrophic cardiomyopathy. J Magn Reson Imaging. 2009;30(4):778-784.
- Han Y, Peters DC, Dokhan B, Manning WJ. Shorter difference between myocardium and blood optimal inversion time suggests diffuse fibrosis in dilated cardiomyopathy. J Magn Reson Imaging. 2009;30(5):967-972.
- Messroghli DR, Walters K, Plein S, et al. Myocardial T1 mapping: application to patients with acute and chronic myocardial infarction. Magn Reson Med. 2007;58(1):34-40.
- Ling LH, Kistler PM, Ellims AH, et al. Diffuse ventricular fibrosis in atrial fibrillation: noninvasive evaluation and relationships with aging and systolic dysfunction. J Am Coll Cardiol. 2012;60(23):2402-2408.
- McLellan AJA, Ling LH, Azzopardi S, et al. Diffuse ventricular fibrosis measured by T1 mapping on cardiac MRI predicts success of catheter ablation for atrial fibrillation. Circ Arrhythm Electrophysiol. 2014;7(5):834-840.
- Treiber JM, Sebastian JS, Backhaus SJ, et al. Atrial fibrillation is linked to increased left ventricular fibrosis and inflammation measured by CMR with prognostic implications. Int J Cardiovasc Imaging. 2026;42:799-808.
- Sossalla S, Pabel S, Knierim M, et al. Effects of atrial fibrillation on the human ventricle. Circ Res. 2022;130(7):994-1010.
- Sossalla S, Vollmann D. Arrhythmia-induced cardiomyopathy. Dtsch Arztebl Int. 2018;115(19):335-341.
- Marrouche NF, Brachmann J, Andresen D, et al. Catheter ablation for atrial fibrillation with heart failure. N Engl J Med. 2018;378(5):417-427.
- Prabhu S, Taylor AJ, Costello BT, et al. Catheter ablation versus medical rate control in atrial fibrillation and systolic dysfunction: the CAMERA-MRI study. J Am Coll Cardiol. 2017;70(16):1949-1961.