A 44-year-old man with Crohn disease developed atraumatic knee marrow edema-like signal and, eight weeks later, a low-energy bicondylar tibial plateau fracture. After fixation and rehabilitation, he was pain-free, walked normally, and had full, painless knee motion at three months.
Case Report
Atraumatic Knee Marrow Edema-Like Signal Preceding a Low-Energy Bicondylar Tibial Plateau Fracture in a Patient with Crohn Disease: A Case Report
In This Article
Summary
Abstract
Bone marrow edema-like signal is a nonspecific magnetic resonance imaging finding whose clinical significance depends on its cause, distribution, associated structural abnormalities, symptoms, and skeletal risk. A 44-year-old construction engineer with Crohn disease and previous systemic corticosteroid exposure developed several weeks of atraumatic, load-related right-knee pain. Available prefracture radiographs showed no visible acute fracture. Noncontrast MRI on 28 July 2025 was reported as showing a medial femoral condyle marrow contusion without a fracture line or subchondral collapse; however, the limited coronal screenshots appeared discordant with the reported localization and were insufficient to establish the precise osseous epicenter without the complete DICOM study. Noncontrast computed tomography on 28 August showed maintained alignment without a visible fracture. Symptoms subsequently worsened during loading. On 22 September, a minor twisting movement while walking was followed by severe pain and inability to bear weight. Radiography and computed tomography demonstrated a comminuted bicondylar tibial plateau fracture, which the source narrative recorded as having been treated with open reduction and internal fixation. At approximately three months postoperatively, he reported no knee pain and had resumed normal walking and usual function; knee range of motion was full and painless. Dual-energy X-ray absorptiometry on 5 February 2026 showed bone mineral density below the expected range for age, with a lowest Z-score of −2.8 at the right total hip. Metabolic laboratory findings were largely within the displayed reference ranges, except for low vitamin B12. The case establishes a temporal sequence but cannot demonstrate direct anatomical progression or causality. Atraumatic marrow edema-like signal accompanied by worsening load-related pain in a patient with systemic skeletal risk factors may warrant diagnostic reassessment, reconsideration of loading, and an individualized bone-health evaluation.
Introduction
Bone marrow edema-like signal is an imaging descriptor rather than a diagnosis. At the knee, it may accompany trauma, stress, or insufficiency injury, osteoarthritis, inflammatory disease, transient bone marrow edema syndrome, osteonecrosis, infection, or neoplasia. The same fluid-sensitive signal pattern can therefore require different management depending on the clinical setting1. Subchondral insufficiency fracture of the knee is diagnosed by integrating the clinical presentation with MRI findings, particularly a subchondral low-signal fracture line, the distribution of surrounding edema-like signal, and the presence or absence of osteochondral collapse. Edema-like signal without a demonstrated fracture line is nonspecific and should not be retrospectively relabeled as a proven insufficiency fracture. Meniscal posterior-root injury, meniscal extrusion, chondrosis, osteoarthritis, osteonecrosis, and transient edema syndromes are relevant imaging differentials2,3,4.
Inflammatory bowel disease (IBD), including Crohn disease, is associated at the population level with low bone mineral density and increased fracture risk. Individual risk is heterogeneous and may reflect chronic inflammation, glucocorticoid exposure, low body mass, malnutrition, malabsorption, smoking, reduced activity, and other patient-specific factors. Current European Crohn’s and Colitis Organisation guidance supports risk-based bone-health assessment and dual-energy X-ray absorptiometry (DXA) in patients with relevant risk factors rather than universal DXA for every patient with IBD5,6,7.
This case addresses a practical diagnostic and management question: how should persistent or worsening load-related knee pain be approached when MRI shows atraumatic edema-like signal but no definite structural fracture is reported? Its educational value lies in recognizing diagnostic uncertainty and the need for reassessment, not in claiming direct anatomical progression from the initial signal abnormality to the later fracture. The report follows the CARE framework to the extent permitted by the retrospective source record8,9.
Case presentation
A 44-year-old man working as a construction engineer developed several weeks of progressively worsening right-knee pain without a preceding fall, direct impact, twisting injury, or other identifiable traumatic event. Pain was provoked by weight bearing and stair climbing and was partially relieved by rest. His occupation involved stair climbing, working on elevated platforms, and carrying equipment.
His medical history included Crohn disease, which had been diagnosed 11 years earlier. The available history recorded systemic corticosteroid treatment for several months at diagnosis, followed by maintenance azathioprine. The disease was described as clinically stable. He reported no previous fracture and had not undergone a bone-density assessment before this episode. The retrospective record did not permit verification of Crohn disease phenotype, prior bowel surgery, documented malabsorption, cumulative glucocorticoid dose, smoking history, family fracture history, recent weight change, or habitual calcium and vitamin D intake; these variables were not inferred.
Clinical examination showed no deformity, swelling, or appreciable effusion. Knee flexion and extension were full. Collateral and cruciate ligament testing was stable, and the distal neurovascular examination was normal. Medial joint-line tenderness was present. During the initial evaluation period, he received a short course of a nonsteroidal anti-inflammatory drug and began physiotherapy emphasizing quadriceps strengthening and lower-limb neuromuscular control. Pain worsened during continued loading, with intermittent giving way and subjective quadriceps weakness. The surviving record does not establish the exact start date, frequency, or weight-bearing intensity of the rehabilitation program.
Clinical timeline
The dated source records establish the sequence shown in Table 1. The fracture occurred approximately eight weeks after the outside MRI and 25 days after the initial CT. The exact dates of symptom onset, the available prefracture radiographs, the operation, and the postoperative radiographs were not recoverable. The three-month clinical outcome was documented by postoperative interval rather than by a recoverable calendar date.
| Event date/interval | Event | Findings/actions | Reporting note | ||||||
| Several weeks before 28 Jul 2025 | Atraumatic right-knee pain began | Progressively worsening, load-related pain; worse with stair climbing and partly relieved by rest. | The exact symptom-onset date was not recoverable from the retrospective record. | ||||||
| Prefracture; exact date unavailable | Standing right-knee radiographs | Anteroposterior and lateral views showed preserved alignment without a visible acute fracture, cortical disruption, or articular-surface depression. | The examination date was not recoverable; the images are described as prefracture radiographs and are not assigned to a specific initial encounter. | ||||||
| 28 Jul 2025 | Outside noncontrast right-knee MRI | The archived report described a medial femoral-condyle marrow contusion; no fracture line, osteochondral defect, or subchondral collapse was described. | The limited coronal screenshots show focal marrow edema-like signal but are discordant with the reported localization; the precise osseous epicenter cannot be established without the full DICOM study. | ||||||
| 26 Aug 2025 | Internal MRI reinterpretation finalized | The reinterpretation retained the marrow-contusion impression and noted a small effusion and suprapatellar quadriceps fat-pad impingement. | The interpreting radiologist's musculoskeletal-subspecialty status was not retrievable. | ||||||
| 28 Aug 2025 (reported 29 Aug 2025) | Initial noncontrast right-knee CT | Alignment was maintained; no visible fracture, dislocation, subluxation, or focal osseous lesion was reported. Displayed reconstruction thickness was 2.00 mm. | Scanner manufacturer and model were not retrievable. CT cannot exclude microscopic trabecular injury. | ||||||
| Late Aug–Sep 2025 | Continued loading and rehabilitation | Pain worsened, with intermittent giving way and subjective quadriceps weakness. | Exact rehabilitation dates, frequency, and weight-bearing intensity were unavailable. | ||||||
| 22 Sep 2025 | Low-energy twisting event and fracture radiographs | A minor twisting movement while walking was followed by immediate severe pain and inability to bear weight. Radiographs showed a comminuted bicondylar tibial plateau fracture with articular involvement. | The fracture occurred approximately 8 weeks after MRI and 25 days after the initial CT. | ||||||
| Shortly after 22 Sep 2025 | Fracture CT | CT showed comminution and split-depression components affecting both tibial plateaus; the morphology was consistent with a Schatzker V pattern. | No formal fracture-CT report was available; classification is morphology based, and the exact acquisition date was not independently confirmed. | ||||||
| After fracture imaging; exact date unavailable | Open reduction and internal fixation | The source narrative recorded operative fixation of the bicondylar tibial plateau fracture. | The operation note, reduction details, implant manufacturer/system, and catalog numbers were unavailable. | ||||||
| Postoperative interval; exact imaging date unavailable | Postoperative right-knee radiographs | Radiographs showed two plate constructs, multiple proximal subchondral rafting screws, maintained reduction, and maintained articular alignment. | The radiograph date was unavailable. Radiographic union is not claimed. | ||||||
| First 6 postoperative weeks; reported interval | Protected postoperative rehabilitation | The source narrative described non-weight-bearing for the first 6 postoperative weeks, followed by graded rehabilitation and progressive weight bearing. | The detailed rehabilitation protocol, visit dates, weight-bearing progression, and adherence were not independently verifiable. | ||||||
| Approximately 3 months after ORIF; exact date unavailable | Clinical follow-up | The patient reported no knee pain and had resumed normal walking and usual function. Knee range of motion was full and painless. | Exact goniometric measurements, validated patient-reported outcome scores, formal return-to-work status, and longer-term follow-up were unavailable. | ||||||
| 8 Jan 2026 | Metabolic laboratory assessment | Vitamin D, calcium, phosphate, magnesium, albumin, alkaline phosphatase, creatinine, alanine aminotransferase, complete blood count, and glycated hemoglobin were not flagged as abnormal; vitamin B12 was low at 104 pmol/L. | Parathyroid hormone, testosterone, thyroid studies, celiac serology, urinary calcium, and bone-turnover markers were unavailable. | ||||||
| 5 Feb 2026 | Dual-energy X-ray absorptiometry | The lowest BMD and Z-score were at the right total hip: 0.657 g/cm² and −2.8, respectively. | At age 45.2 years, Z-scores are preferred. Findings were below the expected range for age and were not interpreted as a BMD-only diagnosis of osteoporosis. | ||||||
Table 1: Clinical timeline. Dated clinical, imaging, treatment, laboratory, and densitometry events are listed in chronological order. Confirmed dates are distinguished from intervals or events whose exact dates were not recoverable from the retrospective record. Please click here to download this Table.
Diagnosis, assessment, and plan
Standing anteroposterior (Figure 1A) and lateral (Figure 1B) right-knee radiographs supplied during revision showed preserved alignment without a visible acute fracture, cortical disruption, or articular-surface depression. Their exact examination date could not be determined. They are therefore described as prefracture radiographs and are not assigned to a specific initial-encounter date.
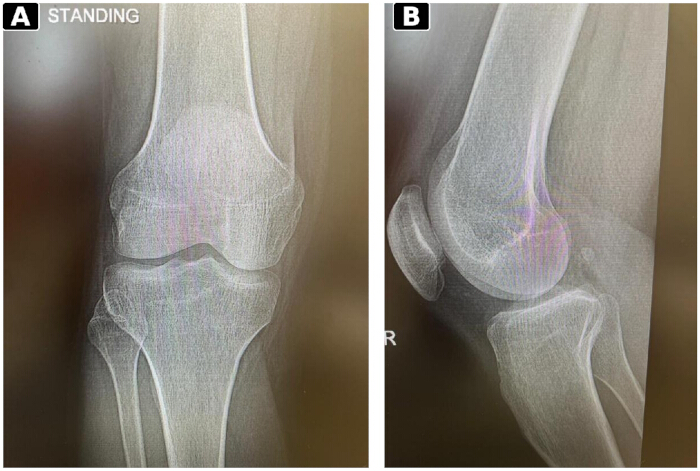
Figure 1: Prefracture right-knee radiographs. (A) The standing anteroposterior view shows preserved alignment without a visible acute fracture, cortical disruption, or articular-surface depression. (B) The lateral view also shows preserved alignment without a visible acute fracture, cortical disruption, or articular-surface depression. The exact examination date was not recoverable; the images are therefore described as prefracture radiographs rather than assigned to a specific initial-encounter date. Please click here to view a larger version of this figure.
The prefracture CT and MRI are presented as Figures 2 and 3, respectively, in the author-confirmed image set. Because the MRI preceded the CT clinically, the two examinations are discussed below in chronological order and are placed together after both descriptions. The outside MRI was acquired on 28 July 2025. The archived report described a routine, noncontrast, multiplanar, multisequence MRI of the right knee. A small joint effusion was present. Patellofemoral alignment and articular cartilage were reported as normal; the medial and lateral menisci, cruciate and collateral ligaments, extensor mechanism, and popliteal region were reported as unremarkable. The impression was “bone marrow contusion of the medial femoral condyle” and suprapatellar quadriceps fat-pad impingement. A subsequent reinterpretation finalized on 26 August 2025 retained this impression.
For this report, “bone marrow edema-like signal abnormality” is used as the neutral imaging term. No subchondral fracture line, osteochondral defect, or collapse was described; consequently, the study does not establish a subchondral insufficiency fracture2,3. The only retrievable PACS series label was Tra_PD_SPIR (24 images). That transverse-series label is not assigned to the two coronal fat-suppressed fluid-sensitive screenshots selected for publication (Figure 3A and Figure 3B). The full DICOM study and complete sequence set were unavailable. The conspicuous signal in the screenshots appears discordant with the medial femoral-condyle localization in the archived report, but the screenshots alone are insufficient to establish the precise osseous epicenter. The MRI manufacturer, scanner model, field strength, knee coil, exact pulse sequence for the published panels, full sequence list, and acquisition parameters were not recoverable retrospectively and are not estimated.
A noncontrast right-knee CT was acquired on 28 August 2025 and reported the next day. Alignment was maintained on the sagittal (Figure 2A) and coronal (Figure 2B) reformatted images, with no fracture, dislocation, subluxation, or focal lytic or sclerotic lesion. The visible reconstruction thickness was 2.00 mm. The scanner manufacturer and model could not be retrieved. CT excluded a macroscopically visible fracture at that examination but could not rule out microscopic trabecular injury. No repeat MRI was obtained to determine whether the edema-like signal persisted or evolved.
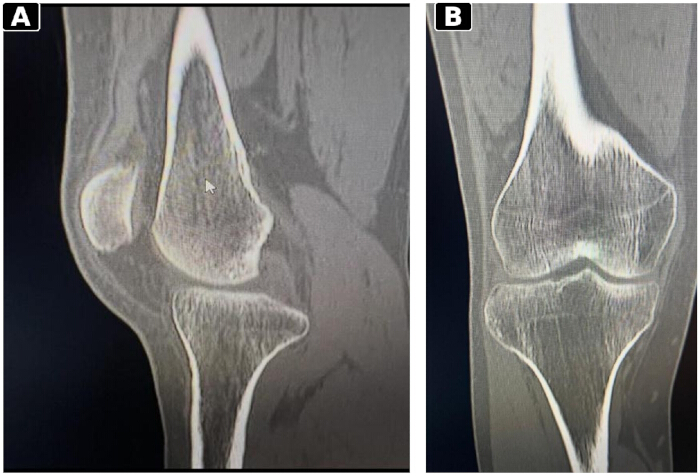
Figure 2: Prefracture noncontrast CT of the right knee. (A) Sagittal reformatted image from 28 August 2025 shows maintained alignment without a visible fracture, cortical break, or articular-surface depression in the displayed sections. (B) Coronal reformatted image from the same examination also shows maintained alignment without a visible fracture, cortical break, or articular-surface depression in the displayed sections. The reconstruction thickness was 2.00 mm; the scanner manufacturer and model were unavailable. CT does not characterize marrow edema-like signal and cannot exclude microscopic trabecular injury. Please click here to view a larger version of this figure.
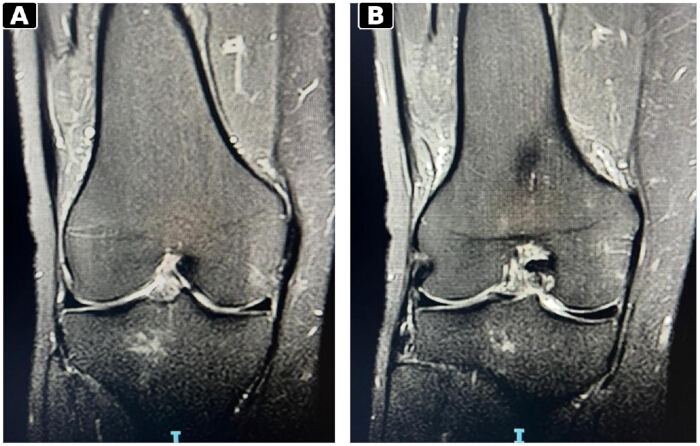
Figure 3: Initial right-knee MRI. (A) The first available coronal fat-suppressed, fluid-sensitive screenshot acquired on 28 July 2025 shows a focal marrow-edema-like signal. (B) The second available coronal fat-suppressed fluid-sensitive screenshot from the same examination also demonstrates the focal marrow edema-like signal. Their appearance is discordant with the medial femoral-condyle localization in the archived report, but the screenshots alone are insufficient to establish the precise osseous epicenter. The discrepancy cannot be resolved without the full DICOM study. No fracture line or subchondral collapse was described; scanner and exact sequence parameters for the displayed panels were not recoverable. Please click here to view a larger version of this figure.
Fracture imaging and treatment
On 22 September 2025, approximately eight weeks after the MRI and 25 days after the initial CT, a minor twisting movement while walking on level ground was followed by immediate severe knee pain and inability to bear weight. Right-knee radiographs showed a comminuted bicondylar tibial plateau fracture with articular involvement. These fracture-episode radiographs are described in the text but are not included among the five revised figure composites. Computed tomography obtained shortly thereafter delineated split-and-depression components affecting both tibial plateaus on three-dimensional volume-rendered (Figure 4A) and sagittal reformatted (Figure 4B) images. The morphology was consistent with a Schatzker V pattern; because no formal fracture-CT report was available, this classification is presented as a morphology-based interpretation rather than a reported diagnosis. The supplied film identifies the fracture-CT scanner listed in the Table of Materials; other acquisition parameters were illegible.
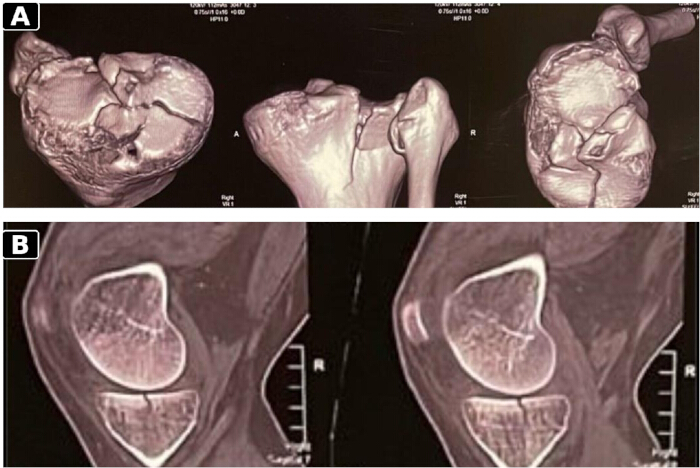
Figure 4: CT morphology of the bicondylar tibial plateau fracture. (A) Three-dimensional volume-rendered reconstruction demonstrates comminution and split-depression components involving both tibial plateaus. (B) The sagittal reformatted CT image also demonstrates comminution and split-depression components involving both tibial plateaus. The overall morphology is consistent with a Schatzker V pattern. No formal fracture-CT report was available; classification is morphology-based. Please click here to view a larger version of this figure.
The source narrative recorded open reduction and internal fixation. Postoperative anteroposterior (Figure 5A) and lateral (Figure 5B) radiographs confirmed plate-and-screw fixation, showing two plate constructs with multiple proximal subchondral rafting screws and maintained articular alignment. The operative note and implant identifiers were unavailable; no manufacturer or precise plate position could be inferred from the radiographic appearance.
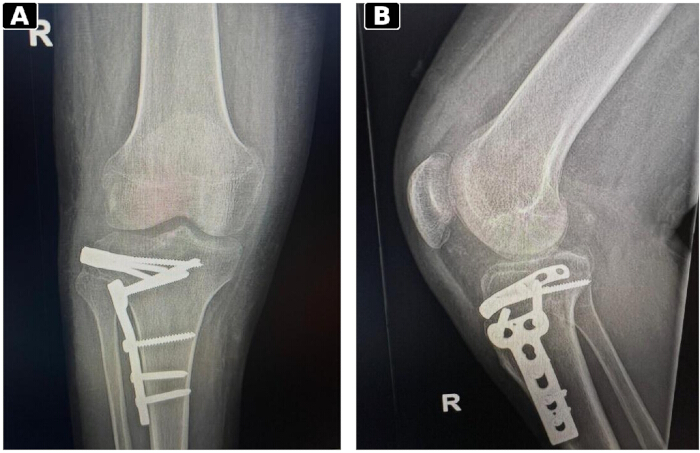
Figure 5: Postoperative right-knee radiographs. (A) The anteroposterior view shows two plate constructs with multiple proximal subchondral rafting screws and maintained articular alignment. (B) The lateral view also shows two plate constructs with multiple proximal subchondral rafting screws, maintaining articular alignment. The image date and implant manufacturer/system were not available; radiographic union is not claimed. Please click here to view a larger version of this figure.
Bone-health assessment
Metabolic laboratory testing collected on 8 January 2026 showed 25-hydroxyvitamin D 114.0 nmol/L, calcium 2.30 mmol/L, phosphate 1.16 mmol/L, magnesium 0.73 mmol/L, albumin 44 g/L, alkaline phosphatase 52 U/L, creatinine 81 µmol/L, and alanine aminotransferase 19 U/L, all within the reporting laboratory's displayed reference ranges. Complete blood count and glycated hemoglobin were not flagged as abnormal. Vitamin B12 was low at 104 pmol/L (displayed reference interval, 145-637 pmol/L). Parathyroid hormone, total or free testosterone, thyroid studies, celiac serology, urinary calcium, and bone-turnover markers were not available in the supplied record. The vitamin D assay was performed by electrochemiluminescence immunoassay.
DXA was performed on 5 February 2026 at age 45.2 years using the densitometry system listed in the Table of Materials. Height was 168.0 cm, and weight was 67.1 kg. The device reports that the total proximal-femur region is labeled as “total femur”; the standard densitometry term “total hip” is used here. Areal bone mineral density (BMD), T-score, and Z-score, respectively, were 1.048 g/cm2, −1.2, and −1.4 at L1–L4; 0.741 g/cm2, −2.1, and −2.1 at the left femoral neck; 0.685 g/cm2, −2.6, and −2.6 at the left total hip; 0.684 g/cm2, −2.5, and −2.5 at the right femoral neck; and 0.657 g/cm2, −2.8, and −2.8 at the right total hip. The lowest Z-score was therefore −2.8 at the right total hip.
For men younger than 50 years, Z-scores are preferred. A Z-score of −2.0 or lower is classified as “below the expected range for age,” and osteoporosis cannot be diagnosed from BMD alone in this age group10. The DXA findings were therefore interpreted as BMD below the expected range for the patient's age rather than as a T-score-only diagnosis of osteoporosis. In conjunction with the low-energy fracture and clinical history, the findings warranted specialist evaluation for secondary skeletal fragility. The available record did not document a verifiable bone-directed medication regimen.
Protocol
The following framework is intended for education and clinical reflection. It is not a validated protocol, and each decision should be individualized based on symptoms, imaging, comorbidities, fracture risk, and specialist judgment. This report describes the routine clinical care of a single patient and did not involve a prospective research intervention or experimental human-subject research protocol. Accordingly, formal ethics committee approval was not required for this single-patient case report. Written informed consent was obtained from the patient for publication of this case and the accompanying de-identified imaging. All the materials used in this study are listed in the Table of Materials.
1. Define the clinical context and risk
- The clinicians documented symptom chronology and mechanism, pain location and severity, rest or night pain, weight-bearing tolerance, and occupational or sporting load.
- The skeletal risk factors were identified, including IBD or other inflammatory disease, prior low-energy fracture, glucocorticoid exposure, low body mass, malnutrition or malabsorption, hypogonadism, smoking, reduced mobility, and bone-active medication exposure.
- The clinicians examined for effusion, focal osseous or joint-line tenderness, restricted motion, instability, quadriceps inhibition, and inability to bear weight. Preserved function did not exclude impaired bone strength.
2. Characterization of the imaging finding
- The clinicians obtained standard knee radiographs when clinically indicated. When symptoms were severe, atraumatic, or discordant with radiographs, the clinicians obtained an MRI with T1-weighted and fluid-sensitive sequences in multiple planes.
- The radiologists reported lesion location and extent and the presence or absence of a subchondral low-signal line, collapse, osteochondral defect, osteonecrosis, chondrosis, osteoarthritis, meniscal posterior-root injury, and meniscal extrusion2,3,4. The clinicians used descriptive terminology when the mechanism was uncertain.
- The clinicians used CT when cortical or articular characterization would change management. A normal radiograph or CT did not, by itself, exclude early trabecular injury.
- The report reserved “persistent marrow edema” for an abnormality demonstrated on serial imaging. Without repeat imaging, the report described persistent or worsening symptoms rather than a persistent signal.
3. Modify loading and reassess when concern persists
- The proposed framework included consideration of activity modification and protected weight-bearing when occult subchondral injury remained in the differential diagnosis.
- Protected weight-bearing refers to partial or otherwise limited weight bearing, usually with an appropriate assistive device. The degree and duration should reflect pain, weight-bearing tolerance, imaging, and overall risk2,11.
- Complete unloading refers to temporary non-weight-bearing and is more restrictive than protected weight-bearing.
- The proposed framework included consideration of complete unloading when pain was severe, weight bearing was not tolerated, or a structural injury was strongly suspected. It leaves the choice and duration to individualized clinical judgment and does not prescribe a fixed threshold or interval.
- The proposed framework called for prompt reassessment when pain worsened, weight-bearing tolerance declined, giving way developed, or the examination changed. Depending on the findings, options included specialist review, repeat MRI, or a change in load protection.
4. Individualize bone-health evaluation
- In IBD, the clinicians considered DXA when additional skeletal-risk factors were present, consistent with current risk-based guidance5.
- In men younger than 50 years, the clinicians reported Z-scores and areal BMD and avoided diagnosing osteoporosis from BMD alone10.
- The clinicians tailored the assessment for secondary causes to the clinical context. Common tests included complete blood count, renal and liver function tests, calcium and albumin, phosphate, alkaline phosphatase, 25-hydroxyvitamin D, parathyroid hormone, thyroid function tests, and morning testosterone12,13.
- After a low-energy fracture, the proposed framework called for a comprehensive fracture-risk and secondary-cause assessment. It specified individualized decisions regarding calcium and vitamin D management and any pharmacologic treatment according to age, fracture characteristics, laboratory findings, overall risk, contraindications, and current guidance5,12,13.
Results
The source narrative recorded open reduction and internal fixation. Available postoperative radiographs (Figure 5A and Figure 5B) confirmed plate-and-screw fixation with maintained reduction, but their metadata did not establish a reliable examination date, and they were not used to claim radiographic union. The source narrative described six weeks of non-weight-bearing, followed by graded rehabilitation; the underlying protocol documentation was unavailable for verification. Approximately three months after open reduction and internal fixation, the patient reported no knee pain and had resumed normal walking and usual function. Knee range of motion was full and painless. Exact goniometric measurements and validated patient-reported outcome scores were not available.
Subsequent laboratory and DXA assessment identified BMD below the expected range for age and a low vitamin B12 concentration. These findings warranted specialist evaluation for secondary skeletal fragility; the available record did not include a final etiologic diagnosis or a verifiable medication regimen. Clinical follow-up was limited to the three-month assessment. The exact follow-up date, formal return-to-work status, quantitative gait assessment, numerical range-of-motion measurements, validated outcome scores, longer-term complications, and radiographic union were unavailable. The favorable clinical outcome at three months is therefore reported independently of the undated postoperative radiographs and is not used to claim fracture union.
Discussion
This case illustrates why atraumatic marrow edema-like signal should remain a descriptive finding when its cause is uncertain. No trauma preceded symptom onset, yet the MRI report used the etiologic term “contusion.” Conversely, no subchondral fracture line or collapse was reported, so the study cannot be retrospectively reclassified as a proven subchondral insufficiency fracture. When pain worsens during loading and systemic skeletal risk factors are present, the combination may warrant proportionate load modification and planned diagnostic reassessment1,2,3.
The latter injury involved the bicondylar tibial plateau. The archived MRI report localized the earlier signal to the medial femoral condyle, whereas the limited coronal screenshots appear discordant with that localization and cannot establish the precise osseous epicenter. No serial MRI documented persistence, resolution, or evolution. Because the discrepancy cannot be resolved from the screenshots and no serial MRI was obtained, neither the identity of the initial lesion relative to the later fracture nor any anatomical or biomechanical progression can be established. Occult tibial microdamage at the earlier examination also cannot be excluded. The minor twisting movement appeared disproportionate to the severity of the fracture, but it does not establish a specific anatomical or biomechanical pathway. The case, therefore, demonstrates temporal association only.
Crohn disease and previous glucocorticoid exposure increased suspicion for impaired bone health, but cannot be assigned as the sole cause of the fracture. IBD populations have higher rates of low BMD and fracture, while individual risk varies with disease activity, nutrition, malabsorption, body composition, smoking, activity, and treatment exposure5,6,7. The later DXA provided objective evidence of BMD below the expected range for age. Vitamin D and measured mineral values were within the displayed reference ranges; low vitamin B12 may reflect nutritional context, but does not independently explain the fracture. The incomplete secondary-cause evaluation limits etiologic interpretation.
The practical implications are cautious. Marrow edema-like signal is not itself a diagnosis; preserved work capacity and a normal CT do not establish normal bone strength; and worsening symptoms during rehabilitation should prompt reconsideration of both the working diagnosis and the loading plan. Reviews of subchondral insufficiency fracture support load protection in selected patients, but its degree and duration are individualized2,11. Likewise, IBD supports risk assessment rather than universal DXA or treatment5. The proposed framework is therefore a teaching aid, not a prescriptive pathway.
This retrospective single-patient report cannot establish incidence, prediction, or causality. Important limitations include unavailable full MRI DICOM data and acquisition parameters, unresolved MRI report–image localization, no serial MRI, an unrecoverable date for the supplied prefracture radiographs, no formal fracture-CT report, incomplete rehabilitation and operative records, unavailable implant identifiers and postoperative radiograph dates, incomplete laboratory evaluation for secondary skeletal fragility, and follow-up limited to three months without quantitative motion, validated outcome scores, formal return-to-work status, longer-term complication data, or verified radiographic union. A formal patient perspective was also unavailable. Prospective studies are needed before standardized reassessment or loading pathways can be recommended.
In this patient with Crohn disease and previous glucocorticoid exposure, an atraumatic knee marrow edema-like MRI finding was followed approximately eight weeks later by a low-energy bicondylar tibial plateau fracture. Subsequent DXA documented BMD below the expected range for age, raising concern for underlying skeletal fragility. The case does not establish direct anatomical progression or causality. Worsening pain during loading may warrant reconsideration of the diagnosis and rehabilitation plan, proportionate load modification, and individualized bone-health assessment.
Disclosures
The author declares no conflicts of interest related to this report.
Acknowledgements
No external funding was received. A formal patient-perspective statement was not available in the retrospective record.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Aquilion Start computed tomography system | Canon Medical Systems; supplied film bears legacy Toshiba Medical Systems branding | Unit-specific catalog number not available https://global.medical.canon/products/computed-tomography/aquilion-start/ | Used for the fracture-episode CT after the low-energy bicondylar tibial plateau fracture. The supplied film identifies an Aquilion Start system; other acquisition parameters were not reliably legible. |
| cobas e 801 immunoassay analyzer | Roche Diagnostics | 08454345001 https://diagnostics.roche.com/global/en/products/instruments/cobas-e-801-ins-2202.html | Used for the 25-hydroxyvitamin D electrochemiluminescence immunoassay reported on 8 January 2026. The specific assay reagent/kit catalog number was not available in the supplied record. |
| Computed tomography system (prefracture right-knee CT) | Not retrievable from retrospective source record | Not retrievable | Noncontrast right-knee CT acquired 28 August 2025. Displayed reconstruction thickness was 2.00 mm. Manufacturer/model were not recoverable. The Aquilion Start fracture-CT system must not be assigned to this earlier examination. |
| Lunar Prodigy Advance DXA system | GE Healthcare | Unit-specific catalog number not available https://www.gehealthcare.com/en-us/products/bone-and-metabolic-health/prodigy | DXA performed 5 February 2026. Used to report areal BMD, T-scores, and Z-scores at L1-L4 and the bilateral proximal femur/total hip regions. The source record identified the Lunar Prodigy Advance system; a unit-specific catalog number was not available. |
| Magnetic resonance imaging system (prefracture right-knee MRI) | Not retrievable from retrospective source record | Not retrievable | Outside noncontrast multiplanar, multisequence right-knee MRI acquired 28 July 2025. The full DICOM study was unavailable. The only retrievable PACS series label was Tra_PD_SPIR (24 images), but it could not be assigned to the published coronal panels. Scanner manufacturer/model, field strength, coil, exact sequence, and acquisition parameters were not recoverable. |
| Orthopedic fixation system (tibial plateau ORIF) | Not retrievable from retrospective source record | Not retrievable | The source narrative recorded open reduction and internal fixation. Postoperative radiographs show two plate constructs with multiple proximal subchondral rafting screws. The operative note and implant identifiers were unavailable; manufacturer/system and precise plate position were not inferred from radiographic appearance. |
References
- Villari E, et al. Bone marrow edema of the knee: a narrative review. Arch Orthop Trauma Surg. 2024;144(5):2305-2316.
- Ochi J, et al. Subchondral insufficiency fracture of the knee: review of current concepts and radiological differential diagnoses. Jpn J Radiol. 2022;40(5):443-457.
- Malghem J, et al. Subchondral insufficiency fractures, subchondral insufficiency fractures with osteonecrosis, and other apparently spontaneous subchondral bone lesions of the knee—pathogenesis and diagnosis at imaging. Insights Imaging. 2023;14(1):164.
- Clark SC, et al. High incidence of medial meniscus root/radial tears and extrusion in 253 patients with subchondral insufficiency fractures of the knee. Knee Surg Sports Traumatol Arthrosc. 2024;32(11):2755-2761.
- Gordon H, et al. ECCO Guidelines on Extraintestinal Manifestations in Inflammatory Bowel Disease. J Crohns Colitis. 2024;18(1):1-37.
- Marzban Abbas Abadi M, Emadian ST, Zamani M, Khalilizad M. Prevalence of osteoporosis in patients with inflammatory bowel disease: a systematic review and meta-analysis. J Health Popul Nutr. 2025;44(1):178.
- Szafors P, et al. Risk of fracture and low bone mineral density in adults with inflammatory bowel diseases: a systematic literature review with meta-analysis. Osteoporos Int. 2018;29(11):2389-2397.
- Gagnier JJ, et al. The CARE guidelines: consensus-based clinical case reporting guideline development. J Clin Epidemiol. 2014;67(1):46-51.
- Riley DS, et al. CARE guidelines for case reports: explanation and elaboration document. J Clin Epidemiol. 2017;89:218-235.
- International Society for Clinical Densitometry. 2023 ISCD Official Positions—Adult. Middletown (CT): International Society for Clinical Densitometry; 2023.
- Wang Z, et al. Subchondral insufficiency fracture of the knee: progress in the pathogenesis and treatment. Front Surg. 2025;12:1640316.
- Fuggle NR, et al. Evidence-based guideline for the management of osteoporosis in men. Nat Rev Rheumatol. 2024;20(4):241-251.
- Adler RA. Osteoporosis in men. In: Feingold KR, Adler RA, Ahmed SF, et al., editors. Endotext. South Dartmouth (MA): MDText.com, Inc.; 2000-. Updated 2024 Mar 26.