This study applied data-mining approaches to characterize Chinese herbal medicine prescribing patterns for acute exacerbation of idiopathic pulmonary fibrosis (AE-IPF). Based on 84 prescriptions from Professor Xu Zhiying’s clinical practice, high-frequency herbs, core combinations, and potential formulas were identified, providing structured insights for future clinical and experimental validation.
Research Article
Analysis of Prescription Medication Rules of Chinese Herbal Medicine for Acute Exacerbation of Idiopathic Pulmonary Fibrosis Based on Data Mining
In This Article
Summary
Abstract
Acute exacerbation of idiopathic pulmonary fibrosis (AE-IPF) is a life-threatening complication with limited effective therapeutic options and high mortality. Although Chinese herbal medicine is increasingly used as an adjunctive approach, the prescribing patterns and potential therapeutic principles of experienced traditional Chinese medicine practitioners for AE-IPF remain insufficiently characterized. This study aimed to characterize the prescription patterns of Chinese herbal medicine used by Professor Xu Zhiying for acute exacerbation of idiopathic pulmonary fibrosis (AE-IPF) using data-mining techniques. Medical records of patients diagnosed with AE-IPF treated at Zhejiang Provincial Hospital of Traditional Chinese Medicine from September 2019 to December 2020 were retrospectively reviewed. A total of 84 prescriptions from 42 patients were collected and entered into the Traditional Chinese Medicine Inheritance and Computing Platform. Prescription characteristics were analyzed using frequency analysis, association rule mining, and entropy hierarchical clustering. Among 112 identified herbal medicines, the cumulative frequency reached 3,004, and 22 herbs were used more than 50 times. The most frequently used herbs included Radix Scutellariae, Bulbus Fritillariae Thunbergii Miq., Pinellia ternata, Forsythia suspensa, Radix et Rhizoma Salviae Miltiorrhizae, and Magnolia officinalis. The dominant meridian distributions involved the lung, stomach, spleen, liver, and large intestine meridians. Association rule analysis identified 11 core herb combinations with support values ranging from 50 to 84, confidence values ranging from 0.82 to 1.00, and lift values greater than 1, indicating stable positive associations among herbal combinations. Entropy hierarchical clustering further generated four candidate formulas characterized by heat-clearing, phlegm-resolving, toxin-removing, and spleen-supporting effects. This study systematically characterized expert prescribing patterns for AE-IPF and provides hypotheses for subsequent clinical and experimental validation.
Introduction
Idiopathic pulmonary fibrosis (IPF) is the most common type of idiopathic interstitial pneumonia. This progressive, irreversible fibrotic lung disorder is driven by epithelial injury, fibroblast activation, and excessive extracellular matrix deposition, ultimately resulting in declining pulmonary function and respiratory failure1. Despite advances in antifibrotic therapies, including pirfenidone and nintedanib, the clinical prognosis of IPF remains poor, particularly among patients experiencing acute exacerbation of IPF (AE-IPF), which represents a devastating clinical event with rapid deterioration and high mortality. Its clinical manifestations include progressive dyspnea and a decline in lung function, among others2. Currently, the occurrence rate of IPF is increasing, with a global annual incidence ranging from 0.2 to 93.7 per 100,000 people3. During AE-IPF, there is a rapid intensification of inflammatory response, involving excessive apoptosis of alveolar epithelial cells, neutrophilic inflammation, and abnormal activation of cytokines such as IL-23 and IL-17A4, often leading to death due to respiratory failure, with a mortality rate as high as 50%5. However, current therapeutic strategies for AE-IPF remain insufficient. Although corticosteroids are widely used in clinical practice, their efficacy is controversial, and immunosuppressive treatment may be accompanied by considerable adverse effects6,7. Moreover, no standardized pharmacological intervention has been established to effectively prevent disease progression or improve survival during AE-IPF episodes. Therefore, identifying novel therapeutic strategies with multi-target regulatory potential has become an important research priority.
In the long-term clinical management of IPF, traditional Chinese medicine (TCM) has been increasingly investigated as a complementary therapeutic approach. According to TCM theory, the core pathogenesis of IPF is obstruction of the lung collaterals. AE-IPF often manifests as patterns such as turbid phlegm obstructing the lung, phlegm-heat interbinding, or dual deficiency of Qi and Yin8,9. Increasing evidence suggests that compound Chinese herbal formulas based on syndrome differentiation may regulate inflammatory responses, oxidative stress, immune imbalance, and fibrotic progression through multi-component and multi-target mechanisms. Several clinical and experimental studies have indicated potential benefits of Chinese herbal medicine in improving respiratory symptoms and delaying pulmonary fibrosis progression. However, most previous studies have focused on stable-stage IPF, whereas therapeutic principles and prescription characteristics specifically targeting AE-IPF remain insufficiently investigated. Combinations of tonifying herbs (such as Astragalus membranaceus), phlegm-resolving herbs (such as Bulbus Fritillariae Thunbergii Miq.), and heat-clearing herbs (such as Radix Scutellariae) can significantly alleviate clinical symptoms in IPF patients10,11. Nevertheless, several important knowledge gaps remain. First, existing studies of Chinese herbal medicine for IPF mainly focus on chronic disease management, while systematic investigations targeting the acute exacerbation phase are limited. Second, traditional clinical experience is often transmitted through individual case reports or expert consensus, and objective approaches for identifying prescription patterns and core herbal combinations are still lacking. Third, the potential medication principles and candidate formulas used by experienced clinicians for AE-IPF have not been sufficiently characterized using modern analytical approaches. Current evidence is predominantly centered on the stable phase of IPF, with a lack of systematic exploration into syndrome differentiation patterns, medication principles, and mechanisms of action during AE-IPF12. Furthermore, the inheritance of traditional empirical formulas often relies on case summaries, and large-sample data mining analyses are scarce, which hinders the standardization and promotion of TCM experience13,14.
Professor Xu Zhiying, a senior respiratory medicine specialist at Zhejiang Provincial Hospital of Traditional Chinese Medicine, has accumulated long-term clinical experience in the syndrome differentiation and prescription management of interstitial lung diseases, including IPF and AE-IPF11. His therapeutic approach integrates traditional TCM theories, such as phlegm-heat obstructing the lung and lung collateral obstruction, with individualized clinical decision-making. Previous studies have reported that prescription experiences of experienced TCM practitioners may provide valuable insights into the standardization and inheritance of complex herbal treatment strategies through data-mining approaches. However, the present study does not aim to establish Professor Xu’s prescriptions as universal therapeutic rules or confirm clinical efficacy, but rather to systematically characterize his prescription patterns as a representative clinical experience for hypothesis generation and future validation. Data mining (DM) methods provide a systematic approach for analyzing complex clinical prescription datasets and extracting hidden therapeutic patterns11. Through association rule analysis, clustering algorithms, and network visualization, DM methods can identify high-frequency herbs, core combinations, and potential novel formulas, thereby facilitating the transformation of empirical clinical knowledge into structured and evidence-oriented therapeutic strategies13,14. Therefore, this study aimed to systematically characterize the prescription patterns of Chinese herbal medicine used by Professor Xu Zhiying for AE-IPF based on data-mining techniques. Specifically, this study focused on identifying frequently used herbs, association patterns, and potential formula combinations rather than evaluating therapeutic efficacy. The findings were intended to provide structured information regarding expert clinical experience and generate hypotheses for subsequent clinical and experimental validation. We hypothesized that data mining analysis could reveal consistent prescription characteristics, identify core herbal combinations, and provide potential candidate formulas reflecting the therapeutic principles of AE-IPF management. The novelty of this study lies in its focus on the acute exacerbation phase of IPF, the integration of large-scale clinical prescription data with modern analytical approaches, and the systematic identification of medication rules from the experience of an expert clinician. These findings may provide structured information regarding prescription characteristics and support future clinical and experimental validation studies.
Protocol
This study was approved by the Ethics Committee of the First Affiliated Hospital of Zhejiang Chinese Medical University (Approval No. 2020-KL-072-01). Due to the retrospective nature of the study and the use of existing medical records, informed consent was waived. Patient confidentiality was maintained throughout data extraction and analysis, and only de-identified information was used for research purposes.
Data source
Medical records of patients diagnosed with AE-IPF treated by Professor Xu at Zhejiang Provincial Hospital of Traditional Chinese Medicine from September 2019 to December 2020 were retrospectively reviewed. A total of 96 patients with AE-IPF were initially screened. After applying the predefined inclusion and exclusion criteria, 42 eligible patients were included, and 84 complete Chinese herbal medicine prescriptions were obtained for subsequent data mining analysis. The 84 prescriptions were derived from 42 patients, with each prescription representing an independent clinical adjustment based on syndrome differentiation and reflecting real-world prescribing decisions during the AE-IPF treatment period. Each prescription was considered as an independent analytical unit, and all prescriptions were derived from real-world clinical practice during the acute exacerbation phase. Diagnostic Criteria: The diagnosis of AE-IPF was established based on the diagnostic criteria for interstitial lung diseases issued by the European Respiratory Society (ERS) and the American Thoracic Society (ATS) in 201815, as well as the Chinese Expert Consensus on the Diagnosis and Treatment of Acute Exacerbation of Idiopathic Pulmonary Fibrosis formulated by the Interstitial Lung Disease Group of the Chinese Thoracic Society16. Inclusion criteria includes: meeting the diagnostic criteria for IPF and being in the acute exacerbation phase; fulfilling the diagnostic criteria for AE-IPF according to Professor Xu’s staging theory for IPF treatment, with TCM syndrome differentiation identified as phlegm-heat obstructing the lung or phlegm-dampness obstructing the lung; experiencing typical respiratory worsening or acute deterioration within one month; high-resolution computed tomography (HRCT) revealing new ground-glass opacities or consolidations superimposed on pre-existing reticulations or honeycombing; absence of confirmed pulmonary infection. Exclusion criteria includes patients with severe primary diseases such as cardiovascular and cerebrovascular disorders, hematopoietic system diseases, or psychiatric illnesses; patients complicated with pulmonary heart disease or respiratory failure; pregnant or lactating women, and those with known allergy to any component of the trial medication; patients with poor compliance (inability to undergo treatment as required, or voluntary discontinuation of treatment).
As this was a retrospective observational study based on existing medical records, randomization and blinding were not applicable. The study design focused on identifying prescription patterns rather than evaluating treatment efficacy. Therefore, clinical outcomes such as symptom improvement rate, hospitalization duration, predefined endpoints and were not analyzed in this data-mining study.
Standardization of Chinese Herbal Medicine Nomenclature
The nomenclature of herbal medicines was standardized according to the Chinese Pharmacopoeia (2015 Edition)17 and the second edition of Chinese Materia Medica (New Century Edition)18. Each herb was converted into a unified coded format before statistical analysis. Different synonyms, processing forms, and regional naming variations referring to the same medicinal material were merged into a single standardized entry. The final standardized dataset was independently reviewed by two researchers before being imported into the analysis platform. Medicinal materials without specified processing methods-such as white peony root, white atractylodes rhizome, and Ephedra-were recorded in their raw form. For herbs with multiple names that do not affect their efficacy or indications, a unified naming standard was applied.
Prescription entry and verification
The screened medications were entered into a computerize traditional chinese medicine inheritance and prescription analysis platform for subsequent data-mining analysis. To ensure completeness and accuracy, a standardized data management procedure was implemented. Two independent researchers performed data extraction and entry separately, and discrepancies were reviewed and resolved by a senior clinician with more than 15 years of experience in respiratory medicine and TCM practice. The extracted prescription information was cross-checked against the original electronic medical records. Records with incomplete prescription components, unclear herb names, or inconsistent medication information were excluded before analysis. Medication prescribing patterns were explored using the medical case analysis and prescription analysis functions of the data-mining platform.
Data mining workflow and outcome assessment
The overall analytical workflow consisted of four sequential steps. First, standardized prescription data were imported into the computerized traditional Chinese medicine data-mining platform. Second, frequency analysis was performed to identify commonly used herbs, with herb frequency and cumulative application frequency considered the primary outcome measures. Third, association rule analysis based on the Apriori algorithm was conducted to identify core herb combinations, using support and confidence values as quantitative evaluation indicators. Finally, entropy-based clustering analysis was performed to generate potential novel formulas, and the extracted combinations were interpreted according to TCM theory and previous pharmacological evidence.
Because this study aimed to identify prescription patterns rather than compare intervention effects, conventional hypothesis-testing statistics were not applicable. Descriptive statistical analyses were performed to summarize herb frequencies and therapeutic categories. The robustness of association rules was assessed using multiple quantitative indicators, including support, confidence, and lift. Support reflected the frequency of occurrence of herb combinations, confidence represented the conditional probability between associated herbs, and lift values greater than 1 indicated positive correlations beyond random co-occurrence. These quantitative parameters were used to evaluate the strength and reliability of identified prescription patterns. Association strength was quantitatively evaluated using support, confidence, and lift values, while entropy-based clustering parameters were used to identify potential formula combinations.
Herbal frequency analysis
Herb frequency was defined as the cumulative occurrence count of each herb across all 84 prescriptions. Frequency analysis was performed using Excel PivotChart to rank herbs by their total occurrences, and herbs with the highest frequencies were compiled into a high-frequency list. Based on these frequency results, we further analyzed the medicinal properties of the herbs, including the four natures (cold, hot, warm, cool), five flavors (sour, bitter, sweet, pungent, salty), and meridian tropism (e.g., lung, spleen meridians), to summarize the overall prescription characteristics and compatibility principles from the perspective of TCM property theory.
Analysis of prescription medication rules
Association rule analysis was performed using the Apriori algorithm in IBM SPSS Modeler software. Each prescription was treated as a “transaction” and each herb as an “item.” High-frequency drug combinations and their internal relationships were explored through complex network analysis. The core parameters were predefined before analysis. The minimum support threshold was set to 50 prescriptions, ensuring that only frequently observed herb combinations were retained. Because the dataset comprised 84 prescriptions, the absolute support frequency could not exceed 84 occurrences. The confidence threshold was set to 0.8, meaning that when herb A appeared, the probability of herb B co-occurrence exceeded 80%, thereby ensuring the reliability of the extracted association rules. However, because confidence is asymmetric and may be influenced by the baseline frequency of the consequent herb, lift values were additionally calculated to determine whether the observed co-occurrence exceeded random expectations. A lift value greater than 1 indicated a positive association, a value equal to 1 indicated independence, and a value less than 1 indicated a negative association. Rules meeting the criteria of support ≥50, confidence ≥0.80, and lift >1 were considered meaningful and retained for interpretation. The retained rules were exported and ranked by support, confidence, and lift values to systematically summarize the core herb combinations and potential compatibility patterns for AE-IPF.
Novel formula analysis
Subsequently, a novel formula analysis was conducted using the complex system entropy clustering method. This analysis was performed using the computerized traditional Chinese medicine data-mining platform. First, using the previously constructed formula–herb data matrix, we set the correlation degree to 8 to control the number and cohesiveness of core herb combinations, and the penalty degree to 2 to constrain association strength, thereby ensuring clinical rationality of the extracted combinations. After parameter configuration, the “Extract Combinations” function in the software was applied to automatically identify implicit, highly correlated core combinations among herbs, based on the improved mutual information method and complex entropy clustering algorithm. The platform then further clustered and integrated these core combinations to ultimately generate potential novel formulas for the treatment of AE-IPF. The reliability of the extracted core combinations and candidate formulas was further evaluated through three approaches: consistency assessment with high-frequency herb results; comparison with classical TCM therapeutic principles for AE-IPF; and interpretation based on previously reported pharmacological mechanisms of representative herbs. These procedures were used as internal validation approaches to improve the clinical interpretability of the identified prescription patterns.
Results
Herbal frequency analysis
A total of 112 kinds of herbs were identified from the same analytical dataset consisting of 84 TCM prescriptions derived from 42 AE-IPF patients. Frequency analysis was performed on this dataset to characterize the overall distribution and recurrence patterns of herbal use. Among the 112 identified herbal medicines, 22 herbs were used more than 50 times. The seven most frequently used herbs, including Radix Scutellariae, Bulbus Fritillariae Thunbergii Miq., Pinellia ternata, Forsythia suspensa, Radix et Rhizoma Salviae Miltiorrhizae, Magnolia officinalis, and Platycodon grandifloras, were used more than 100 times. The complete frequency distribution of all high-frequency herbs is presented in Table 1.
Herbal frequency analysis
Based on their therapeutic functions, the 112 herbal medicines were classified into different categories, including tonifying deficiency herbs, phlegm-resolving and cough-suppressing herbs, heat-clearing herbs, blood-activating and stasis-dispelling herbs, dampness-resolving herbs, and qi-regulating herbs. The distribution and cumulative frequency of each therapeutic category are summarized in Table 2, demonstrating the dominant pharmacological characteristics of the prescriptions.
Statistical analysis of medicinal properties
The four natures and channel tropisms of the Chinese medicines in the prescriptions were statistically analyzed. As shown in Figure 1A, cold-natured herbs represented the predominant category (59%), followed by cool (13%), warm (12%), hot (8%), and neutral (8%) properties. The distribution of meridian tropisms is shown in Figure 1B, with the lung, stomach, spleen, liver, large intestine, and heart meridians being the most frequently involved. Among the four natures, cold was the most frequent, followed by cold (59%), hot (8%), neutral (8%), cool (13%), and warm (12%) (Figure 1A). The top six meridians were the lung meridian (1,650), stomach meridian (1,218), spleen meridian (1,112), liver meridian (1,109), large intestine meridian (1,012), and heart meridian (910) (Figure 1B).
Analysis of prescription patterns
The same standardized dataset of 84 prescriptions from 42 AE-IPF patients used for frequency analysis was further analyzed using association rule mining to identify recurrent herb combinations and compatibility patterns. Using the prescription pattern analysis function, with the minimum occurrence frequency set to 50, confidence level set to 0.8, and lift value incorporated as an additional association-strength indicator, 11 commonly used herbal combinations were identified. The extracted association rules demonstrated high occurrence stability, with occurrence frequencies ranging from 50 to 84, confidence values ranging from 0.82 to 1.00, and lift values ranging from 1.05 to 1.32. All retained rules showed lift values greater than 1, indicating that the observed herb co-occurrences were stronger than expected under independent occurrence assumptions and represented positive association patterns rather than simple frequency-driven combinations. All retained association rules met the predefined criteria, indicating stable and non-random co-occurrence relationships among the identified herb combinations.
During the association-rule mining process, combinations with support values below 50 prescriptions, confidence values below 0.80, or lift values ≤1 were excluded because they represented relatively infrequent or statistically unstable co-occurrence patterns. Although these excluded combinations may reflect individualized prescribing preferences, they were not considered sufficiently reproducible for defining core prescription patterns within this dataset.
The identified association rules were further visualized using network analysis (Figure 2), which demonstrated the relationships among frequently co-occurring herbs. The detailed association combinations and their occurrence frequencies are summarized in Table 3. These results revealed stable compatibility patterns among core herbs used for AE-IPF management. The core herbal composition for treating IPF acute exacerbation was determined as: Radix Scutellariae, Bulbus Fritillariae Thunbergii, Cortex Mori, Radix et Rhizoma Salviae Miltiorrhizae, Flos Lonicerae Japonicae, Forsythia suspensa, and Coicis Semen.
Analysis of novel formula
Using the entropy-based hierarchical clustering method integrated within the software, the correlation coefficient was s experimental validation.et to 8 and the penalty coefficient to 2. Using the same dataset of 84 prescriptions from 42 AE-IPF patients, entropy-based hierarchical clustering generated 68 preliminary clustering results related to AE-IPF treatment patterns. From these clustering results, eight potential herbal combinations were extracted and assembled (Table 4), whereas other low-frequency or poorly cohesive clusters were discarded because they lacked sufficient internal correlation or clinical interpretability. Based on these combinations, four candidate formulas were subsequently generated through entropy hierarchical clustering analysis (Table 5). These candidate formulas represented potential therapeutic patterns characterized by heat-clearing, phlegm-resolving, toxin-removing, and spleen-supporting effects, including Rhizoma Fagopyri Dibotryis-Radix Scutellariae-Poria, Radix Scutellariae-Herba Erodii Stephaniani-Cortex Mori, Cortex Mori-Flos Lonicerae Japonicae-Semen Coicis, Root of Yangmei Actinidia-Gnaphalium affine-Houttuynia cordata, Rhizoma Fagopyri Dibotryis-Poria-Phragmites rhizome, Rhizoma Fagopyri Dibotryis-Radix Scutellariae-Herba Erodii Stephaniani, Semen Coicis-Meretricis Concha-Bulbus Fritillariae Thunbergii, and Houttuynia cordata- Arctium lappa Fruit- Root of Yangmei Actinidia (Table 4). These combinations can be formulated into four novel prescriptions for the treatment of AE-IPF, including Rhizoma Fagopyri Dibotryis-Radix Scutellariae-Poria-Phragmites rhizome, Rhizoma Fagopyri Dibotryis-Radix Scutellariae-Herba Erodii Stephaniani-Cortex Mori, Cortex Mori-Flos Lonicerae Japonicae-Semen Coicis-Meretricis Concha-Bulbus Fritillariae Thunbergii, and Root of Yangmei Actinidia-Gnaphalium affine- Houttuynia cordata-Arctium lappa Fruit (Table 5).
Summary of data-mining findings and workflow reliability
Collectively, all analyses were performed using the same standardized dataset comprising 84 prescriptions from 42 AE-IPF patients. Frequency analysis identified consistent high-frequency herbs, association rule mining further confirmed stable herb compatibility patterns, and entropy-based hierarchical clustering generated candidate formulas based on these recurrent combinations. The concordance among these three analytical approaches supports the reliability of the data-mining workflow and indicates that the identified patterns were not solely driven by individual high-frequency herbs but reflected broader prescription structures. These findings support our hypothesis that data-mining approaches can reveal reproducible prescribing characteristics, core herbal combinations, and potential formula patterns in AE-IPF management. However, the extracted combinations should be interpreted as hypothesis-generating patterns rather than validated therapeutic regimens, and further clinical and experimental validation is required.
DATA AVAILABILITY:
The datasets generated and analyzed during the current study include de-identified prescription records and clinical information from patients with acute exacerbation of idiopathic pulmonary fibrosis (AE-IPF). The original clinical records were deposited in a public repository (https://doi.org/10.5281/zenodo.21661675). The de-identified data required to reproduce the data-mining analyses, including standardized prescription records, herb-frequency information, association-rule inputs, and clustering analysis datasets, have been provided as Supplementary File 1. These data include the core analytical dataset used for frequency analysis, association rule mining, and entropy-based hierarchical clustering.
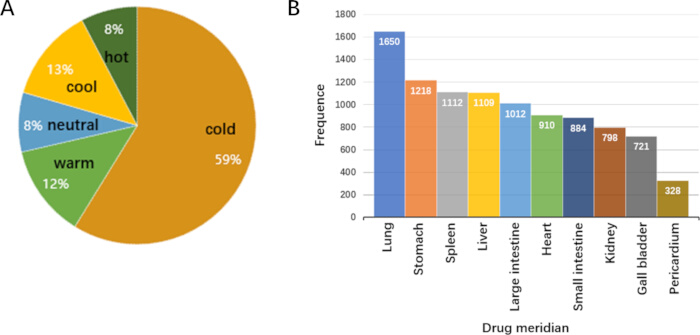
Figure 1: Distribution of herbal medicinal properties in the AE-IPF prescriptions. (A) Distribution of medicinal nature categories (cold, cool, warm, hot, neutral). (B) Frequency of meridian tropisms across all prescriptions. Please click here to view a larger version of this figure.
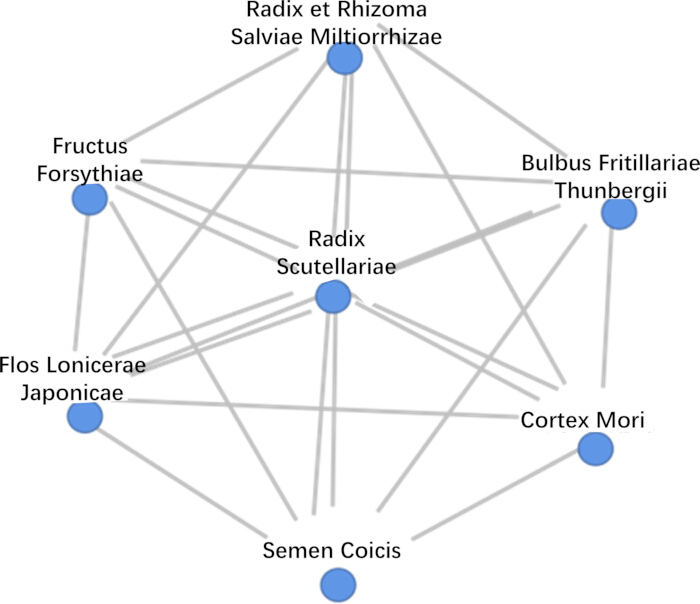
Figure 2. Network visualization of association rules among high-frequency herbs.
Nodes represent individual herbs, and edges represent co-occurrence relationships identified by association rule mining. Node size is proportional to the frequency of herb occurrence across the analyzed prescriptions, with larger nodes indicating herbs with higher application frequencies. Edge thickness represents the strength of association between herbs based on support values derived from association rule analysis. The network was constructed as a weighted network, with quantitative information reflected by node frequency and edge strength. Please click here to view a larger version of this figure.
Table 1: Frequency distribution of high-frequency Chinese herbal medicines (frequency ≥50) in 84 AE-IPF prescriptions. AE-IPF, acute exacerbation of idiopathic pulmonary fibrosis. The table presents Chinese herbal medicines identified from 84 prescriptions, with a frequency threshold of ≥50 occurrences. “Number” represents the cumulative occurrence count of each herb across all prescriptions, and “Frequency” represents the proportion of each herb occurrence relative to the total number of herb applications (expressed as a percentage). Herbs are ranked according to their occurrence frequency. Please click here to download this Table.
Table 2: Classification and cumulative frequency of herbal medicines by therapeutic function category. Herbal medicines were classified according to their traditional therapeutic functions based on standardized Chinese materia medica terminology. “Number” indicates the cumulative occurrence count of herbs within each therapeutic category, and “Occurrence frequency” represents the proportion of occurrences contributed by each category among all recorded herb applications. Common herbs are listed with their corresponding occurrence counts. Multiple therapeutic categories may overlap because individual herbs may possess more than one traditional function. Please click here to download this Table.
Table 3: Association rules for core herb combinations identified by Apriori algorithm (support ≥ 50, confidence ≥ 0.8, lift > 1). Association rules were generated using the Apriori algorithm. Support indicates the number of prescriptions containing the corresponding herb combination. Confidence represents the conditional probability that the consequent herb(s) appear when the antecedent herb(s) are present. Lift indicates the strength of association beyond random co-occurrence, with values >1 representing positive associations. Only rules meeting the predefined criteria of support ≥50, confidence ≥0.80, and lift >1 were retained. Please click here to download this Table.
Table 4: Potential core herb combinations extracted by entropy-based hierarchical clustering. Potential core herb combinations were identified using entropy-based hierarchical clustering analysis from standardized prescription data. The extracted combinations represent frequently associated herbal patterns generated by the clustering algorithm and are presented as candidate compatibility relationships rather than validated therapeutic formulas. Please click here to download this Table.
Table 5: Four candidate novel formulas generated by entropy-based clustering analysis. Candidate formulas were generated by integrating potential core herb combinations identified through entropy-based hierarchical clustering analysis. These formulas represent computationally derived prescription patterns reflecting potential therapeutic principles and require further clinical and experimental validation. Please click here to download this Table.
Supplementary File 1: Raw data. The de-identified data required to reproduce the data-mining analyses, including standardized prescription records, herb-frequency information, association-rule inputs, and clustering analysis datasets.Please click here to download this file.
Discussion
IPF is a chronic, progressive fibrotic lung disease and a refractory condition of the respiratory system. It is primarily caused by abnormal lung tissue structure and deposition of extracellular matrix in the lungs19. Patients with IPF often present with typical features such as chronic inflammation, decreased pulmonary function, and pulmonary fibrosis20. Through data-mining methods, this study characterized Dr. Xu's prescribing patterns and identified frequently used herbs, core herbal combinations, and potential candidate formulas for AE-IPF.
It should be emphasized that the 84 prescriptions analyzed in this study represent real-world clinical prescribing records rather than evidence of treatment efficacy. The value of these prescriptions lies in their ability to reflect repeated clinical decision-making patterns of an experienced practitioner during AE-IPF management. Therefore, the extracted herb combinations should be interpreted as potential prescribing characteristics and research hypotheses rather than validated therapeutic regimens.
In the present study, the support and confidence thresholds were predefined based on both methodological considerations and the characteristics of the prescription dataset. Because the analysis involved 84 clinical prescriptions containing multiple herbs, a support threshold of 50 was selected to ensure that extracted combinations represented highly recurrent compatibility patterns rather than occasional co-occurrences. A confidence threshold of 0.8 was chosen to identify reliable associations with a high probability of herb coexistence. Nevertheless, confidence alone cannot determine whether an association is truly meaningful because it may be affected by the overall frequency of the consequent herb. Therefore, lift values were incorporated to evaluate whether the observed co-occurrence exceeded the probability expected by chance. The combination of support, confidence, and lift provided a more comprehensive assessment of association strength and improved the interpretability and reproducibility of the identified prescription patterns. Although different threshold settings may influence the number of extracted rules, these criteria allowed the identification of clinically meaningful and reproducible core combinations. Future studies involving larger datasets may further explore parameter optimization through sensitivity analyses.
In practical applications of prescription data mining, several analytical challenges should also be considered. Parameter selection, such as support, confidence, and lift thresholds in association rule analysis, may influence the number and strength of extracted rules. Excessively strict thresholds may exclude clinically meaningful but less frequent combinations, whereas overly relaxed thresholds may generate unstable or spurious associations. These issues can be recognized by evaluating the consistency of extracted patterns across different parameter settings and addressed through sensitivity analyses. In addition, data quality and preprocessing procedures, including incomplete prescription records, inconsistent herb nomenclature, and variations in processing methods, may affect analytical reliability. In the present study, these potential sources of bias were minimized through standardized herb nomenclature, merging synonymous medicinal materials, independent data verification by two researchers, and cross-checking with original medical records. Future multicenter datasets with standardized data collection protocols may further improve the robustness and reproducibility of prescription pattern analyses.
The top 22 herbs used are identified more than 50 times, suggesting concentrated therapeutic patterns. Most of the herbs, such as Radix Scutellariae, Bulbus Fritillariae Thunbergii, Forsythia suspensa, and Radix et Rhizoma Salviae Miltiorrhizae, are cold or cool, consistent with the predominating phlegm-heat pattern and excess heat also discussed in authoritative articles in regard to AE-IPF21,22,23,24,25. This assertion is supported further by the extensive clinical TCM literature stating that AE-IPF typically presents as heat accumulation and phlegm obstruction, blocking the lung, rendering compromised lung Qi dynamics.
The primary flavors of the herbs-bitter, sweet, and pungent-each serve their function of clearing heat, resolving phlegm, tonifying supports spleen, and moving lung Qi26,27,28. These functions represent some of the pathological processes observed in AE-IPF airflow inflammation, mucus hypersecretion, and oxidative stress response.
Association-rule clustering identified Radix Scutellariae, Bulbus Fritillariae Thunbergii, Cortex Mori, Radix et Rhizoma Salviae Miltiorrhizae, Flos Lonicerae Japonicae, Forsythia suspensa, and Semen Coicis as a main herbal cluster. The cluster of herbs is indicative of the principle of clearing heat, resolving phlegm, moving stasis, and detoxifying, consistent with principles established in other data-mining studies of pulmonary inflammatory disorders25,26,27,28,29.
Modern pharmacological evidence supports the therapeutic logic of the herbs. Baicalin, derived from Radix Scutellariae, is demonstrated as effective for both antibacterial and anti-inflammatory purposes30,31,32. In experimental pulmonary fibrosis models, baicalin treatment reduced collagen deposition and inhibited fibroblast activation, suggesting its potential contribution to fibrosis regulation33. The presence of chlorogenic acid in Flos Lonicerae Japonicae can inhibit Staphylococcus aureus, along with various respiratory viruses34. Salvia miltiorrhiza, for example, possesses broad-spectrum anti-bacterial and anti-fibrotic actions35. Compounds such as morin and cudraflavone B in Cortex Mori have been shown to reduce inflammation from macrophages while also suppressing COX-2 expression36; and alcohol extracts of Cortex Mori can improve bronchospasm induced by histamine and leukotriene37. Bulbus Fritillariae Thunbergii alkaloids, such as peimine and peiminine, support bronchodilation via Ca2+-dependent K+ channels38, while isopeimine inhibits NF-κB activity and diminishes inflammatory responses39. Together, these pharmacological findings provide preliminary biological support for the core combinations identified in this study. Recent experimental studies have further demonstrated that Chinese herbal compounds can attenuate pulmonary fibrosis through regulation of inflammatory responses, oxidative stress, epithelial–mesenchymal transition (EMT), and fibroblast activation. For example, Astragalus membranaceus and Salvia miltiorrhiza-derived compounds have been reported to inhibit myofibroblast activation and extracellular matrix deposition through modulation of TGF-β/Smad and NF-κB signaling pathways in cellular and animal models of pulmonary fibrosis 2. These findings provide additional biological plausibility for the multi-target therapeutic characteristics of the herbal combinations identified in our analysis. However, most available evidence is derived from isolated compounds or individual herbs, and whether the identified multi-herb combinations exert synergistic effects in AE-IPF remains unclear. Future studies should incorporate in vitro and in vivo validation approaches, including cellular fibrosis models, animal models of pulmonary fibrosis, inflammatory cytokine profiling, transcriptomic analysis, and pharmacokinetic evaluation, to confirm the biological activity and molecular mechanisms of the candidate formulas. Previous experimental investigations have shown that multi-component Chinese herbal formulas may regulate pulmonary fibrosis-related pathways, including TGF-β/Smad signaling, oxidative stress responses, macrophage polarization, and extracellular matrix remodeling, in bleomycin-induced pulmonary fibrosis models, suggesting potential mechanisms that warrant further validation for the candidate formulas identified in this study40.
Entropy-based clustering identified four candidate formulas that integrate complementary therapeutic actions, including heat-clearing, phlegm-resolving, spleen-fortifying, and toxin-removing. These findings are consistent with previous network pharmacology studies, which have demonstrated that multi-herb preparations can exert synergistic effects through multi-component and multi-target interactions, modulating oxidative stress, fibroblast proliferation, immune regulation, and other pathways relevant to pulmonary fibrosis29,30,31,32,33,34.
Existing literature confirms partial consistency between our findings and previous data-mining studies conducted in other TCM settings11. Previous analyses of IPF-related prescriptions from different institutions have also reported frequent application of heat-clearing, phlegm-resolving, and blood-activating herbs, suggesting common therapeutic principles across clinical practitioners11. However, several prescription characteristics identified in the present study, including the specific combination of Radix Scutellariae, Bulbus Fritillariae Thunbergii, Cortex Mori, and Radix et Rhizoma Salviae Miltiorrhizae, may reflect Professor Xu's individualized clinical experience and syndrome differentiation strategy23. Although several core herbs, such as Radix Scutellariae, Bulbus Fritillariae Thunbergii, and Pinellia ternata, are consistent with classical TCM principles of heat-clearing and phlegm-resolving, the novelty of this study does not lie in identifying entirely new therapeutic concepts. Instead, its contribution is the systematic quantification of prescription frequency, compatibility relationships, and potential formula evolution within a specific expert clinical dataset. Comparative studies involving multiple experts and centers are required to distinguish universally applicable prescription principles from practitioner-specific preferences and to further evaluate the generalizability of these findings.
Several limitations of this study should be acknowledged. First, the single-center retrospective design, based on a single practitioner's clinical records, may introduce selection bias, regional practice bias, and practitioner-specific prescribing preferences. Consequently, the identified prescription patterns should be interpreted as the clinical experience of one expert rather than as universal TCM treatment rules for AE-IPF, and external validation using multicenter datasets involving multiple TCM practitioners is required. In addition, the absence of a control group and longitudinal clinical outcome data precludes any assessment of the relationship between the identified prescription patterns and therapeutic efficacy. Future multicenter validation cohorts involving different hospitals and clinicians are needed to evaluate the reproducibility and generalizability of these findings. Second, although internal validation was performed through consistency analysis and pharmacological interpretation, external validation using independent prescription datasets remains necessary. Third, the biological effects of the candidate formulas require verification through mechanistic studies using experimental models. The proposed mechanisms remain incompletely understood and necessitate further empirical evidence from in vitro and in vivo experiments, as well as pharmacological studies. Moreover, given the multi-component and multi-target nature of TCM prescriptions, further analyses—including molecular docking, network pharmacology, serum pharmacochemistry, and metabolomics—are needed to elucidate the active components and their mechanisms of action, thereby clarifying whether and how these candidates formulas may offer therapeutic benefits for AE-IPF.
In summary, this data-mining approach effectively characterized the prescribing patterns, core herb combinations, and candidate formulas within this single-expert clinical dataset, providing structured insights that may inform future investigations into the clinical relevance and biological mechanisms of these combinations.
In this study, data-mining techniques were applied to characterize the prescription patterns of Chinese herbal medicine for AE-IPF based on 84 prescriptions from Professor Xu Zhiying's clinical practice. The analysis identified 22 high-frequency herbs (frequency ≥50), with Radix Scutellariae, Bulbus Fritillariae Thunbergii, and Pinellia ternata being the most prominent, and revealed a therapeutic focus on heat-clearing, phlegm-resolving, toxin-removing, and spleen-supporting actions. Association rule mining further identified 11 core herb combinations with support ≥50, confidence ≥0.8, and lift >1, while entropy-based hierarchical clustering generated four candidate formulas that integrate these complementary therapeutic principles. The findings are largely supported by documented pharmacological actions of the constituent herbs, including anti-inflammatory, anti-fibrotic, and immunomodulatory effects. However, several limitations must be acknowledged: the single-center, single-practitioner design limits generalizability; the absence of clinical outcome data precludes efficacy assessment; and the candidate formulas require validation through experimental and clinical studies. Future multicenter investigations involving multiple TCM practitioners and prospective cohort designs are warranted to confirm the reproducibility, clinical relevance, and therapeutic value of these prescription patterns. Despite these limitations, this study provides a systematic, data-driven framework for characterizing expert prescribing experience and may serve as a foundation for future mechanistic and translational research in TCM-based AE-IPF management.
Disclosures
The authors declare no conflicts of interest.
Acknowledgements
This study received funding from the research project on the medication pattern of Professor Xu Zhiying's staged treatment of idiopathic pulmonary interstitial fibrosis based on data mining methods (Project No. 2020ZB094).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Electronic medical record system | Zhejiang Provincial Hospital of Traditional Chinese Medicine | N/A | Hospital information system; Internal clinical database |
| IBM SPSS Modeler | IBM Corp., Armonk, NY, USA | Version 18.0 | IBM SPSS Modeler 18.0 |
| Microsoft Excel | Microsoft Corporation, USA | Microsoft Office 2019 | Microsoft Office package |
| Traditional Chinese Medicine Inheritance and Computing Platform | China Academy of Chinese Medical Sciences | Version 3.5 | Commercial software platform |
| Traditional Chinese Medicine Inheritance and Computing Platform | China Academy of Chinese Medical Sciences | Version 2.5 | Commercial software platform |
References
- Lynch DA, et al. Diagnostic criteria for idiopathic pulmonary fibrosis: a Fleischner Society White Paper. Lancet Respir Med. 2018;6(2):138–53.
- Liu Q, Liu X, Wang G, Wu F, Hou Y. Genome-wide DNA methylation analysis of Astragalus and Danshen on the intervention of myofibroblast activation in idiopathic pulmonary fibrosis. BMC Pulm Med. 2023;23(1):325.
- Maher TM, et al. Global incidence and prevalence of idiopathic pulmonary fibrosis. Respir Res. 2021;22(1):197.
- Senoo S, Taniguchi A, Itano J, Oda N, Morichika D. Essential role of IL-23 in the development of acute exacerbation of pulmonary fibrosis. Am J Physiol Lung Cell Mol Physiol. 2021;321(5):L925–L40.
- Ghazipura M, et al. Pirfenidone in Progressive Pulmonary Fibrosis: A Systematic Review and Meta-Analysis. Ann Am Thorac Soc. 2022;19(6):1030–9.
- Qin S, Tan P, Xie J, Zhou Y, Zhao J. A systematic review of the research progress of traditional Chinese medicine against pulmonary fibrosis: from a pharmacological perspective. Chin Med. 2023;18(1):96.
- Collard HR, et al. Acute Exacerbation of Idiopathic Pulmonary Fibrosis. An International Working Group Report. Am J Respir Crit Care Med. 2016;194(3):265–75.
- Gan W, et al. Modified Maimendong decoction in the treatment of patients with idiopathic pulmonary fibrosis: Study protocol for a randomized controlled trial. Medicine (Baltimore). 2020;99(49):e23460.
- Yu XQ, Yang SG, Xie Y, Li JS. Traditional Chinese medicine in the treatment of idiopathic pulmonary fibrosis based on syndrome differentiation: Study protocol of an exploratory trial. J Integr Med. 2020;18(2):163–8.
- Wang Y, Xu B, Wang J, Li S, Xie Y. Traditional Chinese Medicine Ion Introduction Therapy Reduces the Incidence of Acute Exacerbation of Idiopathic Pulmonary Fibrosis: A Prospective Cohort Study. Int J Gen Med. 2025;18:21–32.
- Zhang S, et al. Medication regularity of pulmonary fibrosis treatment by contemporary traditional Chinese medicine experts based on data mining. J Thorac Dis. 2018;10(3):1775–87.
- Hailong Z, et al. Efficacy and safety of traditional Chinese medicine in patients with acute exacerbation of idiopathic pulmonary fibrosis: study protocol for randomized, controlled, exploratory clinical trial. Trials. 2022;23(1):103.
- Wu Q, Xu Y, Zhang KJ, Jiang SM, Zhou Y. A Clinical Model for the Prediction of Acute Exacerbation Risk in Patients with Idiopathic Pulmonary Fibrosis. Biomed Res Int. 2020;2020:8848919.
- Wu X, et al. Comparison of 4 kinds of traditional Chinese medicine injections to assist in improving clinical indicators of patients with idiopathic pulmonary fibrosis: A systematic review and network meta-analysis. Medicine (Baltimore). 2022;101(47):e31877.
- Raghu G, et al. Idiopathic Pulmonary Fibrosis (an Update) and Progressive Pulmonary Fibrosis in Adults: An Official ATS/ERS/JRS/ALAT Clinical Practice Guideline. Am J Respir Crit Care Med. 2022;205(9):e18–e47.
- Interstitial Lung Disease Group of Society of Respiratory Medicine of Chinese Medical Association. Chinese expert consensus on diagnosis and treatment of idiopathic pulmonary fibrosis. Chin J Tuberc Respir Dis. 392016. p. 427–32.
- Chinese Pharmacopoeia Commission. Pharmacopoeia of the People’s Republic of China. China Medical Science Press; 2018.
- Gao X. Chinese Materia Medica. China Press of Traditional Chinese Medicine; 2017.
- Li Y, et al. Exploring therapeutic targets for molecular therapy of idiopathic pulmonary fibrosis. Sci Prog. 2024;107(2):368504241247402.
- Li X, et al. Lenalidomide attenuates post-inflammation pulmonary fibrosis through blocking NF-kappaB signaling pathway. Int Immunopharmacol. 2022;103:108470.
- Qin Y. The Complete Medical Works of Bian Que (Qin Yueren) and Hua Tuo. China Press of Traditional Chin Med; 2025.
- Zhang S. Collected Annotations and Corrections on the Classic of Difficult Issues. Tianjin Science and Technology Press; 2010.
- Shi X, et al. Analysis of Xu Zhiying’s approach in the treatment of idiopathic pulmonary fibrosis based on the ‘lung ripening’ theory from the Classic of Difficult Issues. China Journal of Traditional Chinese Medicine and Pharmacy. 2021;36(8):4714–7.
- Huang X, Liu R, Li W, Bin F. Treatment of idiopathic pulmonary fibrosis based on the ‘lung heat’ theory. Global Traditional Chinese Medicine. 2022;15(8):1431–4.
- Yu Q, Yu X. Exploring the mechanism of the Astragalus-Salvia miltiorrhiza herb pair in the treatment of pulmonary fibrosis based on the ‘lung deficiency and collaterals stasis’ theory, network pharmacology, and molecular docking. Journal of Practical Traditional Chinese Internal Medicine. 2024;38(12):75–9+168–70.
- Zhang C, Zhu Z. Discussion on the pathogenesis and treatment of idiopathic pulmonary fibrosis based on the collateral disease theory. Journal of Practical Traditional Chinese Internal Medicine.1–7.
- Song J, Teng Y, Chai L, Yan J. Treatment of idiopathic pulmonary fibrosis based on the principle of using pungent herbs to moisten. Journal of Zhejiang Chinese Medical University. 2024;48(7):802–6.
- Li G. Treatise on the Spleen and Stomach. People's Military Medical Press; 2005.
- Yan X, et al. Comparative study on the antitussive, expectorant, and antiasthmatic effects of alcohol-water extracts from Fritillaria unibracteata and Fritillaria thunbergii. Chinese Journal of Experimental Traditional Medical Formulae. 2012;18(10):244–8.
- Jia S. Meaning of Drug Properties. China Press of Traditional Chinese Medicine; 2015.
- Zhu X, et al. Study on the ex vivo antibacterial effects of Coptis chinensis and other Chinese herbal medicines against common pathogenic bacteria. Feed Research. 2021;44(7):98–101.
- Xin W, Song J, He G, Du G. Research advances in the pharmacological effects and mechanisms of baicalein and baicalin. Chinese Journal of New Drugs. 2013;22(6):647–53+59.
- Gao Y, et al. Baicalein attenuates bleomycin-induced pulmonary fibrosis in rats through inhibition of miR-21. Pulm Pharmacol Ther. 2013;26(6):649–54.
- Guan Z, Zhao J, Lin Q. Experimental study on the antibacterial effect of Lonicera japonica extract. China Modern Doctor. 2009;47(15):150–1+3.
- Liu X, et al. Study on the ex vivo antibacterial effects of seven single Chinese herbs and their formulations. Chinese Journal of Disinfection. 2023;40(2):98–102.
- Hosek J, et al. Natural compound cudraflavone B shows promising anti-inflammatory properties in vitro. J Nat Prod. 2011;74(4):614–9.
- Liu H, Li Y, Huang Z. Research progress on the pharmacological effects of Morus alba root bark. Chinese Journal of Experimental Traditional Medical Formulae. 2019;25(20):229–34.
- Wu X, et al. Investigation of association of chemical profiles with the tracheobronchial relaxant activity of Chinese medicinal herb Beimu derived from various Fritillaria species. J Ethnopharmacol. 2018;210:39–46.
- Zhou M, et al. Comparison and evaluation of antimuscarinic and anti-inflammatory effects of five Bulbus fritillariae species based on UPLC-Q/TOF integrated dual-luciferase reporter assay, PCA and ANN analysis. J Chromatogr B Analyt Technol Biomed Life Sci. 2017;1041–1042:60–9.
- Wang L, Zhu T, Feng D, Li R, Zhang C. Polyphenols from Chinese Herbal Medicine: Molecular Mechanisms and Therapeutic Targets in Pulmonary Fibrosis. Am J Chin Med. 2022;50(4):1063–94.