This propensity score-matched study demonstrates that a multimodal pain management approach, combining standard analgesics with interventional, psychological, and palliative therapies, yields superior pain control, quality of life, and mental health outcomes, with reduced opioid escalation—suggesting potential benefits in mitigating opioid-related adverse events.
Research Article
Comprehensive Pain Management, Quality of Life, and Mental Health in Advanced Cancer: A Propensity Score-Matched Retrospective Study
In This Article
Summary
Abstract
For advanced cancer patients, unrelieved moderate-to-severe pain adversely affects quality of life and psychological well-being. While pain control is fundamental to palliative care, the benefits associated with a multimodal approach warrant investigation. This PSM-based retrospective study (2022–2025) evaluated the associations between comprehensive pain management and quality-of-life and mental health outcomes in advanced cancer. Participants received either comprehensive management (standard analgesics plus ≥1 adjunct modality: interventional oncology, thermotherapy, psychological counseling, or palliative support) or pharmacotherapy alone. One-to-one nearest-neighbor matching balanced demographics, disease status, and baseline pain severity. Primary endpoints (Numerical Rating Scale [NRS], Pain Management Index, European Organization for Research and Treatment of Cancer Quality of Life Core Scale, Hospital Anxiety and Depression Scale) were assessed at baseline and two weeks. Propensity matching yielded 60 balanced pairs from 150 patients (standardized mean differences < 0.1). At 2 weeks, multimodal therapy was associated with superior analgesia (NRS: 2.8 ± 1.1 vs 4.2 ± 1.3), higher response rates (58.3% vs 35.0%), and fewer undertreated cases (16.7% vs 41.7%) (all P < 0.05). Comprehensive care was associated with better functional capacity (68.5 ± 12.4 vs 55.3 ± 13.6), lower symptom burden (25.6 ± 8.9 vs 38.4 ± 11.2) (P < 0.001), and lower anxiety/depression scores (6.2 ± 2.8 vs 9.5 ± 3.1; 5.8 ± 2.5 vs 8.9 ± 3.0, P < 0.001). Opioid escalation was attenuated in the multimodal arm (47.26% vs 65.27%, P < 0.001), while adverse events were similar (P > 0.05). Regression identified comprehensive care as an independent correlate of better outcomes, and sensitivity analyses confirmed its robustness. In conclusion, comprehensive pain management was associated with superior pain control, better quality of life, and improved psychological outcomes in advanced cancer compared to standard analgesia, alongside reduced opioid escalation—a finding that may have clinical relevance for reducing opioid-related adverse events.
Introduction
In advanced malignancy, pain is a frequent and debilitating symptom that significantly impairs patients' quality of life, daily functioning, and mental health1. According to epidemiological surveys, pain prevalence ranges from 54.6% to 69% among individuals with advanced-stage or metastatic malignancy2, of which about 50% of patients with stage IV report moderate to severe pain, and a quarter of patients still experience severe pain that is difficult to control in the last week of life3. The pathophysiological mechanism of cancer pain is complex, often involving nociceptive, neuropathic, and mixed pain components, and breakthrough pain occurs frequently, which significantly interferes with the daily activities, sleep, social function, and emotional state of patients4.
Pain management is the core component of palliative care. The World Health Organization (WHO) three-step analgesia principle has long been used as the gold standard for cancer pain treatment, and strong opioids are the cornerstone for severe cancer pain treatment5. However, relying solely on drug analgesia has many limitations. First of all, ~30–40% of patients still cannot obtain satisfactory analgesia through standard drug treatment6. Secondly, prolonged opioid therapy commonly induces adverse effects, including constipation, nausea, and somnolence, while also posing risks of tolerance and potential misuse7. Moreover, the multidimensional nature of cancer pain determines that the simple biomedical model is difficult to comprehensively solve the pain of patients. Factors such as psychological pain, social isolation, and spiritual distress jointly affect the overall comfort of patients8.
In recent years, the comprehensive pain management model has gradually attracted attention, which is, on the basis of standardized drug analgesia, integrating multidisciplinary treatment measures such as interventional therapy, psychological support, physical therapy, and palliative care9. Multidisciplinary approaches facilitate holistic evaluation of cancer pain's complex dimensions, ultimately improving patient functioning and well-being10,11. Tumor interventional therapy can provide precise pain relief for pain caused by soft tissue masses12. Psychological counseling, such as cognitive behavioral therapy and mindfulness training, can help relieve anxiety and depression and improve pain perception13. The multidisciplinary team (MDT) of palliative care focuses on the overall comfort and meaning of life of patients14. The hypothesized advantages of comprehensive pain management for advanced cancer patients' quality of life and psychological status await confirmation through rigorous clinical research9,10.
Despite the growing adoption of multimodal pain management in many centers worldwide, evidence for its benefits in specific populations and real-world settings remains limited. Most existing studies have been conducted in Western populations or specialized palliative care units, and data from Chinese community-based hospital settings are sparse. Furthermore, the comparative effectiveness of this approach versus standard pharmacotherapy alone—particularly after controlling for selection bias using propensity score methods—has not been extensively evaluated in Chinese populations with advanced cancer. Multidimensional assessments covering pain control, quality of life, psychological outcomes, and opioid consumption in a single cohort are also scarce.
To address these gaps, this retrospective investigation employed propensity score-matched (PSM) cohorts to evaluate associations between multimodal pain therapy versus conventional pharmacologic management and clinical outcomes—including pain relief, quality of life, and psychological well-being—in a Chinese community hospital setting. The following hypotheses were proposed: (i) patients receiving comprehensive pain management may show lower pain intensity and higher pain relief rate than those receiving standardized drug analgesia alone; (ii) Comprehensive pain management may be associated with better quality of life and mental health, including improved functional status, reduced symptom burden, and improvements in anxiety and depression; (iii) The multimodal analgesia group showed attenuated opioid dose increases, while adverse reaction frequencies remained similar across cohorts. By evaluating the aforementioned hypotheses, we aim to generate preliminary evidence guiding improved analgesic approaches in advanced malignancy.
Protocol
Study design and patient selection
This retrospective cohort study was conducted at Lezhi County People's Hospital. The study protocol was approved by the institutional ethics committee (Approval No. LRYLL202602) on March 12, 2026. Data extraction was initiated only after formal ethics approval was obtained. Clinical data were obtained from the institutional electronic medical records retrospectively and a dedicated pain management database for patients treated between June 1, 2022, and June 30, 2025. The institutional ethics committee waived the requirement for informed consent because this retrospective study analyzed previously collected, anonymized clinical data and posed minimal risk to participants. The investigation was conducted in accordance with the principles of the Declaration of Helsinki. An overview of the study design and patient selection is presented in Figure 1.
Patients were included if they were aged ≥ 18 years, had pathologically or cytologically confirmed advanced malignancy (clinical stage III or IV), experienced cancer-related pain with a Numerical Rating Scale (NRS) score ≥ 4 (moderate to severe pain) at enrollment, had an expected survival of ≥3 months, and possessed complete clinical records containing all necessary evaluation indicators15. Exclusion criteria comprised severe cognitive impairment or psychiatric disease that precluded cooperation with pain assessment and quality-of-life investigation, severe non-cancer pain (e.g., acute surgical or traumatic pain) that could confound evaluation, emergency admission or hospital stay < 72 h that prevented treatment completion and efficacy assessment, allergy to opioids or a history of opioid abuse, and missing key baseline data (e.g., primary assessment scales).
PSM was performed to minimize selection bias. Propensity scores were estimated via multivariable logistic regression, with treatment assignment as the dependent variable. Covariates were selected a priori and included age, sex, tumor type, stage, bone metastasis, Eastern Cooperative Oncology Group (ECOG) score, baseline NRS, and pain type. One-to-one nearest-neighbor matching without replacement was applied with a caliper of 0.2 standard deviation (SD) of the logit-transformed propensity scores. The target estimand was the average treatment effect on the treated (ATT). Common support was confirmed by visual inspection of propensity score overlap; no patients were excluded for non-overlap. Of the 150 initially enrolled patients, 30 cases (18 study, 12 control) did not satisfy the caliper and were excluded. The remaining 60 matched pairs (120 patients) achieved standardized mean differences (SMDs) < 0.1 for all covariates, confirming adequate balance.
Prior to PSM, 150 patients met the eligibility criteria and were enrolled, comprising 82 cases in the study group (comprehensive management) and 68 in the control group. Among the 82 patients initially assigned to the study group, 44 (53.7%) received ablation/TACE, 18 (22.0%) received hyperthermia, 52 (63.4%) received psychological counseling, and 34 (41.5%) received palliative care support. Combination therapy (≥2 adjunctive modalities) was administered to 43 patients (52.4%), with interventional treatment plus psychological counseling being the most frequent combination (n = 22, 26.8%), followed by interventional treatment plus palliative support (n = 12, 14.6%) and psychological counseling plus palliative support (n = 9, 11.0%). The remaining 39 patients (47.6%) received a single adjunctive modality.
Sample size calculation
The primary outcome for sample size estimation was defined as the between-group difference in post-treatment pain intensity measured by the NRS. Based on previous pilot experiments and multimodal analgesia research16, the assumed mean NRS reduction was 3.5 points for the study group and 2.0 points for the control group, with a pooled standard deviation of 2.0. A two-sided significance level (α) of 0.05 and a statistical power of 80% were specified. Using a two-sample t-test, the minimum required sample size was calculated to be at least 52 cases per group. Accounting for expected data loss during propensity score matching (estimated at 20%) and the inherent limitations of retrospective studies, we selected 60 cases per group for analysis, totaling 120 matched patients. To ensure an adequate number of matched pairs, 150 patients were initially enrolled in the database.
Treatment groups
In routine clinical practice, the analgesic strategy was determined by the attending oncologist based on MDT recommendations. The decision to add a specific adjunctive modality was guided by the predominant pain mechanism and clinical presentation. Specifically, interventional oncology (ablation/TACE) was recommended for pain originating from soft tissue compression; local deep hyperthermia was considered for pain associated with pleural/peritoneal effusions or superficial metastatic lesions; psychological counseling was offered to patients with significant emotional distress, maladaptive coping, or anxiety/depression symptoms; and palliative care support was provided to those with complex existential concerns, family conflicts, or multifaceted symptom burdens requiring comprehensive team-based management. Patients who received standard pharmacotherapy alone (control group) did not receive any of the above adjunctive modalities, typically due to patient preference, good initial response to opioids, or absence of MDT referral during the study period17.
For patients in the study group, each adjunctive modality was delivered in accordance with standardized institutional protocols. Ablation/TACE was indicated for symptomatic soft-tissue masses, depending on lesion size, location, and patient performance status. Hyperthermia was indicated for pain refractory to opioids in the setting of effusion-related or superficial metastatic lesions, applied locally using a deep hyperthermia device at 40–43 °C for 30–60 min per session, two to three times weekly, for a total of six sessions over 2 weeks. Psychological counseling, indicated for patients with elevated anxiety or depression scores (HADS-A or HADS-D ≥ 8) or self-reported emotional distress, comprised individual 30 min sessions once weekly, incorporating cognitive-behavioral techniques (cognitive restructuring, behavioral activation), relaxation training (progressive muscle relaxation, guided imagery), and psychological support, delivered by a trained clinical psychologist or licensed psychotherapist, for a total of two sessions during the 2 week study period. Palliative care support, indicated for patients with complex physical symptoms, existential distress, or family communication needs, was provided by an MDT (oncologist, palliative care nurse, social worker, and chaplain when available), including comprehensive symptom review, life review, family meetings, and advance care planning discussions, with team meetings conducted weekly and individualized interventions delivered as needed throughout the two-week period. Adherence to scheduled interventions was defined as completion of at least 80% of planned sessions. Overall adherence rates were 92% for psychological counseling, 88% for hyperthermia, and 95% for palliative care support; interventional treatment adherence was 100% since it was delivered as inpatient procedures under direct supervision.
Outcome measures
All outcomes were assessed at enrollment (baseline) and two weeks post-treatment by trained study staff who were not involved in clinical decision-making. Pain intensity was measured using the NRS (0–10)18, with pain response defined as a ≥50% reduction from baseline. Pain management quality was evaluated using the Pain Management Index (PMI)19, where a negative value indicated inadequate analgesia. The Chinese version of the European Organization for Research and Treatment of Cancer Quality of Life Core Questionnaire (EORTC QLQ-C30) was used to evaluate quality of life20, with raw scores for functional and symptom domains linearly transformed to a 0–100 scale (higher scores indicated better function or worse symptoms, respectively). The Hospital Anxiety and Depression Scale (HADS)21 was administered to assess psychological well-being. It comprises separate anxiety (HADS-A) and depression (HADS-D) subscales, each scored from 0 to 21, with higher scores indicating more severe symptoms. Morphine equivalent daily dose (MEDD) was calculated at baseline and post-treatment to assess opioid requirement changes.
Adverse events associated with each treatment modality were assessed and graded in accordance with CTCAE version 5.0. Ablation-related grade 1-2 skin reactions (erythema, local warmth or superficial burns) occurred in 6 of 44 recipients (13.6%) with no grade ≥3 events. Hyperthermia-related local warmth sensation was reported by 12 of 18 recipients (66.7%), and mild superficial burns (grade 1) occurred in 2 patients (11.1%), both of which resolved with conservative management. No serious adverse events (grade ≥ 3) were attributed to hyperthermia. No specific adverse events were attributable to psychological counseling or palliative care support beyond those associated with standard pharmacotherapy. Importantly, the overall frequencies of common opioid-related adverse events (constipation, nausea/vomiting, somnolence, urinary retention, and respiratory depression) were compared between the two groups as secondary outcomes.
Statistical analysis
Data were analyzed using appropriate statistical software, with statistical significance defined as a two-sided P value < 0.05. The primary endpoint was defined as the between-group difference in posttreatment pain intensity (NRS). Secondary endpoints, analyzed in hierarchical order, included pain response rate, analgesic adequacy (PMI), quality-of-life (EORTC QLQ-C30), psychological distress (HADS), and opioid requirement changes. Sample size calculation, detailed in the preceding subsection, yielded 60 pairs after accounting for matching losses. For continuous variables, intergroup differences were assessed using paired t-tests for normally distributed variables (age, baseline NRS, hemoglobin, and post-treatment outcomes including NRS, EORTC QLQ-C30 domains, and HADS subscales) or Wilcoxon signed-rank tests for non-normally distributed variables (albumin, creatinine, and MEDD percentage increase). Distributional assumptions were evaluated with the Shapiro–Wilk test. Binary categorical variables were analyzed using McNemar's test, whereas variables with more than two categories were assessed using the McNemar–Bowker test. Change-score analysis (Δ values: post-treatment minus baseline) served as the primary approach for continuous outcomes. Multivariable linear regression models were constructed to identify independent correlates of improvements in outcomes (ΔEORTC functional domain, ΔHADS-A, and ΔHADS-D) using the full matched cohort in long-format data (n = 120). Covariates selected a priori included treatment group, age, sex, tumor type, cancer stage, bone metastasis, ECOG performance status, baseline NRS (for the quality-of-life model), and baseline HADS scores (for the psychological models). Multicollinearity was assessed using variance inflation factors (VIF > 10 excluded); model assumptions were verified via residual plots. No multiplicity adjustment was applied for primary and secondary endpoints, given their prespecified hierarchical order. Subgroup analyses stratified by tumor type and baseline pain intensity were performed on the matched pairs using paired t-tests. Sensitivity analyses—including kernel matching, inverse probability of treatment weighting (IPTW), and subgroup analyses—were conducted to test the robustness of the findings.
Results
Initially, 150 patients with advanced cancer who met the eligibility criteria were enrolled, comprising 82 in the study group and 68 in the control group. Following 1:1 PSM, 60 well-matched pairs were successfully generated, yielding a final analytical cohort of 120 patients. After matching, we observed no significant between-group differences across all evaluated covariates: demographics (age, sex, marital status, education), oncological factors (tumor type/stage, bone metastasis), functional status (ECOG), pain profile (baseline NRS, type, duration), and laboratory values (hemoglobin, albumin, creatinine). All covariates achieved balance (P > 0.05, SMD < 0.1), confirming excellent intergroup comparability post matching. Table 1 presents the postmatching baseline characteristics of the study population.
At 2 weeks post treatment, the study group exhibited significantly lower NRS scores (2.8 ± 1.1 vs 4.2 ± 1.3, P < 0.001) and a higher pain response rate (≥50% NRS reduction: 58.3% vs 35.0%, P = 0.011) compared to controls. PMI assessment revealed significantly fewer cases of inadequate analgesia in the study group than in controls (16.7% vs 41.7%, P = 0.006), as shown in Table 2.
At 2 weeks, the study group demonstrated significantly better quality of life, with higher functional domain scores and lower symptom domain scores compared to controls. The study group exhibited a superior quality of life compared to controls. Table 3 presents the pre- and post-treatment quality-of-life scores for both groups.
Following 2 weeks of intervention, patients receiving comprehensive pain management achieved significantly greater reductions in psychological distress relative to controls, as evidenced by lower HADS anxiety (6.2 ± 2.8 vs 9.5 ± 3.1) and depression (5.8 ± 2.5 vs 8.9 ± 3.0) scores (both P < 0.001; Table 4).
After two weeks of intervention, patients receiving comprehensive pain management required substantially less opioid dose escalation (47.26% increase) compared to those on standard therapy (65.27% increase, P < 0.001), indicating favorable analgesic efficacy with reduced opioid burden (Table 5).
No significant between-group differences were observed in the incidence of adverse reactions throughout the study period (P > 0.05). The most commonly reported events were constipation and nausea/vomiting. While the incidence of constipation was marginally reduced in the comprehensive management cohort compared with controls, the between-group difference did not reach statistical significance (Table 6).
The results of multiple linear regression analysis (Table 7) showed that after adjusting for demographic characteristics and clinical variables, comprehensive pain management (study group) was significantly associated with improvements in quality of life (β = 14.042, 95% CI: 8.03 to 20.06, P < 0.001), anxiety (β = −3.295, 95% CI: −4.37 to −2.22, P < 0.001), and depression (β = −3.078, 95% CI: −4.08 to −2.08, P < 0.001). A higher baseline NRS score was associated with greater quality-of-life improvement (β = 2.694, P = 0.037). Higher baseline HADS-A and HADS-D scores were significantly associated with greater improvements in anxiety (β = −0.993, P < 0.001) and depression (β = −0.904, P < 0.001), respectively, suggesting that patients with poorer baseline psychological status may experience greater benefit from comprehensive management. Age and sex were not significantly associated with any of the three outcomes (all P > 0.05).
Multiple sensitivity analyses yielded findings consistent with the primary analysis, as presented in Table 8. Effect estimates remained stable when applying alternative matching algorithms—kernel matching (NRS mean difference: −1.5, 95% CI: −1.9 to −1.1; EORTC functional domain: +13.1, 95% CI: 8.1 to 18.1) and inverse probability of treatment weighting (IPTW: NRS mean difference: −1.5, 95% CI: −1.9 to −1.1; EORTC functional domain: +12.8, 95% CI: 7.9 to 17.7)—with all P values < 0.001, suggesting that the findings were not sensitive to the choice of analytical method. Subgroup analyses stratified by tumor type and baseline pain intensity showed consistent directional effects favoring the comprehensive management group across all subgroups. The most pronounced differences were observed in patients with moderate baseline pain (mean difference: −1.8, 95% CI: −2.5 to −1.0) and those with lung cancer (mean difference: −1.5, 95% CI: −2.0 to −1.0) or gastrointestinal cancer (mean difference: −1.5, 95% CI: −2.3 to −0.6). Patients with other tumor types also showed a significant difference (mean difference: −0.7, 95% CI: −1.3 to −0.1, P = 0.027), suggesting that the observed associations generalize across diverse cancer populations. Taken together, these sensitivity analyses suggest that the findings associated with comprehensive pain management were reasonably robust, and the results of the main analysis were not substantially affected by the choice of analytical method or population heterogeneity.
Data availability
Due to patient confidentiality requirements and restrictions imposed by the Ethics Committee of Lezhi County People's Hospital, the data generated and/or analyzed during this study cannot be deposited in a publicly accessible data repository. De-identified data may be made available to qualified researchers upon reasonable request, subject to review and approval by the Ethics Committee and completion of the required data use agreement. Requests may be directed to the corresponding author, who will facilitate the institutional review process.
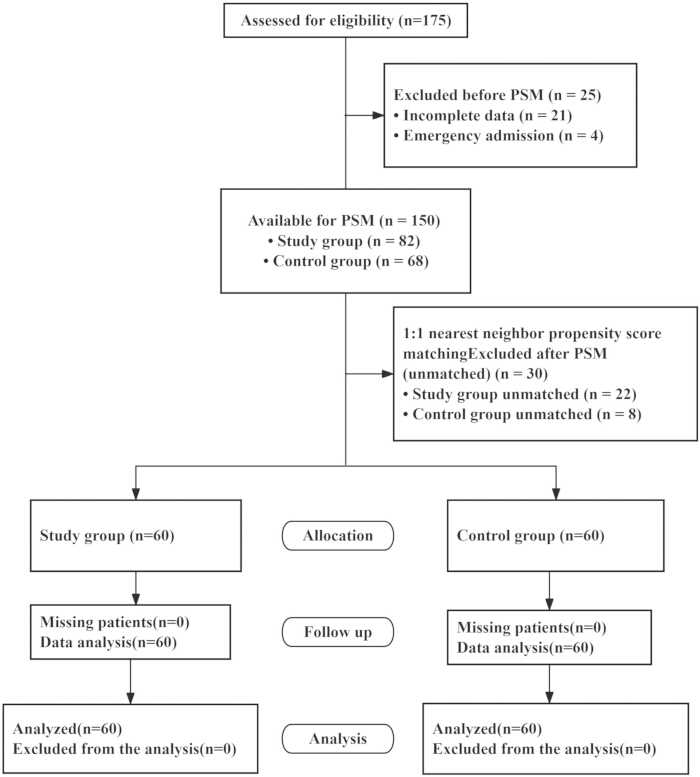
Figure 1: Design flow chart. This figure illustrates the patient selection and grouping process. It details the inclusion and exclusion criteria, the initial enrollment of 150 patients, the allocation to the study group (comprehensive pain management) and control group (standard pharmacotherapy), and the final cohort of 120 patients after 1:1 propensity score matching. Abbreviation: PSM = propensity score matching. Please click here to view a larger version of this figure.
| Variable | Study Group (n=60) | Control Group (n=60) | P-value | SMD |
| Age (years, Mean±SD) | 58.9±11.8 | 59.1±11.9 | 0.919 | 0.017 |
| Sex [n(%)] | 1 | 0.022 | ||
| Male | 33 (55.0) | 34 (56.7) | ||
| Female | 27 (45.0) | 26 (43.3) | ||
| Marital status [n(%)] | 0.845 | 0.048 | ||
| Married | 42 (70.0) | 44 (73.3) | ||
| Other (unmarried/divorced/widowed) | 18 (30.0) | 16 (26.7) | ||
| Educational level [n(%)] | 0.856 | 0.048 | ||
| High school or above | 28 (46.7) | 26 (43.3) | ||
| Middle school or below | 32 (53.3) | 34 (56.7) | ||
| Tumor type [n(%)] | 0.999 | 0.063 | ||
| Lung cancer | 25 (41.7) | 26 (43.3) | ||
| Gastrointestinal cancer | 16 (26.7) | 15 (25.0) | ||
| Breast cancer | 11 (18.3) | 12 (20.0) | ||
| Other | 8 (13.3) | 7 (11.7) | ||
| Tumor stage [n(%)] | 1 | 0.026 | ||
| Stage III | 23 (38.3) | 24 (40.0) | ||
| Stage IV | 37 (61.7) | 36 (60.0) | ||
| ECOG performance status [n(%)] | 0.553 | 0.035 | ||
| 0-1 | 25 (41.7) | 26 (43.3) | ||
| 2 | 28 (46.7) | 27 (45.0) | ||
| 3-4 | 7 (11.7) | 7 (11.7) | ||
| Baseline NRS score (points, Mean±SD) | 6.4±1.2 | 6.5±1.2 | 0.637 | 0.083 |
| Pain type [n(%)] | 0.653 | 0.048 | ||
| Nociceptive | 27 (45.0) | 26 (43.3) | ||
| Neuropathic | 13 (21.7) | 12 (20.0) | ||
| Mixed | 20 (33.3) | 22 (36.7) | ||
| Pain duration [n(%)] | 0.839 | 0.048 | ||
| <3 months | 22 (36.7) | 20 (33.3) | ||
| ≥3 months | 38 (63.3) | 40 (66.7) | ||
| Bone metastasis [n(%)] | 35 (58.3) | 34 (56.7) | 1 | 0.033 |
| Laboratory parameters (Mean±SD) | ||||
| Hemoglobin (g/L) | 112.5±18.3 | 114.2±17.6 | 0.596 | 0.095 |
| Albumin (g/L) | 36.20 [33.10, 38.85] | 35.95 [31.83, 39.45] | 0.768 | 0.099 |
| Creatinine (μmol/L) | 73.75 [61.70, 91.00] | 74.75 [60.25, 91.40] | 0.568 | 0.096 |
Table 1: Baseline characteristics of the two groups after propensity score matching. Continuous variables: age, baseline NRS, and hemoglobin were normally distributed and are presented as Mean ± SD, compared using paired t-tests; albumin and creatinine were non-normally distributed and are presented as Median [Q1, Q3], compared using paired Wilcoxon signed-rank tests. Categorical variables: paired proportions were compared using McNemar's test (binary variables) or McNemar-Bowker test (polytomous variables). All SMDs were <0.1, confirming adequate covariate balance between groups. Abbreviations: PSM = propensity score matching; SMD = standardized mean difference; ECOG = Eastern Cooperative Oncology Group performance status; NRS = Numeric Rating Scale.
| Outcome | Study Group (n=60) | Control Group (n=60) | Statistical Value | P-value |
| Post-treatment NRS score (Mean±SD) | 2.8±1.1 | 4.2±1.3 | t=-6.015 | <0.001 |
| Pain response rate [n(%)] | 35 (58.3) | 21(35.0) | χ²=6.43 | 0.011 |
| Inadequate analgesia [n(%)] | 10(16.7) | 25(41.7) | χ²=7.259 | 0.006 |
Table 2: Comparison of pain control outcomes after treatment. Pain response: ≥50% NRS reduction from baseline. Inadequate analgesia: negative PMI. Statistical methods: paired t-test for continuous data; McNemar test for categorical data. Abbreviations: NRS = Numeric Rating Scale; PMI = Pain Management Index.
| Domain | Study Group (n=60) | Control Group (n=60) | Intergroup Difference (95% CI) | P-value |
| Functional Domain | +13.2 (8.3, 18.1) | <0.001 | ||
| Pretreatment | 48.6±10.2 | 49.1±10.5 | ||
| Post treatment | 68.5±12.4 | 55.3±13.6 | ||
| Symptom Domain | -12.8 (-16.5, -9.1) | <0.001 | ||
| Pretreatment | 42.3±9.8 | 41.8±10.3 | ||
| Post treatment | 25.6±8.9 | 38.4±11.2 |
Table 3: EORTC QLQ-C30 scores before and after treatment: comparison between groups (x̄±s). Quality of life was measured using the Chinese version of the EORTC QLQ-C30. Scores were linearly transformed to a 0–100 scale; higher scores indicate better function for the Functional Domain and worse symptoms for the Symptom Domain. All data are presented as Mean ± SD. The “Net Difference Between Groups” represents the difference between the study group and control group in post-treatment scores (Study − Control). Intergroup comparisons were performed using paired t-tests. Abbreviation: EORTC QLQ-C30 = European Organization for Research and Treatment of Cancer Quality of Life Core Scale.
| Symptom | Study Group (n=60) | Control Group (n=60) | Intergroup Difference (95% CI) | P-value |
| Anxiety (HADS-A) | -3.3 (-4.4, -2.2) | <0.001 | ||
| Pretreatment | 12.8±3.2 | 12.5±3.4 | ||
| Post treatment | 6.2±2.8 | 9.5±3.1 | ||
| Depression (HADS-D) | -3.1 (-4.1, -2.1) | <0.001 | ||
| Pretreatment | 11.6±3.0 | 11.9±3.3 | ||
| Post treatment | 5.8±2.5 | 8.9±3.0 |
Table 4: HADS scores before and after treatment: comparison between groups (x̄±s). HADS (subscales: HADS-A anxiety, HADS-D depression; range 0–21 per subscale, higher scores indicate greater severity). The “Net Difference Between Groups” represents the difference between the study group and control group in post-treatment scores (Study − Control). Negative values indicate greater improvement in the study group. Intergroup comparisons were performed using paired t-tests, consistent with the matched-pair design. Abbreviation: HADS = Hospital Anxiety and Depression Scale.
| Parameter | Study Group (n=60) | Control Group (n=60) | Statistical Value | P-value |
| Baseline MEDD (mg/24 h) | 48.5±15.6 | 46.8±16.2 | t=0.612 | 0.543 |
| Posttreatment MEDD (mg/24 h) | 69.6±22.0 | 78.2±23.5 | t=-2.122 | 0.038 |
| MEDD Increase (%) | 47.26 [32.07, 57.67] | 65.27 [59.73, 83.77] | Z = −5.786 | <0.001 |
Table 5: Analgesic dose changes before and after treatment: comparison between groups (x̄±s). MEDD (oral morphine mg/24 h via conversion factors). MEDD change formula: [(Post − Baseline) / Baseline] × 100%. Baseline and post-treatment MEDD were analyzed using paired t-tests. MEDD increase was non-normally distributed and compared using paired Wilcoxon signed-rank test, presented as median [first quartile, third quartile]. Abbreviation: MEDD = morphine equivalent daily dose.
| Adverse Event | Study Group (n=60) | Control Group (n=60) | P-value |
| Constipation | 32 (53.3) | 38 (63.3) | 0.146 |
| Nausea and vomiting | 24 (40.0) | 28 (46.7) | 0.125 |
| Somnolence | 12 (20.0) | 15 (25.0) | 0.25 |
| Urinary retention | 4 (6.7) | 6 (10.0) | 0.508 |
| Respiratory depression | 1 (1.7) | 2 (3.3) | 0.56 |
Table 6: Adverse event rates: comparison between groups [n(%)]. Data are presented as n (%). Comparisons were performed using McNemar's test for matched-pair binary data. For rare events (urinary retention and respiratory depression), exact P-values were obtained from the binomial distribution (two-tailed). No test statistics are reported as McNemar's test does not provide a chi-square value in 2 × 2 tables.
| Dependent Variable | Independent Variable | β | Standardized β | 95% CI | P-value |
| QoL improvement (ΔEORTC functional domain) | Study group (vs. Control group) | 14.042 | 0.387 | 8.03, 20.06 | <0.001 |
| Age (per 10-year increase) | 0.146 | 0.095 | -0.12, 0.41 | 0.277 | |
| Female (vs. Male) | -5.551 | -0.152 | -11.74, 0.64 | 0.078 | |
| Baseline NRS score (per 1-point increase) | 2.694 | 0.178 | 0.17, 5.22 | 0.037 | |
| Bone metastasis (vs. No bone metastasis) | -0.126 | -0.003 | -6.55 6.30 | 0.969 | |
| ECOG score 2-4 (vs. 0-1) | 1.708 | 0.047 | -4.44, 7.86 | 0.583 | |
| Anxiety improvement (ΔHADS-A) | Study group (vs. Control group) | -3.295 | -0.348 | -4.37, -2.22 | <0.001 |
| Age (per 10-year increase) | 0.014 | 0.036 | -0.03, 0.06 | 0.535 | |
| Female (vs. Male) | -0.42 | -0.044 | -1.50, 0.66 | 0.445 | |
| Baseline HADS-A score (per 1-point increase) | -0.993 | -0.688 | -1.16, -0.83 | <0.001 | |
| Depression improvement (ΔHADS-D) | Study group (vs. Control group) | -3.078 | -0.37 | -4.08, -2.08 | <0.001 |
| Age (per 10-year increase) | -0.019 | -0.052 | -0.06, 0.02 | 0.391 | |
| Female (vs. Male) | 0.067 | 0.008 | -0.96, 1.09 | 0.897 | |
| Baseline HADS-D score (per 1-point increase) | -0.904 | -0.681 | -1.07, -0.74 | <0.001 |
Table 7: Multiple linear regression: predictors of improved quality of life and mental health. ΔEORTC functional domain = post-treatment minus pre-treatment; positive values indicate improved quality of life. ΔHADS = post-treatment minus pre-treatment; negative values indicate reduced anxiety/depression. Models adjusted for all variables listed. QoL model: R2 = 0.212, adjusted R2 = 0.170, F = 5.070, P < 0.001. Anxiety model: R2 = 0.621, adjusted R2 = 0.607, F = 47.043, P < 0.001. Depression model: R2 = 0.575, adjusted R2 = 0.560, F = 38.940, P < 0.001. Abbreviations: EORTC = European Organization for Research and Treatment of Cancer; HADS = Hospital Anxiety and Depression Scale.
| Analytical Method | Primary Outcome | Mean Difference (95% CI) | P-value |
| Primary analysis | |||
| PSM 1:1 nearest neighbor matching | NRS score | −1.4 (−1.9 to −0.9) | <0.001 |
| EORTC functional domain | +13.2 (8.3 to 18.1) | <0.001 | |
| HADS anxiety | −3.3 (−4.4 to −2.2) | <0.001 | |
| Alternative matching/weighting methods | |||
| Kernel matching | NRS score | −1.5 (−1.9 to −1.1) | <0.001 |
| EORTC functional domain | +13.1 (8.1 to 18.1) | <0.001 | |
| Inverse probability of treatment weighting (IPTW) | NRS score | −1.5 (−1.9 to −1.1) | <0.001 |
| EORTC functional domain | +12.8 (7.9 to 17.7) | <0.001 | |
| Subgroup analyses (NRS score) | |||
| Stratified by tumor type | |||
| Lung cancer | NRS score | −1.5 (−2.0 to −1.0) | <0.001 |
| Gastrointestinal cancer | NRS score | −1.5 (−2.3 to −0.6) | 0.001 |
| Breast cancer | NRS score | −1.0 (−1.7 to −0.3) | 0.008 |
| Other | NRS score | −0.7 (−1.3 to −0.1) | 0.027 |
| Stratified by baseline pain intensity | |||
| Moderate pain (NRS 4–6) | NRS score | −1.8 (−2.5 to −1.0) | <0.001 |
| Severe pain (NRS 7–10) | NRS score | −1.7 (−2.4 to −1.0) | <0.001 |
Table 8: Sensitivity analysis results. Mean difference represents the difference between the study group and the control group (Study − Control). Negative values indicate greater improvement in the study group for pain outcomes; positive values indicate greater improvement in the study group for quality of life. EORTC functional domain and HADS trends were consistent with primary analyses (HADS data not shown in this table for brevity). Abbreviations: PSM = propensity score matching; IPTW = inverse probability of treatment weighting; EORTC = European Organization for Research and Treatment of Cancer; HADS = Hospital Anxiety and Depression Scale; NRS = Numerical Rating Scale.
Discussion
Employing PSM in a retrospective cohort, we examined associations in pain control, quality of life, and psychological well-being between advanced cancer patients managed with multimodal pain therapy and those receiving standard pharmacologic analgesia alone. After 2 weeks of intervention, the comprehensive pain management cohort was associated with more favorable outcomes compared to controls, including diminished pain intensity, elevated pain relief rates, superior quality of life, reduced anxiety and depression, and slower opioid dose progression. Adverse event rates did not differ significantly between groups. Multiple regression analysis suggested that receiving comprehensive pain management was independently associated with improved patient outcomes after adjusting for measured confounders, and the strength of the association varied across treatment modalities. Consistency was observed between the results of multiple sensitivity analyses and the primary analysis. Taken together, these findings suggest associations rather than causal effects, a fundamental limitation of the retrospective observational design.
Comprehensive pain management recipients achieved lower NRS scores and higher posttreatment response rates, which were associated with superior analgesia—a finding that aligns with prior research. A multicenter study by Tagami et al.22 showed that specialized palliative care based on patient-reported outcomes enabled 87.9% of patients to achieve the goal of pain management, and the median remission time was only 3 days, which was significantly better than traditional single-drug treatment. In the study of neuropathic cancer pain, Barbaro et al.23 also found that the integration of anticonvulsant drugs and interventional therapy could further reduce the intensity of pain. The comprehensive management cohort exhibited a reduced frequency of undertreated pain compared to controls, a finding that parallels earlier research and supports the potential of multimodal approaches to minimize analgesic inadequacy. In addition, the increase of opioid dose in patients receiving comprehensive management (47.26%) was less than that in the control group (65.27%), suggesting that comprehensive management may be associated with slower opioid dose escalation while achieving superior analgesic efficacy. Possible explanations for this association include: interventional oncology directly targets the etiology of pain, thereby reducing pain stimuli at the source and decreasing opioid demand24; psychological counseling may improve patients' pain perception and coping ability, enhancing the efficiency of analgesic utilization25. Multimodal treatment may achieve the "opioid sparing effect" through synergistic action. Similar findings have emerged from multidisciplinary pain management studies. Ferron et al.26 reported that comprehensive pain management programs were associated with reduced opioid use across all patients, with two-thirds completely discontinuing opioids. Kwon et al.27 also demonstrated that interdisciplinary interventions were associated with a significant reduction in opioid doses after 12 months. Patients receiving multimodal pain therapy demonstrated better quality-of-life outcomes on the EORTC QLQ-C30, with improved functional status and reduced symptom severity compared with controls. Patients with advanced cancer often face multiple interrelated challenges, including physical pain, functional limitations, and psychological distress. Comprehensive management, through multidisciplinary collaboration, may be associated with more comprehensive responsiveness to patients' multidimensional needs. In this study, the independent correlation of tumor interventional therapy, psychological counseling, and palliative care support with quality-of-life improvement was statistically significant, suggesting that different treatment modalities may contribute to overall patient comfort through distinct pathways. This finding is consistent with Temel et al.28, in which multidisciplinary approaches were associated with superior quality-of-life outcomes among patients with advanced lung cancer. Parallel findings emerged from real-world observations, in which patients managed with a multidisciplinary approach experienced more pronounced improvements in quality of life. Unlike the Temel study, among the treatment measures examined in our cohort, oncology intervention emerged as the factor most strongly correlated with gains in functional status, while psychological counseling was more closely associated with improvement in the emotional dimension. This aligns with Li et al.14, who reported that multidisciplinary palliative care enhances quality of life primarily through symptom control and psychological adaptation. Patients who received comprehensive pain management had lower HADS anxiety and depression scores, suggesting that comprehensive pain management was associated with better mental health. Cancer pain, anxiety, and depression often interact bidirectionally. Psychological counseling, as a component of comprehensive management, showed a strong correlation with improvement in anxiety and depression in this study, with a standardized regression coefficient higher than that for the overall study group, suggesting that psychological counseling may be the modality most closely related to mental health improvement. This observation is consistent with the conclusions of previous meta-analyses. The systematic review by Wang et al.29 showed that cognitive behavioral therapy can significantly reduce the anxiety (SMD = -0.61) and depression (SMD = -0.83) scores of cancer patients. Luo et al.30 's randomized controlled study on patients with advanced cancer also showed that 6 weeks of mindfulness-based stress reduction training could significantly reduce the HADS score, and the improvement effect lasted for 3 months after treatment. In this study, palliative care support was also independently correlated with anxiety improvement, suggesting that life-review and family meetings may contribute to psychological pain relief by enhancing mental comfort. This is consistent with Saracino et al.31, who found that meaning-centered therapy effectively alleviated existential distress and anxiety in patients with advanced cancer.
We acknowledge that the study group was heterogeneous, encompassing four distinct adjunctive modalities, and that the sample sizes for individual modalities—particularly hyperthermia (n = 18)—limited our ability to detect independent effects. Rather than interpreting these modalities as isolated variables, we suggest that the benefits of comprehensive pain management may arise from synergistic interactions among multiple components. Interventional oncology directly targets the etiology of pain, psychological counseling addresses maladaptive cognitions and emotional distress, and palliative care provides comprehensive symptom management and psychosocial support. These components may produce additive or synergistic effects that collectively enhance pain control, functional status, and psychological well-being beyond what any single modality could achieve alone. This integrative perspective aligns with the biopsychosocial model of pain, which emphasizes the interplay of biological, psychological, and social factors in shaping pain experience and treatment response. Multivariable regression analysis using the full matched cohort demonstrated that comprehensive pain management (study group) was independently correlated with significant improvements in quality of life, anxiety, and depression after controlling for demographic characteristics and clinical variables. These findings have clinical plausibility. The multimodal approach may achieve its benefits through multiple complementary mechanisms. First, interventional oncology components directly target the etiology of pain, reducing tumor compression and periosteal erosion, thereby potentially enhancing the functional dimension of quality of life by improving physical function. Chen et al.32 reported, via multivariable logistic analysis, that radiotherapy recipients achieved significantly higher pain relief rates than non-recipients (100% vs 60.8%). Multivariable analysis by Canon et al.33 also confirmed that response to radiotherapy was an independent correlate of improvements in physical function, mood, and life enjoyment. According to the International Association for the Study of Pain (IASP) pain classification framework, nociceptive pain generally responds better to etiological treatment than to symptom suppression alone. Second, psychological counseling, a core component of the comprehensive protocol, directly targets emotion-regulation mechanisms and may contribute to improved mental health by modifying catastrophizing cognitions and enhancing self-efficacy. Rooney et al.34 demonstrated that individual pain beliefs and coping strategies critically modulate pain experience. The strong correlation between the comprehensive management and HADS improvement in the present study supports this theoretical framework. Third, the inclusion of palliative care support provides multidisciplinary symptom management and psychosocial support, addressing the multidimensional nature of cancer pain that extends beyond nociception to encompass psychological, social, and existential dimensions35. The synergistic combination of these modalities may account for the superior outcomes observed in pain control, quality of life, and psychological well-being among patients receiving comprehensive management. Notably, higher baseline symptom burden—including greater pain intensity (baseline NRS) and greater psychological distress (baseline HADS-A and HADS-D scores)—was associated with more pronounced treatment benefits, suggesting that patients with poorer baseline status may derive particular advantage from the multimodal approach.
This study has the following implications for clinical practice. First, integrating multidisciplinary treatment alongside standard pharmacologic analgesia was associated with better patient outcomes, consistent with current guideline recommendations for "early integration of MDTs." Second, the differential patterns of association between specific treatments and outcomes suggest that clinical decision-making might be tailored to the patient's predominant problem. Third, the lower opioid dose escalation and superior analgesic efficacy observed in the study group are consistent with the application of "multimodal analgesia" concepts in cancer pain management36,37.
Multiple sensitivity analyses yielded findings consistent with the primary analysis. Mean differences remained stable when applying alternative matching algorithms (kernel matching and inverse probability of treatment weighting), suggesting that the findings were not sensitive to the choice of analytical method. Stratified analyses showed that patients with different tumor types and different baseline pain intensities who received comprehensive pain management had greater pain reduction than those in the control group, with consistent directional effects across all subgroups. These observations suggest that the improvements associated with comprehensive pain management were observed across diverse patient populations, supporting the robustness of the study findings. The E-value for the primary outcome (NRS reduction) was 2.56, suggesting that an unmeasured confounder would need to have a risk ratio of 2.56 with both treatment assignment and the outcome—over and above measured covariates—to completely explain away the observed association. According to the E-value interpretation framework proposed by Sjolander et al.38, an E value >2.0 indicates that relatively strong unmeasured confounding would be required to overturn the finding. This E-value is considered acceptable in observational studies, suggesting that the risk of residual confounding is manageable. However, as with all observational research, the possibility of residual confounding by unmeasured factors—such as socioeconomic status, social support, or pain coping styles—cannot be entirely excluded. Taken together, the results of this study appear reasonably robust to the analytical choices made, although causal inferences should be made with caution.
Several limitations should be considered when interpreting these findings. First, as a retrospective observational study, our findings describe associations rather than causal effects. Although PSM was used to control for measured confounders, residual confounding from unmeasured variables—such as socioeconomic status, social support systems, and prior psychiatric history—may have influenced the observed associations. Additionally, confounding by indication is a particular concern in this context: patients who received comprehensive management may have differed from those receiving standard care in ways not fully captured by our covariates, potentially biasing the observed treatment-outcome associations in either direction. Second, the single-center design and modest sample size limit generalizability to other populations and settings, and may also reduce statistical power for subgroup analyses. Third, there was individual variation in the combination and intensity of treatment modalities, and the dose-response relationship across modalities was not explored in depth in this study. Fourth, the two-week follow-up period was relatively short. This timeframe may have captured immediate effects—including potentially "placebo-like" responses to increased clinical attention and multidisciplinary engagement—rather than sustained long-term functional and psychological gains. Longer follow-up is needed in future studies to determine whether the observed improvements are durable over time. Fifth, quality-of-life and mental health assessments relied on patient self-reports; although standardized scales were used, recall and reporting biases may be present. Sixth, this study did not perform stratified analyses by pain mechanism (e.g., nociceptive-dominant vs neuropathic-dominant), and different pain types may respond differently to specific treatments. Notably, the subgroup analyses presented should be interpreted as exploratory rather than confirmatory, given the limited sample size within each subgroup and the absence of prespecified hypotheses. Finally, the generalizability of our findings to other healthcare systems or populations with different demographic or cultural characteristics remains to be established. Based on these findings and limitations, we suggest the following directions for future research: (i) Prospective cohort designs or randomized controlled trials should be employed to further validate these findings and collect more comprehensive information on potential confounders; (ii) multi-center collaborations with larger samples would enhance generalizability and enable more precise effect estimation for individual treatment modalities; (iii) standardized treatment protocols and recording of key implementation parameters would allow exploration of the "optimal dose" and combination strategies for different treatment modalities; (iv) longer follow-up is needed to assess treatment effect durability, alongside health economic evaluations to determine the cost-effectiveness of comprehensive pain management; (v) multidimensional assessment of patient outcomes should incorporate objective indicators (e.g., activity monitoring, physiological parameters) and caregiver reports; (vi) stratified randomized designs based on pain mechanism should be considered to explore individualized treatment strategies.
In conclusion, comprehensive pain management was associated with superior pain control, better quality of life, and improved psychological outcomes in advanced cancer compared to standard analgesia alone. The multimodal approach was also associated with attenuated opioid escalation. These findings suggest that comprehensive pain management may offer a viable real-world strategy for advanced cancer care, with the potential to reduce opioid-related adverse events while maintaining effective analgesia. Prospective studies with longer follow-up are warranted to further assess the durability of these associations.
Disclosures
The authors have no conflicts of interest to declare.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Analgesic Medications | |||
| Acetaminophen (Paracetamol) SR Tablets | Sino-American Tianjin Smith Kline & French Laboratories Ltd. | National Drug Approval No. H12021118 | Non-opioid analgesic for mild cancer pain (Step 1 of WHO ladder) |
| Fentanyl Transdermal Patch | Henan Lingrui Pharmaceutical Co., Ltd. | National Drug Approval No. H20123327 | Fentanyl transdermal patch, a strong opioid analgesic for severe cancer pain |
| Ibuprofen SR Capsules | Sino-American Tianjin Smith Kline & French Laboratories Ltd. | National Drug Approval No. H20123327 | NSAID, non-opioid analgesic for mild cancer pain (Step 1 of WHO ladder) |
| Morphine (sustained-release) | Mundipharma (China) Pharmaceutical Co., Ltd. | National Drug Approval No. HJ20130900–HJ20130904 | Sustained-release morphine sulfate, a strong opioid analgesic for severe cancer pain |
| Oxycodone (OxyContin) | Mundipharma (China) Pharmaceutical Co., Ltd. | National Drug Approval No. HJ20140312–HJ20140325 | Sustained-release oxycodone hydrochloride, a strong opioid analgesic for severe cancer pain |
| Tramadol Hydrochloride SR Tablets (domestic) | North China Pharmaceutical Co., Ltd. | National Drug Approval No. H20020248 | Tramadol hydrochloride, a weak opioid analgesic for moderate cancer pain |
| Assessment Tools | |||
| EORTC QLQ-C30 (Chinese Version) | European Organisation for Research and Treatment of Cancer | N/A | Chinese version of the core quality of life questionnaire for cancer patients, assessing functional and symptom domains |
| Hospital Anxiety and Depression Scale (HADS) | GL Assessment / Mapi Research Trust | N/A | Hospital Anxiety and Depression Scale, assessing anxiety and depression status. |
| Numerical Rating Scale (NRS) | N/A | N/A | Numeric Rating Scale (0-10), assessing pain intensity |
| Statistical Software | |||
| Sample Size Calculation Software | G*Power | Version 3.1.9.7 | Used for a priori power analysis. Free software, available at https://www.psychologie.hhu.de/arbeitsgruppen/allgemeine-psychologie-und-arbeitspsychologie/gpower |
| Statistical Analysis Software | R Foundation for Statistical Computing | R (version 4.3.1) | Used for all data analysis. Open-source software (GPL license), available at https://www.r-project.org/ |
| Statistical Analysis Software | IBM SPSS Statistics | Version 26.0 | Used for all data analysis. Commercial license required; available at https://www.ibm.com/products/spss-statistics |
| Interventional Equipment | |||
| Deep Hyperthermia Unit (High-frequency) | Jilin Mida Medical Equipment Co., Ltd. | National Medical Device Registration No. 20163260187 (NRL-001) | Used for local deep hyperthermia to assist analgesia in patients with pleural/peritoneal effusions or superficial metastatic lesions |
| Medical Linear Accelerator (Vitalbeam) | Varian Medical Systems, Inc. | National Medical Device Registration No. 20163322474 | Used for palliative radiotherapy of bone metastases and soft tissue masses |
References
- Goel V, Kaizer A, Darrow D, Rosielle D. Cancer patients quality of life after intrathecal drug delivery for advanced pain management: a patient-reported outcome analysis. Pain Med. 2025;26:261-8.
- Li Q, et al. A scoping review of breakthrough cancer pain: multidimensional patient needs and influencing factors. Asia Pac J Oncol Nurs. 2025;12:100780.
- Khojayeva K, Aubakirova M, Viderman D. Advanced pain management in patients with terminal cancer. Curr Med Chem. 2025. Epub ahead of print.
- Carbonara L, et al. Adherence to ESMO guidelines on cancer pain management and their applicability to specialist palliative care centers: an observational, prospective, and multicenter study. Pain Pract. 2024. Epub ahead of print.
- Imkamp MSV, Theunissen M, Viechtbauer W, van Kuijk SMJ, van den Beuken-van Everdingen MHJ. Shifting views on cancer pain management: a systematic review and network meta-analysis. J Pain Symptom Manage. 2024;68:223-36.
- Shapoo N, Rehman A, Izaguirre-Rojas C, Gotlieb V, Boma N. Cancer pain is not one-size-fits-all: evolving from tradition to precision. Clin Pract (Basel). 2025;15:173.
- Rezuș II, et al. Minimally invasive techniques versus opioids in patients with unresectable pancreatic cancer: a systematic review and meta-analysis of randomized controlled trials. Transl Gastroenterol Hepatol. 2025;10:45.
- Azizoddin DR, Bulls HW, Kang HA, Enzinger AC. Beyond opioids: a multidisciplinary approach to cancer pain management. JCO Oncol Pract. 2025;21:1545-8.
- Li X, Jia F, Wu P, Wen Q. Multimodal rehabilitation for advanced cancer pain: a narrative review of emerging nonpharmacological strategies. Curr Oncol Rep. 2026;28:3.
- Varrassi G, et al. Advances in the pathophysiology and management of cancer pain: a scoping review. Cancers (Basel). 2026;18:259.
- Yee Kin C. Neural correlates of emotional regulation in response to stress: an fMRI study. Dev Psychol Innov. 2025;1:15-20.
- Oldenburger E, et al. International consensus on palliative radiotherapy endpoints for future clinical trials in bone metastases: a second update. Radiother Oncol. 2026;214:111300.
- Arefian M. Efficacy of two psychological interventions on pain, distress, and post-traumatic growth in breast cancer survivors: a 2-year follow-up of two randomized controlled trials. Eur J Oncol Nurs. 2026;80:103099.
- Li Y, Wang T, Zhang Y, Zhao Y. Effect of nurse-led and physician-led multidisciplinary team palliative care on quality of life, negative emotions, and pain for cancer patients: a meta-analysis. Precis Med Sci. 2025;14:75-84.
- Woo A, et al. Cut points for mild, moderate, and severe pain among cancer and non-cancer patients: a literature review. Ann Palliat Med. 2015;4:176-83.
- Vu CN, Lewis CM, Bailard NS, Kapoor R, Rubin ML, Zheng G. Association between multimodal analgesia administration and perioperative opioid requirements in patients undergoing head and neck surgery with free flap reconstruction. JAMA Otolaryngol Head Neck Surg. 2020;146:708-13.
- Anekar AA, Hendrix JM, Cascella M. WHO analgesic ladder. In: StatPearls. Treasure Island (FL): StatPearls Publishing; 2026.
- Martinsson L, Fransson P, Andersson S. Palliative medicine physicians' experiences using the Numeric Rating Scale for pain assessment in patients with advanced cancer: a qualitative study. BMJ Open. 2026;16:e102830.
- Mao P, et al. Pain and its treatment among outpatients with malignant tumors in China. Cancer Manag Res. 2025;17:1843-50.
- Peykov G, et al. Validation of the Bulgarian versions of the EORTC QLQ-C30 and FACT-G: reliability, construct validity, and agreement in cancer survivors. Eur J Transl Myol. 2025;35:14121.
- Sun H, Lv H, Niu L, Chen S, Zhang Z, Yan M. Distress thermometer and determinants of psychological distress in metastatic breast cancer. BMJ Support Palliat Care. 2026;16:401-6.
- Tagami K, et al. Cancer pain management in patients receiving inpatient specialized palliative care services. J Pain Symptom Manage. 2024;67:27-38.e21.
- Barbaro S, et al. Cancer-induced neuropathic pain: clinical features and treatment options. Cureus. 2025;17:e99374.
- Aman MM, et al. The American Society of Pain and Neuroscience (ASPN) best practices and guidelines for the interventional management of cancer-associated pain. J Pain Res. 2021;14:2139-64.
- Trullols M, Ruiz de Porras V. Opioid use in cancer pain management: navigating the line between relief and addiction. Int J Mol Sci. 2025;26:7459.
- Ferron SM, Clavel AL, Panopoulos GE, Kaper GM, Gustafson SK. Individualized opioid tapering in a community interdisciplinary pain management program with flexible care plans: outcomes, patient retention, and follow-up. J Opioid Manag. 2025;21:281-302.
- Kwon E, et al. A comprehensive, multimodal, interdisciplinary approach to chronic non-cancer pain management in a family medicine clinic: a retrospective cohort review. Perm J. 2021;25:20.307.
- Temel JS, et al. Stepped palliative care for patients with advanced lung cancer: a randomized clinical trial. JAMA. 2024;332:471-81.
- Wang X, Li W, Zhao T, Jin Q, Wang H. Cognitive behavioral therapy's impact on anxiety, depression, and quality of life in patients with head and neck cancer: a systematic review. Front Psychol. 2025;16:1547999.
- Luo X, Miao X, Ding N, Fu Z, Wang X, Li Y. Application of the end-of-life demands card game and mindfulness-based cancer recovery program for reducing negative emotion in patients with advanced lung cancer: a randomized controlled trial. Front Psychol. 2025;16:1476207.
- Saracino RM, et al. A pragmatic randomized controlled pilot trial of brief meaning-centered psychotherapy in home care. Cancer. 2025;131:e70082.
- Chen D, et al. Efficacy of multidisciplinary pain management for advanced cancer patients. Pain Manag Nurs. 2025;26:349-57.
- Cañón V, et al. Quality of life improvement in patients with bone metastases undergoing palliative radiotherapy. Rep Pract Oncol Radiother. 2022;27:428-39.
- Rooney T, Sharpe L, Todd J, Colagiuri B. Cognitive bias modification for interpretation mitigates nocebo hyperalgesia. J Pain. 2026;40:105646.
- Hoveidaei A, Karimi M, Khalafi V, Fazeli P, Hoveidaei AH. Impacts of radiation therapy on quality of life and pain relief in patients with bone metastases. World J Orthop. 2024;15:841-9.
- Davis MP, Bohlke K, Davies A. Opioid conversion in adults with cancer: MASCC-ASCO-AAHPM-HPNA-NICSO guideline clinical insights. J Pain Symptom Manage. 2026;71(2):e141-e144.
- Hwang W. Evolution of pain management in lung cancer surgery: from opioid-based to personalized analgesia. Anesth Pain Med (Seoul). 2025;20:109-20.
- Sjölander A, Ciocănea-Teodorescu I, Gabriel EE. Bounds and E-values for marginal causal effects. Epidemiology. 2026;37:5-15.