This study developed an admission-variable nomogram for early neurological deterioration after minor small subcortical infarction and reported bootstrap internal validation, imaging and treatment sensitivity analyses, and a 24-hlandmark analysis of blood pressure variability.
Research Article
Admission-Parameter Nomogram for Early Neurological Deterioration after Minor Small Subcortical Infarction: A Retrospective Cohort Study
In This Article
Summary
Abstract
Early neurological deterioration (END) was common after minor subcortical infarction, but prediction was complicated by heterogeneous mechanisms, including intrinsic small-vessel disease and branch atheromatous disease (BAD). A retrospective analysis included 240 patients admitted within 24 h of symptom onset with a National Institutes of Health Stroke Scale (NIHSS) score of 5 or less. END was defined as an increase of at least 2 NIHSS points within 72 h after admission. The primary logistic model retained admission systolic blood pressure (SBP) as a continuous variable and included baseline NIHSS, neutrophil-to-lymphocyte ratio (NLR), and vascular stenosis of at least 50%. A three-knot restricted cubic spline was used to assess SBP nonlinearity. Internal validation used 1,000 bootstrap resamples, and calibration used bootstrap out-of-bag predictions. END occurred in 54 of 240 patients (22.5%). For each 10 mmHg increase in SBP, the adjusted odds ratio (OR) was 1.19 (95% confidence interval [CI], 1.04–1.36); the corresponding ORs were 1.36 (1.04–1.78) per NIHSS point, 1.34 (1.10–1.62) per NLR unit, and 2.21 (1.13–4.31) for stenosis. Evidence of SBP nonlinearity was absent (P = 0.595). The primary model had an apparent area under the receiver operating characteristic curve (AUC) of 0.762 (95% bootstrap CI, 0.686–0.826), an optimism-corrected AUC of 0.741, and an out-of-bag Brier score of 0.158. MRI-only, parent-artery-stenosis exclusion, and ischemic-END analyses were directionally consistent. Suspected BAD was present in 83.3% of END cases and materially increased performance in an expanded exploratory model, emphasizing etiologic heterogeneity. In a 24-h landmark analysis, the addition of SBP variability improved discrimination for deterioration after 24 h, but these post-admission metrics were not included in the admission-only model. The nomogram provided an internally validated prognostic estimate for enhanced monitoring and reassessment; external validation was required before treatment selection or bedside implementation.
Introduction
Acute ischemic stroke remained a major cause of death and long-term disability worldwide1. A low baseline National Institutes of Health Stroke Scale (NIHSS) score was often described as a minor stroke, but “minor” reflected the measured deficit at presentation rather than biological stability or the absence of disability. Initially, mild weakness, gait impairment, dysarthria, or loss of hand function could worsen during the first h or days. This early neurological deterioration (END) could alter monitoring needs, diagnostic reassessment, rehabilitation planning, and prognosis. In lacunar or small subcortical stroke, pooled data indicated that END occurred in approximately one-fifth to one-quarter of patients; an increase of at least 2 NIHSS points was the most frequently used threshold and produced comparatively consistent estimates2. Patients who deteriorated had worse functional outcomes than those who remained stable3.
The definition of the underlying phenotype also required care. Small subcortical infarction described an anatomic pattern, small-artery occlusion was an etiologic classification, and a lacunar syndrome was a clinical presentation. These concepts overlapped but were not interchangeable. A compatible syndrome could arise from an intrinsic perforator lesion, plaque at a penetrating-artery origin, or parent-artery atherosclerosis, and routine classification could not always distinguish these mechanisms4. Lipohyalinosis, microatheroma, thrombus propagation, impaired collateral supply, and parent-artery disease could coexist5,6. Branch atheromatous disease (BAD), often inferred from a lesion at least 15 mm in diameter, involvement of at least three axial slices, or extension to the ventral pontine surface, was particularly associated with progression7. Magnetic resonance diffusion-weighted imaging improved lesion confirmation, whereas computed tomography could exclude hemorrhage without directly visualizing a small acute subcortical infarct. Accordingly, the broader term “minor small subcortical infarction” was used, and imaging-related and BAD-related uncertainty was explicitly examined.
Deep perforating arteries had limited collateral connections, and a small increase in lesion volume could interrupt densely packed strategic pathways. END could therefore reflect extension of ischemia, thrombus propagation along a perforator, edema, recurrent ischemia, or fluctuating perfusion. Ischemia-related inflammation and endothelial injury could further amplify tissue damage8. Although these mechanisms were not directly measured using a bedside model, routinely available clinical, laboratory, and vascular variables could serve as practical markers of tissue vulnerability.
Admission blood pressure (BP) was one such marker, but its interpretation was complex. Higher systolic BP (SBP) could represent chronic hypertension, acute stress, or compensation to preserve perfusion; excessive pressure could also contribute to endothelial and blood–brain barrier stress when autoregulation was impaired9,10. The association was therefore prognostic rather than necessarily causal. Baseline NIHSS, when complemented by SBP, summarized initial neurological severity and could indirectly reflect lesion burden or strategic pathway involvement. Modeling SBP continuously avoided assuming that a single data-derived cutoff separated low- and high-risk patients, whereas an assessment of nonlinearity could determine whether a simple linear trend was adequate.
Inflammatory and vascular measurements could add further information. The neutrophil-to-lymphocyte ratio (NLR) was inexpensive, rapidly available, and summarized the balance between circulating neutrophils and lymphocytes. Higher NLR has been associated with END, although it remains a nonspecific marker influenced by infection, physiological stress, and comorbidity11. Recorded arterial stenosis could indicate atherosclerotic burden, compromised inflow, or a parent-artery mechanism in an apparent lacunar presentation. Combining SBP, baseline NIHSS, NLR, and stenosis could therefore represent hemodynamic, clinical, inflammatory, and vascular dimensions of risk without specialized biomarkers.
BP also changed after admission. Short-term BP variability had been associated with END12, potentially through unstable perfusion when autoregulation was impaired. However, variability indices required repeated measurements, were unavailable at admission, and could be affected by deterioration or treatment. Directly adding these indices to a baseline model would have created a temporal mismatch. A 24-h landmark analysis among patients who remained free of END could instead assess whether accumulated BP information improved the prediction of later deterioration.
Published END scores were derived from different populations and cannot be assumed to transfer directly to the cohort. A progressive lacunar stroke score used diabetes, diastolic BP, pure motor syndrome, and asymptomatic intracranial atheromatosis13, whereas an END-of-ischemic-origin score for thrombolysed minor stroke with large-vessel occlusion used occlusion site and thrombus length14. These predictors reflected different mechanisms, treatments, and eligibility criteria. Furthermore, an apparent development-sample advantage of a multivariable model could diminish after correction for overfitting. Internal validation, calibration assessment, and sensitivity analyses were therefore needed before bedside application or comparison with existing tools.
The retrospective cohort was reanalyzed to develop an admission-variable nomogram for END after minor small subcortical infarction. The analysis was designed to report imaging, acute treatment, missing-data, and outcome-ascertainment procedures transparently; retain continuous SBP, assess nonlinearity, and quantify internal optimism; and test robustness in MRI-only, parent-artery-stenosis, BAD, ischemic-END, and treatment-adjusted analyses. A separate 24-hlandmark analysis distinguished dynamic prediction using BP variability from baseline prediction. Admission SBP, baseline NIHSS, NLR, and recorded vascular stenosis were hypothesized to provide complementary prognostic information. The model was intended to support enhanced observation and timely reassessment, not to establish causality, mandate treatment, or imply improved outcomes without prospective external validation.
Protocol
The study was conducted in accordance with the Declaration of Helsinki and was approved by the institutional ethics committee of Jinhua Municipal Central Hospital (No. 2022129). The requirement for written informed consent was waived because only retrospective, de-identified data were analyzed. The research tools used in this protocol are listed in the Table of Materials.
1. Study design and source population
A retrospective observational cohort study was conducted at the comprehensive stroke center of Jinhua Municipal Central Hospital, Zhejiang, China. Consecutive admissions from June 2024 through September 2025 were screened. Patients were included if they had been admitted within 24 h of symptom onset, had a baseline NIHSS score of 5 or less, and had received a treating-team diagnosis of minor ischemic stroke compatible with a small subcortical or perforator-territory process. Patients were excluded for other documented etiologic subtypes, a baseline NIHSS score greater than 5, an onset-to-admission time greater than 24 h, severe pre-existing neurological dysfunction or severe systemic disease, or incomplete core clinical or imaging data. Every exclusion was recorded in the flow diagram.
2. Etiologic classification and brain imaging
The etiologic classification assigned during routine care by the treating stroke team was abstracted. Because this was a retrospective electronic-record study, the assignment was not considered prospective, centralized, blinded, or independently re-adjudicated. For MRI-confirmed cases, an acute subcortical lesion compatible with the neurological syndrome on diffusion-weighted imaging, with a corresponding apparent diffusion coefficient abnormality and no cortical infarction, was required. For CT-only cases, exclusion of hemorrhage and a cortical territorial infarct, together with a compatible lacunar clinical syndrome, was required. CT alone was acknowledged as potentially unable to directly confirm a small acute subcortical infarct.
Imaging modality, onset-to-imaging time, maximum lesion diameter, slice thickness, number of involved axial slices, ventral pontine surface involvement, parent-artery stenosis, and nonculprit stenosis were recorded. Suspected BAD was operationalized as any of the following: a maximum lesion diameter of at least 15 mm, involvement of at least three axial slices, or ventral pontine surface involvement. Detailed lesion side, anatomic location, responsible artery segment, and a traceable, independent, blinded reread were unavailable and were not imputed.
3. Angiographic assessment of stenosis
CTA or MRA stenosis measurements were abstracted from the clinical imaging reports. The percentage of intracranial stenosis was calculated using the WASID formula:
[1 - (diameter at the narrowest lumen
/diameter of the adjacent normal reference artery)] x 10015
Parent-artery stenosis was defined as narrowing of at least 50% in the artery supplying the infarct territory. Nonculprit stenosis was defined as narrowing of at least 50% outside that territory. The primary model variable, any vascular stenosis of at least 50%, was considered positive if either component was positive. Because the responsible artery segment was not retained, segment-specific measurements could not be independently verified.
4. Baseline clinical, laboratory, and treatment variables
Age, sex, vascular history, smoking, alcohol use, pre-stroke antiplatelet use, pre-stroke modified Rankin Scale score, onset-to-admission time, admission SBP and diastolic BP (DBP), baseline NIHSS, platelet count, blood glucose, neutrophil count, lymphocyte count, and blood-draw time were extracted. NLR was calculated as the absolute neutrophil count divided by the absolute lymphocyte count.
Intravenous thrombolysis, single versus dual antiplatelet strategy, treatment-start time after admission, statin intensity, in-hospital BP-lowering treatment, glucose management, anticoagulation, and the recorded timing of antithrombotic exposure relative to blood collection were reported. No participant received in-hospital anticoagulation. Intravenous fluid volume was not included because it was not reliably recoverable. These interventions were treated as potential confounders or consequences of the clinical state rather than randomized exposures.
5. Neurological assessments and END
NIHSS scores documented at admission, approximately 24 and 72 h were used, and additional assessments triggered by clinical worsening were included. The scores were recorded by the routine stroke team. Predictor blinding and centralized duplicate scoring were not documented. Primary END was defined as an increase of at least 2 total NIHSS points within 72 h after admission relative to baseline, consistent with contemporary lacunar-stroke literature2,3. The time and documented cause of deterioration were recorded. All-cause qualifying deterioration was included in the primary outcome, and the model was repeated using ischemic-cause END only.
6. Missing-data handling
Missingness was audited before analysis. For three records with a missing raw NLR value but available neutrophil and lymphocyte counts, NLR was calculated deterministically. For four records with a missing raw 24-h SBP SD but available mean SBP and coefficient of variation, SD was calculated as coefficient of variation × mean SBP. After these deterministic derivations, the four primary predictors and the outcome were complete, and all 240 patients were included in the primary model without multiple imputation. The single record with a missing pre-blood-draw antithrombotic status was excluded only from the treatment-adjusted exploratory model.
7. Statistical analysis and model development
Approximately symmetric continuous variables were summarized as mean ± SD, and skewed or ordinal variables were summarized as median (interquartile range). Welch t tests or Mann–Whitney U tests were used as appropriate. Categorical variables were summarized as n (%) and compared using chi-square or Fisher's exact tests.
The primary logistic regression model included continuous admission SBP scaled per 10 mmHg, baseline NIHSS per point, NLR per unit, and any vascular stenosis of at least 50%. The intercept, coefficients, standard errors, ORs, 95% CIs, and two-sided P values were reported. SBP nonlinearity was examined using a restricted cubic spline with three knots at the 10th, 50th, and 90th percentiles (130.9, 157.0, and 194.0 mmHg), adjusted for NIHSS, NLR, and stenosis. A likelihood-ratio test was used for the nonlinear term. The linear SBP term was used when nonlinearity was not supported.
An SBP threshold of 169 mmHg was retained only as a secondary simplified analysis. The threshold was selected using the maximum Youden index in the development data, and cutoff uncertainty was quantified using 1,000 bootstrap resamples. The unvalidated 0–12 score and low-, intermediate-, and high-risk categories were not reinstated.
Discrimination was estimated using the AUC and 95% bootstrap CI. The combined model was compared with each component using paired bootstrap differences, and superiority was not claimed when the difference CI included zero. Optimism was estimated using 1,000 bootstrap resamples. Out-of-bag bootstrap predictions were generated for calibration and calculation of the Brier score. Decision-curve analysis was conducted only across threshold probabilities of 5%–30%, for which the modeled action was enhanced neurological observation and clinician reassessment rather than automatic treatment.
Sensitivity analyses were performed in the MRI-only cohort, after exclusion of parent-artery stenosis of at least 50%, after exclusion of suspected BAD, and using ischemic-cause END only. Exploratory ridge-penalized expanded models containing imaging, onset-time, and treatment variables were fitted to reduce instability. In a 24-hlandmark analysis, patients who deteriorated before 24 hwere removed, and a landmark model was compared with models that added SBP SD, coefficient of variation (CV), or average real variability (ARV). These models were interpreted as dynamic post-admission predictions. Transparent prediction-model reporting principles were followed16. The reproducible revision analysis was performed using Python 3.13.5, pandas 2.3.3, NumPy 2.3.3, and SciPy 1.16.2.
Results
Cohort and baseline characteristics
Of 965 screened patients, 240 were included (Figure 1). Among the included patients, 194 (80.8%) underwent MRI, and 46 (19.2%) were classified using CT-only imaging. END occurred in 54 patients (22.5%). Baseline NIHSS was 3 (IQR, 2–4) in the END group and 2 (IQR, 1–3) in the no-END group (P < 0.001). NLR was 3.2 (IQR, 2.7–4.3) and 2.3 (IQR, 1.8–3.2), respectively (P < 0.001). Admission SBP was 169.1 ± 25.8 mmHg in the END group and 156.5 ± 24.5 mmHg in the no-END group (P = 0.002). Any vascular stenosis of at least 50% was present in 31/54 patients (57.4%) in the END group and 69/186 patients (37.1%) in the no-END group (P = 0.008). Suspected BAD was present in 45/54 patients (83.3%) in the END group and 41/186 patients (22.0%) in the no-END group (P < 0.001). Median treatment-start time after admission was 2.7 h(IQR, 2.0–3.9) in the END group and 3.2 h(IQR, 2.1–4.9) in the no-END group (P = 0.104). No participant received in-hospital anticoagulation. Baseline clinical, imaging, and treatment characteristics were reported in Table 1.
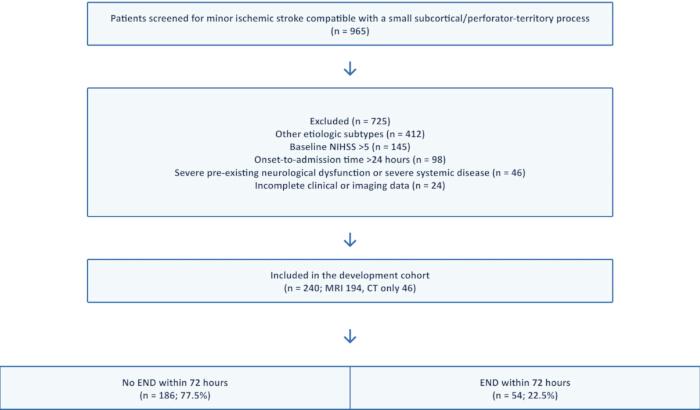
Figure 1: Study cohort flow. Of 965 screened patients, 725 were excluded, and 240 entered the development cohort; 194 underwent MRI, and 46 were classified using CT only. The cohort included 186 patients without END and 54 patients with END within 72 h. Values are presented as n or n (%). Please click here to view a larger version of this figure.
| Characteristic | Overall (n = 240) | No END (n = 186) | END (n = 54) | P value | Missing, n |
| Age, years | 63.4 ± 11.1 | 63.6 ± 11.4 | 62.9 ± 10.2 | 0.665 | 0 |
| Male sex | 159 (66.2%) | 128 (68.8%) | 31 (57.4%) | 0.119 | 0 |
| Hypertension | 145 (60.4%) | 114 (61.3%) | 31 (57.4%) | 0.607 | 0 |
| Diabetes mellitus | 61 (25.4%) | 44 (23.7%) | 17 (31.5%) | 0.245 | 0 |
| Coronary heart disease | 13 (5.4%) | 10 (5.4%) | 3 (5.6%) | 1 | 0 |
| Previous stroke/TIA | 23 (9.6%) | 17 (9.1%) | 6 (11.1%) | 0.665 | 0 |
| Current smoking | 101 (42.1%) | 79 (42.5%) | 22 (40.7%) | 0.82 | 0 |
| Alcohol use | 77 (32.1%) | 58 (31.2%) | 19 (35.2%) | 0.579 | 0 |
| Prestroke antiplatelet use | 25 (10.4%) | 22 (11.8%) | 3 (5.6%) | 0.184 | 0 |
| Onset-to-admission time, hours | 12.9 (7.9–17.7) | 13.4 (8.1–18.3) | 12.1 (6.4–14.9) | 0.046 | 0 |
| Admission SBP, mmHg | 159.3 ± 25.3 | 156.5 ± 24.5 | 169.1 ± 25.8 | 0.002 | 0 |
| Admission DBP, mmHg | 89.6 ± 15.9 | 87.9 ± 15.2 | 95.4 ± 16.7 | 0.004 | 0 |
| Baseline NIHSS score | 2.0 (1.0–3.0) | 2.0 (1.0–3.0) | 3.0 (2.0–4.0) | <0.001 | 0 |
| NLR | 2.6 (1.9–3.5) | 2.3 (1.8–3.2) | 3.2 (2.7–4.3) | <0.001 | 0 |
| Platelet count, ×10⁹/L | 207.0 ± 57.7 | 204.3 ± 55.6 | 216.3 ± 64.2 | 0.216 | 0 |
| Blood glucose, mmol/L | 5.1 (4.5–6.3) | 5.0 (4.5–6.1) | 5.5 (4.6–7.1) | 0.042 | 0 |
| MRI used for index-infarct classification | 194 (80.8%) | 151 (81.2%) | 43 (79.6%) | 0.799 | 0 |
| CT used for index-infarct classification | 46 (19.2%) | 35 (18.8%) | 11 (20.4%) | 0.799 | 0 |
| Maximum lesion diameter, mm | 12.4 (10.3–15.0) | 12.1 (9.9–13.7) | 17.2 (13.2–20.2) | <0.001 | 0 |
| Suspected branch atheromatous disease | 86 (35.8%) | 41 (22.0%) | 45 (83.3%) | <0.001 | 0 |
| Parent-artery stenosis ≥50% | 26 (10.8%) | 16 (8.6%) | 10 (18.5%) | 0.039 | 0 |
| Nonculprit stenosis ≥50% | 74 (30.8%) | 53 (28.5%) | 21 (38.9%) | 0.145 | 0 |
| Any vascular stenosis ≥50% | 100 (41.7%) | 69 (37.1%) | 31 (57.4%) | 0.008 | 0 |
| Intravenous thrombolysis | 35 (14.6%) | 27 (14.5%) | 8 (14.8%) | 0.956 | 0 |
| Dual antiplatelet therapy | 127 (52.9%) | 102 (54.8%) | 25 (46.3%) | 0.268 | 0 |
| Single antiplatelet therapy | 113 (47.1%) | 84 (45.2%) | 29 (53.7%) | 0.268 | 0 |
| High-intensity statin | 170 (70.8%) | 129 (69.4%) | 41 (75.9%) | 0.35 | 0 |
| In-hospital BP-lowering treatment | 113 (47.1%) | 79 (42.5%) | 34 (63.0%) | 0.008 | 0 |
| Glucose-management intervention | 18 (7.5%) | 16 (8.6%) | 2 (3.7%) | 0.378 | 0 |
| Treatment-start time after admission, hours | 3.1 (2.1–4.7) | 3.2 (2.1–4.9) | 2.7 (2.0–3.9) | 0.104 | 0 |
| In-hospital anticoagulation | 0 (0.0%) | 0 (0.0%) | 0 (0.0%) | NA | 0 |
| Recorded antithrombotic exposure before blood draw | 201 (84.1%) | 153 (82.7%) | 48 (88.9%) | 0.274 | 1 |
| Values are mean ± SD, median (IQR), or n (%), as indicated. P values were obtained using the Welch t test, Mann–Whitney U test, chi-square test, or Fisher exact test, as appropriate. Missing, n gives unavailable records. Treatment-start time is measured after admission. Anticoagulation was absent in all participants; no between-group P value was calculated. BAD, branch atheromatous disease; BP, blood pressure; CT, computed tomography; DBP, diastolic blood pressure; END, early neurological deterioration; IQR, interquartile range; MRI, magnetic resonance imaging; NIHSS, National Institutes of Health Stroke Scale; NLR, neutrophil-to-lymphocyte ratio; SBP, systolic blood pressure; SD, standard deviation; TIA, transient ischemic attack. | |||||
Table 1: Baseline clinical, imaging, and treatment characteristics. Approximately symmetric variables are presented as mean ± SD, skewed or ordinal variables as median (IQR), and categorical variables as n (%). Treatment-start time was measured in h after admission. Anticoagulation was absent in all participants; therefore, no between-group P value was calculated.
Values are mean ± SD, median (IQR), or n (%), as indicated. P values were obtained using the Welch t test, Mann–Whitney U test, chi-square test, or Fisher exact test, as appropriate. Missing n gives unavailable records. Treatment-start time is measured after admission. Anticoagulation was absent in all participants; no between-group P value was calculated. BAD, branch atheromatous disease; BP, blood pressure; CT, computed tomography; DBP, diastolic blood pressure; END, early neurological deterioration; IQR, interquartile range; MRI, magnetic resonance imaging; NIHSS, National Institutes of Health Stroke Scale; NLR, neutrophil-to-lymphocyte ratio; SBP, systolic blood pressure; SD, standard deviation; TIA, transient ischemic attack.
Primary model, spline analysis, nomogram, and simplified threshold
The three-knot restricted cubic spline did not support a nonlinear association between SBP and END (likelihood-ratio P = 0.595; Figure 2). Continuous linear SBP was therefore retained in the primary model. The secondary 169 mmHg threshold had a sensitivity of 53.7% and a specificity of 72.0%. Its 95% bootstrap interval was 153–183 mmHg, indicating cohort dependence. In the simplified binary-SBP model, SBP of at least 169 mmHg was associated with an OR of 2.69 (95% CI, 1.38–5.23; P = 0.004) after adjustment for NIHSS, NLR, and stenosis (Supplementary Table 1).
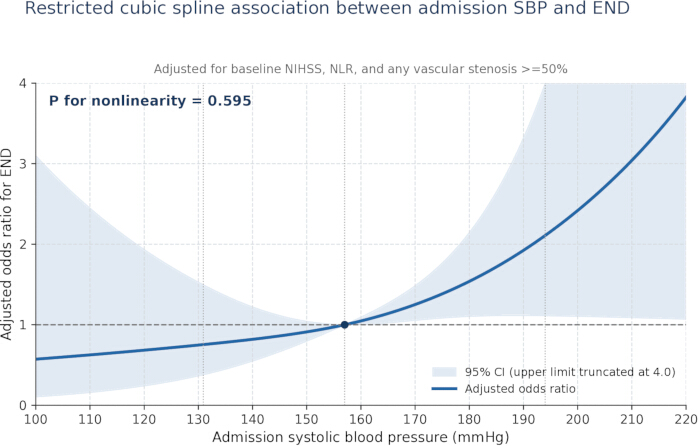
Figure 2: Restricted cubic spline association between admission SBP and END. The analysis included 240 participants and 54 END events. Three knots were placed at 130.9, 157.0, and 194.0 mmHg; 157.0 mmHg was the reference. Adjusted ORs and 95% Wald CIs were estimated after adjustment for baseline NIHSS, NLR, and any stenosis of at least 50%. The test for nonlinearity was not significant (P = 0.595). Please click here to view a larger version of this figure.
SBP and DBP were moderately correlated (Pearson r = 0.71). In the joint SBP–DBP sensitivity model, SBP was not independently associated with END (OR, 1.04 per 10 mmHg; 95% CI, 0.86–1.26; P = 0.689), whereas DBP was borderline (OR, 1.35 per 10 mmHg; 95% CI, 0.99–1.84; P = 0.058). Baseline NIHSS, NLR, and stenosis remained associated with END in the joint model (Supplementary Table 2).
In the primary multivariable logistic model, the intercept was −6.1206 (SE, 1.2121). The OR per 10 mmHg higher SBP was 1.19 (95% CI, 1.04–1.36; P = 0.012). The ORs were 1.36 (95% CI, 1.04–1.78; P = 0.024) per NIHSS point, 1.34 (95% CI, 1.10–1.62; P = 0.003) per NLR unit, and 2.21 (95% CI, 1.13–4.31; P = 0.020) for any vascular stenosis of at least 50% (Table 2). The fitted equation was logit(p) = −6.1206 + 0.1715 × (SBP/10) + 0.3080 × NIHSS + 0.2917 × NLR + 0.7935 × stenosis and was translated into the admission-variable nomogram (Figure 3).
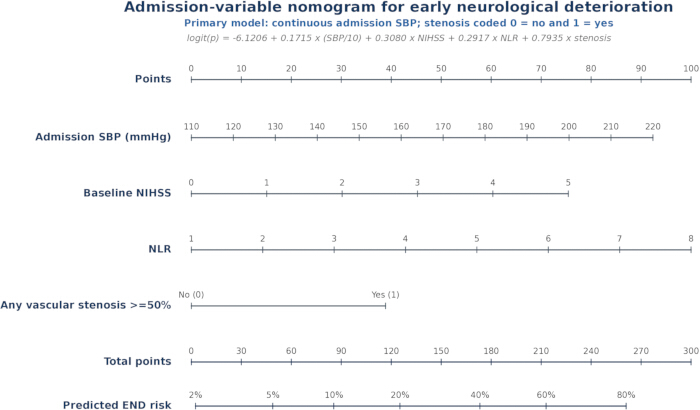
Figure 3: Admission-variable nomogram. The nomogram was fitted to 240 participants with 54 END events, and continuous SBP, baseline NIHSS, NLR, and stenosis status were converted into points and predicted probability. The exact logistic equation was printed above the scales. Please click here to view a larger version of this figure.
| Predictor | β | SE | OR | 95% CI lower | 95% CI upper | P value |
| Intercept | -6.120568721 | 1.212085806 | 0.002197206 | 0.000204231 | 0.023638453 | <0.001 |
| SBP (per 10 mmHg) | 0.171451155 | 0.068246221 | 1.187026161 | 1.038407784 | 1.356915009 | 0.011996612 |
| Baseline NIHSS (per point) | 0.308032832 | 0.136179749 | 1.360745664 | 1.041977682 | 1.777033036 | 0.023700017 |
| NLR (per unit) | 0.291674855 | 0.09812684 | 1.338667686 | 1.104448646 | 1.622557264 | 0.002954556 |
| Any vascular stenosis ≥50% | 0.793451391 | 0.341145581 | 2.211014347 | 1.132928703 | 4.314997432 | 0.020026876 |
Table 2: Primary multivariable logistic model. The model included 240 participants and 54 END events. SBP was scaled per 10 mmHg. Coefficients, SEs, ORs, 95% CIs, P values, and the intercept permit independent calculation.
The model included n = 240 participants and 54 END events. SBP was scaled per 10 mmHg. CI, confidence interval; END, early neurological deterioration; NIHSS, National Institutes of Health Stroke Scale; NLR, neutrophil-to-lymphocyte ratio; OR, odds ratio; SBP, systolic blood pressure; SE, standard error.
Discrimination, calibration, and decision analysis
Among 240 participants with 54 END events, the apparent AUC of the primary model was 0.762 (95% bootstrap CI, 0.686–0.826), and the optimism-corrected AUC was 0.741. Individual AUCs were 0.648 (95% bootstrap CI, 0.560–0.731) for SBP, 0.668 (95% bootstrap CI, 0.592–0.740) for NIHSS, 0.711 (95% bootstrap CI, 0.634–0.781) for NLR, and 0.602 (95% bootstrap CI, 0.524–0.683) for stenosis (Figure 4). Paired bootstrap AUC differences favored the combined model over SBP (difference, 0.114; 95% CI, 0.043–0.186; P < 0.001), NIHSS (difference, 0.095; 95% CI, 0.025–0.169; P = 0.008), and stenosis (difference, 0.161; 95% CI, 0.087–0.240; P < 0.001), but not conclusively over NLR (difference, 0.051; 95% CI, −0.021 – 0.128; P = 0.188).
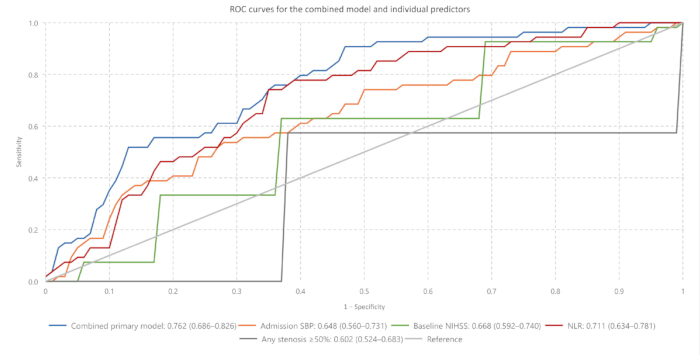
Figure 4: ROC curves for the combined primary model and individual predictors. The analysis included 240 participants and 54 END events. Legend entries report AUCs and 95% percentile CIs from 1,000 nonparametric participant-level bootstrap resamples. Pairwise AUC differences were calculated using the same resampled participant indices for the combined model and each comparator. Please click here to view a larger version of this figure.
Using 1,000 bootstrap iterations, participant-level out-of-bag predictions yielded an AUC of 0.733 and a Brier score of 0.158. Participants were ranked by mean out-of-bag predicted probability and divided into five equal-sized groups of 48 for calibration assessment (Figure 5). The mid-range groups showed sampling variability; therefore, calibration was described as approximate rather than excellent. Decision-curve analysis showed greater net benefit for enhanced neurological monitoring than monitoring all or none across much of the prespecified 5%–30% threshold range (Figure 6). This analysis represented mathematical utility rather than evidence that model-guided monitoring improved outcomes.
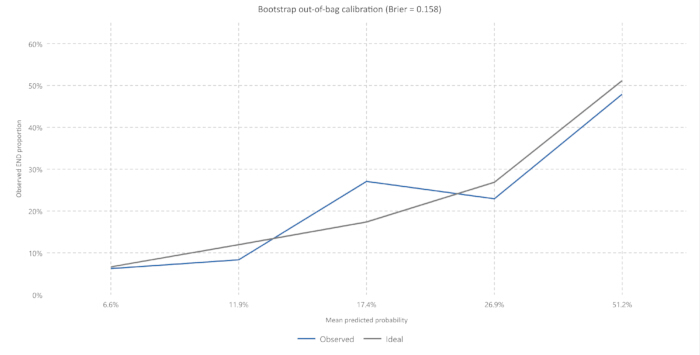
Figure 5: Bootstrap out-of-bag calibration. In each of 1,000 bootstrap iterations, the primary model was refitted in the bootstrap sample and used to predict participants not selected in that sample. Per-participant out-of-bag predictions were averaged, sorted, and divided into five equal-sized groups of 48. Each point compares the group-mean predicted probability with the observed END proportion. The out-of-bag AUC was 0.733, and the Brier score was 0.158. The 45° line denotes ideal calibration. Please click here to view a larger version of this figure.
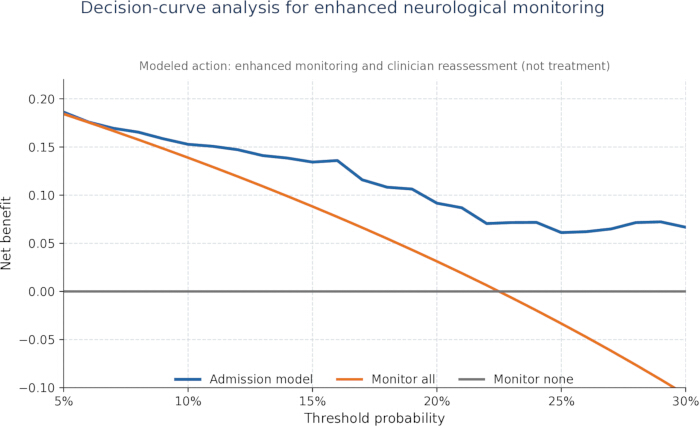
Figure 6: Decision-curve analysis for enhanced neurological monitoring and clinician reassessment. The analysis included 240 participants and 54 END events. Net benefit was calculated as true positives/n − false positives/n × [threshold probability/(1 − threshold probability)] for thresholds of 5%–30%. The admission model was compared with strategies of monitoring all patients and monitoring no patients. The modeled action was enhanced neurological observation and clinician reassessment; it did not prescribe thrombolysis, antithrombotic escalation, or BP treatment. Please click here to view a larger version of this figure.
Sensitivity, confounder, and dynamic BP analyses
The apparent and optimism-corrected AUCs were 0.784 and 0.763, respectively, in the MRI-only cohort (n = 194; 43 events); 0.767 and 0.743 after exclusion of parent-artery stenosis of at least 50% (n = 214; 44 events); and 0.766 and 0.745 for ischemic-cause END only (52 events). After exclusion of suspected BAD, only 9 events remained among 154 patients. The resulting apparent AUC of 0.844 and optimism-corrected AUC of 0.777 were imprecise and did not establish performance in intrinsic small-vessel disease (Table 3).
A ridge-penalized expanded baseline model that added suspected BAD, parent-artery stenosis, nonculprit stenosis, lesion diameter, onset-to-admission time, and imaging modality had an apparent AUC of 0.917 and an optimism-corrected AUC of 0.895. A treatment-adjusted exploratory model involving 239 patients had apparent and optimism-corrected AUCs of 0.928 and 0.894, respectively. The increase in performance was largely associated with BAD and lesion characteristics. These post hoc models did not replace external validation.
For the 24-h landmark analysis, 12 patients with earlier END were removed, leaving 228 patients and 42 late events. The base landmark model had apparent and optimism-corrected AUCs of 0.900 and 0.886, respectively. Addition of SBP SD yielded apparent and corrected AUCs of 0.933 and 0.917, addition of SBP CV yielded AUCs of 0.938 and 0.924, and addition of SBP ARV yielded AUCs of 0.926 and 0.911, respectively (Table 4). The BP variability measures were strongly correlated and were assessed one at a time. Because the measures summarized the first 24 h, they were not interpreted as predictors of admission.
| Analysis | n | END events | AUC | 95% CI lower | 95% CI upper | Optimism-corrected AUC | Mean optimism |
| MRI-only cohort | 194 | 43 | 0.784075158 | 0.698971234 | 0.858494296 | 0.762577064 | 0.021498094 |
| Excluding parent-artery stenosis ≥50% | 214 | 44 | 0.76684492 | 0.691076661 | 0.844557494 | 0.743372957 | 0.023471963 |
| Excluding suspected BAD | 154 | 9 | 0.844444444 | 0.712559733 | 0.937221057 | 0.777259626 | 0.067184818 |
| Ischemic-cause END only | 240 | 52 | 0.765957447 | 0.696140304 | 0.826356765 | 0.745421413 | 0.020536034 |
| Each analysis refitted the four-predictor continuous-SBP model. Counts are integers. BAD, branch atheromatous disease; AUC, area under the receiver operating characteristic curve; CI, confidence interval; END, early neurological deterioration; MRI, magnetic resonance imaging; SBP, systolic blood pressure. | |||||||
Table 3: Sensitivity analyses. Each analysis refitted the four-predictor continuous-SBP model. Sample sizes and END-event counts are reported as integers. Results after exclusion of suspected BAD were event-limited.
Each analysis refitted the four-predictor continuous-SBP model. Counts are integers. BAD, branch atheromatous disease; AUC, area under the receiver operating characteristic curve; CI, confidence interval; END, early neurological deterioration; MRI, magnetic resonance imaging; SBP, systolic blood pressure.
| Analysis | n | END events | AUC | 95% CI lower | 95% CI upper | Optimism-corrected AUC | Mean optimism |
| 24-hour landmark base model | 228 | 42 | 0.899641577 | 0.846615322 | 0.939225245 | 0.886162408 | 0.013479169 |
| 24-hour landmark + SBP SD | 228 | 42 | 0.932923707 | 0.876962806 | 0.976850902 | 0.91689537 | 0.016028338 |
| 24-hour landmark + SBP CV | 228 | 42 | 0.938300051 | 0.890462815 | 0.978702433 | 0.923886437 | 0.014413614 |
| 24-hour landmark + SBP ARV | 228 | 42 | 0.926395289 | 0.87816513 | 0.962965313 | 0.910898406 | 0.015496883 |
| Patients with END before 24 hours were excluded. BP variability metrics were added one at a time. Counts are integers. ARV, average real variability; AUC, area under the receiver operating characteristic curve; BP, blood pressure; CI, confidence interval; CV, coefficient of variation; END, early neurological deterioration; SBP, systolic blood pressure; SD, standard deviation. | |||||||
Table 4: Exploratory 24-h landmark analyses. Patients with END before 24 h were excluded. BP-variability metrics were added one at a time to avoid collinearity. Sample sizes and END-event counts are reported as integers.
Patients with END before 24 hours were excluded. BP variability metrics were added one at a time. Counts are integers. ARV, average real variability; AUC, area under the receiver operating characteristic curve; BP, blood pressure; CI, confidence interval; CV, coefficient of variation; END, early neurological deterioration; SBP, systolic blood pressure; SD, standard deviation.
Applicability of published END models
The progressive lacunar stroke score could not be calculated because pure motor syndrome and the published DBP category were not captured, and the cohort definition differed. The ENDI score could not be calculated because thrombus length and the responsible artery segment were unavailable, and because the score was developed for a different large-vessel-occlusion population. The current admission model was calculable using continuous SBP, baseline NIHSS, NLR, and any vascular stenosis of at least 50%, but it remained internally validated only within the development cohort (Supplementary Table 3).
DATA AVAILABILITY:
The de-identified participant-level dataset used for this revision is provided as Supplementary File 1.
Supplementary Table 1: Simplified binary-SBP model. The secondary model included SBP dichotomized at 169 mmHg, baseline NIHSS, NLR, and any vascular stenosis of at least 50%. The SBP threshold was selected using the maximum Youden index. Its 95% bootstrap interval was 153–183 mmHg. This model was presented only as a secondary, simplified analysis. Please click here to download this file.
Supplementary Table 2: Joint SBP–DBP sensitivity model. The model simultaneously included SBP and DBP, each scaled per 10 mmHg, together with baseline NIHSS, NLR, and any vascular stenosis of at least 50%. The analysis assessed the joint association of the two BP components with END. Please click here to download this file.
Supplementary Table 3: Applicability of published END models. The table compares the original populations, required predictors, and applicability of the Progressive Lacunar Stroke score, the ENDi score, and the current admission model. Published scores were not calculated when required predictor components were unavailable or when the target population differed from the present cohort. Please click here to download this file.
Supplementary File 1: De-identified participant-level dataset. The CSV file contains the de-identified participant-level data used for the revision analyses. Please click here to download this file.
Abbreviations: ARV, average real variability; AUC, area under the receiver operating characteristic curve; BAD, branch atheromatous disease; BP, blood pressure; CI, confidence interval; CT, computed tomography; CV, coefficient of variation; DBP, diastolic blood pressure; END, early neurological deterioration; ENDi, early neurological deterioration of ischemic origin; IQR, interquartile range; MRI, magnetic resonance imaging; NIHSS, National Institutes of Health Stroke Scale; NLR, neutrophil-to-lymphocyte ratio; OR, odds ratio; ROC, receiver operating characteristic; SBP, systolic blood pressure; SD, standard deviation; SE, standard error; TIA, transient ischemic attack.
Discussion
In this development cohort, END occurred in 22.5%, closely matching contemporary pooled estimates for lacunar ischemic stroke2. Continuous admission SBP, baseline NIHSS, NLR, and any recorded stenosis were associated with END in the four-variable model. However, the optimism-corrected AUC of 0.741 and the out-of-bag Brier score of 0.158 supported moderate, rather than definitive, prognostic performance.
The revised SBP analysis materially changed the interpretation. The previous 169 mmHg dichotomy discarded information and appeared more precise than justified. The spline showed no evidence of nonlinearity, and the bootstrap cutoff interval spanned 153–183 mmHg. In addition, inclusion of DBP attenuated the SBP coefficient. These findings supported treatment of BP as a continuous prognostic marker and avoidance of a universal treatment threshold. BP may have reflected stroke-related stress, pre-existing hypertension, autoregulatory impairment, pain, or early physiological instability; however, an observational association could not determine the benefit or harm of BP reduction.
The 24-hlandmark analysis supported the concern that dynamic BP contained additional information. Prior work had linked acute BP variability with END12,17. In the present dataset, SD, CV, and ARV each improved discrimination for deterioration after 24 h. Nevertheless, these measurements occurred during the outcome window and may have been influenced by treatment or evolving stroke. They were therefore considered time-updated warning markers rather than baseline confounders or causal treatment targets.
BAD represented the strongest source of etiologic heterogeneity. Eighty-three percent of END cases met the operational BAD definition, and the addition of BAD and lesion features markedly increased apparent model performance. Larger, more proximal lesions may have involved multiple perforators or a parent-artery plaque and may have been prone to infarct extension7. Concurrent stenosis may also have reduced perfusion reserve, but the absence of artery-segment and vessel-wall data prevented confirmation of a responsible plaque. Accordingly, the term “minor small subcortical infarction” was used in the title rather than implying etiologically homogeneous SAO.
Higher NIHSS values within the 0–5 range may have indicated involvement of a strategically important corticospinal pathway or greater initial tissue injury. NLR may have reflected ischemia-related innate immune activation; neutrophil products, oxidative stress, and matrix metalloproteinases can aggravate endothelial injury, whereas relative lymphopenia may reflect stress signaling8,11. These mechanisms remained biologically plausible but were not established by the retrospective associations.
A valid quantitative comparison with published scores was not possible. The Progressive Lacunar Stroke score required pure motor syndrome and a published DBP category, which were not captured in the dataset13. The ENDi score required occlusion site and thrombus length and had been developed for thrombolysed minor stroke with large-vessel occlusion14. Calculation of either score with missing components would have created a misleading comparison. A qualitative applicability comparison was therefore added in Supplementary Table 3, comparisons with individual predictors were reported, and claims of superiority over established models were removed.
Several limitations were important. First, the study was a single-center retrospective development study without external validation. Second, etiologic assignment came from routine care; detailed lesion location, side, responsible arterial segment, raw-image rereading, and traceable independent blinded adjudication were unavailable. Third, 46 patients were classified using CT-only imaging, and CT may have missed a small acute subcortical infarct; the MRI-only analysis partially addressed this concern but did not eliminate it. Fourth, suspected BAD dominated the event distribution, and the non-BAD analysis contained only 9 events. Fifth, treatments were not randomized; treatment timing may have been related to clinical trajectory, one pre-blood-draw treatment value was missing, and intravenous fluid volume was unavailable. Sixth, NIHSS assessments were routine rather than centrally blinded. Seventh, the sample was small for expanded models, and bootstrap validation could not substitute for geographic and temporal validation. Finally, the 24-hBP variability analysis was landmark-based and could not be combined uncritically with an admission-only nomogram.
Disclosures
The authors disclosed no conflicts of interest.
Acknowledgements
The medical staff in the Department of Neurology and the Advanced Stroke Center of Jinhua Municipal Central Hospital were thanked for their assistance with patient care and data collection.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Automated hematology analyzer | Sysmex Corporation | XN-1000 | Routine blood counts used to derive the neutrophil-to-lymphocyte ratio |
| Computed tomography scanner | Siemens Healthineers | SOMATOM Drive | Noncontrast computed tomography and computed tomography angiography acquisition during routine clinical care |
| CTA/MRA image acquisition and stenosis assessment | Department of Radiology, Jinhua Municipal Central Hospital | Institutional clinical CTA/MRA protocols; WASID measurement convention for intracranial stenosis | Retrospective abstraction from signed routine-care radiology reports; no separate research imaging platform. No protocol identifier was assigned |
| Electronic medical record and clinical data source | Jinhua Municipal Central Hospital | Institutional hospital information, laboratory, medication, and radiology-report systems | Retrospective extraction of de-identified routine-care data; no standalone research electronic medical record product. Commercial catalog number, version, and RRID not applicable. |
| Magnetic resonance imaging scanner | GE HealthCare | SIGNA Pioneer 3.0T | Diffusion-weighted imaging, apparent diffusion coefficient imaging, and magnetic resonance angiography acquisition during routine clinical care |
| Microsoft Excel | Microsoft Corporation | Microsoft 365 | Table review and submission packaging |
| Microsoft Word | Microsoft Corporation | Microsoft 365 | Manuscript preparation |
| National Institutes of Health Stroke Scale | National Institute of Neurological Disorders and Stroke | NIHSS assessment form | Routine neurological assessments |
| NumPy | Open-source Python package | 2.3.3 | Numerical computation; no project-specific RRID was reported. |
| pandas | Open-source Python package | 2.3.3 | Data management; no project-specific RRID was reported. |
| Python | Python Software Foundation | 3.13.5 | Reproducible statistical analysis; RRID: SCR_008394. |
| SciPy | Open-source Python package | 1.16.2 | Statistical functions; no project-specific RRID was reported. |
References
- Campbell BCV, Khatri P. Stroke. Lancet. 2020;396(10244):129-142.
- Werring DJ et al. Early neurological deterioration in acute lacunar ischemic stroke: systematic review of incidence, mechanisms, and prospects for treatment. Int J Stroke. 2025;20(1):7-20.
- Vynckier J et al. Early neurologic deterioration in lacunar stroke: clinical and imaging predictors and association with long-term outcome. Neurology. 2021;97(14):e1437-e1446.
- Wardlaw JM et al. European Stroke Organisation guideline on cerebral small vessel disease, part 2, lacunar ischaemic stroke. Eur Stroke J. 2024;9(1):5-68.
- Caplan LR. Lacunar infarction and small vessel disease: pathology and pathophysiology. J Stroke. 2015;17(1):2-6.
- Regenhardt RW, Das AS, Lo EH, Caplan LR. Advances in understanding the pathophysiology of lacunar stroke: a review. JAMA Neurol. 2018;75(10):1273-1281.
- Yamamoto Y et al. Characteristics of intracranial branch atheromatous disease and its association with progressive motor deficits. J Neurol Sci. 2011;304(1-2):78-82.
- Castellanos M et al. Inflammation-mediated damage in progressing lacunar infarctions: a potential therapeutic target. Stroke. 2002;33(4):982-987.
- He Y et al. Effect of blood pressure on early neurological deterioration of acute ischemic stroke patients with intravenous rt-PA thrombolysis may be mediated through oxidative stress-induced blood–brain barrier disruption and AQP4 upregulation. J Stroke Cerebrovasc Dis. 2020;29(8):104997. doi:10.1016/j.jstrokecerebrovasdis.2020.104997.
- Jordan JD, Powers WJ. Cerebral autoregulation and acute ischemic stroke. Am J Hypertens. 2012;25(9):946-950.
- Zhao L, Zhou S, Dai Q, Li J. Neutrophil-to-lymphocyte ratio predicts early neurological deterioration in patients with anterior circulation stroke. Int J Gen Med. 2024;17:5325-5331.
- Chung JW et al. Blood pressure variability and the development of early neurological deterioration following acute ischemic stroke. J Hypertens. 2015;33(10):2099-2106.
- Bashir S et al. Progressive lacunar strokes: a predictive score. J Stroke Cerebrovasc Dis. 2022;31(8):106510. doi:10.1016/j.jstrokecerebrovasdis.2022.106510.
- Seners P et al. Prediction of early neurological deterioration in individuals with minor stroke and large vessel occlusion intended for intravenous thrombolysis alone. JAMA Neurol. 2021;78(3):321-328.
- Samuels OB et al. A standardized method for measuring intracranial arterial stenosis. AJNR Am J Neuroradiol. 2000;21(4):643-646.
- Collins GS, Reitsma JB, Altman DG, Moons KGM. Transparent reporting of a multivariable prediction model for individual prognosis or diagnosis: the TRIPOD statement. Ann Intern Med. 2015;162(1):55-63.
- Duan Z et al. Effect of blood pressure variability on early neurological deterioration in single small subcortical infarction with parental arterial disease. eNeurologicalSci. 2017;8:22-27.