This protocol describes circumferential transforaminal endoscopic lumbar foraminotomy for 360° decompression of the exiting nerve root in patients with lumbar foraminal stenosis using a step-by-step, landmark-based approach to achieve adequate bony and soft-tissue decompression.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
Circumferential Transforaminal Endoscopic Lumbar Foraminotomy for 360° Exiting Nerve Root Decompression in Patients with Lumbar Foraminal Stenosis
In This Article
Summary
Abstract
Lumbar foraminal stenosis is a common cause of intractable radiculopathy that may require surgical treatment when conservative management is ineffective. Transforaminal endoscopic lumbar foraminotomy (TELF) has been developed as a minimally invasive alternative to conventional open surgery, offering reduced tissue disruption and faster recovery. However, conventional TELF techniques may provide limited decompression in complex cases involving severe bony stenosis, fibrosis, or postoperative anatomical changes. This protocol describes circumferential TELF (C-TELF), an advanced endoscopic decompression technique designed to achieve 360° decompression of the exiting nerve root (ENR) in patients with lumbar foraminal stenosis. The goal of this protocol is to provide a reproducible, step-by-step method for achieving circumferential neural decompression through a landmark-based transforaminal approach. The technique incorporates sequential bony unroofing, soft-tissue removal, and complete neural mobilization within the foraminal zone. The procedure is performed using a percutaneous transforaminal approach under fluoroscopic guidance and endoscopic visualization. Decompression is conducted sequentially from the lower pedicle to the upper pedicle to enlarge the neural foramen and establish an adequate safety margin around the ENR. By achieving circumferential decompression, this technique aims to minimize residual neural compression and facilitate durable decompression. This protocol provides detailed procedural guidance to support the safe and reproducible implementation of C-TELF, particularly in patients with complex or refractory lumbar foraminal stenosis.
Introduction
Lumbar foraminal stenosis is a common cause of intractable radiculopathy, particularly in older adults and patients who have undergone previous lumbar surgery1,2. This condition often leads to persistent leg pain, functional disability, and reduced quality of life3,4. Degenerative changes, including disc collapse, facet hypertrophy, and ligament thickening, contribute to the progressive narrowing of the neural foramen5. Although conventional open decompression and fusion surgery can relieve symptoms, these procedures are associated with significant tissue injury, perioperative morbidity, and the risk of adjacent segment degeneration6,7. Minimally invasive spinal surgery techniques have been developed to overcome these limitations. Among them, transforaminal endoscopic lumbar foraminotomy (TELF) has emerged as an effective surgical option for lumbar foraminal stenosis8,9. This technique allows direct decompression of the exiting nerve root (ENR) through a transforaminal route while preserving normal anatomical structures10. In addition, TELF can be performed under local anesthesia, which may reduce surgical risk in older or medically compromised patients11,12. The development of TELF has been supported by advances in surgical instrumentation, visualization systems, and operative strategies13. The introduction of outside-in approaches and progressive foraminal unroofing techniques has enabled safer and more effective access to the stenotic zone14,15. These advances have expanded the indications for endoscopic spine surgery and improved clinical outcomes in selected patient populations16.
Despite these advances, conventional TELF techniques may provide only partial decompression and may not fully address complex or multifactorial compression, particularly in cases involving severe bony stenosis, fibrosis, or postoperative anatomical changes17,18. In patients with a history of lumbar fusion, foraminal stenosis may result from a combination of disc collapse, scar tissue formation, and hardware-related irritation19. In such cases, incomplete decompression may contribute to persistent or recurrent symptoms20. To address these limitations, an extended form of TELF has been developed to achieve circumferential decompression of the ENR. This technique emphasizes the complete removal of compressive structures, including bone, ligament, and soft tissue, under direct endoscopic visualization (Figure 1 and Figure 2)8,16. Compared with conventional TELF techniques, this approach is intended to provide more comprehensive neural decompression in selected cases21. Although C-TELF evolved from previously described extended TELF techniques, the focus of the procedure extends beyond wider bony decompression alone. Extended TELF was developed to create larger decompression margins and reduce the risk of residual or recurrent foraminal stenosis. In contrast, C-TELF places additional emphasis on meticulous release of the ENR through the removal of fibrotic tissue, scar tissue, and residual compressive structures surrounding the nerve root. This approach aims to achieve adequate decompression and free neural mobilization under direct endoscopic visualization. The overall goal of this method is to achieve 360° decompression of the ENR through a reproducible, landmark-based endoscopic technique. This study describes a detailed protocol for C-TELF and provides guidance for its application in patients with complex lumbar foraminal stenosis. C-TELF is particularly useful in patients with severe bony stenosis, foraminal fibrosis, postoperative foraminal stenosis, and recurrent radiculopathy. These complex conditions often require more extensive neural decompression and neural release than can be achieved using conventional decompression techniques. Detailed inclusion criteria, exclusion criteria, and patient selection guidelines are provided in the Protocol section.
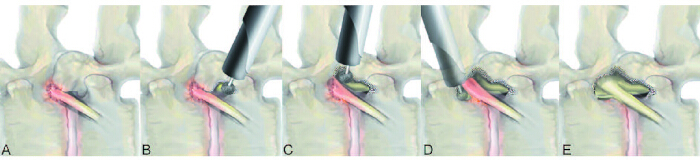
Figure 1. Lateral-view schematic of circumferential transforaminal endoscopic lumbar foraminotomy (C-TELF). (A) Lumbar foraminal stenosis causing compression of the exiting nerve root (ENR). (B) Initial bony decompression beginning at the lower pedicle wall. (C) Progressive bony unroofing toward the facet joint cleft, allowing exposure of the proximal and axillary portions of the ENR. (D) Extension of bone resection to the isthmus and upper pedicle wall to expose the shoulder portion of the ENR. (E) Final schematic demonstrating complete circumferential (360°) decompression of the ENR. Please click here to view a larger version of this figure.
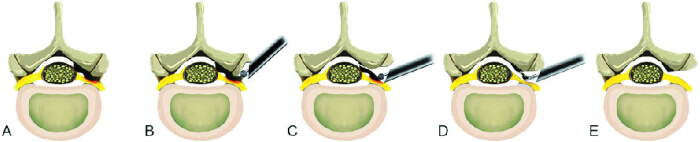
Figure 2. Axial-view schematic of C-TELF. (A) Lumbar foraminal stenosis causing compression of the ENR. (B) Undercutting of the superior articular process during initial bony decompression. (C) Landmark-based foraminal unroofing focused on identification of the facet joint cleft. (D) Removal of ligamentous soft tissues to expose the dural sac and ENR. (E) Final schematic demonstrating complete decompression from the proximal foraminal zone to the lateral exit zone with an adequate bony decompression margin. Please click here to view a larger version of this figure.
Access restricted. Please log in or start a trial to view this content.
Protocol
Institutional Review Board approval was obtained before data extraction, and all procedures were performed in accordance with institutional guidelines for human research. This study was approved by the Institutional Review Board of Kyung Hee University Hospital at Gangdong (Approval No. KHNMC 2026-04-033). The requirement for informed consent was waived because of the retrospective nature of the analysis and the use of de-identified data.
1. Preoperative Planning
- Evaluate the patient’s symptoms and neurological findings. Confirm radicular pain corresponding to a single ENR.
- Perform a physical examination. Check dermatomal pain distribution, motor weakness, and reflex changes.
- Obtain lumbar magnetic resonance imaging (MRI). Identify foraminal or extraforaminal nerve root compression (Figure 3A).
- Obtain computed tomography (CT) scans. Assess bony stenosis, osteophytes, and pedicle morphology.
- Obtain dynamic X-rays. Evaluate segmental instability.
- Exclude patients with definite instability or hardware failure.
- Perform a selective nerve root block at the suspected level. Confirm symptom relief.
- Use a selective nerve root block primarily when the symptomatic level is uncertain. Define a positive response as significant but transient relief of the patient’s typical radicular symptoms following the injection, with improvement resolving within 2 weeks.
- Define the surgical target as the ENR within the foraminal zone. Plan a circumferential decompression strategy (Figure 3).
- Apply the following inclusion criteria.
- Include patients with clinical symptoms and signs consistent with lumbar foraminal or extraforaminal nerve root compression.
- Confirm foraminal stenosis by MRI and/or CT findings that correlate with the patient's symptoms.
- Include patients with persistent symptoms despite at least 6 weeks of appropriate conservative treatment, including medication, physical therapy, and/or injection therapy.
- Include patients with complex foraminal pathology, including severe bony stenosis, foraminal fibrosis, postoperative foraminal stenosis, recurrent radiculopathy, or failed previous lumbar procedures.
- Apply the following exclusion criteria.
- Exclude patients with segmental instability demonstrated on dynamic radiographs.
- Exclude patients with high-grade spondylolisthesis.
- Exclude patients with predominant central canal stenosis requiring direct central decompression.
- Exclude patients with spinal infection, tumor, or acute fracture.
- Exclude patients with hardware failure requiring revision instrumentation.
- Exclude patients with severe spinal deformity requiring corrective fusion surgery.
- Consider C-TELF in the following situations.
- Severe bony foraminal stenosis requiring extensive bony decompression.
- Foraminal fibrosis or scar tissue causing nerve root tethering.
- Postoperative foraminal stenosis after previous lumbar surgery.
- Recurrent radiculopathy after prior decompression procedures.
- Combined bony and soft-tissue compression that may not be adequately addressed by standard TELF.
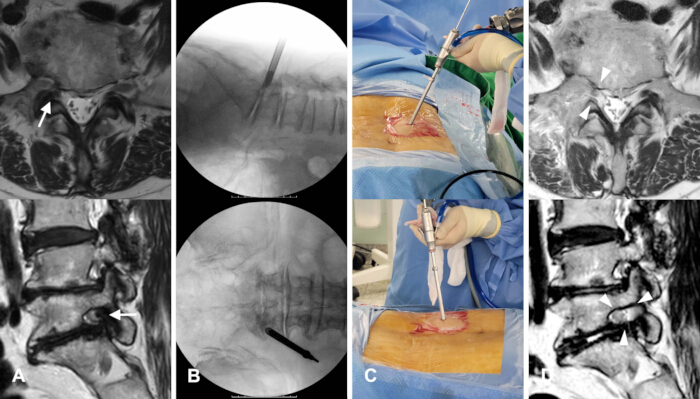
Figure 3. Representative case of C-TELF. (A) Preoperative magnetic resonance imaging (MRI) demonstrating severe right-sided L5–S1 foraminal stenosis (arrows). (B) Intraoperative fluoroscopic images showing placement of the working sheath within the right L5–S1 intervertebral foramen. (C) Intraoperative photographs demonstrating the full-endoscopic transforaminal procedure using a working-channel endoscope; the surgical trajectory is approximately 60°, selected within the recommended 45°–60° range according to the patient’s foraminal anatomy and target pathology. (D) Postoperative MRI demonstrating enlargement of the foraminal space and complete decompression of the ENR (arrowheads). Please click here to view a larger version of this figure.
2. Fluoroscopic-Guided Transforaminal Approach
- Place the patient in a prone position on a radiolucent table. Maintain mild hip and knee flexion.
- Administer local anesthesia at the skin entry site and maintain conscious sedation. Preserve patient feedback throughout the procedure.
- Identify the target level using fluoroscopy. Determine the skin entry point. Select the skin entry point to achieve a relatively steep trajectory (approximately 45°–60°) that passes through the lateral surface of the facet joint toward the target foramen.
- Determine the final trajectory angle based on the target level, foraminal anatomy, and anticipated working corridor. In general, select a relatively steep trajectory because the viewing angle of the working-channel endoscope is typically inclined at approximately 20°–30°.
- If the initial approach is too shallow, visualization and decompression of the proximal foraminal zone, including the axillary region of the ENR, may be difficult. Therefore, initiate the procedure with a trajectory of approximately 45°–60° and gradually flatten the working corridor as decompression progresses.
- The representative case shown in Figure 3C illustrates an approach angle of approximately 60°.
- Insert a spinal needle toward the foraminal zone. Direct the needle toward the disc or the vertebral surface near the inferior pedicle while maintaining contact with the surface of the superior articular process.
- Confirm the needle position under fluoroscopic guidance. In the anteroposterior view, position the needle tip near the mid-pedicular line at the target level. In the lateral view, advance the needle tip to the disc level or the vertebral surface adjacent to the inferior pedicle. Plan the entry point and trajectory preoperatively using axial MRI to provide a safe corridor along the lateral margin of the facet joint toward the foraminal zone.
- Insert a guidewire and remove the needle while maintaining the guidewire position.
- Insert sequential dilators over the guidewire. Monitor continuously for signs of ENR irritation and avoid provoking nerve irritation.
- Sequentially dilate the soft-tissue corridor using four serial dilators with progressively increasing outer diameters (2.5, 3.9, 5.2, and 6.3 mm). After completing serial dilation, insert the blunt obturator, then advance the final working sheath into the foraminal zone.
- Monitor continuously for signs of ENR irritation during dilation. Because the procedure is performed under local anesthesia, nerve irritation may be indicated by reproduction of the patient's typical radicular pain or involuntary muscle twitching. If these signs occur, stop advancement, reassess the trajectory, and proceed carefully after the symptoms have resolved.
- Advance the beveled working sheath into the foraminal zone. Orient the beveled opening away from the ENR (Figure 3B).
- Confirm the sheath position using fluoroscopy. Verify that the distal end of the working sheath is safely seated within the foraminal zone (Figure 3B).
- Place the sheath within the outer foraminal zone to avoid direct nerve compression.
- Confirm the position of the working sheath under fluoroscopic guidance. In the anteroposterior view, position the sheath tip just lateral to the facet joint and foraminal zone. In the lateral view, position the sheath tip at or slightly posterior to the posterior vertebral line. This position allows the beveled opening to provide optimal access for foraminal decompression.
- Insert the fenestrated 45° working tube (see Table of Materials), with an outer diameter of approximately 7.5 mm, over the obturator and advance it into the foraminal zone under fluoroscopic guidance.
3. Endoscopic Bony Unroofing
- Insert the endoscope through the working sheath (Figure 3C). Identify the lower pedicle, superior articular process, facet joint, disc surface, ENR, and surrounding perineural fat.
- Use a working-channel endoscope designed for transforaminal spinal endoscopy. In this protocol, a 30° endoscope with an outer diameter of approximately 7.3 mm and a 4.7-mm working channel is used (see Table of Materials).
- Use the oblique optical configuration to facilitate visualization of the foraminal structures and enable circumferential decompression around the ENR.
- Begin decompression at the lower pedicle margin. Maintain a stable orientation using bony landmarks.
- Undercut the superior articular process and the adjacent portion of the pedicle using an endoscopic burr. Identify the cephalad margin of the lower pedicle, which serves as the inferior boundary of the foraminal zone. This approach initiates foraminal decompression while minimizing the risk of nerve root injury (Figure 4A).
- Identify the cephalad margin of the lower pedicle as the inferior boundary of the foraminal zone. Use this bony landmark as a reliable reference point during decompression.
- Perform bony decompression using a straight 3.5-mm diamond burr designed for working-channel endoscopic surgery (see Table of Materials). Operate the burr in continuous rotation mode at approximately 80,000 rpm to undercut the bony structures while minimizing soft-tissue injury.
- Undercut the superior articular process and expose the ligamentum flavum. Advance the undercutting toward the ENR until the facet joint cleft is identified (Figure 4B).
- Identify the facet joint cleft during progressive undercutting of the superior articular process. Endoscopically, it appears as a gap between the superior and inferior articular processes, often containing synovial tissue. Recognize this landmark as indicating that decompression has reached the proximal foraminal zone, where the origin of the ENR is typically located.
- Upon reaching the facet joint cleft, continue removing bone medially to expose the axillary portion of the ENR and identify the site of nerve root impingement.
- Extend the decompression toward the upper portion of the foraminal zone. Resect the isthmus and upper pedicle wall to expose the shoulder portion of the ENR.
- Continue resection until the shoulder portion, origin, and proximal course of the ENR are clearly exposed, allowing circumferential decompression around the nerve root.
- Extend the decompression to achieve wide unroofing of the foraminal zone from the lower to the upper pedicle, allowing circumferential visualization of the ligamentous structures surrounding the ENR.
- Expand the bony resection margin along the pedicle walls from the lower to the upper pedicle. Ensure sufficient working space around the nerve root.
- Confirm adequate foraminal unroofing by identifying the ligamentum flavum between the lower and upper pedicle walls and the facet joint cleft. These anatomical landmarks indicate that an adequate bony resection margin and working space have been achieved.
- Adequate bony resection margins are critical for complete decompression and the prevention of residual compression.
- Monitor decompression progress primarily under endoscopic visualization. Use intermittent fluoroscopic confirmation to assess the extent of bony unroofing. Consider decompression adequate when the resection extends beyond the medial pedicular line on the anteroposterior fluoroscopic view and reaches the lower and upper pedicle margins, corresponding to complete foraminal unroofing.
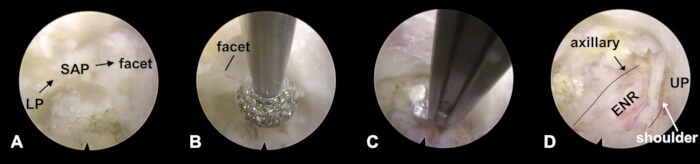
Figure 4. Intraoperative endoscopic views of stepwise circumferential decompression. (A) Initial endoscopic view showing the lower pedicle (LP), hypertrophic superior articular process (SAP), and facet joint before decompression. The LP represents the inferior aspect of the foraminal zone. (B) Landmark-based bony unroofing using an endoscopic burr. Identification of the facet joint cleft serves as the key anatomical landmark during decompression; the structure labeled "facet" in the image corresponds to the facet joint cleft. (C) Soft-tissue decompression using endoscopic instruments following bony unroofing. (D) Final endoscopic view demonstrating complete circumferential decompression of the ENR, with exposure of the axillary and shoulder zones and visualization of the upper pedicle (UP). Please click here to view a larger version of this figure.
4. Soft Tissue Decompression
- Remove the exposed ligamentum flavum using endoscopic punches and forceps (Figure 4C).
- Use 2.9-mm endoscopic micropunches with hook-shaped or beak-shaped tips, 2.9-mm blunt-tipped grasping forceps, and endoscopic Kerrison punches (see Table of Materials). Use these instruments in combination to remove the ligamentum flavum, hypertrophic foraminal ligaments, fibrotic adhesions, and other compressive soft tissues surrounding the ENR.
- Remove hypertrophic foraminal ligaments and fibrotic adhesions. Carefully dissect the nerve root and dural sac using an endoscopic probe and hydrostatic pressure.
- Maintain hydrostatic pressure using an automated irrigation pump with continuous antibiotic-containing saline irrigation. Control the irrigation pressure between 30 and 60 mmHg to maintain a clear operative field and facilitate soft-tissue dissection.
- Dissect fibrotic adhesions using both mechanical dissection and hydrodissection. Use an endoscopic dissector or probe to develop the dissection plane, while saline irrigation or hyaluronate solution facilitates atraumatic separation of adhesions from the nerve root and dural sac.
- Expose the ENR. Remove compressive soft tissue surrounding the nerve root. If necessary, coagulate and reduce or partially remove redundant disc material.
- Manage disc material according to its pathological configuration. Remove extruded fragments beyond the annulus when they contribute to nerve root compression. Manage redundant but contained disc tissue with coagulation and shrinkage rather than excision to achieve adequate decompression.
- Perform circumferential decompression along the nerve root from the shoulder portion to the axillary portion. Extend the release distally toward the lateral exit zone to achieve full-length decompression (Figure 4C).
- Confirm circumferential decompression by verifying that the ENR is completely exposed and released along its entire course. Confirm visualization of the axillary portion, origin, shoulder portion, and lateral exit zone of the ENR, with no residual compressive structures surrounding the nerve root.
- Carefully dissect fibrotic adhesions and gently mobilize the nerve root.
- Severe adhesions may tether the nerve root. Perform dissection meticulously to avoid injury.
- Complete adhesion release only after the nerve root is clearly visualized, freely mobile, and demonstrates spontaneous pulsation. Avoid further dissection once these endpoints are achieved because excessive manipulation may damage the exposed neural sheath.
- Control bleeding using a radiofrequency probe. Maintain a clear endoscopic field with pressure-controlled irrigation.
- Perform hemostasis using a bipolar radiofrequency probe in coagulation mode (see Table of Materials).
- Adjust the power setting according to the surgical location. Use settings of up to approximately 60 W for epidural or ligamentous bleeding away from neural structures and lower settings of approximately 15–30 W near the ENR or dural sac to minimize thermal injury.
- Apply the probe briefly and intermittently under continuous irrigation. Avoid prolonged contact with neural tissue.
- Maintain visualization using continuous saline irrigation delivered through an automated pressure-controlled irrigation pump. Maintain the irrigation pressure between 30 and 60 mmHg and adjust it as needed to preserve a clear endoscopic field while avoiding excessive pressure on neural structures.
5. Finishing Point
- Inspect the surgical field and confirm full exposure of the ENR.
- Ensure decompression from the lower pedicle to the upper pedicle.
- Confirm that adequate bony resection margins have been achieved around the ENR and that no residual ligamentous tissue remains entrapping the nerve root (Figure 4D).
- Confirm adequate bony resection margins by verifying direct visualization of the ENR without intervening compressive soft tissue between the nerve root and the resected bony margins. Confirm that sufficient space has been created around the nerve root and that no residual soft-tissue entrapment remains.
- Confirm free mobilization and visible pulsation of the ENR.
- Assess ENR mobilization by confirming visible spontaneous pulsation, smooth mobility during gentle probing, and, when appropriate, enhanced pulsation during a voluntary cough maneuver in awake patients. These findings indicate adequate neural release and restoration of nerve root mobility.
- Perform final hemostasis and remove the working sheath.
- Confirm adequate hemostasis by verifying that no active bleeding is present during continuous irrigation and that no significant bleeding occurs after temporarily stopping irrigation. Confirm that the endoscopic field remains clear and stable before removing the working sheath.
- Close the skin without drainage.
- Remove the endoscope and working sheath. Close the wound with a single subcutaneous suture followed by skin tape application. If skin approximation is inadequate, place an additional single skin suture at the surgeon's discretion. Do not place a drain routinely.
- Confirm complete neural release after circumferential (360°) decompression of the ENR.
- Confirm complete exposure of the axillary and shoulder zones at the dural sac origin (proximal decompression).
- Confirm complete release of the ENR at the lateral exit zone.
- Confirm adequate decompression margins around the nerve root without residual compression.
- Confirm free mobilization and visible pulsation of the ENR under endoscopic visualization (Figure 4D).
- Confirm the absence of residual compression by direct endoscopic inspection, gentle probing around the nerve root, and verification of adequate neural expansion. Consider decompression complete when no residual compressive structures are present, the ENR is freely mobile, and both the ENR and dural sac demonstrate satisfactory expansion and pulsation. Poor neural expansion, restricted mobility, or diminished pulsation may indicate residual compression.
- Perform postoperative assessment of radicular pain, wound pain, and neurological function, including hip, knee, and ankle muscle strength. Monitor patients for at least 3 h for vital signs and neurological status. If an adverse event or persistent neurological deficit is suspected, obtain postoperative MRI or CT for further evaluation.
Access restricted. Please log in or start a trial to view this content.
Results
The overall workflow of C-TELF is illustrated schematically in the lateral view (Figure 1A–1E) and axial view (Figure 2A–2E). These schematics demonstrate the progression from foraminal stenosis with ENR compression (Figures 1A and 2A), through stepwise bony decompression and foraminal unroofing (Figures 1B–1D and 2B–2D
Access restricted. Please log in or start a trial to view this content.
Discussion
This protocol describes a structured and reproducible technique for circumferential TELF. Radiculopathy caused by lumbar foraminal stenosis is common and often debilitating. Despite open surgery and minimally invasive procedures, incomplete decompression remains a common cause of persistent or recurrent symptoms. Therefore, circumferential decompression of the ENR is important for achieving reliable clinical outcomes19,21. Although C-TELF evolved from previously ...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors declare no competing financial interests or other conflicts of interest related to this work.
Acknowledgements
The authors thank Je-Min Son and Hwa-Young Kim for their valuable support and technical assistance.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 4K Camera Head | Olympus | CH-S400-XZ-EB | Endoscopic visualization |
| Biopsy Forceps, Blakesley | Joimax | BFS323061 | Forceps |
| Biopsy Forceps, Spoon | Joimax | THF322541 | Forceps |
| Biopsy Forceps, Spoon, angled | Joimax | THF322041 | Forceps |
| Closing Cap for Joimax Endoscopes | Joimax | TCC150700 | Working-channel endoscope accessory |
| Computed tomography scanner | GE HealthCare (Korea) | Revolution Frontier | Used for assessing bony stenosis, osteophytes, and pedicle morphology |
| Conscious sedation medication | Bukwang R&D | Midazolam 5 mg/5 mL | Used during the procedure while preserving patient feedback |
| Dynamic X-ray system | Philips | Zenition 70 | Used for evaluating segmental instability |
| Endo-Flexprobe, standard | Joimax | TEFP32020 | Steerable probe |
| Endo-Kerrison-Shaft, 40° | Joimax | EKS32351540 | Endoscopic punch |
| Endo-Kerrison-Shaft, 90° | Joimax | EKS32351590 | Endoscopic punch |
| Endoscopic burr tip | NSK | PDS-1CD330-35 | Straight coarse diamond burr, special long, 3.5 mm; used with Primado2 drill system |
| Endoscopic probe | Joimax | TEFH45025 | Used for nerve root and dural sac dissection |
| Fluoroscopy unit/C-arm | Philips | Zenition 70 | Used for target-level localization, needle placement, and working-sheath position verification |
| Floseal Hemostatic Matrix | Baxter | ADS201844 (5 mL Kit) | Hemostasis |
| Grasper Forceps, Spoon | Joimax | THG323555 | Forceps |
| Guidewire | Mantiz | A1B-1037 | Used for sequential dilation and working-sheath placement |
| Guiding Rod, conical with center and eccentric bore | Joimax | GRD226315 | Access instrument |
| Guiding Tube, conical, green | Joimax | GTC232838 | Access instrument |
| Guiding Tube, conical, red | Joimax | GTC215363 | Access instrument |
| Guiding Tube, conical, yellow | Joimax | GTC224353 | Access instrument |
| Local anesthetic | Huons | Lidocaine 2% | Used at the skin entry site |
| Lumbar magnetic resonance imaging scanner | Philips | MR7700 | Used for identifying foraminal or extraforaminal nerve root compression |
| Metal Hammer | Joimax | TMH200170B | Instrument advancement |
| NiTi Nerve Hook, superelastic | Joimax | TNH322533 | Nerve hook |
| Palm Handle | Joimax | TRPH25100 | Instrument handle |
| Postoperative magnetic resonance imaging scanner | Philips | MR7700 | Used when postoperative imaging is required to evaluate decompression or suspected complications |
| Pressure-controlled irrigation pump | CONMED Corporation | 10K | Pressure maintained at 30–60 mmHg |
| Primado2 Drill System | Nakanishi | P200-CU-100 | Endoscopic burr system; operated with a straight 3.5-mm coarse diamond burr at approximately 80,000 rpm |
| Primado2 Foot Controller | Nakanishi | FC-73 | Endoscopic burr system controller |
| Primado2 Slim Motor Handpiece | Nakanishi | P200-SMH-HS | Endoscopic burr system handpiece |
| Reamer Push-Ejector, green | Joimax | RPE280380 | Bone reamer system |
| Reamer Push-Ejector, red | Joimax | RPE280600 | Bone reamer system |
| Reamer Push-Ejector, yellow | Joimax | RPE280500 | Bone reamer system |
| Scope Working Tube Distance Ring for TESSYS, iLESSYS, MultiZYTE Scopes | Joimax | SWTDR6312 | Working-tube accessory |
| Selective nerve root block needle | BD | 408360 | Used for diagnostic selective nerve root block |
| Semi-Flexible Grasper Forceps | Joimax | TFG322522U | Steerable forceps |
| Sequential dilator (2.5 mm OD) | Joimax | GRC221025 | Length: 220 mm; inner diameter: 1.0 mm; outer diameter: 2.5 mm |
| Sequential dilator (3.9 mm OD) | Joimax | GTC202838 | Length: 205 mm; inner diameter: 2.6 mm; outer diameter: 3.9 mm |
| Sequential dilator (5.2 mm OD) | Joimax | GTC194353 | Length: 195 mm; inner diameter: 4.2 mm; outer diameter: 5.2 mm |
| Sequential dilator (6.3 mm OD) | Joimax | GTC185363 | Length: 185 mm; inner diameter: 5.3 mm; outer diameter: 6.3 mm |
| Silicone Sealing Cap for Luer-Lock, blue | Joimax | JMSDL001 | Sealing cap |
| Skin closure materials | Ethicon | VCP311 | Vicryl 3-0 subcutaneous suture; Steri-Strip skin closure; Neodressing (9 × 7 cm) |
| Spinal needle | TaeChang Industrial Co., Ltd. | SP.QB 21G × 90 mm | Used for transforaminal access to the foraminal zone |
| Stopper | Joimax | JFST061427 | Accessory |
| TESSYS Cleaning Wire | Joimax | TCW40010 | Cleaning accessory |
| TESSYS Endo-Flexprobe Handle | Joimax | TEFH45025 | Probe handle |
| TESSYS Foraminoscope, combo | Joimax | FS6342181C | Working-channel endoscope; 30° viewing angle; 4.7-mm working channel |
| TESSYS Foraminoscope, ocular | Joimax | FS6342181O | Working-channel endoscope; 30° viewing angle; 4.7-mm working channel |
| TESSYS Guiding Rod, blunt, green | Joimax | GRB251025 | Access instrument |
| TESSYS Guiding Rod, blunt, red | Joimax | GRB252050 | Access instrument |
| TESSYS Guiding Rod, blunt, yellow | Joimax | GRB251540 | Access instrument |
| TESSYS Guiding Rod, conical, green | Joimax | GRC241025 | Access instrument |
| TESSYS Guiding Rod, conical, red | Joimax | GRC242050 | Access instrument |
| TESSYS Guiding Rod, conical, yellow | Joimax | GRC241540 | Access instrument |
| TESSYS Guiding Rod, curved, green | Joimax | GRT241025S | Access instrument |
| TESSYS Guiding Rod Forceps | Joimax | GRF182500 | Access instrument |
| TESSYS Reamer Handle XT, cannulated Quick-Lock-System, pull-release | Joimax | RHC108590 | Reamer handle |
| TESSYS Steel Ruler | Joimax | TSR25010 | Measurement tool |
| TESSYS XT Working Tube with Handle, fenestrated | Joimax | WTS217500 | Working sheath |
| TESSYS XT Working Tube with Handle, fenestrated, 45° | Joimax | WTS217503 | Working sheath |
| Trigger-Flex | Elliquence | DTF-40 | Hemostasis/tissue ablation; power setting: 1–60 W; foot-switch activation |
| Tweezers | Joimax | JAF180023 | Tissue handling |
| Vaporflex Bipolar | Joimax | JVP32024 | Hemostasis/tissue ablation; power setting: 1–60 W; foot-switch activation |
| VISERA 4K UHD 31-inch LCD Monitor | Olympus | LMD-X310S | Endoscopic visualization |
| VISERA 4K UHD Camera Control Unit | Olympus | OTV-S400 | Endoscopic visualization |
| VISERA 4K Xenon Light Source | Olympus | CLV-S400 | Endoscopic illumination |
References
- Jenis LG, An HS. Spine update. Lumbar foraminal stenosis. Spine (Phila Pa 1976). 2000;25(3):389-394.
- Genevay S, Atlas SJ. Lumbar spinal stenosis. Best Pract Res Clin Rheumatol. 2010;24(2):253-265.
- Weinstein JN, et al. Surgical versus nonoperative treatment for lumbar spinal stenosis: four-year results of the Spine Patient Outcomes Research Trial. N Engl J Med. 2008;358(8):794-810.
- Deyo RA, et al. Trends, major medical complications, and charges associated with surgery for lumbar spinal stenosis in older adults. JAMA. 2010;303(13):1259-1265.
- Försth P, et al. A randomized, controlled trial of fusion surgery for lumbar spinal stenosis. N Engl J Med. 2016;374(15):1413-1423.
- Ghogawala Z, et al. Laminectomy plus fusion versus laminectomy alone for lumbar spondylolisthesis. N Engl J Med. 2016;374(15):1424-1434.
- Lønne G, et al. Lumbar spinal stenosis: comparison of surgical practice variation and clinical outcome in three national spine registries. Spine J. 2019;19(1):41-49.
- Ahn Y, et al. Percutaneous endoscopic lumbar foraminotomy: an advanced surgical technique and clinical outcomes. Neurosurgery. 2014;75(2):124-133.
- Yeung A, Lewandrowski KU. Five-year clinical outcomes with endoscopic transforaminal foraminoplasty for symptomatic degenerative conditions of the lumbar spine: a comparative study of inside-out versus outside-in techniques. J Spine Surg. 2020;6(Suppl 1):S66-S83.
- Knight MT, et al. Transforaminal endoscopic lumbar decompression and foraminoplasty: a 10-year prospective survivability outcome study of the treatment of foraminal stenosis and failed back surgery. Int J Spine Surg. 2014;8:21.
- Jasper GP, et al. A retrospective evaluation of the clinical success of transforaminal endoscopic discectomy with foraminotomy in geriatric patients. Pain Physician. 2013;16(3):225-229.
- Chung J, et al. Percutaneous endoscopic lumbar foraminoplasty for lumbar foraminal stenosis of elderly patients with unilateral radiculopathy: radiographic changes in magnetic resonance images. J Neurol Surg A Cent Eur Neurosurg. 2019;80(4):302-311.
- Hofstetter CP, et al. AOSpine consensus paper on nomenclature for working-channel endoscopic spinal procedures. Global Spine J. 2020;10(2 Suppl):111S-121S.
- Lewandrowski KU. “Outside-in” technique, clinical results, and indications for transforaminal endoscopic decompression. Int J Spine Surg. 2014;8:21.
- Krzok G. Transforaminal endoscopic surgery: outside-in technique. Neurospine. 2020;17(Suppl 1):S44-S57.
- Ahn Y, Rhee DY. Transforaminal endoscopic lumbar foraminotomy for iatrogenic foraminal stenosis following vertebroplasty. Neurospine. 2024;21(4):1137-1140.
- Giordan E, et al. Full-endoscopic transforaminal lumbar foraminotomy: a systematic review and meta-analysis. Neurospine. 2021;18(4):829-845.
- Ruetten S, et al. Full-endoscopic interlaminar and transforaminal lumbar discectomy versus conventional microsurgical technique: a prospective randomized controlled study. Spine (Phila Pa 1976). 2008;33(9):931-939.
- Telfeian AE, Jasper GP, Francisco GM. Transforaminal endoscopic treatment of lumbar radiculopathy after instrumented lumbar spine fusion. Pain Physician. 2015;18(2):179-184.
- Morgenstern R, et al. The learning curve in foraminal endoscopic discectomy: experience needed to achieve a 90% success rate. SAS J. 2007;1(3):100-107.
- Ahn Y, Park HB, Son S, Yoo BR. Clinical efficacy of extended transforaminal endoscopic lumbar foraminotomy compared with the conventional technique. J Clin Med. 2025;14(18):6446.
- Gadjradj PS, et al. Percutaneous transforaminal endoscopic discectomy versus open microdiscectomy for lumbar disc herniation: a systematic review and meta-analysis. Spine (Phila Pa 1976). 2021;46(8):538-549.
- Gadjradj PS, et al. Full endoscopic versus open discectomy for sciatica: randomised controlled non-inferiority trial. BMJ. 2022;376:e065846.
- Gray CM, Kumar S. Complete resolution of chronic pain, sensory impairment, and motor dysfunction following percutaneous transforaminal endoscopic decompression in a failed back surgery syndrome patient: a case report. J Spine Surg. 2020;6(3):613-619.
- Telfeian AE, et al. Transforaminal endoscopic surgical treatment for postlaminectomy lumbar radiculopathy: case series. World Neurosurg. 2021;150:e577-e584.
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
This article has been published
Video Coming Soon