This study aimed to explore potential drug-drug interactions between eugenol (EUG) and repaglinide (RPG) in patients with type 2 diabetes mellitus (T2DM).
Research Article
Drug-Drug Interaction Between Eugenol and Repaglinide in Type 2 Diabetes Mellitus and Its Potential Mechanism
In This Article
Summary
Abstract
This study investigated the potential drug-drug interaction (DDI) between eugenol (EUG) and repaglinide (RPG) in type 2 diabetes mellitus (T2DM). A T2DM rat model was established using a high-fat diet and streptozotocin (STZ). The single-dose group received 0.4 mg/kg RPG, and co-administration groups were pre-treated with EUG (50, 100, 150 mg/kg) for seven days before receiving a single dose of RPG (0.4 mg/kg). The blood glucose and pharmacokinetic parameters of RPG were assessed in the plasma samples of rats. The effect of EUG on RPG metabolic stability and cytochrome P3A (CYP3A) activity was evaluated in rat liver microsomes (RLM). In T2DM rats, RPG treatment showed a hypoglycemic effect, which was further promoted by EUG co-administration in a dose-dependent manner (p < 0.001). EUG co-administration affected the pharmacokinetics of RPG by increasing the area under the curve (AUC, increased 88.64%, 164.59%, and 244.72% vs single RPG, p < 0.001), plasma maximum concentration (Cmax, increased 18.61%, 53.58%, and 77.63% vs single RPG, p < 0.01), maximum concentration (Tmax, 1.0 h for EUG co-administration vs 0.5 h for single RPG), half-life (t1/2, prolonged 33.86%, 49.61%, and 88.19% vs single RPG, p < 0.01), mean retention time (MRT, prolonged 17.62%, 26.42%, 44.04% vs single RPG, p < 0.001), and decreased the clearance rate (Clz/F, decreased 48.92%, 63.31%, and 74.10% vs single RPG, p < 0.001) in a dose-dependent manner. In vitro RLM study, EUG improved the metabolic stability of RPG by prolonging the half-life (44.09 ± 3.25 min) and reducing the intrinsic clearance (30.55 ± 3.69 µL/min/mg protein). EUG also inhibited the activity of CYP3A with an IC50 of 7.90 ± 1.79 µM. Co-administration of EUG promoted the hypoglycemic effect of RPG through enhancing RPG systemic exposure in T2DM rats, potentially by improving RPG metabolic stability and inhibiting CYP3A activity.
Introduction
Type 2 diabetes mellitus (T2DM) is a chronic metabolic disorder characterized by insulin resistance or reduced insulin efficiency, which affects millions of individuals worldwide1. Complex interactions with genetic susceptibility and lifestyle factors are involved in T2DM, resulting in impaired glucose uptake, excessive hepatic gluconeogenesis, and chronic low-grade inflammation2. T2DM can lead to serious complications if treated improperly, including cardiovascular diseases, kidney disease, retinopathy, and neuropathy, significantly affecting the patients’ life quality and increasing mortality2. Current drug treatments of T2DM include metformin, sulfonylurea drugs, GLP-1 receptor agonists, and DPP-4 inhibitors, etc3. Repaglinide (RPG) is one kind of short-acting meglitinide that works by stimulating insulin secretion and has the characteristic of dose flexibility4. Compared with sulfonylureas, glinides offer superior control of postprandial hyperglycemia, reduce the risk of certain adverse effects such as hypoglycemia, and present a more favorable safety profile, particularly in patients with renal failure5,6. RPG is rapidly absorbed after oral administration, reaching peak plasma concentrations typically within 30–60 min, and its short half‑life results in a brief stimulation of insulin release. Clinically, RPG is used either as monotherapy or in combination with other oral antihyperglycemic agents to optimize glycemic control7. However, its clinical application is limited by low oral bioavailability (about 56%), rapid liver metabolism, and potential risk of hypoglycemia8,9,10,11,12,13,14. These drawbacks highlight the necessity of a comprehensive treatment strategy.
Eugenol (EUG), chemically known as 4-allyl-2-methoxyphenol, is an organic compound with the chemical formula C10H12O215. EUG is a colorless to pale yellow liquid and is an active phenolic compound mainly found in cloves (Eugenia caryophyllata Thunb.) and other aromatic plants16. Much attention has been attracted by EUG due to its various pharmacological properties, including antioxidant, anti-inflammatory, antibacterial, analgesic, and anti-tumor activities17,18,19. Recent studies have demonstrated that EUG has shown the potential value as an adjunctive therapy for T2DM, as both in vitro and in vivo experimental evidence indicate that EUG improves insulin sensitivity, promotes glucose uptake in peripheral tissues, inhibits hepatic gluconeogenesis, and protects pancreatic β-cell function20,21. These multifaceted measures, combined with relatively low toxicity22, position EUG as a highly promising natural drug candidate that can complement shortcomings of traditional clinical drugs and alleviate T2DM-related complications through a synergistic mechanism.
The cytochrome P450 enzymes (P450s) play a crucial role in the process of drug metabolism and mediate drug-drug interactions (DDIs) by either inducing or inhibiting specific subtypes, which is of vital importance for safe and effective drug treatment23. Notably, RPG is mainly metabolized in the liver by CYP2C8 and CYP3A424,25. When co-administered with quercetin (QCT), QCT enhances the in vivo bioavailability of RPG by inhibiting hepatic first-pass and systemic metabolism via CYP450s26. It has also been reported that EUG suppresses the activity of CYP450s, including 1A2, 2C9, 2D6, and 3A4 in a concentration-dependent manner, indicating potential interactions when EUG is co-administered with drugs metabolized by these enzymes27. Despite the promising potential of EUG as an adjunctive therapy for T2DM and the known susceptibility of RPG to CYP‑mediated DDIs, it remains unclear whether EUG alters the systemic exposure, metabolic stability, or CYP3A‑mediated metabolism of RPG. Given that both EUG and RPG are likely to be co‑administered in clinical practice or dietary supplement settings, the lack of DDI data between them poses a potential risk of unintended alterations in RPG plasma concentrations. Such alterations could lead to either reduced therapeutic efficacy or an increased risk of hypoglycemia. Thus, this evidence gap represents a significant obstacle to the rational and safe combination of natural products with conventional antidiabetic drugs. Therefore, it is essential to systematically evaluate the effect of EUG on the pharmacokinetics and pharmacodynamics of RPG and to elucidate the underlying metabolic mechanism, with particular focus on CYP3A activity. Given the above evidence, it could be speculated that EUG may influence RPG metabolism by altering CYP450 activity. This is the first study to investigate the EUG–RPG interaction in a T2DM setting. The findings are expected to fill a critical knowledge gap and provide a mechanistic basis for optimizing the safe co‑administration of EUG and RPG in T2DM management. If co‑administration is considered, the potential for increased RPG exposure should be considered, and signs of hypoglycemia should be monitored, particularly when EUG is taken at high doses or as a concentrated supplement. In addition, although rats express CYP3A isoforms that are functionally analogous to human CYP3A4, direct extrapolation of quantitative findings to humans requires caution due to species differences in enzyme expression and catalytic activity.
Protocol
This study was approved by the Jilin Academy of Chinese Medical Sciences Ethics Committee (Date:2024.11.21/No.2024112) in compliance with the ARRIVE guidelines28. The reagents and the equipment used are listed in the Table of Materials.
1. Animal housing conditions
Male Sprague-Dawley rats (200–250 g) were housed in a laboratory animal room under the following conditions: temperature: 22 °C ± 2 °C, relative humidity: 40–60%, and a 12-h light/dark cycle, with free access to food and water to allow one week of acclimatization29,30.
2. Animal modeling, treatment, and sample processing
The sample size was determined based on a power analysis using the F-test (G*Power 3.1.9.7). A priori power analysis was performed with an effect size of 0.6, an α level of 0.05, and a desired power of 0.8, which yielded a total sample size of 55. This calculation indicated that at least 9 rats were required per group. Therefore, ten rats per group were used, achieving an actual power of 0.86.
Before the T2DM model was established, all rats were fasted for 12 h. Then they were randomly divided into two groups: the control group (n = 10) and the T2DM group (n = 50). The establishment of the T2DM rat model was carried out according to the method reported previously31. In brief, rats in the T2DM group were fed a high-fat diet (with a fat content of 60%) for 4 consecutive weeks and then received a single intraperitoneal injection of 30 mg/kg of STZ dissolved in sterile citrate buffer (pH 4.4). Three days after the STZ injection, the tail vein blood glucose of the rats was measured using a blood glucose meter, and rats with a blood glucose concentration exceeding 16.7 mmol/L were considered to have successfully established the T2DM. For the control group, the rats received a normal diet and received intraperitoneal injections of 0.9% normal saline at the same time period as the T2DM group.
T2DM rats were further divided into four groups with 10 rats in each group: the T2DM + RPG group (single RPG), the T2DM + RPG + EUG (50 mg/kg) group (co-RPG+EUG 50 mg/kg), the T2DM + RPG + EUG (100 mg/kg) group (co-RPG+EUG 100 mg/kg), and the T2DM + RPG + EUG (150 mg/kg) group (co-RPG+EUG 150 mg/kg). After fasting for 12 h, rats in the single RPG group were orally administered 0.4 mg/kg RPG (suspended in normal saline) via a gavage needle26. Rats in the co-RPG+EUG groups orally received 50, 100, and 150 mg/kg EUG, respectively, once daily for seven consecutive days, and on the eighth day, after an additional 12‑h fasting period, the co-administration group was additionally given 0.4 mg/kg RPG via intragastric gavage. Subsequently, blood glucose parameters were assessed using blood samples collected from the tail vein.
For pharmacokinetic analysis, the blood sample (0.2 mL) was collected from the posterior orbital venous plexus of the rats into the heparinized microcentrifuge tubes at various time points (0.25 h, 0.5 h, 1 h, 2 h, 4 h, 6 h, and 8 h post-dose). After collection, the samples were centrifuged (1500 × g, 10 min, 4 °C) to separate the plasma (pale yellow, clear), which was stored at -80 °C until analysis. The plasma samples were subsequently analyzed for RPG concentration using the HPLC method described in step 4.
3. Metabolism study in the pooled rat liver microsomes
To investigate the mechanism underlying the in vivo pharmacokinetic changes, the effect of EUG on the RPG metabolic stability and CYP3A activity was evaluated in RLM. RPG (3 µM) was incubated with or without EUG in PBS buffer at 37 °C with a total volume of 200 µL, including RLM (0.5 mg/mL microsomal protein) and a NADPH regeneration system (1.3 mM NADP, 3.54 mM glucose 6-phosphate, 0.4 U/mL glucose 6-phosphate dehydrogenase, and 3.3 mM MgCl2). After a 5‑min pre‑incubation at 37 °C without NADPH, the reaction was initiated by adding the NADPH regeneration system. The mixture was then incubated at 37 °C in a shaking water bath. At different incubation time points (0 min, 5 min, 15 min, 30 min, 45 min, 60 min), 30 µL samples were collected and transferred to a microcentrifuge tube with ice-cold acetonitrile to terminate the reaction. The samples were centrifuged (12000 × g for 10 min at 4 °C) to obtain the supernatant (clear). The resulting supernatants were then analyzed for RPG concentration using the same HPLC method detailed in step 4.
4. HPLC analysis
The RPG concentration in plasma (from step 2) and microsomal incubations (from step 3) was analyzed using the HPLC method reported by Kim et al.26. The specific operation steps are as follows: samples (120 µL) were mixed with 300 µL of acetonitrile containing ketoconazole (internal standard, 100 ng/mL) to achieve protein precipitation. Then, the mixture was vortexed and centrifuged at 15000 × g for 10 min at 4 °C. The supernatant was transferred to a microcolumn centrifuge tube and evaporated at 25 °C under a nitrogen atmosphere. The residue after drying was re-dissolved with 50 µL mobile phase, then vortexed and centrifuged. Subsequently, 40 µL of the supernatant was injected into the HPLC column (250 mm × 4.6 mm, particle size 5 µm). The column was eluted at 25 °C in an isocratic elution mode with 10 mM phosphate buffer (pH 6.0) and acetonitrile (volume ratio 46.4: 53.6), with a flow rate of 1 mL/min. The eluent was monitored using a fluorescence detector with an excitation wavelength of 240 nm.
5. Statistical analysis
Pharmacokinetic analysis software was used to calculate pharmacokinetic parameters, including AUC, Cmax, Tmax, t1/2, MRT, and clearance. Statistical analysis and graphing software were used for figure generation and data analysis. All data were presented as mean ± standard deviation. Differences among groups were analyzed using one-way ANOVA (for glucose level comparisons) or two-way ANOVA (for pharmacokinetic parameter comparisons), as appropriate, followed by Tukey’s post hoc test for multiple comparisons. The effect of EUG on CYP3A activity was evaluated using nonlinear regression analysis. A p-value < 0.05 was considered statistically significant.
Half-life of EUG on RPG metabolic stability in RLM was calculated by:
t1/2 (min) = 0.693/ln(Ct/C0 × 100).
Intrinsic clearance rate (µL/min/mg protein) = v × 0.693/t1/2;
v (µL/mg) = incubation volume/protein concentration.
Results
EUG promoted the hypoglycemic effect of RPG in T2DM rats
The blood glucose level of the rats in the T2DM group was increased (p < 0.001, 95% CI: -13.90~-11.32) in comparison with that of the control group, indicating the successful conduction of the T2DM model (Figure 1A). Administration of a single RPG suppressed the blood glucose level in the T2DM rats (p < 0.001, 95% CI: 5.26~7.84). Co-administration of RPG and EUG further decreased the glucose level of T2DM rats in an EUG dose-dependent manner (p < 0.001, 95% CI for EUG 50 mg: 2.01~4.59; 95% CI for EUG 100 mg: 4.12~6.70; 95% CI for EUG 150 mg: 5.12~47.70) compared with T2DM rats administered a single RPG (Figure 1B).
EUG improved the systemic exposure of RPG in T2DM rats
The plasma concentration distribution of RPG (single administration or co-administered with EUG) is shown in Figure 2A, and the corresponding pharmacokinetic parameters are detailed in Table 1. The combined administration of EUG and RPG showed that the pharmacokinetic parameters of RPG increase dose-dependently, specifically manifested as the area under the curve (AUC, p < 0.001 for single RPG vs all co-RPG+EUG groups) and plasma maximum concentration (Cmax, p = 0.001 for single RPG vs co-RPG+EUG 50 mg group, p < 0.001 for single RPG vs co-RPG+EUG 100 and 150 mg groups) increasing correspondingly with the elevation in EUG concentration. Additionally, the mean retention time (MRT, p < 0.001 for single RPG vs all co-RPG+EUG groups) and elimination half-life (t1/2, p = 0.001 for single RPG vs co-RPG+EUG 50 mg group, p < 0.001 for single RPG vs co-RPG+EUG 100 and 150 mg groups) of the combined treatment (co-RPG+EUG) group show dose-dependent prolongation, while the clearance rate (CLz/F, p < 0.001 for single RPG vs all co-RPG+EUG groups) of RPG is lower compared to the single RPG treatment group. The time to reach maximum concentration (Tmax) in the combined treatment group exhibited a delayed trend compared to the single RPG group, and no statistical significance was observed among the co-administration groups, as the Tmax was 1 h.
EUG facilitated the metabolic stability of RPG and suppressed the CYP3A activity in RLM
The in vitro RLM study revealed that the half-life (t₁/₂) of RPG was 38.44 ± 2.30 min, and the intrinsic clearance rate was 36.15 ± 2.23 µL/min/mg protein. Co-incubation with EUG significantly prolonged the half-life of RPG (47.43 ± 2.54 min, p = 0.011, 95% CI: 3.49~14.49) and reduced its intrinsic clearance rate (29.28 ± 1.53 µL/min/mg protein, p = 0.012, 95% CI: -11.20~-2.54), indicating that the metabolic stability of RPG was enhanced due to the presence of EUG. Additionally, EUG exhibited a concentration-dependent inhibitory effect on CYP3A activity, with an IC₅₀ value of 7.90 ± 1.79 µM (Figure 2B), providing indirect evidence for the potential association with CYP3A‑mediated interaction.
DATA AVAILABILITY:
Data supporting the findings of this study are provided in Supplementary File 1.
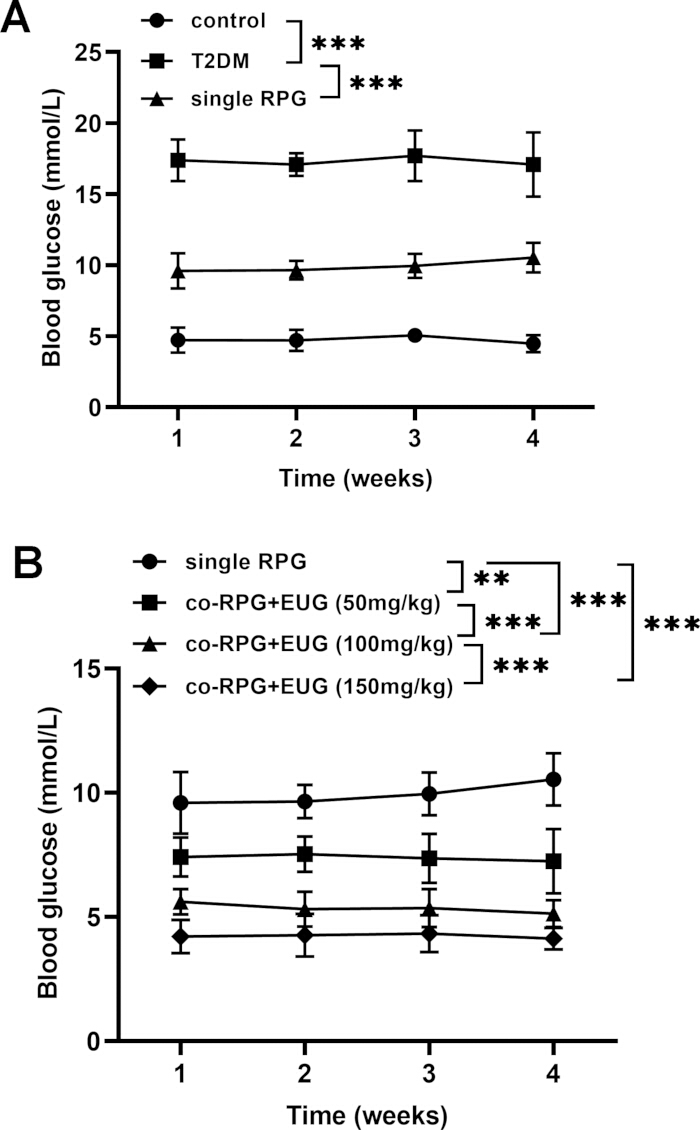
Figure 1: The blood glucose levels of the rats after different treatments. (A) Single RPG administration obviously decreased the glucose level of T2DM rats. (B) The blood glucose level further decreased in T2DM rats when RPG was co-administered with EUG in a dose-dependent manner. **p < 0.01, ***p < 0.001. Please click here to view a larger version of this figure.
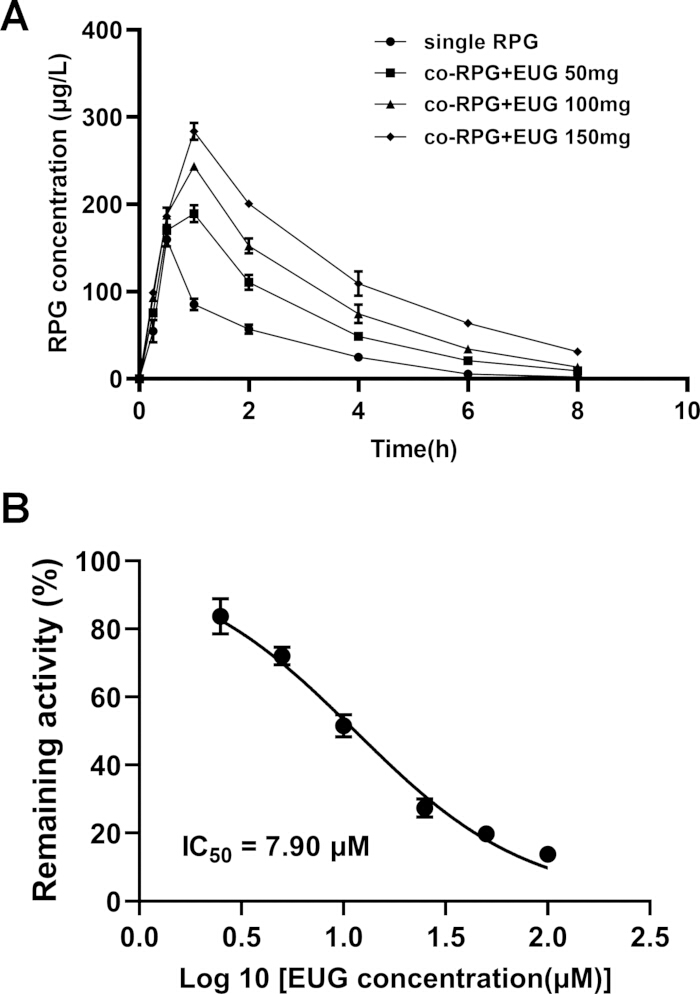
Figure 2: RPG pharmacokinetic curve and its effect on the activity of CYP3A in RLM. (A) RPG co-administered with EUG in T2DM rats significantly improved the systemic exposure of RPG in a dose-dependent manner compared with the single RPG administration. (B) The remaining activity of CYP3A was decreased in a concentration-dependent manner with increasing EUG concentration, yielding an IC50 value of 7.90 ± 1.79 µM. Please click here to view a larger version of this figure.
| Parameters | Single RPG | co-RPG+EUG | co-RPG+EUG | co-RPG+EUG |
| (50 mg) | (100 mg) | (150 mg) | ||
| AUC(0-t) (μg/L×h) | 285.97 ± 24.18 | 539.44 ± 35.87 a | 736.53 ± 39.43 ab | 985.80 ± 51.49 abc |
| MRT(0-t) (h) | 1.93 ± 0.01 | 2.27 ± 0.04 a | 2.44 ± 0.07 ab | 2.78 ± 0.04 abc |
| t1/2 (h) | 1.27 ± 0.03 | 1.70 ± 0.02 a | 1.90 ± 0.05 a | 2.39 ± 0.17 abc |
| Tmax (h) | 0.5 | 1 | 1 | 1 |
| CLz/F (L/h/kg) | 1.39 ± 0.12 | 0.71 ± 0.05 a | 0.51 ± 0.03 ab | 0.36 ± 0.03 ab |
| Cmax (μg/L) | 159.73 ± 8.13 | 189.46 ± 9.91 a | 243.71 ± 3.98 ab | 283.73 ± 9.73 abc |
| Notes: RPG, repaglinide; EUG, eugenol; AUC, area under curve; MRT, mean residence time; t1/2, half life; Tmax, time to maximum concentration; CLz/F, apparent clearance; Cmax, maximum concentration. a: p < 0.05 compared with the single RPG group, b: p < 0.05 compared with the co-RPG+ EUG (50 mg) group, c: p < 0.05 compared with the co-RPG+ EUG (100 mg) group. | ||||
Table 1: The pharmacokinetic parameters of RPG single administration and co-administration with EUG. ap < 0.05 compared with the single RPG group, bp < 0.05 compared with the co-RPG+ EUG (50 mg) group, cp < 0.05 compared with the co-RPG+ EUG (100 mg) group.
Supplementary File 1: Data supporting the findings of this study.Please click here to download this file.
Discussion
T2DM is a chronic metabolic disease that requires long-term treatment, and patients often need to take multiple medications due to underlying conditions such as cardiovascular disease and kidney disease32. The risk of DDIs significantly increases with drug co-administration, as it may affect the absorption, metabolism, or efficacy of hypoglycaemic drugs, which can lead to acute risks such as hypoglycaemic coma and uncontrolled blood sugar levels33. It may also exacerbate organ damage and accelerate the progression of complications34. Thus, DDI evaluation is not only a prerequisite for avoiding adverse reactions and maintaining stable blood glucose levels for T2DM patients but also an important means of reducing the incidence of complications and improving patients' long-term prognosis, highlighting the essential role of DDI assessment in ensuring the safety of drug co-administration.
STZ is commonly used to induce a T2DM animal model as it can target pancreatic β cells via the glucose transporter 2 and releases the nitrosourea group, which produces free radicals that damage the DNA of β cells, depletes energy, promotes β cell apoptosis, resulting in insufficient insulin secretion and the onset of T2DM35. Previous studies have investigated the DDI in STZ-induced T2DM. For instance, viitexin was found to significantly increase the hypoglycemic effect of glibenclamide in STZ-induced T2DM rats through improving the exposure of glibenclamide in vivo and enhancing the metabolic stability of glibenclamide in vitro36. Additionally, DDIs between RPG and QCT have been reported, showing that QCT improved RPG absorption and attenuated its metabolism in T2DM rats26. In this study, the induction of STZ significantly increased the blood glucose levels of the rats, indicating the successful induction of T2DM models. Single RPG treatment decreased blood glucose levels of T2DM rats, further supporting the hypoglycaemic effect of RPG37. Following RPG administration, blood glucose concentrations decreased in a dose-dependent manner when co-administered with an increased dose of EUG, suggesting potential interactions between EUG and RPG that enhance hypoglycemic efficacy in T2DM rats. However, blood glucose levels in T2DM rats receiving co-administration with 150 mg/kg EUG were lower than those in the control group, indicating that high-dose EUG may increase the risk of hypoglycemia when co-administered with RPG. Using body surface area normalization, the 150 mg/kg dose in rats approximates a human equivalent dose of approximately 24 mg/kg38, which is considerably higher than the typical dietary or supplement intake of eugenol from clove products. Therefore, under normal culinary use of EUG with RPG, the risk of clinically relevant hypoglycemia is likely low. Nevertheless, patients taking concentrated eugenol supplements or high‑dose traditional herbal preparations containing clove oil might face a significant safety hazard when co‑administering repaglinide. To mitigate this risk, it is recommended that such patients perform more frequent self‑monitoring of blood glucose. If recurrent hypoglycemia is detected, a preventive dose reduction of RPG should be considered, followed by individualized titration based on glycemic response. These findings might underscore the need for clinical studies to establish safe co‑administration guidelines for EUG and RPG in T2DM management.
An in vivo animal pharmacokinetics study was conducted to further explore the potential effect of EUG on RPG metabolism, taking advantage of animal models to enable controlled dosing, serial blood/tissue sampling, and assessment of systemic metabolite profiles that are not feasible in vitro or in humans at early stages39. It has been previously demonstrated that EUG exhibits extremely low toxicity, as no acute toxicity symptoms were observed in rats when administered a single dose of 2000 mg/kg EUG daily for 14 consecutive days40. This finding supported the safety of the 150 mg/kg dosage employed in the present study. According to the pharmacokinetic curve, the AUC and Cmax values were enhanced gradually based on the incremental EUG concentration, indicating the increased blood concentration of RPG in rats, as both AUC and Cmax represent the total exposure of the RPG in the body and are positively correlated with the degree of RPG absorption41,42. In addition, RPG co-administered with increasing doses of EUG significantly prolonged the mean residence time (MRT), half-life (t1/2), and time to maximum concentration (Tmax) of RPG in vivo, suggesting EUG might slow RPG metabolism, resulting in prolonged drug retention time and potentially extending the therapeutic duration of RPG. Decreased apparent clearance (Clz/F) value provided further evidence of impaired RPG metabolism, as this parameter directly reflects the drug elimination rate43,44. Regarding the Tmax value, it was prolonged from 0.5 h to 1.0 h at the lowest EUG dose (50 mg/kg) and did not change further at higher EUG doses (100 and 150 mg/kg). This observation may be explained by saturation of intestinal first-pass metabolism. Once EUG at 50 mg/kg sufficiently inhibits CYP3A activity, the absorption phase reaches a physiological plateau, and further dose escalation primarily affects systemic metabolism rather than absorption kinetics45. In addition, the lack of further Tmax increase might also be due to the sampling time interval used. Blood samples were collected at 0.25 h, 0.5 h, 1 h, 2 h, 4 h, 6 h, and 8 h post-dose. With this schedule, if the true Tmax in the 50 mg/kg group was 0.75 h, and that in the higher dose groups was 0.9 h or 1.1 h, both would be recorded as 1.0 h. Thus, the apparent ceiling effect could be partly an artifact of the discrete sampling intervals rather than a true absence of dose‑dependent delay. Finer sampling during the early absorption phase (e.g., at 0.5 h, 0.75 h, and 1.0 h) would be needed to determine whether Tmax truly continues to increase with higher EUG doses. Collectively, these findings demonstrated that EUG enhanced the bioavailability of RPG and delayed its metabolism in T2DM rats. This interaction might provide valuable insights for optimizing the co-administration strategy of EUG and RPG in clinical settings to improve therapeutic outcomes.
P450s are predominantly localized in liver microsomes and play a pivotal role in drug metabolism and are essential for evaluating potential DDIs23,46. To investigate the potential mechanism of EUG in affecting RPG, in vitro RLM experiments were performed, revealing that the half-life of RPG was delayed with reduced intrinsic clearance rate, which was consistent with the in vivo pharmacokinetics study. This in vitro approach offers several advantages, including isolation of hepatic metabolic enzymes from systemic confounding factors, precise control of cofactor and substrate concentrations, and direct determination of enzyme kinetic parameters47. In humans, RPG is primarily metabolized by CYP2C8 and CYP3A425,48,49. However, as rats lack the CYP2C8 isoform, the evaluation was confined to CYP3A activity50. In RLMs, CYP3A serves a similar functional role to human CYP3A4, which acts as a dominant enzyme in the metabolism of numerous xenobiotics and clinically important drugs51,52. CYP3A activity was decreased in a concentration-dependent manner with increasing EUG exposure, yielding an IC50 value of 7.90 µM, indicating a moderate inhibitory effect of EUG on CYP3A. It has been reported that RPG is partly metabolized by CYP3A448,53, supporting that EUG could improve the RPG systemic exposure through inhibiting the activity of CYP3A4, which might provide further evidence for the increased blood RPG concentration in the in vivo study after co-administration with EUG.
The above findings revealed the potential DDI between EUG and RPG, suggesting that EUG may increase systemic exposure of RPG by inhibiting CYP3A4 activity, thereby providing a theoretical foundation for their rational clinical co-administration. However, several limitations still warrant further investigation. The absence of a healthy (non-diabetic) control group receiving RPG alone might limit the direct interpretation of whether the observed changes in RPG pharmacokinetics are specifically attributable to EUG or partly to the diabetic state itself. However, the primary objective of this study was to evaluate the metabolic interaction between EUG and RPG specifically in the context of T2DM. Therefore, the experimental design included a single RPG group and RPG + EUG co‑administration groups, all under the same T2DM condition, allowing for the exclusion of the confounding effect of the diabetic state, and to demonstrate that EUG significantly inhibited RPG metabolism in T2DM rats. Furthermore, although a previous study has reported that oral administration of EUG at 50 mg/kg in rats achieves a peak plasma concentration of approximately 25 µg/mL40, the plasma EUG concentrations in the present study were not directly measured. Measurement of EUG plasma concentrations would further strengthen the correlation between in vitro and in vivo data and enable more precise translational interpretation. CYP2C8 is another major metabolic enzyme involved in the metabolism of RPG49,54. However, since rats lack the CYP2C8 isoform50, the in vivo and in vitro data in this work only captured the inhibitory effect of EUG on CYP3A activity, without any contribution from potential CYP2C8 inhibition. This absence of CYP2C8 evaluation means that these findings may not fully reflect the DDI profile in humans. Importantly, a previous study using human liver microsomes reported that EUG also inhibits CYP2C8 activity in a concentration-dependent manner27. Therefore, it is plausible that in humans, EUG could simultaneously inhibit both CYP3A4 and CYP2C8, leading to a greater increase in repaglinide systemic exposure than observed in the rat model. This potential additive or synergistic inhibition could further enhance the hypoglycemic effect but also elevate the risk of severe hypoglycemia. Thus, direct extrapolation of the quantitative pharmacokinetic parameters to clinical settings should be made with caution. Future studies using human liver microsomes, recombinant CYP2C8 enzyme systems, or clinical pharmacokinetic trials are needed to fully characterize the interaction between EUG and repaglinide in humans, particularly the contribution of CYP2C8 inhibition. In addition, given that RPG is metabolized by CYP3A4 and EUG has been shown to inhibit CYP3A, the potential of EUG in affecting the metabolism of other CYP3A4 substrates when co-administered warrants additional investigation. Specifically, the mode of inhibitory effect of EUG on CYP3A remains to be elucidated. Without a formal assessment of the inhibition mechanism, it is currently unclear whether EUG acts as a competitive inhibitor (binding reversibly to the active site of CYP3A), a non‑competitive inhibitor (binding to a different site and reducing enzyme activity without competing with the substrate), or a mechanism‑based inhibitor (causing irreversible inactivation of the enzyme, often time‑ and NADPH‑dependent)55. Each of these modes would have different pharmacokinetic and safety implications for co‑administered drugs. Furthermore, developing new dosage forms, such as solid lipid nanoparticles, may help reduce DDIs, enhance drug absorption, and decrease the required dosage, which is an important direction for future research56. Despite the aforementioned limitations, this work still revealed that EUG may enhance the in vivo bioavailability of RPG, at least in part, by suppressing CYP3A activity. This finding provided a theoretical basis for further mechanistic investigations into the effects of EUG on RPG bioavailability.
Conclusion
In summary, this study demonstrated that EUG enhanced the hypoglycemic effect of RPG in T2DM rats. Pharmacokinetically, EUG dose‑dependently increased RPG systemic exposure, prolonged half‑life, and reduced clearance. Mechanistically, EUG improved RPG metabolic stability and inhibited CYP3A activity. These findings might indicate that EUG enhanced RPG bioavailability mainly via CYP3A inhibition. Clinically, co‑administration of EUG‑rich products with RPG may improve efficacy but requires careful dose adjustment to avoid hypoglycemia. This work might provide a theoretical basis for evaluating DDIs between natural compounds and antidiabetic drugs.
Disclosures
The authors have no financial or proprietary interests in any material discussed in this article.
Acknowledgements
This study was funded by Clinical Study on the Treatment of Vestibular Migraine with Tongxuan Acupuncture Combined with Vestibular Rehabilitation Training (2018187)and Screening and network pharmacology analysis of xanthine oxidase inhibitors based on bioinformatics technology (YDZJ202301ZYTS121).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| acetonitrile | Merck, Germany | 34851 | ≥99.9% |
| chromatographic column | Phenomenex, USA | 00G-4041-E0 | 250 mm × 4.6 mm, particle size 5 μm |
| DAS | Beijing Bozhiyin, China | - | 3.0 |
| EUG | MUST Bio-technology, China | A0074 | purity ≥99% |
| GraphPad Prism | GraphPad Software, USA | - | 9.0.0 |
| High Performance Liquid Chromatography | Shimadzu Corporation, Japan | 228-45147-42 | RF-20A |
| ketoconazole | Merck, Germany | K1003 | Purity 99.0-101.0% |
| Male Sprague-Dawley rats | Shanghai Animal Center, China | - | 200–250 g |
| NADPH | Merck, Germany | 10107824001 | 97% (dry weight) |
| OneTouch Ultra2 blood glucose meter | Life Scan Inc., USA | https://shop.onetouch.com/onetouch-sup-reg-sup-ultra-sup-reg-sup-2-meter/product/OTSUS05_0019 | - |
| PBS | Merck, Germany | P4474 | ph 7.4 |
| RLM | Merck, Germany | M9066 | - |
| RPG | Merck, Germany | R9028 | purity ≥98% |
| STZ | Merck, Germany | S0130 | ≥98% (HPLC) |
| EUG, eugenol; RPG, repaglinide; RLM, rat liver microsomes; NADPH, β-Nicotinamide adenine dinucleotide phosphate; STZ, streptozotocin; PBS, phosphate-buffered saline. |