This controlled before-and-after study demonstrates that a Plan-Do-Check-Act (PDCA)-based governance bundle significantly improves hand hygiene compliance. Furthermore, the intervention effectively reduces hospital-acquired infection rates and elevates nursing management quality in inpatient wards, providing a sustainable, data-driven framework for institutional infection control.
Research Article
Impact of a Plan-Do-Check-Act Hand Hygiene Bundle on Compliance, Infection Rates, and Nursing Quality: A Controlled Before-and-After Study
In This Article
Summary
Abstract
Hand hygiene remains one of the most important measures for preventing hospital-acquired infections, yet sustained compliance in routine inpatient care remains difficult to achieve through reminders or training alone. This study evaluated the effect of a Plan–Do–Check–Act (PDCA)-based hand hygiene governance bundle on hand hygiene compliance, hospital-acquired infection rates, and nursing management quality. A controlled before-and-after study was conducted in 16 inpatient wards of a general hospital. Eight wards received a PDCA-based hand hygiene governance bundle, while eight control wards continued routine hand hygiene management. The study covered a 12-month period, including a 6-month pre-intervention period and a 6-month post-intervention period. The ward-month was used as the main analytical unit. The primary outcome was monthly hand hygiene compliance. Secondary outcomes included hospital-acquired infection rate per 1,000 patient-days and nursing management quality score. Difference-in-differences models were used to estimate intervention-associated changes. Hand hygiene compliance increased from 66.2% to 83.2% in the intervention group and from 63.1% to 66.8% in the control group. The adjusted difference-in-differences odds ratio (OR) for hand hygiene compliance was 2.38 (95% CI: 2.19–2.59, P < 0.001). Hospital-acquired infection rates decreased from 7.07 to 4.37 per 1,000 patient-days in intervention wards, with an adjusted incidence rate ratio of 0.60 (95% CI: 0.52–0.69, P < 0.001). Nursing management quality scores increased more substantially in intervention wards than in control wards. The PDCA-based hand hygiene governance bundle was associated with improved hand hygiene compliance, lower hospital-acquired infection rates, and higher nursing management quality. Embedding hand hygiene into repeated ward-level governance cycles may provide a practical strategy for strengthening infection-control management.
Introduction
Hospital-acquired infections remain a major challenge for patient safety because they increase morbidity, prolong hospitalization, raise healthcare costs, and place additional pressure on clinical staff and hospital management. The WHO Guidelines on Hand Hygiene in Health Care1 position hand hygiene as a core infection-prevention practice because transmission of microorganisms through the hands of healthcare workers is one of the most preventable pathways in healthcare settings. Although the principle is simple, reliable implementation remains difficult in real clinical environments where workload, role differences, supply access, habits, and supervision all influence daily practice.
The burden of healthcare-associated infection is not evenly distributed across healthcare systems. In their review of endemic healthcare-associated infections, Allegranzi et al.2 showed that infection burden is particularly substantial in settings where infection-control infrastructure and surveillance capacity are limited. This problem is not confined to resource-limited systems. Magill et al.3, through a multistate prevalence survey in acute care hospitals, also showed that healthcare-associated infections remain a persistent problem even in highly developed hospital systems. These findings indicate that infection prevention cannot depend only on written policies; it requires observable, repeatable, and accountable clinical behavior.
Hand hygiene is one of the most visible and measurable behaviors within infection prevention. The “My Five Moments for Hand Hygiene” framework proposed by Sax et al.4 translated hand hygiene indications into practical moments that healthcare workers can recognize during patient care. This framework is particularly useful for observation, training, and feedback because it connects hand hygiene behavior to specific care situations rather than treating compliance as a general attitude. However, the gap between knowing the five moments and consistently performing hand hygiene during routine care remains a persistent management problem.
Earlier intervention research has shown that hand hygiene improvement can be achieved when behavioral change is supported by system-level action. Pittet et al.5 reported that a hospital-wide hand hygiene program improved compliance and coincided with reductions in nosocomial infection and methicillin-resistant Staphylococcus aureus transmission. This finding was important because it suggested that hand hygiene improvement should be understood as an institutional practice rather than purely individual behavior. In other words, compliance improves when staff education is supported by accessible hand hygiene resources, monitoring, feedback, and leadership commitment.
The WHO multimodal hand hygiene improvement strategy further developed this institutional perspective by emphasizing system change, training and education, evaluation and feedback, reminders in the workplace, and institutional safety climate6. In a multicountry quasi-experimental study, Allegranzi et al.7 demonstrated that this multimodal strategy was feasible across diverse healthcare settings and was associated with significant improvements in hand hygiene compliance. These studies provide strong evidence for multimodal intervention, but hospitals still need locally actionable governance models that translate broad strategic components into routine ward-level management.
Recent evidence continues to support the link between hand hygiene compliance and infection prevention, while also showing that the effect size can vary across settings and intervention designs. Mouajou et al.8, in a systematic review of hand hygiene compliance and hospital-acquired infection prevention, found that improved compliance is generally associated with reduced infection risk, but the relationship is influenced by baseline compliance, intervention intensity, measurement method, and infection surveillance quality. This means that hand hygiene programs should not only report whether compliance improved but also show how the intervention was implemented and whether management processes changed alongside behavioral outcomes.
Many existing interventions rely heavily on education, posters, reminders, or short-term audits. These measures may improve awareness, but they often fail to create a durable governance loop. Gould et al.9, in a review of interventions to improve hand hygiene compliance, noted that multimodal and feedback-based approaches are more promising than single-component interventions, but heterogeneity in design and implementation makes it difficult to identify which management elements are most effective. This gap is important for nursing and infection-control practice because ward managers need interventions that are not only theoretically sound but also operationally repeatable.
Behavioral and organizational barriers also need to be considered. Huis et al.10 emphasized that hand hygiene improvement depends on determinants such as knowledge, social influence, perceived control, leadership, and feedback. These determinants suggest that hand hygiene should be governed through a structured management process rather than addressed only through individual reminders. In inpatient wards, head nurses and infection-control teams are well positioned to connect observation data, staff training, supply management, and corrective action, but this requires a clear operational framework.
The Plan–Do–Check–Act cycle offers such a framework because it organizes quality improvement into repeated cycles of problem identification, implementation, monitoring, and correction. Sua et al.11 applied PDCA management to hand hygiene and nosocomial infection quality control, showing that cyclic management can improve hand hygiene compliance and infection-control quality in a clinical department. However, more evidence is needed on how PDCA-based hand hygiene governance affects multiple ward-level outcomes simultaneously, especially when compliance, hospital-acquired infection rates, nursing management quality, knowledge scores, and alcohol-based hand rub consumption are examined within the same study structure.
Measurement quality is another important issue in hand hygiene research. Direct observation remains useful because it allows classification by professional role and hand hygiene moment, but it may overestimate compliance when healthcare workers know they are being observed. Srigley et al.12 quantified this Hawthorne effect in hand hygiene monitoring and showed that observed hand hygiene activity may increase when auditors are visible. Therefore, to mitigate this bias, studies relying on direct observation should employ unobtrusive monitoring techniques, utilize unpredictable observation schedules to prevent behavioral conditioning, distribute audits across diverse shifts and staff groups, and interpret compliance results with appropriate caution.
At the same time, quality-improvement studies require transparent reporting of context, intervention content, implementation process, and outcome assessment. The SQUIRE 2.0 guideline developed by Ogrinc et al.13 highlights the need to describe not only whether an intervention worked, but also what was done, how it was implemented, and why the observed changes may have occurred. This principle is particularly relevant for hand hygiene governance because the reproducibility of an intervention depends on concrete details such as training frequency, observation thresholds, feedback mechanisms, corrective action triggers, and ward-level accountability.
Based on these considerations, the present study evaluated a PDCA-based hand hygiene governance bundle in inpatient wards using a controlled before-and-after design. The intervention integrated baseline gap analysis, staff training, visual reminders, supply monitoring, direct observation of hand hygiene, monthly feedback, corrective action, and repeated ward-level reassessment. The study aimed to examine whether this governance bundle was associated with improved hand hygiene compliance, reduced hospital-acquired infection rates, and higher nursing management quality compared with routine hand hygiene management.
Protocol
The study protocol was reviewed and approved by the Ethics Committee of Guangzhou Panyu Shiqiao Hospital (Approval Number: ASJIO729). Because the study strictly used routinely collected, de-identified ward-level quality-improvement and infection-control indicators, the ethics committee explicitly waived the requirement for individual informed consent. No patient names, staff names, medical record numbers, or other directly identifiable information were included in the analytical dataset, and data access was restricted to authorized members of the study team.
Study design
This controlled before-and-after study evaluated the effect of a PDCA-based hand hygiene governance bundle on hand hygiene compliance, hospital-acquired infection rates, and nursing management quality in inpatient wards. The study used the ward-month as the main analytical unit and compared changes between intervention wards and control wards across a pre-intervention and post-intervention period. The methodological structure followed quality improvement reporting principles described in SQUIRE 2.013.
The study workflow is shown in Figure 1, including ward selection, group allocation, baseline observation, intervention implementation, monthly outcome assessment, and repeated PDCA cycles. Baseline ward-level characteristics during the pre-intervention period are summarized in Table 1.
Setting and study period
The study was conducted in 16 inpatient wards of a general hospital, which comprises a total of 32 inpatient wards. Eight wards were assigned to the intervention group, and eight to the control group. Ward allocation was based on the hospital's administrative and infection-control implementation planning rather than individual randomization. Strict randomization was not practically feasible for two primary reasons. First, the PDCA governance bundle required intensive logistical coordination, including specialized observer training and targeted management feedback, which necessitated a guided, phased rollout rather than random assignment. Second, purposeful non-random allocation allowed hospital administrators to group wards in a manner that minimized the risk of structural and administrative cross-contamination between the intervention and control units. To reduce selection bias, intervention and control wards were selected to achieve approximate balance in ward type, baseline patient-days, baseline hand hygiene compliance, baseline hospital-acquired infection rate, and baseline nursing management quality.
The observation period covered 12 consecutive months. The first 6 months were defined as the pre-intervention period, during which both groups received routine hand hygiene management. The following 6 months were defined as the post-intervention period. During the post-intervention period, the intervention wards received the PDCA-based hand hygiene governance bundle, while the control wards continued routine infection-control management. The ward selection, exposure definition, outcome specification, and group comparison structure were organized according to observational study reporting principles14.
The ward-month was selected as the analytical unit because hand hygiene compliance, hospital-acquired infection counts, patient-days, nursing management quality scores, and process indicators were collected and summarized monthly at the ward level. Each of the 16 wards contributed 12 monthly records, resulting in 192 ward-month observations.
Study units and eligibility criteria
A ward-month record was eligible for analysis if the ward remained open for the full calendar month, admitted inpatients during that month, had complete patient-day records, had available hand hygiene observation data, and had a completed nursing management quality assessment for the same month.
Ward-month records were excluded if the ward was temporarily closed, merged with another ward, converted to another clinical function, or experienced a major service disruption that made monthly infection surveillance incomplete. Records were also excluded if any core outcome variable was missing, including hand hygiene opportunities, hand hygiene actions, patient-days, hospital-acquired infection counts, or nursing management quality scores.
Healthcare workers included in hand hygiene observation were nurses, physicians, and care assistants who provided direct patient care in the participating wards. Observations involving administrative personnel, visitors, students without independent clinical duties, temporary visitors, or staff not involved in direct patient care were not included.
Intervention: PDCA-based hand hygiene governance bundle
The intervention was a structured hand hygiene governance bundle implemented through repeated Plan–Do–Check–Act cycles. The bundle combined baseline gap analysis, staff training, workflow reminders, supply monitoring, direct observation of hand hygiene, audit feedback, ward-level accountability, and targeted corrective actions. The intervention structure followed the core components of multimodal hand hygiene improvement, including system change, education, evaluation and feedback, reminders, and safety climate reinforcement6.
During the Plan phase, the infection-control team reviewed baseline hand hygiene compliance, hand hygiene opportunities, hospital-acquired infection rates, alcohol-based hand rub consumption, and nursing management quality scores in each intervention ward. The team identified ward-specific problems, including low compliance before patient contact, missed hand hygiene before aseptic procedures, inconsistent use of alcohol-based hand rub, delayed feedback after audit, and incomplete linkage between hand hygiene performance and nursing management review. Each intervention ward developed a monthly improvement plan specifying the target problem, the person responsible, the expected completion time, the follow-up method, and the measurable target.
During the Do phase, the planned improvement measures were implemented. Each intervention ward received one structured training session at the beginning of the intervention period and one brief refresher session each month. Each session lasted approximately 20–30 min and was delivered by infection-control nurses. Training covered hand hygiene indications, correct use of alcohol-based hand rub, handwashing technique, glove use, and infection-control risk points. Visual reminders were placed near patient bedsides, treatment rooms, medication preparation areas, nursing stations, and ward entrances. The accessibility of alcohol-based hand rub was checked weekly. Empty, misplaced, or poorly accessible dispensers were corrected within 24 h by the ward nursing team. Head nurses organized short ward-level briefings to reinforce hand hygiene requirements during routine nursing management.
During the Check phase, trained observers conducted monthly hand hygiene observations. Observers recorded approximately 180–260 hand hygiene opportunities per ward per month, depending on ward workload and patient care activities. To systematically mitigate the Hawthorne effect, these observations were not conducted in single, prolonged blocks. Instead, they were divided into unannounced, short-duration sessions (typically 15–20 min) that were randomly distributed across various days of the week, including weekends, and across multiple working shifts. A ward-month was considered observation-complete when at least 150 valid hand hygiene opportunities were recorded. If fewer than 150 valid opportunities were recorded because of low activity or incomplete observation coverage, an additional observation session was arranged within the same month. Each observation recorded the professional role of the healthcare worker, the hand hygiene moment, the number of opportunities, and whether the required hand hygiene action was performed. Hand hygiene opportunities were classified according to the five indications of hand hygiene: before touching a patient, before clean or aseptic procedures, after body fluid exposure risk, after touching a patient, and after touching patient surroundings1.
During the Act phase, the intervention team used monthly findings to revise the next improvement cycle. Each intervention ward received a monthly feedback report that included overall hand hygiene compliance, compliance by professional role, compliance by hand hygiene moment, alcohol-based hand rub consumption, hospital-acquired infection rate, and nursing management quality score. Corrective action was triggered when any of the following criteria were met: monthly hand hygiene compliance below 80%, compliance for any professional group below 75%, compliance for any hand hygiene moment below 70%, hospital-acquired infection rate increasing by at least 20% compared with the ward’s pre-intervention mean, or repeated documentation problems in nursing management quality assessment. Wards meeting any trigger criterion completed a corrective action form within 7 days and received focused supervision in the following month. If a specific hand hygiene moment or professional group showed lower compliance, corrective actions were directed to that problem rather than repeated as general education. The next PDCA cycle then began with an updated problem list and revised ward-level improvement target.
Control condition and contamination control
Control wards continued routine hand hygiene management during the same study period. Routine management included standard infection-control policies, availability of alcohol-based hand rub, routine hand hygiene reminders, and regular infection-control supervision. Control wards did not receive the structured monthly PDCA cycle, ward-specific feedback reports, corrective action forms, intensified observation feedback, or targeted governance meetings used in the intervention wards.
To reduce contamination between groups, intervention-specific feedback reports, corrective action forms, ward-level PDCA records, and monthly improvement meetings were not circulated to control wards during the study period. Hospital-wide infection-control policies that applied to all wards were maintained consistently in both groups.
Outcome measures
The primary outcome was monthly hand hygiene compliance, assessed via direct human observation. Compliance was calculated at the individual ward-month level as the total number of observed hand hygiene actions within a specific ward during a given month divided by the corresponding total number of observed hand hygiene opportunities, multiplied by 100%. A hand hygiene action was counted as valid when the healthcare worker performed hand hygiene using alcohol-based hand rub or soap-and-water handwashing immediately after a defined opportunity occurred and before moving to the next care activity. Actions performed too early, too late, or unrelated to the observed opportunity were not counted as compliant actions.
The main secondary outcome was the hospital-acquired infection rate. Hospital-acquired infections were identified through the hospital infection-control surveillance system according to institutional surveillance criteria aligned with healthcare-associated infection monitoring practice. To ensure clarity and international comparability, the composite HAI rate in this study specifically included central line-associated bloodstream infections (CLABSI), catheter-associated urinary tract infections (CAUTI), surgical site infections (SSI), hospital-acquired/ventilator-associated pneumonia (HAP/VAP), and infections caused by targeted multidrug-resistant organisms (e.g., methicillin-resistant Staphylococcus aureus and Clostridioides difficile). Suspected cases were reviewed by infection-control practitioners, and monthly ward-level counts were finalized after verification with clinical records, microbiology reports, antimicrobial use records, temperature charts, imaging reports where applicable, and ward infection-control logs. The monthly hospital-acquired infection rate was calculated as the number of hospital-acquired infection cases divided by total patient-days and multiplied by 1,000. Patient-days were used as the denominator because they represent cumulative inpatient exposure time and are commonly used in healthcare-associated infection surveillance15.
Another secondary outcome was nursing management quality. Nursing management quality was assessed monthly using a structured ward-level assessment form. The assessment covered hand hygiene governance, infection-control documentation, availability of supplies, staff training completion, audit feedback, environmental management, and corrective action implementation. Scores ranged from 0 to 100, with higher scores indicating better nursing management quality. A monthly score below 80 was treated as a management-warning value and required review by the head nurse. A score below 75 triggered a written corrective action plan.
Additional process indicators included hand hygiene knowledge score and alcohol-based hand rub consumption. Hand hygiene knowledge was assessed using a structured knowledge test, with scores ranging from 0 to 100. A score of 80 or above was considered satisfactory. Staff with scores below 80 received additional brief training before the next monthly assessment. Alcohol-based hand rub consumption was calculated as milliliters per patient-day and was evaluated as a supporting process measure to objectively corroborate the direct observation findings of hand hygiene compliance. Detailed operational definitions, thresholds, and calculation formulas are provided in Supplementary Table 1.
Data collection procedures
Data were collected monthly from each participating ward. Hand hygiene observation data were collected by trained infection-control observers using a standardized observation form. Observers recorded the ward code, month, professional role, hand hygiene moment, number of opportunities, and number of performed actions. The same observation rules were applied to intervention and control wards.
Prior to formal data collection, all observers completed standardized calibration training and achieved ≥90% inter-rater agreement using standardized clinical scenarios. Detailed protocols regarding observer training, the five indications classification, and validation criteria are provided in Supplementary File 1.
Hospital-acquired infection cases and patient-day counts were obtained from routine infection-control surveillance records. Monthly admission counts and patient-days were checked against ward administrative records before analysis. Nursing management quality scores were obtained from monthly nursing quality assessments. Alcohol-based hand rub consumption was obtained from ward supply records and standardized by patient-days.
For each ward-month, the final analytical dataset included ward code, group assignment, month, study period, PDCA stage, admissions, patient-days, hand hygiene opportunities, hand hygiene actions, hand hygiene compliance, hospital-acquired infection cases, hospital-acquired infection rate per 1,000 patient-days, nursing management quality score, hand hygiene knowledge score, and alcohol-based hand rub consumption.
Data quality control and missing data handling
Rigorous data quality control procedures were implemented to minimize measurement bias and ensure data integrity. These included concurrent temporal observations for both groups, monthly data aggregation to reduce daily fluctuation noise, and strict predefined screening for logical inconsistencies or out-of-range values. A comprehensive description of the specific data-checking algorithms, flagging thresholds, and missing data handling procedures is detailed in Supplementary File 1.
Because direct observation of hand hygiene inherently risks altering staff behavior (the Hawthorne effect), the data collection protocol mandated strictly unpredictable observation schedules. By utilizing unobtrusive, brief monitoring windows randomly dispersed across different weekdays, weekends, varied shifts (morning, afternoon, and night), professional roles, and hand hygiene moments, the study sought to capture routine clinical practice rather than conditioned compliance. The identical observation protocol was applied equally to both groups to prevent differential measurement bias (i.e., ensuring observers did not apply differing levels of scrutiny between the intervention and control wards), whereas the aforementioned randomized scheduling was explicitly implemented to minimize sampling bias.
All included ward-month records contained complete core outcome variables. Therefore, no imputation was performed. Although predefined exclusion criteria were established a priori to handle potential ward closures or missing variables, no ward-month records actually met these criteria during the study. Consequently, zero records were excluded, and all 192 planned ward-month observations were completely retained, thereby ensuring that both intervention and control groups were continuously evaluated across the exact same 12-month calendar period.
Statistical analysis
Statistical analysis was performed using SPSS and R16. Descriptive tables were generated accordingly. Specific modeling approaches were tailored to the distribution of each outcome: logistic regression for hand hygiene compliance, Poisson or negative binomial regression for hospital-acquired infection rates, and linear regression for continuous nursing management quality and knowledge scores. All statistical estimations, incorporating the difference-in-differences framework and clustered standard error computations, were executed in R utilizing the stats, MASS, sandwich, and lmtest packages. Figures were prepared using GraphPad Prism and checked against the final statistical output.
Continuous variables were summarized as mean and standard deviation when approximately normally distributed, and as median and interquartile range when the distribution was skewed. The normality of continuous variables for descriptive summaries, as well as the normality of model residuals for linear regression analyses, was assessed using histograms, Q–Q plots, and the Shapiro–Wilk test. Categorical variables were summarized as counts and percentages. Baseline comparability between intervention and control wards was assessed using pre-intervention ward-level indicators, including admissions, patient-days, hand hygiene opportunities, hand hygiene compliance, hospital-acquired infection rate, nursing management quality score, hand hygiene knowledge score, and alcohol-based hand rub consumption.
The main analysis compared pre-intervention to post-intervention changes between intervention and control wards. For hand hygiene compliance, the model incorporated the number of hand hygiene actions as the outcome of interest, while explicitly specifying the varying number of observed hand hygiene opportunities per ward-month as the binomial denominator. This specification functionally accounts for the differential observation volumes across units in a manner analogous to an offset. The intervention effect was estimated using a logistic regression model within a difference-in-differences framework, incorporating group, period, and group-by-period interaction terms. Throughout the manuscript, the term 'adjusted' applied to effect estimates (e.g., adjusted odds ratios or incidence rate ratios) explicitly denotes that these parameters were derived from these fully specified multivariable models—mathematically adjusting for the study group main effect, period main effect, variable exposure volumes, and ward-level clustering—rather than implying the inclusion of additional clinical covariates. To prevent over-parameterization, the specific calendar month was not included as a continuous or categorical covariate in these primary models, as the binary 'period' variable sufficiently captured the overarching temporal shift. However, to ensure our findings were not confounded by seasonal fluctuations, calendar month was explicitly incorporated as an additional covariate within our predefined sensitivity analyses.
To formally validate the parallel trends assumption inherent to difference-in-differences modeling, pre-intervention monthly outcomes were visually inspected to confirm that the temporal slopes for the intervention and control wards were parallel prior to implementation. Statistically, this assumption was evaluated by introducing a group-by-month interaction term into the specific regression models tailored to each respective outcome (i.e., logistic, count, and linear models) restricted solely to the pre-intervention period; a non-significant interaction (P ≥ 0.05) confirmed that the pre-intervention trends (slopes) between the two groups did not significantly diverge, irrespective of any constant absolute differences in their baseline levels. The primary models reported effect estimates with 95% confidence intervals rather than relying only on P values.
For hospital-acquired infection rates, monthly infection counts were analyzed using a count model. Specifically, these models incorporated the study group, period, and the group-by-period interaction as fixed effects. To rigorously adjust for varying baseline exposure volumes across units, the natural logarithm of monthly patient-days was defined and entered as the offset term. In alignment with our overarching analysis strategy, ward-level clustering was accounted for using cluster-robust standard errors, and thus explicit random-effects parameters were not included in the model. The final choice between the Poisson and negative binomial specifications was explicitly determined by evaluating the dispersion parameter (θ) estimated from the initial negative binomial model. The simpler Poisson model was deemed appropriate when this parameter indicated no substantial overdispersion; otherwise, the negative binomial specification was retained to account for the excess variance. The effect estimate was reported as an incidence rate ratio with 95% confidence interval. Hospital-acquired infection rates were also described as cases per 1,000 patient-days.
For nursing management quality scores and hand hygiene knowledge scores, linear regression models were used with group, period, and group-by-period interaction terms; the resulting interaction coefficient (β) represents the adjusted mean difference in score improvements between the two groups. To rigorously account for ward-to-ward variability and the non-independence of monthly data, observations were strictly not treated as independent. Across all models—including those for hand hygiene compliance, hospital-acquired infections, nursing management quality, alcohol-based hand rub consumption, and all subgroup analyses—the fixed effects consistently comprised the study group, the intervention period, and their interaction. Rather than fitting generalized linear mixed models (GLMMs) with random effects, clustering was explicitly addressed by computing cluster-robust standard errors at the ward level for every model. This approach appropriately adjusts all P values and widens the confidence intervals to correct for intra-class correlation, directly ensuring that the inferential statistics are robust and not optimistically narrow. Alcohol-based hand rub consumption was analyzed quantitatively to serve as an objective proxy measure, triangulating the behavioral changes observed in hand hygiene compliance.
Subgroup analyses were conducted by professional role and hand hygiene moment. The professional role was categorized as nurse, physician, or care assistant. Hand hygiene moment was categorized as before touching a patient, before clean or aseptic procedures, after body fluid exposure risk, after touching a patient, and after touching patient surroundings. These analyses were considered supportive because the study was primarily designed to evaluate ward-level changes rather than individual-level staff effects.
Extensive sensitivity analyses were conducted to confirm the robustness of our primary models. These included excluding the initial implementation transition month to account for phase-in effects and explicitly incorporating the calendar month as an additional covariate to adjust for potential seasonal variations. To streamline the main text, the detailed methodologies and complete results for these sensitivity analyses are provided exclusively in Supplementary File 2.
Although the intervention was hypothesized to yield beneficial outcomes, all statistical tests remained two-sided to conservatively allow for the detection of any unintended negative effects (e.g., paradoxical decreases in compliance or increases in infection rates), aligning with standard epidemiological reporting practices. A P value below 0.05 was considered statistically significant. No adjustment for multiple comparisons was applied across the primary and secondary outcomes, as these endpoints represented distinct, pre-specified domains of the intervention's impact (i.e., behavioral, clinical, and administrative dimensions) rather than multiple tests of a single hypothesis. Similarly, no adjustment was applied to the supportive subgroup analyses, which were strictly interpreted as exploration. The analysis file included data import, variable checking, descriptive summaries, baseline comparison, difference-in-differences models, count models for hospital-acquired infection rates, sensitivity analyses, subgroup analyses, and figure-ready output tables.
Results
Baseline ward characteristics
A total of 16 inpatient wards were included in the study, with 8 wards in the intervention group and 8 wards in the control group.
The two groups showed no marked imbalance in ward workload or observation volume at baseline. Baseline hand hygiene compliance was 66.2% in the intervention group and 63.1% in the control group. The baseline hospital-acquired infection rate was 7.07 per 1,000 patient-days in the intervention group and 6.20 per 1,000 patient-days in the control group. Baseline nursing management quality scores were 76.7 and 75.4 in the intervention and control groups, respectively. Alcohol-based hand rub consumption was 44.2 L/1,000 patient-days in the intervention group and 42.6 L/1,000 patient-days in the control group. These baseline patterns suggested broadly similar workload and observation intensity, although the intervention wards had slightly higher baseline hand hygiene compliance, hospital-acquired infection rate, nursing management quality score, and alcohol-based hand rub consumption (Table 1).
Monthly hand hygiene compliance
Hand hygiene compliance increased more clearly in the intervention wards than in the control wards after implementation of the PDCA-based hand hygiene governance bundle. In the intervention group, compliance increased from 66.2% during the pre-intervention period to 83.2% during the post-intervention period, corresponding to an absolute increase of 17.0 percentage points. In the control group, compliance increased from 63.1% to 66.8%, corresponding to an absolute increase of 3.7 percentage points (Table 2).
In practical terms, the improvement in hand hygiene compliance within the intervention group was 13.3 percentage points higher than the concurrent improvement observed in the control group. In the adjusted model, the post-intervention period in the PDCA group was associated with higher hand hygiene compliance compared with the background change in the control group. The adjusted difference-in-differences odds ratio (OR) for hand hygiene compliance was 2.38 (95% CI: 2.19–2.59, P < 0.001) (Table 3).
The monthly trend showed a progressive increase in the intervention wards rather than an abrupt single-month change. Compliance in the intervention group increased from 76.7% in the first post-intervention month to 87.6% in the final post-intervention month. In contrast, the control group showed only modest fluctuation over the same period, increasing from 66.3% to 69.6%. During the pre-intervention period, the two groups showed broadly similar month-to-month trajectories, without a clear opposing baseline trend (Figure 2).
Hospital-acquired infection rate
A lower post-intervention hospital-acquired infection rate was observed in the intervention wards. In the intervention group, the hospital-acquired infection rate decreased from 7.07 to 4.37 per 1,000 patient-days, representing a reduction of 2.70 infections per 1,000 patient-days. In the control group, the rate changed from 6.20 to 6.50 per 1,000 patient-days, indicating no comparable downward pattern (Table 2).
Similarly, the intervention group achieved a greater reduction in the hospital-acquired infection rate, decreasing by an additional 3.01 infections per 1,000 patient-days compared to the change in the control group. In the adjusted count model using patient-days as the offset, the post-intervention period in the PDCA group was associated with a lower hospital-acquired infection rate compared with the control condition. The adjusted incidence rate ratio (IRR) was 0.60 (95% CI: 0.52–0.69, P < 0.001; Table 3), with a 95% confidence interval of 0.52 to 0.69 and a P value below 0.001 (Table 3).
The monthly trend supported the aggregate finding. In the intervention group, hospital-acquired infection rates fluctuated during the baseline period and then remained generally lower after implementation, reaching 3.42 per 1,000 patient-days in the third post-intervention month and 3.70 per 1,000 patient-days in the final post-intervention month. The control group did not show a consistent downward pattern and remained within a higher post-intervention range, with monthly values between 5.06 and 7.60 per 1,000 patient-days (Figure 3).
Nursing management quality and process indicators
Nursing management quality scores increased more substantially in the intervention wards than in the control wards. The mean nursing management quality score increased from 76.7 to 86.8 in the intervention group, giving a within-group increase of 10.1 points. In the control group, the score increased from 75.4 to 78.1, giving a within-group increase of 2.8 points (Table 2).
In practical terms, the intervention wards achieved a net improvement in nursing management quality that was 7.37 points greater than the concurrent change observed in the control group. Statistically, this adjusted difference-in-differences estimate (β) was 7.37 (95% CI: 6.45–8.29, P < 0.001; Table 3).
Alcohol-based hand rub consumption increased alongside hand hygiene compliance. In the intervention group, consumption increased from 44.2 to 50.3 L/1,000 patient-days, while in the control group it increased from 42.6 to 44.2 L/1,000 patient-days. The adjusted difference-in-differences estimate for alcohol-based hand rub consumption was 4.50 L/1,000 patient-days (95% CI: 3.61–5.39, P < 0.001). This increase was consistent with the higher observed hand hygiene compliance in the intervention wards (Table 3).
The monthly nursing management quality trend also showed clearer separation after implementation. Intervention wards increased from a baseline range of 75.8 to 78.7 to a post-intervention range of 85.2 to 88.3. Control wards changed more modestly, from a baseline range of 74.4 to 76.1 to a post-intervention range of 77.2 to 80.1 (Figure 4).
Compliance by professional role and hand hygiene moment
Subgroup analysis showed that hand hygiene compliance improved across all observed professional groups in the intervention wards. Among nurses, compliance increased from 72.7% to 82.9%. Among physicians, compliance increased from 59.6% to 73.3%. Among care assistants, compliance increased from 54.8% to 67.6%. The control wards showed smaller increases over the same period, from 72.3% to 77.4% among nurses, from 57.5% to 61.2% among physicians, and from 53.3% to 59.2% among care assistants (Figure 5A).
Improvements were also observed across the five hand hygiene moments in the intervention wards. Compliance before patient contact increased from 56.4% to 76.4%, and compliance before clean or aseptic procedures increased from 69.0% to 87.0%. Compliance after body fluid exposure increased from 76.7% to 85.6%, while compliance after patient contact increased from 71.5% to 84.2%. Compliance after touching patient surroundings increased from 56.4% to 71.6%. Descriptively, the largest absolute gains were observed in moments that were weaker at baseline, particularly before patient contact and after touching patient surroundings. However, consistent with the exploratory design of these subgroup assessments, formal statistical tests for superiority between subgroups (e.g., evaluating whether one professional role or hand hygiene moment significantly outperformed another at the 95% confidence level) were not performed, and these differences should be interpreted descriptively (Figure 5B).
Sensitivity and robustness checks
Comprehensive sensitivity and robustness checks confirmed that our primary and secondary findings were highly robust and not driven by the initial implementation transition month or seasonal calendar-month fluctuations. The full detailed results of these sensitivity analyses are presented in Supplementary File 2.
In summary, the implementation of the PDCA-based hand hygiene governance bundle yielded comprehensive and consistent improvements across the targeted clinical and administrative domains. The intervention was associated with a significant, sustained increase in ward-level hand hygiene compliance and a concurrent reduction in hospital-acquired infection rates. Furthermore, these behavioral and clinical benefits were objectively corroborated by increased alcohol-based hand rub consumption and significant enhancements in overall nursing management quality scores.
DATA AVAILABILITY:
All raw data supporting the conclusions of this study, including the fully de-identified monthly ward-level analytical dataset, have been deposited in a public repository to ensure full transparency and reproducibility. The complete dataset is publicly accessible at Zenodo via the following Digital Object Identifier (DOI) or URL: https://zenodo.org/records/21242367.
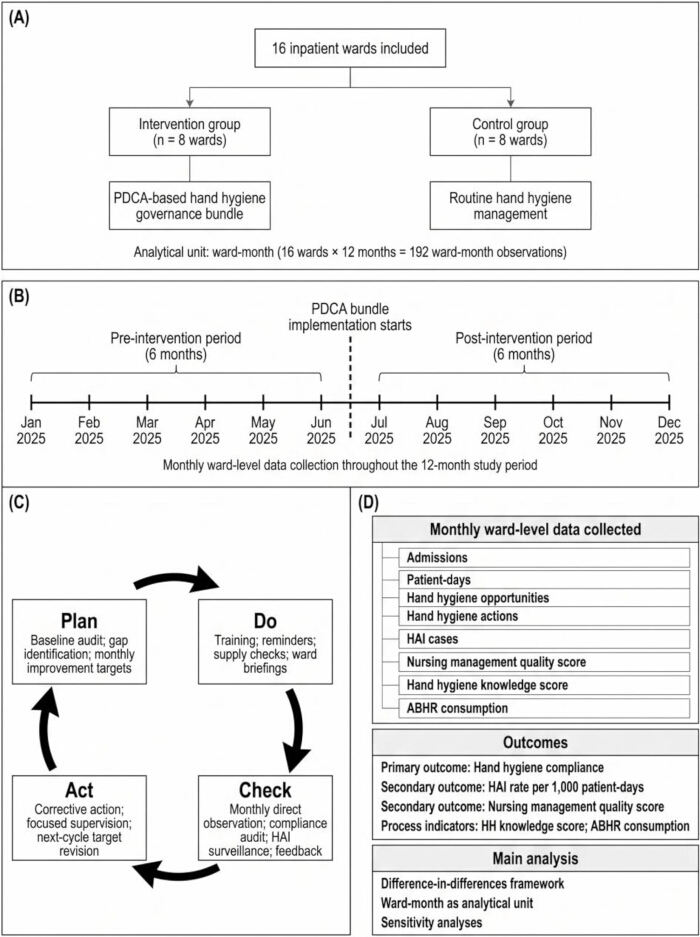
Figure 1: Study design and PDCA-based hand hygiene governance workflow. (A) Controlled before-and-after design including 16 inpatient wards, with 8 wards in the intervention group and 8 wards in the control group. The unit of analysis is the ward-month (n = 192 observations). (B) Study timeline showing a 6-month pre-intervention period and a 6-month post-intervention period. (C) Core components of the PDCA-based hand hygiene governance bundle. (D) Monthly data collection and outcome assessment. Abbreviations: PDCA, Plan-Do-Check-Act; HAI, hospital-acquired infection; HH, hand hygiene; ABHR, alcohol-based hand rub. Please click here to view a larger version of this figure.
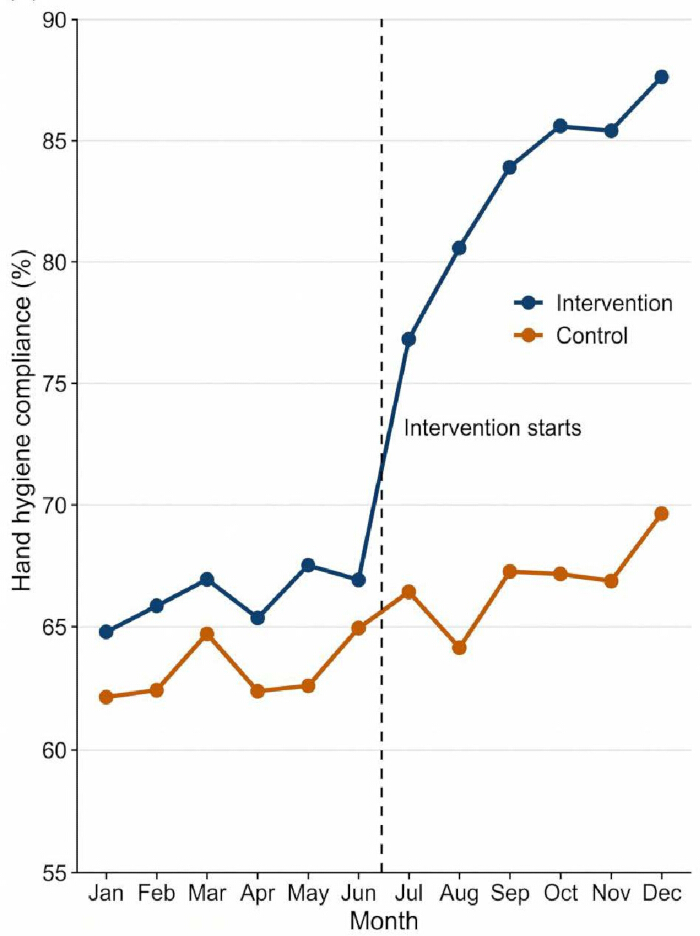
Figure 2: Monthly hand hygiene compliance by group. The graph displays the unadjusted monthly hand hygiene compliance percentages for the intervention (blue) and control (orange) groups across the 12-month study period. The vertical dashed line indicates the initiation of the PDCA-based intervention. The analytical unit is the ward-month. Abbreviations: PDCA, Plan-Do-Check-Act. Please click here to view a larger version of this figure.
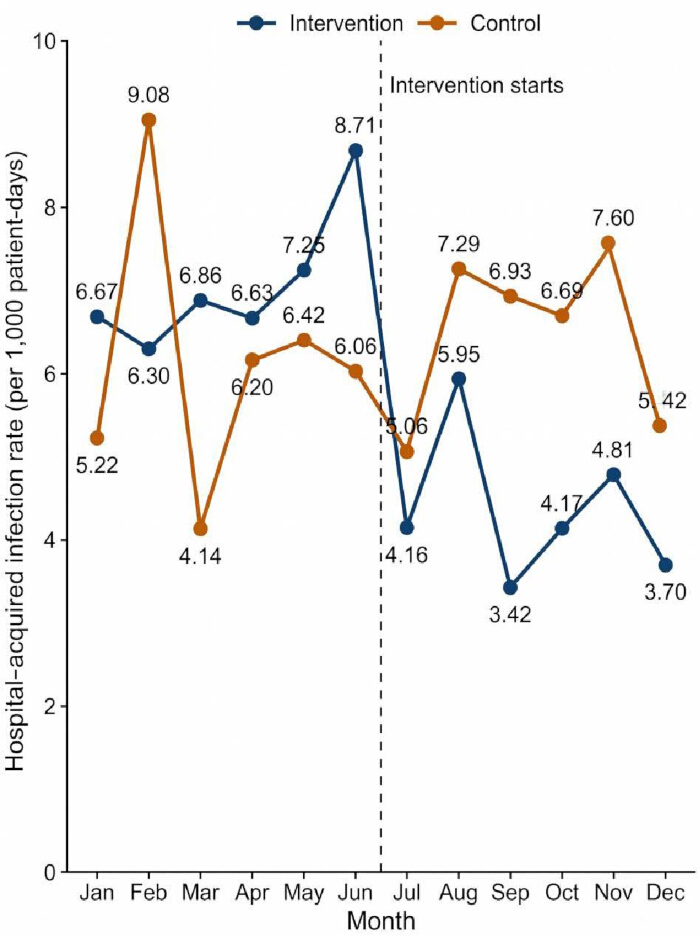
Figure 3: Monthly hospital-acquired infection rate by group. The graph displays the unadjusted monthly hospital-acquired infection (HAI) rate per 1,000 patient-days for the intervention and control groups. The vertical dashed line indicates the initiation of the PDCA-based intervention. The analytical unit is the ward-month. Abbreviations: HAI, hospital-acquired infection; PDCA, Plan-Do-Check-Act. Please click here to view a larger version of this figure.
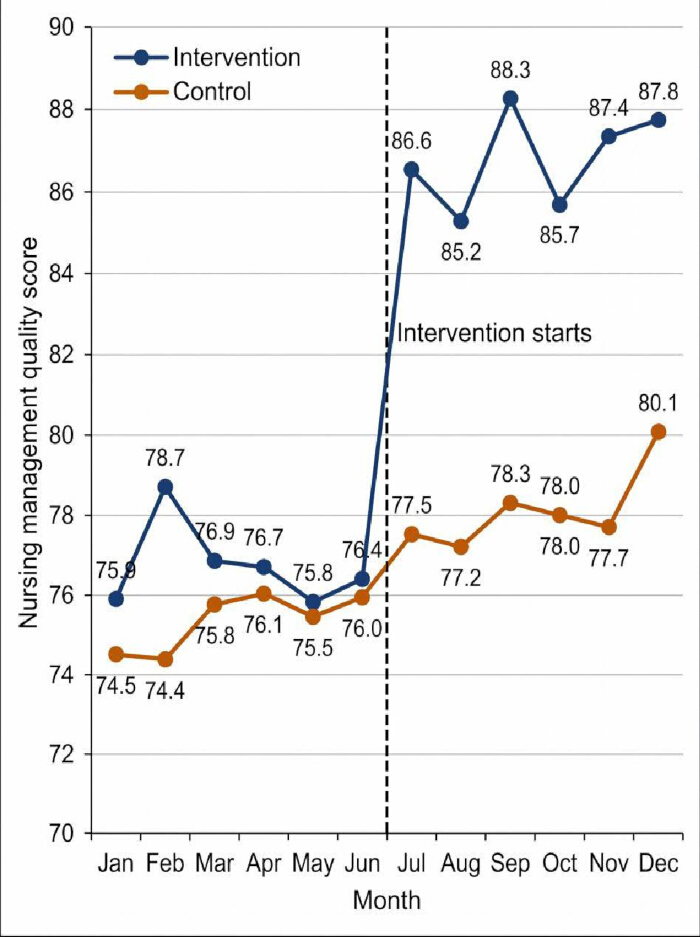
Figure 4: Monthly nursing management quality score by group. The graph displays the unadjusted mean monthly nursing management quality scores (0–100 scale) for the intervention and control groups. The vertical dashed line indicates the initiation of the PDCA-based intervention. The analytical unit is the ward-month. Abbreviations: PDCA, Plan-Do-Check-Act. Please click here to view a larger version of this figure.
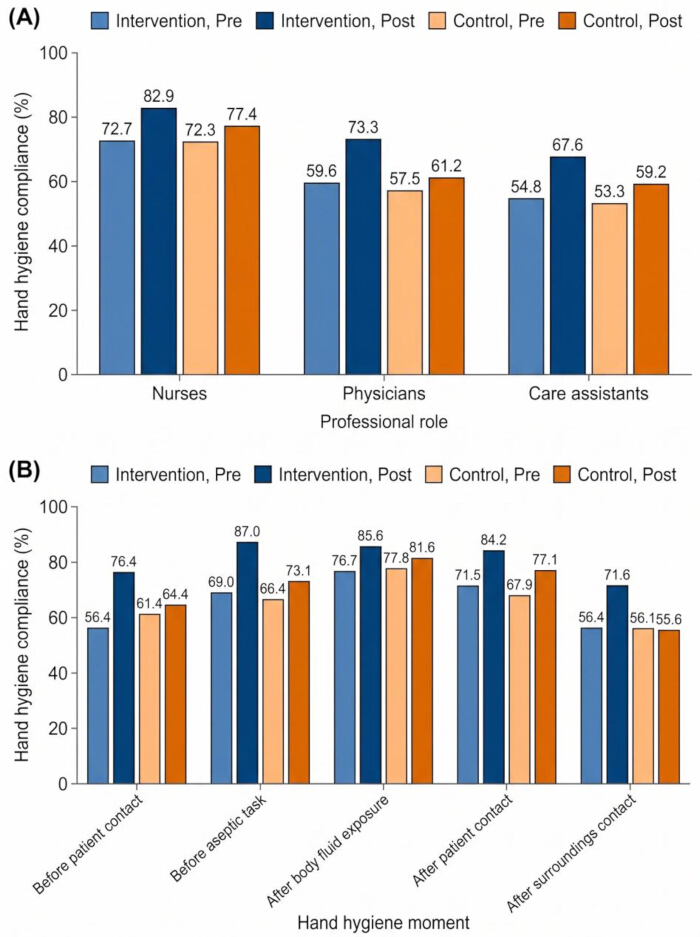
Figure 5: Hand hygiene compliance by professional role and hand hygiene moment. (A) Subgroup analysis of hand hygiene compliance by professional role (nurses, physicians, and care assistants) in intervention and control wards during the pre- and post-intervention periods. (B) Subgroup analysis of hand hygiene compliance by the WHO five moments in both groups. Data are presented as aggregate descriptive percentages; formal statistical testing for superiority between these exploratory subgroups was not performed. Please click here to view a larger version of this figure.
| Characteristic | Intervention wards | Control wards |
| No. of wards | 8 | 8 |
| Total admissions, n | 8,757 | 8,548 |
| Patient-days, n | 57,005 | 56,811 |
| Observed hand hygiene opportunities, n | 65,293 | 65,136 |
| Observed hand hygiene actions, n | 43,223 | 41,103 |
| Baseline hand hygiene compliance, % | 66.2 | 63.1 |
| Hospital-acquired infection cases, n | 403 | 352 |
| Baseline HAI rate, per 1,000 patient-days | 7.07 | 6.2 |
| Nursing management quality score, mean | 76.7 | 75.4 |
| Hand hygiene knowledge score, mean | 82.6 | 81.2 |
| Alcohol-based hand rub consumption, L/1,000 patient-days | 44.2 | 42.6 |
Table 1: Baseline characteristics of intervention and control wards during the pre-intervention period. Values are summarized across the 6-month pre-intervention period. HAI, hospital-acquired infection.
| Group | Intervention | Intervention | Control | Control |
| Period | Pre | Post | Pre | Post |
| Admissions, n | 8,757 | 8,702 | 8,548 | 8,341 |
| Patient-days, n | 57,005 | 55,404 | 56,811 | 53,220 |
| HH opportunities, n | 65,293 | 60,731 | 65,136 | 61,016 |
| HH actions, n | 43,223 | 50,517 | 41,103 | 40,740 |
| HH compliance, % | 66.2 | 83.2 | 63.1 | 66.8 |
| HAI cases, n | 403 | 242 | 352 | 346 |
| HAI rate per 1,000 patient-days | 7.07 | 4.37 | 6.2 | 6.5 |
| Nursing management score, mean | 76.7 | 86.8 | 75.4 | 78.1 |
| HH knowledge score, mean | 82.6 | 90.7 | 81.2 | 84.6 |
| ABHR consumption, L/1,000 patient-days | 44.2 | 50.3 | 42.6 | 44.2 |
Table 2: Pre-post outcome summary by group. Values are summarized by ward-month (16 wards; 192 ward-month observations). HH, hand hygiene; HAI, hospital-acquired infection; ABHR, alcohol-based hand rub.
| Outcome | Hand hygiene compliance, % | HAI rate per 1,000 patient-days | Nursing management quality score | ABHR consumption, L/1,000 patient-days |
| Intervention Pre | 66.2 | 7.07 | 76.7 | 44.2 |
| Intervention Post | 83.2 | 4.37 | 86.8 | 50.3 |
| Intervention Within-group Change | 17 | −2.70 | 10.1 | 6.1 |
| Control Pre | 63.1 | 6.2 | 75.4 | 42.6 |
| Control Post | 66.8 | 6.5 | 78.1 | 44.2 |
| Control Within-group Change | 3.7 | 0.3 | 2.8 | 1.6 |
| Unadjusted DID | 13.3 percentage points | −3.01 per 1,000 patient-days | 7.3 points | 4.5 L/1,000 patient-days |
| Model | Binomial model with ward-level clustering | Count model with log(patient-days) offset | Linear model with ward-level clustering | Linear model with ward-level clustering |
| Adjusted Effect Estimate | Adjusted DID OR = 2.38 | Adjusted DID IRR = 0.60 | Adjusted DID β = 7.37 points | Adjusted DID β = 4.50 L/1,000 patient-days |
| 95% CI | 2.19 to 2.59 | 0.52 to 0.69 | 6.45 to 8.29 | 3.61 to 5.39 |
| P Value | <0.001 | <0.001 | <0.001 | <0.001 |
Table 3: Difference-in-differences estimates for primary and secondary outcomes. DID, difference-in-differences; OR, odds ratio; IRR, incidence rate ratio; HAI, hospital-acquired infection; ABHR, alcohol-based hand rub. The DID estimate represents the group-by-period interaction effect.
Supplementary Table 1: Operational definitions, thresholds, and calculation formulas for study variables. This comprehensive table details the specific definitions, data sources, analytical units, and calculation methods for all variables evaluated in the study, including primary and secondary outcomes, process indicators, and subgroup categorizations. Additionally, it outlines the predefined quantitative thresholds utilized to trigger targeted corrective actions within the Plan-Do-Check-Act (PDCA) governance cycles, as well as the predefined data quality exclusion rules. Abbreviations: HAI, hospital-acquired infection; ABHR, alcohol-based hand rub; PDCA, Plan-Do-Check-Act; OR, odds ratio; IRR, incidence rate ratio. Please click here to download this file.
Supplementary File 1: Detailed data collection, quality control, and missing data handling procedures. Please click here to download this file.
Supplementary File 2: Sensitivity and robustness analyses. Please click here to download this file.
Discussion
This controlled before-and-after study demonstrates that a PDCA-based hand hygiene governance bundle significantly improves compliance, reduces hospital-acquired infection (HAI) rates, and enhances nursing management quality. Unlike interventions relying solely on generalized education, our approach translates multimodal strategies into a repeatable, ward-level governance cycle. Our findings align with international literature demonstrating the broad efficacy of multimodal programs in reducing healthcare-associated infections7,17. However, compared to established interventions, our continuous, data-driven closed-loop system helps sustain performance where one-off campaigns often fail, despite the sustained administrative effort and resources such intensive monitoring programs globally require17.
The mechanical strength of the PDCA framework lies in its iterative nature—combining baseline gap analysis, direct observation, feedback, and targeted corrective action11. By linking behavioral outcomes with HAI rates and nursing quality scores, we demonstrate that hand hygiene is best managed as an institutional practice rather than an isolated individual behavior. Targeted audit and feedback can successfully improve practice when it is specific, timely, and tied to predefined corrective action thresholds18. Furthermore, while improved hand hygiene is generally associated with reduced infection risk, the magnitude of effect varies8 highlighting why our closed-loop process systematically addresses environmental and workflow barriers rather than relying on passive reminders alone.
Practical implications of our findings extend to the necessity of tailored, role-specific reinforcement. Our subgroup analysis revealed persistent differences in compliance among physicians, nurses, and care assistants, closely aligning with broader international literature highlighting how professional socialization and workflow constraints profoundly influence role-specific adherence. This confirms that while a standardized bundle elevates overall baseline performance, entrenched professional role differences require nuanced, specific feedback19. Furthermore, the substantial gains in moments weaker at baseline, such as before patient contact, suggest that targeted governance can successfully address specific clinical risk points.
Despite the robustness of our results, several limitations warrant consideration. First, hand hygiene compliance measured by direct observation carries an inherent risk of the Hawthorne effect, where observed compliance can artificially increase during monitoring12. Second, unmeasured ward-level factors and barriers to audit-and-feedback programs, such as workflow burden and feedback fatigue, remain relevant when interpreting sustainability20. Finally, the reduction in HAI rates should be interpreted cautiously, as infections are multifactorial and very high hand hygiene compliance may not always lead to continued proportional reductions in infection rates21 . Nevertheless, in conclusion, this study provides a practical, sustainable model for embedding hand hygiene into routine ward governance. Future research should leverage multicenter designs and complementary monitoring methods to further validate the sustainability of this data-driven cycle.
Disclosures
The authors have nothing to disclose.
Acknowledgements
We would like to express our sincere gratitude to the administrative and clinical staff at Guangzhou Panyu District Eighth People's Hospital, Guangzhou Panyu Shiqiao Hospital, and Guangzhou Panyu District Third People's Hospital for their invaluable support and cooperation during this study. Special thanks are extended to the ward managers and infection-control practitioners who facilitated the implementation of the Plan-Do-Check-Act (PDCA) governance bundle and assisted in the monthly data collection across the participating inpatient wards. Their dedication to improving patient safety and healthcare quality made this research possible. This research received no specific grant from any funding agency in the public, commercial, or not-for-profit sectors.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Alcohol-based hand rub (ABHR) | 3M Company, St. Paul, MN, USA | N/A | Used by healthcare workers for hand hygiene actions during the study period. |
| Alcohol-based hand rub consumption records | Ward supply records / Hospital logistics system | N/A | Used to calculate alcohol-based hand rub consumption standardized by patient-days. |
| GraphPad Prism | GraphPad Software, San Diego, CA, USA | Version 9.0 | Used to prepare figures and check graphical outputs against final statistical results. |
| Hand hygiene knowledge test | Study team / Infection-control nurses | N/A | Structured 0–100 test; Used to assess healthcare workers’ knowledge of hand hygiene indications, procedures, glove use, and infection-control risk points. |
| Hospital infection-control surveillance records | Hospital infection-control department | N/A | Used to identify monthly hospital-acquired infection cases and verify infection events using clinical, microbiological, medication, temperature, imaging, and ward log data. |
| IBM SPSS Statistics | IBM Corp., Armonk, NY, USA | Version 27.0 | Used for descriptive statistics and baseline comparison tables. |
| Nursing management quality assessment form | Hospital nursing management department | N/A | Structured 0–100 scoring form; Used for monthly assessment of hand hygiene governance, infection-control documentation, supplies, staff training, audit feedback, environmental management, and corrective action implementation. |
| PDCA corrective action form | Study team / Infection-control department | N/A | Ward-month observation form; Used to record ward code, month, professional role, hand hygiene moment, hand hygiene opportunities, and performed hand hygiene actions. |
| R packages: stats, MASS, sandwich, lmtest | R Foundation / CRAN | Versions consistent with R 4.3.2 | Used for regression modeling, count models, robust standard errors, and statistical inference. |
| R software | R Foundation for Statistical Computing, Vienna, Austria | Version 4.3.2 | Used for difference-in-differences models, Poisson/negative binomial models, clustered standard errors, subgroup analyses, and sensitivity analyses. |
| Standardized hand hygiene observation form | Study team / Infection-control department | N/A | Ward-month observation form; Used to record ward code, month, professional role, hand hygiene moment, hand hygiene opportunities, and performed hand hygiene actions. |
| Ward administrative records | Hospital administrative system | N/A | Used to obtain admissions, patient-days, and ward workload indicators for denominator calculation and baseline comparison. |
References
- WHO guidelines on hand hygiene in health care: First global patient safety challenge clean care is safer care. World Health Organization, 2009.
- Allegranzi, B. Burden of endemic health-care-associated infection in developing countries: A systematic review and meta-analysis. Lancet. 2011;377(9761):228-241.
- Magill, S. S. Multistate point-prevalence survey of health care-associated infections. N. Engl. J. Med. 2014;370(13):1198-1208.
- Sax, H. "My five moments for hand hygiene": A user-centred design approach to understand, train, monitor and report hand hygiene. J. Hosp. Infect. 2007;67(1):9-21.
- Pittet, D. Effectiveness of a hospital-wide programme to improve compliance with hand hygiene. Lancet. 2000;356(9238):1307-1312.
- Who. A guide to the implementation of the WHO multimodal hand hygiene improvement strategy. World Health Organization. 2009; https://www.who.int/publications/i/item/a-guide-to-the-implementation-of-the-who-multimodal-hand-hygiene-improvement-strategy.
- Allegranzi, B. Global implementation of WHO's multimodal strategy for improvement of hand hygiene: A quasi-experimental study. Lancet Infect. Dis. 2013;13(10):843-851.
- Mouajou, V., Adams, K., DeLisle, G., Quach, C. Hand hygiene compliance in the prevention of hospital-acquired infections: A systematic review. J. Hosp. Infect. 2022;119:33-48.
- Gould, D. J., Moralejo, D., Drey, N., Chudleigh, J. H., Taljaard, M. Interventions to improve hand hygiene compliance in patient care. Cochrane Database Syst. Rev. 2017;9(9):CD005186.
- Huis, A. A systematic review of hand hygiene improvement strategies: A behavioural approach. Implement. Sci. 2012;7:92.
- Sua, Y. P., Wang, Y., Liu, X. Application of PDCA in improving hand hygiene compliance and nosocomial infection quality in orthopedics. Front. Nurs. 2024;11(3):376-382.
- Srigley, J. A., Furness, C. D., Baker, G. R., Gardam, M. Quantification of the hawthorne effect in hand hygiene compliance monitoring using an electronic monitoring system: A retrospective cohort study. BMJ Qual. Saf. 2014;23(12):974-980.
- Ogrinc, G. Squire 2.0: Revised publication guidelines from a detailed consensus process. BMJ Qual. Saf. 2016;25(12):986-992.
- von Elm, E. The strengthening the reporting of observational studies in epidemiology (strobe) statement: Guidelines for reporting observational studies. Lancet. 2007;370 (9596):1453-1457.
- CDC. National healthcare safety network patient safety component manual. Centers for Disease Control and Prevention. 2026; https://www.cdc.gov/nhsn/pdfs/pscmanual/pscmanual_current.pdf.
- The R Core Team. R: A language and environment for statistical computing. R Foundation for Statistical Computing. 2026; https://cran.r-project.org/doc/manuals/r-release/fullrefman.pdf.
- Clancy C, Delungahawatta T, Dunne C P. Hand hygiene-related clinical trials reported between 2014 and 2020: A comprehensive systematic review. Journal of Hospital Infection. 2021;111:6-26.
- Smiddy, M. P. Efficacy of observational hand hygiene audit with targeted feedback on doctors' hand hygiene compliance. J. Hosp. Infect. 2019;102(3):e89-e94.
- Bredin, D., O’Doherty, D., Hannigan, A., Kingston, L. Hand hygiene compliance by direct observation in physicians and nurses: A systematic review and meta-analysis. J. Hosp. Infect. 2022;130:20-33.
- Livorsi, D. J. Evaluation of barriers to audit-and-feedback programs that used direct observation of hand hygiene compliance: A qualitative study. JAMA Netw. Open. 2018;1 (6):e183344.
- Marra, A. R. Edmond, M. B. New technologies to monitor healthcare worker hand hygiene. Clin. Microbiol. Infect. 2014;20(1):29-33.