This retrospective study evaluates whether a 6-month multimodal psychological nursing program [cognitive behavioral nursing, mindfulness-based stress reduction (MBSR), and family support] is associated with improvements in mental health, treatment adherence, and quality of life in hemodialysis-dependent cancer patients with renal failure.
Research Article
Association of Multimodal Psychological Nursing with Mental Health and Quality of Life in Cancer Patients with Renal Failure Receiving Hemodialysis
In This Article
Summary
Abstract
Patients undergoing hemodialysis for both renal failure and cancer experience significant physical and psychological distress, yet effective long-term psychological nursing strategies for this population remain underexplored. This retrospective cohort study aimed to evaluate the long-term effects of a multimodal psychological nursing program on mental health and quality of life in these patients. A total of 431 patients were screened, of whom 362 were eligible; 87 eligible patients, including 17 who died, were excluded before analysis, leaving 275 patients receiving hemodialysis for renal failure complicated by cancer between January 2022 and January 2024 in the final complete-case analysis. Based on nursing records, 132 patients receiving conventional care were assigned to the control group, while 143 patients receiving an additional six-month multimodal psychological nursing program (integrating cognitive behavioral nursing, mindfulness-based stress reduction, and family support system construction) formed the observation group. Outcome measures, including negative emotions [Self-Rating Anxiety Scale (SAS), Self-Rating Depression Scale (SDS), Distress Thermometer (DT)], treatment adherence, quality of life [Kidney Disease Quality of Life Short Form (KDQOL-36)], psychological resources [Herth Hope Index (HHI), Connor-Davidson Resilience Scale (CD-RISC), Multidimensional Health Locus of Control Scale (MHLC)] were compared at baseline, immediately post-intervention, and at 12-month follow-up, and nursing satisfaction was compared at the end of the intervention. At both post-intervention and follow-up assessments, the observation group demonstrated significantly greater improvements than the control group across all outcomes: lower anxiety, depression, and distress scores; higher treatment adherence and self-management; better quality of life on all domains; enhanced hope, resilience, and internal health locus of control; and higher nursing satisfaction (all p < 0.05). In conclusion, a six-month multimodal psychological nursing program is associated with sustained improvements in negative emotions, treatment adherence, quality of life, and positive psychological resources in cancer patients with renal failure receiving hemodialysis, with effects lasting up to 12 months post-intervention.
Introduction
Chronic kidney disease (CKD) has become a major public health problem threatening human health worldwide1. The 2012 China national CKD survey reported a 10.8% overall CKD prevalence2. Due to population aging and rising metabolic diseases like diabetes and hypertension, end-stage renal disease cases have increased annually. Clinical treatment of end-stage renal disease relies on renal replacement therapy, including regular hemodialysis and peritoneal dialysis3. Maintenance hemodialysis is widely used as a mature option4. However, its long-term, time-intensive nature makes patients more prone to psychological disorders such as depression and anxiety compared to the general population5. Among hemodialysis patients, the coexistence of malignant tumors has received increasing clinical attention. There is a complex pathophysiological association between renal failure and malignant tumors. On the one hand, the accumulation of uremic toxins, immune dysfunction, and the formation of a chronic inflammatory microenvironment in the setting of CKD can significantly increase the risk of malignant tumors. On the other hand, malignant tumors and their treatments can directly or indirectly impair renal function, leading to or worsening renal failure6. When these two serious diseases, renal failure and malignant tumor, coexist in the same patient, the patient not only has to bear the treatment burden of hemodialysis but also faces the survival threat posed by the cancer diagnosis, treatment side effects, and prognostic uncertainty, thereby falling into a dilemma of dual physiological and psychological stress.
Anxiety and depression, the most common mental disorders in hemodialysis patients, reduce quality of life and adversely affect clinical outcomes and prognosis. Studies have shown that approximately three-quarters of hemodialysis patients experience varying degrees of anxiety, and more than 80% have varying degrees of depression, indicating that anxiety and depression are quite prevalent in the hemodialysis population7. As dialysis duration increases in maintenance hemodialysis patients, complication rates and financial burden rise, quality of life declines, and anxiety and depression worsen8. Existing research confirms a significant correlation between anxiety, depression, and mortality in this population9. Furthermore, treatment adherence is one of the key determinants of clinical prognosis in hemodialysis patients. Maintenance hemodialysis therapy involves multidimensional adherence behaviors, including regular dialysis attendance, strict dietary and fluid restrictions, complex medication regimens, and regular laboratory monitoring. Non-adherence in any aspect may lead to adverse consequences such as reduced dialysis adequacy, electrolyte disturbances, and worsening cardiovascular complications, thereby increasing hospitalization rates and mortality risk. However, in patients with renal failure complicated by cancer, treatment adherence issues are often more prominent due to the superimposed complexity of treatment regimens for the two diseases, the accumulation of treatment-related fatigue and discomfort, and the weakening effect of negative emotions on behavioral motivation. Patients may voluntarily abandon some treatment measures due to feelings of hopelessness or may have difficulty understanding and executing complex treatment instructions because of uremia-related cognitive impairment.
Facing the prevalent negative emotional disorders and treatment adherence issues among hemodialysis patients, the importance of psychological nursing has gained increasing attention. The traditional biomedical model tends to focus on the control of somatic symptoms and the improvement of laboratory indicators, while paying insufficient attention to patients' psychological needs. This physically oriented care model no longer meets the requirements of modern holistic nursing10. Although recent studies have explored psychosocial interventions for hemodialysis patients-such as psychosocial support, positive psychological interventions, and cognitive behavioral therapy-and have shown benefits for depression11,12, psychiatric association guidelines also support their therapeutic effects on depression, anxiety, and quality of life in maintenance hemodialysis patients, findings remain inconsistent, with some studies limited by small samples and short follow-ups13.
To address the specific needs of this dual-burden population, our multimodal program was deliberately constructed by integrating three evidence-based components with distinct but complementary functions14,15,16. First, cognitive behavioral nursing was selected because it directly targets the maladaptive illness cognitions and behavioral withdrawal that are prevalent in this group. Its problem-solving training component is particularly relevant for enhancing patients' ability to manage complex treatment regimens. Second, mindfulness-based stress reduction (MBSR) was chosen to specifically alleviate the cumulative stress and emotional distress triggered by repeated, prolonged hemodialysis sessions and cancer-related uncertainty. Third, family support system construction was incorporated because the chronic nature of both diseases demands long-term behavioral maintenance, which is best reinforced through an optimized caregiving environment. Together, these components are expected to act synergistically to address the cognitive, emotional, and social dimensions of psychological distress.
Based on the above background, this retrospective cohort study included 275 hemodialysis patients with renal failure complicated by cancer, comparing changes in various indicators at baseline, intervention end, and 12 months post-intervention between a routine care group and a six-month multimodal psychological nursing group. We hypothesized that, compared with routine care alone, the multimodal program would be associated with significantly greater and sustained improvements in negative emotions (anxiety, depression, and distress), treatment adherence and self-management behaviors, quality of life, and positive psychological resources (hope, resilience, and internal locus of control), with these effects lasting up to 12 months after the intervention. By employing standardized tools to assess these outcomes, this study seeks to provide evidence-based references for optimizing nursing care in this vulnerable population.
Protocol
This study protocol adheres to the ethical principles set forth in the Declaration of Helsinki and has been approved by the Ethics Committee of Shuguang Hospital Affiliated to Shanghai University of Traditional Chinese Medicine (Approval No.: SG-2025-091; date of approval: August 5, 2025). The Ethics Committee formally waived the requirement for informed consent because the study was retrospective and analyzed only archived clinical data, with all patient-identifiable information strictly anonymized. The approval covers the full data-collection window of the study (January 2022 to July 2025). The details of all the equipment and software used are listed in the Table of Materials.
Study design and participants
This retrospective cohort study included patients with renal failure complicated by malignancy who received maintenance hemodialysis at our hospital from January 2022 to January 2024. The data cut-off date for all follow-up assessments was July 31, 2025, ensuring that every enrolled patient had a minimum observational window of 18 months from baseline. Based on electronic medical records and nursing notes, patients were assigned to a control group (conventional hemodialysis nursing) or an observation group (conventional plus multimodal psychological nursing). Negative emotions, treatment compliance, quality of life, and psychological resources were compared at three time points: baseline (before psychological nursing), at 6 months (end of intervention), and at 18 months (12 months post-intervention) to assess long-term effects. A total of 431 patients were initially screened. Of these, 69 were excluded at baseline based on the predefined exclusion criteria, including severe cardiac, cerebral, or pulmonary insufficiency or other severe somatic diseases (n = 16), history of psychiatric disorders or severe cognitive dysfunction (n = 9), speech, hearing, or severe visual impairment (n = 7), participation in other psychological nursing studies or systematic psychotherapy within the past 3 months (n = 15), terminal stage of cancer or severe cachexia (n = 12), and irregular hemodialysis treatment or undergoing peritoneal dialysis or kidney transplantation (n = 10). The remaining 362 eligible patients were followed for 18 months, during which 87 were further excluded due to incomplete clinical records or missing questionnaire data at any time point (n = 48), loss to follow-up before the 18-month assessment (n = 22), or death during the observation period (n = 17). Exclusion rates were similar between the two groups. The final analytic cohort consisted of 275 patients (132 in the control group and 143 in the observation group) with complete data at all three time points. The assignment to groups was determined by the temporal implementation of a revised clinical nursing protocol: patients enrolled between January 2022 and March 2023 received conventional care (control group), while those enrolled between April 2023 and January 2024, following the hospital-wide rollout of the multimodal psychological nursing program, received the combined intervention (observation group). The study flow chart is shown in Figure 1.
Inclusion and exclusion criteria
Inclusion criteria: (1) Age 18-75 years; (2) Diagnosed with chronic renal failure, on regular hemodialysis for ≥3 months (2-3 sessions/week, 4 h each); (3) Confirmed diagnosis of malignant tumor by pathological or cytological examination, or cancer patients with a clear clinical diagnostic basis; (4) Conscious with basic literacy and language communication skills, able to independently complete questionnaire assessments; (5) Expected survival ≥18 months; (6) Complete clinical data, including baseline demographic information, questionnaire data, nursing records, and follow-up data; (7) Patients in the observation group had complete records of the 6-month multimodal psychological nursing, while patients in the control group had concurrent routine nursing records.
Exclusion Criteria: (1) Patients with severe cardiac, cerebral, or pulmonary insufficiency or other severe somatic diseases that preclude cooperation with assessment; (2) Previous history of psychiatric disorders or severe cognitive dysfunction; (3) Presence of speech, hearing, or severe visual impairment affecting questionnaire completion; (4) Participation in other psychological nursing studies or undergoing systematic psychotherapy within the past 3 months; (5) Terminal stage of cancer or severe cachexia; (6) Irregular hemodialysis treatment or undergoing peritoneal dialysis or kidney transplantation; (7) Incomplete clinical data or incomplete follow-up data.
Sample size calculation
This study is a retrospective cohort study, and the sample size was calculated based on previous literature17. Using the Self-Rating Anxiety Scale (SAS) score, the primary outcome measure, as a reference, an assumed effect size of Cohen's d = 0.4 was used, with a two-sided test was set with α = 0.05 and a power (1 - β) = 0.90. Using power-analysis software, the minimum required sample size was 118 patients per group. Considering the potential for 10%-15% missing data or data quality issues inherent in retrospective studies, it was ultimately determined that each group should have no fewer than 130 patients, with a total sample size of no less than 260 patients. A total of 275 patients were actually enrolled, including 132 in the control group and 143 in the observation group, meeting the sample size requirement. Notably, the observed post-intervention effect size for the SAS score (Cohen's d = 1.741) was larger than the estimate derived from the referenced literature. This discrepancy likely reflects differences in the study population and the intensity of the multimodal intervention. It should be noted that this sample size calculation and the post-hoc power analysis were performed after the data were analyzed, and therefore represent a post hoc justification rather than a prospective sample size estimation. Despite this, the achieved sample size still exceeded the minimum calculated requirement, and post-hoc power analysis confirmed that the final sample provided sufficient statistical power (>0.99) to detect the primary outcome. Therefore, the observed larger effect size does not compromise the validity of the sample size estimation.
Grouping method
Data were collected through medical record review at baseline (admission), at the 6-month time point (upon completion of the nursing intervention as documented in nursing records), and at the final follow-up (12 months post-intervention). The control group (n = 132) received routine hemodialysis nursing care, including assistance with dialysis treatment, vital signs monitoring, vascular access care, dietary guidance, medication education, and complication management. Nursing staff provided health education and psychological counseling according to standard procedures, without a systematic psychological nursing program. The observation group (n = 143) received, in addition to the routine care provided to the control group, a 6-month multimodal psychological nursing program. This program integrated three components: cognitive behavioral nursing, MBSR, and family support system construction.
Routine nursing protocol (both groups)
The control group received routine hospital hemodialysis nursing care, including monitoring of vital signs before, during, and after dialysis; vascular access care; dietary and fluid management guidance; medication guidance; health education and routine psychological comfort measures, such as listening, encouragement, and emotional counseling.
Multimodal psychological nursing protocol (observation group only)
The multimodal psychological nursing program lasted for 6 months (24 weeks) and integrated three components: (1) Cognitive Behavioral Nursing (Weeks 1-24): Based on cognitive behavioral therapy theory, systematic nursing care was provided targeting patients' maladaptive cognitions and negative automatic thoughts. The program comprised four phases delivered through 12 structured individual sessions: cognitive assessment and relationship building (Weeks 1-4, sessions 1-2), cognitive restructuring (Weeks 5-12, sessions 3-6, weekly 45-60 min individualized sessions), behavioral activation and coping training (Weeks 13-20, sessions 7-10), and consolidation and relapse prevention (Weeks 21-24, sessions 11-12). (2) Mindfulness-Based Stress Reduction (Weeks 1-24): Adapted from the classic Kabat-Zinn MBSR protocol, sessions were held twice weekly during dialysis (40 min/session), including mindful breathing (10 min), body scan (15 min), mindful meditation (10 min), and sharing (5 min). Patients were also instructed to practice mindful breathing for 15 min daily at home, with weekly nurse feedback via WeChat. (3) Family Support System Construction (Weeks 1-24): This component included family psychoeducation (Weeks 1-4), communication skills training (Weeks 5-12, monthly 90 min workshops), caregiver support groups (Weeks 13-20, monthly 120 min sessions), and family resource linkage (Weeks 21-24).
Treatment fidelity verification
To retrospectively verify treatment fidelity, we reviewed standardized nursing records and electronic medical records for three core components. A complete intervention was defined as ≥80% adherence across all components-specifically, participation in at least 10 of 12 cognitive sessions, ≥38 of 48 MBSR sessions, and completion of all three family support phases. Of the 187 patients allocated to the observation group, 14 failed to meet this 80% threshold; these patients were excluded from the final analysis and were included among the 48 patients excluded for incomplete records or missing questionnaire data. The program was delivered by five registered nurses (each with ≥5 years of hemodialysis experience) who completed a 40 h certified training in cognitive behavioral nursing and MBSR, under senior clinical psychologist supervision, with quarterly competency reassessments. Fidelity was independently checked by two research assistants against a predefined intervention checklist; disagreements were resolved by a third reviewer.
Clinical outcome measures
Data were collected through the electronic medical record system and nursing assessment records. All outcome measures were assessed at the following three time points: before nursing intervention (baseline), at the end of the nursing intervention (6 months), and 12 months after the end of the nursing intervention (18 months after baseline).
Negative emotions and psychological status
Self-Rating Anxiety Scale (SAS)18: Zung's 20-item, 4-point scale. Standard scores: <50 normal, 50-59 mild, 60-69 moderate, ≥70 severe anxiety.
Self-Rating Depression Scale (SDS)19: Zung's 20-item, 4-point scale. Standard scores: <50 normal, 50-59 mild, 60-69 moderate, ≥70 severe depression.
Distress Thermometer (DT)20: NCCN-recommended single-item 0-10 visual scale (0=no distress, 10=extreme distress).
Treatment adherence and self-management behaviors
Dialysis Treatment Adherence Questionnaire: The Treatment Adherence Scale for Maintenance Hemodialysis Patients21 assesses dietary, fluid, medication, and dialysis regimen adherence (0-100 scale; higher=better adherence).
Hemodialysis Patient Self-Management Behavior Questionnaire: The Chinese version of the Hemodialysis Patient Self-Management Behavior Scale22 has 20 items across four dimensions (problem-solving, self-care, partnership, emotional management), rated 1-4 (never to always). Total score 20-80; higher=stronger self-management.
Quality of life
Kidney Disease Quality of Life Short Form (KDQOL-36)23: Includes SF-12, Burden of Kidney Disease, Symptoms/Problems, and Effects on Daily Life. Each domain scored 0-100; higher=better QoL.
Psychological resources and coping
Herth Hope Index (HHI)24: 12 items, 4-point Likert scale (total score 12-48); higher scores indicate greater hope.
Connor-Davidson Resilience Scale (CD-RISC)25: 25 items across three dimensions (tenacity, strength, optimism), 5-point Likert scale (0-100); higher scores indicate better resilience.
Multidimensional Health Locus of Control Scale (MHLC)26: Only the Internality subscale (6 items, 6-point Likert scale) was used in this study, as it directly assesses the extent to which patients believe their health outcomes are determined by their own behaviors and efforts-a mechanism theoretically central to sustained treatment adherence and self-management. Higher scores indicate a stronger internal health locus of control.
Nursing satisfaction
Nursing satisfaction was assessed at the 6-month time point (end of the intervention) using a single-item, 4-level global rating scale (1 = dissatisfied, 2 = fair, 3 = satisfied, 4 = very satisfied). The scale was designed to be concise and practical for routine clinical use, and its framework was consistent with the approach described by Cheng and Lai27. We acknowledge that this single-item measure lacks formal psychometric validation therefore, these findings should be interpreted with caution, and future studies should use validated instruments to confirm them.
Statistical analysis
Statistical analyses were performed using statistical software. The normality of continuous variables was assessed using the Kolmogorov-Smirnov test combined with visual inspection of Q-Q plots. Normally distributed data are presented as mean ± standard deviation (SD), and non-normally distributed data as median with interquartile range (IQR). Categorical variables are expressed as frequencies and percentages and were compared using the chi-square test or Fisher's exact test, as appropriate. To evaluate longitudinal effects across three time points (baseline, 6 months [end of intervention], and 18 months [12-month follow-up]), we adopted a stratified approach based on data distribution. For normally distributed outcomes, we used repeated-measures ANOVA with group as the between-subjects factor and time as the within-subjects factor, focusing on the group × time interaction; the baseline value of the outcome and key covariates were entered as covariates. For non-normally distributed outcomes, we used generalized estimating equations (GEE). The primary outcome family was negative emotions (SAS, SDS, DT), measured at 6 and 18 months post-baseline, resulting in six between-group comparisons. Bonferroni correction was used for this primary family, with two-sided α = 0.05/6 = 0.0083. The remaining outcomes, including treatment adherence, self-management behaviour, KDQOL-36, psychological resources (HHI, CD-RISC, MHLC-Internality) and nursing satisfaction, were secondary exploratory endpoints. No multiplicity correction was performed for these exploratory outcomes; their p values are hypothesis-generating rather than confirmatory.
Results
These analyses tested the hypothesis that, compared with routine care alone, the six-month multimodal psychological nursing program would be associated with significantly greater and sustained improvements in negative emotions, treatment adherence and self-management behaviors, quality of life, and positive psychological resources, with effects lasting up to 12 months after the intervention.
Baseline characteristics
There were no statistically significant differences in baseline characteristics such as sex, age, BMI, dialysis vintage, primary cancer type, cancer stage, ECOG performance status, marital status, and education level (p > 0.05), suggesting that the groups were comparable with respect to these measured characteristics. Detailed baseline data are presented in Table 1.
Comparison of negative emotions
As shown in Table 2, before nursing intervention, no significant differences existed between groups in SAS, SDS, or DT scores (p > 0.05). At intervention end and 12 months later, the observation group showed significantly lower scores than the control group (p < 0.001 for all comparisons). Repeated-measures ANOVA revealed significant group × time interactions for SAS (F = 49.002, p < 0.001; partial η2 = 0.152) and SDS (F = 65.684, p < 0.001; partial η2 = 0.194). The effect sizes for between-group differences at post-intervention were large (Cohen's d: SAS = 1.741, SDS = 1.867). Notably, the observation group's anxiety scores decreased from 55.87 ± 8.92 at baseline to 42.35 ± 6.78 at 6 months (mean reduction of 13.52 points), and this improvement was largely maintained at 12-month follow-up (43.68 ± 7.15). In contrast, the control group showed minimal change over time.
Comparison of treatment adherence and self-management behavior scores
Table 3 shows that the observation group exhibited significantly higher scores on both the Dialysis Treatment Adherence Questionnaire and the Hemodialysis Patient Self-Management Behavior Questionnaire at 6 months and 12 months compared to controls (p < 0.001). The adherence score in the observation group improved from 63.18 ± 9.85 at baseline to 82.56 ± 7.45 at 6 months, representing a 30.7% improvement. The self-management score showed a similar pattern (baseline: 49.66 ± 8.11; 6 months: 69.44 ± 5.36). These improvements were sustained at 12-month follow-up (adherence: 80.28 ± 7.83; self-management: 68.69 ± 7.55).
Comparison of kidney disease quality of life scores
Table 4 presents KDQOL-36 scores. At 6 months, the observation group scored significantly higher than controls across all four dimensions (all p < 0.001). The largest within-group improvement in the observation group was observed in the SF-12 domain (from 53.18 ± 8.75 to 72.56 ± 7.24), followed by "Burden of Kidney Disease" (from 49.32 ± 8.15 to 68.45 ± 6.82) and "Effects of Kidney Disease on Daily Life" (from 46.32 ± 7.88 to 65.18 ± 6.58). At 6 months, the largest between-group differences were observed in the "Burden of Kidney Disease" domain (observation group 68.45 ± 6.82 vs. control group 49.18 ± 7.68; mean difference 19.27 points) and the SF-12 domain (72.56 ± 7.24 vs. 53.42 ± 8.18; mean difference 19.14 points), followed by the "Effects of Kidney Disease on Daily Life" domain (65.18 ± 6.58 vs. 46.25 ± 7.42; mean difference 18.93 points).
Comparison of psychological resources and coping scores
Table 5 shows that the observation group scored significantly higher than the control group on HHI, CD-RISC, and MHLC-Internality at both post-intervention and follow-up (p < 0.001). The HHI score improved from 31.75 ± 4.76 to 40.66 ± 5.21 in 6 months and remained elevated at 40.12 ± 6.33 at 12 months. The CD-RISC score showed a similar pattern (baseline: 59.32 ± 8.92; 6 months: 78.65 ± 7.18). Notably, the MHLC-Internality score-reflecting patients' belief that their health outcomes are determined by their own behaviors-increased from 22.71 ± 3.65 to 29.71 ± 2.85 at 6 months and remained significantly higher than baseline at 12 months (28.90 ± 2.88). This shift toward a more internal locus of control was sustained, suggesting a durable cognitive reappraisal of illness management.
Comparison of nursing satisfaction
The four-level distribution of nursing satisfaction is shown in Table 6. The overall satisfaction rate (proportion rating "satisfied" or "very satisfied") was 83.92% (120/143) in the observation group versus 70.45% (93/132) in the control group (χ2=7.123, df=1, p =0.007). The full distribution was as follows: "very satisfied," 43.36% (62/143) vs. 36.36% (48/132); "satisfied," 40.56% (58/143) vs. 34.09% (45/132); "fair," 12.59% (18/143) vs. 21.21% (28/132); and "dissatisfied," 3.50% (5/143) vs. 8.33% (11/132). Because nursing satisfaction was a secondary, exploratory endpoint, this comparison was not included in the multiple-testing correction; the p value should therefore be interpreted as hypothesis-generating.
Taken together, the analyses support the following conclusions. First, among patients receiving hemodialysis for renal failure complicated by cancer, a six-month multimodal psychological nursing program was associated with significantly greater reductions in anxiety, depression, and psychological distress than conventional care alone; these differences remained statistically significant after Bonferroni correction for the primary outcome family and after adjustment for baseline values and key covariates. Second, the program was associated with significantly higher treatment adherence, self-management behaviour, and quality of life, and with greater hope, resilience, and internal health locus of control at both post-intervention and 12-month follow-up; however, because these were secondary, exploratory endpoints analysed without multiplicity correction, these findings should be regarded as hypothesis-generating rather than confirmatory. Third, nursing satisfaction was higher in the observation group. The analyses do not establish causality, cannot exclude residual or unmeasured confounding, and do not identify which component of the multimodal program was responsible for the observed associations.
Data Availability
The raw datasets generated and analyzed during the current study are available as supplementary File 1.
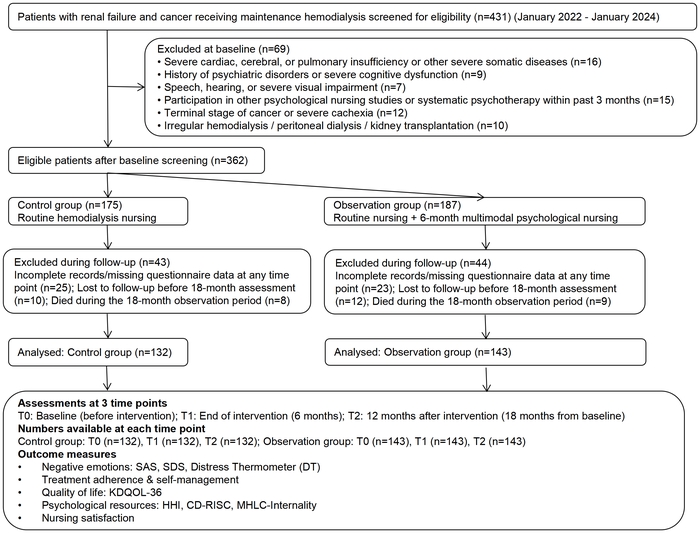
Figure 1: STROBE flow diagram of patient screening, eligibility, group allocation, follow-up, and analysis in this retrospective cohort study. This flowchart illustrates the patient selection process for this retrospective cohort study. A total of 431 patients with renal failure complicated by malignancy who received maintenance hemodialysis were initially screened between January 2022 and January 2024. After excluding 69 patients who met the predefined exclusion criteria, 362 eligible patients were followed for 18 months. During the follow-up period, 87 patients were further excluded due to incomplete clinical records or missing questionnaire data (n = 48), loss to follow-up before the 18-month assessment (n = 22), or death during the observation period (n = 17). The final analytic cohort comprised 275 patients, with 132 assigned to the control group (conventional care) and 143 to the observation group (conventional care plus multimodal psychological nursing). Data were collected at three time points: baseline, 6 months (end of intervention), and 18 months (12-month post-intervention follow-up). Please click here to view a larger version of this figure.
Table 1. Baseline demographic and clinical characteristics of the study population. Data are presented as mean ± SD or n (%). BMI, body mass index; ECOG, Eastern Cooperative Oncology Group. Dialysis vintage is expressed in months. Group comparisons were performed using independent t-test for continuous variables, Mann-Whitney U test for non-normally distributed data, and chi-square test for categorical variables. All variables were complete for all 275 patients, with no missing data. Baseline comparability was assessed on measured characteristics only; unmeasured factors such as personality traits, prior psychological trauma, baseline social support, and patient motivation could not be compared and may differ between groups. Please click here to download this Table.
Table 2. Comparison of negative emotion scores between the two groups at three time points. Data are presented as mean ± SD for normally distributed variables or median (IQR) for non-normally distributed variables. SAS, Self-Rating Anxiety Scale; SDS, Self-Rating Depression Scale; DT, Distress Thermometer. SAS and SDS were analysed by repeated-measures ANOVA (F statistics with partial η2 are reported); DT was analysed by generalized estimating equations (GEE), and Wald χ2 statistics are reported. SAS, SDS, and DT constitute the pre-specified primary outcome family; Bonferroni correction was applied across the six primary between-group comparisons (adjusted α = 0.0083). Please click here to download this Table.
Table 3. Comparison of treatment adherence and self-management behavior scores between the two groups at three time points. Data are presented as mean ± SD. The Dialysis Treatment Adherence Questionnaire (range 0-100) assesses adherence to dietary, fluid, medication, and dialysis regimen recommendations; higher scores indicate better adherence. The higher the score of the Hemodialysis Patient Self-Management Behavior Questionnaire (ranging from 20 to 80), the stronger the self-management ability. *p < 0.05 compared with baseline within the same group (post-hoc pairwise comparison with Bonferroni correction). Please click here to download this Table.
Table 4. Comparison of KDQOL-36 domain scores between the two groups at three time points. Data are presented as mean ± SD. KDQOL-36, Kidney Disease Quality of Life Short Form (36 items). The four domain scores (SF-12, Burden of Kidney Disease, Symptoms/Problems, and Effects of Kidney Disease on Daily Life) are each transformed to a 0-100 scale; higher scores indicate better quality of life. * p < 0.05 compared with baseline within the same group (post-hoc pairwise comparison with Bonferroni correction). Please click here to download this Table.
Table 5. Comparison of psychological resources and coping scores between the two groups. Data are presented as mean ± SD. HHI, Herth Hope Index (range 12-48); CD-RISC, Connor-Davidson Resilience Scale (range 0-100); MHLC-Internality, Multidimensional Health Locus of Control-Internality subscale (range 6-36). Higher scores indicate greater hope, resilience, and internal health locus of control, respectively. * p < 0.05 compared with baseline within the same group. Please click here to download this Table.
Table 6. Comparison of nursing satisfaction between the two groups. Data are presented as n (%). Nursing satisfaction was assessed using a single-item, 4-level global rating scale (1 = dissatisfied, 2 = fair, 3 = satisfied, 4 = very satisfied). The overall satisfaction rate was calculated as the proportion of patients rating "satisfied" or "very satisfied". Group comparison was performed using the chi-square test. Please click here to download this Table.
Supplementary File 1: Raw data supporting the findings of this study.Please click here to download this file.
Discussion
The role of psychological nursing in the management of chronic diseases has received increasing attention; however, research on the long-term effects of psychological nursing in patients with the dual disease burden of both renal failure and malignancy remains relatively limited. Based on the observed mind-body interactions in clinical practice, our team designed a multimodal psychological nursing protocol integrating cognitive behavioral nursing, MBSR, and family support system construction, and systematically evaluated its effects in 275 patients with renal failure and cancer undergoing hemodialysis using a retrospective cohort design. The results showed that, compared with conventional care alone, the multimodal psychological nursing protocol was associated with significantly better outcomes in anxiety, depression, and psychological distress, enhanced treatment adherence and self-management behaviors, strengthened hope, psychological resilience, and internal health locus of control, and sustained improvements in quality of life during the 12-month follow-up period after the intervention, together with higher nursing satisfaction at the end of the intervention. These findings provide important evidence for understanding the long-term effects of multimodal psychological nursing in patients with dual disease burden and offer an actionable framework for clinical nursing practice. A review by Vijayakumar28 reported that the prevalence of depression in patients with end-stage renal disease undergoing hemodialysis is as high as 39.3% when assessed by screening questionnaires and 22.8% when assessed by clinical interviews, rates substantially higher than those in the general population, and that the presence of depressive symptoms increases the risk of mortality by 1.5-fold in this population. Given this serious mental health challenge, exploring effective non-pharmacological nursing strategies is of considerable clinical importance.
From the perspective of psychopathological mechanisms, the negative emotions in patients with renal failure complicated by cancer have multiple sources, including not only the physical pain and functional loss caused by the diseases themselves but also fear of prognostic uncertainty, accumulation of treatment burden, and loss of social role functioning. In this study, after receiving multimodal psychological nursing, the observation group showed significantly lower scores on the SAS, SDS, and DT compared with the control group, and these effects persisted until 12 months after the completion of the intervention. This long-term association may be partially explained by the mechanisms of cognitive-behavioral nursing, although this remains a potential pathway requiring confirmation in future studies. By identifying and challenging negative automatic thoughts-such as cognitive distortions like "cancer equals death" or "dialysis is hopeless"-cognitive-behavioral nursing helps patients establish a more adaptive cognitive framework for their illnesses. The TACcare randomized controlled trial reported by Jhamb et al.29 demonstrated that cognitive-behavioral therapy delivered via telehealth combined with targeted symptom management significantly improved pain, fatigue, and depressive symptoms in dialysis patients. Specifically, pain severity decreased by 0.96 points, fatigue improved by 2.81 points, and depression scores decreased by 1.73 points in the intervention group at the 3-month follow-up compared with the control group. This study confirms the effectiveness of cognitive-behavioral nursing in symptom management for dialysis patients. Through a 12-month follow-up design, the present study further confirms that the adaptive cognitive patterns established through cognitive restructuring have good temporal stability. This may be related to the internalization of cognitive coping strategies by patients during the nursing process, enabling them to autonomously mobilize these strategies for emotional regulation when facing disease-related stressors again. MBSR is another core component of the multimodal psychological nursing protocol, and its role in alleviating patients' negative emotions has been validated in multiple studies. A randomized controlled trial by Wu et al.30 showed that a 12-week intervention combining mindfulness meditation with progressive muscle relaxation significantly reduced SAS and SDS scores, and improved sleep quality and quality of life in maintenance hemodialysis patients. The study by Cengiz et al.31 further expanded the perspective of mindfulness-based care by implementing an 8-week mindfulness-based compassionate living training program for hemodialysis patients. Their results demonstrated a significant decrease in stress scores and marked improvements in quality of life, self-compassion, and mindful awareness in the intervention group. Notably, the intervention by Cengiz et al.31 was delivered during dialysis sessions, lasting 30 min per session, twice a week, which is highly consistent with the design concept of integrating mindfulness practice into dialysis days in the present study. This approach of embedding psychological nursing into routine dialysis procedures not only improves accessibility and adherence to care but, more importantly, helps patients directly practice and experience mindfulness skills within the specific stressful context of dialysis, achieving a high degree of congruence between the learning environment and the application environment. On this basis, the present study extended the nursing period to six months and included a 12-month follow-up. The results showed that the observed improvement in negative emotions in the observation group remained significant at the end of follow-up, suggesting that the awareness and acceptance cultivated through mindfulness practice may have enduring psychological protective effects.
Higher treatment adherence was another difference observed in the observation group of this study. Treatment adherence in patients on maintenance hemodialysis involves multiple dimensions, including fluid intake restriction, dietary management, medication regimens, and regular dialysis attendance. Non-adherence in any of these areas can lead to serious adverse consequences32. For patients with concurrent cancer, the superimposition of treatment regimens makes adherence management even more challenging. In this study, the observation group scored significantly higher than the control group on both the Dialysis Treatment Adherence Questionnaire and the Hemodialysis Patient Self-Management Behavior Questionnaire, and this difference persisted at the 12-month follow-up. This finding can be explained by behavioral activation and the theory of health locus of control. Behavioral activation techniques encourage patients to develop and implement pleasant activity schedules, gradually restoring social functioning and regularity in daily activities. This process not only directly enhances patients' active participation in their treatment but, more importantly, reshapes their attributional patterns regarding their health locus of control33. Dewanto et al.34 reported that, through a descriptive correlational analysis of patients with chronic renal failure on hemodialysis, family support showed a significant positive correlation with patients' adherence to dialysis treatment. That study confirmed that patients who receive adequate family support are more likely to complete their hemodialysis treatment regularly. Furthermore, the results of the present study showed a significant increase in the internal locus of control scores on the MHLC scale in the observation group, indicating that patients gradually shifted from an external control mode-where illness is seen as fate or entirely determined by doctors-to an internal control mode, believing that they can influence health outcomes through their own efforts. This shift in health locus of control may be a key psychological mechanism underlying sustained improvement in treatment adherence35.
The study also found a significant improvement in quality of life: the observation group scored higher than controls on all KDQOL-36 dimensions. In a preliminary study by Cecyli et al.36, an 8-week structured MBSR program was implemented in hemodialysis patients, and the results showed significant improvements in the intervention group across multiple KDQOL dimensions, including symptoms/problems, effects of kidney disease on daily life, sleep, physical functioning, and role limitations due to physical health. Despite the study's small-sample quasi-experimental design, the large effect sizes offer preliminary evidence that mindfulness-based interventions may improve quality of life in dialysis patients. Several ongoing clinical studies are further expanding the research landscape in this area. In addition, the Hemomindful program developed by Brazilian researchers explored an individualized mindfulness-based intervention delivered at the dialysis chairside. Preliminary feasibility data from this program showed patient satisfaction scores of 8.58, and qualitative interview results revealed positive changes in participants' awareness of daily activities, management of emotional reactivity, and coping with pain and discomfort37. These studies suggest that integrating mindfulness-based interventions into the dialysis treatment process is feasible and well accepted. The contribution of this study lies in its demonstration, through a 6-month relatively long nursing period and a 12-month follow-up design, that the beneficial associations of multimodal psychological nursing on quality of life are sustained over time, thereby providing more robust evidence to support the integration of psychological nursing into routine dialysis treatment protocols in clinical practice.
Changes in the psychological-resource measures accompanied the observed differences between groups and may represent one pathway through which the multimodal program was associated with its long-term effects. The observation group scored significantly higher on the HHI, CD-RISC, and the Internality subscale of the MHLC scale than the control group. The improvement in hope can be explained by the goal-setting and behavioral activation techniques employed in cognitive behavioral nursing. During the nursing process, the therapist helped patients break down abstract hopes for survival into concrete, achievable small goals. Each achievement of a goal served as positive reinforcement for self-efficacy, and this gradual accumulation of experiences constituted the foundation for the sustained growth of hope. The enhancement of psychological resilience was closely related to the training in emotion regulation skills provided by MBSR therapy. The comparative study by Salehi Mobarakeh et al.38 explored the effects of mindfulness-based cognitive therapy and spiritual self-care training (SSCT) on components of suffering in hemodialysis patients, and the results showed that both interventions significantly reduced patients' physical, psychological, and existential suffering. Notably, the study found that SSCT was superior to mindfulness-based cognitive therapy in alleviating physical and psychological suffering, suggesting that integrating more individualized spiritual elements into psychological nursing may yield additional benefits. In this study, the family support system building module provided patients with multiple forms of social support-emotional, instrumental, and informational-through caregiver support groups and family meetings, thereby responding to the differentiated needs of different patient populations for types of support. The unique value of family support lies not only in providing direct emotional comfort and practical help to patients but, more importantly, in constructing an environment that continuously offers positive interpersonal feedback through improved family communication patterns. This environmental factor plays a crucial catalytic role in maintaining hope and psychological resilience.
This study has several limitations. First, as a retrospective cohort study, selection bias and unmeasured confounding cannot be completely excluded. Although the two groups were comparable on measured baseline characteristics, unmeasured factors such as personality traits, prior psychological trauma, baseline social support, and patient motivation were not available and could not be compared; patients in the observation group may have had a stronger inherent tendency to actively seek psychological support, and this individual difference may have influenced the observed outcomes. Second, the study was conducted at a single hospital in China, with a specific healthcare organization and nurse-to-patient ratio, which limits the representativeness of the sample and the generalizability of the findings. The multimodal program requires intensive personnel involvement and structured protocols and may not be directly replicable in healthcare systems with limited nursing resources or different cultural backgrounds. Future multicenter studies in diverse geographic, economic, and cultural contexts are therefore needed to validate its external validity and adaptability. Third, because group assignment was determined by the calendar date of a hospital-wide rollout, the design is effectively a before-and-after comparison rather than a randomized one; any secular change occurring over the same period-such as changes in nursing staffing, hemodialysis practice, oncology treatment, or the COVID-19 recovery-could be confounded with the intervention. We confirm that no other systematic change to hemodialysis or oncology care occurred at the time of the rollout; nevertheless, this potential confounding cannot be fully excluded, and future prospective randomized trials are needed to confirm causality. Fourth, 87 of the 362 eligible patients (24.03%) were excluded after baseline, including 17 deaths and 22 losses to follow-up. Because the analysis was restricted to patients with complete data, differential survival and drop-out between groups may introduce survivor bias and selection bias this potential bias cannot be fully excluded, and the results should be interpreted with caution. Fifth, multiple-testing control was applied only to the pre-specified primary outcome family; the secondary outcomes (treatment adherence, self-management, quality of life, psychological resources, and nursing satisfaction) were analysed as exploratory endpoints without multiplicity correction, and their p values should therefore be interpreted as hypothesis-generating rather than confirmatory. Sixth, although the program showed statistically significant associations with multiple questionnaire-based outcomes, the clinical significance and minimal clinically important differences of these changes remain to be established. Future prospective randomized controlled trials with larger samples, longer follow-up, and qualitative methods are needed to clarify patients' subjective experiences and mechanisms of change, and to evaluate clinical hard endpoints such as hospitalization rates, cardiovascular events, and survival.
The analysis of this retrospective cohort study suggests that a six-month multimodal psychological nursing program is associated with significant and durable improvements on alleviating negative emotions, improving treatment adherence and quality of life, and enhancing positive psychological resources in patients with renal failure complicated by cancer undergoing hemodialysis. These associations persisted throughout the 12-month follow-up period after the completion of the nursing intervention. It is important to emphasize that, due to the retrospective cohort design, the associations observed in this study should not be interpreted as causal. Although we observed consistent and statistically significant differences between the two groups across multiple outcomes, we cannot exclude the possibility of residual confounding or selection bias. Therefore, the mechanisms discussed above-including cognitive restructuring, mindfulness practice, and family support-should be viewed as potential explanatory pathways rather than proven causal mediators. Future prospective randomized controlled trials are warranted to establish causality and to isolate the specific contribution of each component of the multimodal program.
Disclosures
The authors declare no financial or non-financial conflicts of interest. No artificial intelligence tools were used in the design, conduct, analysis, or reporting of this study.
Acknowledgements
The authors have no acknowledgments to report. This study received no external funding.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 20x objective lens | Olympus | MPLFLN | Objective lens/2D mapping analysis |
| Acetaminophen | Sigma-aldrich | 103-90-2 | Analyte/analysis |
| Anodisc aluminum oxide (AAO) membrane (200 nm pore size) | Whatman | 6809-5522 | Vaccum filtration/CNT scaffold |
| Ar | Hanyoung Gas Technology | www.gasmaster.co.kr | Ar gas purge source/ALD |
| Au (99.999%) | iTASCO | EAU0KI0001 | E-beam evaporation target |
| BPE (1,2-bis(4-pyridyl)ethylene) (97%) | Sigma-aldrich | 13362-78-2 | Analyte/analysis |
| Dream Plus | MDM instrument | www.wiley.com/doi/10.1002/adma.202203671 | DI-water purifier/CNT scaffold |
| DST1 | Vaccoat | www.vaccoat.com/products/magnetron-sputter-coater-dst1-300/ | Sputter/metal deposition |
| F 12/100/940 | Lenton | www.nature.com/articles/s41427-023-00523-7 | Furnace/CNT cleaning |
| FEX-MD | WEVE | www.mdpi.com/2079-6447/4/4/29 | Raman spectroscopy/LOD analysis |
| H1850 | Cence | 203270008 | Centrifuge/CNT scaffold |
| Invia confocal Raman microscope | Renishaw | www.renishaw.com | Raman spectroscopy/2D mapping analysis |
| JAC-3010 | KODO | U02-328-321 | Sonicator/CNT scaffold |
| KVE-C3001160 | Korea Vacuum Tech | www.koreavac.com | E-beam evaporator/metal deposition |
| Methanol (99.5%) | Samchun | www.samchun.com/en/sub/product/list.asp | Solvent/analysis |
| plus 200 | Quros | www.quros.co.kr | Atomic layer deposition/oxide intermediary layer |
| S-4800 | HITACHI | www.hitachi-hightech.com | SEM/analysis |
| Secure-seal | Electron Microscopy Sciences | 70333-36 | Hybridization chamber |
| TNWDS 0.2 wt% | Timesnano | TNWDS | SWNT CNT/CNT scaffold |
| Trimethylaluminium(TMA) | UPChem | www.upchem.co.kr/eng/product/product.php | Al2O3 precursor/ALD |
| VACNT with entangled canopy on top | Porifera Inc. | www.porifera.com | VACNT scaffold |
References
- Lameire NH, et al. Harmonizing acute and chronic kidney disease definition and classification: report of a Kidney Disease: Improving Global Outcomes (KDIGO) Consensus Conference. Kidney Int. 2021;100(3):516-26.
- Zhang L, et al. Prevalence of chronic kidney disease in China: a cross-sectional survey. Lancet. 2012;379(9818):815-22.
- Cheng HT, Xu X, Lim PS, Hung KY. Worldwide epidemiology of diabetes-related end-stage renal disease, 2000-2015. Diabetes Care. 2021;44(1):89-97.
- Basaran E, Uysal C. Sleep quality in hemodialysis patients according to renal anemia treatment outcomes. Advances in Modern Biomedicine. 2025;1(3):1-10.
- Li Y, Zhu B, Shen J, Miao L. Depression in maintenance hemodialysis patients: what do we need to know? Heliyon. 2023;9(9):e19383.
- Yousafzai IK, et al. Frontiers in cancer and haematology: emerging biomarkers, therapeutics, and technologies. Current Cancer Research. 2026;1(1):54-68.
- Nagy E, et al. Anxiety and depression in maintenance hemodialysis patients: prevalence and their effects on health-related quality of life. Int Urol Nephrol. 2023;55(11):2905-14.
- Al-Shammari N, et al. Prevalence of depression, anxiety, and their associations among end-stage renal disease patients on maintenance hemodialysis: a multi-center population-based study. Psychol Health Med. 2021;26(9):1134-42.
- Schouten RW, et al. Anxiety symptoms, mortality, and hospitalization in patients receiving maintenance dialysis: a cohort study. Am J Kidney Dis. 2019;74(2):158-66.
- Barnes GL, Haghiran MZ, Tracy DK. Contemporary perceptions and meanings of 'the medical model' amongst NHS mental health inpatient clinicians. Int J Ment Health Nurs. 2022;31(3):567-75.
- Barello S, et al. The effect of psychosocial interventions on depression, anxiety, and quality of life in hemodialysis patients: a systematic review and a meta-analysis. Int Urol Nephrol. 2023;55(4):897-912.
- Hernandez R, et al. Feasibility of an internet-based positive psychological intervention for hemodialysis patients with symptoms of depression. Soc Work Health Care. 2018;57(10):864-79.
- Chen HC, et al. The effectiveness of a psychoeducational intervention on health outcomes of patients undergoing haemodialysis: a randomized controlled trial. Int J Nurs Pract. 2023;29(3):e13123.
- Li Y, Yan Y. The impact of evidence-based nursing combined with cognitive behavioral therapy on disease management and quality of life in chronic renal failure patients undergoing hemodialysis. Br J Hosp Med (Lond). 2026;87(5):49922.
- Ajele KW, Idemudia ES. Mindfulness-based interventions for depression, anxiety, and stress in adults with cancer: a stratified subgroup meta-analysis. Psychooncology. 2026;35(3):e70424.
- Zhang L, et al. Experiences of effective psychological adjustment in patients undergoing maintenance hemodialysis: a qualitative study. Patient Prefer Adherence. 2026;20:576627.
- Ren W, Chen Z, Liu X, Zhu X. Effect of evidence-based nursing supervision on hemodialysis patients with chronic kidney failure. Medicine (Baltimore). 2025;104(41):e44777.
- Dunstan DA, Scott N. Norms for Zung's Self-rating Anxiety Scale. BMC Psychiatry. 2020;20(1):90.
- Lindseth G, Helland B, Caspers J. The effects of dietary tryptophan on affective disorders. Arch Psychiatr Nurs. 2015;29(2):102-7.
- Ownby KK. Use of the Distress Thermometer in clinical practice. J Adv Pract Oncol. 2019;10(2):175-79.
- Zhang Y, HJ. Development of a treatment adherence scale for maintenance hemodialysis patients with end-stage renal disease. Chinese General Practice. 2013;16(34):3312-16.
- Li H, Cao Y, Jiang Y, Wang J. Introduction of hemodialysis patient self-management scale and reliability and validity test. Chinese Journal of Nursing. 2015;50(11):1392-95.
- Peipert JD, et al. Kidney Disease Quality of Life 36-item short form survey (KDQOL-36) normative values for the United States dialysis population and new single summary score. J Am Soc Nephrol. 2019;30(4):654-63.
- Nayeri ND, et al. Construct validity of the Herth Hope Index: a systematic review. Int J Health Sci (Qassim). 2020;14(5):50-57.
- Martinez S, et al. Factor structure and psychometric properties of the Connor-Davidson Resilience Scale (CD-RISC) in individuals with opioid use disorder. Drug Alcohol Depend. 2021;221:108632.
- Wallston KA. The validity of the Multidimensional Health Locus of Control Scales. J Health Psychol. 2005;10(5):623-31.
- Cheng WLS, Lai CKY. Satisfaction Scale for Community Nursing: development and validation. J Adv Nurs. 2010;66(10):2331-40.
- Vijayakumar V. Effectiveness of pharmacological versus non-pharmacological methods for managing depression in patients undergoing hospital hemodialysis: a narrative review. Cureus. 2025;17(10):e94326.
- Jhamb M, et al. Effects of technology assisted stepped collaborative care intervention to improve symptoms in patients undergoing hemodialysis: the TACcare randomized clinical trial. JAMA Intern Med. 2023;183(8):795-805.
- Wu Y, et al. Effects of mindfulness meditation combined with progressive muscle relaxation on sleep disorders, anxiety, and depression in patients with sarcopenia undergoing hemodialysis. Front Psychiatry. 2025;1542028.
- Cengiz M, Kılıc D, Coban M. The effects of Mindfulness-Based Compassionate Living practice on stress, self-efficacy, and quality of life of haemodialysis patients: a randomized controlled trial. Health Educ Res. 2025;40(5):cyaf040.
- Win KCM, et al. Factors contributing to non-adherence to treatment among adult patients with long-term haemodialysis: an integrative review. Nurs Rep. 2025;15(9):314.
- Peipert A, Rutter LA, Howard J, Lorenzo-Luaces L. Self-guided behavioral activation using an online single-session intervention: content and lexical analyses of activity scheduling. Behav Ther. 2025;56(3):501-12.
- Dewanto A, Indrawati L, Nuryanti L. The relationship between family social support and compliance of chronic renal failure patients undergoing hemodialysis. Journal of Vocational Nursing. 2025;6(1):1-6.
- De Las Cuevas C. Psychiatric patients' perceived health control and reactance: implications for medication adherence. Patient Prefer Adherence. 2023;17:1591-601.
- Cecyli C, SN, Thenmozhi P. Effectiveness of a mindfulness-based stress reduction program on quality of life among hemodialysis patients: a preliminary study. Journal of Pharmaceutical and Medical Sciences. 2025;12:33-37.
- Adamoli AN, et al. Feasibility of the Hemomindful Program: a mindfulness-based program performed during hemodialysis. J Bras Nefrol. 2025;47(1):e20240068.
- Salehi Mobarakeh A, Golparvar M, Yousefi Z. A comparative study on the efficacy of mindfulness-based cognitive therapy and spiritual self-care training on the components of suffering in hemodialysis patients. Hospital Practices and Research. 2025;10(2):674-82.