This retrospective cohort study compares resin infiltration combined with flowable resin composite pit-and-fissure sealing versus sealing alone for non-cavitated initial occlusal carious lesions in permanent molars.
Research Article
Resin Infiltration with Flowable Resin Composite Sealing for Non-Cavitated Occlusal Caries: A Retrospective Cohort Study
* These authors contributed equally
In This Article
Summary
Abstract
Non-cavitated occlusal pit-and-fissure carious lesions in permanent molars are common among children and adolescents; however, evidence remains limited on whether resin infiltration, combined with flowable resin composite pit-and-fissure sealing, provides superior short-term lesion control compared with sealing alone. This single-center retrospective cohort study included permanent molars with non-cavitated occlusal pit-and-fissure carious lesions, classified according to the International Caries Detection and Assessment System (ICDAS) codes 1–2, in patients aged 6–18 years. The affected tooth served as the unit of analysis. The primary outcome was lesion progression within 12 months, defined as cavitation or localized enamel breakdown, a new radiolucency in dentin, or an operative restoration due to caries progression on the same occlusal surface. A total of 842 patients with 1,117 affected teeth were included, of which 989 teeth had evaluable 12-month outcomes, comprising 330 teeth in the combined-treatment group and 659 teeth in the sealing-alone group. Lesion progression occurred in 6.97% of teeth treated with the combined approach compared with 13.05% of teeth treated with sealing alone, corresponding to an absolute risk reduction of 6.08 percentage points. Modified Poisson regression with generalized estimating equations demonstrated that the combined treatment was associated with a significantly lower 12-month risk of lesion progression after adjustment for prespecified confounders (adjusted RR, 0.52; 95% CI, 0.33–0.82; p = 0.005). Sensitivity analyses, including complete-case analysis, inverse probability of treatment weighting, restriction to baseline ICDAS 2 lesions, and exclusion of partially erupted molars, yielded consistent findings (RRs, 0.51, 0.54, 0.49, and 0.56; p = 0.006, 0.008, 0.009, and 0.022, respectively). These findings suggest that resin infiltration combined with flowable resin composite pit-and-fissure sealing may provide more effective short-term control of lesion progression than sealing alone and may represent a useful microinvasive treatment option for non-cavitated initial occlusal pit-and-fissure carious lesions in permanent molars.
Introduction
Dental caries remains one of the oral diseases with the heaviest global burden. The World Health Organization has reported that oral diseases affect nearly 3.7 billion people worldwide, and untreated caries in permanent teeth is among the most common health conditions in the Global Burden of Disease Study1. The pit-and-fissure surfaces of permanent molars in children and adolescents are particularly susceptible to caries because of their deep, narrow morphology and the difficulty of effective plaque control in these areas. Modern caries management has shifted from post-cavitation restorations to early lesion control and tooth preservation based on risk assessment2. The International Caries Classification and Management System emphasizes that nonrestorative control strategies should be prioritized for initial non-cavitated lesions3. Similarly, the American Dental Association and the American Academy of Pediatric Dentistry recommend pit-and-fissure sealing for non-cavitated occlusal caries in children and adolescents to prevent or arrest lesion progression4.
Flowable resin composite has been used as a pit-and-fissure sealing material, and a randomized study suggests that it may provide retention and caries-control effects comparable to those of conventional resin sealants at 36 months5. However, non-cavitated initial pit-and-fissure carious lesions are not limited to surface color changes. Subsurface demineralization may extend beneath an apparently intact enamel surface, and surface sealing acts mainly at the fissure entrance rather than directly occluding microporosities within the lesion body6. Resin infiltration is a microinvasive approach in which a low-viscosity resin penetrates the demineralized lesion body and occludes enamel microporosities, thereby providing an additional internal sealing mechanism7. Effective resin infiltration depends on adequate erosion of the relatively impermeable surface layer covering the lesion body. In an in vitro study of ICDAS 2 pit-and-fissure lesions, hydrochloric acid gel containing abrasives and applied with brushing produced greater surface-layer erosion and deeper resin penetration than phosphoric acid-based pretreatment, highlighting the importance of lesion pretreatment before occlusal infiltration8.
Although clinical guidelines continue to emphasize sealing for initial occlusal caries, clinical evidence supporting occlusal resin infiltration has gradually accumulated9. In a split-mouth randomized trial of primary molars, both infiltration and sealing showed high efficacy in arresting initial occlusal caries over 2–3 years, and radiographic progression was significantly less frequent after infiltration than after fluoride varnish alone10. A 3-year randomized trial in permanent teeth found that resin infiltration provided lesion control comparable to conventional fissure sealing, with favorable radiographic findings11. A subsequent 24-month randomized trial reported favorable caries-preventive performance when a resin infiltrant was combined with a nanoparticle resin-based sealant12. Nevertheless, evidence remains limited regarding tooth-level lesion progression in routine clinical practice and the direct comparison of resin infiltration combined with flowable resin composite sealing versus flowable resin composite sealing alone13.
This single-center retrospective cohort study included non-cavitated initial occlusal pit-and-fissure carious lesions in permanent first and second molars of patients aged 6-18 years. The primary objective was to compare the 12-month risk of lesion progression after resin infiltration combined with flowable resin composite pit-and-fissure sealing versus flowable resin composite pit-and-fissure sealing alone. Outcome assessment was based on clinical records, intraoral photographs, and digital bitewing radiographs. Because lesion progression is more directly relevant to clinical decision-making than sealant retention alone, the study focused on whether the lesion progressed deeper, aiming to provide evidence closer to routine outpatient practice for the microinvasive management of initial pit-and-fissure caries. The null hypothesis was that the 12-month risk of lesion progression would not differ between teeth treated with resin infiltration combined with flowable resin composite pit-and-fissure sealing and those treated with flowable resin composite pit-and-fissure sealing alone.
Protocol
This single-center retrospective cohort study was designed and reported in accordance with the STROBE Statement14. The study used previously acquired outpatient medical records, intraoral photographs, and digital imaging data without requiring any additional examinations or treatments. The study protocol was approved by the Ethics Committee of Sinopharm Dongfeng Stomatological Hospital, Hubei University of Medicine (approval number LW-2026-01). Because all data had been de-identified before analysis, the ethics committee waived the requirement for informed consent.
Case source and study population
The study was conducted in the Department of Preventive Dentistry at Sinopharm Dongfeng Stomatological Hospital, Hubei University of Medicine. The retrospective study period included consecutive patients who received the index treatment between January 1, 2022, and December 31, 2023. Follow-up data were retrieved through February 28, 2025, and the database was locked on March 31, 2025. Data were obtained from the electronic medical record system, treatment record system, billing code system, digital imaging archive, and intraoral photography system. The index date was defined as the date on which the eligible microinvasive treatment was completed. The unit of analysis was the index occlusal lesion of the affected tooth rather than the patient.
Treatment allocation was not randomized and was not determined for research purposes. Instead, treatment selection was made by the treating dentist as part of routine clinical practice and was not systematically recorded as an independent decision variable. Lesion characteristics, eruption status, the feasibility of moisture control, operator preference, and other clinical considerations may all have influenced treatment selection. Consequently, different eligible teeth within the same patient could receive different treatment strategies, and each tooth was classified according to the treatment actually received. The unequal group sizes reflected the relative frequency with which the two treatment strategies were used in routine clinical practice rather than a planned 1:1 allocation. Statistical analyses accounted for clustering at the patient level.
The study population consisted of permanent first or second molars in patients aged 6–18 years. Eligible teeth met all of the following inclusion criteria: at the index visit, the target occlusal surface was diagnosed as International Caries Detection and Assessment System (ICDAS) code 1 or 2 after tooth cleaning, isolation, and continuous air-drying for 5 s; the baseline digital bitewing radiograph demonstrated no dentin radiolucency on the occlusal surface; and either resin infiltration combined with flowable resin composite pit-and-fissure sealing or flowable resin composite pit-and-fissure sealing alone was completed during the same visit.
For teeth without an outcome event within 12 months, follow-up at the same hospital between 10 and 14 months after the index treatment was required, with interpretable clinical records, intraoral photographs, and digital bitewing radiographs available. For teeth that underwent operative restoration because of progression of caries on the same occlusal surface within 12 months, the treatment record documenting the restoration served as evidence of the outcome, and no additional endpoint imaging was required.
The exclusion criteria were as follows: previous resin infiltration, pit-and-fissure sealing, restoration, crown restoration, or root canal treatment involving the index occlusal surface; localized enamel breakdown, a definite cavity, an underlying dentinal shadow, or radiographic dentin radiolucency at baseline; concomitant enamel hypoplasia, moderate-to-severe fluorosis-related structural defects, or traumatic crown defects; orthodontic attachments covering the index occlusal surface; inability to confirm the primary exposure; or uninterpretable follow-up data. If multiple eligible treatment records for the same tooth were identified during the study period, only the earliest eligible treatment was retained as the index treatment.
Lesion diagnosis and classification criteria
Baseline lesion diagnosis was based on standardized clinical examination, intraoral photographs, and digital bitewing radiographs obtained on the day of the index visit. Baseline and follow-up digital bitewing radiographs were acquired using the same model of complementary metal-oxide-semiconductor (CMOS) intraoral sensor according to a standardized clinical protocol (70 kVp, 7 mA, and an exposure time of 0.10–0.14 s, depending on tooth size and arch). A bitewing positioning system consisting of a sensor holder, bite block, alignment arm, and aiming ring was used to standardize sensor positioning and X-ray beam alignment. The sensor was positioned parallel to the crowns of the index molars, and the central X-ray beam was directed through the interproximal contacts. At follow-up, the same sensor type, positioning system, exposure protocol, and software display conditions were used whenever technically feasible. Images showing substantial proximal contact overlap, geometric distortion, or incomplete visualization of the index occlusal surface were considered uninterpretable. Routine daily system checks and monthly quality-control procedures were performed throughout the study period.
Before clinical examination, the tooth surface was cleaned with fluoride-free prophylaxis paste. After isolation, the tooth was continuously air-dried for 5 s, and lesion assessment was performed under standard operatory light by dentists trained in the International Caries Detection and Assessment System (ICDAS). When necessary, a ball-ended probe was used only to remove debris and confirm surface continuity; sharp probing was not performed. ICDAS code 1 was defined as the first visual change in enamel that became visible only after air-drying, including a chalky white or discolored lesion. ICDAS code 2 was defined as a distinct visual change in enamel color or translucency that was visible when wet and became more apparent after air-drying15. Both ICDAS codes required an intact enamel surface with no localized enamel breakdown or definite cavitation.
Because bitewing radiographs do not provide the same anatomical precision for occlusal lesions as for proximal lesions, the radiographic categories E0, E1, E2, D1, D2, and D3 were used only as prespecified study-specific ordinal descriptors of radiographic appearance rather than direct measures of histological lesion depth. E0 indicated no visible occlusal radiolucency; E1 and E2 indicated radiolucency apparently confined to the outer and inner halves of the enamel, respectively; and D1, D2, and D3 indicated radiolucency apparently extending into the outer, middle, and inner thirds of dentin, respectively16. Eligible lesions were clinically classified as ICDAS code 1 or 2 and demonstrated no radiographic evidence of dentin involvement, corresponding to the study-specific radiographic categories E0–E2.
When discrepancies existed among the clinical records, intraoral photographs, and radiographic findings, two assessors independently reviewed the case. If disagreement persisted after independent review, the case was referred to a third senior dentist for adjudication in accordance with the predefined adjudication procedure described below. Cases that remained uninterpretable after adjudication were excluded from the study.
Exposure and treatment protocols
The exposure of interest was the microinvasive treatment strategy implemented at the index visit. All procedures were performed according to a standardized departmental protocol by three dentists with more than 5 years of experience in preventive and restorative dentistry: operator 1 (X.Q.), operator 2 (Z.Z.), and operator 3 (J.Z.). Before study initiation, all operators received standardized training on the clinical procedures and treatment protocols used in this study.
Before treatment, the tooth surface was cleaned with fluoride-free prophylaxis paste. Isolation was achieved using either a rubber dam or cotton rolls in combination with high-volume suction. Rubber dam isolation was preferred when eruption status and tooth position permitted stable clamp placement and complete field control. Cotton rolls combined with high-volume suction were used when partial eruption, tooth position, or inadequate clamp stability precluded reliable rubber dam placement. The isolation method was recorded for each affected tooth and included as a prespecified covariate because moisture control could influence both treatment selection and material performance. The distribution of isolation methods between treatment groups is presented in Table 1. All light-curing procedures were performed using an LED curing unit with an output intensity of at least 1000 mW/cm2.
In the combined treatment group, a 15% hydrochloric acid pretreatment gel was applied to the occlusal pit-and-fissure lesion for 120 s, then rinsed with water for 30 s and air-dried. The lesion was then dehydrated with 99% ethanol for 30 s. A low-viscosity light-cured resin infiltrant was subsequently applied for 3 min and light-cured for 40 s. The infiltrant application was repeated for 1 min, followed by a second 40-s light-curing cycle. After completion of resin infiltration, the fissure entrance and adjacent enamel were etched with 37% phosphoric acid for 20 s, rinsed thoroughly, and air-dried. A universal adhesive was then applied and light-cured for 20 s, after which the fissure system was sealed with a flowable resin composite. A dental probe was used to facilitate penetration of the material into the fissures and to remove any trapped air bubbles before light curing for 40 s. Finally, marginal adaptation and occlusal contacts were evaluated and adjusted as necessary.
In the sealing-alone group, resin infiltration was not performed. Instead, the fissures and adjacent enamel were directly etched with 37% phosphoric acid for 20 s, then rinsed and air-dried. The same universal adhesive was applied and light-cured for 20 s, and the same flowable resin composite was used to complete pit-and-fissure sealing. Final light curing, assessment of marginal adaptation, and occlusal adjustment were performed using the same procedures as those used in the combined treatment group.
Following treatment, patients in both groups received identical oral hygiene instructions and were advised to brush twice daily with toothpaste containing 1450 ppm fluoride. Adherence to these oral hygiene instructions was not systematically monitored due to the study's retrospective design. Supplementary sealing performed within 30 days after the index treatment to correct marginal bubbles or localized underfilling was considered part of the original treatment procedure and was not classified as an outcome event.
Baseline data and potential confounders
Potential confounders were prespecified before data extraction. Patient-level variables included age, sex, total dmft+DMFT score, and the visible plaque index. The total dmft+DMFT score was obtained from the full-mouth record of decayed, missing, and filled teeth on the day of the index visit, and the visible plaque index was obtained from the full-mouth examination performed at the same visit.
Tooth-level variables included dental arch (maxillary or mandibular), molar type (first or second permanent molar), eruption status, baseline ICDAS classification, and the baseline study-specific radiographic appearance category. Operator-level variables included operator identity and isolation method.
Complete eruption was defined as the entire occlusal surface being above the gingival margin, allowing complete isolation. Partial eruption was defined as the persistence of a gingival operculum covering part of the occlusal surface. The visible plaque index was calculated as the proportion of examined tooth surfaces that were positive for visible plaque at the index visit. All covariates were determined at the time of the index treatment, and no follow-up information was used to define baseline variables.
Follow-up and outcome assessment
Routine outpatient follow-up was performed by the treating dentists at approximately 6 and 12 months after treatment as part of standard clinical care. The observation period for this study was 12 months after the index treatment. For affected teeth without evidence of lesion progression during the observation period, the follow-up visit closest to 12 months within a prespecified window of 10–14 months was designated as the endpoint visit. For affected teeth that underwent operative restoration because of progression of carious lesions on the same occlusal surface within 12 months, the first visit documenting lesion progression was used as the time point for outcome ascertainment. Affected teeth without a recorded outcome within 12 months and without a qualifying 10–14-month follow-up visit were classified as lost to follow-up. The 6-month visit was primarily conducted as a routine clinical review. Findings from this visit informed subsequent clinical management and were used to ascertain outcomes if lesion progression was identified; otherwise, the primary outcome was determined using the follow-up visit closest to 12 months.
The primary outcome was lesion progression within 12 months. Lesion progression was defined as the occurrence of any of the following events during the observation period: (1) development of a definite cavity or localized enamel breakdown at the margin of the sealant or on the corresponding occlusal surface beneath the sealant, with the lesion confirmed as carious in the clinical record; (2) appearance of a new radiolucency extending beyond the enamel into dentin on a digital bitewing radiograph of the index occlusal surface, categorized for study purposes as D1, D2, or D3; or (3) placement of an operative restoration on the occlusal surface because of progression of the carious lesion.
Partial or complete loss of the sealant in the absence of any of the above findings was not considered lesion progression. Similarly, restorations placed because of trauma, occlusal interference, or non-carious material fracture were not classified as outcome events.
Data extraction and quality control
Data extraction was performed using a prespecified data dictionary and standardized extraction forms. Two investigators (X.Q. and Z.Z.) independently extracted data from the electronic medical record system, treatment record system, billing code system, digital imaging archive, and intraoral photography system. The study database was established using double data entry, and any discrepancies were resolved by reviewing the original source records.
Treatment assignment had to be confirmed by both the treatment records and the corresponding billing codes. When discrepancies were identified between these sources, the procedure records and intraoperative photographs were reviewed. Cases for which the treatment assignment could not be confirmed after review were excluded.
Before assessment, all image files were de-identified, relabeled using study identification numbers, and separated from treatment records and billing information. Initial interpretation of the images was performed without access to patient identifiers or documented treatment allocation. When review of the clinical records was required for outcome adjudication, these records were accessed only after completion of the initial image interpretation.
Two uniformly trained dentists (X.Q. and Z.Z.) independently assessed the baseline ICDAS classification, study-specific radiographic appearance category, and follow-up outcomes. Both assessors had also served as treating dentists within the clinical cohort. Therefore, although treatment information was documented, complete masking of treatment allocation could not be guaranteed during the initial image review.
Before formal image interpretation, assessor calibration was performed using 50 non-study cases. Formal assessment commenced only after the weighted κ coefficients reached 0.80 for both ICDAS classification and the study-specific radiographic appearance category. In the calibration dataset, the final weighted κ coefficients were 0.84 for ICDAS classification and 0.88 for the study-specific radiographic appearance category.
When disagreements occurred during formal assessment, the two assessors first performed a joint reassessment. If consensus could not be reached, the case was adjudicated by a third senior dentist (J.L.), who had not participated in the initial paired assessment. Third-review adjudication was required for 58 of 1,117 baseline assessments (5.19%) and 46 of 989 follow-up outcome assessments (4.65%).
Cases with missing data on the primary exposure or primary outcome were excluded from the analysis. Missing data were limited to the total dmft+DMFT score and the visible plaque index and were handled using multiple imputation by chained equations with 20 imputations. The imputation model included treatment group, 12-month lesion progression, age, sex, total dmft+DMFT score, visible plaque index, dental arch, molar type, eruption status, baseline ICDAS classification, baseline study-specific radiographic appearance category, operator, and isolation method.
Statistical analysis
No a priori sample size calculation was performed. Instead, all consecutive eligible cases identified during the study period were included in the analysis. The affected tooth was used as the unit of analysis, and all statistical models accounted for clustering at the patient level to adjust for the correlation among multiple affected teeth within the same individual.
Continuous variables were first assessed for their distribution. Normally distributed variables are presented as the mean ± standard deviation, whereas non-normally distributed variables are presented as the median and interquartile range. Categorical variables are presented as counts and percentages. Baseline covariate balance was assessed using standardized mean differences (SMDs), with an absolute SMD <0.10 indicating adequate balance. Baseline hypothesis testing was not used to determine covariate inclusion in the regression models.
The prespecified null hypothesis was that the 12-month risk of lesion progression would not differ between the two treatment groups, corresponding to a relative risk (RR) of 1.00. The primary analysis first estimated the cumulative incidence and crude RR of 12-month lesion progression in the two groups, together with 95% confidence intervals (CIs). Unadjusted analyses were performed using modified Poisson regression with generalized estimating equations (GEEs), including treatment group as the only independent variable. The adjusted analysis used the same modeling framework and additionally included age, sex, total dmft+DMFT score, visible plaque index, molar type, dental arch, eruption status, baseline ICDAS classification, baseline study-specific radiographic appearance category, operator, and isolation method. Robust variance estimation with an exchangeable working correlation structure was used, and adjusted RRs with corresponding 95% CIs were reported. Covariates were selected a priori on the basis of clinical relevance and temporal sequence rather than univariable p values.
No imputation was performed for the primary exposure or the primary outcome. Missing covariate data were handled using multiple imputation by chained equations, generating 20 imputed datasets, and estimates were pooled according to Rubin's rules. Four prespecified sensitivity analyses were conducted to assess the robustness of the primary findings. First, the primary analysis was repeated using complete-case analysis. Second, the primary analysis was repeated using inverse probability of treatment weighting (IPTW) based on propensity scores. The propensity score model included the same baseline covariates as the primary adjusted analysis, and covariate balance after weighting was reassessed using standardized mean differences. Third, the analysis was repeated after restricting the study population to teeth with baseline ICDAS code 2 lesions only. Fourth, the analysis was repeated after excluding partially erupted molars.
All statistical tests were two-sided, and p < 0.05 was considered statistically significant. Statistical analyses were performed using R software, version 4.4.2.
Results
Study population screening and baseline characteristics
During the study period, 1,278 patients were screened, and 1,694 candidate affected-tooth records were identified. After exclusion of 577 teeth, 1,117 affected teeth from 842 patients were included in the baseline cohort. A total of 989 affected teeth had an evaluable primary outcome at 12 months: 330 teeth in the combined treatment group (292 patients) and 659 teeth in the sealing-alone group (593 patients).
As described in the Protocol, the two treatment strategies were selected as part of routine clinical care rather than assigned according to a prespecified allocation ratio. Flowable resin composite pit-and-fissure sealing alone was used more frequently during the study period, resulting in an approximate 1:2 group distribution. The specific reasons for treatment selection were not systematically recorded as an independent variable. However, the observed baseline differences in lesion characteristics, operator distribution, and isolation method suggest that both clinical and procedural factors may have influenced treatment selection.
Because the affected tooth was the unit of analysis, individual patients could contribute more than one tooth and could also contribute teeth to both treatment groups. Consequently, the number of patients in the two groups cannot be summed directly (Figure 1).
Baseline covariate balance was assessed using the absolute standardized mean difference (SMD), with an absolute SMD < 0.10 indicating adequate balance. Imbalance was observed for age, total dmft+DMFT score, visible plaque index, the proportion of second molars, eruption status, baseline ICDAS classification, the study-specific radiographic appearance categories E0 and E2, operator distribution, and isolation method. In contrast, sex, dental arch, study-specific radiographic appearance category E1, and the distribution of operator 2 were relatively well balanced between the treatment groups (Table 1).
Twelve-month follow-up completion and lesion progression outcomes
Among the affected teeth with an evaluable primary outcome at 12 months, lesion progression occurred in 23 of 330 teeth (6.97%) in the combined treatment group and in 86 of 659 teeth (13.05%) in the sealing-alone group. Accordingly, 307 of 330 teeth (93.03%) and 573 of 659 teeth (86.95%), respectively, showed no evidence of lesion progression.
Among the components of lesion progression, newly detected radiolucency extending into dentin was the most frequent event, followed by operative restoration performed because of the progression of caries on the same occlusal surface (Table 2).
Primary analysis of the 12-month risk of lesion progression between the two treatment strategies
Modified Poisson regression with generalized estimating equations demonstrated that the combined treatment strategy was associated with a lower 12-month risk of lesion progression than flowable resin composite pit-and-fissure sealing alone. The crude relative risk (RR) was 0.53 (95% CI, 0.34–0.84; p = 0.006). After adjustment for the prespecified confounders, the association remained statistically significant, with an adjusted RR of 0.52 (95% CI, 0.33–0.82; p = 0.005).
Because the adjusted 95% confidence interval excluded 1.00 and the corresponding p value was <0.05, the prespecified null hypothesis that there would be no difference in the 12-month risk of lesion progression between the two treatment groups was rejected (Table 3).
Sensitivity analyses and robustness of the results
Before inverse probability of treatment weighting (IPTW), several baseline covariates demonstrated meaningful imbalance, particularly isolation method, operator 1, study-specific radiographic appearance category E2, age, and baseline ICDAS code 2. After IPTW, all absolute SMD values were <0.10, meeting the prespecified criterion for adequate covariate balance (Figure 2).
The distribution of stabilized weights was relatively concentrated, with no evidence of extreme weights (median, 0.98; interquartile range, 0.86–1.17; range, 0.57–2.46). The estimated effective sample sizes after weighting were 308.6 affected teeth in the combined treatment group and 606.8 affected teeth in the sealing-alone group, for a total of 915.4 affected teeth.
All prespecified sensitivity analyses produced results consistent with those of the primary analysis. In the complete-case analysis, IPTW analysis, analysis restricted to baseline ICDAS code 2 lesions, and analysis excluding partially erupted molars, the combined treatment remained associated with a lower 12-month risk of lesion progression. Across these analyses, the estimated RRs ranged from 0.49 to 0.56, with corresponding p values ranging from 0.006 to 0.022 (Table 4).
DATA AVAILABILITY:
The de-identified dataset underlying the findings of this study, together with the associated data documentation, is publicly available in Figshare: https://doi.org/10.6084/m9.figshare.33061760.
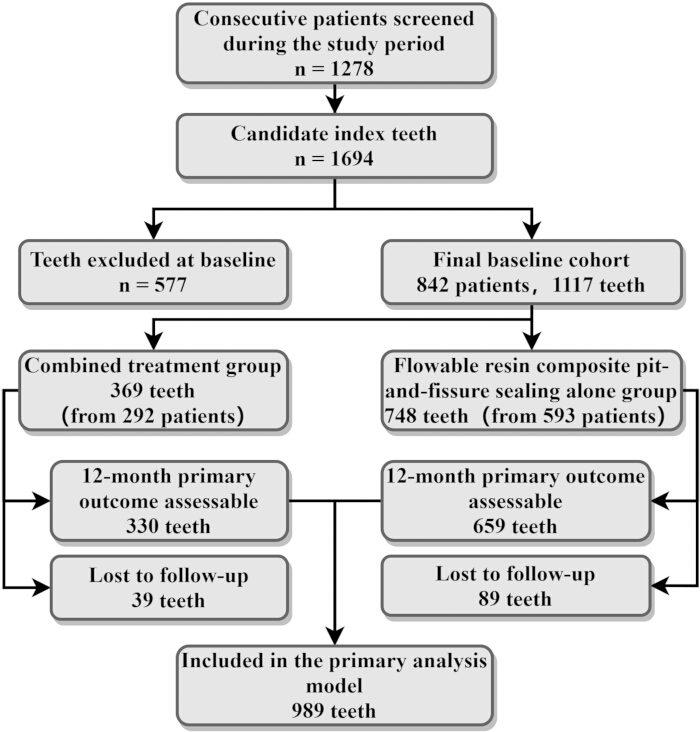
Figure 1: Flowchart of study population screening and inclusion. Treatment was selected during routine clinical care without a prespecified allocation ratio; therefore, sealing alone was used more frequently than the combined treatment during the study period. The same patient could contribute multiple affected teeth and could also contribute affected teeth to both treatment groups; therefore, patient numbers across groups cannot be directly summed. The primary analysis included only affected teeth with an evaluable primary outcome at 12 months. Please click here to view a larger version of this figure.
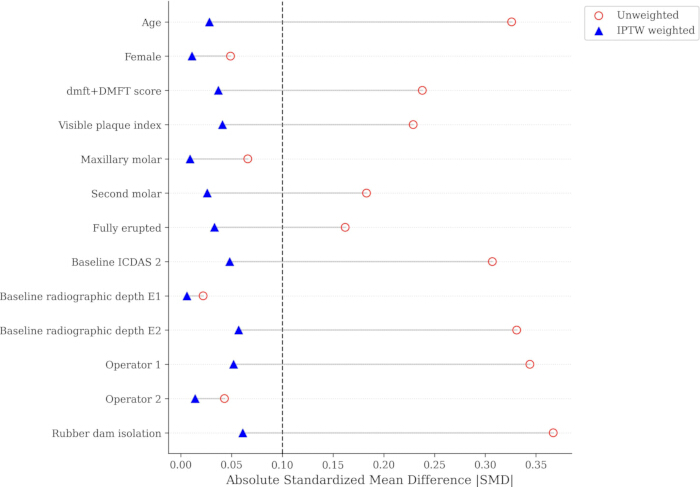
Figure 2: Covariate balance before and after inverse probability of treatment weighting based on propensity scores. Each point represents the absolute standardized mean difference for 1 baseline covariate or 1 dummy variable level of a multicategory variable. The dashed line indicates the prespecified balance threshold of an absolute standardized mean difference of 0.10. Multicategory variables entered the balance plot as k−1 dummy variables; the omitted reference levels in this plot were baseline study-specific radiographic appearance category E0 and operator 3. This plot was generated based on 989 affected teeth with an evaluable primary outcome at 12 months. Covariate balance diagnostics for inverse probability of treatment weighting were performed after handling missing covariates using 20-fold multiple imputation, consistent with the primary analysis. Please click here to view a larger version of this figure.
| Variable | Overall (n = 1117) | Combined treatment group (n = 369) | Sealing-alone group (n = 748) | |SMD| |
| Contributing patients, n | 842 | 292 | 593 | — |
| Age, years | 12.71 ± 2.31 | 13.21 ± 2.24 | 12.46 ± 2.31 | 0.33 |
| Female | 536(47.99%) | 184(49.86%) | 352(47.06%) | 0.056 |
| Total dmft+DMFT score | 3 [1, 5] | 4 [2, 6] | 3 [1, 5] | 0.247 |
| Visible plaque index, % | 24.32 [15.57, 35.86] | 27.18 [18.36, 39.14] | 22.91 [14.69, 34.08] | 0.241 |
| Maxillary molars | 522(46.73%) | 181(49.05%) | 341(45.59%) | 0.069 |
| Second molars | 294(26.32%) | 118(31.98%) | 176(23.53%) | 0.19 |
| Complete eruption | 859(76.90%) | 301(81.57%) | 558(74.60%) | 0.169 |
| Baseline ICDAS 2 | 579(51.84%) | 230(62.33%) | 349(46.66%) | 0.319 |
| Baseline radiographic depth E0 | 492(44.05%) | 132(35.77%) | 360(48.13%) | 0.252 |
| Baseline radiographic depth E1 | 418(37.42%) | 135(36.59%) | 283(37.83%) | 0.026 |
| Baseline radiographic depth E2 | 207(18.53%) | 102(27.64%) | 105(14.04%) | 0.34 |
| Operator 1 | 372(33.30%) | 164(44.44%) | 208(27.81%) | 0.352 |
| Operator 2 | 383(34.29%) | 121(32.79%) | 262(35.03%) | 0.047 |
| Operator 3 | 362(32.41%) | 84(22.76%) | 278(37.17%) | 0.318 |
| Rubber dam isolation | 689(61.68%) | 271(73.44%) | 418(55.88%) | 0.374 |
Table 1: Comparison of baseline characteristics of patients and affected teeth between the 2 treatment groups. Except for “Contributing patients”, all other baseline characteristics were summarized at the affected-tooth level; patient-level variables were assigned to each included affected tooth. The sum of patient numbers in the 2 groups may exceed the total number of patients because the same patient could contribute affected teeth to both treatment groups. Age is presented as mean ± standard deviation, total dmft+DMFT score and visible plaque index are presented as median [interquartile range], and the remaining variables are presented as n (%). An absolute standardized mean difference less than 0.10 was considered indicative of good baseline balance. In the baseline cohort, missingness was observed only for the total dmft+DMFT score (30/1117, 2.69%) and the visible plaque index (26/1117, 2.33%); all other baseline covariates were complete. Abbreviations: SMD = standardized mean difference; dmft+DMFT = decayed, missing, and filled teeth score; ICDAS = International Caries Detection and Assessment System.
| Item | Overall (n = 989) | Combined treatment group (n = 330) | Sealing-alone group (n = 659) |
| Primary outcome | |||
| Lesion progression within 12 months | 109(11.02%) | 23(6.97%) | 86(13.05%) |
| No lesion progression within 12 months | 880(88.98%) | 307(93.03%) | 573(86.95%) |
| Components of progression events | |||
| Definite cavity or localized enamel breakdown, clinically confirmed as a carious lesion | 42 | 8 | 34 |
| New dentin radiolucency | 79 | 16 | 63 |
| Of which, D1 | 46 | 10 | 36 |
| Of which, D2 | 22 | 4 | 18 |
| Of which, D3 | 11 | 2 | 9 |
| Operative filling because of progression of carious lesions on the same occlusal surface | 58 | 11 | 47 |
Table 2: Twelve-month follow-up completion and lesion progression outcomes in the 2 treatment groups. The denominators for the percentages of “Lesion progression within 12 months” and “No lesion progression within 12 months” were the numbers of affected teeth with an evaluable primary outcome at 12 months in each column. For the components of progression events, only case numbers are reported, and the component events were not mutually exclusive; the same affected tooth could meet multiple progression criteria. A newly detected radiolucency extending into the dentin is reported using the study-specific ordinal categories D1, D2, and D3.
| Measure | Combined treatment group vs sealing-alone group (reference group) |
| Crude RR | 0.53 |
| 95% CI | 0.34–0.84 |
| P | 0.006 |
| Adjusted RR | 0.52 |
| 95% CI | 0.33–0.82 |
| P | 0.005 |
Table 3: Modified Poisson regression with generalized estimating equations of the association between the 2 treatment strategies and the 12-month risk of lesion progression. The reference group was the flowable resin composite pit-and-fissure sealing-alone group. Both the crude and adjusted models used modified Poisson regression with generalized estimating equations, robust variance estimation, an exchangeable correlation structure, and patient-level clustering. The adjusted model included age, sex, total dmft+DMFT score, visible plaque index, maxillary or mandibular arch, molar type, eruption status, baseline ICDAS classification, baseline study-specific radiographic appearance category, operator, and isolation method. Missing covariates were handled using 20-fold multiple imputation; no imputation was performed for missing main exposure or primary outcome data. p-values were obtained using the Wald test. Abbreviations: RR = relative risk; CI = confidence interval; ICDAS = International Caries Detection and Assessment System.
| Sensitivity analysis scheme | Included affected teeth, n | Progression events, n | RR(95% CI) | P |
| Complete-case analysis | 947 | 105 | 0.51(0.32–0.83) | 0.006 |
| Analysis based on inverse probability weighting using propensity scores | 989 | 109 | 0.54(0.34–0.85) | 0.008 |
| Analysis including only baseline ICDAS 2 lesions | 517 | 69 | 0.49(0.29–0.84) | 0.009 |
| Analysis after excluding partially erupted molars | 781 | 76 | 0.56(0.34–0.92) | 0.022 |
Table 4: Sensitivity analysis results for the primary outcome. All relative risks represent the risk of 12-month lesion progression in the combined treatment group compared with the sealing-alone group. The complete-case analysis, the restricted analysis of baseline ICDAS 2 lesions, and the analysis after excluding partially erupted molars all used modified Poisson regression with generalized estimating equations, robust variance estimation, an exchangeable correlation structure, and clustering by patient, consistent with the primary analysis. In the restricted analyses, restriction variables with no variation in the corresponding subsample were not included. The inverse probability weighting analysis used weights constructed from propensity scores based on logistic regression and used weighted modified Poisson regression with generalized estimating equations to estimate the relative risk. All p-values were obtained using the Wald test. Abbreviations: RR = relative risk; CI = confidence interval; ICDAS = International Caries Detection and Assessment System.
Discussion
Resin infiltration combined with flowable resin composite pit-and-fissure sealing was associated with a significantly lower 12-month risk of lesion progression than sealing alone. The adjusted relative risk was 0.52, with the 95% confidence interval excluding 1.00 and a corresponding p value of 0.005; therefore, the prespecified null hypothesis of no difference between the two treatment groups was rejected. Because treatment was not randomly allocated, these findings should be interpreted as an adjusted association rather than definitive evidence of causality. For non-cavitated initial occlusal pit-and-fissure carious lesions, treatment aims to stabilize subsurface demineralization beneath a clinically pseudointact enamel surface17. Flowable resin composite sealing primarily provides an external barrier that limits plaque accumulation and substrate diffusion, whereas resin infiltration may also penetrate the porous lesion body, reduce lesion permeability, and provide internal sealing18. The combined approach, therefore, integrates internal lesion stabilization with external surface isolation, providing a biologically plausible explanation for the lower risk of progression observed in this study19.
Laboratory and clinical evidence support this treatment concept. Resin infiltrants demonstrate greater penetration, reduced microleakage, and improved bonding compared with conventional fissure sealants in demineralized pits and fissures20,21, while ex vivo studies indicate that infiltrants are compatible with adhesive resin procedures without adversely affecting hybrid-layer formation22. Meyer-Lueckel et al. further showed that effective erosion of the surface layer enhances resin penetration, highlighting the importance of appropriate lesion pretreatment8. Previous clinical studies also provide important context. Bakhshandeh and Ekstrand reported that infiltration and sealing effectively arrested initial occlusal lesions in primary molars, with infiltration combined with fluoride varnish producing less radiographic progression than fluoride varnish alone10. Similarly, Anauate-Netto et al. observed low three-year progression rates following resin infiltration and conventional fissure sealing in permanent teeth11, and a subsequent 24-month trial demonstrated favorable outcomes with resin infiltration combined with a nanoparticle-resin-based sealant12. Rather than introducing a new treatment concept, the present study extends prior evidence by evaluating this combined approach in a larger real-world cohort and directly comparing it with flowable resin composite sealing alone.
Most progression events in the present study were identified as new dentin radiolucencies rather than clinically visible cavitation, indicating that failure generally reflected progression of subsurface disease before obvious surface breakdown. This pattern is consistent with the natural history of non-cavitated occlusal caries, in which the enamel surface often remains clinically intact despite ongoing subsurface demineralization23. Resin infiltration may occlude porous pathways within the lesion before placement of the external seal, thereby complementing the protective effect of the surface seal24,25,26. Although the combined treatment group contained higher proportions of ICDAS 2 and E2 lesions, it still demonstrated a lower adjusted risk of progression, suggesting that the observed association was unlikely to be explained solely by preferential selection of lower-risk lesions. Radiographic assessment of dentin involvement was therefore clinically meaningful, although the inherent limitations of bitewing radiography for early occlusal lesions should be recognized27.
The observational design introduces potential sources of bias. Treatment reflected routine clinical decision-making rather than random allocation, and the specific reasons for selecting one treatment strategy over another were not systematically documented. Consequently, confounding by indication cannot be excluded. Nevertheless, adjustment for prespecified confounders, generalized estimating equations, multiple imputation, inverse probability of treatment weighting, and four sensitivity analyses all produced consistent estimates, supporting the internal consistency of the findings28. The study also benefits from several strengths, including a large consecutive real-world cohort, standardized clinical protocols, outcome assessment using clinical records, intraoral photographs, and bitewing radiographs, independent, calibrated assessment by two examiners, and correction for clustering of multiple teeth within individual patients. These characteristics complement, rather than replace, the stronger causal inference provided by randomized clinical trials.
Several limitations should also be considered. The observation period was limited to 12 months, precluding assessment of long-term lesion stability, sealant durability, and reintervention. The study was conducted at a single center and included only permanent first and second molars from patients aged 6–18 years, which limits generalizability to other populations, tooth types, or restorative materials. In addition, the combined protocol used fluoride-free prophylaxis prior to hydrochloric acid conditioning but did not include sodium hypochlorite deproteinization. Experimental and ex vivo studies suggest that sodium hypochlorite may enhance the removal of residual organic material, increase resin penetration, improve initial fissure sealing, and strengthen the bond between infiltrated enamel and resin composite29,30,31. However, these findings remain largely laboratory-based, and their clinical relevance requires prospective evaluation. Although imaging was standardized and image interpretation was performed independently using de-identified records, complete masking of treatment allocation could not be guaranteed because the assessors had also participated in patient treatment.
In conclusion, resin infiltration combined with flowable resin composite pit-and-fissure sealing was associated with better short-term control of non-cavitated occlusal pit-and-fissure carious lesions than sealing alone in this retrospective cohort. The approximately 6-percentage-point absolute reduction in lesion progression corresponds to roughly one fewer progression event per 17 treated teeth over 12 months, suggesting that the combined protocol may be a useful microinvasive treatment option when adequate isolation and standardized operative procedures can be achieved. Continued clinical and radiographic follow-up remains essential, and future prospective studies should determine the long-term durability of this approach, identify the lesions most likely to benefit, and evaluate whether optimized pretreatment strategies, including sodium hypochlorite deproteinization, further improve clinical outcomes.
Disclosures
The authors declare that they have no competing interests related to this study. No financial or non-financial conflicts exist, including employment, consultancies, stock ownership, honoraria, or paid expert testimony.
Acknowledgements
Not applicable. This study received no specific funding.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 37% phosphoric acid etchant (Total Etch) | Ivoclar Vivadent AG, Schaan, Liechtenstein | 550588AN | 37% phosphoric acid etching gel used for enamel etching before pit-and-fissure sealing. |
| Ball-ended probe / WHO probe (Qulix CP-11.5B Probe) | HuFriedyGroup, Chicago, IL, USA | PCP11.5B6 | Single-ended, color-coded WHO CP-11.5B ball-ended probe used to remove debris and confirm surface continuity without sharp probing. |
| Digital bitewing imaging system (RVG 6200 Intraoral Sensor, Size 2) | Carestream Dental LLC, Atlanta, GA, USA | 1065804 | Size 2 CMOS intraoral digital X-ray sensor used for posterior bitewing radiography. |
| Flowable resin composite (Filtek Supreme Flowable Restorative, shade A2) | 3M Oral Care / Solventum, St. Paul, MN, USA | 6032A2 | Light-curing flowable resin composite used for pit-and-fissure sealing after adhesive application. |
| Fluoride-free prophylaxis paste (Cleanic in Tube without Fluoride, Mint, 100 g) | Kerr Corporation / Envista, Orange, CA, USA | 3183 | Fluoride-free prophylaxis paste used for tooth-surface cleaning before examination and treatment. |
| Intraoral photography system (EyeSpecial C-V Dental Camera) | SHOFU Dental GmbH, Ratingen, Germany | E0027 | Dental camera system used for standardized intraoral photography and retrospective outcome review. |
| LED light-curing unit (Woodpecker iLED Plus) | Guilin Woodpecker Medical Instrument Co., Ltd., Guilin, Guangxi, China | iLED Plus | Dental LED curing light with an output intensity of 1,000–2,500 mW/cm². |
| R statistical software and packages | R Foundation for Statistical Computing, Vienna, Austria; Comprehensive R Archive Network | R 4.4.2; geepack 1.3.12; mice 3.17.0; WeightIt 1.4.0; cobalt 4.5.5; tableone 0.13.2 | Used for modified Poisson generalized estimating equations, cluster-robust variance estimation, multiple imputation, propensity-score inverse probability of treatment weighting, covariate-balance diagnostics, standardized mean differences, and baseline table generation. |
| Resin infiltration system (Icon; Icon Etch, Icon Dry, and Icon Infiltrant) | DMG Chemisch-Pharmazeutische Fabrik GmbH, Hamburg, Germany | Kit catalog number: 220403 (confirm against product packaging) | System comprising 15% hydrochloric acid etching gel, 99% ethanol drying agent, and low-viscosity light-curing resin infiltrant used for enamel lesion infiltration. |
| Rubber dam system (Hygenic Dental Dam Starter Kit with Winged Clamps) | COLTENE / Hygenic, Cuyahoga Falls, OH, USA | H02778 | Dental dam isolation kit used when tooth position and eruption status permitted stable clamp placement and complete field control. |
| Universal adhesive (Scotchbond Universal Adhesive) | 3M Oral Care / Solventum, St. Paul, MN, USA | 41258 | Light-curing universal dental adhesive used before placement of the flowable resin composite. |
References
- World Health Organization. Oral health [Internet]. 2025 Mar 17. Available at: https://www.who.int/news-room/fact-sheets/detail/oral-health
- Martignon S, et al. CariesCare practice guide: Consensus on evidence into practice. Br Dent J. 2019;227(5):353-362.
- Pitts NB, et al. ICCMS guide for practitioners and educators [Internet]. London: ICDAS Foundation; 2014. Available at: https://www.iccms-web.com/uploads/asset/59284654c0a6f822230100.pdf
- Wright JT, et al. Evidence-based clinical practice guideline for the use of pit-and-fissure sealants: A report of the American Dental Association and the American Academy of Pediatric Dentistry. J Am Dent Assoc. 2016;147(8):672-682.e12.
- Ozan G, et al. Comparative evaluation of a fissure sealant and a flowable composite: A 36-month split-mouth randomized clinical study. J Dent. 2022;123:104205.
- Paris S, et al. Comparison of sealant and infiltrant penetration into pit and fissure caries lesions in vitro. J Dent. 2014;42(4):432-438.
- Kielbassa AM, Muller J, Gernhardt CR. Closing the gap between oral hygiene and minimally invasive dentistry: A review on the resin infiltration technique of incipient (proximal) enamel lesions. Quintessence Int. 2009;40(8):663-681.
- Meyer-Lueckel H, Moser C, Wierichs RJ, Lausch J. Improved surface layer erosion of pit and fissure caries lesions in preparation for resin infiltration. Caries Res. 2022;56(5-6):496-502.
- Slayton RL, et al. Evidence-based clinical practice guideline on nonrestorative treatments for carious lesions: A report from the American Dental Association. J Am Dent Assoc. 2018;149(10):837-849.e19.
- Bakhshandeh A, Ekstrand K. Infiltration and sealing versus fluoride treatment of occlusal caries lesions in primary molar teeth: 2-3 years results. Int J Paediatr Dent. 2015;25(1):43-50.
- Anauate-Netto C, et al. Caries progression in non-cavitated fissures after infiltrant application: A 3-year follow-up of a randomized controlled clinical trial. J Appl Oral Sci. 2017;25(4):442-454.
- Elkwatehy WMA, Bukhari OM. The efficacy of different sealant modalities for prevention of pits and fissures caries: A randomized clinical trial. J Int Soc Prev Community Dent. 2019;9(2):119-128.
- Miranda SB, et al. Efficacy of resin infiltrants in non-cavitated occlusal carious lesions: A systematic review. J Clin Med. 2026;15(3):1310.
- von Elm E, et al. The Strengthening the Reporting of Observational Studies in Epidemiology (STROBE) statement: Guidelines for reporting observational studies. Ann Intern Med. 2007;147(8):573-577.
- International Caries Detection and Assessment System Coordinating Committee. Criteria manual: International Caries Detection and Assessment System II [Internet]. Revised 2008 Dec and 2009 Jul. Available at: https://www.iccms-web.com/uploads/asset/5ccb149905404942610729.pdf
- Anusavice KJ. Present and future approaches for the control of caries. J Dent Educ. 2005;69(5):538-554.
- Sadıkoğlu İS. White spot lesions: Recent detection and treatment methods. Cyprus J Med Sci. 2020;5(3):260-266.
- Chen Y, Chen D, Lin H. Infiltration and sealing for managing non-cavitated proximal lesions: A systematic review and meta-analysis. BMC Oral Health. 2021;21(1):13.
- Silva VB, et al. Sealing carious fissures with resin infiltrant in association with a flowable composite reduces immediate microleakage? Pesqui Bras Odontopediatria Clin Integr. 2020;20:e5114.
- Al Tuwirqi AA, Alshammari AM, Felemban OM, Ali Farsi NM. Comparison of penetration depth and microleakage of resin infiltrant and conventional sealant in pits and fissures of permanent teeth in vitro. J Contemp Dent Pract. 2019;20(11):1339-1344.
- Zhou Y, et al. Microleakage, microgap, and shear bond strength of an infiltrant for pit and fissure sealing. Heliyon. 2023;9(5):e16248.
- Kielbassa AM, Summer S, Frank W, Lynch E. Equivalence study of the resin-dentine interface of internal tunnel restorations when using an enamel infiltrant resin with ethanol-wet dentine bonding. Sci Rep. 2024;14:12444.
- Flemming J, Hannig C, Hannig M. Caries management—The role of surface interactions in de- and remineralization processes. J Clin Med. 2022;11(23):7044.
- Lausch J, Askar H, Paris S, Meyer-Lueckel H. Micro-filled resin infiltration of fissure caries lesions in vitro. J Dent. 2017;57:73-76.
- Featherstone JDB. Dental caries: A dynamic disease process. Aust Dent J. 2008;53(3):286-291.
- Weerheijm KL, Kidd EAM, Groen HJ. The effect of fluoridation on the occurrence of hidden caries in clinically sound occlusal surfaces. Caries Res. 1997;31(1):30-34.
- Lussi A, Megert B, Longbottom C, Reich E, Francescut P. Clinical performance of a laser fluorescence device for detection of occlusal caries lesions. Eur J Oral Sci. 2001;109(1):14-19.
- Simoneau G, et al. Recommendations for the use of propensity score methods in multiple sclerosis research. Mult Scler. 2022;28(9):1467-1480.
- Kielbassa AM, et al. Resin infiltration of deproteinised natural occlusal subsurface lesions improves initial quality of fissure sealing. Int J Oral Sci. 2017;9(2):117-124.
- Ulrich IB, Pasztorek M, Frank W, Kielbassa AM. An ex vivo study on the correlation between lesion size and resin infiltration area in natural proximal subsurface carious lesions deproteinized with sodium hypochlorite. J Dent. 2025;160:105858.
- He J, et al. Effect of NaOCl or EDTA pretreatments on the shear bond strength of the resin-infiltrated white spot lesions to the resin composite: An in vitro study. BMC Oral Health. 2025;25:1494.