This study examined the acute effects of neuromuscular electrical stimulation priming on volleyball spike performance and three-dimensional kinematics in male university volleyball players. Compared with the time-matched control group, the NMES conditioning group demonstrated greater ball velocity and phase-specific differences in lower-limb joint angles, segmental velocities, and shoulder–hip separation angle.
Research Article
Acute Effects of Neuromuscular Electrical Stimulation Priming on Volleyball Spike Performance and Three-Dimensional Kinematics
* These authors contributed equally
In This Article
Summary
Abstract
Volleyball spiking is a complex explosive skill that requires coordinated force generation and transfer across the upper limbs, trunk, and lower limbs. Neuromuscular electrical stimulation (NMES) has been proposed as a preconditioning strategy for enhancing neuromuscular activation; however, its acute effects on phase-specific volleyball spike kinematics remain unclear. This study investigated the acute effects of NMES priming on spike performance and three-dimensional kinematics in male university volleyball players. Thirty participants were randomly assigned to an NMES conditioning group (n = 15) or a control group (n = 15). All participants completed a baseline spike assessment and a second assessment 72 h later. Immediately before the second assessment, the NMES group received 30 min of stimulation applied to the upper-limb muscles, including the deltoid, biceps brachii, and triceps brachii; the external oblique as a core muscle; and the vastus lateralis as a lower-limb muscle. The control group completed the same time-matched assessment without NMES. Three-dimensional kinematic data were collected using a synchronized four-camera three-dimensional motion-analysis system. The primary analysis compared performance and kinematic variables between the groups at the second assessment. Compared with the control group, the NMES group demonstrated greater ball velocity, smaller knee and ankle angles at bilateral-foot contact, greater hip, knee, and ankle angles at bilateral take-off, and higher thigh, calf, and foot segmental velocities. The NMES group also showed a smaller shoulder–hip separation angle at bilateral take-off and ball contact. These findings indicate that acute NMES priming applied to upper-limb, core, and lower-limb muscles may influence phase-specific joint configurations, lower-limb segmental velocities, and ball velocity during volleyball spiking. NMES may therefore have potential as a pre-performance neuromuscular activation strategy, although further studies using concealed allocation, blinded assessment, and direct group-by-time analyses are required.
Introduction
Volleyball is a competitive sport that relies heavily on explosive power and coordination, and spiking is one of the most important means of scoring1. This technical movement places high demands on the athlete’s muscle output capacity, movement timing control, and neuromuscular control ability2. A successful spike consists of three key stages: the run-up, take-off, and aerial hitting phases. Effective performance across these stages depends on coordinated force production and efficient energy transfer through the segments of the kinetic chain3. Previous studies have shown that hip-knee-ankle triple extension, trunk stability, and upper limb joint angles and velocity at the moment of hitting the ball are all important factors affecting spiking performance4.
During competition and high-intensity training, athletes often suffer from insufficient neural drive and poor movement pre-activation, which leads to reduced coordination of the kinetic chain and decreased muscle strength, and affects their overall athletic performance5. NMES is a non-invasive neural activation technology that addresses this and has attracted significant attention in sports science in recent years6. Studies have shown that NMES can stimulate target muscle groups via an external electric current, and increase the excitability of spinal motor neurons and the recruitment efficiency of fast muscle fibers, thereby enhancing muscle strength output and motor control performance7,8. Although NMES has been widely used in long-term training strategies, such as rehabilitation and muscle strength enhancement, its single, immediate application in the field of competitive sports has not been fully tested9. Although sports like volleyball are highly dependent on accurate timing and integrated movements, investigations of empirical research into the impact of NMES on the three stages of spiking (run-up, take-off, and aerial hitting) based on kinematic indicators are rare10. The volleyball spike jump is characterized by a rapid stretch–shortening cycle. During the final approach and bilateral-foot contact, the lower-limb muscles undergo eccentric loading as the hip, knee, and ankle joints flex. This is followed immediately by rapid concentric action and coordinated triple extension during take-off. The effective transition between these eccentric and concentric actions contributes to the production of vertical impulse and take-off performance during spiking.
Previous NMES research in sport has largely focused on rehabilitation, isolated muscle strengthening, or general neuromuscular performance, whereas its immediate application to complex sport-specific skills remains less clearly understood. In addition, existing volleyball biomechanical studies have primarily characterized spike technique, joint motion, or arm-swing patterns without directly examining the acute effects of multiregional NMES conditioning. Therefore, the present study investigated whether a single NMES session applied to upper-limb, core, and lower-limb muscles was associated with differences in volleyball spike performance and phase-specific three-dimensional kinematics. The methodological contribution of this study lies in the synchronized analysis of body-segment motion and ball velocity across the run-up, bilateral-foot contact, take-off, and aerial ball-contact events within a randomized, time-matched controlled design. This approach extends conventional volleyball kinematic analysis by linking an acute neuromuscular conditioning intervention with movement characteristics across the complete spike sequence.
Protocol
Participants and eligibility criteria
The study protocol was approved by the Academic Ethics Committee of Jimei University (Approval No. JD02RS02406) and was conducted in accordance with the Declaration of Helsinki. Before enrollment, all participants received a detailed explanation of the study purpose, experimental procedures, potential risks, and their right to withdraw from the study at any time without penalty. Written informed consent was obtained from all participants before any study-related procedures were performed. Thirty healthy male university students with volleyball training experience were recruited from elective volleyball courses at a normal university through course announcements. Potential participants completed a health- and injury-history questionnaire before enrollment. Participants were eligible if they: (1) were male university students; (2) had completed formal volleyball training; (3) demonstrated stable proficiency in the volleyball spike technique; (4) had previous competitive or organized volleyball experience; and (5) were able to complete the testing procedures safely. Participants were excluded if they had current musculoskeletal pain or injury that could affect spike performance, a history of recent surgery involving the upper limbs, lower limbs, or trunk, a neurological or cardiovascular disorder, or any contraindication to NMES. The participants’ mean age, height, and body mass were 20.2 ± 1.15 years, 182.1 ± 3.17 cm, and 70.6 ± 8.34 kg, respectively. Details of the equipment and materials used in this study, including manufacturers and model or catalog numbers, are provided in the Table of Materials.
Randomization, allocation concealment, and blinding
After completion of the baseline assessment, eligible participants were randomly assigned in a 1:1 ratio to either the NMES conditioning group or the control group using a simple drawing-of-lots procedure. Thirty identical folded cards, 15 labeled “NMES” and 15 labeled “Control,” were placed in an opaque container and drawn individually by the participants. No formal allocation-concealment procedure was used because the group labels became visible immediately after each card was drawn. Because the NMES intervention was readily identifiable, participants and the personnel administering the intervention could not be blinded to group assignment. The assessors responsible for motion capture, marker tracking, and outcome assessment were also not blinded to the intervention condition. The absence of allocation concealment and assessor blinding was acknowledged as a methodological limitation. Participants were assigned to the NMES conditioning group (n = 15) or the control group (n = 15). Independent-samples t-tests showed no significant between-group differences in age, height, body mass, or body mass index at baseline (all p > 0.05).
Experimental design
This study used a randomized, parallel-group, two-assessment controlled design. All participants completed a baseline spike assessment and a second assessment 72 h later. During the 72 h interval, participants were instructed to avoid organized training, strenuous exercise, and other high-intensity physical activity. Immediately before the second assessment, participants in the NMES conditioning group received a 30 min NMES intervention. Participants in the control group received no NMES intervention and completed the same time-matched second assessment. The values reported in Table 1 were obtained during the second assessment. Therefore, the NMES-group values represent measurements obtained immediately after NMES, whereas the control-group values represent measurements obtained during the second assessment without NMES. Table 1 does not present baseline values or pre–post change scores.
Experimental setting and equipment
Testing was conducted on an indoor volleyball court. The equipment included synchronized LED signal lights, a three-dimensional motion-analysis system, a three-dimensional calibration frame measuring 2.0 m x 1.5 m x 2.0 m (Figure 1A), four high-speed cameras, five frequency-modulated pulse therapy devices (Figure 1B), and standard volleyballs. The four cameras were positioned around the calibrated capture volume near the attacking zone at position 4. Video was recorded at a resolution of 1920 x 1080 pixels, a sampling frequency of 180 Hz, and a shutter speed of 1/1000 s. The global x-axis represented the mediolateral direction, the y-axis represented the direction of the spike approach, and the z-axis represented the vertical direction. Before testing, participants completed a standardized 20 min warm-up consisting of light running, dynamic lower- and upper-limb stretching, paired passing, setting, defensive movements, and submaximal spike practice.
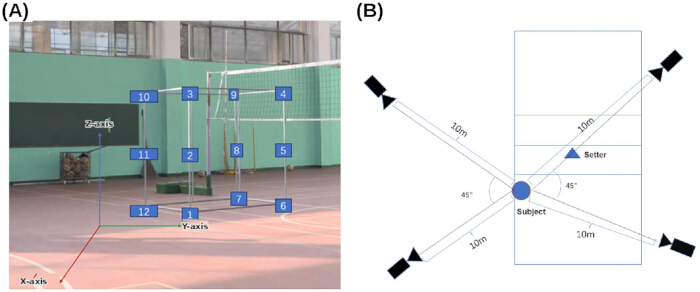
Figure 1: Experimental setup for volleyball spike testing. (A) Three-dimensional calibration frame (2.0 m × 1.5 m × 2.0 m). (B) Four-camera arrangement for three-dimensional motion capture. Please click here to view a larger version of this figure.
Standardization of spike trials
A marked starting position was established 3 m behind the take-off area at position 4. The same experienced setter performed all sets during both assessments and remained at position 3. The setter was instructed to deliver the ball to a consistent height and position above the net so that each participant could use the same approach and spike technique. A 3 m x 3 m target area was marked in the opponent’s court. A valid trial was defined as one in which: (1) the participant began from the marked starting position; (2) the prescribed approach, bilateral take-off, and aerial hitting sequence was completed; (3) the ball was contacted cleanly; (4) the ball landed within the predefined target area; and (5) the anatomical and ball markers remained visible during the relevant analysis period. Each participant completed two familiarization attempts followed by recorded attempts until three valid trials were obtained. A 60 s passive rest interval was provided between attempts.
A trial was considered invalid if the set was unsuitable, the participant altered the prescribed approach, the participant failed to contact the ball cleanly, the ball landed outside the predefined target area, or marker visibility was insufficient. Invalid trials were excluded and repeated until three valid trials had been recorded. Among the three valid trials, the best-performing trial was selected for kinematic and performance analysis. The same trial-selection procedure was applied to both groups and at both assessments.
NMES intervention and stimulated muscle groups
The NMES intervention was administered for 30 min using five frequency-modulated pulse therapy devices. NMES was applied to upper-limb, core, and lower-limb muscles. The stimulated upper-limb muscles were the deltoid, biceps brachii, and triceps brachii. The stimulated core muscle was the external oblique, and the stimulated lower-limb muscle was the vastus lateralis. Self-adhesive electrodes were positioned over the muscle bellies according to anatomical landmarks and the device manufacturer’s instructions. Stimulation intensity was increased gradually until a clearly visible muscle contraction was produced without causing pain or intolerable discomfort. The mean recorded output values were 35.73 W for the deltoid, 35.21 W for the biceps brachii, 34.36 W for the triceps brachii, 33.85 W for the external oblique, and 37.09 W for the vastus lateralis. Immediately after completion of the NMES intervention, participants began the second spike assessment. Participants in the control group completed the same testing procedures without receiving electrical stimulation.
Stimulation parameters
The frequency-modulated pulse therapy device was operated at a fixed pulse frequency of 1000 Hz for all participants. Stimulation intensity was the only participant-specific output parameter and was gradually increased until a clearly visible muscle contraction was produced without pain or intolerable discomfort. The available study records did not contain independent settings for the pulse waveform, pulse width, duty cycle, contraction/rest cycle, or ramp-up/ramp-down times. These parameters could not be retrospectively retrieved; therefore, they are reported as unavailable rather than estimated.
NMES contraindications and safety monitoring
Before enrollment, participants were screened for contraindications to NMES using a health-history questionnaire and verbal confirmation by the research personnel. Participants were excluded if they had an implanted electronic device or cardiac pacemaker, epilepsy, clinically diagnosed cardiovascular disease, impaired skin sensation, open wounds, skin infection or irritation at an electrode site, an acute musculoskeletal injury, or a previous adverse reaction to electrical stimulation. Before electrode placement, the skin over each target muscle was inspected for wounds, irritation, infection, or other abnormalities. During stimulation, participants were continuously monitored and were instructed to report pain, dizziness, excessive muscle cramping, skin irritation, abnormal muscle contractions, or other unexpected symptoms. The stimulation intensity was reduced if excessive discomfort occurred. The intervention was discontinued if a participant experienced intolerable pain, dizziness, persistent skin irritation, abnormal muscle contractions, or another potentially unsafe response. Any adverse response and the action taken by the research personnel were documented.
Motion capture and calibration
Before each testing session, the measurement space was calibrated using a three-dimensional calibration frame measuring 2.0 m x 1.5 m x 2.0 m. All calibration points were visible in at least two camera views. The four cameras were synchronized using an LED signal that was visible in all camera recordings. Three-dimensional coordinates were reconstructed using three-dimensional motion-analysis software and a direct linear transformation procedure. Calibration quality was assessed by comparing the known coordinates of the calibration-frame control points with their reconstructed coordinates. The root-mean-square reconstruction error was 0.138 cm. Calibration was repeated when all required control points were not clearly visible or when the reconstruction error exceeded the laboratory acceptance criterion.
Marker placement and tracking
Twenty-one reflective markers were attached to anatomical landmarks on each participant. The marker locations included the top of the head; left and right ears; left and right acromia; left and right anterior superior iliac spines; left and right radial heads; left and right radial styloid processes; distal phalanges of the third fingers; left and right upper tibiae; left and right lateral malleoli; left and right calcanei; and distal phalanges of the left and right feet. One additional lightweight reflective marker was securely attached to the surface of the volleyball. The marker attachment was checked before every attempt to ensure that it remained fixed during the spike. Markers were digitized manually and tracked frame by frame using three-dimensional motion-analysis software. Automatic trajectories were visually inspected and manually corrected when necessary. Marker gaps of no more than five consecutive frames were reconstructed using cubic-spline interpolation. Trials containing longer gaps or missing marker data at a key event were excluded and repeated.
Event detection and technical phase division
Four key events were identified through frame-by-frame inspection of the synchronized camera recordings: (1) initial left-foot contact, defined as the first frame in which the left foot visibly contacted the floor (Figure 2A); (2) bilateral-foot contact, defined as the first frame in which both feet were simultaneously in contact with the floor (Figure 2B); (3) bilateral take-off, defined as the first frame in which both feet had completely left the floor (Figure 2C); (4) ball contact, defined as the first frame in which the hitting hand visibly contacted and displaced the ball (Figure 2D). The run-up phase extended from initial left-foot contact to bilateral-foot contact. The take-off phase extended from bilateral-foot contact to bilateral take-off. The aerial hitting phase extended from bilateral take-off to ball contact11,12. All events were identified by the same assessor to maintain consistency.
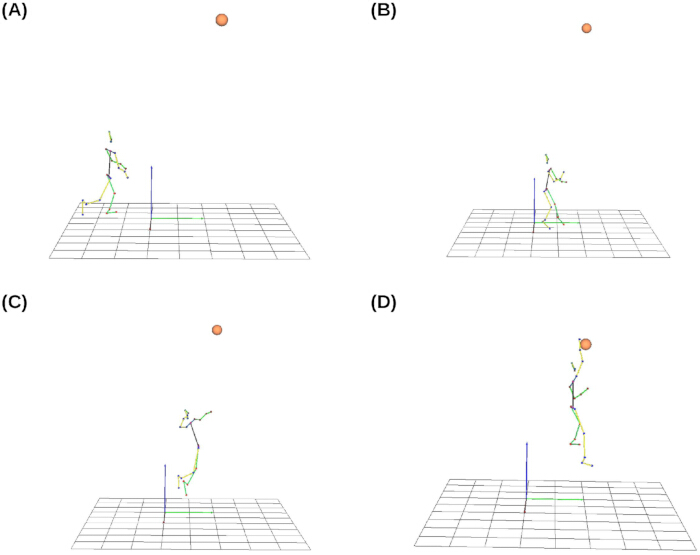
Figure 2: Key events of the volleyball spike. (A) Initial left-foot contact. (B) Bilateral-foot contact. (C) Bilateral take-off. (D) Ball contact. Please click here to view a larger version of this figure.
Data processing
The kinematic parameters of volleyball spiking technique analyzed in this study are: shoulder-hip separation angle (Figure 3A) [the x-axis of the trunk coordinate system is defined as the line connecting the left anterior superior iliac spine to the right anterior superior iliac spine, the y-axis is defined as the forward direction of the anterior superior iliac spine, the z-axis is defined as the line connecting the midpoints of the two anterior superior iliac spines to the midpoints of the two acromion on the longitudinal axis, the angle formed by the local vector of the left anterior superior iliac spine relative to the right anterior superior iliac spine and the local vector of the left acromion relative to the right acromion and rotated relative to the xy plane of the coordinate system]; shoulder joint angle (Figure 3B) [the angle formed by the elbow joint, shoulder joint and hip joint]; elbow joint angle (Figure 3B) [the angle formed by the shoulder joint, elbow joint and wrist joint]; wrist joint angle (Figure 3B) [the angle formed by the elbow joint, wrist joint and finger joint]; hip joint angle (Figure 3C) [the angle formed by the shoulder joint, hip joint and knee joint]; knee joint angle (Figure 3C) [the angle formed by the hip joint, knee joint and ankle joint]; ankle joint angle (Figure 3C) [the angle formed by the knee joint, ankle joint and toes]13,14,15,16,17,18,19. Thigh, calf, and foot segmental velocities were calculated from the three-dimensional displacement of the corresponding segment center between consecutive frames. Linear velocity was obtained using a central-difference numerical differentiation procedure and was expressed in meters per second. Ball velocity was calculated from the resultant three-dimensional displacement of the ball marker divided by the sampling interval of 1/180 s. Peak ball velocity was defined as the highest resultant velocity recorded during the first three frames after hand–ball contact and was expressed in meters per second.
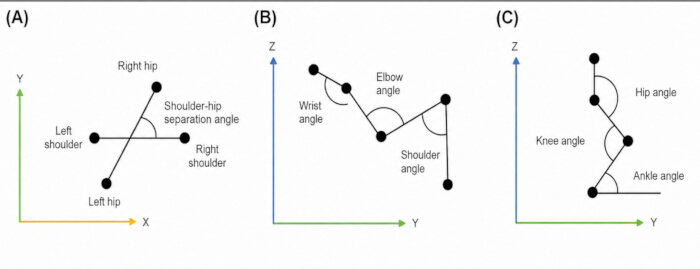
Figure 3: Kinematic parameters of the volleyball spike. (A) Shoulder–hip separation angle. (B) Shoulder, elbow, and wrist joint angles. (C) Hip, knee, and ankle joint angles. Please click here to view a larger version of this figure.
Statistical analysis
Statistical analyses were performed using SPSS. Continuous variables are presented as means and standard deviations. Independent-samples t-tests were used to compare age, height, body mass, and body mass index between the groups at baseline. The primary analysis compared the second-assessment kinematic and performance variables between the NMES conditioning group and the time-matched control group using the Mann–Whitney U test. The standardized Z statistic was reported for Mann–Whitney U comparisons. Effect size was calculated as r = |Z|/√N, where N was the total sample size for each comparison (N = 30); values of 0.10, 0.30, and 0.50 were interpreted as small, moderate, and large effects, respectively. The 95% confidence intervals for the mean difference (NMES − Control) were estimated from the reported means, SDs, and sample sizes using the Welch method. Pearson product–moment correlation coefficients were calculated using the second-assessment data from the NMES conditioning group to examine relationships among the kinematic and performance variables. The 95% confidence intervals for the correlation coefficients were calculated using Fisher’s z transformation. Benjamini–Hochberg false-discovery-rate correction was applied separately within each event family. Each run-up event family comprised three comparisons, whereas the bilateral take-off and ball-contact event families comprised 55 comparisons each. Statistical significance was set at α = 0.05 (Table 2 and Table 3).
Results
Between-group differences in spike performance and kinematic parameters
Table 1 presents the between-group differences in volleyball spike performance and phase-specific kinematic parameters at the second assessment. Each group included 15 participants. During the aerial hitting phase, ball velocity at the moment of ball contact was significantly higher in the NMES conditioning group than in the control group (11.69 ± 2.14 vs. 9.95 ± 1.48 m/s; Z = −2.344, p = 0.019).
At initial left-foot contact during the run-up phase, no significant between-group differences were observed in hip angle (139.31 ± 13.30° vs. 144.30 ± 14.28°; Z = −0.850, p = 0.395), knee angle (128.30 ± 20.94° vs. 141.40 ± 16.34°; Z = −1.846, p = 0.065), or ankle angle (83.20 ± 14.67° vs. 85.00 ± 20.52°; Z = −0.436, p = 0.663).
At bilateral-foot contact during the run-up phase, the NMES conditioning group demonstrated a significantly smaller knee angle than the control group (107.78 ± 13.38° vs. 117.59 ± 14.66°; Z = −2.095, p = 0.036). The ankle angle was also significantly smaller in the NMES conditioning group (106.45 ± 14.50° vs. 118.91 ± 12.34°; Z = −2.510, p = 0.012). No significant difference was found in hip angle between the groups (130.15 ± 13.79° vs. 132.04 ± 11.52°; Z = −0.560, p = 0.575).
At bilateral take-off, the shoulder–hip separation angle was significantly smaller in the NMES conditioning group than in the control group (9.75 ± 6.65° vs. 17.98 ± 10.19°; Z = −2.121, p = 0.034). The NMES conditioning group also showed significantly greater hip angle (158.95 ± 6.57° vs. 153.09 ± 7.47°; Z = −2.033, p = 0.042), knee angle (172.15 ± 5.59° vs. 162.96 ± 24.43°; Z = −2.738, p = 0.006), and ankle angle (149.32 ± 8.63° vs. 132.20 ± 24.43°; Z = −2.530, p = 0.011).
Lower-limb segmental velocities at bilateral take-off were also significantly higher in the NMES conditioning group. Thigh velocity was 4.01 ± 0.41 m/s in the NMES conditioning group and 3.70 ± 0.32 m/s in the control group (Z = −2.385, p = 0.017). Calf velocity was 3.93 ± 0.50 m/s and 3.51 ± 0.43 m/s, respectively (Z = −2.344, p = 0.019), while foot velocity was 3.91 ± 0.83 m/s and 3.26 ± 0.98 m/s, respectively (Z = −2.344, p = 0.019).
No significant between-group differences were observed at bilateral take-off in shoulder angle (99.42 ± 21.85° vs. 101.02 ± 23.87°; Z = −0.306, p = 0.760), elbow angle (72.54 ± 20.70° vs. 71.46 ± 18.14°; Z = −0.175, p = 0.861), or wrist angle (145.44 ± 27.50° vs. 156.19 ± 14.40°; Z = −0.829, p = 0.407).
At ball contact during the aerial hitting phase, the shoulder–hip separation angle was significantly smaller in the NMES conditioning group than in the control group (2.56 ± 4.01° vs. 7.49 ± 6.34°; Z = −2.421, p = 0.014).
No significant between-group differences were observed at ball contact in shoulder angle (141.04 ± 16.85° vs. 138.54 ± 13.55°; Z = −0.786, p = 0.432), elbow angle (149.22 ± 9.00° vs. 141.75 ± 10.56°; Z = −1.615, p = 0.106), wrist angle (154.23 ± 19.27° vs. 155.69 ± 8.97°; Z = −0.567, p = 0.570), hip angle (156.16 ± 9.67° vs. 159.69 ± 11.54°; Z = −1.099, p = 0.272), knee angle (156.15 ± 17.41° vs. 157.69 ± 17.53°; Z = −0.187, p = 0.852), or ankle angle (120.22 ± 32.46° vs. 132.09 ± 12.62°; Z = −0.477, p = 0.633).
Similarly, no significant between-group differences were found at ball contact in thigh velocity (1.55 ± 0.48 vs. 1.57 ± 0.33 m/s; Z = −0.820, p = 0.412), calf velocity (2.52 ± 0.76 vs. 2.32 ± 0.82 m/s; Z = −0.850, p = 0.395), or foot velocity (3.10 ± 1.28 vs. 2.58 ± 1.35 m/s; Z = −1.182, p = 0.237).
Overall, compared with the control group, the NMES conditioning group demonstrated greater ball velocity, smaller knee and ankle angles at bilateral-foot contact, greater lower-limb joint angles and segmental velocities at bilateral take-off, and a smaller shoulder–hip separation angle at both bilateral take-off and ball contact.
Table 1: Performance and phase-specific kinematic variables at the second assessment. Values are presented as mean ± SD. Joint and shoulder–hip separation angles are reported in degrees (°); ball and segmental velocities are reported in meters per second (m/s). The 95% CIs represent the mean difference (NMES − Control). Abbreviations: CI = confidence interval; NMES = neuromuscular electrical stimulation; SD = standard deviation. Please click here to view a larger version of this figure.
Correlations during the run-up phase
The results showed that the hip joint angle and ankle joint angle were significantly negatively correlated when the left foot touched the ground during the approach phase (r = −0.575, p = 0.025) (Table 2).
The results showed that at the moment of foot contact during the run-up phase, the knee joint angle was significantly positively correlated with the hip joint angle (r = 0.590, p = 0.020), and the knee joint angle was significantly positively correlated with the ankle joint angle (r = 0.935, p < 0.001) (Table 2).
Table 2: Correlations among lower-limb joint angles during the run-up phase. Effect size is represented by the Pearson product–moment correlation coefficient (r). Abbreviations: CI = confidence interval; FDR = false discovery rate; NMES = neuromuscular electrical stimulation. Please click here to view a larger version of this figure.
Correlations at bilateral take-off
At bilateral take-off, ball velocity was significantly negatively correlated with elbow angle (r = −0.516, p = 0.049) and significantly positively correlated with shoulder–hip separation angle (r = 0.619, p = 0.024). Knee angle was significantly positively correlated with ankle angle (r = 0.613, p = 0.015) and significantly negatively correlated with foot velocity (r = −0.515, p = 0.049). Thigh velocity was significantly negatively correlated with both elbow angle (r = −0.518, p = 0.048) and wrist angle (r = −0.518, p = 0.048). Calf velocity was strongly and positively correlated with foot velocity (r = 0.854, p < 0.001). In addition, elbow angle was significantly positively correlated with wrist angle (r = 0.585, p = 0.022) (Table 3).
At ball contact during the aerial hitting phase, hip angle was significantly positively correlated with foot velocity (r = 0.571, p = 0.026). Ankle angle was significantly positively correlated with wrist angle (r = 0.575, p = 0.025) and significantly negatively correlated with shoulder–hip separation angle (r = −0.539, p = 0.038). Thigh velocity was strongly and positively correlated with calf velocity (r = 0.845, p < 0.001) and significantly positively correlated with shoulder joint angle (r = 0.567, p = 0.027).
Calf velocity was significantly positively correlated with foot velocity (r = 0.624, p = 0.013), shoulder joint angle (r = 0.518, p = 0.048), and shoulder–hip separation angle (r = 0.621, p = 0.014). Shoulder joint angle was significantly positively correlated with elbow angle (r = 0.597, p = 0.019), while elbow angle was significantly positively correlated with shoulder–hip separation angle (r = 0.630, p = 0.012) (Table 3).
Table 3: Correlations among spike-performance and kinematic variables at take-off and ball contact. Effect size is represented by the Pearson product–moment correlation coefficient (r). Joint and shoulder–hip separation angles are reported in degrees (°); ball and segmental velocities are reported in meters per second (m/s). Abbreviations: CI = confidence interval; FDR = false discovery rate; NMES = neuromuscular electrical stimulation. Please click here to view a larger version of this figure.
DATA AVAILABILITY:
The de-identified participant-level kinematic and performance data supporting the findings of this study are publicly available in the Zenodo repository under DOI: 10.5281/zenodo.21876465. The dataset contains the individual participant values from the selected best-performing valid trial at the predefined volleyball spike events, which were used for the statistical analyses reported in this article.
Discussion
The study investigated the acute effects of a single immediate NMES intervention on volleyball players’ spiking performance, with a focus on kinematic changes during the run-up, take-off, and aerial hitting phases. The results showed that when NMES was applied immediately to the lower limbs and key core muscle groups, participants’ joint angles, movement velocity, and ball velocity were significantly improved. This shows that NMES can instantly improve neuromuscular coordination and movement output efficiency, and substantially assist technical sports movements that require explosive power (such as spiking).
The results further indicated that the knee and ankle angles of the experimental group were significantly smaller than those of the control group at the moment when both feet touched the ground. This meant that their lower limbs showed a greater degree of flexion, which is conducive to storing elastic energy before leaving the ground and is a key mechanism in the stretch-shortening cycle (SSC)20,21. Previous studies have shown that NMES can increase the excitability of spinal motor neurons and recruit more fast-twitch muscle fibers, which further supports the observation of improved movement preparation posture in this study22,23,24. In addition, the present study found a high positive correlation between the knee and ankle angles (r = 0.935, p < 0.001). This reflects that NMES improves joint coordination, and is conducive to the stability and efficiency of lower limb kinetic energy transmission and the principle of coordinated stability in the kinetic chain25,26. NMES therefore enhances overall movement quality by improving joint timing and coordination between muscle groups27.
During the take-off phase, the experimental group had significantly greater extension angles at the hip, knee, and ankle joints than the control group, and thigh, calf, and foot velocities were all improved (p < 0.05). This indicates a more complete and powerful triple-extension pattern, which is the basis for strong vertical propulsion28,29. A potential reason for this is that NMES increases the rate of force development (RFD), thereby enhancing the drive of the cerebral cortex and the efficiency of synapses30,31. The study also observed that ball velocity was negatively correlated with elbow angle (r = −0.516, p = 0.049). This means that if the upper limbs are bent too early or the angle is incorrect when the arm is swung, it may lead to incomplete kinetic energy transfer and affect the efficiency of the hit32,33. This finding is consistent with previous research into the relationship between body segment force timing and hitting efficiency and indicates that NMES can optimize athletic performance by strengthening neuromuscular drive and timing coordination34,35.
In the aerial hitting phase, the experimental group had a significantly smaller shoulder-hip separation angle than the control group (Z = −2.421, p = 0.014). This reflects stronger trunk stability and core control capabilities during flight, which helps stabilize the upper limb movement trajectory, reduce movement energy loss, and thereby improve the accuracy and efficiency of the hit36,37. In addition, the significant correlation between the experimental group’s thigh and calf velocity (r = 0.845) and calf and foot velocity (r = 0.624) proves that the coordinated actions between the nodes of the kinetic chain are real-time optimized. This bottom-up transmission mode of kinetic energy is crucial for the hitting action38,39. NMES’ immediate promotion of proprioceptive input and movement patterns is a possible explanatory mechanism for this phenomenon40.
The present findings showed that, at the second assessment, the NMES conditioning group demonstrated greater ball velocity, smaller knee and ankle angles at bilateral-foot contact, greater hip, knee, and ankle angles and higher lower-limb segmental velocities at bilateral take-off, and a smaller shoulder–hip separation angle at bilateral take-off and ball contact than the control group. These findings indicate that acute NMES conditioning applied to upper-limb, core, and lower-limb muscles was associated with phase-specific differences in volleyball spike kinematics and ball velocity. However, the present study did not directly measure muscle activation, force production, injury risk, long-term training adaptation, or competitive match performance. Therefore, the observed kinematic differences should not be interpreted as evidence that NMES prevents injuries or broadly improves athletic or competitive performance. In addition, because the principal analysis compared the two groups at the second assessment, the findings should be interpreted as between-group differences rather than definitive within-participant improvements caused by NMES. Future studies should include direct measures of muscle activation and kinetics, concealed allocation, blinded outcome assessment, larger samples, and group-by-time analyses to clarify the acute and longer-term effects of NMES on volleyball-specific performance. Accordingly, the present findings should be interpreted as specific to trained male university volleyball players and should not be generalized to female athletes or athletes with substantially different competitive experience without further evidence.
At the second assessment, the NMES conditioning group demonstrated greater ball velocity and phase-specific differences in joint angles, shoulder–hip separation, and lower-limb segmental velocities compared with the control group. These findings suggest that a single 30-min NMES conditioning session may be associated with acute changes in volleyball spike kinematics and ball velocity. The results should not be generalized to injury prevention, long-term adaptation, or broader competitive-performance benefits, as these outcomes were not measured in the present study.
Disclosures
The authors declare no conflicts of interest. A generative artificial intelligence tool, ChatGPT (OpenAI), was used during manuscript revision to assist with English-language editing, grammatical correction, and improvement of clarity and readability. The AI tool was not used to generate, manipulate, or interpret the research data; perform the statistical analyses; produce the study results; or prepare or modify the figures. All AI-assisted text was critically reviewed, verified, and revised by the authors, who take full responsibility for the accuracy, integrity, and content of the final manuscript.
Acknowledgements
This study was supported by the Key Project of the Fujian Province Young and Middle-aged Teachers’ Education and Research Project (Science and Technology) (No. JZ240034), the Social Science Foundation of Fujian Province (No. FJ2025T011), the PhD Research Start-up Fund of Jimei University (No. Q202440), and the Ministry of Education Industry–Academia Collaborative Education Project (No. 231104575130151).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Frequency-modulated pulse therapy device | Manufacturer not specified in the study records | Guangzhou, China | ZN-566 |
| High-speed camera | Sony Corporation | Tokyo, Japan | PXW-FS7 |
| SPSS | IBM | Armonk, NY, USA | Version 27 for Windows |
| Three-dimensional motion-analysis system | Visol Inc. | Gwangmyeong, Republic of Korea | Kwon3D |
References
- Mekuriyaw E. Effect of high intensity interval training on selected physical fitness qualities and spiking technique of volleyball project players [doctoral dissertation]. Ethiopia: Bahir Dar University; 2022.
- Maffiuletti NA, et al. Electrical stimulation for investigating and improving neuromuscular function in vivo: Historical perspective and major advances. J Biomech. 2023;152:111582.
- Liu M, Wu J, Tao J. Optimal recognition of volleyball player’s arm movement track based on embedded microprocessor. Wirel Commun Mob Comput. 2022;(1):3525197.
- Kawai M, et al. Effect of ball positions on trunk, hip, knee, and ankle joint kinematics and kinetics during a spike jump in volleyball. Gait Posture. 2024;113:419-426.
- Van Dyke M. Does the use of the antagonist facilitated specialization and oscillatory training methods reduce co-activation and improve rate of force development to a greater extent than traditional methods. Culminating Projects in Kinesiology. 2015.
- Qi S, et al. Advances in non-invasive brain stimulation: enhancing sports performance function and insights into exercise science. Front Hum Neurosci. 2024;18:1477111.
- Chen CF, et al. Kinematic analysis of countermovement jump performance in response to immediate neuromuscular electrical stimulation. Math Biosci Eng. 2023;20(9):16031-16042.
- Chen CF, Shen XX, Chou YC, Wu HJ. Effects of hurdle leg stretch and neuromuscular electrical stimulation intervention on front kick in martial arts: A kinematic analysis. Mol Cell Biomech. 2025;22(3):1479-1479.
- Muthalib M, et al. Effects of increasing neuromuscular electrical stimulation current intensity on cortical sensorimotor network activation: a time domain fNIRS study. PLoS One. 2015;10(7):e0131951.
- Xu X, et al. Effects of electrical stimulation on skin surface. Acta Mech Sin. 2021;37(12):1843-1871.
- Oliveira LDS, et al. A systematic review of volleyball spike kinematics: Implications for practice and research. Int J Sports Sci Coach. 2020;15(2):239-255.
- Giatsis G, Tilp M. Spike arm swing techniques of Olympics male and female elite volleyball players (1984-2021). J Sports Sci Med. 2022;21(3):465.
- Chen C, et al. Analysis of rhythmic movement techniques in female college long jump athletes: Insights from athletics open. Mol Cell Biomech. 2025;22(5):1711-1711.
- Chen CF, et al. Running speed and slope effects on spatiotemporal parameters and running technology in male and female recreational runners. Mol Cell Biomech. 2025;22(5):1832-1832.
- Chen CF, et al. The impact and correlation of running landing methods on leg movement ability. Acta Bioeng Biomech. 2023;25(4):155-162.
- Chen CF, Wu HJ. The effect of an 8-week rope skipping intervention on standing long jump performance. Int J Environ Res Public Health. 2022;19(14):8472.
- Chen CF, Wu HJ, Liu C, Wang SC. Kinematics analysis of male runners via forefoot and rearfoot strike strategies: A preliminary study. Int J Environ Res Public Health. 2022;19(23):15924.
- Chen CF, Chuang MH, Wu HJ. Joint energy and shot mechanical energy of glide-style shot put. Proc Inst Mech Eng P J Sports Eng Technol. 2022;239(2):274-282.
- Chen CF, et al. Motion analysis for jumping discus throwing correction. Int J Environ Res Public Health. 2021;18(24):13414.
- Sheppard JM, et al. Relative importance of strength, power, and anthropometric measures to jump performance of elite volleyball players. J Strength Cond Res. 2008;22(3):758-765.
- Milo N, Grosu E, Milo M. Vertical jump enhancement with respect to volleyball vertical jump. Stud Univ Babes-Bolyai Educ Artis Gymnast. 2017;62(4):87-102.
- Borzuola R, Labanca L, Macaluso A, Laudani L. Modulation of spinal excitability following neuromuscular electrical stimulation superimposed to voluntary contraction. Eur J Appl Physiol. 2020;120:2105-2113.
- Borzuola R, et al. Frequency-dependent effects of superimposed NMES on spinal excitability in upper and lower limb muscles. Heliyon. 2024;10(21):e40145.
- Bickel CS, Yarar-Fisher C, Mahoney ET, McCully KK. Neuromuscular electrical stimulation-induced resistance training after SCI: a review of the Dudley protocol. Top Spinal Cord Inj Rehabil. 2015;21(4):294-302.
- Khan MA, et al. A systematic review on functional electrical stimulation based rehabilitation systems for upper limb post-stroke recovery. Front Neurol. 2023;14:1272992.
- Li S, et al. The effect of neuromuscular electrical stimulation superimposed on quadriceps training on gait dynamics after anterior cruciate ligament reconstruction. J Back Musculoskelet Rehabil. 2025;38(1):139-147.
- Wang X, Li H, Chen J. Neuromuscular electrical stimulation enhances lower limb muscle synergies during jumping in martial artists post-anterior cruciate ligament reconstruction: A randomized crossover trial. Bioengineering (Basel). 2025;12(5):535.
- He J, Li M, Zhang Q, Zhang Z. Associations between the performance of vertical jump and accelerative sprint in elite sprinters. Front Bioeng Biotechnol. 2025;13:1539197.
- Junge N, et al. Force-velocity-power profiling of maximal effort sprinting, jumping and hip thrusting: Exploring the importance of force orientation specificity for assessing neuromuscular function. J Sports Sci. 2021;39(18):2115-2122.
- Seitz LB, Haff GG. Factors modulating post-activation potentiation of jump, sprint, throw, and upper-body ballistic performances: A systematic review with meta-analysis. Sports Med. 2016;46:231-240.
- Karabel F, Makaracı Y. Optimal recovery time for post-activation performance enhancement after an acute bout of plyometric exercise on unilateral countermovement jump and postural sway in national-level female volleyball players. Appl Sci (Basel). 2025;15(8):4079.
- Gupta D, Jensen JL, Abraham LD. Biomechanics of hang-time in volleyball spike jumps. J Biomech. 2021;121:110380.
- Suhadi S, Guntur G, Kriswanto ES, Nopembri S. Muscular endurance and strength as predominant factors on spike among young volleyball athletes. Retos. 2023;50:349-356.
- Gonçalves CA, et al. Neuromuscular jumping performance and upper-body horizontal power of volleyball players. J Strength Cond Res. 2021;35(8):2236-2241.
- Garcia S, et al. Comparison of landing kinematics and kinetics between experienced and novice volleyball players during block and spike jumps. BMC Sports Sci Med Rehabil. 2022;14(1):105.
- Sedaghati P, Baharmast Hossein Abadi A, Zolghadr H. Effect of core stability exercises on volleyball players: A systematic review. Phys Treat Spec Phys Ther J. 2023;13(3):147-158.
- Comba D, et al. Evaluation of lower extremity and core strength in young female and male volleyball players. J Pioneer Med Sci. 2024;13(1):53-57.
- Tsoukos A, et al. Upper and lower body power are strong predictors for selection of male junior national volleyball team players. J Strength Cond Res. 2019;33(10):2760-2767.
- Baena-Raya A, et al. The force-velocity profile as determinant of spike and serve ball velocity in top-level male volleyball players. PLoS One. 2021;16(4):e0249612.
- Li X, Wang D, Gao S, Zhou C. Impacts of kinematic information on action anticipation and the related neurophysiological associations in volleyball experts. Brain Sci. 2024;14(7):647.