This article describes a single preoperative ultrasound-derived venous C2/A measurement, complemented by D-dimer, for identifying orthopedic surgery patients at increased risk of postoperative lower-limb DVT.
Research Article
Preoperative Venous Circumference-Squared-to-Area Ratio (C2/A) and D-dimer for Deep Vein Thrombosis Prediction After Orthopedic Surgery
In This Article
Summary
Abstract
Deep vein thrombosis (DVT) is a common complication after orthopedic surgery. This prospective observational study evaluated whether a single preoperative baseline measurement of the venous circumference-squared-to-area ratio (C2/A), alone and with D-dimer, was associated with DVT detected during the first 7 postoperative days. One hundred fifty adults undergoing orthopedic surgery were enrolled; 37 developed DVT and 113 did not. Preoperative circumference (C) and area (A) were measured separately at end-expiration with the ultrasound system's built-in measurement package during the same acquisition cycle. Investigators calculated C2/A as C2 divided by A. To apply this rule consistently to the retained participant-level dataset, all revision analyses used C2/A recalculated from the retained C and A fields. Postoperative ultrasound was performed at 12-h intervals for 7 days under a prespecified intensified study-surveillance schedule used only for outcome ascertainment. The areas under the receiver operating characteristic curves were 0.893 for common femoral vein C2/A, 0.817 for superficial femoral vein C2/A, 0.906 for popliteal vein C2/A, and 0.834 for D-dimer. The originally specified superficial femoral vein C2/A plus D-dimer model had an apparent area under the curve of 0.887 and a stratified 5-fold cross-validated out-of-fold area under the curve of 0.877. A 5-variable exploratory model had an out-of-fold area under the curve of 0.938. Using cohort-derived thresholds of 16.26 for superficial femoral vein C2/A and 2.15 mg/L FEU for D-dimer, DVT occurred in 0 of 78 patients with neither marker elevated, 15 of 50 with one elevated, and 22 of 22 with both elevated. Preoperative venous C2/A and D-dimer were associated with early postoperative DVT, but the thresholds and models are exploratory and require external validation.
Introduction
Lower-limb deep vein thrombosis (DVT) remains a major perioperative complication after orthopedic surgery. Surgical trauma, reduced mobility, local venous stasis, and postoperative hypercoagulability converge to increase venous thromboembolism risk, and thrombus propagation or embolization can lead to pulmonary embolism and substantial morbidity1,2. Although pharmacologic, exercise-based, and mechanical prophylaxis strategies are widely used, postoperative DVT continues to occur, indicating a need for preoperative markers that are non-invasive and closely related to the local venous environment3,4.
Current screening relies heavily on Doppler ultrasonography and D-dimer testing5,6. Ultrasonography is non-invasive, repeatable, and central to DVT diagnosis, but conventional measurements such as diameter and flow are often interpreted after thrombus formation or after hemodynamic disturbance is already evident7,8. D-dimer is sensitive for thrombotic disease but has limited specificity in perioperative patients because age, trauma, inflammation, and surgery-related fibrinolysis can elevate circulating levels without established DVT9,10. Recent age-adjusted D-dimer work also emphasizes that age materially influences interpretation, although those thresholds were designed for diagnostic exclusion rather than preoperative prediction11. Clinical risk scores such as the Caprini score summarize systemic and historical risk factors, but they do not directly quantify subtle local venous geometry12.
Venous cross-sectional geometry provides a plausible link between local anatomy and thrombotic risk. The morphology index C2/A, calculated as cross-sectional circumference squared divided by cross-sectional area, increases as a vessel becomes less circular or more distorted. A higher value may reflect flattening, reduced wall compliance, external compression, or abnormal transmural pressure13. Morphological studies of venous disease support the relevance of venous wall and lumen structure to clinical venous dysfunction13. C2/A may therefore capture local structural susceptibility, whereas D-dimer reflects systemic fibrin turnover. Combined with a clinical score such as Caprini, these two markers may provide a more complete preoperative risk picture14. Therefore, this study investigated the predictive value of single baseline preoperative C2/A measured in the CFV, SFV, and POV for postoperative DVT after orthopedic surgery, and whether combining C2/A with D-dimer improves discrimination.
Protocol
The study was conducted in accordance with institutional human research guidelines. The study was approved by the Ethics Committee of Xijing Hospital, Air Force Medical University (approval number KY20232031-F-1). All participants were informed of the study procedures and provided written informed consent before enrollment. The main equipment, assays, software, and RRID status are listed in the Table of Materials. Because this was a prospective observational study without an experimental intervention, no separate experimental control group was required.
Study design and participants
This prospective observational study enrolled 150 patients scheduled for orthopedic surgery at the First Affiliated Hospital of Air Force Medical University between December 2023 and July 2024. Eligible patients had no preoperative lower-limb DVT and were able to complete the standardized ultrasound examination. Patients with pre-existing DVT, a previous history of DVT, lower-limb vascular injury or deformity, deep venous valve dysfunction, heart failure, lower-limb venous hypertension caused by pelvic or abdominal tumors, coagulation abnormalities, long-term anticoagulant therapy, a severe fracture preventing cooperation with the examination, or impaired consciousness were excluded. Patients without postoperative DVT served as the comparator group.
Preoperative clinical and laboratory data
Baseline clinical variables included age, sex, body mass index, medical history, Caprini score, C-reactive protein, platelet count, D-dimer, surgical duration, tourniquet duration, and bed-rest duration. D-dimer was measured in a preoperative fasting venous blood sample on a fully automated coagulation analyzer using an immunoturbidimetric method and was reported in mg/L fibrinogen-equivalent units (FEU). The manufacturer, analyzer model, and assay details are listed in the Table of Materials.
Ultrasound examination and C2/A measurement
All ultrasound examinations were performed with a color Doppler ultrasound system equipped with a 12–3 MHz high-frequency linear-array transducer in venous imaging mode. Patients were placed in the supine position with the lower limbs externally rotated. The common femoral vein (CFV), superficial femoral vein (SFV), and popliteal vein (POV) were scanned sequentially at prespecified anatomic levels. Probe pressure was kept as low as possible to avoid visible venous deformation. The manufacturer and exact system and transducer models are listed in the Table of Materials.
For each venous segment, cross-sectional circumference (C) and cross-sectional area (A) were measured separately on transverse images at end-expiration with the bedside ultrasound system's built-in measurement package. C and A were obtained during the same acquisition cycle. Three acquisitions were performed per segment and summarized in the retained participant-level table. Investigators calculated C2 and the unitless morphology index C2/A; no external calculation software was used. For the revision analysis, the stated calculation rule was applied uniformly to the retained numerical fields, with C2/A calculated as the square of the retained C value divided by the retained A value. Because C and A were separate device-derived measurements rather than an analytically exported perimeter-area pair from a shared digital contour, C2/A is interpreted as a measurement-derived morphology index. Diameter, flow velocity, and blood flow volume were measured on longitudinal images. All preoperative examinations were performed by the same ultrasound physician, who had more than 5 years of experience and was blinded to the baseline clinical and laboratory data at the time of measurement. Formal intraobserver and interobserver reproducibility analyses were not prospectively performed. Postoperative surveillance was used only to ascertain DVT outcomes.
Postoperative surveillance and outcome definition
Postoperative lower-limb venous ultrasound was performed according to a prespecified intensified study-surveillance schedule at 12-h intervals until postoperative day 7; monitoring stopped when DVT was first detected. The twice-daily schedule was selected to standardize outcome-ascertainment opportunities across participants and to improve temporal resolution for detecting early or asymptomatic DVT. This study schedule was more intensive than routine clinical surveillance, was used only for outcome ascertainment, and should not be interpreted as a clinical monitoring recommendation.
Statistical analysis
Continuous variables were summarized as mean ± standard deviation and compared between DVT and non-DVT groups using Welch two-sample t-tests. Sex distribution was compared using the Pearson chi-square test. Receiver operating characteristic (ROC) curves were used to assess discrimination. Optimal thresholds were selected by maximizing the Youden J index in this development cohort, with values exactly at the threshold classified as positive. AUC 95% confidence intervals were obtained from 3,000 stratified bootstrap resamples, and sensitivity and specificity confidence intervals were obtained using exact Clopper-Pearson intervals. Apparent combined-marker probabilities were estimated with logistic regression in the full cohort. Exploratory internal validation used stratified 5-fold cross-validation; StandardScaler and L2-penalized logistic regression were fitted within each training fold before generating out-of-fold probabilities for the held-out fold. The 5-variable model was considered overfitting-prone because 37 events yielded 7.4 events per variable. All tests were two-sided, with p < 0.05 denoting statistical significance. The locked revision analysis used Python 3.9.6, pandas 2.3.3, NumPy 2.0.2, SciPy 1.13.1, scikit-learn 1.6.1, statsmodels 0.14.6, Matplotlib 3.9.4, and openpyxl 3.1.5.
Results
Study design and participants
The analysis included 150 patients, of whom 69 were male and 81 were female. The mean age was 55.01 years ± 14.25 years. Postoperative DVT occurred in 37 patients (24.7%), whereas 113 patients (75.3%) did not develop DVT during ultrasound surveillance. Figure 1 summarizes the workflow from preoperative enrollment to postoperative outcome ascertainment and analysis.
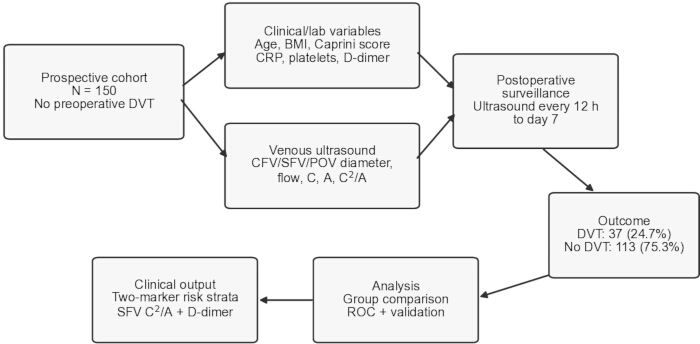
Figure 1: Study design and analysis workflow. Patients without preoperative DVT underwent a single baseline clinical, laboratory, and lower-limb venous ultrasound assessment. Only the preoperative C2/A measurement was used for prediction. Postoperative ultrasound at 12-h intervals through postoperative day 7 followed a prespecified intensified surveillance schedule used to standardize outcome-ascertainment opportunities and improve temporal resolution for early or asymptomatic DVT; surveillance stopped after DVT detection. This study schedule exceeded routine clinical monitoring and is not proposed as a clinical surveillance recommendation. The workflow shows the DVT (n = 37) and non-DVT (n = 113) comparison groups, marker analysis, ROC analysis, and exploratory risk stratification. CFV, common femoral vein; DVT, deep vein thrombosis; POV, popliteal vein; ROC, receiver operating characteristic; SFV, superficial femoral vein. Please click here to view a larger version of this figure.
Preoperative clinical and laboratory data
Patients who developed DVT were older than those who did not develop DVT (63.73 years ± 9.49 years vs. 52.16 years ± 14.42 years, p < 0.001), and they had higher preoperative D-dimer levels (5.69 mg/L ± 6.28 mg/L vs. 1.20 mg/L ± 2.28 mg/L, p < 0.001). Sex distribution did not differ significantly between groups. These results indicate that patients who subsequently developed DVT already had a higher systemic risk profile before postoperative thrombosis was detected (Table 1).
| Clinical parameter | DVT group (n = 37) | Non-DVT group (n = 113) | t/χ² value | P value |
| Age (years) | 63.73 ± 9.49 | 52.16 ± 14.42 | 5.60 | <0.001 |
| Male, n (%) | 15 (40.5%) | 54 (47.8%) | 0.59 | 0.443 |
| Female, n (%) | 22 (59.5%) | 59 (52.2%) | ||
| D-dimer (mg/L) | 5.69 ± 6.28 | 1.20 ± 2.28 | 4.26 | <0.001 |
Table 1: Comparison of clinical data between patients with postoperative DVT and those without postoperative DVT. Values are mean ± standard deviation or n (%), as appropriate. p values were calculated using Welch two-sample t-tests or chi-square tests. DVT, deep vein thrombosis.
Ultrasound examination and C2/A measurement
The ultrasound protocol quantified both conventional hemodynamic variables and cross-sectional morphology. Representative images show the transverse circumference and area measurements used to calculate C2/A (Figure 2). Compared with the non-DVT group, the DVT group had significantly higher C2/A values in all three venous segments. Mean CFV C2/A was 17.12 ± 1.59 in the DVT group and 14.71 ± 1.34 in the non-DVT group; mean SFV C2/A was 17.21 ± 2.41 and 14.81 ± 2.53, respectively; and mean POV C2/A was 18.65 ± 2.68 and 15.27 ± 1.36, respectively. All three differences were statistically significant (p < 0.001) (Figure 3).
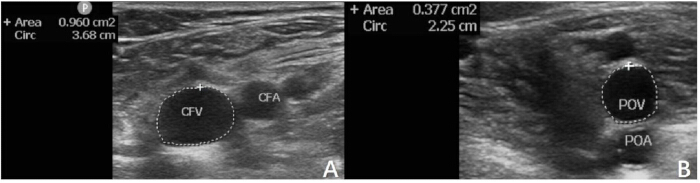
Figure 2: Representative transverse ultrasound measurements. Panel (A) shows the common femoral vein (CFV), and Panel (B) shows the popliteal vein (POV). Cross-sectional circumference (C) and area (A) were measured separately at end-expiration during the same acquisition cycle with the ultrasound system's built-in measurement package. The images illustrate the measurement inputs used to calculate C2/A. CFA, common femoral artery; CFV, common femoral vein; POA, popliteal artery; POV, popliteal vein. Please click here to view a larger version of this figure.
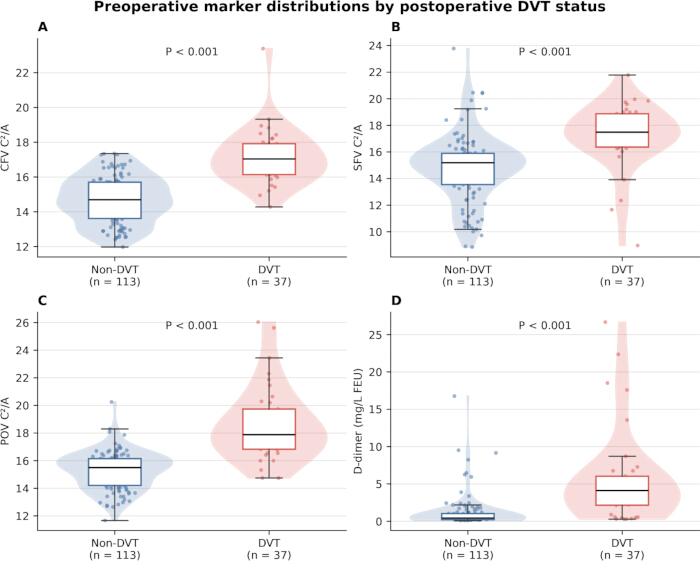
Figure 3: Preoperative marker distributions by postoperative DVT status. Panels (A–D) show recalculated CFV C2/A, SFV C2/A, POV C2/A, and D-dimer (mg/L FEU), respectively, in patients who developed DVT (n = 37) and those who did not (n = 113). Violin plots show the distributions, boxes indicate the median and interquartile range, whiskers extend to 1.5 times the interquartile range, and points represent individual patients. p values were calculated using Welch two-sample t-tests. CFV, common femoral vein; DVT, deep vein thrombosis; POV, popliteal vein; SFV, superficial femoral vein. Please click here to view a larger version of this figure.
Several conventional ultrasound variables also differed between groups. CFV blood flow, SFV blood flow, and POV blood flow were lower in patients who developed DVT, whereas selected circumference and area measurements differed by venous segment. These findings indicate that postoperative DVT risk was associated with both altered preoperative venous geometry and altered hemodynamic profiles (Table 2).
| Ultrasound parameter | DVT group (n = 37) | Non-DVT group (n = 113) | t value | p value |
| CFV diameter (mm) | 11.05 ± 1.19 | 10.36 ± 1.29 | 3.03 | 0.003 |
| CFV flow velocity (cm/s) | 18.15 ± 5.71 | 19.55 ± 7.52 | -1.19 | 0.238 |
| CFV blood flow (mL/min) | 587.41 ± 118.46 | 683.21 ± 136.65 | -4.11 | <0.001 |
| CFV-C (mm) | 43.93 ± 4.83 | 38.04 ± 3.84 | 6.75 | <0.001 |
| CFV-A (mm²) | 114.16 ± 23.86 | 99.47 ± 17.81 | 3.44 | 0.001 |
| CFV C²/A | 17.12 ± 1.59 | 14.71 ± 1.34 | 8.34 | <0.001 |
| SFV diameter (mm) | 6.87 ± 1.24 | 6.54 ± 1.15 | 1.43 | 0.157 |
| SFV flow velocity (cm/s) | 14.73 ± 6.00 | 15.14 ± 6.88 | -0.34 | 0.732 |
| SFV blood flow (mL/min) | 162.43 ± 73.95 | 261.32 ± 92.82 | -6.61 | <0.001 |
| SFV-C (mm) | 33.65 ± 3.98 | 31.65 ± 3.99 | 2.65 | 0.010 |
| SFV-A (mm²) | 67.48 ± 15.38 | 70.03 ± 17.38 | -0.85 | 0.399 |
| SFV C²/A | 17.21 ± 2.41 | 14.81 ± 2.53 | 5.21 | <0.001 |
| POV diameter (mm) | 6.88 ± 1.35 | 6.94 ± 1.30 | -0.22 | 0.823 |
| POV flow velocity (cm/s) | 9.74 ± 4.23 | 9.29 ± 3.52 | 0.59 | 0.559 |
| POV blood flow (mL/min) | 108.66 ± 33.37 | 156.38 ± 48.47 | -6.69 | <0.001 |
| POV-C (mm) | 36.01 ± 2.94 | 34.26 ± 2.44 | 3.27 | 0.002 |
| POV-A (mm²) | 70.71 ± 11.82 | 77.63 ± 11.29 | -3.13 | 0.003 |
| POV C²/A | 18.65 ± 2.68 | 15.27 ± 1.36 | 7.38 | <0.001 |
Table 2: Comparison of ultrasound parameters between patients with postoperative DVT and those without postoperative DVT. Values are mean ± standard deviation. p values were calculated using Welch two-sample t-tests. C, circumference; A, area; CFV, common femoral vein; POV, popliteal vein; SFV, superficial femoral vein.
Predictive performance of C2/A, D-dimer, and combined models
ROC analysis showed that C2/A values in all three venous segments discriminated postoperative DVT risk. The AUC values were 0.893 (95% CI, 0.833-0.940) for CFV C2/A, 0.817 (95% CI, 0.720-0.900) for SFV C2/A, 0.906 (95% CI, 0.839-0.959) for POV C2/A, and 0.834 (95% CI, 0.750-0.904) for D-dimer (Figure 4). Using the cohort-derived Youden J cutoffs, CFV C2/A ≥15.87 yielded 86.5% sensitivity and 80.5% specificity; SFV C2/A ≥16.26 yielded 83.8% sensitivity and 80.5% specificity; POV C2/A ≥16.42 yielded 86.5% sensitivity and 85.0% specificity; and D-dimer ≥2.15 mg/L FEU yielded 75.7% sensitivity and 88.5% specificity (Table 3).
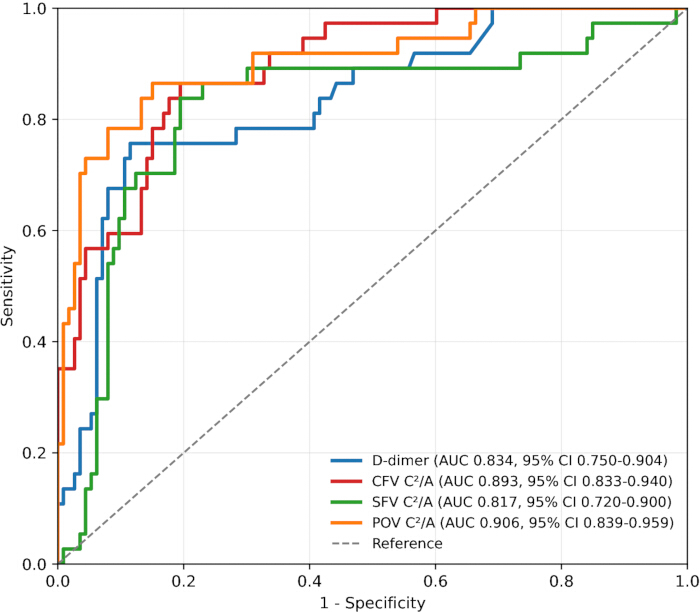
Figure 4: Single-marker ROC curves for preoperative D-dimer and venous C2/A. ROC curves are shown for D-dimer, CFV C2/A, SFV C2/A, and POV C2/A in the same 150-patient cohort (37 DVT events, 113 non-DVT). AUCs with 95% CIs were estimated using 3,000 stratified bootstrap resamples. Cohort-derived Youden J cutoffs were D-dimer ≥2.15 mg/L FEU, CFV C2/A ≥15.87, SFV C2/A ≥16.26, and POV C2/A ≥16.42. Threshold-level values were classified as positive. AUC, area under the curve; CFV, common femoral vein; DVT, deep vein thrombosis; POV, popliteal vein; ROC, receiver operating characteristic; SFV, superficial femoral vein. Please click here to view a larger version of this figure.
| Parameter | Sensitivity (%) | Specificity (%) | AUC | 95% CI | Cutoff value | p value |
| D-dimer (mg/L) | 75.7 | 88.5 | 0.834 | 0.750-0.904 | >=2.15 | <0.001 |
| CFV diameter (mm) | 83.8 | 48.7 | 0.651 | 0.556-0.743 | >=10.23 | 0.006 |
| CFV blood flow (mL/min) | 67.6 | 63.7 | 0.705 | 0.608-0.795 | <=615.50 | <0.001 |
| CFV-C (mm) | 59.5 | 92.9 | 0.845 | 0.768-0.910 | >=43.28 | <0.001 |
| CFV-A (mm²) | 59.5 | 68.1 | 0.679 | 0.576-0.774 | >=108.86 | 0.001 |
| CFV C²/A | 86.5 | 80.5 | 0.893 | 0.833-0.940 | >=15.87 | <0.001 |
| SFV blood flow (mL/min) | 73 | 82.3 | 0.808 | 0.721-0.886 | <=172.10 | <0.001 |
| SFV-C (mm) | 35.1 | 89.4 | 0.635 | 0.524-0.741 | >=35.93 | 0.014 |
| SFV C²/A | 83.8 | 80.5 | 0.817 | 0.720-0.900 | >=16.26 | <0.001 |
| POV blood flow (mL/min) | 97.3 | 45.1 | 0.785 | 0.702-0.858 | <=159.91 | <0.001 |
| POV-C (mm) | 67.6 | 64.6 | 0.683 | 0.575-0.789 | >=35.38 | <0.001 |
| POV-A (mm²) | 43.2 | 87.6 | 0.648 | 0.539-0.749 | <=66.00 | 0.007 |
| POV C²/A | 86.5 | 85 | 0.906 | 0.839-0.959 | >=16.42 | <0.001 |
| CFV diameter + D-dimer | 70.3 | 89.4 | 0.828 | 0.741-0.906 | >=0.28 | <0.001 |
| CFV blood flow + D-dimer | 81.1 | 85 | 0.87 | 0.802-0.931 | >=0.27 | <0.001 |
| CFV-C + D-dimer | 94.6 | 80.5 | 0.923 | 0.879-0.961 | >=0.22 | <0.001 |
| CFV-A + D-dimer | 75.7 | 85.8 | 0.864 | 0.795-0.922 | >=0.26 | <0.001 |
| CFV C²/A + D-dimer | 81.1 | 90.3 | 0.928 | 0.883-0.966 | >=0.35 | <0.001 |
| SFV blood flow + D-dimer | 94.6 | 76.1 | 0.919 | 0.865-0.963 | >=0.19 | <0.001 |
| SFV-C + D-dimer | 81.1 | 82.3 | 0.858 | 0.779-0.923 | >=0.22 | <0.001 |
| SFV C²/A + D-dimer | 89.2 | 81.4 | 0.887 | 0.813-0.945 | >=0.19 | <0.001 |
| POV blood flow + D-dimer | 83.8 | 77.9 | 0.879 | 0.815-0.934 | >=0.25 | <0.001 |
| POV-C + D-dimer | 86.5 | 69 | 0.846 | 0.773-0.910 | >=0.18 | <0.001 |
| POV-A + D-dimer | 73 | 85.8 | 0.838 | 0.753-0.912 | >=0.27 | <0.001 |
| POV C²/A + D-dimer | 86.5 | 90.3 | 0.933 | 0.880-0.973 | >=0.21 | <0.001 |
Table 3: ROC analysis of ultrasound parameters, D-dimer, and combined predictors. Diagnostic performance is summarized by sensitivity, specificity, AUC, 95% confidence interval, cutoff value, and p value. Cutoffs are cohort-derived and exploratory, and the exact selection rule was Youden J. AUC, area under the curve; CFV, common femoral vein; D-dimer, D-dimer concentration; POV, popliteal vein; ROC, receiver operating characteristic; SFV, superficial femoral vein.
The originally specified SFV C2/A plus D-dimer model was retained to avoid post hoc switching of the venous segment after applying the explicit C2/A calculation rule. This 2-marker model had an apparent AUC of 0.887 (95% CI, 0.813-0.945), sensitivity of 89.2%, and specificity of 81.4%. In stratified 5-fold internal validation, its out-of-fold AUC was 0.877 (95% CI, 0.799-0.938) (Figure 5). The exploratory 5-variable model had an apparent AUC of 0.960 (95% CI, 0.926-0.986) and an out-of-fold AUC of 0.938 (95% CI, 0.894-0.973). Using cohort-derived thresholds of SFV C2/A ≥16.26 and D-dimer ≥2.15 mg/L FEU, DVT occurred in 0/78 patients (0.0%; 95% CI, 0.0%–4.6%) with neither marker elevated, 15/50 (30.0%; 95% CI, 17.9%–44.6%) with one elevated, and 22/22 (100.0%; 95% CI, 84.6%–100.0%) with both elevated (Figure 6). Tourniquet exposure occurred after the baseline ultrasound and, therefore, could not directly alter the preoperative C2/A measurement. Among tourniquet users (n = 56), duration correlated with CFV C2/A (Spearman rho = 0.285, p = 0.033) and POV C2/A (rho = 0.281, p = 0.036), whereas the association with SFV C2/A was not statistically significant (rho = 0.240, p = 0.074). These unadjusted associations are non-causal and are reported in Supplementary Table 1.
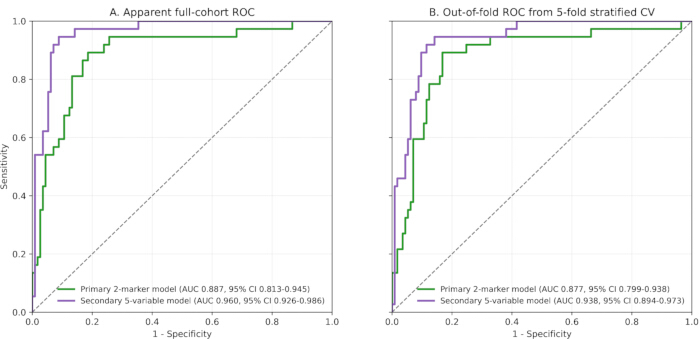
Figure 5: Apparent versus internally cross-validated combined-model ROC curves. Panel (A) shows apparent full-cohort ROC curves for the originally specified 2-marker logistic model (SFV C2/A + D-dimer) and the secondary 5-variable model (age + body mass index + Caprini score + SFV C2/A + D-dimer). Panel (B) shows out-of-fold ROC curves from stratified 5-fold cross-validation with fold-internal standardization and fold-specific model fitting. The 2-marker model achieved an apparent AUC of 0.887 and an out-of-fold AUC of 0.877; the 5-variable model achieved an apparent AUC of 0.960 and an out-of-fold AUC of 0.938. This is exploratory internal validation; no external validation was performed. AUC, area under the curve; D-dimer, D-dimer concentration; ROC, receiver operating characteristic; SFV, superficial femoral vein. Please click here to view a larger version of this figure.
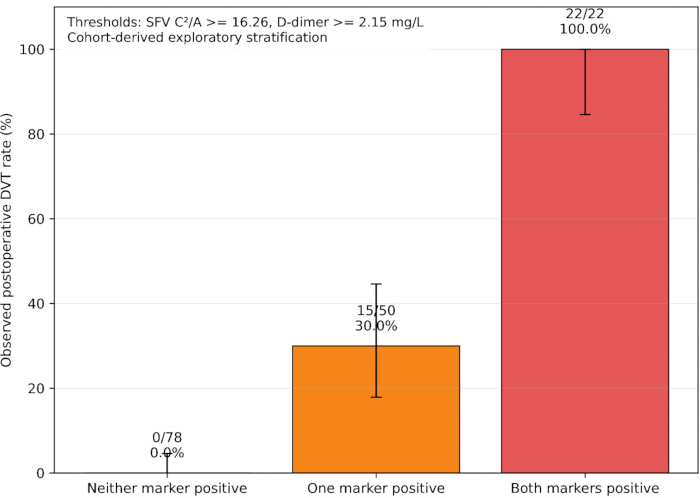
Figure 6: Exploratory three-strata postoperative DVT rates based on cohort-derived Youden thresholds. Patients were stratified using SFV C2/A ≥16.26 and D-dimer ≥2.15 mg/L FEU. Threshold-level values were classified as elevated. The observed DVT rates were 0/78 (0.0%; 95% CI, 0.0%–4.6%) with neither marker elevated, 15/50 (30.0%; 95% CI, 17.9%–44.6%) with one elevated, and 22/22 (100.0%; 95% CI, 84.6%–100.0%) with both elevated. This cohort-derived stratification is exploratory and is not externally validated. DVT, deep vein thrombosis; SFV, superficial femoral vein. Please click here to view a larger version of this figure.
Taken together, the results support an association between higher preoperative C2/A and postoperative DVT across all three venous segments. POV and CFV C2/A showed the strongest single-marker discrimination, while the prespecified SFV C2/A plus D-dimer model provides an exploratory assessment of complementary local morphology and systemic coagulation information.
DATA AVAILABILITY:
A de-identified individual-level numerical dataset, an accompanying data dictionary, and the analysis code are provided in Supplementary File 1.
Supplementary Table 1: Association between tourniquet duration and venous C2/A measurements. Please click here to download this file.
Supplementary File 1: Data supporting the findings of this study. Please click here to download this file.
Discussion
This prospective observational study found that higher preoperative venous C2/A was associated with postoperative lower-limb DVT after orthopedic surgery. After applying the explicit calculation rule uniformly to the retained C and A fields, POV and CFV C2/A provided the strongest single-marker discrimination. The originally specified SFV C2/A plus D-dimer model was retained without post hoc switching of venous segment and showed good apparent and internally cross-validated discrimination. All thresholds and risk strata were derived in the same small, single-center cohort. C2/A should therefore be interpreted as an exploratory adjunct to established risk assessment, including Caprini scoring5, rather than as a replacement or a basis for intensifying anticoagulation.
C2/A describes cross-sectional shape rather than diameter alone. For a given area, flattening or contour irregularity increases circumference and therefore increases C2/A. Such deformation may be associated with reduced venous compliance, external compression, disturbed flow distribution, and local stasis12. Within Virchow's triad, a high C2/A could represent a structural substrate for low shear and endothelial activation that acts together with postoperative hypercoagulability. This mechanistic interpretation is biologically plausible but remains an inference; the present study did not measure shear stress, endothelial biomarkers, or causal changes in venous wall function.
D-dimer reflects systemic fibrin formation and degradation, whereas C2/A may capture local venous geometry9. Their complementary biological domains provide a rationale for the stronger combined discrimination observed here15. Age-adjusted D-dimer strategies are useful for diagnostic exclusion of acute DVT, but they should not be transferred directly to preoperative risk prediction11. Likewise, this exploratory model should complement, not supplant, clinical assessment. Prospective impact studies would be required before using it to alter surveillance frequency or thromboprophylaxis because bleeding outcomes and treatment benefit were not evaluated.
Tourniquet duration was analyzed because it can influence perioperative venous flow, but the baseline C2/A measurement preceded tourniquet exposure. The observed associations between tourniquet variables and DVT or baseline C2/A are therefore non-causal and may reflect procedure type, patient selection, anesthesia, or thromboprophylaxis. Lower-limb DVT is also prognostically heterogeneous; thrombus location, symptoms, and concomitant superficial vein thrombosis can influence subsequent risk16. Future studies should record these features and compare contour-based C2/A with automated segmentation, venous compliance measures, three-dimensional imaging, and serial morphology.
This study has limitations. It included 150 patients and 37 DVT events at one orthopedic center; the 5-variable model had 7.4 events per variable and remains prone to overfitting. No external validation, calibration validation, or decision-curve analysis was available. The retained analysis dataset contained participant-level summary C and A fields rather than the three individual acquisition-level values; consequently, the revision applied the explicit formula to the retained summaries and could not quantify acquisition-level variability in C2/A. In addition, C and A were separate device-derived measurements rather than an exported perimeter-area pair from a shared digital contour. One physician performed the preoperative measurements, and formal intraobserver and interobserver reproducibility analyses were not prospectively performed. The intensified 12-h surveillance schedule may have increased detection of early or asymptomatic DVT relative to routine care and may limit clinical feasibility and generalizability. Procedure type, anesthesia, pharmacologic and mechanical prophylaxis, and other perioperative confounders were not fully modeled. Surveillance ended on postoperative day 7, limiting assessment of later thromboembolism, pulmonary embolism, and bleeding. The findings may not generalize to other surgical specialties or medical patients. Multicenter studies should retain acquisition-level measurements, prespecify blinded reliability testing, use routine-care-compatible surveillance, and perform external validation before clinical application.
Disclosures
The authors declare no conflicts of interest.
Acknowledgements
This work was supported by the National Natural Science Foundation of China (No. 82071932).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| C²/A calculation | Investigator-calculated | Not applicable | C and A were measured with the ultrasound system measurement package; C²/A was calculated as C² divided by A |
| Color Doppler ultrasound diagnostic system | Philips | CX50 | |
| D-DI2, Tina-quant D-Dimer Gen.2 | Roche Diagnostics | Material No. 07429410190 | |
| D-dimer analyzer | Roche Diagnostics | cobas t 711 coagulation analyzer | |
| IBM SPSS Statistics | IBM Corp. | Version 25.0 | RRID:SCR_016479. Used for the original statistical summaries. |
| L12-3 broadband linear-array ultrasound transducer | Philips | L12-3; 12–3 MHz | |
| Matplotlib | Matplotlib Development Team | Version 3.9.4 | RRID:SCR_008624. Used for figure generation in the revision analysis. |
| NumPy | NumPy Developers | Version 2.0.2 | RRID:SCR_008633. Used for numerical operations in the revision analysis. |
| openpyxl | openpyxl Developers | Version 3.1.5 | RRID not available. Used for spreadsheet input and output. |
| pandas | pandas Development Team | Version 2.3.3 | RRID:SCR_018214. Used for data handling and tabulation. |
| Python Programming Language | Python Software Foundation | Version 3.9.6 | RRID:SCR_008394. Runtime for the revision analysis. |
| scikit-learn | scikit-learn Developers | Version 1.6.1 | RRID:SCR_002577. Used for cross-validation and ROC modeling. |
| SciPy | SciPy Community | Version 1.13.1 | RRID:SCR_008058. Used for statistical tests. |
| statsmodels | statsmodels Developers | Version 0.14.6 | RRID:SCR_016074. Used for logistic regression and statistical utilities. |
References
- Lv B, Xue F, Shen YC, Hu FB, Pan MM. Pulmonary thromboembolism after distal ulna and radius fractures surgery: a case report and a literature review. World J Clin Cases. 2021;9(1):197-203.
- Liu F, Tan J, Pan Y. Prevention of deep vein thrombosis in postoperative orthopedic patients: a hybrid meta-analysis and clinical case study. Front Med (Lausanne). 2025;12:1603191.
- Sun Y, Zhao H, Gao Z, Li L. Safflower Yellow combined with low molecular weight heparin in preventing deep vein thrombosis after orthopaedic surgery: a meta-analysis and literature review. Altern Ther Health Med. 2024;30(11):276-281.
- Rostagno C, Gatti M, Cartei A, Civinini R. Early deep venous thrombosis after hip fracture surgery in patients in pharmacological prophylaxis. J Clin Med. 2025;14(3):726.
- Chen H, Sun L, Kong X. Risk assessment scales to predict risk of lower extremity deep vein thrombosis among multiple trauma patients: a prospective cohort study. BMC Emerg Med. 2023;23(1):144.
- Li J, et al. Clinical predictive factors of lower extremity deep vein thrombosis in relative high-risk patients after neurosurgery: a retrospective study. Dis Markers. 2020;2020:5820749.
- Dai X, et al. Predictive value of preoperative erythrocyte electrophoresis exponent for acute deep vein thrombosis after total knee arthroplasty in patients with knee osteoarthritis. J Orthop Surg Res. 2020;15(1):496.
- Shi Z, Zhang M, Dong X, Xu J. Serum lipoprotein (a) on postoperative day 3: a strong predictor of portal and/or splenic vein thrombosis in cirrhotic patients with splenectomy. Clin Appl Thromb Hemost. 2020;26:1076029620912020.
- Huang Y, et al. The value of D-dimer in the prognosis of dilated cardiomyopathy: a retrospective cohort study. Sci Rep. 2024;14(1):26806.
- Lin Y, et al. Predictive value of combining Padua score with D-dimer for deep vein thrombosis in acute ischemic stroke patients with alteplase. Clin Lab. 2025;71(9):1717.
- Righini M, et al. Age-adjusted D-dimer cutoff levels to rule out pulmonary embolism: the ADJUST-PE study. JAMA. 2014;311(11):1117-1124.
- Chen X, et al. Impact of combining ultrasound parameter and the Caprini score on predicting lower extremity deep venous thrombosis after orthopedic surgery. Ann Ital Chir. 2025;96(3):380-390.
- Matei SC, et al. Impact of statin treatment on patients diagnosed with chronic venous disease: morphological analysis of the venous wall and clinical implications. Phlebology. 2022;37(3):188-95.
- Sheng J, Han X, Zheng H, Ma H. Combined assessment of Caprini score, D-dimer, and thromboelastography for predicting deep venous thrombosis in lung cancer patients. Am J Cancer Res. 2025;15(7):3299-3309.
- Hong Y, et al. The effect of portable intermittent pneumatic compression devices in preventing lower limb deep vein thrombosis in patients undergoing major orthopedic surgery: a quasi-experimental multicenter study. Int J Orthop Trauma Nurs. 2026;61:101279.
- Dubois-Silva A, et al. Prognostic significance of concomitant superficial vein thrombosis in patients with deep vein thrombosis of the lower limbs. Thromb Haemost. 2021;121(12):1650-1659.