This case presents the successful multidisciplinary management of recurrent perineal urethral squamous cell carcinoma involving robot-assisted radical Cystoprostatovesicourethrectomy and gracilis muscle flap reconstruction.
Case Report
Recurrent Perineal Urethral Squamous Cell Carcinoma Multidisciplinary Approach
In This Article
Summary
Abstract
Perineal recurrence of urethral squamous cell carcinoma (SCC) after radical penectomy is a rare and technically demanding entity, and non-surgical modalities such as radiotherapy or systemic chemotherapy may not achieve optimal local control in this setting, necessitating aggressive surgical resection combined with complex reconstructive techniques. We report the multidisciplinary management of an extensive perineal recurrence in a 56-year-old male with a history of primary urethral SCC (pT2 pN0 G2, first diagnosed in 2013) treated by radical penectomy and bilateral inguinal lymphadenectomy, who presented in April 2021 with perineal tumor recurrence. After an endoscopic and diagnostic evaluation, a perineal resection was performed, resulting in rpT4 G2 with positive surgical margins cranially toward the bladder and ventrally toward the symphysis. Complete tumor resection was deemed unachievable in that conventional way. After further consultation, the patient underwent robot-assisted radical Cystoprostatovesicourethrectomy with en bloc perineal tumor excision, bilateral pelvic and salvage inguinal lymphadenectomy with ICG-guided lymphangiography, prophylactic appendectomy, urinary and stool diversion via ileal conduit and colostomy. Histopathology confirmed R0 resection. Three weeks after the initial ablative surgery, the resulting large perineal defect, extending from the symphysis anteriorly to the rectum posteriorly, was closed with a left pedicled gracilis muscle flap. The 5-year follow-up was oncologically and functionally uneventful (last CT 03/2026). This case underscores the importance of interdisciplinary management involving urology, visceral surgery, reconstructive surgery, and radiology. It also highlights the benefits of integrating minimally invasive robotic techniques.
Introduction
Primary urethral carcinoma is a rare malignancy, accounting for less than 1% of all genitourinary tumors1. Squamous cell carcinoma (SCC) represents approximately 16%–34% of urethral carcinoma cases in men, often associated with chronic irritation or infection2.
The annual incidence is approximately 4.3 per million in males and 1.5 per million in females, with higher rates in elderly patients and African Americans3. In proximal urethral SCC, radical surgery provides control over the local disease, but even with systemic therapy, it is linked to poor survival and a high risk of distant metastasis4.
The EAU guidelines recommend that all patients with locally advanced disease (≥T3N0-2M0) be discussed within a multidisciplinary team5, for men with locally advanced squamous cell carcinoma, curative radiotherapy combined with radio-sensitizing chemotherapy can be offered as a definitive treatment. In cases of local urethral recurrence, both salvage surgery and radiotherapy may be considered5.
Furthermore, for locally advanced urethral squamous cell carcinoma, the EAU guidelines recommend considering cisplatin-based neoadjuvant chemotherapy prior to radical surgery. This recommendation is supported by retrospective series demonstrating that neoadjuvant chemotherapy is associated with improved relapse-free and overall survival in patients with locally advanced disease, whereas adjuvant chemotherapy has not consistently demonstrated an overall survival benefit6. In a 27-year institutional experience, 45.7% of patients with primary urethral SCC received neoadjuvant chemotherapy, with 5-year recurrence-free and overall survival rates of 56.8% and 93.8%, respectively7. Furthermore, platinum-containing neoadjuvant regimens have demonstrated a response rate of 72% in advanced urethral carcinomas8. However, the rarity of this disease precludes prospective randomized trials, and treatment decisions must be individualized within a multidisciplinary framework9.
In cases of non-muscle-invasive and locally confined muscle-invasive urothelial bladder cancer, Del Giudice et al. found that urethrectomy can be safely postponed unless urothelial disease is explicitly identified before or during surgery, without affecting survival rates, and with the benefit of reducing surgical complications at the time of radical cystectomy10.
Perineal recurrence after prior radical surgery (penectomy and urethrectomy) is particularly challenging due to extensive local invasion, prior lymphadenectomy, contamination risk, and the creation of large soft-tissue defects that are difficult to close primarily9. For the resulting perineal defect, temporary negative pressure wound therapy (NPWT) promotes granulation tissue formation and prepares the wound bed, while a pedicled gracilis muscle flap provides well-vascularized, bulky tissue coverage with low donor-site morbidity and high success rates, thereby shortening the time to heal the perineal defect via secondary intention11,12.
It is essential, however, to recognize that this ultraradical, multidisciplinary strategy is resource-intensive and demands a high level of institutional expertise. Successful execution requires the coordinated availability of robotic pelvic surgery, reconstructive microsurgery, interventional radiology, specialized stoma therapy, and intensive care support. Consequently, this approach is primarily applicable to referral centers with established multidisciplinary teams and should not be generalized to all perineal recurrences without rigorous preoperative patient selection. The following case presentation illustrates the technical feasibility and oncological potential of this strategy, while acknowledging that the single-case nature of the evidence precludes broad generalizability.
Case presentation:
The patient is a 56-year-old male in good performance status and normal habitus with a history of hypospadias and surgical correction. The patient had numerous urethral fistulas and perineal abscesses, and after many endoscopic urethral stenosis interventions and 2 mesh-graft urethroplasties, he received an infravesical urinary diversion through a perineal Boutonière. In 2013, urethral cancer was identified in the distal penile urethra. A radical penectomy, followed by inguinal lymphadenectomy (right 7 LN, left 11 LN), and due to suspected LN in follow-up, a secondary right supraininguinal lymphadenectomy (5 LN) was performed. The histological result was pT2 pN0 (0/23) cM0 R0 G2. Later, due to abscesses in the Boutonière region, the urine was diverted via a suprapubic catheter (SPC). Again in 2019, he developed an abscess in the perineum with an MRSA colony, which was drained successfully. In April 2021, he presented with a large symptomatic perineal mass. The clinical examination and multi-resonance imaging (MRI) confirmed the diagnosis of a ca. 6 cm local recurrence of the known 2013 urethral SCC (Figure 1 and Figure 2). The tumor was resected via perineal resection, but surgical margins remained positive. After thorough consultation with the patients, we opted for a more radical approach and proceeded with the recommended extensive surgery.
Diagnosis, assessment, and plan:
Clinical examination showed a large local recurrence in the perineum in the region of the Boutonière. The radical penectomy scar was normal. The anus was also intact. We tested a suspected inguinal LN on the left side. Otherwise, the bilateral inguinal scars of the lymphadenectomy were also normal. A biopsy confirmed the malignant nature of the mass.
Contrast-enhanced computed tomography (CT) showed no distant metastases. An MRI revealed a well-circumscribed, solid midline mass localized to the perineal/urethral region. The lesion was situated anterior to the rectum and posterior to the symphysis pubis, occupying the periurethral space and displaying intermediate signal intensity on T2-weighted sequences. A preserved fat plane was present between the posterior aspect of the mass and the anterior rectal wall, suggesting a lack of direct rectal invasion. The surrounding pelvic floor musculature and ischiorectal fossae appeared uninvolved (Figure 1 and Figure 2).
A perineal resection was performed, resulting in rpT2 cN0 c M0 G2 (UICC stage IV) with positive surgical margins cranially toward the bladder and ventrally toward the symphysis. Complete tumor resection was deemed unachievable in that conventional way. The patient was presented at a multidisciplinary board meeting to determine the treatment plan. After the perineal tumor excision failed to achieve the negative surgical margins, the need for more radical intervention was deemed necessary. With Radical prostatectomy alone, the radicality of the intervention could be achieved. Yet, in the urinary-diverted relatively young patient with SPC, a secondary SCC in the bladder was a matter of time, let alone the complications associated with dislocations, obstruction, and catheter-associated infection of the SPC.
After an interdisciplinary case presentation, the planned strategy included a robot-assisted radical Cystoprostatovesicourethrectomy with en bloc perineal tumor excision, bilateral pelvic removal, and removal of the suspected left-sided inguinal lymph node, appendectomy, urinary and stool diversion via ileal conduit, and temporary colostomy. A plastic surgery consultation was obtained preoperatively for pedicled gracilis flap reconstruction. The rationale was to achieve R0 resection while minimizing morbidity through minimally invasive techniques and accelerating the perineal healing processes through reconstructive intervention.
Multiple preoperative trials to sanitize MRSA colonization in the SPC area and to analyze the results were unsuccessful. Therefore, another trial postoperatively was planned.
Protocol
The study complies with the Declaration of Helsinki and was approved by the ethics committees of the Westfalen-Lippe Medical Association and the University of Muenster (2023–500-f-S) for retrospective data management. The patient consented in writing to all treatment steps and anonymous publication. The reagents and the equipment used are listed in the Table of Materials.
1. Robot-assisted radical Cystoprostatovesicourethrectomy and perineal tumor excision
- Preoperative planning and patient preparation
- Anesthesia and intensive care teams were consulted for preoperative risk assessment.
- Two blood units were prepared. No bowel preparation was performed according to institutional standards.
- A broad-spectrum antibiotic with cephalosporin and metronidazole was administered perioperatively and continued for 1 week.
- Patient positioning
- The patient was carefully positioned in the lithotomy position with a Trendelenburg tilt. This positioning provided optimal access to both the abdominal and perineal fields.
2. Establishment of the capnoperitoneum, Trocar placement, and robotic docking
- Establishment of the capnoperitoneum
- Pneumoperitoneum was established through minilaparotomy at the supraumbilical site.
- Insufflation pressure was initially set to 12 mmHg and maintained at 8 mmHg during the procedure to minimize cardiopulmonary compromise while providing adequate working space.
- Trocar placement.
- A transperitoneal approach was utilized to maximize working space and to enable a better understanding of the abdominal anatomy.
- Standard cystectomy robotic trocar (8 mm) placement was performed, including a supraumbilical camera port and bilateral working ports, placed under direct visualization, lateral to the rectus muscles at the level of the umbilicus, with 8 cm between the trocars. The third arm was placed on the left side. All these trocars were placed in a horizontal line crossing above the umbilicus.
- Two assistant trocars (12 mm) were placed on the right side. The first one was placed between the camera port and the right-sided robotic trocar. The second one is in the right lower abdominal quadrant.
- Robotic docking
- The robotic surgical system was docked between the patient's legs to allow deep pelvic access through to the perineum.
3. The radical surgery
- After identifying and resecting the distal parts of both ureters, a systematic mobilization of the bladder and prostate was undertaken, with sharp and blunt dissection using the robotic monopolar scissors to deal with dense adhesions from previous surgeries.
- The blood supply of both bladder and prostate was secured using clips and then transected. The neurovascular bundles were preserved. The prostate and perineal tumor were carefully dissected from the rectum with the monopolar scissors, leaving them intact. This was followed by en bloc resection of the remaining perineal tumor mass, ensuring wide radial margins around the recurrent squamous cell carcinoma while preserving critical neurovascular structures where possible and minimizing the risk of tumor dissemination.
- The perineal defect was closed from the abdominal aspect using a 3-0 barbed suture to approximate the levator ani fibers to close the defect and achieve sufficient bleeding control.
- Bilateral pelvic lymphadenectomy was performed using the robotic monopolar scissors and bipolar forceps to achieve thorough oncologic staging and remove any potential micrometastatic disease, with meticulous clipping of lymphatic vessels to reduce the subsequent risk of lymphocele formation.
- Inguinal lymphadenectomy was performed open surgically through an inguinal incision. The lymphatic vessels were meticulously ligated when visible.
- The left-sided suspected Lymph node was removed via open surgical excision.
- The urinary diversion was established via creation of an ileal conduit. An endo-stapler was utilized to harvest the 20 cm ileal segment, 20 cm proximal from the ileocecal valve. A reinforcement suture for the enterotomy was not performed in accordance with institutional standards.
- The mesenteric window of the ileal conduit segment was closed with monofilament 3-0 suture. The left ureter was brought under the sigmoid colon through a mesenteric tunnel. A Wallace technique was used to connect both ureters with 5-0 monofilament suture. The ureteroentro anastomosis was done with a 4-0 barbed suture.
- The fecal diversion was achieved through the formation of an end colostomy, also with an endo-stapler. These diversions were strategically chosen to separate urinary and fecal streams, thereby significantly reducing the risk of contamination and infection in the large perineal wound.
- 15 Chariere-Robinson drains were inserted: an abdominal drain and two bilaterally inguinal drains. The abdominal drain was removed on postoperative day 1 (POD1) after the creatinine value of the drain exudate was plasma-equivalent. The inguinal drains were removed in the second postoperative week, after the exudate volume fell below 30 mL per day.
- The patient was allowed to drink on the day of surgery. On the first postoperative day, a gradual diet consisted of fluid foods and yogurt, then escalated to a normal diet on POD 2 and 3.
4. Perineal wound management with negative pressure wound therapy (NPWT)
NOTE: Rationale: management of the resulting large, contaminated soft-tissue defect in a perineal field complicated by MRSA colonization and high bacterial load required a staged approach. Negative pressure wound therapy (NPWT) served as an effective bridge, promoting granulation, reducing edema, and preparing a clean, vascularized wound bed for definitive reconstruction.
- Immediately following tumor resection and hemostasis, a vac system was applied directly to the extensive perineal defect. Continuous NaCl instillation and negative-pressure settings (-125 mmHg) were optimized to facilitate exudate removal, reduce bacterial colonization, and stimulate angiogenesis in this high-risk area.
- Serial operative debridement combined with dressing changes was performed on postoperative days 4, 8, 10, and 17. Each session involved careful assessment and removal of any remaining necrotic or fibrinous tissue under appropriate anesthesia. This progressive approach promoted the development of healthy, robust granulation tissue, optimized the wound environment, and significantly reduced the risk of flap failure during subsequent reconstruction.
5. Gracilis muscle flap reconstruction
- The pedicled gracilis muscle flap was selected for its reliable vascular anatomy, sufficient bulk to obliterate dead space, excellent reach to the perineum, and low donor-site morbidity. This reconstructive step was essential to provide durable, well-vascularized coverage over exposed pelvic organs, prevent perineal hernia, and restore functional and aesthetic integrity of the perineum.
- The urinary diversion with ileal conduit, alongside the fecal diversion with colostomy and the NPWT, allowed successful sanitation of MRSA colonization after surgery, facilitating the flap reconstruction.
- Serial wound assessment during the negative pressure wound therapy phase demonstrated the progressive development of a well-vascularized, fibrin-covered granulation tissue base, with no evidence of necrotic debris, purulent exudate, or surrounding cellulitis. These findings were consistent with adequate wound bed preparation and supported the decision to proceed with the flap reconstruction.
- Harvest of the left gracilis muscle was performed through a longitudinal medial thigh incision. The muscle was carefully mobilized while preserving the dominant proximal vascular pedicle (medial circumflex femoral artery and venae comitantes) to ensure robust perfusion. Distal tendinous insertions were divided, and motor nerve branches were sacrificed as needed for flap mobility.
- The flap was then rotated and tunneled subcutaneously without tension through a generous tunnel to reach the perineal defect. It was meticulously secured with multiple interrupted absorbable sutures to fill all dead space, cover critical structures, and provide a stable platform for skin grafting or secondary closure if required.
- Layered closure of both the donor site and recipient perineal wound was completed over drains. Strict postoperative immobilization with restricted hip abduction and flexion was maintained for 4 weeks to protect the vascular pedicle, prevent tension or kinking, and optimize flap integration and healing.
Results
Histopathology confirmed R0 resection with rpT4 pN0 (0/14) cM0 R0 G3. The ablative surgery took almost 3 h and 30 min, and minimal blood loss was noted. Flatus was noted on postoperative day (POD) 2, and a bowel movement on POD 3. The patient was discharged from the urological department 10 days after surgery and referred to the reconstructive surgery department, from which he was discharged on postoperative day 36. Serial wound assessments during the NPWT phase demonstrated progressive granulation tissue formation, with the wound bed transitioning from a primarily fibrinous, exudative surface at baseline to a well-vascularized, clean granulation base by POD 17, confirming adequate wound bed preparation for flap reconstruction. The gracilis flap integrated well, providing stable perineal coverage. Readmission for an infected pelvic lymphocele (Staphylococcus aureus) was managed successfully with CT-guided drainage and antibiotics, resulting in complete resolution. At the 5-year follow-up (last CT scan, March 2026), the patient remained free of local recurrence and distant metastasis, with no evidence of regional lymphadenopathy. Functionally, the patient reported satisfactory urinary diversion via the ileal conduit and stable fecal diversion through the end colostomy, with no episodes of stomal stenosis, parastomal hernia, or recurrent urinary tract infections requiring hospitalization. Furthermore, the patient was offered a colostomy reversal, which he declined. The perineal reconstruction remained stable, with no signs of flap compromise, wound breakdown, or perineal hernia. The patient maintained an ECOG performance status of 0, with full ambulation and independence in activities of daily living (Figure 3).
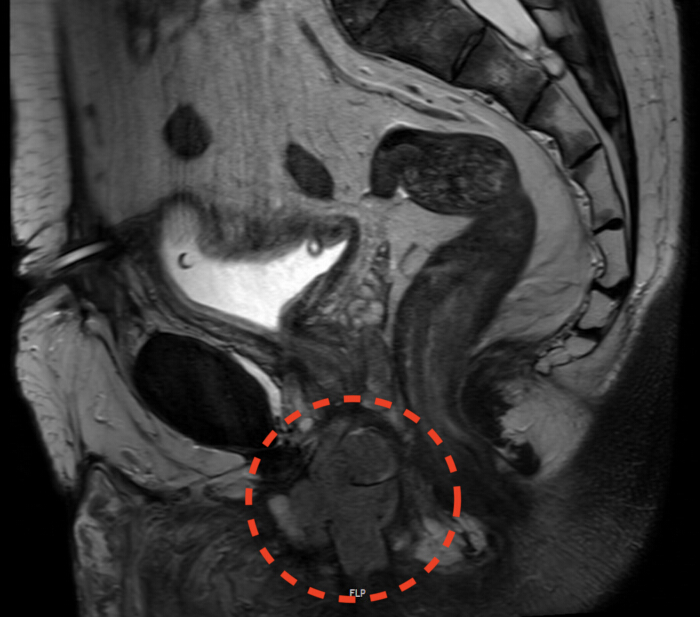
Figure 1: Sagittal magnetic resonance image of the recurrent urethral tumor (April 2021). Sagittal T2-weighted magnetic resonance image demonstrating a well-circumscribed solid midline mass in the perineal/urethral region. The lesion is located anterior to the rectum and posterior to the pubic symphysis, occupying the periurethral space and exhibiting intermediate T2 signal intensity. Please click here to view a larger version of this figure.
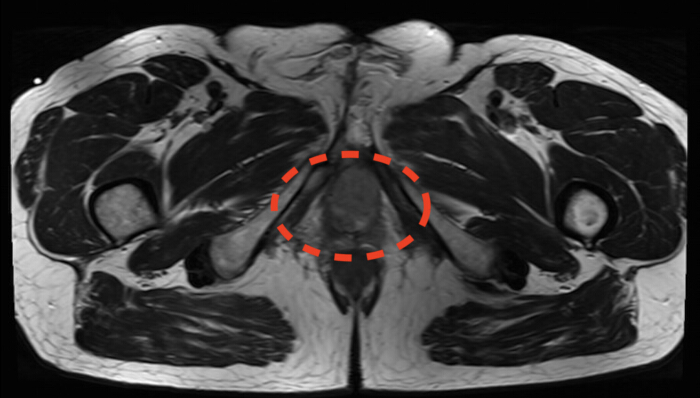
Figure 2: Axial magnetic resonance image of the recurrent urethral tumor (April 2021). Axial magnetic resonance image demonstrating a preserved fat plane between the posterior aspect of the tumor and the anterior rectal wall, suggesting the absence of direct rectal invasion. The pelvic floor musculature and ischiorectal fossae appear uninvolved. Please click here to view a larger version of this figure.
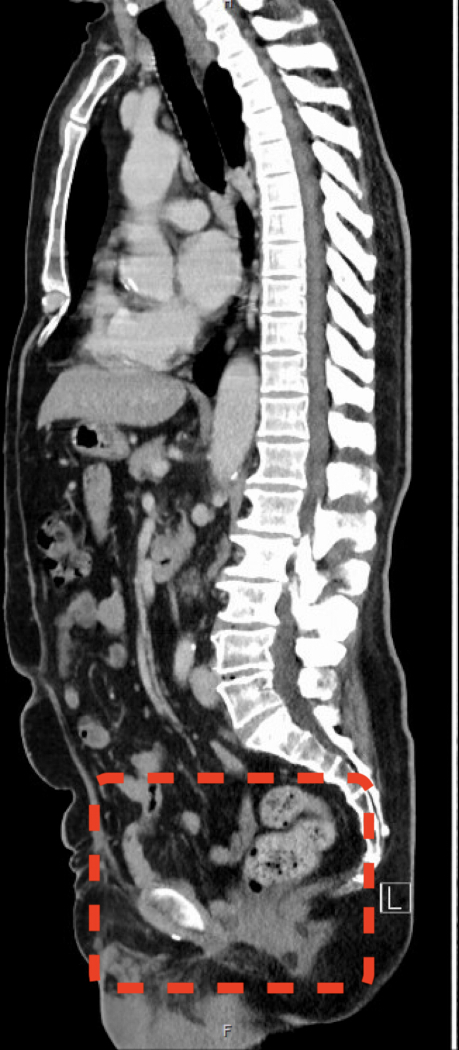
Figure 3: Sagittal computed tomography image of the pelvis and perineum during follow-up (March 2026). Sagittal computed tomography image obtained during routine follow-up demonstrating a tumor-free surgical site, with no evidence of local recurrence, abscess formation, or regional lymph node metastasis. Please click here to view a larger version of this figure.
| Challenge | Prevention | Management |
| wound contamination | Perioperative culture-directed antibiotics; NPWT with instillation (-125 mmHg); serial debridement | Delayed flap until negative cultures + healthy granulation tissue; colostomy diverts fecal stream |
| MRSA-colonisation | Preoperative decolonization trial (e.g., topical antiseptics, targeted antibiotics) | If decolonization fails preoperatively, urinary/fecal diversion and NPWT facilitate postoperative eradication |
| Pelvic/inguinal lymphocele | Meticulous ligation/clipping of lymphatics; bipolar coagulation; pelvic drain (remove when output <30 ml/day) | CT-guided drainage + culture-directed antibiotics; sclerotherapy/surgical marsupialization if refractory |
| Gracilis flap tension/congestion | Dissect pedicle to origin; create generous subcutaneous tunnel (≥4–5 cm); confirm perfusion (ICG if available) | Secure without tension; careful postoperative hip mobilization (restricted abduction/flexion × 4 weeks) |
Table 1: Troubleshooting guide for common challenges.
Discussion
This case demonstrates the value of a coordinated, multidisciplinary approach to recurrent perineal urethral SCC, a rare and aggressive disease with limited high-level evidence to guide management13. Robot-assisted techniques facilitated precise oncologic resection, while NPWT effectively bridged the large defect by promoting granulation and reducing the risk of infection14. Subsequent gracilis muscle flap reconstruction provided robust, vascularized coverage with high long-term success rates and minimal donor-site morbidity, even in complex perineal wounds15,16.
After the initial perineal resection yielded positive margins (cranially toward the bladder and ventrally toward the symphysis), conventional salvage options were exhausted. Given the patient’s history of long-term suprapubic diversion and the inherent risk of secondary malignancy in a chronically irritated bladder, a robot‑assisted radical cystoprostatovesicourethrectomy was chosen over prostatectomy alone. This ultraradical approach achieved R0 resection, eliminated the defunctionalized bladder as a future cancer risk, and addressed the positive deep margins in a single en bloc procedure.
Furthermore, the patient’s clinical course, spanning hypospadias repair, recurrent urethral fistulas and abscesses, multiple endoscopic stricture interventions, two mesh‑graft urethroplasties, and a perineal Boutonière diversion, represents a textbook example of chronic mucosal irritation and infection. Prolonged inflammation, especially in the setting of MRSA colonization and repeated surgical trauma, likely induced squamous metaplasia and subsequent malignant transformation. This case supports the emerging recognition that long‑standing infectious and foreign‑body inflammation is a significant risk factor for urethral SCC, independent of classic human papillomavirus association17,18.
After tumor extirpation, the large perineal defect with a contaminated field and MRSA history required robust vascularized tissue. The pedicled gracilis flap was selected over alternatives (e.g., VRAM or gluteal fold flap) because it offers: a reliable dominant vascular pedicle, sufficient muscle bulk to obliterate dead space and protect the pelvic floor, low donor-site morbidity, a well-hidden thigh incision, and proven efficacy in infected wounds15. Staged negative-pressure wound therapy served as an effective bridge, preparing the wound bed and reducing the bacterial load before definitive flap coverage14.
The management of locally recurrent urethral SCC is guided by the EAU guidelines5, which strongly advocate for multidisciplinary decision-making and acknowledge the role of cisplatin-based neoadjuvant chemotherapy and definitive chemoradiotherapy for select patients. However, published surgical series underscore the poor prognosis of proximal disease, with 5-year overall survival ranging from 10% to 60% depending on the extent of resection and use of systemic therapy6,7. In this case, definitive chemoradiotherapy was considered. Still, it ultimately deferred due to the patient's prior perineal surgery with positive margins, extensive perineal scarring, MRSA colonization, and the presence of a long-term defunctionalized bladder. These factors predispose to poor radiation tolerance and secondary malignancy risk. Consequently, a robotically assisted radical en bloc resection, followed by staged gracilis flap reconstruction, was selected to achieve the only potentially curative option: an R0 resection. This approach aligns with the EAU recommendation for salvage surgery in recurrent disease and resulted in a 5-year disease-free survival rate that compares favorably with published series of locally advanced urethral SCC7. Based on our experience, Table 1 summarizes common challenges that may be encountered with this approach, along with practical strategies for managing them.
Limitations
Several limitations warrant consideration. This single-case report is subject to selection bias, and the favorable outcome may reflect patient-specific factors not generalizable to broader populations. The approach is resource-intensive, requiring coordinated availability of robotic pelvic surgery, general surgery, reconstructive surgery, interventional radiology, stoma therapy, and intensive care, expertise typically limited to high-volume centers. The surgeon who carried out this case has experience with ~3,000 robotic procedures, and performing such cases requires advanced skills that may not be replicable by all surgeons. Although the patient remains disease-free at 5 years, this follow-up is modest for a recurrent SCC with known late recurrence risk. We did not employ validated PROMs to systematically assess quality of life, body image, or sexual function. The absence of a comparator arm precludes direct comparison with alternative strategies. The patient did not receive neoadjuvant chemotherapy, since the suspicion preoperatively was of a locally confined disease not requiring systemic therapy. Finally, as a positive-outcome case report, this manuscript is subject to publication bias, which may overstate success rates.
Future directions
The rarity of recurrent urethral SCC highlights several research priorities: prospective registries; future trials should investigate immunotherapy (PD-1/PD-L1 inhibitors), ctDNA as a biomarker for minimal residual disease, and pCR as a surrogate endpoint. Reconstructive Research: Comparative studies of flap types should assess donor-site morbidity, functional outcomes, and QoL. Modern Radiotherapies may reduce toxicity while achieving sufficient tumor control. Finally, this patient’s extensive history of urethral inflammation suggests that investigating inflammation-driven carcinogenesis, the immune microenvironment, and microbiome composition through translational research may reveal novel therapeutic targets.
Disclosures
The authors have nothing to disclose. The authors used a language model (Gemini) exclusively for language polishing and grammatical refinement. All scientific content was controlled, verified, and approved by the authors, who assume full responsibility for the final manuscript.
Acknowledgements
The authors thank the entire multidisciplinary team (urology, general surgery, interventional radiology, and pathology) for their collaborative care. No external funding was received for this work.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| da Vinci Xi Surgical System | Intuitive Surgical | www.intuitive.com | |
| Monopolar Curved Scissors | Intuitive Surgical | www.intuitive.com | |
| Maryland Bipolar Forceps | Intuitive Surgical | www.intuitive.com | |
| Hem-o-lok Clips | Teleflex | www.teleflex.com | |
| V-Loc Barbed Suture | Medtronic | www.medtronic.com | |
| Endo GIA Stapler | Medtronic | www.medtronic.com | |
| Veraflo NPWT System | Solventum (3M) | www.solventum.com | |
| Chariere-Robinson Drain | — | www.convatec.com (or the actual manufacturer used) | |
| 8 mm Robotic Trocar | Intuitive Surgical | www.intuitive.com | |
| 12 mm Assistant Trocar | — | www.medtronic.com (or manufacturer used) | |
| 3-0 Monofilament Suture | Ethicon | www.ethicon.com | |
| 4-0 Barbed Suture | Medtronic | www.medtronic.com | |
| 5-0 Monofilament Suture | Ethicon | www.ethicon.com | |
| Normal Saline | — | www.baxter.com (or manufacturer used) |
References
- Wnętrzak I, et al. Epidemiology of primary urethral cancer: insights from four European countries with a focus on Poland. Cancers (Basel). 2026;18(2):290.
- Aleksic I, et al. Primary urethral carcinoma: a Surveillance, Epidemiology, and End Results data analysis identifying predictors of cancer-specific survival. Urol Ann. 2018;10(2):170-174.
- Wenzel M, et al. Incidence rates and contemporary trends in primary urethral cancer. Cancer Causes Control. 2021;32(6):627-634.
- Castiglione F, et al. Primary squamous cell carcinoma of the male proximal urethra: outcomes from a single centre. Eur Urol Focus. 2021;7(1):163-169.
- Gakis G, et al. European Association of Urology guidelines on primary urethral carcinoma: 2020 update. Eur Urol Oncol. 2020;3(4):424-432.
- Aijaz P, et al. A systematic review of the clinical features, management, and outcomes in urethral squamous cell carcinoma. Cureus. 2025;17(12):e100444.
- Zahir M, Doshi C, Escobar D, Daneshmand S. Primary urethral squamous cell carcinoma: insights and outcomes from a 27-year institutional experience. J Clin Oncol. 2026;44(7 Suppl):627.
- Dayyani F, et al. Retrospective analysis of survival outcomes and the role of cisplatin-based chemotherapy in patients with urethral carcinomas referred to medical oncologists. Urol Oncol. 2013;31(7):1171-1177.
- Janisch F, et al. Current disease management of primary urethral carcinoma. Eur Urol Focus. 2019;5(5):722-734.
- Del Giudice F, et al. Delayed versus concomitant urethrectomy for non-metastatic urothelial carcinoma of the urinary bladder undergoing radical cystectomy: perioperative and survival outcomes from a single tertiary centre in the United Kingdom. J Pers Med. 2025;15(8):375.
- Walma MS, Burbach JP, Verheijen PM, Pronk A, van Grevenstein WM. Vacuum-assisted closure therapy for infected perineal wounds after abdominoperineal resection: a retrospective cohort study. Int J Surg. 2016;26:18-24.
- Rinkinen JR, et al. Long-term outcomes analysis of flap-based perineal reconstruction. J Gastrointest Surg. 2024;28(1):57-63.
- Laukhtina E, et al. Follow-up of the urethra and management of urethral recurrence after radical cystectomy: a systematic review and proposal of a management algorithm by the European Association of Urology Young Academic Urologists Urothelial Carcinoma Working Group. Eur Urol Focus. 2022;8(6):1635-1642.
- Cahill C, Fowler A, Williams LJ. The application of incisional negative pressure wound therapy for perineal wounds: a systematic review. Int Wound J. 2018;15(5):740-748.
- Felmerer G, et al. Effectiveness and outcome of gracilis muscle flap reconstruction following perineal surgery: a retrospective single-center cohort study. Ann Med Surg (Lond). 2026;88(2):1255-1263.
- Thiele JR, et al. Reconstruction of perineal defects: a comparison of the myocutaneous gracilis and the gluteal fold flap in interdisciplinary anorectal tumor resection. Front Oncol. 2020;10:668.
- Francis S, et al. Implant-associated malignancies in the genitourinary system: a comprehensive review of evidence and gaps. Int Urol Nephrol. 2026;58(3):803-810.
- Velazquez EF, et al. Epithelial abnormalities and precancerous lesions of the anterior urethra in patients with penile carcinoma: a report of 89 cases. Mod Pathol. 2005;18(7):917-923.
Reprints and Permissions
This article has been published
Video Coming Soon