This study assessed the prevalence and risk factors of iron deficiency anemia among pregnant women in Bisha, Saudi Arabia. IDA was common during the second trimester and associated with rural residence, family history, and low intake of red meat, poultry, and citrus fruits. Affected women commonly experienced fatigue and dizziness.
Research Article
Iron Deficiency Anemia in Pregnancy: Status and Contributing Factors Among Women in Northern Asir, Saudi Arabia
In This Article
Summary
Abstract
Iron deficiency anemia (IDA) is a common nutritional disorder during pregnancy and is linked to adverse maternal and fetal outcomes. Beyond hematological markers, understanding related sociodemographic, dietary, and clinical factors is important for prevention.
This study aimed to assess iron status and examine associations between sociodemographic characteristics, dietary habits, clinical factors, and IDA among pregnant women in Bisha, Saudi Arabia. A cross-sectional study was conducted from December 2022 to May 2023 at the Maternity and Children’s Hospital in Bisha. The study included 135 pregnant women and 65 non-pregnant controls. Data was collected using a validated questionnaire covering demographics, diet, and clinical history. Blood samples were analyzed to measure hemoglobin, serum iron, ferritin, total and unsaturated iron-binding capacity, and transferrin saturation. Multivariate logistic regression identified independent risk factors for IDA. IDA was highly prevalent among pregnant women, particularly in the second trimester. Compared with controls, affected women had lower hemoglobin, serum iron, ferritin, and transferrin saturation, and higher iron-binding capacity. Lower intake of red meat, poultry, and citrus fruits, rural residence, and family history of anemia were independently associated with IDA. Fatigue and dizziness were more common among affected women.
Introduction
Anemia is defined as a reduction in hemoglobin concentration, which in severe cases compromises oxygen delivery to vital organs1. It affects individuals across all age groups, although infants and pregnant women are particularly vulnerable1. Mild anemia may remain asymptomatic, whereas moderate to severe forms commonly present with fatigue, weakness, dizziness, and pallor. When left untreated, anemia is associated with reduced physical capacity, impaired cognitive development, increased susceptibility to infections during childhood, and unfavorable maternal and fetal outcomes during pregnancy2,3. Iron deficiency anemia (IDA), the most common type of anemia, arises from depleted iron stores that result in diminished hemoglobin synthesis4,5. It is recognized as the most prevalent nutritional disorder worldwide and in the Eastern Mediterranean Region (EMR), according to the World Health Organization (WHO)6. An estimated 149 million individuals in the EMR are affected by iron deficiency or anemia, including approximately 83 million women6,7. In the Gulf countries, the prevalence of anemia among women of reproductive age ranges from 15% to 48%8. In Saudi Arabia, IDA represents a major public health concern, with reported prevalence rates ranging from 28% to 42%9. A survey conducted among schoolgirls in Riyadh reported a prevalence of 40.5% among adolescents aged 16–18 years10. Reducing the burden of IDA among women of childbearing age remains a critical health priority, as it is strongly associated with increased maternal morbidity, prenatal mortality, and adverse fetal outcomes4,5.
Globally, anemia has received considerable attention within public health initiatives. WHO and the United Nations International Children's Emergency Fund (UNICEF) established targets to eliminate iron deficiency by the year 2000, and the 1992 International Conference on Nutrition emphasized reducing IDA among women of reproductive age by one-third compared with 1990 levels6,11. Despite these international efforts, IDA continues to represent a significant health challenge, particularly in low- and middle-income countries where nutritional deficiencies and limited access to healthcare services are common. The etiology of IDA is multifactorial. Inadequate consumption of iron-rich foods remains a leading cause globally and is often compounded by reduced iron absorption due to dietary inhibitors such as tea12,13. Among women of reproductive age, excessive menstrual blood loss is a frequent contributing factor, while gastrointestinal disorders are more commonly implicated in postmenopausal women and men14. During pregnancy, increased physiological iron requirements further increase the likelihood of deficiency, particularly when iron stores prior to conception are insufficient6,11.
Local evidence underscores the burden of IDA in Saudi Arabia; however, most studies have focused on children, adolescents, or women in general rather than specifically on pregnant women. A recent study conducted in Bisha reported high rates of anemia among children under 10 years of age and among females, but pregnant women were excluded from the analysis15. This gap in evidence is notable, as pregnancy is a period of increased vulnerability to iron deficiency, with important implications for both maternal and neonatal health16. Given the magnitude of the problem and the limited research focused on pregnant women in the Northern Asir region, further investigation is needed. Examining the prevalence of IDA in this population and identifying factors associated with it, such as age, education, place of residence, dietary practices, and family history, is important for informing appropriate prevention and intervention strategies.
Based on the high burden of IDA reported among pregnant women in Saudi Arabia and the influence of sociodemographic, dietary, and obstetric factors on maternal iron status, this study hypothesized that iron deficiency anemia is highly prevalent among pregnant women in Northern Asir and is associated with modifiable nutritional and demographic risk factors. Accordingly, the present study aimed to assess iron status and examine factors associated with iron deficiency among pregnant women attending the Maternity and Children’s Hospital in Bisha, Northern Asir, Saudi Arabia.
Protocol
Ethical statement: The study was performed in accordance with the institutional guidelines and the ethical principles of the Declaration of Helsinki. Ethical approval was obtained from the Ethical Committee of Bisha University (UBCOM-RELOC), with approval number H-06-BH-087/(0802.23). Participation was voluntary, and written informed consent was obtained from all participants prior to enrollment. The materials, equipment, and analytical procedures used in the study are summarized in the Table of Materials.
Study design and setting
A retrospective cross-sectional study was conducted at the Maternity and Children’s Hospital in Bisha, Saudi Arabia, between December 2022 and May 2023 to assess iron status and examine factors associated with iron deficiency among pregnant women in the Northern Asir Region.
Study population and sampling methodology
A total of 200 participants were enrolled, including 135 pregnant women attending routine antenatal care clinics and 65 age-matched non-pregnant women who served as a control group. Participants were recruited from outpatient clinics via convenience sampling during the study period. Eligible women presenting during clinic hours were consecutively approached, and recruitment continued until the target sample size was reached. To reduce potential selection bias within this framework, controls were age-matched using simple random sampling from eligible non-pregnant clinic attendees.
Pregnant women were eligible for inclusion if they were aged 18 years or older and had a pregnancy with a gestational age between 12 and 36 weeks. Eligible participants were enrolled regardless of their iron status and subsequently classified as pregnant women with IDA or without IDA based on laboratory findings. According to the WHO criteria, anemia during pregnancy was defined as hemoglobin (Hb) concentrations < 11.0 g/dL during the first and third trimesters and < 10.5 g/dL during the second trimester. IDA was diagnosed in women who met the pregnancy-specific Hb threshold and had evidence of iron deficiency, including serum ferritin < 15 ng/mL, serum iron < 10 µmol/L, and total iron-binding capacity (TIBC) ≥ 68 µmol/L17,18. Pregnant women who did not meet these diagnostic criteria were classified as the pregnant without IDA group. Non-pregnant women of reproductive age with no current pregnancy and without known hematological disorders served as the control group. Exclusion criteria for both groups included a documented history of chronic or systemic conditions associated with altered iron metabolism or inflammatory status, such as chronic kidney disease, autoimmune disorders, malignancy, inflammatory bowel syndrome, chronic liver disease, or hereditary iron disorders (e.g., hemochromatosis). Women with acute infections at the time of sampling, those who had received intravenous iron therapy or blood transfusions within the preceding three months, and those receiving long-term immunosuppressive therapy were also excluded. Body mass index (BMI) and ethnicity were recorded for all participants; however, these variables were not used as exclusion criteria and were instead considered as potential covariates in the analysis.
Sample size determination
The sample size was calculated using an epidemiological sample-size calculation software19, based on an anticipated prevalence of IDA among pregnant women in Saudi Arabia of 40%6, with a 95% confidence level and a 5% margin of error. The minimum required sample size was estimated at 182 participants; therefore, a total of 200 participants were recruited to enhance statistical precision.
Data collection
Questionnaire
Data was collected using a structured and validated questionnaire. The questionnaire was developed following an extensive review of the literature and was evaluated by a panel of subject experts, including obstetricians, nutritionists, and epidemiologists, to ensure content validity. A pilot study involving 20 participants, who were not included in the final analysis, was conducted to assess clarity, reliability, and feasibility. The internal consistency of the questionnaire was acceptable, with Cronbach’s alpha of 0.81.
The final questionnaire consisted of three sections comprising a total of 35 items (Supplementary File 1):
Section 1 (Sociodemographic data, 10 items): age, education level, occupation, place of residence, nationality, and family history of anemia.
Section 2 (Dietary habits, 12 items): frequency of consumption of iron-rich foods (red meat, white meat, fish, vegetables, and fortified cereals), tea and coffee intake, and dietary regimen. Dietary variables were selected a priori based on their established relevance to iron intake, iron bioavailability, and dietary factors that may influence iron absorption. The questionnaire included major dietary sources of iron, including red meat, poultry, fish, green leafy vegetables, and fortified cereals. Vitamin C-rich foods, particularly citrus fruits, were assessed because vitamin C can enhance the absorption of non-heme iron. In contrast, tea and coffee consumption were assessed because dietary polyphenols may inhibit non-heme iron absorption when consumed with or near meals. Dietary regimen and fast-food consumption were also assessed to indicate overall dietary patterns and nutritional adequacy. The selected dietary items were informed by literature reviewed during questionnaire development and were subsequently evaluated by obstetric, nutrition, and epidemiology experts for content validity.
Section 3 (Clinical history and symptoms, 13 items): gestational age, parity, history of blood transfusion, fatigue, dizziness, fever, and other symptoms commonly associated with anemia.
Biochemical assessment
For each participant, a 5 mL venous blood sample was obtained after an overnight fast. Samples were centrifuged at 2000 × g for 15 min to separate the serum, which was subsequently analyzed immediately. Hemoglobin concentration was measured using an automated hematology analyzer and reported in grams per deciliter (g/dL). Serum ferritin levels were assessed using an electrochemiluminescence immunoassay (ECLIA) on an automated immunoassay analyzer and expressed in nanograms per milliliter (ng/mL). Serum iron, total iron-binding capacity (TIBC), and unsaturated iron-binding capacity (UIBC) were determined using a colorimetric method on an automated biochemical analyzer, with results reported in micromoles per liter (µmol/L). Transferrin saturation (TR-SAT) was calculated as the ratio of serum iron to TIBC multiplied by 100 and expressed as a percentage.
Statistics and data analyses
Data was coded and analyzed using standardized statistical analysis software. Descriptive statistics, including means, standard deviations, and percentages, were used to summarize sociodemographic, dietary, clinical, and biochemical variables. Group comparisons were conducted using an unpaired Student’s t-test or one-way analysis of variance (ANOVA), as appropriate. Statistical significance was defined as p < 0.05. Graphical outputs were produced using graphing and statistical software.
To examine factors independently associated with IDA, a multivariate logistic regression model was applied. IDA status was specified as the binary dependent variable (IDA = 1, non-IDA/control = 0). Independent variables were selected a priori based on biological plausibility and evidence from previous studies and included sociodemographic characteristics (residence, family history of anemia), physiological status (pregnancy), and dietary variables (intake of red meat, poultry, and citrus fruits).
Categorical variables were coded using dummy variables, and dietary intake variables were classified as low or adequate based on reported consumption frequency (≤2 times per week vs. >2 times per week). All selected variables were entered simultaneously into the regression model to estimate their independent associations while accounting for potential confounding factors. Adjusted odds ratios (ORs) with 95% confidence intervals (CIs) were reported, where ORs greater than 1 reflected a higher odds of IDA. A visual summary of the ORs and corresponding 95% CIs was presented using a forest plot generated in spreadsheet software.
Results
Study population and participant characteristics
A total of 200 women were enrolled in the study, including 135 pregnant women and 65 non-pregnant controls. Among the pregnant women, 91 (67.4%) were diagnosed with IDA, while 44 (32.6%) had no evidence of IDA.
Questionnaire-based findings
Sociodemographic characteristics
Among pregnant women with IDA, the majority were aged 20–40 years (57.1%), followed by those aged 18–20 years (22.0%) and those older than 40 years (21%). Most women with IDA resided in rural areas (64.8%), whereas 35.2% lived in urban areas. Regarding educational attainment, secondary education was the most common level (30.8%), followed by primary education (32%), intermediate education (22.0%), and university education or higher (15.4%). Most women with IDA were unemployed (82.4%), while 17.6% were employed. Saudi nationals accounted for 57.1% of the IDA group, while non-Saudi nationals accounted for 43%. A positive family history of IDA was reported by 62.6% of women with IDA, whereas 37.4% reported no family history (Table 1).
Dietary habits
This study examined the frequency of dietary intake among pregnant women for selected food items, classified as ≤2 times per week or ≥3 times per week. Among women with IDA (n = 91), most reported consuming tea (69.2%), citrus fruits (61.5%), red meat (70.3%), red fish (93.4%), and white meat (88.0%) ≤2 times/week, while poultry was more commonly consumed ≥3 times/week (53.8%). In women without IDA (n = 44), tea consumption was more frequent, with 52.3% consuming it ≥3 times/week. Poultry (79.5%) and red meat (56.8%) were also predominantly consumed ≥3 times/week. However, citrus fruits (54.5%), red fish (84.1%), and white meat (84.1%) were more commonly consumed ≤2 times/week. Overall, among all pregnant participants (N = 135), tea (62.2%), citrus fruits (59.3%), red meat (61.5%), red fish (90.4%), and white meat (86.7%) were predominantly consumed ≤2 times/week. In contrast, poultry was consumed ≥3 times/week by 62.2% of participants (Table 2).
Clinical history and symptoms
The study evaluated participants' medical and clinical characteristics, including gestational age, recent illness, clinical symptoms, gastrointestinal (GIT) bleeding, history of blood transfusion, and adherence to dietary regimens. Gestational age was distributed across trimesters, with 54.8% of participants in the second trimester, 26% in the third trimester, and 19.3% in the first trimester. Recent illness was reported by 37.8% of participants, whereas 62% reported no illness. Symptoms such as dizziness, fatigue, or fever were reported by 66.7% of participants, while 33% reported no symptoms. No cases of GIT bleeding were recorded. In terms of clinical status, 41.5% of participants were symptomatic and 58.5% were asymptomatic. A history of blood transfusion was reported by 9% of participants, while 91.1% reported no previous transfusion. Adherence to a specific dietary regimen was reported by 14.8% of participants, whereas 85.2% reported no dietary adherence (Table 3).
Biochemical assessment
Hemoglobin concentrations
Hemoglobin levels were measured in both non-pregnant controls and pregnant women with IDA. The control group comprised 65 non-pregnant women. Mean Hb levels were significantly lower among pregnant women with IDA (8.09 g/dL) compared with non-pregnant controls (12.99 g/dL) (Figure 1).
Iron status biomarkers
Iron biomarker levels were compared between pregnant women with IDA and non-pregnant controls. Blood samples were analyzed to determine serum iron, ferritin, TIBC, UIBC, and transferrin saturation (TR-SAT). Mean serum iron levels were significantly lower among pregnant women with IDA (5.42 µmol/L) than among non-pregnant controls (23.71 µmol/L) (Figure 2A). TIBC values were higher in pregnant women with IDA (68.09 µmol/L) compared with non-pregnant controls (56.08 µmol/L) (Figure 2B). Transferrin saturation levels were also lower among pregnant women with IDA (10.50%) than among non-pregnant controls (41.09%) (Figure 2C). UIBC levels were higher in pregnant women with IDA (62.67 µmol/L) compared with non-pregnant controls (32.36 µmol/L) (Figure 2D). Ferritin levels were lower among pregnant women with IDA (9.08 ng/mL) than among non-pregnant controls (77.82 ng/mL) (Figure 2E).
Multivariate logistic regression analysis
Multivariate logistic regression analysis was performed to identify factors independently associated with IDA. To avoid incorporation bias, laboratory parameters used in the diagnostic definition of IDA (including serum ferritin and transferrin saturation) were not included as independent variables in the regression model. After adjustment for potential confounders, lower red meat intake, lower poultry intake, lower citrus fruit intake, rural residence, and a positive family history remained independently associated with increased odds of IDA.
Dietary variables also demonstrated significant independent associations with IDA. Lower red meat intake was associated with increased odds of IDA (OR = 4; 95% CI: 2.136–7.489; p < 0.001), while lower poultry consumption showed a similar association (OR = 3.5; 95% CI: 1.906–6.426; p < 0.001). Physiological status was significantly related to iron status, with pregnancy independently associated with higher odds of IDA (OR = 3; 95% CI: 1.699–5.296; p < 0.001). Sociodemographic and familial factors were also associated with IDA. A positive family history of IDA was linked to increased odds of the condition (OR = 2.3; 95% CI: 1.255–4.215; p = 0.007), and rural residence was independently associated with IDA (OR = 1.8; 95% CI: 1.020–3.178; p = 0.043). Reduced citrus fruit intake was likewise independently associated with IDA (OR = 1.6; 95% CI: 1.029–2.487; p = 0.037). Overall, IDA was independently associated with dietary intake patterns, pregnancy status, and selected sociodemographic characteristics (Table 4 and Figure 3).
DATA AVAILABILITY STATEMENT
The authors confirm that all data supporting the findings of this study are provided within the article and are available in the Zenodo repository https://doi.org/10.5281/zenodo.21549421.
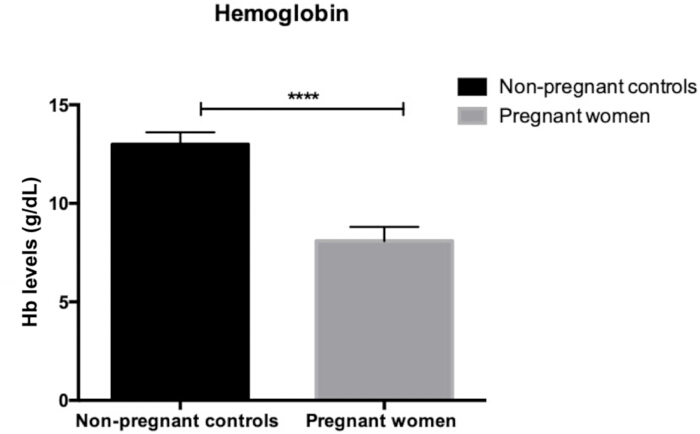
Figure 1: Comparison of hemoglobin levels between non-pregnant controls and pregnant women with IDA. The figure demonstrates significantly higher mean Hb levels (g/dL) in non-pregnant controls compared with those of pregnant women with IDA. A highly significant difference was observed between the two groups (****p < 0.001, unpaired t-test). Please click here to view a larger version of this figure.
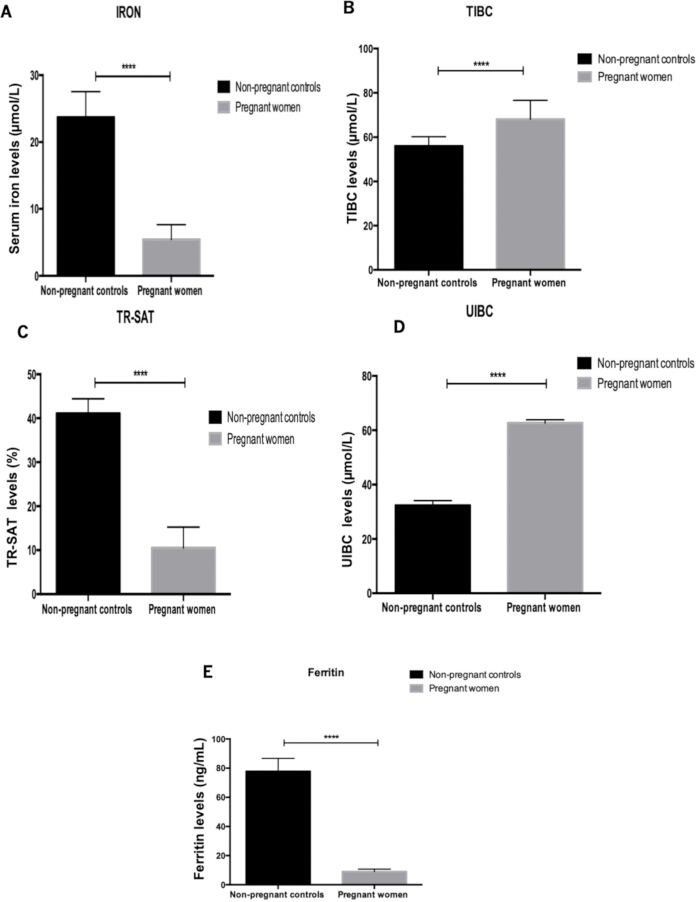
Figure 2: Comparison of iron biomarkers between non-pregnant controls and pregnant women with IDA. (A) Serum iron levels: non-pregnant controls showed significantly higher serum iron levels (µmol/L) compared with those of pregnant women with IDA (****p < 0.001, unpaired t-test). (B) Total iron-binding capacity (TIBC): TIBC levels were significantly higher in pregnant women with IDA than in non-pregnant controls (****p < 0.001, unpaired t-test). (C) Transferrin saturation (TR-SAT): Pregnant women with IDA exhibited significantly lower transferrin saturation percentages than non-pregnant controls (****p < 0.001, unpaired t-test). (D) Unsaturated iron-binding capacity (UIBC): UIBC levels were significantly higher in pregnant women with IDA than in non-pregnant controls (****p < 0.001, unpaired t-test). (E) Ferritin levels: Ferritin concentrations (ng/mL) were higher in non-pregnant controls than in pregnant women with IDA (****p < 0.001, unpaired t-test). Please click here to view a larger version of this figure.
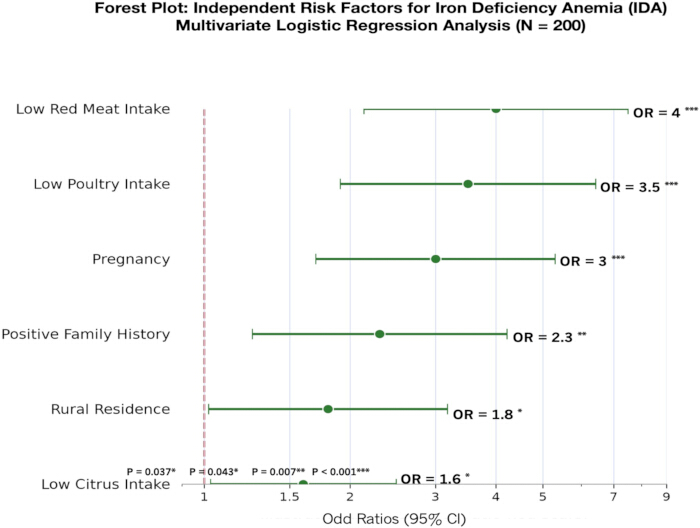
Figure 3: Forest plot of independent risk factors for iron deficiency anemia. It illustrates the adjusted odds ratios (ORs) and 95% confidence intervals (CIs) for independent risk factors associated with IDA identified through multivariate logistic regression analysis (N = 200). The vertical dashed line represents the null value (OR = 1). Risk factors are grouped by domain: nutritional, physiological, and sociodemographic/genetic. Low intake of iron-rich foods showed the strongest associations with IDA, followed by pregnancy status, positive family history of IDA, and rural residence. Please click here to view a larger version of this figure.
| Characteristic | Pregnant with IDA (n = 91) | Pregnant without IDA (n = 44) | Non-pregnant controls (n = 65) | Total (N = 200) |
| Age (years) | ||||
| 18–20 | 20 (22.0%) | 6 (13.6%) | 9 (13.8%) | 35 (17.5%) |
| 20–40 | 52 (57.1%) | 24 (54.5%) | 36 (55.4%) | 112 (56.0%) |
| >40 | 19 (21%) | 14 (31.8%) | 20 (30.8%) | 53 (26.5%) |
| Residence | ||||
| Rural | 59 (64.8%) | 23 (52.3%) | 40 (61.5%) | 122 (61.0%) |
| Urban | 32 (35.2%) | 21 (47.7%) | 25 (38.5%) | 78 (39.0%) |
| Education level | ||||
| Primary | 29 (32%) | 9 (20.5%) | 20 (30.8%) | 58 (29%) |
| Intermediate | 20 (22.0%) | 9 (20.5%) | 14 (21.5%) | 43 (21.5%) |
| Secondary | 28 (30.8%) | 16 (36.4%) | 23 (35.4%) | 67 (33.5%) |
| University or higher | 14 (15.4%) | 10 (22.7%) | 8 (12.3%) | 32 (16.0%) |
| Employment status | ||||
| Employed | 16 (17.6%) | 12 (27.3%) | 13 (20.0%) | 41 (20.5%) |
| Unemployed | 75 (82.4%) | 32 (72.7%) | 52 (80.0%) | 159 (79.5%) |
| Nationality | ||||
| Saudi | 52 (57.1%) | 28 (63.6%) | 39 (60.0%) | 119 (59.5%) |
| Non-Saudi | 39 (43%) | 16 (36.4%) | 26 (40.0%) | 81 (40.5%) |
| Family history of IDA | ||||
| Positive | 57 (62.6%) | 19 (43.2%) | 38 (58.5%) | 114 (57%) |
| Negative | 34 (37.4%) | 25 (56.8%) | 27 (41.5%) | 86 (43.0%) |
Table 1: Sociodemographic profiles of pregnant women attending the antenatal clinic at the Maternity and Children’s Hospital, Bisha, Saudi Arabia.
| Food Item | Pregnant with IDA (n = 91) ≤2/week | Pregnant with IDA (n = 91) ≥3/week | Pregnant without IDA (n = 44) ≤2/week | Pregnant without IDA (n = 44) ≥3/week | Total (N = 135) ≤2/week | Total (N = 135) ≥3/week |
| Tea | 63 (69.2%) | 28 (30.8%) | 21 (47.7%) | 23 (52.3%) | 84 (62.2%) | 51 (37.8%) |
| Citrus fruits | 56 (61.5%) | 35 (38.5%) | 24 (54.5%) | 20 (45.5%) | 80 (59.3%) | 55 (40.7%) |
| Poultry | 42 (46.2%) | 49 (53.8%) | 9 (20.5%) | 35 (79.5%) | 51 (37.8%) | 84 (62.2%) |
| Red meat | 64 (70.3%) | 27 (29.7%) | 19 (43.2%) | 25 (56.8%) | 83 (61.5%) | 52 (38.5%) |
| Red fish | 85 (93.4%) | 6 (6.6%) | 37 (84.1%) | 7 (16%) | 122 (90.4%) | 13 (9.6%) |
| White meat | 80 (88%) | 11 (12.1%) | 37 (84.1%) | 7 (16%) | 117 (86.7%) | 18 (13.3%) |
Table 2: Rate of dietary intake of tea, citrus, poultry, red meat, red fish, and white meat among the participants.
| Characteristic | Pregnant with IDA (n = 91) | Pregnant without IDA (n = 44) | Total (N = 135) |
| Gestational age (GA) | |||
| First trimester | 17 (18.7%) | 9 (20.5%) | 26 (19.3%) |
| Second trimester | 50 (55%) | 24 (54.5%) | 74 (54.8%) |
| Third trimester | 24 (26.4%) | 11 (25.0%) | 35 (26%) |
| Recent illness | |||
| Yes | 37 (40.7%) | 14 (31.8%) | 51 (37.8%) |
| No | 54 (59.3%) | 30 (68.2%) | 84 (62.2%) |
| Clinical symptoms (dizziness, fatigue, fever) | |||
| Yes | 68 (74.7%) | 22 (50.0%) | 90 (66.7%) |
| No | 23 (25.3%) | 22 (50.0%) | 45 (33.3%) |
| GIT bleeding | |||
| Yes | 0 | 0 | 0 |
| Clinical presentation of IDA | |||
| Symptomatic | 46 (50.5%) | 10 (22.7%) | 56 (41.5%) |
| Asymptomatic | 45 (49.5%) | 34 (77.3%) | 79 (58.5%) |
| Blood transfusion history | |||
| Yes | 10 (11.0%) | 2 (4.5%) | 12 (9%) |
| No | 81 (89.0%) | 42 (95.5%) | 123 (91.1%) |
| Adherence to dietary regime | |||
| Yes | 16 (17.6%) | 4 (9.1%) | 20 (14.8%) |
| No | 75 (82.4%) | 40 (91%) | 115 (85.2%) |
Table 3: Medical history, clinical presentation, blood transfusion status, and dietary regimen among the participants.
| Risk factor | Odds ratio | 95% CI | p-value | Domain |
| Low red meat intake | 4 | 2.136–7.489 | <0.001*** | Nutritional |
| Low poultry intake | 3.5 | 1.906–6.426 | <0.001*** | Nutritional |
| Pregnancy | 3 | 1.699–5.296 | <0.001*** | Physiological |
| Positive family history | 2.3 | 1.255–4.215 | 0.007** | Genomic/Social |
| Rural residence | 1.8 | 1.020–3.178 | 0.043* | Genomic/Social |
| Low citrus intake | 1.6 | 1.029–2.487 | 0.037* | Nutritional |
Table 4: Multivariate logistic regression analysis identifying independent risk factors for IDA among study participants (N = 200). Odds ratios (ORs) were adjusted for nutritional, physiological, and sociodemographic variables.
Supplementary File 1: Questionnaire: Iron Deficiency Anemia Among Pregnant Women Please click here to download this file.
Discussion
Iron deficiency anemia (IDA) remains a major global public health concern, particularly among pregnant women. Physiological changes during pregnancy, including plasma volume expansion and increasing fetal iron requirements, contribute to declining maternal iron status as gestation progresses. Maternal plasma volume typically increases by approximately 40–50%, resulting in physiological hemodilution and reduced hemoglobin concentration despite an increase in total red blood cell mass. This adaptive response decreases blood viscosity, facilitates uteroplacental perfusion, and optimizes maternal–fetal oxygen and nutrient exchange. Adequate plasma volume expansion is also considered a marker of normal placental and cardiovascular adaptation, whereas insufficient expansion has been associated with adverse pregnancy outcomes, including preeclampsia, a hypertensive disorder characterized by abnormal placentation and endothelial dysfunction20. Concurrently, maternal iron requirements increase substantially to support expanded erythropoiesis, placental development, and fetal growth, with particularly high demand during the second trimester. When dietary iron intake and body iron stores are insufficient to meet these demands, IDA may develop or deteriorate21,22. Within this context, the present study provides one of the first detailed assessments of iron status and associated factors among pregnant women in Bisha, Saudi Arabia, addressing an important regional data gap. Previous research in the same area assessed IDA prevalence in the general population but excluded pregnant women, limiting direct comparability15.
The present study identified a high prevalence of IDA among pregnant women (67.4%), based on WHO pregnancy-specific hemoglobin thresholds (<11.0 g/dL during the first and third trimesters and <10.5 g/dL during the second trimester). This prevalence substantially exceeds the WHO threshold of 40% for classification as a severe public health problem6,17, indicating that IDA represents a major maternal health concern in the Northern Asir region. The prevalence was also notably higher than reported estimates for the Eastern Mediterranean region (38.9%) and the global average (38.1%)6. Compared with other Saudi regions, the prevalence in Bisha exceeded those reported in Makkah (39.0%), Al-Khobar (41.3%), and Asir (31.9%), while remaining slightly lower than the prevalence reported in Al-Ahsa (73.3%)16,23,24,25. These differences suggest that IDA may vary across geographical and sociodemographic contexts within Saudi Arabia, potentially reflecting differences in healthcare access, dietary habits, education, and socioeconomic conditions9. Sociodemographic characteristics in the present study were significantly associated with IDA. A substantial proportion of participants resided in rural areas, had lower educational attainment, and reported unemployment, factors consistently associated with higher anemia prevalence in studies from Singapore, Malaysia, and Ethiopia26,27,28. Lower educational status may be related to reduced nutritional awareness, limited healthcare utilization, and lower dietary diversity, whereas rural residence may reflect differences in food availability and access to antenatal care29. Consistent with regional findings, studies among adolescents in Saudi Arabia have also associated low socioeconomic status and inadequate fruit-juice intake with anemia; reported prevalence rates of 16.7% among males and 34.0% among females are comparable with findings from Saudi Arabia and other Gulf countries, where anemia is more common among female adolescents (22.4–40.0%) than males (12.8–18.4%). More than half of the participants in the present study also reported a family history of anemia, suggesting possible shared genetic, dietary, or environmental influences on iron status30.
Dietary patterns were independently associated with IDA. Lower intake of red meat, poultry, and citrus fruits was associated with higher odds of IDA, consistent with previous studies26,27,28. Red meat and poultry provide heme iron, while citrus fruits may enhance non-heme iron absorption through their vitamin C content. Frequent tea consumption was also associated with IDA, potentially because tea polyphenols inhibit iron absorption31,32,33. Emerging evidence indicates that although anemia during pregnancy is influenced by multiple maternal and nutritional factors, iron deficiency has a stronger relationship with overall dietary quality and inadequate intake of iron and other micronutrients34,35. Dietary inadequacies are common among pregnant women in Saudi Arabia, with most participants in previous research consuming less than the recommended dietary allowance (RDA) for vitamin B1, calcium, iron, and total energy. Although protein intake exceeded the RDA in most women, total energy intake remained low, suggesting that protein may have contributed to meeting caloric requirements rather than primarily serving its physiological functions35. These findings support the interpretation that iron deficiency is strongly associated with dietary patterns, whereas anemia is multifactorial, emphasizing the importance of comprehensive nutritional strategies rather than single-nutrient interventions. Nevertheless, dietary behavior alone may be insufficient to normalize iron levels once deficiency is established, as pregnancy-related iron depletion may reflect cumulative physiological demands, short interpregnancy intervals, blood loss during delivery, and inadequate restoration of iron stores. Accordingly, iron supplementation alongside dietary modification remains important, particularly in settings with a high prevalence of anemia34.
Physiological factors were also associated with IDA, with the second trimester showing the highest proportion of affected participants, consistent with previous studies identifying mid-pregnancy as a period of increased iron demand36. Longitudinal research has reported that anemia prevalence increases throughout pregnancy, from 11.8% in the first trimester to 28.8% in the third trimester, reflecting physiological hemodilution and increasing maternal iron requirements as gestation advances37. In contrast, the present study observed the largest proportion of IDA cases during the second trimester. This difference may reflect the cross-sectional design and distribution of participants across gestational ages rather than the longitudinal progression of anemia during pregnancy. At the global level, WHO estimates that anemia affects nearly 38.9% of pregnant women6, with similar prevalence reported in studies from Saudi Arabia. Biochemical analyses further confirmed significantly lower hemoglobin, serum iron, ferritin, and transferrin saturation, together with higher total and unsaturated iron-binding capacity, among pregnant women with IDA compared with non-pregnant controls. Similarly, comparisons of anemic and non-anemic pregnancies have demonstrated increased TIBC and reduced serum ferritin and transferrin saturation, while serum transferrin receptor levels were higher in anemic pregnancies, particularly in mild and moderate anemia, reflecting increased cellular iron demand38. These biomarker patterns are consistent with recognized diagnostic features of iron deficiency and findings from regional and international studies26,27,28. Multivariate regression further demonstrated strong associations between IDA and dietary intake patterns, pregnancy status, rural residence, and family history of anemia, underscoring the multifactorial nature of iron deficiency during pregnancy. Similarly, a recent cross-sectional study among pregnant women in Ethiopia identified maternal nutritional status and dietary diversity as significant predictors of anemia in multivariable analysis, supporting the contribution of nutritional and sociodemographic factors to anemia risk39,40. However, because both studies were cross-sectional, these associations should not be interpreted as temporal or causal relationships.
Beyond its biochemical and nutritional dimensions, IDA during pregnancy has broader implications for maternal functioning and well-being. Previous studies have reported associations between anemia and reduced maternal cognitive performance, impaired attention, and increased susceptibility to adverse maternal outcomes41,42. Although the present study does not establish causation or evaluate maternal or neonatal outcomes, these reported associations highlight the potential functional and societal significance of the high burden of IDA observed in this population. The study has several limitations that should also be considered. First, pregnancy and neonatal outcomes were not evaluated, preventing assessment of relationships between maternal iron status and adverse maternal or neonatal outcomes. Second, information on prenatal vitamins and iron supplementation was not collected. Because iron supplementation may substantially influence maternal hemoglobin concentrations and iron biomarkers, the absence of these data may have resulted in residual confounding. Future prospective longitudinal studies should incorporate serial maternal hematological assessments, pregnancy and neonatal outcomes, and detailed information on prenatal micronutrient supplementation to better characterize these relationships.
Overall, the present findings contribute to the growing regional evidence that IDA among pregnant women in Saudi Arabia remains a considerable public health concern. The 67.4% prevalence observed among pregnant women in Bisha, together with the consistent associations with nutritional intake, sociodemographic context, pregnancy stage, and biochemical iron indicators, demonstrates the multifactorial nature of iron deficiency during pregnancy. Pregnant women with IDA showed markedly lower hemoglobin, serum iron, ferritin, and transferrin saturation levels, and elevated total iron-binding capacity and unsaturated iron-binding capacity, reflecting depleted iron stores and reduced iron availability. Multivariate analysis identified lower intake of red meat, poultry, and citrus fruits, pregnancy status, rural residence, and a positive family history of anemia as independent factors associated with IDA. Collectively, these findings support routine screening, strengthened nutritional counseling, iron supplementation when clinically indicated, and targeted preventive strategies within antenatal care services to reduce the substantial burden of IDA in this population.
Disclosures
The authors declare no conflicts of interest.
Acknowledgements
The authors are thankful to the Deanship of Graduate Studies and Scientific Research at the University of Bisha for supporting this work through the Fast-Track Research Support Program.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 5 mL Vacutainer Blood Collection Tubes | Becton, Dickinson and Company (BD), Franklin Lakes, NJ, USA | https://www.bd.com/en-us/products-and-solutions/products?query=5+mL+Vacutainer+Blood+Collection+Tubes | Used for venous blood sample collection. |
| Cobas 8000 Modular Analyzer | Roche Diagnostics, Basel, Switzerland | Cobas 8000 | Used for serum ferritin, serum iron, TIBC, and UIBC analyses. |
| Ferritin ECLIA Reagent Kit | Roche Diagnostics, Basel, Switzerland | https://diagnostics.roche.com/global/en/products/lab/elecsys-ferritin-cps-000468.html | Electrochemiluminescence immunoassay for serum ferritin determination. |
| GraphPad Prism | GraphPad Software, San Diego, CA, USA | Version 9 | Used for graphical presentation of results. |
| IBM SPSS Statistics | IBM Corporation, Armonk, NY, USA | Version 26.0 | Used for statistical analyses. |
| Iron Colorimetric Reagent Kit | Roche Diagnostics, Basel, Switzerland | https://custombiotech.roche.com/global/en/products/cb/iron-bio-ht-3810349.html | Used for serum iron measurement. |
| Laboratory Centrifuge | Hospital Clinical Laboratory | N/A | Used to separate serum at 2000 × g for 15 min. |
| Microsoft Excel | Microsoft Corporation, Redmond, WA, USA | Microsoft 365 (or applicable version) | Used to generate the forest plot and organize study data. |
| OpenEpi Version 3.01 | OpenEpi | Version 3.01 | Used for sample size calculation. |
| Structured questionnaire (Supplementary File 1) | Developed by the authors | N/A | Questionnaire developed specifically for this study to collect sociodemographic, dietary, and clinical data. |
| Sysmex XN-1000 Hematology Analyzer | Sysmex Corporation, Kobe, Japan | XN-1000 | Used for hemoglobin measurement. |
| TIBC/UIBC Colorimetric Reagent Kit | Roche Diagnostics, Basel, Switzerland | https://diagnostics.roche.com/global/en/products/lab/uibc-cps-000266.html | Used for determination of TIBC and UIBC. |
References
- Abu-Ouf NM, Jan MM. The impact of maternal iron deficiency and iron deficiency anemia on child’s health. Saudi Med J. 2015;36(2):146-149.
- Kaur S. Iron deficiency anemia (IDA): a review. Int J Sci Res. 2016;5(4):1999-2003.
- Zhang Q, et al. Adverse effects of iron deficiency anemia on pregnancy outcome and offspring development and intervention of three iron supplements. Sci Rep. 2021;11(1):6087.
- Hallberg L, Hulthén L, Garby L. Iron stores and haemoglobin iron deficits in menstruating women: calculations based on variations in iron requirements and bioavailability of dietary iron. Eur J Clin Nutr. 2000;54(8):650-657.
- World Health Organization Regional Office for the Eastern Mediterranean. Guidelines for the control of iron deficiency in countries of the Eastern Mediterranean, Middle East and North Africa. WHO Regional Office for the Eastern Mediterranean; Alexandria; 1996.
- World Health Organization. The global prevalence of anaemia in 2011. World Health Organization; Geneva; 2015.
- World Health Organization. Turning the tide of malnutrition: responding to the challenge of the 21st century. World Health Organization; Geneva; 2000.
- Verster A, van der Pols JC. Anaemia in the Eastern Mediterranean Region. World Health Organization Regional Office for the Eastern Mediterranean; Alexandria; 1995.
- Radhwi OO, Raslan OM, Almoshary MA, Mansory EM. Unmasking iron deficiency and iron deficiency anemia in Saudi Arabia: data from a large private-sector laboratory. Saudi Med J. 2025;46(9):1000-1007.
- Al-Shehri S. Health profile of Saudi adolescent schoolgirls. Presidency of Girls’ Education; Riyadh; 1996.
- World Health Organization. The prevalence of anemia in women: a tabulation of available information. 2nd ed. World Health Organization; Geneva; 1992.
- Wiafe MA, Apprey C, Annan RA. Patterns of dietary iron intake, iron status, and predictors of haemoglobin levels among early adolescents in a rural Ghanaian district. J Nutr Metab. 2020;2020:3183281.
- McIntyre AS, Long RG. Prospective survey of investigations in outpatients referred with iron deficiency anaemia. Gut. 1993;34(8):1102-1107.
- Dudwe R, Singh N. Study of the prevalence and pattern of anaemia in unmarried anaemic females aged 15–30 years. SSR Inst Int J Life Sci. 2020;6(1):2469-2479.
- Belali TM. Iron deficiency anaemia: prevalence and associated factors among residents of northern Asir Region, Saudi Arabia. Sci Rep. 2022;12(1):19170.
- Mokhtar A, El-Soadaa S. Prevalence and risk factors of anemia among a sample of pregnant females attending primary health care centers in Makkah, Saudi Arabia. Pak J Nutr. 2012;11(12):1113-1120.
- World Health Organization. Haemoglobin concentrations for the diagnosis of anaemia and assessment of severity. World Health Organization; Geneva; 2011.
- Api O, et al. Diagnosis and treatment of iron deficiency anemia during pregnancy and the postpartum period: Iron Deficiency Anemia Working Group consensus report. Turk J Obstet Gynecol. 2015;12(3):173-181.
- Dean AG, Sullivan KM, Soe MM. OpenEpi: open source epidemiologic statistics for public health. Version 3.01. OpenEpi; 2013.
- Roberts JM, Hubel CA. The two-stage model of preeclampsia: variations on the theme. Placenta. 2009;30(Suppl A):S32-S37.
- Scholl TO. Maternal iron status: relation to fetal growth, length of gestation, and iron endowment of the neonate. Nutr Rev. 2011;69(Suppl 1):S23-S29.
- Suega K, Dharmayuda TG, Sutarga IM, Bakta IM. Iron-deficiency anemia in pregnant women in Bali, Indonesia: a profile of risk factors and epidemiology. Southeast Asian J Trop Med Public Health. 2002;33(3):604-607.
- Rasheed P, Koura MR, Al-Dabal BK, Makki SM. Anemia in pregnancy: a study among attendees of primary health care centers. Ann Saudi Med. 2008;28(6):449-452.
- Mahfouz AA, et al. Anemia among pregnant women in the Asir region, Saudi Arabia: an epidemiologic study. Southeast Asian J Trop Med Public Health. 1994;25(1):84-87.
- Taha A, et al. Iron deficiency anaemia in reproductive-age women attending obstetrics and gynecology outpatient services of a university health centre in Al-Ahsa, Saudi Arabia. Afr J Tradit Complement Altern Med. 2014;11(2):339-342.
- Loy SL, et al. Iron status and risk factors of iron deficiency among pregnant women in Singapore: a cross-sectional study. BMC Public Health. 2019;19(1):397.
- Abd Rahman R, et al. The prevalence and risk factors of iron deficiency anemia among pregnant women in Malaysia: a systematic review. Front Nutr. 2022;9:847693.
- Kassa GM, Muche AA, Berhe AK, Fekadu GA. Prevalence and determinants of anemia among pregnant women in Ethiopia: a systematic review and meta-analysis. BMC Hematol. 2017;17(1):17.
- Anders AP, Cammack SE. Maternity care deserts: disparities in maternal and infant access to care and potential solutions. Neoreviews. 2026;27(5):e287-e295.
- Alquaiz AM, et al. Prevalence and correlates of anaemia in adolescents in Riyadh city, Kingdom of Saudi Arabia. Public Health Nutr. 2015;18(17):3192-3200.
- Geissler C, Singh M. Iron, meat and health. Nutrients. 2011;3(3):283-316.
- Fan FS. Iron deficiency anemia due to excessive green tea drinking. Clin Case Rep. 2016;4(11):1053-1056.
- Haniff J, et al. Anemia in pregnancy in Malaysia: a cross-sectional survey. Asia Pac J Clin Nutr. 2007;16(3):527-536.
- Kangalgil M, Sahinler A, Kırkbir IB, Ozcelik AO. Associations of maternal characteristics and dietary factors with anemia and iron deficiency in pregnancy. J Gynecol Obstet Hum Reprod. 2021;50(8):102137.
- Almurshed KS, Bani IA, Al-Kanhal MA, Al-Amri MA. A study of maternal dietary intake during pregnancy in Riyadh, Saudi Arabia. J Fam Community Med. 2007;14(1):9-13.
- Obeagu EI. Pregnancy-associated anemia and its relationship with gestational age: a review. Middle East Res J Nurs. 2024;4(6):80-84.
- Aldakhil LO, Alobaid S, Almogbel AT, Alfouzan SM. Anemia in pregnancy: incidence, risk factors, and outcomes. Cureus. 2025;17(10):e93807.
- Sharma JB, et al. Cross-sectional comparative study of serum erythropoietin, transferrin receptor, ferritin levels and other hematological indices in normal pregnancies and iron deficiency anemia during pregnancy. Eur J Obstet Gynecol Reprod Biol. 2016;203:99-103.
- Fekadu Gemede H, Ayele K, Demisew M. Prevalence and determinants of nutritional anaemia among pregnant women in the Sibu Sire District, Western Ethiopia: a cross-sectional study. BMJ Open. 2025;15(6):e100995.
- Abdul Rohim R, Ahmad WMA, Mamat M. Associated factors of anaemia in pregnancy using logistic regression: a case study in Hulu Terengganu. Int Med J. 2018;25(2):74-78.
- Murray-Kolb LE, et al. CHERG iron report: maternal mortality, child mortality, perinatal mortality, child cognition, and estimates of prevalence of anemia due to iron deficiency. Child Health Epidemiology Reference Group; 2012. https://ghdx.healthdata.org/record/cherg-iron-report-maternal-mortality-child-mortality-perinatal-mortality-child-cognition-and
- Milman N. Iron deficiency and anaemia in pregnant women in Malaysia: still a significant and challenging health problem. J Pregnancy Child Health. 2015;2(3):168.
Reprints and Permissions
This article has been published
Video Coming Soon