This cross-sectional study reports covariate-conditional associations between the appendicular skeletal muscle mass-to-visceral fat area ratio and bone mineral density in adults with type 2 diabetes.
Research Article
Appendicular Skeletal Muscle Mass-to-Visceral Fat Area Ratio and Bone Mineral Density in Type 2 Diabetes: A Cross-Sectional Study
In This Article
Summary
Abstract
Bone fragility is common in type 2 diabetes mellitus (T2DM), but body mass index alone does not capture the balance between appendicular muscle and visceral adiposity. This retrospective cross-sectional study examined the association between the appendicular skeletal muscle mass-to-visceral fat area ratio (SVR) and bone mineral density (BMD) in hospitalized adults with T2DM. A total of 2,820 records were included in descriptive analyses, and 2,798 records with complete BMD endpoints and Model 5 covariates were included in regression analyses. Appendicular skeletal muscle mass and visceral fat area were obtained using multifrequency bioelectrical impedance analysis, whereas lumbar spine, femoral neck, and total hip BMD were measured by dual-energy X-ray absorptiometry. In fully adjusted linear models, each 1-SD increase in SVR was associated with higher lumbar spine BMD (0.017 g/cm2; 95% CI, 0.007–0.027; P = 0.001), femoral neck BMD (0.027 g/cm2; 95% CI, 0.019–0.035; P < 0.001), and total hip BMD (0.028 g/cm2; 95% CI, 0.020–0.036; P < 0.001). Sex-specific tertile plots did not reproduce the monotonic pattern seen with global tertiles, which were strongly sex-imbalanced. Natural cubic-spline models detected nonlinearity at all three sites (all P for nonlinearity < 0.001), with increasing predicted BMD that flattened at higher SVR values. HC3-robust confidence intervals were similar to the primary estimates. These findings describe cross-sectional conditional associations and do not establish causality, bone strength, fracture prediction, or a clinical SVR threshold.
Introduction
Osteoporosis is characterized by low bone mass, deterioration of bone microarchitecture, and increased susceptibility to fragility fracture1,2. Fracture risk is influenced by age, sex, inherited susceptibility, body composition, and metabolic disease3. In type 2 diabetes mellitus (T2DM), areal bone mineral density (BMD) may be preserved or elevated despite an increased risk of fracture; therefore, BMD in this population should be interpreted as a skeletal phenotype rather than as a direct measure of bone strength or fracture probability4.
Muscle, adipose tissue, and bone form an interdependent musculoskeletal-metabolic system. Loss of skeletal muscle may reduce mechanical loading and alter myokine signaling, whereas visceral adiposity may contribute to inflammatory and adipokine pathways relevant to bone remodeling5,6. Because body mass index (BMI) and waist measurements do not separately quantify appendicular muscle and visceral fat, a composite body-composition ratio may provide complementary information while remaining a statistical exposure rather than a distinct biological mechanism7,8.
Muscle–bone crosstalk provides additional biological context for evaluating composite body-composition measures in relation to BMD9. Previous studies have directly examined SVR in relation to BMD. Liu et al. evaluated the association of appendicular skeletal muscle mass-to-visceral fat area ratio (SVR) with BMD and osteoporosis in a general adult population, whereas Guo et al. studied 422 Chinese patients with T2DM and reported age- and sex-dependent associations with BMD and estimated 10-year fracture probability10,11.
The novelty of this study lies in its comprehensive evaluation of the SVR in a large cohort of adults with T2DM. By examining bone mineral density at three clinically relevant skeletal sites and incorporating sequential covariate adjustment, sex-standardized and sex-stratified analyses, simultaneous assessment of the muscle and visceral-fat components, nonlinear spline modeling, and robust sensitivity analyses, this study provides a more rigorous and clinically contextualized characterization of the association between body-composition balance and skeletal health in T2DM. The present study extends this literature using a larger single-center endocrinology inpatient dataset (2,820 records), three site-specific BMD outcomes, sequential covariate adjustment, sex-standardized and sex-stratified analyses, simultaneous appendicular skeletal muscle mass (ASM)/visceral fat area (VFA) component models, and prespecified subgroup interaction tests. The authors are not aware of overlap between the present cohort and the datasets reported in those studies. We hypothesized that higher SVR would be positively associated with lumbar spine, femoral neck, and total hip BMD.
Protocol
This retrospective study was approved by the Ethics Review Board of Changzhou Second People's Hospital (Approval No. KY017-01) and conducted in accordance with the Declaration of Helsinki. The requirement for written informed consent was waived because the analysis used anonymized clinical records. The study included records from 2017 through 2022.
Study design and records
This retrospective cross-sectional analysis used inpatient records from the Department of Endocrinology, The Second People's Hospital of Changzhou, The Third Affiliated Hospital of Nanjing Medical University. The screening file contained 3,495 records after preliminary cleaning, and the analysis unit was an inpatient record. T2DM was defined by the documented inpatient diagnosis in the electronic medical record.
Records were excluded for age younger than 18 years or older than 80 years; alanine aminotransferase or aspartate aminotransferase of at least 120 U/L; eGFR below 30 mL/min/1.73 m2; hemoglobin below 90 g/L; thyroid-stimulating hormone below 0.3 µIU/L or at least 10 µIU/L; or documented active chronic infection, inflammatory disease, malignancy, extreme physical immobility, or another condition expected to substantially distort body-composition or BMD assessment. A total of 366 records were removed because key laboratory or body-composition information was incomplete, and 309 were removed by the prespecified clinical or data-quality criteria, leaving 2,820 records for the descriptive analyses. Twenty-two records lacked all three BMD endpoints and were excluded from regression, leaving 2,798 complete records for each skeletal-site model.
Structured variables were exported from the electronic medical record and curated. Variable definitions and data-quality summaries were independently reviewed, and any discrepancies were resolved by consensus before statistical analysis.
Clinical and laboratory measurements
Age, sex, diabetes duration, smoking status, alcohol consumption, blood pressure, and anthropometric measurements were extracted from electronic medical records. Body weight and height were measured with calibrated equipment while participants wore light clothing and no shoes. BMI was calculated as weight in kilograms divided by height in meters squared. Waist circumference was measured at the umbilical level, hip circumference at the maximal gluteal protrusion, and waist-to-hip ratio as waist circumference divided by hip circumference. Resting blood pressure was obtained after 10 min of seated rest using an automated sphygmomanometer.
All clinical, laboratory, body-composition, and BMD measurements were obtained during the same index hospitalization. Venous blood was collected after an overnight fast within 24 h of admission.
Blood assays
Venous blood samples were collected after an overnight fast within 24 h of admission. Hemoglobin was measured using an automated hematology analyzer. Alanine aminotransferase, aspartate aminotransferase, gamma-glutamyl transferase, serum uric acid, creatinine, triglycerides, total cholesterol, high-density lipoprotein cholesterol, and low-density lipoprotein cholesterol were measured using an automated chemistry analyzer. Glycated hemoglobin (HbA1c) was measured by high-performance liquid chromatography. Thyroid-stimulating hormone, free triiodothyronine, and free thyroxine were quantified using chemiluminescent immunoassay. Estimated glomerular filtration rate (eGFR) was calculated using the Chronic Kidney Disease Epidemiology Collaboration (CKD-EPI) 2021 creatinine equation.
Bone mineral density and body composition
Areal bone mineral density was measured at the lumbar spine, femoral neck, and left total hip using a dual-energy X-ray absorptiometry system and was expressed in g/cm2. Standard anteroposterior lumbar spine and proximal femur acquisition protocols were used. Before scanning, participants removed metallic objects and were positioned supine by trained radiologic technologists. For lumbar spine acquisition, the lower legs were supported to reduce lumbar lordosis, and the lumbar vertebrae were included within the predefined analysis region. For proximal femur acquisition, the left leg was internally rotated and stabilized using the manufacturer-provided positioning device to obtain standardized femoral-neck and total-hip regions.
All scans were reviewed by trained operators for patient motion, metallic interference, incomplete acquisition, anatomical positioning, and region-of-interest placement. Scans with substantial motion, positioning errors, or artifacts that could invalidate the BMD estimate were repeated when clinically feasible or excluded from the analytical dataset. Daily phantom calibration and routine quality control checks were performed before clinical scanning in accordance with the manufacturer's instructions and the hospital's standard operating procedures. Images were analyzed using the manufacturer-provided analysis software.
Body composition was assessed using a multi-frequency bioelectrical impedance analyzer. The device uses direct segmental multifrequency bioelectrical impedance analysis with an eight-point tactile-electrode system and impedance measurements at 1, 5, 50, 250, 500, and 1,000 kHz. Measurements were performed in the morning after an overnight fast and after voiding, before breakfast and before strenuous physical activity. Participants were measured barefoot and wearing light clothing. The palms and soles were cleaned before measurement to ensure adequate electrode contact. Participants stood upright with their heels correctly positioned on the foot electrodes, held the hand electrodes with their thumbs placed on the designated contacts, maintained their arms extended away from the trunk, and remained still and silent throughout the measurement.
Appendicular skeletal muscle mass and visceral fat area were obtained from the device-generated body-composition report. Visceral fat area was a proprietary algorithm-derived estimate based on the bioelectrical impedance measurements and participant characteristics; it was not directly quantified by computed tomography, magnetic resonance imaging, or dual-energy X-ray absorptiometry. SVR was calculated as appendicular skeletal muscle mass (kg) divided by bioelectrical impedance analysis (BIA)- estimated VFA (cm2), with units of kg/cm2. In the 2,820-record descriptive cohort, raw SVR was 0.207 ± 0.090 kg/cm2 (median, 0.195; range, 0.063–0.766), and the global tertile cut points were 0.1518 and 0.2361 kg/cm2. VFA ranged from 18.9 to 270.6 cm2; no zero or negative VFA values were present. No prespecified threshold for very-low-VFA, winsorization rule, or additional extreme-ratio exclusion criterion was applied; all finite values were analyzed. SVR was interpreted as a composite ratio exposure reflecting muscle relative to visceral adiposity, not as an independent biological mechanism. Cohort-standardized SVR was calculated as (SVR − cohort mean)/cohort SD.
Statistical analysis
Continuous variables were summarized as mean ± standard deviation (SD) or median (interquartile range), and categorical variables as n (%). Across SVR tertiles, approximately normal continuous variables were compared by analysis of variance, skewed variables by the Kruskal-Wallis test, and categorical variables by the chi-square test. The primary linear model for each BMD endpoint was: BMD = β0 + β1(SVR z score) + β2(age) + β3(sex) + β4(BMI) + β5(waist-to-hip ratio) + β6(diabetes duration) + β7(hemoglobin) + β8(eGFR) + β9(alanine aminotransferase [ALT]) + β10(aspartate aminotransferase [AST]) + ε. Sequential Models 1-5 retained the definitions reported in Table 2. Age and sex were treated as demographic confounders. BMI and waist-to-hip ratio were included as body-size and central-adiposity covariates but may partly lie on the pathway linking body composition with BMD. Diabetes duration, hemoglobin, eGFR, ALT, and AST were included as clinical-status covariates and may also be downstream correlates. Accordingly, Model 5 estimates a covariate-conditional association rather than a total causal effect.
A VIF below 5 was considered acceptable. Because the three primary models used the same 2,798 records and the same design matrix, the VIFs were identical across BMD endpoints: diabetes duration 1.25, hemoglobin 1.57, eGFR 1.64, BMI 2.01, age 2.13, waist-to-hip ratio 2.50, sex 2.51, AST 2.80, ALT 3.05, and standardized SVR 3.48.
Subgroup models used the Model 5 covariate set after removing the stratifying variable: sex was removed from sex-stratified models, age from age-stratified models, BMI from BMI-stratified models, diabetes duration from duration-stratified models, and eGFR from renal-function-stratified models. Glycemic-control category was not a Model 5 covariate, so the Model 5 covariates were retained in that analysis. Sex-stratified models and the sex interaction used sex-specific SVR z scores; all other subgroup analyses used the cohort-standardized SVR. Each interaction model added subgroup indicators and SVR-by-subgroup product terms and was compared with the corresponding main-effects model by a nested F test. Benjamini-Hochberg correction was applied to the complete family of 18 interaction tests (three BMD endpoints × six subgroup factors).
No a priori power calculation was performed because all eligible records from the fixed retrospective period were analyzed. Precision was evaluated using two-sided 95% confidence intervals. Linear-model assumptions were assessed using residual-versus-fitted, quantile–quantile (Q–Q) plots, scale-location, Cook’s distance, Breusch–Pagan, and studentized-residual diagnostics. HC3 heteroscedasticity-consistent confidence intervals were calculated as a sensitivity analysis. Nonlinearity was tested by comparing Model 5 with a natural cubic-spline exposure term 3 degrees of freedom [df]) using a partial F test; 4-df and central 2nd–98th percentile analyses assessed shape sensitivity. Population-average predictions were displayed over the 2nd–98th percentiles of raw SVR.
Results
Record selection and analytic samples
Among 3,495 inpatient T2DM records available after preliminary cleaning, 366 were excluded because key laboratory or body-composition fields were incomplete and 309 were excluded based on prespecified clinical or data quality criteria, leaving 2,820 records for the descriptive analyses. Within this cohort, 22 records lacked all three BMD endpoints and were excluded from regression. The same 2,798 records contributed to each skeletal-site Model 5 analysis. Missingness among primary variables was: age 0/2,820 (0%), sex 0 (0%), BMI 2 (0.071%), waist-to-hip ratio 0 (0%), diabetes duration 0 (0%), hemoglobin 0 (0%), eGFR 0 (0%), ALT 0 (0%), AST 0 (0%), SVR 0 (0%), and each BMD endpoint 22 (0.78%). The two missing BMI values occurred within the 22 BMD-missing records, so no further record was lost from Model 5 (Figure 1).
Record characteristics across SVR tertiles
The descriptive cohort included 1,620 male and 1,200 female inpatient records, with a mean age of 58.02 ± 11.97 years. The empirical cut points separating the global SVR tertiles were 0.1518 and 0.2361. Global tertiles were strongly sex-imbalanced: female/male records numbered 773/167 in tertile 1, 344/596 in tertile 2, and 83/857 in tertile 3. Across successively higher global tertiles, mean age, BMI, and waist-to-hip ratio were lower, and the proportion of male records was higher (Table 1).
Mean BMD increased across global SVR tertiles at each skeletal site, but this descriptive pattern coincided with marked sex imbalance. Therefore, Figure 2 was recalculated using sex-specific SVR tertiles (cut points: men, 0.2094 and 0.2739; women, 0.1174 and 0.1562). Among men, mean BMD decreased modestly across sex-specific tertiles at the lumbar spine (1.056, 1.020, and 1.002 g/cm2; P < 0.001), femoral neck (0.824, 0.812, and 0.803 g/cm2; P = 0.030), and total hip (0.974, 0.961, and 0.943 g/cm2; P < 0.001). Among women, tertile differences were not statistically significant at the lumbar spine (P = 0.382), femoral neck (P = 0.180), or total hip (P = 0.077). These plots are presented descriptively; adjusted associations were evaluated in continuous multivariable models (Table 1 and Figure 2).
Blood pressure quality assurance identified five SBP and eight DBP values already missing before cleaning. Ten records triggered at least one plausibility or pair-consistency rule; overlapping flags resulted in seven additional SBP and nine additional DBP values being set to missing, yielding 12 missing cleaned SBP and 17 missing cleaned DBP values. The nonidentifying audit trail is provided in Supplementary Table 1.
Association between SVR and site-specific BMD
In unadjusted analyses, higher standardized SVR was positively associated with BMD at the lumbar spine, femoral neck, and total hip. The magnitude of the estimates varied across sequential adjustment models, reflecting the correlations of SVR with sex, body size, and central adiposity. Nevertheless, positive associations were observed at all three skeletal sites in the fully adjusted model, which included age, sex, BMI, waist-to-hip ratio, diabetes duration, hemoglobin, eGFR, alanine aminotransferase, and aspartate aminotransferase.
Each 1-SD higher SVR was associated with a 0.017 g/cm2 higher lumbar spine BMD (β = 0.017; 95% CI, 0.007–0.027; P = 0.001), a 0.027 g/cm2 higher femoral neck BMD (β = 0.027; 95% CI, 0.019–0.035; P < 0.001), and a 0.028 g/cm2 higher total hip BMD (β = 0.028; 95% CI, 0.020–0.036; P < 0.001). Each model included 2,798 inpatient records (Table 2 and Figure 3).
In simultaneous component models adjusted for the Model 5 covariates, standardized ASM was positively associated with lumbar spine BMD (0.045 g/cm2; 95% CI, 0.034–0.056), femoral neck BMD (0.050 g/cm2; 95% CI, 0.042–0.058), and total hip BMD (0.049 g/cm2; 95% CI, 0.040–0.057). Corresponding standardized VFA coefficients were 0.002 g/cm2 (95% CI, −0.013 to 0.016), −0.005 g/cm2 (95% CI, −0.016 to 0.006), and −0.019 g/cm2 (95% CI, −0.031 to −0.007), respectively. These component models remain cross-sectional conditional associations.
HC3-robust sensitivity estimates were 0.017 g/cm2 (95% CI, 0.007–0.027; P < 0.001) for lumbar spine, 0.027 g/cm2 (95% CI, 0.019–0.035; P < 0.001) for femoral neck, and 0.028 g/cm2 (95% CI, 0.019–0.037; P < 0.001) for total hip BMD, closely matching the model based primary estimates.
Subgroup and continuous association analyses
For total hip BMD, the adjusted coefficient per 1-SD increase in SVR was 0.024 g/cm2 (95% CI, 0.010–0.039) among records in the <50-year age subgroup, 0.022 g/cm2 (95% CI, 0.010–0.035) among records in the 50–65-year subgroup, and 0.053 g/cm2 (95% CI, 0.036–0.070) among records in the >65-year subgroup. Corresponding estimates were 0.020 g/cm2 (95% CI, 0.009–0.032) for BMI <24 kg/m2, 0.050 g/cm2 (95% CI, 0.035–0.066) for BMI 24–28 kg/m2, and 0.061 g/cm2 (95% CI, 0.034–0.089) for BMI ≥28 kg/m2. The age and BMI interaction tests remained significant after FDR correction (both FDR P < 0.001), as did the glycemic-control interaction (FDR P = 0.003). Interactions with sex, diabetes duration, and renal function did not remain significant after FDR correction for total hip BMD. These subgroup results were exploratory (Figure 4).
Natural cubic-spline models (3 df) detected nonlinearity for lumbar spine, femoral neck, and total hip BMD (P for nonlinearity = 1.30 × 10⁻6, 6.90 × 10⁻10, and 8.97 × 10⁻16, respectively). The adjusted curves rose across most of the displayed SVR distribution and flattened at higher values; the shape was retained using 4 df and after restriction to the central 2nd–98th percentiles. Residual diagnostics showed some non-normality and evidence of heteroscedasticity for lumbar spine BMD (Breusch–Pagan P = 0.002), but no observation had Cook’s distance >1 (Supplementary Figure 1 and Supplementary Table 1). HC3-robust sensitivity estimates remained positive and similar to Model 5 (lumbar spine, 0.017; femoral neck, 0.027; total hip, 0.028 g/cm2 per 1-SD higher SVR; Figure 5 and Supplementary Table 1).
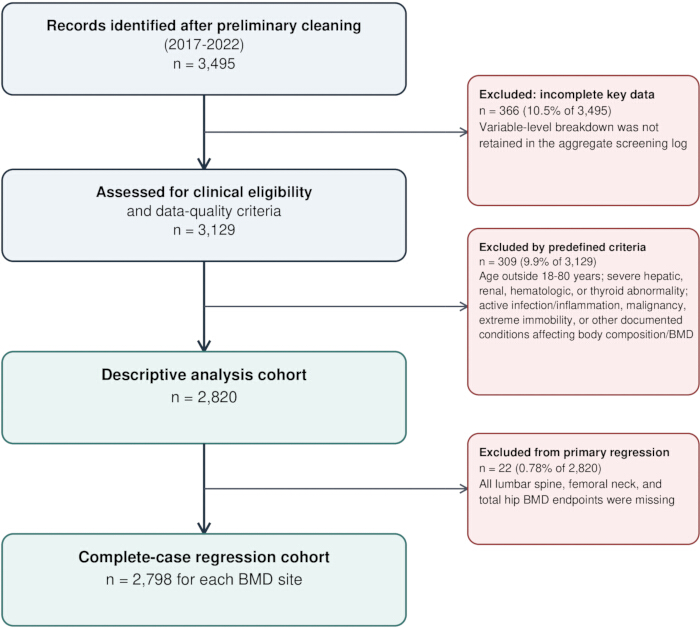
Figure 1. STROBE-style flow diagram of record screening and analysis samples. The screening unit was an inpatient record. Of 3,495 records available after preliminary cleaning, 366 were excluded because key laboratory or body-composition data were incomplete and 309 were excluded based on prespecified clinical or data-quality criteria. The descriptive cohort included 2,820 records. Twenty-two records with all three BMD endpoints missing were excluded from regression, leaving 2,798 records for each skeletal-site model. Please click here to view a larger version of this figure.
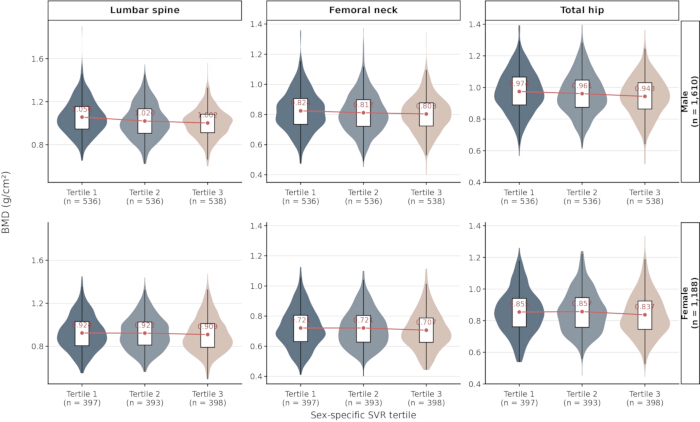
Figure 2. Sex-stratified BMD distributions across sex-specific SVR tertiles in the complete-case cohort (n = 2,798). Violin and box plots show lumbar spine, femoral neck, and total hip BMD separately for men and women; points indicate group means and labels show the mean BMD. Sex-specific tertiles used cut points of 0.2094 and 0.2739 kg/cm2 in men and 0.1174 and 0.1562 kg/cm2 in women. P values are from one-way analysis of variance. BMD is expressed as g/cm2. These unadjusted plots are descriptive. Please click here to view a larger version of this figure.
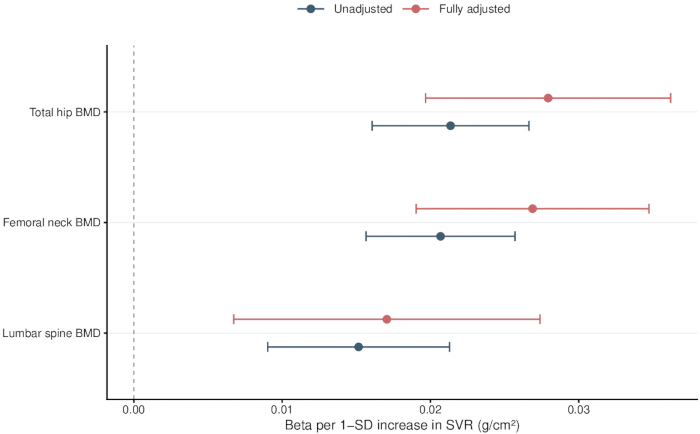
Figure 3. Unadjusted and fully adjusted associations between standardized SVR and total hip BMD. All estimates used n = 2,798 records. The exposure was cohort-standardized SVR, and coefficients represent the BMD difference in g/cm2 per 1-standard deviation (SD) in SVR. Model 5 included age, sex, body mass index (BMI), waist-to-hip ratio, diabetes duration, hemoglobin, estimated glomerular filtration rate (eGFR), alanine aminotransferase (ALT), and aspartate aminotransferase (AST). Horizontal bars show two-sided model based 95% Wald confidence intervals. Please click here to view a larger version of this figure.
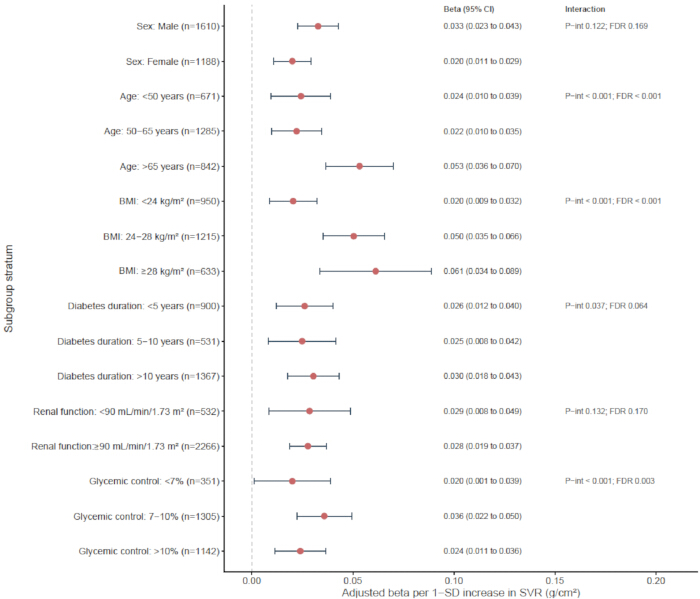
Figure 4. Exploratory subgroup associations between standardized SVR and total hip BMD. Total hip BMD is shown for compact presentation; complete site-specific results are reported in Table 2 and Supplementary Table 1. Points and horizontal bars show adjusted coefficients and 95% Wald confidence intervals. Sex strata use sex-specific SVR z scores; other strata use cohort-standardized SVR. The subgroup analyses are exploratory. Please click here to view a larger version of this figure.
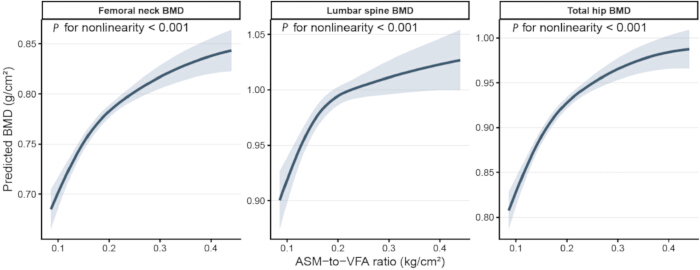
Figure 5. Adjusted nonlinear associations between SVR and BMD. Lines and shaded bands show population-average Model 5 predictions and 95% confidence intervals from natural cubic-spline models with 3 df (degrees of freedom), displayed from the 2nd to 98th percentiles of raw SVR. P values compare the spline model with the corresponding linear Model 5 by partial F test. The curves describe model based cross-sectional associations and do not establish thresholds or causal effects. Please click here to view a larger version of this figure.
Table 1: Baseline clinical, biochemical, bone-density, and body-composition characteristics stratified by SVR tertile. Values are mean ± standard deviation (SD), median (interquartile range), or n (%), as appropriate. Please click here to download this Table.
Table 2: Regression and interaction summary for the association between standardized SVR and BMD. The table includes sequential regression models, stratified models, interaction tests, sample sizes, beta coefficients, 95% confidence intervals, and P values. Please click here to download this Table.
Supplementary Figure 1. Model diagnostics for the three fully adjusted linear models. Panels show residual-versus-fitted, normal quantile–quantile (Q–Q) plots, scale-location, and Cook’s distance plots. Dashed Cook’s-distance lines indicate 4/n; no observation had Cook’s distance >1. Please click here to download this file.
Supplementary Table 1. Supplementary analyses and supporting statistical results. The table presents sensitivity analyses, missingness, blood pressure audit, sex-specific tertile summaries, field availability, interaction multiplicity, model diagnostics, HC3-robust estimates, and spline source results. Please click here to download this file.
Supplementary File 1. Reproducibility package for the study. This supplementary file contains the deidentified analytical dataset, figure and table source data, statistical analysis code, model outputs, data-quality rules, and package-version information used to reproduce the analyses reported in this study. Please click here to download this file.
Discussion
In this retrospective cross-sectional analysis, higher SVR was associated with higher areal BMD at the lumbar spine, femoral neck, and total hip after covariate adjustment. The apparent global-tertile pattern coincided with marked sex imbalance and was not reproduced in sex-specific unadjusted plots, underscoring the importance of continuous adjusted analyses. Spline analyses suggested increasing associations that flattened at higher SVR values, and HC3-robust estimates were similar to the primary results. These estimates are covariate-conditional associations and should not be interpreted as evidence that changing SVR will change BMD.
The results are consistent with the broader concept that diabetic skeletal fragility is shaped by more than areal BMD alone4. They also align with previous studies linking the ASM-to-VFA ratio with BMD in general and diabetic populations10,11. The present analysis contributes a large single-center dataset, three skeletal-site outcomes, sequential covariate adjustment, and subgroup visualization. It should therefore be interpreted as confirmatory and clinically contextual rather than as a first-in-field report.
The marked sex imbalance across the global SVR tertiles explains why their unadjusted BMD gradient should not be interpreted as an exposure effect. When tertiles were recalculated within sex, men showed modest inverse gradients whereas, women showed no statistically significant differences. In contrast, continuous covariate-adjusted models showed positive associations. These results indicate sensitivity to exposure categorization, sex distribution, and covariate structure and argue against using the descriptive tertiles as clinical cut points.
The component analyses also clarify the interpretation of the ratio. ASM was positively associated with all three BMD outcomes when ASM and VFA were entered together, whereas VFA showed a detectable inverse association only at the total hip. Exploratory interactions involving age, BMI, and glycemic control for total hip BMD remained significant after FDR correction, but they may reflect distributional differences, selection, measurement scale, or residual confounding and require independent replication.
Several biological pathways may explain the observed direction of the association. Skeletal muscle imposes mechanical loading on bone and also releases myokines that influence osteoblast and osteoclast activity9. In contrast, visceral adiposity is linked to insulin resistance, systemic inflammation, and altered adipokine signaling, all of which may disturb bone remodeling12,13. Aging and obesity can also impair skeletal muscle integrity and regenerative capacity14,15. Shared mesenchymal differentiation and genetic pathways may further connect osteoporosis, sarcopenia, obesity, and metabolic disease16. These mechanisms suggest that a high SVR may represent a metabolic and mechanical environment more favorable to skeletal maintenance.
Clinically, SVR should be regarded as contextual body-composition information rather than a diagnostic or treatment threshold. The study did not evaluate fractures, bone strength, treatment response, or prospective risk. Related observational evidence in postmenopausal women with T2DM provides additional context17.
This study has several limitations. First, its cross-sectional, single-center design precludes temporal or causal inference and limits generalizability beyond Chinese endocrinology inpatients. The analysis was conducted at the record level; unique individuals and repeat admissions could not be distinguished, and one admission identifier appeared in two nonidentical retained rows that could not be adjudicated against the source records. Second, the precise interval between BIA, DXA, anthropometry, and laboratory testing was not recorded, although all measurements were obtained during the same hospitalization. Historical instrument software versions and center-specific precision estimates were also unavailable. Third, VFA was estimated by BIA, which is sensitive to hydration status and prediction algorithms and is not equivalent to CT-, MRI-, or DXA-based compartment measurements. Fourth, residual confounding is likely because sufficiently complete information was unavailable for physical activity, menopausal status, sex hormones, vitamin D, calcium intake, anti-osteoporosis and diabetes medications, glucocorticoids, renal-bone parameters, muscle strength, falls, and other lifestyle or treatment factors. Fifth, the spline shapes are model dependent; residual non-normality and lumbar spine heteroscedasticity were present, although HC3-robust estimates were similar and no observation had a Cook's distance >1. Finally, the characteristics of the 675 pre-analysis exclusions could not be compared because only aggregate exclusion counts were available. Prospective multicenter studies with standardized same-day measurements, imaging-based visceral-fat assessment, detailed treatment and lifestyle covariates, and fracture or bone-quality outcomes are needed.
DATA AVAILABILITY:
The deidentified analytical dataset, figure and table source data, analysis code, model outputs, data-quality rules, and package-version information have been uploaded with the revised submission as Supplementary File 1.
Disclosures
The authors declare no competing interests.
Acknowledgements
This research was funded by the Clinical Research Project of Changzhou Medical Center, Nanjing Medical University (Grant No. CMCB202407).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Automated chemistry analyzer | Siemens | ADVIA 2400 | Biochemical assays |
| Automated hematology analyzer | Sysmex | XN-2800 | Hemoglobin and complete blood count measurements |
| Automated sphygmomanometer | Omron | U703 | Resting blood pressure measurement |
| Chemiluminescent immunoassay analyzer | Siemens | ADVIA Centaur XPT | Thyroid hormone measurements |
| Dual-energy X-ray absorptiometry scanner | Hologic | EXPLORER | Lumbar spine, femoral neck, and total hip BMD measurements |
| Height and weight scale | Hengqi Inc. | RGZ-120-RT | Anthropometric measurements |
| High-performance liquid chromatography analyzer | TOSOH | G8-90SL | HbA1c measurement |
| Multifrequency bioelectrical impedance analyzer | Biospace | InBody 720 | Appendicular skeletal muscle mass and visceral fat area measurements |
| R statistical software | R Foundation for Statistical Computing | Version 4.6.0 | Statistical analysis and figure generation |
References
- Compston JE, McClung MR, Leslie WD. Osteoporosis. Lancet. 2019;393(10169):364-76.
- Fan S, et al. Sarcopenic obesity and osteoporosis: Research progress and hot spots. Exp Gerontol. 2024;195:112544.
- Trajanoska K, et al. Assessment of the genetic and clinical determinants of fracture risk: genome wide association and mendelian randomisation study. Bmj. 2018;362:k3225.
- Khosla S, Samakkarnthai P, Monroe DG, Farr JN. Update on the pathogenesis and treatment of skeletal fragility in type 2 diabetes mellitus. Nat Rev Endocrinol. 2021;17(11):685-97.
- Hirschfeld HP, Kinsella R, Duque G. Osteosarcopenia: where bone, muscle, and fat collide. Osteoporos Int. 2017;28(10):2781-90.
- Chedraui P, Giannini A, Simoncini T. Osteo-sarcopenic obesity in midlife and older women: a current worldwide public health challenge. Climacteric. 2025;28(6):751-4.
- Hua Y, Fang J, Yao X, Zhu Z. Can waist circumference be a predictor of bone mineral density independent of BMI in middle-aged adults? Endocr Connect. 2021;10(10):1307-14.
- Yin Z, Yan H, Yu Y, Liu Y. Different associations between waist circumference and bone mineral density stratified by gender, age, and body mass index. BMC Musculoskelet Disord. 2022;23(1):786.
- Gries KJ, et al. Muscle-derived factors influencing bone metabolism. Semin Cell Dev Biol. 2022;123:57-63.
- Liu J, Ji F, Lee H, Kim JH. Association between the appendicular skeletal muscle mass-to-visceral fat area ratio and bone mineral density and osteoporosis: A cross-sectional study. Exp Gerontol. 2025;206:112772.
- Guo Y, et al. The associations between skeletal muscle mass to visceral fat area ratio (SVR) with bone mineral density (BMD) and 10-year probability of fracture risk in Chinese patients with type 2 diabetes mellitus (T2DM): a cross-sectional study. Endokrynol Pol. 2025;76(2):202-11.
- Lee K. Association of osteosarcopenic obesity and its components: osteoporosis, sarcopenia and obesity with insulin resistance. J Bone Miner Metab. 2020;38(5):695-701.
- Imerb N, Thonusin C, Chattipakorn N, Chattipakorn SC. Aging, obese-insulin resistance, and bone remodeling. Mech Ageing Dev. 2020;191:111335.
- Dungan CM, et al. In vivo analysis of γH2AX+ cells in skeletal muscle from aged and obese humans. FASEB J. 2020;34(5):7018-35.
- Munoz-Canoves P, Neves J, Sousa-Victor P. Understanding muscle regenerative decline with aging: new approaches to bring back youthfulness to aged stem cells. FEBS J. 2020;287(3):406-16.
- You Y, et al. WTAP-mediated m(6)A modification modulates bone marrow mesenchymal stem cells differentiation potential and osteoporosis. Cell Death Dis. 2023;14(1):33.
- Gao L, et al. Relationship between body composition and bone mineral density in postmenopausal women with type 2 diabetes mellitus. BMC Musculoskelet Disord. 2022;23(1):893.