This protocol presents a rat model of contrast-induced acute kidney injury and evaluates the post-contrast administration of N-acetylcysteine and montelukast, separately and in combination. The treatment regimens were associated with less severe renal dysfunction, oxidative stress, inflammation, and histopathological injury, although combined treatment did not consistently outperform monotherapy.
Method Article
Nephroprotective Effects of Post-contrast N-Acetylcysteine and Montelukast Treatment in a Rat Model of Contrast-induced Acute Kidney Injury
In This Article
Summary
Abstract
Contrast-induced acute kidney injury (CI-AKI) is an important complication of iodinated contrast exposure in which oxidative stress and inflammatory processes contribute to renal damage. This study established an experimental rat model of CI-AKI and examined the effects of treatment initiated after contrast administration with N-acetylcysteine (NAC), montelukast, or a combination of both. Adult male Wistar rats underwent water deprivation followed by sequential intravenous administration of Nω-nitro-L-arginine methyl ester (L-NAME), indomethacin, and iohexol. Treatment was initiated 1 h after completion of iohexol administration, approximately 1.5 h after L-NAME administration, and was continued once daily for 3 consecutive days. Renal function indices, oxidative stress parameters, inflammatory cytokines, renal injury biomarkers, and kidney histopathology were evaluated. The untreated CI-AKI group exhibited pronounced renal dysfunction, an unfavorable oxidative stress and inflammatory profile, and substantial histopathological damage. Compared with the untreated CI-AKI group, animals receiving NAC, montelukast, or the combined regimen generally showed improved biochemical and histopathological findings. Glutathione (GSH) levels were highest, and mean histopathological injury scores were numerically lowest in the combination group; however, combined treatment did not consistently outperform monotherapy across the assessed outcomes. This protocol provides a controlled preclinical framework for evaluating post-contrast interventions in CI-AKI, and the findings warrant further experimental investigation of NAC and montelukast without establishing clinical efficacy or a combination-specific advantage.
Introduction
Acute kidney injury (AKI) frequently complicates the course of hospitalized patients and contributes to increased morbidity, mortality, and healthcare resource use. As iodinated contrast media are routinely employed in diagnostic imaging and interventional procedures, deterioration of kidney function following contrast exposure has become an important clinical concern. Current nomenclature distinguishes contrast-associated acute kidney injury (CA-AKI), which encompasses any episode of AKI occurring after contrast administration, from contrast-induced acute kidney injury (CI-AKI), in which renal injury is causally attributed to the contrast agent. In controlled experimental models, where contrast exposure can be directly linked to renal damage, the term CI-AKI therefore remains widely used1,2.
Patients with chronic kidney disease, diabetes mellitus, advanced age, heart failure, or other cardiovascular comorbidities are particularly susceptible to CI-AKI. Kidney function recovers in many affected patients; however, persistent renal impairment, the need for renal replacement therapy, and an increased risk of death may occur in more severe cases. CI-AKI is also associated with longer hospitalization and greater use of healthcare resources. These adverse consequences underscore the continuing need to develop effective preventive and therapeutic approaches for contrast-related renal injury1,3,4,5.
The development of CI-AKI involves several interrelated processes, including altered renal perfusion, medullary oxygen imbalance, oxidative stress, inflammation, and direct tubular toxicity. Contrast exposure shifts intrarenal vascular tone toward vasoconstriction while weakening vasodilatory responses, thereby reducing renal blood flow. The outer medulla is particularly vulnerable because oxygen availability in this region is already limited under physiological conditions. A further decline in oxygen delivery after contrast administration may therefore precipitate hypoxic tubular injury2,6,7.
Renal hypoxia following contrast exposure is accompanied by increased generation of reactive oxygen species (ROS), which contributes substantially to kidney injury. When ROS production exceeds endogenous antioxidant capacity, oxidative damage may develop in cellular lipids, proteins, and DNA, while inflammatory signaling is simultaneously enhanced. In both experimental and clinical settings, contrast administration has been associated with increased oxidative stress parameters and impaired antioxidant defenses. Molecular pathways implicated in this response include nicotinamide adenine dinucleotide phosphate (NADPH) oxidase–dependent radical formation and activation of nuclear factor kappa-B (NF-κB)1,6,8,9.
The contribution of inflammation indicates that CI-AKI cannot be explained by hemodynamic disturbance alone. Recent evidence has also implicated ferroptosis, nitrosative stress, and neutrophil extracellular traps in renal injury following contrast exposure. Recognition of these additional mechanisms has broadened the range of molecular targets being investigated for the prevention and treatment of CI-AKI1.
Serum creatinine and urine output are commonly used to identify CI-AKI, but both may change only after renal injury has already developed. This limitation has encouraged the evaluation of earlier indicators, including kidney injury molecule-1 (KIM-1), which reflects tubular damage, and cystatin C, which is associated with changes in glomerular filtration. Evidence from experimental and clinical studies indicates that alterations in these biomarkers may become detectable during the early phase of CI-AKI and therefore support earlier assessment of renal injury9,10,11.
Advances in understanding the pathophysiology of CI-AKI have encouraged the evaluation of pharmacological interventions directed at oxidative and inflammatory pathways. Adequate hydration remains the principal preventive measure, whereas the reported benefits of drug-based approaches have varied across studies. Consequently, no pharmacological treatment has yet demonstrated sufficient consistent efficacy to be adopted as a standard clinical intervention for CI-AKI1,4,12,13.
N-acetylcysteine (NAC) has been widely evaluated as a pharmacological approach for limiting CI-AKI. Its proposed renoprotective effects are related to the scavenging of reactive species and the restoration of glutathione reserves. Early clinical support came from a landmark study of patients with chronic kidney disease, in which NAC reduced the incidence of contrast-related renal dysfunction14. Later clinical trials and evidence syntheses, however, produced inconsistent findings, with some studies reporting benefit and others showing no meaningful clinical effect. The effectiveness of NAC for CI-AKI, therefore, remains uncertain12,15,16,17.
Montelukast selectively blocks the cysteinyl leukotriene receptor-1 and has long been used to treat asthma and allergic disorders. Experimental evidence also indicates that this agent exerts anti-inflammatory, antioxidant, and anti-apoptotic effects. Across different models of renal injury, montelukast administration has been associated with reduced lipid peroxidation, strengthened endogenous antioxidant defenses, less severe histopathological damage, and attenuation of kidney injury18,19,20,21,22.
Evidence specifically examining montelukast in CI-AKI remains limited. Available experimental findings suggest that its renal effects may involve modulation of oxidative and inflammatory signaling. Reduced expression of NADPH oxidase 4 (NOX4), p22phox, and NF-κB has been proposed as one mechanism through which montelukast may attenuate contrast-related renal injury9.
NAC and montelukast influence partially distinct but overlapping pathways involved in renal injury. NAC primarily supports antioxidant defense, whereas montelukast has both anti-inflammatory and antioxidant actions. Concurrent administration of these agents may therefore affect multiple components of CI-AKI pathophysiology; however, whether their interaction produces an additive or synergistic benefit has not been established in experimental models18,19,20,21,22.
Previous investigations have predominantly evaluated interventions administered before contrast exposure, whereas evidence concerning treatments initiated after exposure remains scarce. In particular, post-contrast administration of montelukast together with NAC has received limited investigation in experimental CI-AKI. The present study therefore evaluated montelukast and NAC, administered after contrast exposure either separately or in combination, with respect to renal function, oxidative stress parameters and antioxidant defenses, renal injury and inflammatory biomarkers, and histopathological alterations in a rat model of CI-AKI.
Protocol
All experimental procedures involving animals were conducted in accordance with internationally accepted guidelines for the care and use of laboratory animals and complied with the Animal Research: Reporting of In Vivo Experiments (ARRIVE) guidelines. The experimental protocol was approved by the Ahi Evran University Animal Experiments Local Ethics Committee, Kırşehir, Turkey (Decision No. 2, Meeting No. 12, Date: 12 June 2025). Every effort was made to minimize animal suffering and to reduce the number of animals used throughout the study. The details of all the reagents and the equipment used are listed in the Table of Materials.
Preparation of chemicals
Nω-nitro-L-arginine methyl ester (L-NAME), indomethacin, iohexol, montelukast sodium, and NAC were used in this study. A 10 mg/mL L-NAME solution was prepared in sterile 0.9% normal saline using 1 g of L-NAME per 100 mL. The solution was freshly prepared on the day of administration and used without storage beyond that day. For induction of the experimental CI-AKI model, L-NAME was administered intravenously (IV) at 10 mg/kg. In a rat weighing approximately 220 g, the calculated amount was approximately 2.2 mg, corresponding to an administration volume of approximately 0.22 mL. Indomethacin was prepared in 5% sodium bicarbonate solution at a concentration of 10 mg/mL by dissolving 100 mg in a final volume of 10 mL. The preparation was vortexed until visually homogeneous. The final pH of the prepared indomethacin solution was not measured during the experiment and therefore could not be retrospectively determined. A specific sterility or filtration procedure for the prepared indomethacin solution was not documented in the experimental records and, therefore, could not be reported retrospectively. No formal stability interval was established or evaluated; the solution was freshly prepared and used on the same day. To induce the experimental CI-AKI model, indomethacin was administered intravenously at 10 mg/kg. For a rat weighing approximately 220 g, the calculated amount was approximately 2.2 mg, corresponding to an administration volume of approximately 0.22 mL.
The commercial iohexol formulation, containing 647 mg iohexol/mL and an equivalent iodine concentration of 300 mg/mL, was administered without additional dilution. The exact temperature of iohexol at the time of injection was not recorded. A formulation-specific osmolality value could not be reliably verified from the available experimental records and is therefore not reported. For induction of the experimental CI-AKI model, iohexol was administered intravenously at 3 g iodine/kg. In a rat weighing approximately 220 g, this dose provided approximately 0.66 g of iodine and corresponded to an injection volume of approximately 2.2 mL.
A montelukast sodium suspension was prepared in 0.5% carboxymethyl cellulose (CMC). It was freshly prepared on each administration day and vortexed immediately before dosing to obtain an even distribution of suspended particles. The montelukast dose required for each animal was calculated separately from the body weight recorded at study initiation using the following formula: required dose (mg) = body weight (kg) × 10 mg/kg. For an animal weighing approximately 220 g, the calculated dose was approximately 2.2 mg and was delivered by oral gavage. The suspension was visually inspected before each administration, and any preparation showing sedimentation was vortexed again before use.
NAC was administered to the treatment groups from its commercial formulation without further dilution at an intraperitoneal dose of 100 mg/kg. For each animal, the required dose was calculated individually from the body weight recorded at study initiation. In an animal weighing approximately 220 g, this corresponded to approximately 22 mg of NAC and an administration volume of approximately 0.15 mL. Before dosing, the solution was examined visually, and only preparations that were clear and free of visible particles were used.
Each preparation underwent visual inspection before administration. The L-NAME, indomethacin, iohexol, and NAC solutions were checked for discoloration and visible particles. Immediately before administration, the montelukast suspension was vortexed and examined visually to confirm uniformity. Any preparation that failed to satisfy these acceptance criteria was not used. Laboratory coats, protective gloves, and eye protection were worn during the preparation and administration of all chemicals. All procedures complied with institutional laboratory safety and biosafety requirements.
Animal selection, housing, experimental groups, and randomization
Thirty adult male Wistar albino rats (8–12 weeks old; body weight, 200–220 g) were obtained from the Experimental Animal Research Laboratory of Ahi Evran University, Kırşehir, Türkiye. Male rats were selected to maintain methodological consistency with previously published experimental CI-AKI models and to avoid introducing estrous-cycle stage as an additional biological variable. Sex was not evaluated as an experimental variable in the present study. The animal facility held a breeding/production license no. 184, and the rats were bred and maintained there under standard laboratory conditions. At enrollment, the animals had no documented specific pathogen-free (SPF) status or other formally assigned microbiological health classification. Each rat was housed separately in a polycarbonate cage measuring 40 cm × 25 cm × 20 cm, with coarsely chopped pine shavings used as bedding. Room conditions were maintained at 24 °C ± 2 °C and 35% ± 10% relative humidity by an automated environmental control and ventilation system. A 12 h light/12 h dark schedule was applied, with illumination from 07:00 to 19:00. No dedicated environmental enrichment was supplied during the 7-day acclimatization phase or the subsequent experimental period. Standard pelleted rodent feed and tap water were available ad libitum, apart from the defined 16 h period of water deprivation preceding CI-AKI induction. The feed composition was 24% crude protein, 3.94% crude cellulose, 5.08% crude fat, 8.8% crude ash, 1.44% lysine, 0.61% methionine, 1.14% calcium, 0.89% phosphorus, and 0.28% sodium. All animals were acclimatized for 7-days before the experimental procedures began. Daily observations were conducted during both the acclimatization and experimental periods to assess general condition, food and water consumption, mobility, posture, coat appearance, and any signs of distress. To minimize selection bias, the animals were allocated to the five experimental groups using a computer-generated random allocation sequence with six animals assigned to each group. The sample size was determined by an a priori power analysis using G*Power version 3.1.9.6.
The sample size was determined by an a priori power analysis for a fixed-effects one-way analysis of variance involving five experimental groups. Assuming an effect size (f) of 0.65, a type I error rate (α) of 0.05, and a statistical power of 80%, the required total sample size was calculated as 30 animals, corresponding to six animals per group. The effect size (f = 0.65) was assumed a priori to represent a large overall between-group effect for the five-group comparison. The calculation was intended to determine the sample size required to detect such an overall effect and was not specifically designed to detect smaller pairwise differences between the active treatment groups. The individual animal was considered the experimental unit for all analyses.
Except for routine husbandry, daily health monitoring, and terminal procedures, animals in the Control group did not undergo protocol-related handling or restraint, water deprivation, intravenous or intraperitoneal injections, oral gavage, or vehicle administration. The CI-AKI group comprised animals in which the CI-AKI model was established on day 8 and that received no treatment. The CI-AKI + Montelukast group comprised animals in which the CI-AKI model was established and that were subsequently treated with montelukast. The CI-AKI + NAC group comprised animals in which the CI-AKI model was established and that were subsequently treated with NAC. The CI-AKI + Montelukast + NAC group comprised animals in which the CI-AKI model was established and that were subsequently treated with a combination of montelukast and NAC. Neither the Control group nor the untreated CI-AKI group underwent treatment-matched sham procedures. Specifically, no sham handling, sham oral gavage, sham treatment injections, or treatment-matched vehicle administrations were performed in these groups. The vehicles used for the preparation of L-NAME, indomethacin, and montelukast were 0.9% normal saline, 5% sodium bicarbonate solution, and 0.5% CMC, respectively, as described in the preparation of chemicals. NAC was administered from its commercial formulation without further dilution, and no separate vehicle was prepared for NAC. On day 8, all animals except those in the Control group underwent 16 h of water deprivation, followed by sequential intravenous administration of L-NAME (10 mg/kg), indomethacin (10 mg/kg), and iohexol (3 g iodine/kg) to induce contrast-induced acute kidney injury. In the designated treatment groups, montelukast (10 mg/kg, oral gavage) and/or NAC (100 mg/kg, intraperitoneal injection) were first administered 1 h after completion of iohexol administration on day 8, corresponding to approximately 1.5 h after L-NAME administration, and were subsequently administered once daily at the same time on days 9 and 10.
Drug administration protocol
CI-AKI was established according to a published experimental protocol consisting of 16 h of water deprivation followed by sequential intravenous administration of L-NAME, indomethacin, and iohexol23,24,25. L-NAME and indomethacin were each given at 10 mg/kg, whereas iohexol was administered at 3 g iodine/kg. The treatment doses were 10 mg/kg for montelukast sodium and 100 mg/kg for NAC. Selection of the model-induction and treatment doses was guided by previously published experimental studies22,26,27. No preliminary dose-ranging or dose-optimization study was performed. The NAC and montelukast doses were selected independently based on previously published experimental studies of the individual agents and were not derived from a combination-specific dose-finding study. The selected doses were not intended to represent pharmacologically equipotent exposures, and no dose-response or formal drug-interaction analysis was performed. No prespecified numerical or laboratory threshold was used to define successful model induction at the individual-animal level. At the study endpoint, successful establishment of renal injury was supported by the characteristic histopathological alterations observed in the untreated CI-AKI group compared with the Control group. On day 8, all animals except those in the Control group underwent a single 16 h period of water deprivation immediately before induction of contrast-induced acute kidney injury. Water deprivation was not repeated during the remainder of the experimental period. Standard pelleted chow remained available ad libitum throughout the water-deprivation period. Upon completion of the single 16 h water-deprivation period, access to tap water was restored simultaneously and ad libitum in all water-deprived experimental groups, before administration of the first model-inducing agent, L-NAME, and was maintained for the remainder of the experimental period. The timing and conditions of water restoration were identical across all water-deprived groups. Water intake after restoration was not restricted to a predefined volume and was not quantitatively measured. Paired body weights immediately before and after the 16 h water-deprivation period were not measured; therefore, dehydration-associated percentage body weight loss could not be calculated. Urine output was not quantitatively monitored. Following restoration of water access, induction of CI-AKI was initiated. All sequential intravenous administrations of L-NAME, indomethacin, and iohexol were performed through a lateral tail vein using a 26 G needle attached to a sterile 5 mL syringe. Before intravenous administration, the tail was warmed in water for several minutes to facilitate visualization and dilation of the lateral tail veins. Following each intravenous administration, the vein was flushed with 0.5 mL of sterile 0.9% normal saline, in addition to the calculated administration volume of the respective model-inducing agent. The injection site was visually monitored throughout administration and flushing for swelling, leakage, or evidence of extravasation. L-NAME (10 mg/kg) was administered first. Fifteen minutes after L-NAME administration, indomethacin (10 mg/kg) was administered intravenously through the same lateral tail vein. Fifteen minutes after indomethacin administration, iohexol was administered intravenously through the same lateral tail vein at a dose of 3 g iodine/kg. For each animal, the iohexol dose and corresponding injection volume were calculated individually based on the body weight recorded at study initiation and the commercial iodine concentration of 300 mg iodine/mL. This corresponded to an administration volume of 10 mL/kg and, therefore, approximately 2.0–2.2 mL for rats weighing 200–220 g. No separate protocol-defined maximum permitted intravenous volume was prespecified; the largest single-agent intravenous administration used in this study was iohexol at 10 mL/kg. Iohexol was administered slowly over approximately 1–2 min. Successful intravenous administration was verified by the absence of visible swelling, leakage, or extravasation at the injection site. No partial extravasation was observed, and no injection required reattempt or repeat dosing because of suspected extravasation. One hour after completion of iohexol administration, the designated treatments were first administered to the treatment groups. Because iohexol administration was initiated 30 min after L-NAME administration and completed over approximately 1–2 min, treatment initiation occurred approximately 91–92 min (about 1.5 h) after L-NAME administration. Montelukast sodium (10 mg/kg) was administered by oral gavage, whereas NAC (100 mg/kg) was administered intraperitoneally.
Oral gavage was performed using a 22 G stainless-steel feeding cannula. Each animal was maintained in an upright position, and the feeding cannula was gently advanced through the esophagus into the stomach. If excessive resistance was encountered, the cannula was withdrawn and repositioned before administration. The animal was observed for regurgitation during and immediately after gavage. No regurgitation or other evidence of incomplete oral dosing was observed during or immediately after gavage in any animal, and no animal was excluded on the basis of suspected unsuccessful oral administration. Intraperitoneal injections were administered into the lower right quadrant of the abdomen. The needle was inserted at an angle of approximately 30°–45°, and aspiration was performed before administration to check for inadvertent vascular entry. The injection site was visually monitored during and immediately after administration for leakage, bleeding, or other visible complications. The designated treatments were administered once daily at the same time on days 8, 9, and 10. Accordingly, animals in the CI-AKI + Montelukast group received montelukast once daily for three consecutive days, animals in the CI-AKI + NAC group received NAC once daily for three consecutive days, and animals in the CI-AKI + Montelukast + NAC group received both montelukast and NAC once daily according to the same 3-day treatment schedule. All model-induction and treatment administrations were performed by the same investigator. Body weight was measured once for each animal at study initiation and was not remeasured during the experimental period. For each animal, the dose and corresponding administration volume of all model-inducing agents and study treatments were calculated individually using the body weight recorded at study initiation. All intravenous, intraperitoneal, and oral gavage procedures were performed using the same standardized technique to minimize administration-related variability.
Euthanasia procedure, humane endpoints, and sample collection
Animals were observed once daily throughout the experiment for changes in general condition, food and water consumption, mobility, posture, coat appearance, and evidence of distress. The prospectively defined humane endpoints comprised marked lethargy, inability to access or consume available food or water, abnormal posture, reduced mobility, persistent piloerection, and any other overt manifestation of distress. Animals meeting any of these criteria were to undergo immediate euthanasia; however, no animal fulfilled the humane endpoint criteria during the study. On day 11, 24 h after the final treatment, deep anesthesia was induced by intraperitoneal administration of ketamine (80 mg/kg) together with xylazine (10 mg/kg). The absence of the pedal withdrawal response was used to verify an adequate anesthetic plane. Once sufficient anesthetic depth had been confirmed, approximately 3–5 mL of blood was obtained from each animal by intracardiac puncture. Euthanasia was then completed by exsanguination while the animal remained under deep anesthesia. The absence of both cardiac activity and spontaneous respiration was used to confirm death.
Blood collected for serum biochemical measurements was placed in anticoagulant-free tubes and left until clotting was complete. The tubes were then centrifuged at 3,000 × g for 10–15 min at 4 °C, after which the serum fraction was separated and stored at −80 °C until analysis. Samples intended for glutathione measurement were collected separately in tubes containing ethylenediaminetetraacetic acid (EDTA). Because these specimens were anticoagulated, they were processed without a clotting stage in accordance with the corresponding glutathione assay procedure. Serum separation was considered acceptable when the recovered serum was clear and showed no visible evidence of hemolysis.
Once death had been confirmed, a median laparotomy was carried out and both kidneys were carefully removed from each animal. Surrounding adipose and connective tissues were cleared from the specimens. The right kidney was reserved solely for histopathological examination, whereas the left kidney was assigned to biochemical analysis. Mixed tissue from the left kidney was analyzed without separately dissecting the renal cortex and medulla. The two kidneys were handled independently, and specimens from different animals remained separate throughout processing without pooling. The entire right kidney was placed in 10% neutral buffered formaldehyde and processed for histopathological assessment. Sections encompassing the renal cortex and outer medulla were prepared and examined according to the procedures described in the histopathological processing and scoring. Each left kidney was labeled individually and maintained at -80 °C until homogenization and biochemical testing. After excision, gross tissue integrity was checked, and an adequate amount of tissue was retained for the intended histopathological and biochemical assessments.
The investigator responsible for model induction and treatment administration could not be blinded because the experimental groups underwent different procedures. However, group identities were concealed from the investigators conducting the biochemical and statistical analyses and from the pathologist performing the histopathological assessments. All enrolled animals were retained in the study and included in the subsequent analyses. Biological samples, animal tissues, formaldehyde-based fixatives, and other chemical waste materials were handled with appropriate personal protective equipment. Disposal of all biological and chemical waste was carried out in compliance with institutional biosafety and hazardous-waste management requirements.
Biochemical analyses
Biochemical measurements were conducted using serum, EDTA-anticoagulated blood, and left-kidney tissue homogenates collected from each animal. The procedures are presented below according to the biological matrix used for each parameter. Serum was analyzed for urea, blood urea nitrogen (BUN), creatinine, superoxide dismutase (SOD), and malondialdehyde (MDA). Urea, BUN, and creatinine served as renal function indices, whereas SOD activity and MDA concentration were evaluated as oxidative stress parameters. Serum urea and BUN values were obtained using the same enzymatic urease–glutamate dehydrogenase assay. In this method, urea was hydrolyzed by urease to produce ammonia, which subsequently reacted with 2-oxoglutarate and reduced nicotinamide adenine dinucleotide (NADH) in the presence of glutamate dehydrogenase. The analytical method used was an enzymatic urease–glutamate dehydrogenase kinetic assay. The decrease in absorbance resulting from NADH consumption was measured kinetically using a spectrophotometer. Serum creatinine concentration was measured colorimetrically using an automated biochemistry analyzer. Serum SOD activity was measured colorimetrically using a commercially available assay kit on the same automated biochemistry analyzer. The SOD assay was based on the generation of superoxide radicals by the xanthine–xanthine oxidase system and their reaction with 2-(4-iodophenyl)-3-(4-nitrophenyl)-5-phenyltetrazolium chloride to form a colored formazan product. The endpoint absorbance was measured at 505 nm, and SOD activity was expressed as U/mL. Serum MDA concentration was determined colorimetrically using the thiobarbituric acid reaction. Serum samples were mixed with cold trichloroacetic acid to precipitate proteins, and the resulting precipitate was separated by centrifugation. This centrifugation step was performed at 7,500 × g for 5 min at 4 °C. The supernatant was reacted with thiobarbituric acid at 90 °C for 60 min, cooled, and measured at 532 nm. MDA concentrations were calculated from the corresponding calibration curve and expressed as nmol/mL. Glutathione (GSH) analysis was performed using EDTA-anticoagulated blood. Proteins were precipitated with trichloroacetic acid, and the resulting deproteinized samples were analyzed colorimetrically by a modified Ellman method. The samples were combined with 5,5′-dithiobis(2-nitrobenzoic acid) (DTNB) in 500 mM Tris buffer at pH 8.2. Reaction of the thiol groups of GSH with DTNB generated a colored product, and absorbance was recorded at 412 nm. Catalase (CAT) activity was determined using a two-step colorimetric procedure. Samples were initially incubated with a known amount of hydrogen peroxide, which catalase converted to water and molecular oxygen. After the enzymatic reaction was terminated, residual hydrogen peroxide was measured using a chromogenic reagent. Absorbance was recorded at 405 nm, and CAT activity was reported as U/mL. For renal tissue measurements, the left kidney from each animal was used as mixed tissue without separating the cortex from the medulla. As stated in the procedure, the right kidney was retained solely for histopathological assessment. Samples belonging to individual animals were processed independently and were not pooled at any stage. Each left-kidney specimen was homogenized on ice in 50 mM phosphate buffer at pH 7.4 using a tissue-to-buffer ratio of 1:10 (w/v). One animal-specific renal tissue homogenate was generated for each rat. Separate aliquots of this homogenate were used for the different renal tissue measurements, ensuring that all parameters were derived from the same individual animal. The resulting renal tissue homogenates were centrifuged at 14,000 × g for 10 min at 4 °C. Following centrifugation, the supernatant obtained from each animal was collected separately and divided into aliquots for the planned renal tissue analyses. Tumor necrosis factor-alpha (TNF-α), interleukin-1 beta (IL-1β), interleukin-6 (IL-6), cystatin C, and KIM-1 concentrations in the renal tissue supernatants were measured using rat-specific enzyme-linked immunosorbent assay (ELISA) kits. The assays were performed according to the manufacturer’s protocols. The incubation conditions were identical for the TNF-α, IL-1β, IL-6, cystatin C, and KIM-1 ELISAs. For each assay, the samples and ELISA reagents were incubated for 1 h at 37 °C; after five washing cycles, substrate solutions A and B were added and incubated for 10 min at 37 °C. Briefly, standards and renal tissue supernatants were added to the antibody-precoated wells, followed by the corresponding biotinylated detection antibody and streptavidin–horseradish peroxidase conjugate. After the specified incubation steps, unbound components were removed using an automated microplate washer. The substrate solution was subsequently added, and the color reaction was terminated using the acidic stop solution. Absorbance was measured at 450 nm using a microplate reader, and analyte concentrations were calculated from the corresponding standard curves. Renal tissue ELISA measurements were performed in duplicate. For each analyte, the mean of the two technical replicate wells was calculated to obtain a single animal-level value. Technical replicate wells and separate aliquots obtained from the same animal-specific homogenate were not considered independent observations. All biochemical measurements were performed under standardized assay-specific conditions. Serum, EDTA-anticoagulated blood, and renal tissue samples were processed separately according to the requirements of the corresponding analytical methods. Investigators performing the biochemical analyses were blinded to group allocation. The individual animal, rather than each serum sample, blood sample, kidney specimen, homogenate aliquot, or technical replicate well, was considered the experimental unit. Accordingly, six independent animal-level observations were included in the statistical analysis for each experimental group.
Histopathological processing and scoring
Right-kidney specimens were prepared for microscopic evaluation by routine histological processing. The whole right kidney from each animal was immersed in 10% neutral buffered formaldehyde for 72 h at room temperature. After fixation, tissue dehydration was performed sequentially in 50%, 70%, 80%, 96%, and 100% ethanol, with each concentration applied for 1 h. The specimens were then exposed to two xylene baths for 30 min per bath before paraffin embedding. Using a rotary microtome, 5 µm sections that included both the renal cortex and outer medulla were obtained from the paraffin blocks.
For hematoxylin and eosin (HE) staining, the sections were deparaffinized and rehydrated, exposed to hematoxylin for 5 min, and washed under running tap water for an additional 5 min. Acid alcohol was used for differentiation, after which the sections were blued in ammoniated water for 1 min and counterstained with eosin for 2 min. The stained sections were subsequently dehydrated in ascending alcohol concentrations, cleared with xylene, and mounted permanently under coverslips.
Sections designated for Masson’s trichrome staining were likewise deparaffinized and rehydrated. Mordant treatment was performed for 60 min at 56 °C, followed by rinsing under running tap water for 10 min. The sections were then treated sequentially with Weigert’s iron hematoxylin for 10 min, Biebrich scarlet–acid fuchsin solution for 15 min, phosphotungstic acid solution for 10 min, and aniline blue solution for 10 min. After immersion in 1% acetic acid for 5 min, the sections were dehydrated, cleared in xylene, and mounted with coverslips.
Before microscopic assessment, the adequacy of staining was verified separately for each method. HE-stained sections were considered suitable when nuclear details and cytoplasmic contrast were clearly discernible, whereas Masson’s trichrome-stained sections were accepted when connective tissue structures could be distinctly visualized. For each animal, three HE-stained sections and three Masson’s trichrome-stained sections were examined. Five randomly selected microscopic fields were evaluated in each section using a 40× objective. Accordingly, 15 microscopic fields per staining method were examined for each animal. All microscopic examinations were performed using the same objective and standardized evaluation conditions across all animals and experimental groups. Masson’s trichrome-stained sections were evaluated qualitatively for interstitial collagen distribution and deposition, extracellular matrix accumulation, and tubulointerstitial architecture. These sections were not used to generate the semi-quantitative 0–3 histopathological injury scores. Representative HE- and Masson’s trichrome-stained photomicrographs were acquired using a 40× objective, and a 100 µm scale bar was included in each representative image. These photomicrographs were obtained for illustrative purposes and were not treated as independent observations in the histopathological scoring or statistical analyses. All histopathological assessments were conducted by one experienced pathologist who remained blinded to the experimental group identities. Using a single blinded examiner was intended to limit assessment bias and variation attributable to differences between observers. Tubular necrosis, tubular dilatation, cellular degeneration, and vascular congestion were scored semi-quantitatively on HE-stained renal sections according to a system adapted from previously published renal injury models28,29. For each parameter, scores ranged from 0 to 3, corresponding to absent, mild, moderate, and severe histopathological damage, respectively. For each animal, the findings from the five microscopic fields examined in each of the three HE-stained sections, corresponding to 15 fields in total, were considered collectively to assign a single 0–3 score for each histopathological parameter. Thus, each animal contributed one score for tubular necrosis, tubular dilatation, cellular degeneration, and vascular congestion. Histological sections and microscopic fields were treated as within-animal subsamples and were not considered independent observations. Within each section, microscopic fields were randomly selected from comparable renal cortical and outer medullary regions to standardize anatomical sampling across animals and experimental groups. The individual animal, rather than each kidney, histological section, or microscopic field, was considered the experimental unit. Accordingly, six independent animal-level observations were included in the statistical analysis for each experimental group. The values presented in Table 3 represent the group means calculated from the individual animal-level scores of the six animals in each experimental group.
Statistical analysis
Statistical analyses were performed using statistical analysis software. The individual animal was considered the experimental unit for all statistical analyses. Each experimental group comprised six independent animals (n = 6 per group). Technical replicates, assay wells, tissue sections, and microscopic fields were not treated as independent observations and were not used to increase the statistical sample size. Continuous variables are presented as mean ± standard deviation (SD). Normality was evaluated separately within each experimental group using the Shapiro–Wilk test, and homogeneity of variances was assessed using Levene’s test. Given the fully balanced experimental design with equal sample sizes across groups, a one-way analysis of variance (ANOVA) was used to compare groups. Pairwise comparisons were performed using Duncan’s post hoc multiple comparison test. Potential outliers were evaluated by graphical examination of boxplots and inspection of individual observations. No observation was considered to represent a measurement error or an invalid experimental result, and no data point was excluded on statistical grounds. A p-value < 0.05 was considered statistically significant.
Results
Serum kidney function markers (urea, blood urea nitrogen, and creatinine)
The experimental design, animal grouping, treatment schedule, and sample collection timeline of the present study are summarized in Figure 1. Statistically significant differences were observed among the groups for serum urea, BUN, and creatinine levels (p = 0.003, p = 0.003, and p = 0.002, respectively). The mean serum urea level was 67.43 mg/dL ± 53.11 mg/dL in the Control group and increased to 606.71 mg/dL ± 429.42 mg/dL in the CI-AKI group. Similarly, the mean BUN level increased from 31.51 mg/dL ± 24.82 mg/dL in the Control group to 268.63 mg/dL ± 190.84 mg/dL in the CI-AKI group. Serum creatinine levels also increased markedly, from 0.60 mg/dL ± 0.05 mg/dL in the Control group to 3.27 mg/dL ± 2.14 mg/dL in the CI-AKI group. Duncan’s post hoc comparisons demonstrated that serum urea, BUN, and creatinine levels were significantly lower in each treatment group, the CI-AKI + Montelukast, CI-AKI + NAC, and CI-AKI + Montelukast + NAC groups, than in the untreated CI-AKI group (all p < 0.05). Data for serum renal function markers are presented in Table 1.
Oxidative stress parameters and antioxidant enzyme activities
Statistically significant differences were observed among the groups in terms of SOD, GSH, CAT, and MDA levels (p = 0.044, p = 0.001, p = 0.003, and p = 0.001, respectively; Table 1). Duncan’s post hoc analysis showed that GSH levels were significantly higher in the montelukast, NAC, and combination-treatment groups than in the untreated CI-AKI group (all p < 0.05). The combination group also had a significantly higher GSH level than the Control group (p < 0.05). However, no statistically significant differences were observed between the combination group and either monotherapy group or between the two monotherapy groups (all p > 0.05). The lowest SOD level was observed in the CI-AKI group (92.23 U/mL ± 16.37 U/mL), whereas the Control group showed 147.81 U/mL ± 33.27 U/mL. GSH levels were lowest in the CI-AKI group (66.05 mmol/L ± 24.72 mmol/L) and highest in the CI-AKI + Montelukast + NAC group (172.44 mmol/L ± 60.48 mmol/L). CAT activity was highest in the Control group (93.35 U/mL ± 18.75 U/mL) and lowest in the CI-AKI group (33.22 U/mL ± 17.07 U/mL). With respect to MDA levels, the highest value was observed in the CI-AKI group (54.13 nmol/mL ± 19.37 nmol/mL), whereas the lowest value was recorded in the CI-AKI + NAC group (21.53 nmol/mL ± 5.07 nmol/mL). Data regarding oxidative stress parameters and antioxidant enzyme activities are presented in Table 1.
Renal injury and inflammatory biomarkers (KIM-1, Cystatin C, TNF-α, IL-1β, and IL-6)
Statistically significant differences were observed among the groups with respect to renal cystatin C, IL-6, KIM-1, TNF-α, and IL-1β levels (p < 0.001, p = 0.008, p = 0.027, p = 0.006, and p < 0.001, respectively; Table 2). Duncan’s post hoc comparisons showed that cystatin C, IL-6, KIM-1, TNF-α, and IL-1β levels were significantly lower in each treatment group, the CI-AKI + Montelukast, CI-AKI + NAC, and CI-AKI + Montelukast + NAC groups, than in the untreated CI-AKI group (all p < 0.05). For IL-1β, a statistically significant difference was also observed between the CI-AKI + Montelukast and CI-AKI + NAC groups (p < 0.05). Renal cystatin C levels were highest in the CI-AKI group (18.43 ng/mL ± 1.06 ng/mL), whereas the Control group exhibited a value of 10.30 ng/mL ± 0.78 ng/mL. Similarly, IL-6 levels were highest in the CI-AKI group (13.41 ng/L ± 2.14 ng/L) and lowest in the Control group (9.29 ng/L ± 2.70 ng/L). KIM-1 levels were highest in the CI-AKI group (3.07 ng/mL ± 0.36 ng/mL), compared with 2.25 ng/mL ± 0.54 ng/mL in the Control group. Likewise, TNF-α levels were highest in the CI-AKI group (161.69 ng/L ± 26.14 ng/L), whereas the lowest were observed in the Control group (95.49 ng/L ± 16.98 ng/L). IL-1β levels were highest in the CI-AKI group (9.28 ng/mL ± 0.68 ng/mL), while the lowest value was observed in the CI-AKI + Montelukast group (7.34 ng/mL ± 0.57 ng/mL). Data regarding renal injury and inflammatory biomarkers are presented in Table 2. Importantly, although some biochemical marker values in the CI-AKI + Montelukast + NAC group were numerically higher than those in the CI-AKI + Montelukast group, Duncan’s post hoc comparisons showed no statistically significant differences between these two treatment groups for any of the evaluated biochemical variables, including oxidative stress parameters, renal injury biomarkers, and inflammatory biomarkers (p > 0.05).
Histopathological evaluation
Histopathological findings
Kidney sections stained with HE demonstrated preserved renal architecture in the Control group, with normal glomerular and tubular morphology. In contrast, the untreated CI-AKI group exhibited marked histopathological alterations, including tubular epithelial injury, widespread cellular degeneration, tubular dilatation, cellular debris within tubular lumina, and vascular congestion. Necrotic changes were particularly evident in the proximal tubular segments. In the CI-AKI + Montelukast group, the severity of tubular injury was reduced compared with the untreated CI-AKI group, although focal degenerative changes remained evident. Similarly, the CI-AKI + NAC group showed better preservation of tubular epithelial integrity and fewer necrotic areas. On qualitative histopathological examination, renal architecture appeared preserved in the CI-AKI + Montelukast + NAC group, with largely preserved cortical and medullary structures and relatively limited tubular necrosis, tubular dilatation, cellular degeneration, and vascular congestion. Masson’s trichrome–stained sections revealed a normal distribution of interstitial collagen in the Control group. In the untreated CI-AKI group, increased interstitial collagen deposition, tubulointerstitial architectural disorganization, and extracellular matrix accumulation were observed. These alterations appeared less pronounced in the treatment groups, including the combined treatment group, compared with the untreated CI-AKI group. Representative HE- and Masson’s trichrome-stained kidney sections illustrating these findings are presented in Figure 2.
Semi-quantitative histopathological scoring
Semi-quantitative histopathological assessment demonstrated that tubular necrosis, tubular dilatation, cellular degeneration, and vascular congestion scores were highest in the untreated CI-AKI group. Mean scores in this group were 2.67, 2.83, 2.67, and 2.50, respectively. The relatively high mean scores, approaching the upper limit of the 0–3 scale, were consistent with the widespread and severe tubular and vascular alterations observed on qualitative histopathological examination in the same group. In contrast, all parameters were absent in the Control group. Lower injury scores were observed in all treatment groups compared with the untreated CI-AKI group. The CI-AKI + Montelukast group exhibited mean scores of 1.33 for tubular necrosis, 1.50 for tubular dilatation, 1.17 for cellular degeneration, and 1.00 for vascular congestion. Corresponding values in the CI-AKI + NAC group were 1.17, 1.17, 0.83, and 0.83, respectively. Numerically, the lowest mean histopathological injury scores were observed in the CI-AKI + Montelukast + NAC group, with mean values of 0.50, 0.67, 0.50, and 0.17 for tubular necrosis, tubular dilatation, cellular degeneration, and vascular congestion, respectively. Detailed histopathological scoring data are presented in Table 3.
The raw data underlying all biochemical and histopathological analyses, original uncropped HE and Masson’s trichrome histology images are provided as Supplementary File 1.
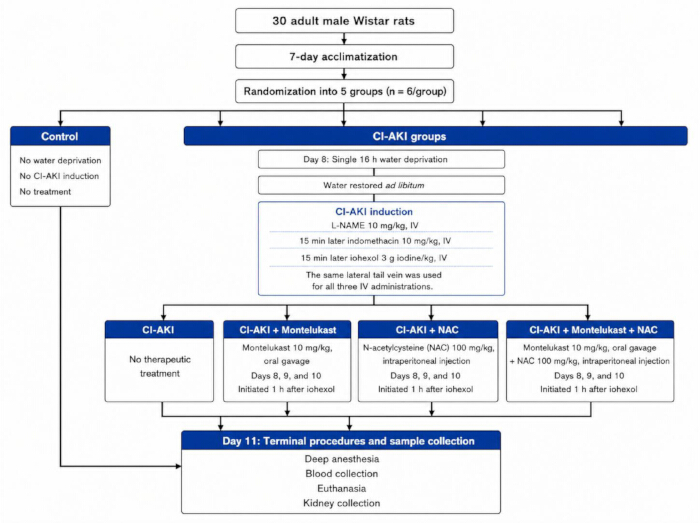
Figure 1: Experimental design and study timeline. Schematic representation of the experimental workflow. Thirty adult male Wistar rats were randomized into five groups (n = 6 per group) after a 7-day acclimatization period. The Control group underwent no water deprivation, CI-AKI induction, or treatment. The remaining groups underwent a single 16 h water-deprivation period followed by sequential intravenous administration of L-NAME (10 mg/kg), indomethacin (10 mg/kg), and iohexol (3 g iodine/kg) to induce CI-AKI. One hour after iohexol administration, the designated treatment groups received montelukast (10 mg/kg, oral gavage), NAC (100 mg/kg, intraperitoneal injection), or both once daily on days 8–10, whereas the untreated CI-AKI group received no therapeutic treatment. All groups underwent terminal procedures and sample collection on day 11. Please click here to view a larger version of this figure.
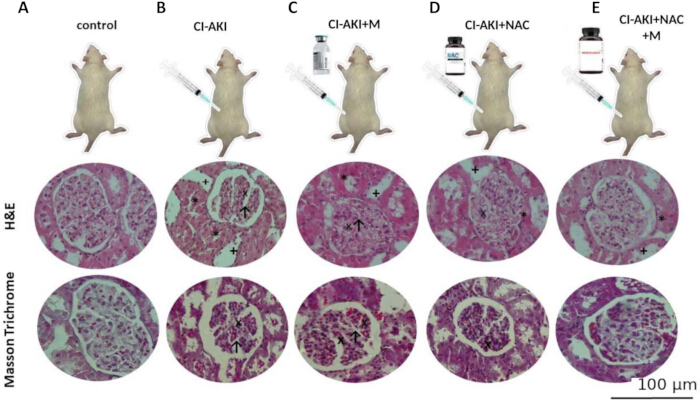
Figure 2: Representative HE- and Masson’s trichrome-stained kidney sections from experimental groups. Representative HE and Masson’s trichrome–stained kidney sections obtained from the (A) Control, (B) CI-AKI, (C) CI-AKI + Montelukast, (D) CI-AKI + NAC, and (E) CI-AKI + Montelukast + NAC groups. HE-stained sections (upper row) demonstrate preserved renal architecture in the Control group, whereas the CI-AKI group exhibits prominent tubular necrosis (*), tubular dilatation (+), cellular degeneration (×), and vascular congestion (↑). These histopathological alterations appeared attenuated in representative sections from the treatment groups compared with those from the untreated CI-AKI group. Masson’s trichrome–stained sections (lower row) show increased interstitial collagen deposition and tubulointerstitial disorganization in the CI-AKI group, whereas these changes appeared less pronounced in the representative sections from the treatment groups. Scale bar = 100 µm. Please click here to view a larger version of this figure.
| Variable | Control | CI-AKI | CI-AKI+M | CI-AKI+NAC | CI-AKI+NAC+M | p |
| UREA (mg/dL) | 67.43±53.11a | 606.71±429.42b | 105.89±28.63a | 243.14±135.99a | 293.61±212.05a | 0.003 |
| BUN (mg/dL) | 31.51±24.82a | 268.63±190.84b | 51.53±14.69a | 129.54±73.54a | 108.38±87.36a | 0.003 |
| Creatinine (mg/dL) | 0.60±0.05a | 3.27±2.14b | 0.61±0.12a | 1.53±1.17a | 1.28±0.55a | 0.002 |
| SOD (U/mL) | 147.81±33.27a | 92.23±16.37b | 130.96±42.19a | 137.87±31.95a | 141.71±30.27a | 0.044 |
| GSH (mmol/L) | 124.29±21.24b | 66.05±24.72a | 133.87±26.95bc | 139.31±30.10bc | 172.44±60.48c | 0.001 |
| CAT (U/mL) | 93.35±18.75c | 33.22±17.07a | 58.67±32.95ab | 52.64±19.97ab | 75.46±26.85bc | 0.003 |
| MDA (nmol/mL) | 23.42±13.48a | 54.13±19.37b | 22.40±14.81a | 21.53±5.07a | 37.01±9.29a | 0.001 |
| Within each row, groups sharing at least one superscript letter were not significantly different, whereas groups with no superscript letter in common were significantly different according to Duncan’s post hoc test (p < 0.05). | ||||||
Table 1: Biochemical and oxidative stress parameters in experimental groups. Significant pairwise differences: urea, BUN, creatinine (CREA), SOD, and MDA, CI-AKI vs Control, CI-AKI+M, CI-AKI+NAC, and CI-AKI+M+NAC; GSH, CI-AKI vs all other groups and Control vs CI-AKI+M+NAC; CAT, Control vs CI-AKI, CI-AKI+M, and CI-AKI+NAC, and CI-AKI vs CI-AKI+M+NAC. Data are presented as mean ± SD (n = 6) and were analyzed using one-way ANOVA followed by Duncan’s post hoc test. Values with no shared superscript letter differ significantly (p < 0.05).
| Variable | Control | CI-AKI | CI-AKI+M | CI-AKI+NAC | CI-AKI+NAC+M | p |
| Cystatin C (ng/mL) | 10.30±0.78a | 18.43±1.06b | 10.90±1.13a | 11.00±0.59a | 11.13±0.84a | <0.001 |
| IL-6 (ng/L) | 9.29±2.70a | 13.41±2.14b | 10.24±0.86a | 10.66±0.83a | 10.85±1.63a | 0.008 |
| KIM-1 (ng/mL) | 2.25±0.54a | 3.07±0.36b | 2.39±0.60a | 2.45±0.33a | 2.45±0.17a | 0.027 |
| TNF-α (ng/L) | 95.49±16.98a | 161.69±26.14b | 110.26±38.12a | 119.42±35.35a | 127.76±15.13a | 0.006 |
| IL-1β (ng/mL) | 7.65±0.53ab | 9.28±0.68c | 7.34±0.57a | 8.24±0.73b | 8.11±0.72ab | <0.001 |
| Within each row, groups sharing at least one superscript letter were not significantly different, whereas groups with no superscript letter in common were significantly different according to Duncan’s post hoc test (p < 0.05). | ||||||
Table 2: Renal injury and inflammatory biomarker levels in experimental groups. Significant pairwise differences: cystatin C, IL-6, KIM-1, and TNF-α, CI-AKI vs Control, CI-AKI+M, CI-AKI+NAC, and CI-AKI+M+NAC; IL-1β, CI-AKI vs all other groups and CI-AKI+M vs CI-AKI+NAC. Data are presented as mean ± SD (n = 6) and were analyzed using one-way ANOVA followed by Duncan’s post hoc test. Values with no shared superscript letter differ significantly (p < 0.05).
| Groups | Tubular necrosis | Tubular dilatation | Cellular degeneration | Vascular congestion |
| Control | 0 | 0 | 0 | 0 |
| CI-AKI | 2.67 | 2.83 | 2.67 | 2.5 |
| CI-AKI+M | 1.33 | 1.5 | 1.17 | 1 |
| CI-AKI+NAC | 1.17 | 1.17 | 0.83 | 0.83 |
| CI-AKI+NAC+M | 0.5 | 0.67 | 0.5 | 0.17 |
Table 3: Comparison of histopathological damage parameters of kidney tissue in experimental groups. Semi-quantitative HE-based histopathological injury scores are presented as group means (n = 6 animals/group). Scores were graded as 0 (no damage), 1 (mild), 2 (moderate), and 3 (severe damage), with higher scores indicating greater histopathological injury.
Supplementary File 1: Data supporting the findings of this study.Please click here to download this file.
Discussion
This experimental CI-AKI study evaluated post-contrast treatment with montelukast, NAC, or their combination across renal function, oxidative stress parameters, inflammatory responses, renal injury biomarkers, and histopathological outcomes. Contrast exposure produced substantial increases in serum urea, BUN, and creatinine and was accompanied by adverse changes in oxidative stress parameters and inflammatory biomarkers. Increased KIM-1 and cystatin C levels provided additional evidence of renal injury.
Post-contrast treatment with montelukast, NAC, or their combination was associated with favorable changes in several evaluated parameters. However, the combination did not consistently outperform montelukast monotherapy across the biochemical outcomes. Taken together, these observations are compatible with the involvement of oxidative stress and inflammation in CI-AKI and suggest that interventions acting on these processes may attenuate renal injury, although the underlying signaling pathways were not directly examined in the present study1,30.
The pronounced elevations in serum urea, BUN, and creatinine after contrast administration support the successful induction of renal dysfunction in this experimental CI-AKI model. Contrast exposure can impair renal function through interacting processes that include intrarenal vasoconstriction, medullary hypoxia, oxidative injury, and tubular cell damage. The resulting reduction in renal perfusion and glomerular filtration may limit the elimination of nitrogenous waste products, thereby increasing their circulating concentrations. The renal function changes observed in the untreated CI-AKI group are consistent with those reported in previous experimental studies1,30,31,32.
Considerable within-group variability was observed for serum urea and BUN in the untreated CI-AKI group, as reflected by the relatively large standard deviations. This dispersion may reflect interindividual biological differences in susceptibility to the sensitized CI-AKI induction protocol, including variability in the renal response to water deprivation, inhibition of nitric oxide and prostaglandin pathways, and contrast exposure. Minor differences in renal functional reserve and physiological responses among animals may also have contributed to the heterogeneous severity of renal injury. Therefore, the large standard deviations should be interpreted as evidence of substantial biological variability within this experimental model rather than as measurement error. Nevertheless, given the small number of animals in each group, the distributional characteristics and the magnitude of treatment-related differences should be interpreted cautiously.
In the present study, serum urea, BUN, and creatinine were numerically lower in the NAC-treated group than in the untreated CI-AKI group, a pattern consistent with possible attenuation of renal dysfunction. NAC has been extensively studied in CI-AKI, but its reported effects on renal function have varied across studies14,15,16,17. Proposed mechanisms include scavenging of reactive species, support of glutathione synthesis, and limitation of oxidative injury within renal tissue1. Thus, the renal function profile observed following NAC treatment may be related to its antioxidant properties, although this mechanism was not directly examined in the present study.
In the present study, serum urea, BUN, and creatinine were numerically lower in the montelukast-treated group than in the untreated CI-AKI group, suggesting a possible attenuation of renal dysfunction. Previous experimental studies, including investigations of CI-AKI, have similarly reported lower serum creatinine and urea levels following montelukast administration9,18,19. The combination group also showed numerically lower renal function markers than the untreated CI-AKI group. However, urea, BUN, and creatinine were numerically lower with montelukast monotherapy than with combined treatment, and Duncan’s post hoc comparisons showed no statistically significant differences between these two groups (p > 0.05). Thus, combination therapy did not demonstrate superiority over montelukast monotherapy for these renal function markers.
Oxidative injury is considered an important contributor to CI-AKI pathophysiology. Medullary hypoxia induced by contrast exposure promotes excess ROS generation, which may damage cellular lipids and mitochondria, injure tubular epithelial cells, and enhance inflammatory signaling1,12,30.
The untreated CI-AKI group exhibited the highest MDA concentration, together with the lowest SOD and CAT activities and the lowest GSH level, indicating an imbalance between oxidative burden and antioxidant defenses following contrast exposure. Comparable profiles, characterized by increased MDA together with reduced antioxidant capacity, have been reported in other experimental models of CI-AKI18,19. These findings are consistent with oxidative stress contributing to the development and progression of renal injury rather than occurring solely as a secondary consequence1,30.
Compared with the untreated CI-AKI group, the NAC- and montelukast-treated groups generally showed lower MDA values together with higher SOD, GSH, and CAT values, a pattern compatible with attenuation of oxidative injury. The proposed antioxidant actions of NAC include the neutralization of reactive species and maintenance of intracellular glutathione availability1,14. Montelukast may also limit renal oxidative injury through mechanisms extending beyond cysteinyl leukotriene receptor blockade, including suppression of oxidative responses within kidney tissue18,33. Previous studies of renal injury, including CI-AKI models, have similarly reported reduced lipid peroxidation and improved antioxidant defenses following montelukast treatment9,19,27. Although favorable oxidative stress parameters were also observed in the combination group, combined treatment did not consistently outperform either monotherapy. Accordingly, these findings do not establish an additive or synergistic antioxidant effect of NAC and montelukast administered together.
The KIM-1 and cystatin C findings provided complementary evidence of renal injury following contrast exposure. KIM-1 is associated primarily with tubular epithelial damage, whereas cystatin C is used as an indicator of alterations related to renal filtration and injury; both have been evaluated as early biomarkers in experimental CI-AKI models1,10. In the untreated CI-AKI group, the highest levels of both biomarkers accompanied the pronounced deterioration in conventional renal function parameters. This pattern is consistent with previous experimental studies reporting elevations in KIM-1 and cystatin C after contrast-induced renal injury1,10.
Compared with the untreated CI-AKI group, the treatment groups showed lower KIM-1 and cystatin C values, a pattern compatible with attenuation of renal injury. This biomarker profile paralleled the numerically lower serum urea and creatinine concentrations observed following treatment. Previous experimental studies have associated montelukast administration with reduced KIM-1 expression, less severe tubular injury, and preservation of renal function in CI-AKI and other renal injury models9,18,19. NAC has likewise been associated with more favorable acute kidney injury biomarker profiles, potentially through limitation of oxidative stress–related cellular damage14,15,16,17. However, no statistically significant differences in KIM-1 or cystatin C were detected between the combination-treatment and montelukast-monotherapy groups (p > 0.05). Accordingly, the present findings do not demonstrate an additional biomarker benefit of combined treatment.
Oxidative and inflammatory responses may reinforce one another during CI-AKI. Excess ROS can stimulate proinflammatory signaling, with subsequent increases in TNF-α, IL-1β, and IL-6 potentially amplifying renal tissue injury1,12,13,30.
The untreated CI-AKI group exhibited the highest TNF-α, IL-1β, and IL-6 concentrations, supporting the presence of an inflammatory response following contrast exposure. In experimental CI-AKI models, increases in these cytokines have been associated with tubular injury, inflammatory cell infiltration, and impaired renal function10,12,13. The inflammatory cytokine profile observed in the present study is consistent with previous experimental findings reported after contrast administration1.
The NAC- and montelukast-treated groups showed lower TNF-α, IL-1β, and IL-6 values than the untreated CI-AKI group, a pattern compatible with attenuation of the inflammatory response. The anti-inflammatory activity proposed for NAC may arise partly from reduced oxidative burden and the resulting limitation of proinflammatory cytokine production1,14,15,16,17. Montelukast may influence cytokine expression through cysteinyl leukotriene receptor blockade as well as modulation of other inflammatory signaling processes18,33. Experimental renal injury studies have also associated montelukast treatment with reduced NF-κB-related signaling and proinflammatory activity9,19,27. Accordingly, the cytokine profile observed in this study is compatible with modulation of inflammatory processes involving pathways such as NF-κB and the NOD-like receptor family pyrin domain-containing 3 (NLRP3) inflammasome. However, NF-κB, NLRP3, and NOX4 were not measured directly; therefore, the biomarker findings provide only indirect supportive evidence and cannot establish pathway-specific activation or inhibition.
Inflammatory cytokine values were lower in the combination-treatment group than in the untreated CI-AKI group, but combined treatment did not consistently produce lower values than montelukast alone. No statistically significant differences were detected between the CI-AKI + Montelukast and CI-AKI + Montelukast + NAC groups for TNF-α, IL-1β, or IL-6 (p > 0.05). Thus, the present results provide no evidence that adding NAC to montelukast confers an additional anti-inflammatory benefit.
Histopathological evaluations further demonstrated that contrast media administration resulted in substantial structural renal injury. The findings of tubular necrosis, tubular dilatation, cellular degeneration, and vascular congestion observed in the CI-AKI group represent characteristic histopathological features of CI-AKI and have been associated with impaired renal perfusion, oxidative stress, and tubular cell injury1,12,18,19. Together with the biochemical findings, these histopathological alterations confirm that contrast media administration resulted in substantial renal tissue injury. The lower degree of histopathological injury observed in the montelukast- and NAC-treated groups suggests that these agents may exert protective effects on renal tissue. Notably, the combination therapy group exhibited the numerically lowest histopathological injury scores among the treatment groups. Furthermore, qualitative evaluation of Masson’s trichrome–stained sections showed less prominent interstitial collagen deposition and better preservation of tubulointerstitial architecture in the treatment groups compared with the untreated CI-AKI group. Given the acute observation period and the qualitative nature of the Masson’s trichrome assessment, these findings should be interpreted as evidence of better structural preservation at the examined time point rather than as evidence of altered long-term extracellular matrix remodeling.
The semi-quantitative histopathological assessment was consistent with the qualitative observations, showing lower injury scores across all treatment groups compared with the untreated CI-AKI group. Although the combination group exhibited the numerically lowest histopathological injury scores, this finding was not accompanied by consistent superiority across the biochemical outcomes. Therefore, the favorable histopathological findings observed with combined treatment should not be interpreted as evidence of an additive or synergistic effect based on the present study design. Similarly, previous studies in experimental models of CI-AKI and other forms of acute kidney injury have reported that suppression of oxidative stress and inflammation reduces histopathological damage and contributes to the preservation of tubular integrity9,18,19,27.
An apparent divergence was observed between the biochemical and histopathological findings. Although several biochemical variables were numerically more favorable in the montelukast monotherapy group than in the combination group, these differences were not statistically significant. In contrast, the combination group exhibited the numerically lowest histopathological injury scores. This partial dissociation may reflect differences in the biological processes and temporal profiles captured by the two assessment approaches. Histopathological examination directly evaluates local cellular and structural injury within renal tissue and may therefore reveal tissue-level preservation at the examined time point even when serum renal function markers and other biochemical measures do not improve to the same magnitude. In contrast, biochemical outcomes provide indirect functional or molecular readouts and may be influenced by renal functional reserve, compensatory mechanisms, interanimal biological variability, and the timing of sample collection. Because all endpoints were assessed at a single terminal time point, structural preservation and biochemical recovery may not have been synchronized. Accordingly, the more favorable histopathological appearance in the combination group should be interpreted as a difference between assessment modalities rather than as evidence of superior overall efficacy. Nevertheless, although histopathological evaluations were performed under blinded conditions to minimize observer bias, all tissue sections were assessed by a single pathologist, precluding evaluation of interobserver variability. Future studies incorporating multiple independent evaluators may further enhance the reliability and reproducibility of the histopathological findings.
Reproducible application of this model depends on consistent performance of several procedural steps. The duration of water deprivation, the predefined intervals separating L-NAME, indomethacin, and iohexol administration, and the slow intravenous delivery of iohexol should be standardized across animals. Tail-vein extravasation can decrease the effective contrast dose and increase variability in the severity of renal injury; therefore, the injection site should be monitored carefully throughout administration. When leakage, extravasation, or substantial resistance during injection occurs, the possibility of incomplete contrast delivery should be considered when interpreting the corresponding findings. Dose consistency may also be affected by regurgitation during oral gavage or inadequate resuspension of the montelukast preparation. Applying the same standardized procedures to all animals and assigning the administrations to the same investigator whenever feasible may reduce avoidable procedural variability.
This protocol enables CI-AKI to be established within a relatively short experimental period while allowing biochemical and histopathological outcomes to be examined in the same animal model1,2,9.
A strength of the present study is that renal injury was characterized using complementary functional, biochemical, inflammatory, and histopathological outcomes. Evaluation of renal function indices together with oxidative stress parameters, inflammatory cytokines, KIM-1, cystatin C, and renal tissue morphology allowed several components of CI-AKI to be examined within the same experiment. The inclusion of KIM-1 and cystatin C also broadened the assessment beyond conventional serum creatinine measurements. Testing montelukast and NAC both separately and together enabled direct comparison of the treatment strategies; however, the findings did not show consistent superiority of the combination over monotherapy across the evaluated outcomes. Moreover, unlike induction approaches based on contrast exposure alone, the present model incorporates renal vasoconstriction and medullary hypoxia, thereby creating a pronounced renal injury setting in which treatment-associated biological changes can be evaluated.
The 1 h interval between contrast exposure and treatment initiation represents only the time point examined in this experimental protocol and should not be interpreted as a clinically validated therapeutic window. Although treatment soon after a known contrast exposure may be relevant to future translational research, the present animal study cannot determine its feasibility or efficacy in clinical settings. In particular, the optimal initiation time, dose, administration route, treatment duration, and patient population remain unknown. These factors must be investigated in dedicated translational and clinical studies before post-contrast NAC or montelukast administration can be considered for clinical use.
Several limitations of the present study should be acknowledged. The findings were obtained from a preclinical animal model and therefore cannot be directly generalized to clinical practice. Because the protocol combined water deprivation with inhibition of nitric oxide and prostaglandin pathways, the resulting renal insult may have been more severe than the injury typically encountered after contrast exposure in patients. The results should consequently be interpreted within the context of this sensitized experimental setting. Although the model permits controlled evaluation of biological responses to candidate renoprotective treatments, it does not reproduce the full heterogeneity or severity range of clinical CI-AKI. Treatment-associated changes observed in this study may therefore differ in patients with milder or more varied risk profiles. Replication in less intensive models that more closely approximate common clinical conditions, followed by appropriately designed clinical studies, is required before the magnitude or clinical relevance of these effects can be determined. An additional limitation is that only male rats were included in the study. Therefore, potential sex-related differences in susceptibility to CI-AKI and responses to NAC and montelukast were not evaluated, and the present findings should not be assumed to generalize to female animals. Future studies including both sexes are needed to determine whether sex influences the severity of renal injury or treatment response.
Another limitation is the absence of a procedural sham group matched to the experimental groups for protocol-related handling, restraint, water deprivation, injections, oral gavage, and vehicle administration. Because the Control group did not undergo these procedures, unequal procedural stress and nonspecific effects related to restraint, repeated handling, injections, oral gavage, and vehicle exposure cannot be completely excluded as potential contributors to some of the observed differences between the Control and experimental groups. Inclusion of appropriately matched procedural sham and vehicle-control groups in future studies would help distinguish these nonspecific procedure-related effects from those specifically attributable to CI-AKI induction and treatment.
Although the prespecified sample size was calculated to provide 80% power for detecting an assumed large overall effect across the five experimental groups, the study was not specifically powered to detect smaller pairwise differences between the monotherapy and combination treatment groups. Therefore, the study may have had limited power to detect such between-treatment differences, and nonsignificant numerical trends should not be interpreted as evidence of equivalence. Studies with larger sample sizes will be required to determine whether these trends represent reproducible treatment differences.
Because only a single dose of each agent was evaluated, the present study cannot determine an optimal NAC–montelukast dose combination, characterize dose-dependent synergistic or antagonistic interactions, or quantify the relative contribution of each agent to the effects observed with combination treatment. Thus, one agent may have contributed more strongly to specific outcomes, but this cannot be established from the current study design. Future studies incorporating multiple dose levels and formal drug-interaction analyses will be required to characterize dose-response relationships and identify an optimal combination regimen.
The study evaluated biochemical indicators of oxidative stress and inflammation but did not directly examine the associated intracellular signaling pathways. Therefore, the observed biomarker profiles cannot demonstrate whether NF-κB-, NLRP3-, or NOX4-related signaling was activated or inhibited by treatment. Future investigations using molecular approaches, including Western blotting and quantitative polymerase chain reaction (qPCR), are required to determine how these pathways contribute to the renal effects of montelukast and NAC.
Because assessments were confined to the acute phase, the present study provides no information regarding subsequent renal recovery or longer-term tissue remodeling. The relatively limited collagen deposition observed in the treatment groups at the examined endpoint should therefore be regarded as an early structural finding rather than as evidence that chronic renal fibrosis was prevented. This finding may instead reflect attenuation of the initial renal insult. Longitudinal studies incorporating later assessment points are needed to determine whether these early changes persist and whether they influence long-term renal function or tissue remodeling.
Overall, post-contrast administration of montelukast and NAC, either alone or in combination, was associated with attenuation of renal dysfunction, oxidative stress, inflammatory responses, and histopathological injury in this experimental CI-AKI model. However, the combination treatment did not demonstrate consistent superiority over monotherapy across the evaluated outcomes. These findings are limited to the present preclinical model and support further experimental investigation rather than direct extrapolation to clinical practice.
In conclusion, post-contrast treatment with montelukast, NAC, or their combination was associated with more favorable biochemical and histopathological findings in this experimental CI-AKI model. However, the combined regimen did not consistently outperform monotherapy across the assessed outcomes. Because these observations were obtained in a preclinical animal study, they should be regarded as a basis for further experimental validation rather than as evidence of clinical efficacy or applicability. Additional research is needed to determine the potential relevance of these post-contrast treatment approaches to clinical CI-AKI.
Disclosures
The authors declare that they have no competing interests. During the preparation of this manuscript, AI-assisted tools were used solely for language editing and grammar correction. No artificial intelligence tools were used for the generation, analysis, or interpretation of data, nor for the creation of any figures, tables, or graphical elements. The authors take full responsibility for the content of the manuscript.
AUTHORS' CONTRIBUTIONS:
YS, CS, and OK contributed to the conception and design of the study. YS performed the experimental procedures and data collection. OK conducted the histopathological examinations. YS and CS performed the statistical analyses and interpreted the data. YS drafted the manuscript. All authors critically revised the manuscript and approved the final version.
Acknowledgements
This study was supported by the Scientific Research Projects Coordination Unit of Kırşehir Ahi Evran University (Project No: TIP.A3.26.006).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Auto Strip Washer | Bio-Tek Instruments, USA | ELx50 | Automated ELISA plate washing. |
| Microplate Reader | Bio-Tek Instruments, USA | ELx800 | ELISA absorbance measurements. RRID:SCR_028651 |
| 10% Neutral Buffered Formalin | Merck | Not recorded | Tissue fixation for histopathology. |
| Benchtop Centrifuge | Nüve | NF048 | Sample preparation and centrifugation. |
| Carboxymethylcellulose (CMC) | Sigma-Aldrich, USA | C5678 | Vehicle used for montelukast suspension. |
| CAT Kit Universal | Otto Scientific | Otto3051 | Colorimetric measurement of CAT activity in serum using a Mindray BS-400 chemistry analyzer. |
| Digital Homogenizer | Daihan Scientific | HG-15D | Tissue homogenization. |
| Eosin Y (Yellowish) | Merck | 1.15935.0025 | HE staining. |
| Harris Hematoxylin Solution | BSLAB | BS-002 | HE staining. |
| Indomethacin | Sigma-Aldrich, USA | I7378 | Used for induction of CI-AKI. |
| Iohexol (Omnipaque 300) | GE HealthCare | Not recorded | Contrast agent used to induce CI-AKI. |
| Ketamine hydrochloride (Ketalar) | Pfizer, USA | Not recorded | General anesthesia before sample collection. |
| Light Microscope (Nikon Eclipse) | Nikon | Ni-U | Histopathological examination and imaging. RRID:SCR_024835 |
| L-NAME (Nω-nitro-L-arginine methyl ester) | Sigma-Aldrich, USA | N5751 | Used for induction of CI-AKI. |
| Masson's Trichrome Staining Kit | MOSLAB, Türkiye | BKMTO001 | Masson trichrome staining. |
| Mindray Chemistry Analyzer | Mindray | BS-400 | Biochemical analyses. |
| Montelukast sodium | Sigma-Aldrich, USA | SML0101 | Administered orally by gavage as treatment. |
| N-acetylcysteine (ASIST 300 mg/2 mL) | MAC  laç, Türkiye | Not recorded | Administered intraperitoneally as treatment. |
| Rat Cystatin C ELISA Kit | BT Lab, China | E0145Ra | ELISA measurement of cystatin C in renal tissue supernatants. |
| Rat IL-1β ELISA Kit | BT Lab, China | E0119Ra | ELISA measurement of IL-1β in renal tissue supernatants. |
| Rat IL-6 ELISA Kit | BT Lab, China | E0135Ra | ELISA measurement of IL-6 in renal tissue supernatants. |
| Rat KIM-1 ELISA Kit | BT Lab, China | E0549Ra | ELISA measurement of KIM-1 in renal tissue supernatants. |
| Rat TNF-α ELISA Kit | BT Lab, China | E0764Ra | ELISA measurement of TNF-α in renal tissue supernatants. |
| Stainless Steel Feeding Needle (22 G Oral Gavage Cannula) | Instech Laboratories, USA | Not recorded | Oral gavage administration. |
| Standard pelleted rodent chow (Optima) | Optima, Türkiye | Not recorded | Lot no. 58931. Nutritional composition: 24% crude protein, 3.94% crude cellulose, 5.08% crude fat, 8.8% crude ash, 1.44% lysine, 0.61% methionine, 1.14% calcium, 0.89% phosphorus, and 0.28% sodium. |
| Universal Creatinine Kit | Otto Scientific | OttoBC139 | Colorimetric measurement of creatinine in serum. |
| Universal GSH Kit | Otto Scientific | Otto3053 | Colorimetric measurement of GSH in EDTA-anticoagulated blood using a modified Ellman method. |
| Universal MDA Kit | Otto Scientific | Otto1001 | Colorimetric measurement of MDA in serum using an ELx800 microplate reader. |
| Universal SOD Kit | Otto Scientific | Otto3047 | Colorimetric measurement of SOD activity in serum using a Mindray BS-400 chemistry analyzer. |
| Universal Urea Kit | Otto Scientific | OttoBC157 | Colorimetric measurement of urea and BUN in serum. |
| Xylazine hydrochloride (Rompun) | Bayer, Germany | Not recorded | General anesthesia before sample collection. |
References
- Wang Z, Wang Q, Gong X. Unveiling the mysteries of contrast-induced acute kidney injury: new horizons in pathogenesis and prevention. Toxics. 2024;12(8):620.
- Cho E, Ko GJ. Pathophysiology and management of radiocontrast-induced nephropathy. Diagnostics. 2022;12(1):180.
- Shuka N, et al. Contrast-induced nephropathy in interventional cardiology: incidence, risk factors, and identification of high-risk patients. Cureus. 2023;15(12):e51283.
- Shams E, Mayrovitz HN. Contrast-induced nephropathy: a review of mechanisms and risks. Cureus. 2021;13(5):e14842.
- Mehran R, et al. A simple risk score for prediction of contrast-induced nephropathy after percutaneous coronary intervention: development and initial validation. J Am Coll Cardiol. 2004;44(7):1393-1399.
- Heyman SN, Reichman J, Brezis M. Pathophysiology of radiocontrast nephropathy: a role for medullary hypoxia. Invest Radiol. 1999;34(11):685-691.
- Geenen RWF, Kingma HJ, van der Molen AJ. Contrast-induced nephropathy: pharmacology, pathophysiology and prevention. Insights Imaging. 2013;4:811-820.
- Manisaligil YA, et al. Assessment of Rac1 and β-PAK expressions in a mouse model for contrast-induced nephropathy. J Basic Clin Health Sci. 2020;4(3):230-236.
- Simsek O, et al. Preventative effect of montelukast in mild to moderate contrast-induced acute kidney injury in rats via NADPH oxidase 4, p22phox and nuclear factor kappa-B expressions. Int Urol Nephrol. 2025;57(7):2313-2325.
- Banda J, et al. Biomarkers for diagnosis and prediction of outcomes in contrast-induced nephropathy. Int J Nephrol. 2020;2020:8568139.
- Zisis IE, et al. Renoprotective effect of vardenafil and avanafil in contrast-induced nephropathy: emerging evidence from an animal model. J Pers Med. 2022;12(5):670.
- Walker H, et al. Systematic review and meta-analysis of prophylaxis use with intravenous contrast exposure to prevent contrast-induced nephropathy. Eur J Radiol. 2022;153:110368.
- Hossain MA, et al. Contrast-induced nephropathy: pathophysiology, risk factors, and prevention. Saudi J Kidney Dis Transpl. 2018;29(1):1-9.
- Tepel M, et al. Prevention of radiographic-contrast-agent-induced reductions in renal function by acetylcysteine. N Engl J Med. 2000;343(3):180-184.
- Liu R, et al. N-acetylcysteine for the prevention of contrast-induced nephropathy: a systematic review and meta-analysis. J Gen Intern Med. 2005;20(2):193-200.
- Zhu R, et al. Association of N-acetylcysteine use with contrast-induced nephropathy: an umbrella review of meta-analyses of randomized clinical trials. Front Med (Lausanne). 2023;10:1235023.
- Sandilands EA, et al. Acetylcysteine has no mechanistic effect in patients at risk of contrast-induced nephropathy: a failure of academic clinical science. Clin Pharmacol Ther. 2022;111(6):1222-1238.
- Sarmadian R, et al. The renoprotective potential of montelukast: a scoping review. Ann Med Surg (Lond). 2024;86(6):3568-3576.
- Kokate D, Marathe P. Evaluation of effect of montelukast in the model of streptozotocin-induced diabetic nephropathy in rats. Indian J Endocrinol Metab. 2024;28(1):47-54.
- Mojtahedi SY, Ghodsi M, Pourpashang P. Renoprotective efficacy of montelukast: an overview on recent advancements. J Nephropharmacol. 2025;14(1):e12759.
- Sener G, et al. Chronic renal failure-induced multiple-organ injury in rats is alleviated by the selective CysLT1 receptor antagonist montelukast. Prostaglandins Other Lipid Mediat. 2007;83(4):257-267.
- Sener G, et al. Montelukast protects against renal ischemia/reperfusion injury in rats. Pharmacol Res. 2006;54(1):65-71.
- Li LP, et al. Intrarenal oxygenation by blood oxygenation level-dependent MRI in contrast nephropathy model: effect of the viscosity and dose. J Magn Reson Imaging. 2012;36(5):1162-1167.
- Liu K, et al. A novel rat model of contrast-induced nephropathy based on dehydration. J Pharmacol Sci. 2019;141(1):49-55.
- Alshogran OY, Al Tahrawi AY, Nusair SD. Exploring the effects of edaravone in rats with contrast-induced acute kidney injury. Life Sci. 2022;309:121006.
- Suddek GM. Montelukast ameliorates kidney function and urinary bladder sensitivity in experimentally induced renal dysfunction in rats. Fundam Clin Pharmacol. 2013;27(2):186-191.
- Aydin A, et al. The examination of the nephroprotective effect of montelukast sodium and N-acetylcysteine in renal ischemia with dimercaptosuccinic acid imaging in a placebo-controlled rat model. Acta Cir Bras. 2020;35(9):e202000905.
- Kara O, Kilitci A, Daglioglu G. Protective effect of resveratrol on cisplatin-induced damage in rat kidney. Cukurova Med J. 2022;47(3):990-995.
- Pandir D, Kara O. Cisplatin-induced kidney damage and the protective effect of bilberry (Vaccinium myrtillus L.): an experimental study. Turk J Med Sci. 2013;43(6):951-956.
- Iordache AM, et al. Phosphodiesterase-5 inhibitors ameliorate structural kidney damage in a rat model of contrast-induced nephropathy. Food Chem Toxicol. 2020;143:111535.
- Morcos SK, Thomsen HS, Webb JA. Contrast-media-induced nephrotoxicity: a consensus report. Eur Radiol. 1999;9:1602-1613.
- Rudnick MR, et al. Nephrotoxicity of ionic and nonionic contrast media in 1196 patients: a randomized trial. Kidney Int. 1995;47(1):254-261.
- Modi K, Padala SA, Gupta M. Contrast-induced nephropathy. In: StatPearls [Internet]. Treasure Island (FL): StatPearls Publishing; 2025 Jan–. Updated 2025 May 5. Available from: https://www.ncbi.nlm.nih.gov/books/NBK448066/