Here, we propose a stereo camera–based augmented reality (AR) approach with markerless registration to assist in the extraction of impacted supernumerary teeth. This workflow provides visual assistance in localizing impacted supernumerary teeth and may serve as a feasible adjunctive approach for clinical use.
Method Article
Camera-Based Augmented Reality Navigation for Assisting the Extraction of Impacted Supernumerary Teeth
In This Article
Summary
Abstract
The surgical removal of deeply impacted supernumerary teeth is a demanding pediatric procedure due to their hidden positions and proximity to vital structures, such as tooth germs and nerves. Conventional freehand methods often rely on subjective mental reconstruction of 3D imaging, which can lead to excessive bone removal and iatrogenic injury. This study presents a standardized protocol that uses a camera-based 3D AR navigation system to assist in localizing impacted supernumerary teeth. A digital workflow was established by integrating preoperative cone-beam computed tomography (CBCT) data with intraoral scans to create a patient-specific virtual plan. During surgery, a high-resolution camera captures the operative field, and the virtual model of the impacted supernumerary tooth is overlaid on the live camera image displayed on the computer screen, providing a visual reference for assisted localization. The AR navigation interface allows surgeons to adjust the transparency of various tissue layers to enhance internal observation and fine-tune image registration via an adjustable localization confidence threshold. Furthermore, the system enables fixing the display once the most accurate alignment is achieved, ensuring visual stability during critical maneuvers. This protocol was demonstrated in a clinical case involving a patient with a deeply impacted supernumerary tooth. The preliminary outcome showed that the system provided intuitive spatial guidance for assisted localization of the impacted supernumerary tooth. The workflow proved clinically feasible, and no intraoperative complications, such as damage to adjacent roots, were observed. In conclusion, camera-based AR navigation may serve as a potential adjunctive approach to conventional techniques for the assisted extraction of impacted supernumerary teeth. By providing real-time visualization of internal structures and interactive control over registration and transparency, this protocol supports the clinical adoption of digital innovations in complex pediatric dental interventions.
Introduction
Supernumerary teeth are teeth that exceed the normal number in the dentition. They represent a common developmental dental anomaly and may also occur as an oral manifestation of certain syndromes. Clinically, supernumerary teeth are most frequently observed in the anterior maxillary region. Some supernumerary teeth only represent an increase in tooth number and may remain asymptomatic; however, they may also cause complications, including abnormal eruption of adjacent teeth, root resorption, dental arch irregularities, and cyst formation1,2. Therefore, surgical removal is usually required when supernumerary teeth interfere with the eruption of permanent teeth, pose a risk of complications, or affect subsequent treatment planning.
Early diagnosis and timely intervention are fundamental to the management of supernumerary teeth. The timing of intervention and the selection of the surgical approach are closely related to the spatial position of the supernumerary tooth. Although the optimal timing of removal remains controversial, many clinicians favor early intervention in cases that have already affected permanent tooth eruption or pose a potential risk of complications3,4. The choice of surgical technique depends largely on clinical and radiographic examinations. CBCT is commonly used before the removal of supernumerary teeth because it allows three-dimensional (3D) assessment of the number, position, root morphology, and relationship of the supernumerary teeth with surrounding anatomical structures. This information helps determine the precise location of the tooth, its labial or palatal position, the degree of bony impaction, and the appropriate surgical approach2,5.
At present, conventional freehand removal mainly relies on the surgeon’s spatial interpretation of preoperative images and experience-based localization. Errors in localization may lead to excessive bone removal and even damage adjacent tooth roots or important anatomical structures3,6. With the development of minimally invasive concepts and advances in digital technology, 3D-printed personalized guides, dynamic navigation, mixed reality, and robot-assisted techniques have been applied to the removal of complex impacted teeth or supernumerary teeth7,8,9,10. These techniques have shown potential to improve localization, shorten operative time, and reduce bone removal. However, these techniques also have limitations. 3D-printed personalized guides usually require preoperative design, model processing, guide printing, and post-processing, which may increase preparation time and workflow complexity. In primary hospitals or institutions with limited equipment, guide fabrication often depends on external processing centers, which may further prolong the preparation time. Dynamic navigation and robot-assisted systems usually require additional tracking devices and registration procedures. In the limited intraoral operative space, these systems may increase the complexity of equipment arrangement and surgical manipulation, and may affect the surgeon’s field of view and instrument handling. Although mixed reality has strong visualization potential, the accuracy of virtual-real registration and the stability of dynamic tracking remain important factors limiting its clinical application. In addition, the high cost of equipment and the long learning curve associated with these technologies may limit their widespread use in outpatient removal of impacted supernumerary teeth.
To address these limitations, the AR method used in this protocol adopts a relatively simple hardware configuration, consisting mainly of a computer, a stereo camera, and AR navigation software. AR technology has been preliminarily applied in oral and maxillofacial procedures, including odontogenic cystectomy, dental implant placement, orthognathic surgery, maxillofacial trauma surgery, and extraction of impacted third molars, and has shown potential for intraoperative visualization and spatial localization11,12,13,14,15,16. Therefore, this protocol proposes a stereo camera-based, markerless, registration-based AR method to assist in the removal of supernumerary teeth. Preoperatively, CBCT data and intraoral scan models are acquired for 3D reconstruction. The digital models of the supernumerary tooth and adjacent teeth are reconstructed and imported into the AR navigation system. Intraoperatively, the stereo camera captures the surgical field in real time. The system performs markerless registration based on dentition morphology, and the virtual model of the supernumerary tooth is overlaid on the live camera image displayed on the screen, thereby providing an intraoperative visual reference for localization. This workflow is particularly suitable for deeply impacted supernumerary teeth in which localization by conventional freehand surgery is expected to be challenging.
Protocol
The procedure described here was approved and performed in accordance with the guidelines of the Human Research Ethics Committee of the Affiliated Stomatology Hospital of Kunming Medical University, Kunming, China (Approval No. KYKQ2025MEC0077). Written consent was obtained from the patient and her legal guardian for the use and publication of the clinical and intraoperative images.
1. Instrument preparation
- Prepare sterile instruments for tooth extraction.
- Prepare the AR equipment, including a laptop computer and a high-definition camera connected to the computer through USB 3.0.
2. Preoperative imaging and patient preparation (Figure 1)
- Perform preoperative high-resolution CBCT-based 3D reconstruction, with particular attention to the position of the impacted supernumerary tooth within the maxilla and its spatial relationship with the adjacent tooth roots and the nasopalatine neurovascular bundle.
NOTE: CBCT acquisition parameters: New Tom 3G; field of view: 153.60 mm x 153.60 mm; matrix size: 512 x 512 pixels; voxel size: 0.300 mm; tube voltage: 110 kVp; tube current: 3 mA.- Export the CBCT dataset in Digital Imaging and Communications in Medicine (DICOM) format from the CBCT software.
- Open Mimics Medical 21.0, hereafter referred to as the 3D reconstruction software. Click File > New Project, import the patient DICOM dataset, and click Next > Open.
- Click Segment > New Mask. In Predefined Threshold Sets, select Bone (CT), and adjust the threshold range using the slider. In this case, set the minimum value to 570 HU and the maximum value to 3071 HU. Generate a mask containing craniofacial skeletal data (named Maxilla).
- Click Segment > Crop Mask, drag the selection box to limit the region to the maxilla, and click OK.
- Click Segment > Edit Masks, select Erase in the pop-up window, and remove the mandibular teeth in contact with the maxillary teeth in the two-dimensional and 3D views. Obtain the maxilla and maxillary dentition.
- Reconstruct the supernumerary tooth and adjacent teeth. Click New Mask, select Enamel (CT, Child) in Predefined Threshold Sets, and click OK to obtain the patient dentition data.
- Click Segment > Edit Masks, select Erase in the pop-up window, and remove the unnecessary teeth, leaving only the impacted supernumerary tooth in the root region of the right maxillary incisor.
- Click Segment > Edit Masks and Multiple Slice Edit to refine the mask of the supernumerary tooth.
- Select the maxilla and supernumerary tooth masks, right-click, and click Calculate Part to generate the corresponding 3D objects.
- Acquire and repair the intraoral scan data of the patient (Figure 2A).
- Before scanning, calibrate the intraoral 3D scanner using the calibration module in the scanning software according to the manufacturer’s instructions. Acquire the intraoral dentition scan using an intraoral 3D scanner (scanning speed: 20 frames/s; single-tooth accuracy: ≤0.01 mm; scanning depth: <22 mm), and export the scan data in STL format.
- Open Geomagic Wrap 2021 (referred to as the 3D scan data processing software).
- Click File > Open, select the STL file of the maxillary dentition scan data, and click Open.
- In the unit selection window, select Millimeters and click OK.
- Click Trim > Trim with Curve to remove redundant and irregular invalid data at the edge of the scan.
- Click Polygons > Fill Single Hole > Flat > Bridge to close the model.
- Click Mesh Doctor > Apply > OK to repair the model.
- Click Save and select STL as the file type.
3. Registration of the 3D scan data with the CBCT-derived reconstruction data
- In the 3D reconstruction software, click Import > STL, and import the repaired STL file of the intraoral scan model.
- Click Align > Point Registration, and select corresponding reproducible landmarks on both the intraoral scan model and the CBCT-derived dentition model. A minimum of four non-collinear points is required for initial point registration, and six points are recommended to improve registration stability. For example, select the mesioincisal angle points of the maxillary central incisors, the canine cusp tips, and either the mesiobuccal cusp tips or central fossae of the maxillary first molars on both sides. Click OK to obtain the initially registered model.
- In Objects, click Contours Visible to evaluate the registration quality in the axial, sagittal, and coronal planes. Satisfactory registration is determined when the dentition contours of the intraoral scan model and the CBCT-derived dentition model show near-complete visual overlap in the two-dimensional views, without obvious translational or rotational mismatch. If mismatch is observed, adjust the model by clicking Reposition > Move with Mouse and Rotate with Mouse to obtain the final registered model.
- Click File > Export > Binary STL > Part, select the impacted supernumerary tooth model and the registered intraoral scan model, and click Add > Finish.
4. Isolation of the anterior dentition data for recognition (Figure 2B)
- Open the 3D scan data processing software.
- Click File > Open, select the STL file of the maxillary dentition scan data, and click Open.
- In the unit selection window, select Millimeters and click OK.
- Click Trim > Trim with Curve. Sequentially click along the gingival margin to outline the crown portion of the maxillary anterior teeth from canine to canine, and click Apply > OK.
- In Model Manager, select the non-anterior crown portion, right-click, and select Delete.
- Click Polygons > Fill Single > Flat > Bridge. Select the green boundary line, hold down the left mouse button, drag the mouse, and select the boundary at the opposite end to complete bridging.
- Click Fill All > Apply > OK to complete model closure.
- Click Mesh Doctor > Apply > OK to complete model repair.
- Click Save and select STL as the file format.
5. Initiation of AR navigation
NOTE: An Intel RealSense D415 camera was used only for RGB image acquisition at 1080p and 30 fps; its depth-sensing function was not used for tracking or registration. The camera calibration parameters were predefined during software development and used for AR registration. No additional calibration was required during subsequent use. In this system, registration was performed using the patient-specific three-dimensional anterior dentition model as the dentition marker. The system matched the projected contour and geometric features of this 3D model with the patient’s anterior dentition in the live RGB camera view. After automatic registration, the virtual supernumerary tooth model was displayed in accordance with its preoperatively defined spatial relationship to the anterior dentition model.
- Open the AR software.
- Click Import STL, select the impacted supernumerary tooth model and the anterior dentition model exported in the previous steps, click OK, and click Save project.
6. Preoperative preparation
- Place the patient in the supine position and adjust the dental chair to the surgical position.
- Disinfect the intraoral and extraoral regions with 0.5% povidone-iodine.
- Cover the head, face, and neck with sterile drapes, exposing only the region from the nasal tip to the submental point.
- Perform local infiltration anesthesia on the buccal and palatal mucosa of the surgical area using approximately 1.7 mL of 4% articaine hydrochloride with epinephrine 1:100,000, containing 68 mg of articaine hydrochloride and 17 µg of epinephrine bitartrate.
- Cover the camera data cable and miniature support bracket with a sterile sleeve. During image acquisition, keep the camera at least 30 cm away from the sterile surgical field.
7. Establishment of the surgical approach under AR assistance
NOTE: Perform the procedure with a team consisting of an attending oral surgeon experienced in AR technology, a surgical assistant, and an AR operation assistant.
- Retract the upper lip using a retractor and a mouth mirror to expose the surgical field.
- Open the AR software and the project file. Select the anterior dentition model and use it as the registration marker. Click Virtual and Navigation > Camera AR Navigation, then select the camera to use to enter the AR navigation interface.
- After the navigation module is successfully activated, the navigation interface displays the live camera view. The registration marker's contour appears at the center of the screen. Because the camera is positioned at a distance and angle from the surgical field, manually adjust the registration marker's size and orientation to match the dentition contour in the camera view. This step serves only as an initial alignment; the final registration is automatically completed in Step 7.4.
- When the feature matching and localization confidence reach the preset threshold (0.7), the system automatically completes registration. Feature matching refers to the matching between the projected contour and the geometric features of the patient-specific three-dimensional anterior dentition model and the visible anterior dentition in the live RGB camera view.
NOTE: Localization confidence refers to the software-estimated reliability of the dentition marker's spatial localization in the camera view. The threshold value of 0.7 represents the preset minimum tracking quality required to accept automatic registration. Registration was considered successful only when both feature matching and localization confidence reached this threshold. This threshold was selected based on repeated preliminary tests to balance rapid recognition and stable AR overlay, but it does not represent a quantitatively measured surgical localization accuracy. - After registration, the contour of the dentition marker changes from red to green. According to the preoperatively defined spatial relationship, the virtual model of the supernumerary tooth is overlaid on the live camera image and displayed on the screen. At this point, the displayed position of the virtual tooth model indicates the location of the impacted supernumerary tooth.
- Adjust the camera angle to obtain an optimal view of the virtual model for intraoperative reference. When the camera is slowly rotated, the relative view between the camera and the dentition marker changes. Because the spatial relationship between the supernumerary tooth model and the dentition marker has been defined preoperatively, the view of the virtual supernumerary tooth model on the screen updates accordingly with the camera view.
- During surgery, have the AR operation assistant hold the camera using a miniature support bracket and continuously adjust the camera position so that the anterior maxillary surgical field is centered in the camera view and the camera optical axis is kept as perpendicular as possible to the surgical field surface, thereby obtaining an optimal operative view.
- Adjust the transparency of the virtual supernumerary tooth model until the scalpel is visible beneath the model in the AR navigation interface. The surgeon can use the screen-displayed contours of the overlaid virtual model to estimate the approximate boundaries of the actual supernumerary tooth. Then, make an approximately 1 cm labial mucosal incision centered over the estimated cervical region of the supernumerary tooth, with the incision oriented approximately perpendicular to the long axis of the supernumerary tooth (Figure 3A). Elevate the mucoperiosteal flap and expose the bone overlying the supernumerary tooth.
- If surgical instruments frequently obscure the dentition recognition area and interrupt real-time AR navigation, activate the image-locking function. After overlaying the virtual model onto the live camera image, lock its position relative to the real anatomical structures and use the screen display as an intraoperative reference for localizing the supernumerary tooth.
NOTE: In the present case, the image-locking function was not used because real-time AR navigation remained stable with minimal intraoperative interference.
8. Exposure and removal of the impacted supernumerary tooth
- Under AR-assisted localization, identify the position and approximate boundaries of the actual supernumerary tooth based on the screen-displayed contours of the virtual model. Use a surgical handpiece to remove the bone overlying the estimated crown area until the crown of the supernumerary tooth is exposed (Figure 3B,C).
- Once the tooth is exposed, perform subsequent sectioning and extraction under direct visualization without further AR guidance.
- Use the surgical handpiece to section the exposed tooth structure in a mesiodistal direction, thereby separating the crown from the root and eliminating resistance. Alternately use a dental elevator and mosquito forceps to remove the crown and root (Figure 3D,F).
- Curette the extraction socket with a curette to ensure that no dental follicle tissue remains.
- Irrigate the extraction socket with sterile saline to ensure that no tooth fragments remain (Figure 3E).
- Close the incision with 3-0 nonabsorbable sutures and apply pressure with hemostatic gauze to achieve hemostasis.
9. Postoperative management
- Observe the patient for 1 h after surgery and discharge the patient when no obvious wound bleeding is present. Allow the patient to start a cool liquid diet 2 h after surgery and gradually transition to a soft diet. Instruct the patient to maintain strict oral hygiene in the surgical area.
- Prescribe oral amoxicillin capsules, 0.5 g twice daily for 3 days, for postoperative infection prophylaxis. Instruct the patient to take one 0.3 g ibuprofen capsule as needed for postoperative pain.
- Remove the sutures 1 week after surgery. Instruct the patient to monitor for wound bleeding, pain, or discomfort and to seek medical attention promptly if any of these symptoms occur.
Results
A 17-year-old female patient underwent CBCT examination during an orthodontic consultation, which revealed two impacted supernumerary teeth in the anterior maxillary region. After evaluation by the orthodontist, removal of the two supernumerary teeth and one retained deciduous tooth was recommended. Intraoral examination showed the retained deciduous tooth, while neither of the supernumerary teeth had erupted into the oral cavity. CBCT showed an inverted supernumerary tooth located above the apex of the right maxillary lateral incisor, with complete bony impaction. The other supernumerary tooth was located on the palatal side between the left maxillary central incisor and lateral incisor, oriented in the labial-palatal direction, and was not completely covered by bone; therefore, its localization difficulty was relatively low. After the condition, treatment plan, potential risks, and alternative treatment options were fully explained to the patient and her family, they agreed to have the inverted, bony-impacted supernumerary tooth above the apex of the right maxillary lateral incisor removed with AR assistance. The other supernumerary tooth and the retained deciduous tooth were removed using a conventional approach.
The perioperative outcomes were as follows: digital design took 15 min. During surgery, the anterior dentition was used as the dentition marker. After the initial manual alignment was completed, no additional point-based intraoperative registration procedure was required, as the AR system automatically completed matching and registration. Using AR-assisted localization, the surgeon identified the incision site and prepared the bone window to expose the impacted supernumerary tooth. The surgical procedure, from incision to complete removal of the impacted supernumerary tooth, took 10 min. During the procedure, AR tracking was temporarily interrupted because surgical instruments obstructed the dentition recognition area. After the anterior dentition was re-exposed, the system recognized it again, and navigation was resumed.
No intraoperative damage to the adjacent tooth roots or important neurovascular structures was observed. The impacted supernumerary tooth was completely removed after crown sectioning to eliminate resistance. Because postoperative inspection showed that the extracted tooth was intact and that no residual tooth fragments or dental follicle tissue remained in the extraction socket, no additional postoperative CBCT examination was performed. The other supernumerary tooth was removed after conventional incision and flap elevation, and the retained deciduous tooth was removed routinely.
The patient returned 1 week after surgery for suture removal. Clinical examination showed no mucosal redness, swelling, or other signs of inflammation in the surgical area. The patient reported no mucosal sensory abnormality. The adjacent teeth showed no discomfort on percussion and no mobility.
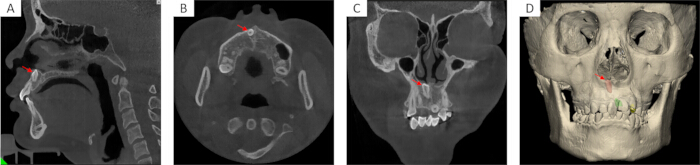
Figure 1: Preoperative CBCT images and 3D reconstruction of the supernumerary teeth. (A) sagittal, (B) axial, and (C) coronal CBCT images showing the position of the impacted supernumerary teeth (red arrows) in the anterior maxilla and their relationship with adjacent tooth roots and surrounding bone. (D) 3D reconstruction model showing the maxilla, dentition, and two supernumerary teeth. The red model represents the labial supernumerary tooth removed with AR assistance, and the green model represents the palatal supernumerary tooth removed using the conventional approach. Please click here to view a larger version of this figure.
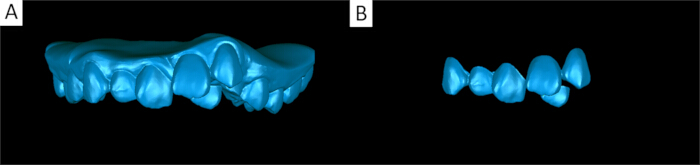
Figure 2: Processing of the intraoral scan model. (A) Repaired maxillary intraoral scan model used for registration with the reconstruction model. (B) A trimmed maxillary anterior dentition model used for markerless AR contour registration. Please click here to view a larger version of this figure.
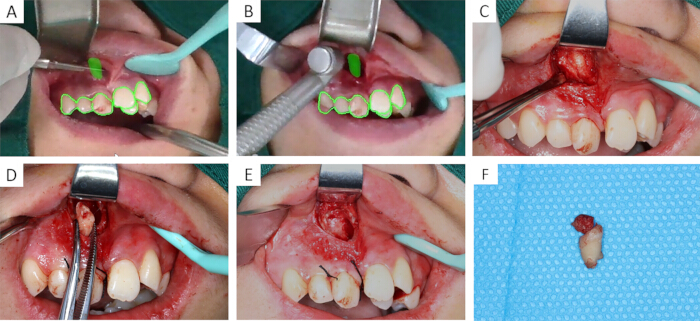
Figure 3: Key intraoperative steps of augmented reality-assisted removal of an impacted supernumerary tooth. (A) Localization before incision. The virtual model of the impacted supernumerary tooth was overlaid on the live camera image displayed in the AR navigation interface. The green contour represents the registered anterior dentition, and the green solid model represents the planned position of the impacted supernumerary tooth. (B) AR navigation was used to guide localization during bone removal. (C) The impacted supernumerary tooth was exposed after removal of the overlying bone. (D) The sectioned tooth fragment was removed from the extraction socket. (E) The extraction socket was inspected after complete removal of the impacted supernumerary tooth. (F) The extracted supernumerary tooth was examined to confirm complete removal. Please click here to view a larger version of this figure.
Discussion
Supernumerary teeth are a common developmental dental anomaly and may lead to complications such as abnormal eruption of adjacent teeth, root resorption, dental arch irregularities, and cyst formation. For supernumerary teeth that interfere with permanent tooth eruption, carry a risk of complications, or affect subsequent orthodontic treatment planning, surgical removal is usually the main treatment option. Supernumerary teeth that have erupted through the mucosa and are directly visible, or those that have penetrated the bone and can be visualized after mucosal incision, are relatively easy to remove. In contrast, supernumerary teeth completely impacted within the bone cannot be directly observed in the surgical field. The determination of their labial-palatal position, bone window size, and surgical approach mainly depends on the surgeon’s spatial interpretation of preoperative images and clinical experience, making these cases more challenging, especially for less experienced young surgeons. Although conventional surgical techniques can also be used to remove impacted supernumerary teeth, their success depends heavily on the surgeon’s experience. If the intraoperative localization deviates from the actual tooth position, excessive bone removal may occur, increasing the risk of injury to adjacent tooth roots or important anatomical structures. At present, various digital technologies have been applied to the removal of impacted supernumerary teeth and have shown preliminary results in localizing the tooth's position, preserving bone, and reducing complications. However, these methods still have limitations, including high time costs, expensive equipment, and difficulty in widespread implementation.
This study proposes a stereo camera-based, augmented-reality-assisted method for removing impacted supernumerary teeth. Preoperatively, 3D models of the supernumerary tooth and adjacent teeth are reconstructed using CBCT and intraoral scan data. Through markerless AR registration, the virtual model is overlaid onto the live camera image displayed in the AR navigation interface, providing a visual reference to help the surgeon estimate the location of the impacted supernumerary tooth. In this workflow, satisfactory CBCT–intraoral scan registration, stable dentition recognition, and appropriate adjustment of the camera angle while maintaining a relatively consistent camera position are critical steps for successful implementation. These steps are necessary to obtain a clear operative view and a stable AR overlay. Therefore, adequate preclinical training and repeated practice are required to ensure reliable preoperative digital design and proficient intraoperative operation of the AR system. Compared with navigation methods that rely on external markers or physical surgical guides, this method does not require the placement of additional artificial markers in the surgical field. This reduces interference from extra registration devices in the limited intraoral space and surgical field, while preserving the natural morphology of the dentition as the basis for registration. In this system, surgical field images are captured by a camera, and the AR overlay is displayed on a screen. Therefore, the system's application is affected by the camera angle, surgical field exposure, and instrument obstruction. The labial approach in the anterior maxillary region usually provides a more direct camera view and sufficient exposure of the surgical field. Soft tissue and instrument obstruction are relatively limited in this approach, which is more favorable for maintaining recognition of dentition contour and virtual-real overlay stability. Compared with conventional surgery, this method may help the surgeon optimize bone window design and localize the surgical approach, thereby potentially reducing the risk of complications. Compared with other digital techniques, this method has a relatively simple hardware configuration and certain advantages in cost and workflow.
However, this protocol still has several limitations. In the present case, AR was used for assisted localization of the impacted supernumerary tooth, and the estimated localization position was used as a visual reference to assist incision positioning and bone-window preparation. It did not provide a preplanned incision line, predefined bone-window boundary, surgical trajectory, or tooth-sectioning plane, which limited the role of AR in this workflow to some extent. In future cases, the design of the incision line, definition of the bone-window boundary, design of the surgical trajectory, and the predefinition of the tooth sectioning plane could be incorporated into the preoperative digital design and visualized intraoperatively using AR, thereby further enhancing the value of this technique for surgical pathway planning and operative guidance. The AR navigation image depends on camera-based acquisition of the surgical field, and image clarity, lighting conditions, camera angle, and surgical field exposure may all affect dentition contour recognition and registration stability. During the procedure, the camera is held by an assistant under sterile conditions. Therefore, the relative stability between the camera and the surgical field must be maintained to avoid overlay deviation caused by hand tremor or changes in viewing angle. In addition, the markerless registration method used in this protocol is based on the contour of the anterior dentition. Surgical instruments, suction devices, or soft tissue may obstruct the camera view and interrupt navigation. In such cases, repeated registration is required, which may affect the surgical workflow. Furthermore, the surgeon mainly observes the AR overlay on a display screen. For beginners, the screen-based two-dimensional display differs from the human eye's natural stereoscopic vision, which may make it difficult to understand the spatial relationship between the virtual model and the real surgical field. To address these issues, improvements can be made through both training and system optimization. First, standardized simulation training with 3D-printed models can be used to familiarize surgeons with image registration, virtual-real overlay interpretation, and AR-assisted bone window localization, thereby reducing localization errors caused by insufficient familiarity with the technology. Second, tracking algorithms and clinical application scenarios can be further optimized. For example, once stable registration is achieved, the spatial relationship between the dentition contour and the virtual model can be locked, and the virtual model's position can be updated in real time as dentition features are re-exposed. The camera can also be fixed with a mechanical support or integrated into an operating light to reduce hand-held camera vibration and operational burden.
The stereo camera-based AR-assisted method for impacted supernumerary tooth removal provides an intuitive and simplified visual aid for intraoperative localization. This method has certain advantages in hardware configuration, workflow, and potential clinical implementation. However, the present single-case demonstration only demonstrates feasibility in clinical practice, and its clinical application should be approached with caution. Further larger-sample and multicenter studies are needed to validate its localization accuracy, clinical efficiency, and safety. Considering the equipment's technical advantages and accessibility, this method may have potential for future use in primary healthcare settings, where access to advanced digital surgical equipment is often limited. This study preliminarily demonstrates the feasibility of using this technique to remove impacted supernumerary teeth and provides a methodological basis for establishing a standardized AR-assisted extraction workflow.
Disclosures
The authors used DeepSeek solely for English-language editing and translation assistance. All AI-assisted text was reviewed and revised by the authors, who take full responsibility for the final content of the manuscript.
Acknowledgements
This work was supported by the Kunming Medical University Team for Diagnosis and Treatment of Complex Craniofacial Malformations (2024XKTDTS08), Yunnan Provincial Clinical Medical Center Research Project (2024YNLCYXZX0227, 2024YNLCYXZX0229), Yunnan Clinical Research Center for Oral Diseases (202505AJ310001), the Yunnan Province High Level Talent Training Support Plan (YNWR-MY-2020-086), Kunming Medical University Education and Teaching Research Project (2026-JY-Z-18).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 0.5% povidone-iodine | N/A | N/A | Used for intraoral and extraoral disinfection before surgery. |
| 3-0 non-absorbable silk suture | Johnson (Suzhou) Medical Devices Co., Ltd. | Tissue suturing. | |
| 4% articaine hydrochloride with epinephrine | Used for local anesthesia. | ||
| Camera | Intal RealSense | D415 | Used to acquire the real-time visual field for recognition of the marker. |
| CBCT | Quantitative Radiology s.r.1.Verona, Italy | New Tom 3G | Used to acquire images of the tooth and surrounding structures. |
| Curette | N/A | N/A | Used to curette the extraction socket and remove residual dental follicle tissue. |
| Dental elevator | N/A | N/A | Used to loosen and remove the sectioned crown and root fragments. |
| E3D CMF | Hunan Liuwei Jinghang Digital Technology Co., Ltd., Hunan, China. | https://www.e3d-med.com/ | AR navigation software. |
| Geomagic Wrap 2021 | 3D Systems Corporation | version 2021 | Processing of the intraoral scan model and segmentation of the anterior teeth for use as the registration marker. |
| hemostatic gauze | N/A | N/A | Used for compression hemostasis after wound closure. |
| Intraoral scanner | SHINING 3D | Aoralscan 3 CA3-C80046J04;https://www.shining3d.cn/ | Used to acquire digital dental arch data. |
| J45-LED surgical handpiece | Guangdong JINME Medical Technology Co., Ltd. | 45-TUP; https://www.jinmedental.cn/ | Removal of the bone overlying the supernumerary tooth and sectioning of the crown from the root. |
| Laptop computer | Lenovo Group Limited | Legion Y7000 IRX9; Intel Core i7-13650HX CPU; NVIDIA GeForce RTX 4060 Laptop GPU, 8 GB GDDR6; 24 GB DDR5 RAM; 512 GB SSD. | Running the AR software. |
| Mimics | Materialise | version 21.0 | Used for three-dimensional reconstruction. |
| Sterile drapes | N/A | N/A | Used to cover the head, face, and neck, exposing only the surgical region. |
| Sterile sleeve | N/A | N/A | Used to cover the camera data cable and miniature support bracket during intraoperative image acquisition. |
| USB 3.0 cable | N/A | N/A | Used to connect the camera to the laptop computer for image acquisition. |
References
- Tworkowski K, Gąsowska E, Baryła D, Gabiec K. Supernumerary teeth: literature review. J Pre Clin Clin Res. 2020;14(1):18-21.
- He L, et al. Prevalence, clinical characteristics, and 3-dimensional radiographic analysis of supernumerary teeth in Guangzhou, China: a retrospective study. BMC Oral Health. 2023;23(1):351.
- Barham M, et al. Influence of mesiodens on adjacent teeth and the timing of its safe removal. Imaging Sci Dent. 2022;52(1):67-74.
- Jang DH, et al. Determination of the range of intervention timing for supernumerary teeth using the Korean Health Insurance Review and Assessment Service database. J Clin Pediatr Dent. 2023;47(1):67-73.
- Pacurar C, et al. Impaction predictors and diagnostic performance of CBCT versus panoramic radiography for supernumerary teeth in a Romanian multicenter cohort. Diagnostics (Basel). 2025;15(23):3019.
- Maddalone M, Rota E, Amosso E, Porcaro G, Mirabelli L. Evaluation of surgical options for supernumerary teeth in the anterior maxilla. Int J Clin Pediatr Dent. 2018;11(4):294-8.
- Jo C, Bae D, Choi B, Kim J. Removal of supernumerary teeth utilizing a computer-aided design/computer-aided manufacturing surgical guide. J Oral Maxillofac Surg. 2017;75(5):924.e1-9.
- Xu F, et al. Precision extraction of lingual mandibular supernumerary teeth using dynamic navigation and high-speed handpieces: a case report. Am J Case Rep. 2024;25:e945262.
- Liu SL, Li M, Zhang FQ, Ma W. Assisted removal of impacted supernumerary teeth using HoloLens 2 and mixed reality. J Oral Maxillofac Surg. 2026;84(5):753-9.
- Liu C, et al. Efficiency for robotic-assisted extraction of completely impacted supernumerary teeth in children: a randomized controlled trial. BMC Oral Health. 2025;25(1):1831.
- Lysenko A, et al. The use of augmented reality navigation technology in combination with endoscopic surgery for the treatment of an odontogenic cyst of the upper jaw: a technical report. Imaging Sci Dent. 2022;52(2):225-30.
- Rosu SN, et al. Augmented reality in implant and tooth-supported prosthodontics practice and education: a scoping review. Dent J (Basel). 2025;13(9):435.
- Civita F, et al. Augmented reality vs CAD/CAM system in orthognathic surgery: development and accuracy evaluation. Maxillofac Plast Reconstr Surg. 2025;47(1):33.
- Lin L, et al. The application of augmented reality in craniofacial bone fracture reduction: study protocol for a randomized controlled trial. Trials. 2022;23(1):241.
- Ceccariglia F, et al. Application of augmented reality to maxillary resections: a three-dimensional approach to maxillofacial oncologic surgery. J Pers Med. 2022;12(12):2047.
- Pellegrino G, et al. Augmented reality in dental extractions: narrative review and an AR-guided impacted mandibular third-molar case. Appl Sci (Basel). 2025;15(17):9723.