This study integrates network-based target mapping, GEO expression data, and docking to rank candidates related to the Zhenwu-Wuling combination in chronic heart failure.
Research Article
Network Pharmacology, GEO Transcriptomics, and Molecular Docking of Zhenwu Decoction with Wuling Powder for Chronic Heart Failure
29 views
⸱
September 11th, 2026
In This Article
Summary
Abstract
Zhenwu Decoction combined with Wuling Powder is used in chronic heart failure (CHF), but its molecular basis is not fully defined. We integrated network-based target mapping, Gene Expression Omnibus (GEO) transcriptomic data, and molecular docking to prioritize candidate targets and pathways. Compound records for the eight herbs were obtained from pharmacological and chemical databases and subjected to compound and target screening. CHF-associated genes were collated from six disease resources, and their overlap with formula-related targets was examined using PPI network and functional enrichment analyses. GSE5406 provided myocardial expression data for failing and nonfailing samples. The workflow yielded 89 screened compounds, 314 nonredundant compound targets, and 2,515 CHF-related targets, with 143 shared genes. AKT1, IL6, TNF, SRC, and ESR1 ranked highest in the disease-target network. The expression analysis returned 1,348 differentially expressed genes (DEGs) and selected HSP90AA1 and STAT1 as transcriptomic hub candidates. Enriched terms clustered around hypoxia, circulation, TNF-related signaling, PI3K-Akt, and MAPK pathways. Docking produced negative predicted scores for representative constituent-target pairs; the most negative score was observed for STAT1 and alisol C (-9.2 kcal/mol). These findings generate a testable computational hypothesis and prioritize candidates for experimental validation.
Introduction
CHF comprises a heterogeneous syndrome arising from structural or functional myocardial abnormalities. Such changes can compromise ventricular filling or systolic ejection and are often accompanied by pulmonary or systemic congestion. Typical symptoms include dyspnea, fatigue, and fluid retention1. A retrospective analysis of China's Global Burden of Disease data from 1990 to 2023 showed that the national prevalence of newly diagnosed CHF increased by 208.4% over three decades2.
In traditional Chinese medicine (TCM), CHF corresponds to cardiac edema, dyspnea syndrome, and generalized edema. Its pathogenesis is commonly described as deficiency in the root and excess in the branch. Deficiency of yin, yang, and qi constitutes the underlying pathological basis, whereas internal fluid accumulation and blood stasis represent the manifest excess. Accordingly, TCM management emphasizes warming yang, removing retained fluid, promoting circulation, and resolving stasis.
The combined use of Zhenwu Decoction and Wuling Powder is a classical herbal strategy for clinical CHF management. Zhenwu Decoction warms yang and promotes diuresis, whereas Wuling Powder supports yang qi and regulates fluid metabolism. Together, the two formulas may reinforce yang and eliminate internal dampness. Clinical evidence suggests that this combination can relieve symptoms, improve cardiac function indicators, and slow CHF deterioration3. We first mapped formula constituents and candidate CHF targets using network pharmacology, then used docking to rank selected constituent-target pairs. GEO-derived expression profiles were then used to place the network candidates in a myocardial disease context and to examine downstream pathways. The study provides a hypothesis-generating computational framework for prioritizing candidates for subsequent experimental validation; it does not establish clinical efficacy or a validated mechanism.
Protocol
This study analyzed public database resources and did not involve new human participants, human specimens, or animal experiments. All databases, web-based resources, software, analysis packages, visualization tools, molecular docking tools, and other computational resources used in this study, together with their details, are listed in the Table of Materials.
Formula composition and botanical provenance
The eight distinct crude drugs were aligned to current botanical and pharmacopoeial naming as follows: Aconiti Lateralis Radix Praeparata, the processed lateral root of Aconitum carmichaelii Debeaux; Poria, the sclerotium of Wolfiporia cocos (F.A.Wolf) Ryvarden & Gilb.; Atractylodis Macrocephalae Rhizoma, the rhizome of Atractylodes macrocephala Koidz.; Paeoniae Radix Alba, the root of Paeonia lactiflora Pall.; Zingiberis Rhizoma Recens, the fresh rhizome of Zingiber officinale Roscoe; Alismatis Rhizoma, the rhizome of Alisma orientale (Sam.) Juzep.; Polyporus, the sclerotium of Polyporus umbellatus (Pers.) Fr.; and Cinnamomi Ramulus, the young twig of Cinnamomum cassia (L.) J.Presl. The prescription comprised 9 g Aconiti Lateralis Radix Praeparata, 12 g Poria, 9 g Paeoniae Radix Alba, 12 g Atractylodis Macrocephalae Rhizoma (stir-fried Atractylodes), 9 g Zingiberis Rhizoma Recens, 9 g Polyporus, 15 g Alismatis Rhizoma, and 6 g Cinnamomi Ramulus; the corresponding ratio was 3:4:3:4:3:3:5:2. Aconiti Lateralis Radix Praeparata was treated as processed material. This was an entirely in silico study: no decoction batch was prepared, purchased, chemically assayed, or administered. Manufacturer, lot number, batch-specific processing records, and voucher specimens are therefore not applicable; the gram amounts define the formula composition and relative ratio, not experimental exposure. Poria and Atractylodis Macrocephalae Rhizoma are shared by the two formulae. Botanical names and medicinal-part terminology were checked against the 2025 Pharmacopoeia of the People’s Republic of China4.
Screening and target prediction of active ingredients in Zhenwu Decoction and Wuling Powder
TCMSP was queried separately for compounds recorded for Zhenwu Decoction and Wuling Powder, including Aconiti Lateralis Radix Praeparata, Poria, Atractylodis Macrocephalae Rhizoma, Paeoniae Radix Alba, Zingiberis Rhizoma Recens, Alismatis Rhizoma, Polyporus, and Cinnamomi Ramulus. Initial filtering required oral bioavailability (OB) of at least 30% and drug-likeness (DL) of at least 0.18. When a simplified molecular-input line-entry system (SMILES) record was unavailable, the corresponding structure was retrieved from a public chemical database. SMILES records were evaluated for physicochemical and drug-likeness properties. A compound passed the secondary filter when its molecular weight was ≤500, lipophilicity ≤5, hydrogen-bond donors ≤5, hydrogen-bond acceptors ≤10, at least three of the Lipinski, Ghose, Veber, Egan, and Muegge rule sets were positive, and predicted gastrointestinal absorption was high5. Eligible structures were subjected to target prediction, and only predictions with probability >0.02 were included in the target list. TCMSP and target-prediction records were combined at the herb-compound-target level, duplicate identifiers were collapsed, and gene names were standardized to official gene symbols.
Deduplication produced 646 candidate associations; 71 rows without a mapped official gene symbol were excluded, leaving 575 standardized associations. The independent herb-level integration yielded 314 nonredundant target genes. The compound and target screening criteria are supported by the TCMSP and SwissTargetPrediction source papers6,7.
Screening of disease targets for CHF
CHF-related gene entries were downloaded from GeneCards, OMIM, TTD, DisGeNET, DrugBank, and PharmGKB. The disease search used four phrases: heart failure, congestive heart failure, diastolic heart failure, and systolic heart failure. For GeneCards, entries with relevance scores below 0.20 were excluded. The six database-derived target sets were integrated after duplicate identifiers were removed, while preserving the source database for each record. All screened gene names were standardized to official gene symbols. The overlap between the formula and CHF target lists was visualized using a Venn diagram. The shared identifiers were treated as candidate formula-related targets for CHF.
TCMSP was searched on 7 February 2026; SwissTargetPrediction, GeneCards, OMIM, and DisGeNET on 10 February 2026; and PharmGKB, TTD, and DrugBank on 12 February 2026. Disease queries were entered as heart failure, congestive heart failure, heart failure, diastolic, and heart failure, systolic; the search was restricted to Homo sapiens where supported. Retrieved entries were standardized to official gene symbols before deduplication.
Construction of the protein-protein interaction (PPI) network and screening of core targets
The shared target identifiers were queried in STRING for PPI analysis. The query used Homo sapiens interactions and a confidence cutoff above 0.9. Isolated nodes were omitted, and the resulting STRING interaction data were used for network visualization and topological analysis. Candidate hubs were ranked by network topology. Betweenness, closeness, degree, and eigenvector centralities were calculated as network descriptors. Degree was the primary ranking variable, and the five highest-degree targets were retained as candidate hubs.
Official gene symbols were used for gene-level analyses, including AKT1, IL6, TNF, SRC, ESR1, BCL2, CASP3, PPARG, PTGS2, and MMP9; protein names are written in full only when needed for clarity. The initial PPI network contained 143 nodes and 584 interaction records before visualization-specific filtering; after network processing, the graph contained 143 nodes and 292 edges.
Construction of the drug-disease-component-target network
Once names were standardized, the network data were assembled and used to construct the drug-disease-component-target graph.
GO and KEGG enrichment analyses
The candidate CHF target list was submitted to Metascape for functional annotation and pathway enrichment analysis. The analysis was run for Homo sapiens. The raw p-value cutoff was set at 0.01, a minimum overlap of 3, and a minimum enrichment score of 1.5. GO bar charts and KEGG bubble plots were generated for visualization. The 143-gene input set was used for Gene Ontology biological-process (GO-BP), molecular-function (GO-MF), and KEGG enrichment analyses. The analysis thresholds were raw p < 0.01, minimum overlap 3, and minimum enrichment 1.58. The GO-CC analysis was based on a 60-gene hit list against a 30,230-gene library. Because this input differed from the 143-gene input used for the BP, MF, and KEGG analyses, the GO-CC results were reported separately and were not quantitatively pooled with the other categories.
Screening of heart failure-related targets based on the GEO database
The GSE5406 dataset9 was used for differential-expression analysis. The series included 210 myocardial samples: 108 with ischemic cardiomyopathy, 86 with idiopathic dilated cardiomyopathy, and 16 nonfailing donor controls. The GEO record identifies the platform as GPL96, the Affymetrix Human Genome U133A Array. The series matrix was already robust multi-array average (RMA)-normalized. Probes without matched SYMBOL annotations were removed after matching to the platform annotation, and rowSums(expression > 0.5) ≥ 3 was applied before limma fitting. Group levels were defined as Control, DCM, and ICM, with a no-intercept design matrix (~0 + group) and the contrasts (DCM+ICM)/2-Control, DCM-Control, and ICM-Control. Differential expression was defined as adjusted p value < 0.05 and |log2(Fold Change)| > 0.3. Because all samples were processed within one GEO series and no separate batch variable was available, no batch-correction term was introduced. Differential-expression results were visualized using heatmaps and volcano plots. DEGs were subjected to PPI analysis followed by network-based hub ranking. Docking and pose visualization were conducted for the selected targets and prescription compounds.
The GEO record identifies the platform as GPL96, the Affymetrix Human Genome U133A Array. Group levels were defined as Control, DCM, and ICM, with a no-intercept design matrix (~0 + group) and the contrasts (DCM+ICM)/2-Control, DCM-Control, and ICM-Control. The series matrix was already robust multi-array average (RMA)-normalized; probes with missing SYMBOL annotations were removed after matching to the platform annotation, and the code applies rowSums(expression > 0.5) ≥ 3 before limma fitting. Because all samples were processed within one GEO series and no separate batch variable was available, no batch-correction term was introduced.
Molecular docking verification
A three-dimensional PDB structure for each receptor was obtained from the RCSB Protein Data Bank. Protein structures were prepared by removing crystallographic waters and non-receptor ligands. Structure-data file (SDF) structures for the five highest-degree compounds were obtained from a public chemical database.
The receptor structures used for docking were AKT1/1H10 (chain A, 1.40 Å, 4IP), IL6/1ALU (chain A, 1.90 Å, TLA), TNF/1A8M (chain A, 2.30 Å, no co-crystallized ligand), SRC/1A09 (chain A, 2.00 Å, no ligand), ESR1/1A52 (chain A, 2.80 Å, EST), STAT1/1BF5 (chain A, 2.90 Å, no ligand), and HSP90AA1/3OWB (chain A, 2.05 Å, BSM). The center, box dimensions, and random seed were specified for each tested pair. The search boxes were defined to encompass the receptor for exploratory global docking.
Receptor and ligand files were prepared with the docking-preparation tools. Waters were deleted and polar hydrogens were added to receptor structures. SDF ligands were converted to PDB, then dehydrated and hydrogenated before PDBQT export. The prepared receptor-ligand files were assigned to the docking models. PDBQT files were loaded into AutoDock Vina. Vina runs were executed and scores were recorded. Scores below -5 kcal/mol were treated as comparatively more favorable and scores below -7 kcal/mol as more strongly predicted interactions10; these are not experimental thresholds. The three complexes with the best predicted scores were selected for visualization.
No search-depth or output-mode override was specified; therefore, the documented command-line defaults were used: exhaustiveness 8 and at most 9 modes. Pair-specific random seeds were used, and mode 1 (the best-scoring returned pose) was selected for representative visualization. The HSP90AA1 output-file assignment was confirmed because each mode-1 score matched the corresponding HSP90AA1 value in the docking-score matrix. Molecular dynamics simulations were not performed, so the scores are exploratory computational predictions only.
Results
Active ingredients and targets of Zhenwu Decoction combined with Wuling Powder
Constituent-target records were obtained for each herb. The corresponding per-herb target counts were Aconiti Lateralis Radix Praeparata, 178; Poria, 21; Atractylodis Macrocephalae Rhizoma, 18; Paeoniae Radix Alba, 86; Zingiberis Rhizoma Recens, 127; Alismatis Rhizoma, 96; Polyporus, 4; and Cinnamomi Ramulus, 45. After symbol standardization and deduplication, the integrated formula-related set contained 314 nonredundant target genes. The herb assignment of dihydrocapsaicin is reported as a database assignment rather than as confirmation of botanical provenance.
Acquisition of CHF related disease targets
Across the six disease resources, 3,563 raw CHF target records were collected. The distribution was as follows: 2,000 targets from GeneCards, 973 from OMIM, 17 from PharmGKB, 83 from TTD, 459 from DisGeNET, and 31 from DrugBank. Deduplication reduced the list to 2,515 unique CHF-associated targets. Comparison of the two target lists identified 143 intersecting targets between CHF-related genes and targets of Zhenwu Decoction combined with Wuling Powder, as shown in Figure 1.
Construction of the PPI network
The resulting PPI graph comprised 143 nodes and 292 edges (mean degree, 4.08). The five highest-degree nodes were AKT1, TNF, IL6, SRC, and ESR1. These nodes were retained as candidate hubs for the formula-CHF analysis (Figure 2). In this analysis, hub candidates were prioritized by degree within the specified network. High connectivity was used for candidate selection and was not interpreted as proof of causal importance or therapeutic efficacy.
Drug-disease-component-target network analysis
The finalized graph comprised 384 nodes and 615 edges. Here, node degree was defined as the number of directly connected edges. Table 1 reports the top ten targets ranked by degree value in the 384-node, 615-edge drug-disease-component-target network; the 143-node, 292-edge PPI network is reported separately in Figure 2. Figure 3 shows the corresponding drug-disease-component-target graph. In the network graph, regular hexagons represent active components of individual herbal medicines, whereas diamonds represent drug therapeutic targets.
GO enrichment analysis
Gene Ontology analysis was performed on the 143 shared targets. The analysis identified 1,647 biological-process (BP) terms and 188 molecular-function (MF) terms; the cellular-component (CC) panel is retained descriptively as explained below. All enriched terms were sorted by -log10(p) in descending order, and the top ten terms in each GO category were selected for visualization. BP terms were mainly enriched in cellular response to hypoxia, response to decreased oxygen levels, blood circulation, response to altered oxygen levels, and circulatory system processes. The descriptive CC panel displayed caveolae, ficolin-1-rich granule lumens, plasma membrane lipid rafts, membrane microdomains, and endocrine lumens; row-level CC statistics are not claimed. MF terms mainly involved scaffold protein binding, regulation of protein tyrosine kinase activity, heme binding, and regulation of protein kinase activity. The top ten enriched terms in each GO category were visualized in Figure 4. Because the GO-CC analysis used a different input size from the 143-gene BP/MF/KEGG analysis, the categories were reported separately and were not quantitatively pooled.
KEGG enrichment analysis
KEGG analysis was performed on the 143 shared target genes. The leading enriched pathways were MAPK, PI3K-Akt, cancer-related pathways, viral infection pathways, tuberculosis, influenza A, AGE-RAGE, lipid/atherosclerosis, and measles (Figure 5).
Screening of DEGs for heart failure based on the GEO database
GEO was queried with "heart failure", and limma in R was used to compare the failing and nonfailing groups. Screening thresholds were set as adjusted p value < 0.05 and |log2(Fold Change)| > 0.3. The analysis yielded 1,348 DEGs, of which 568 were upregulated and 780 were downregulated. A volcano plot displayed differential expression results, while a heatmap illustrated the expression pattern across the two groups (Figure 6, Figure 7).
The DEGs were first intersected with disease-related genes retrieved from disease databases, yielding 407 overlapping disease genes. These genes were then intersected with drug target genes, resulting in 18 intersecting genes. PPI analysis of the 18 genes generated a network with 18 nodes and 10 interaction edges. Among all nodes, HSP90AA1 and STAT1 had the highest degree values. The two transcriptomic hub candidates were docked against five prioritized compounds: β-sitosterol, alisol C, benzoylnapelline, dihydrocapsaicin, and kaempferol. The resulting Vina scores were negative across the tested pairs; STAT1 with alisol C yielded the most negative value (-9.2 kcal/mol), and every GEO-derived pair scored below -5 kcal/mol. These values are comparative docking predictions and do not establish affinity, activity, or biological effect.
Molecular docking results
Docking was used to compare prioritized constituents with CHF-related hubs from the network and GEO analyses. These included AKT1, IL6, TNF, SRC, and ESR1 from disease database mining, as well as the GEO-derived hub genes HSP90AA1 and STAT1. The docking procedure is described in the Protocol section. Table 2 summarizes the predicted-score matrix for the prioritized compounds and CHF-related targets from both analytical sources. Alisol C scored more negatively than -7 kcal/mol with AKT1 and SRC, while benzoylnapelline crossed the same descriptive cutoff for TNF, AKT1, and SRC. All GEO-derived hub-compound pairs scored below -5 kcal/mol. Among all ligand-target pairs, STAT1 gave the most negative score with alisol C (-9.2 kcal/mol) and benzoylnapelline (-8.7 kcal/mol), indicating the most negative predicted scores among the tested complexes, not experimental affinity.
DATA AVAILABILITY:
Publicly available data were analyzed in this study. The transcriptomic series GSE5406 is available from the NCBI Gene Expression Omnibus (GEO) under accession number GSE5406. All study-generated and retained data and analysis records are provided in the supplementary raw data folder (Supplementary File 1). It contains the compound and target audit, target source data, PPI network files, verified enrichment data, GSE5406 analysis code, docking inputs, outputs, configurations, and logs, docking visualizations, and file manifest and legends.
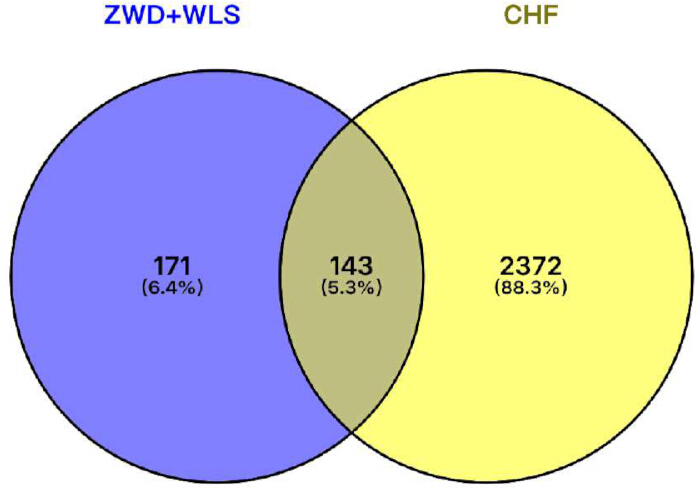
Figure 1: Venn diagram of drug and disease targets. The blue region represents targets of Zhenwu Decoction combined with Wuling Powder, the yellow region represents CHF-related targets, and the overlapping region represents the 143 shared targets. Numbers indicate target counts and percentages. Please click here to view a larger version of this figure.
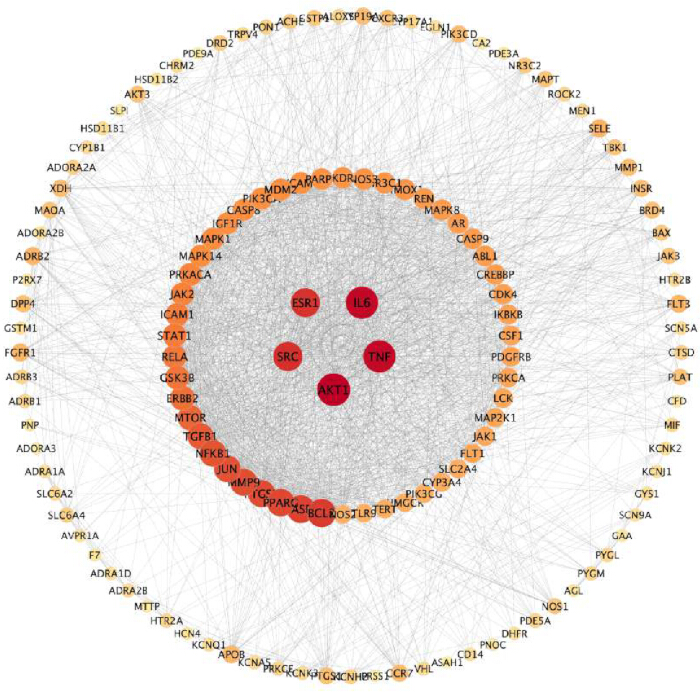
Figure 2: PPI network. Node color and size represent degree, with larger, darker-red nodes indicating higher-degree targets. Gray edges represent high-confidence PPI links. Isolated nodes are not shown. Please click here to view a larger version of this figure.
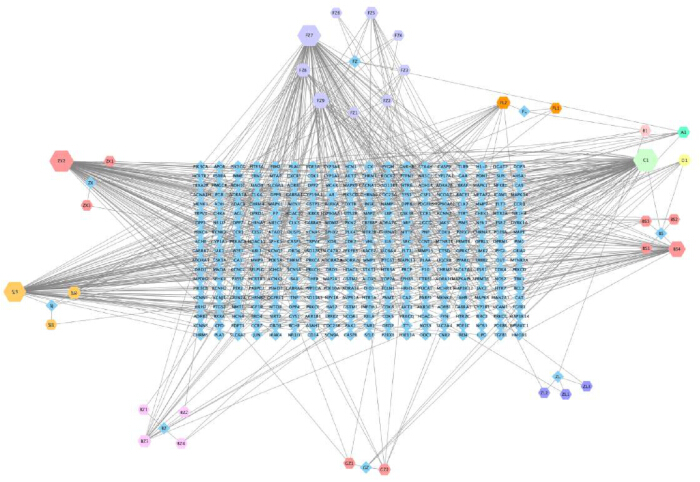
Figure 3: Drug-disease-component-target network. Node colors identify the eight herb groups; node shapes distinguish herbs, components, and targets; node size represents degree; gray edges represent herb-component and component-target associations. Please click here to view a larger version of this figure.
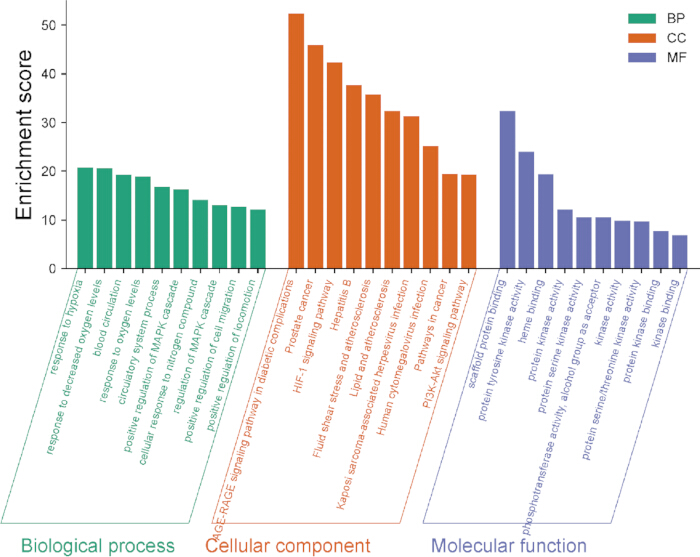
Figure 4: GO enrichment analysis. Green, orange, and purple bars represent biological process (BP), cellular component (CC), and molecular function (MF), respectively. Bar height indicates enrichment score, and the top ten terms in each category are shown. The CC analysis used a 60-gene hit list, whereas the BP and MF analyses used the 143-gene shared-target input; therefore, the categories are displayed descriptively and are not quantitatively pooled. Please click here to view a larger version of this figure.
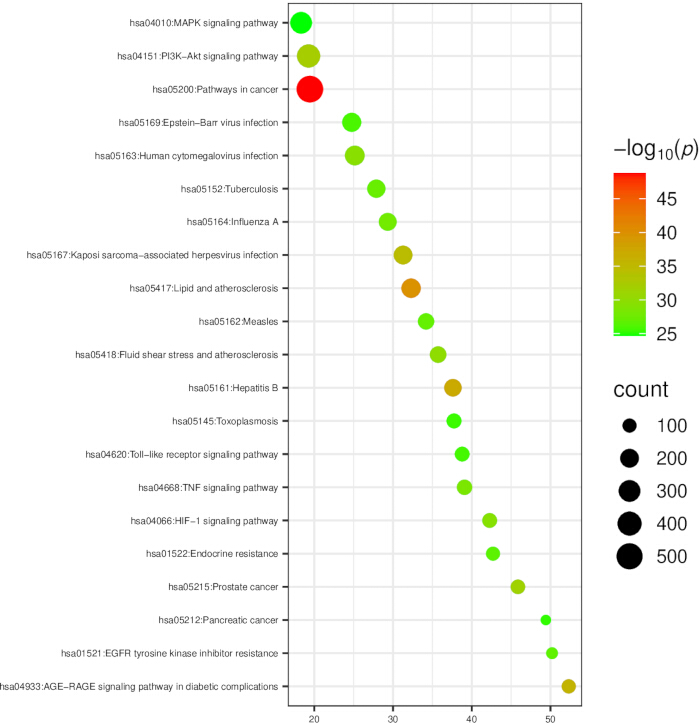
Figure 5: KEGG enrichment analysis. Dot position shows enrichment ratio, dot size shows gene count, and color encodes -log10(p), with warmer colors indicating smaller p values. Please click here to view a larger version of this figure.
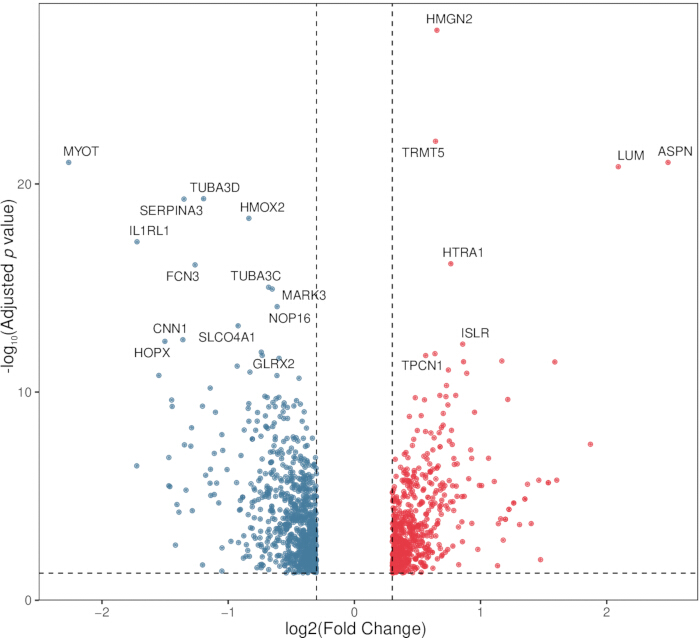
Figure 6: Volcano plot of differentially expressed genes. Red points represent upregulated genes and blue points represent downregulated genes at the stated thresholds. The vertical axis is -log10(adjusted p value), the horizontal axis is log2(Fold Change), and dashed lines indicate adjusted p value < 0.05 and |log2(Fold Change)| > 0.3. Please click here to view a larger version of this figure.
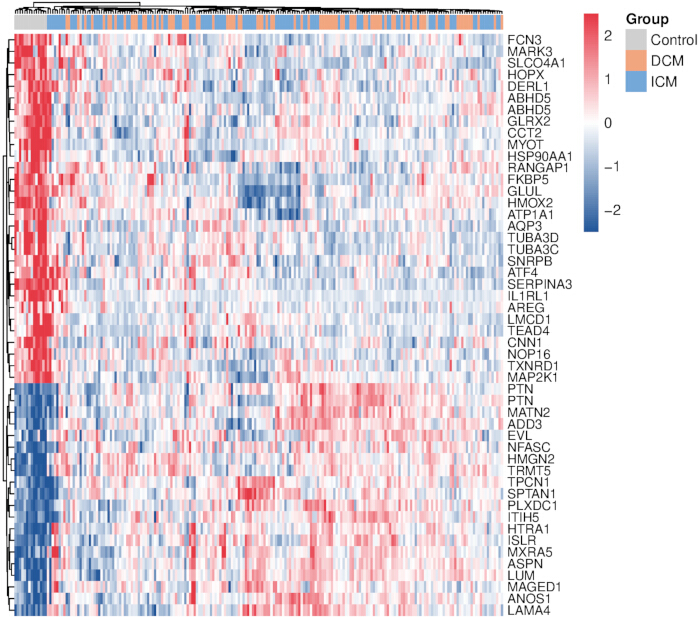
Figure 7: Heatmap of DEGs. The heatmap shows the top 50 DEGs; red and blue indicate relatively higher and lower expression, respectively, after row-wise scaling. The top annotation identifies the control, idiopathic cardiomyopathy, and ischemic cardiomyopathy groups. Please click here to view a larger version of this figure.
| Protein name | Gene symbol | Degree |
| AKT serine/threonine kinase 1 | AKT1 | 94 |
| Interleukin-6 | IL6 | 91 |
| Tumor necrosis factor | TNF | 91 |
| SRC proto-oncogene, non-receptor tyrosine kinase | SRC | 78 |
| Estrogen receptor 1 | ESR1 | 77 |
| B-cell lymphoma/leukemia 2 | BCL2 | 74 |
| Caspase 3 | CASP3 | 72 |
| Peroxisome proliferator-activated receptor gamma | PPARG | 70 |
| Prostaglandin-endoperoxide synthase 2 | PTGS2 | 69 |
| Matrix metalloproteinase 9 | MMP9 | 68 |
Table 1: Core genes and degree values. Degree values are from the 384-node, 615-edge drug-disease-component-target network, not the separate 143-node, 292-edge PPI network. Official gene symbols are used.
| Target gene | β-sitosterol | Alisol C | Benzoylnapelline | Dihydrocapsaicin | Kaempferol |
| AKT1 | -6.2 | -7.0 | -7.2 | -4.8 | -5.9 |
| IL6 | -5.7 | -6.6 | -6.1 | -4.0 | -4.6 |
| TNF | -5.5 | -6.8 | -7.6 | -5.0 | -6.3 |
| SRC | -5.2 | -8.0 | -8.0 | -5.6 | -6.9 |
| ESR1 | -3.2 | -6.7 | -7.9 | -4.3 | -3.2 |
| STAT1 | -6.1 | -9.2 | -8.7 | -5.3 | -8.6 |
| HSP90AA1 | -6.4 | -6.9 | -7.1 | -5.4 | -7.3 |
Table 2: Molecular docking scores. Values are predicted docking scores in kcal/mol; more negative values indicate more favorable predicted poses within this run and do not establish biological affinity or activity.
Supplementary File 1: Supplementary raw data folder. Please click here to download this file.
Discussion
CHF requires long-term clinical management and often involves complex medication regimens. Studies by Wang JX and Zhang S11 and other studies indicate that long-term combined conventional pharmacotherapy may reduce medication adherence. Poor adherence can increase the risk of readmission and adverse emotional outcomes. Available drugs largely focus on symptom control and slowing ventricular remodeling. The 2023 National Guidelines for the Management of Heart Failure in China12 recommend adding the soluble guanylate cyclase stimulator vericiguat to GDMT in patients with recently worsening heart failure. Nevertheless, several challenges remain in heart failure management. Cardiomyocytes are terminally differentiated and have limited regenerative capacity, so myocardial injury often progresses irreversibly. Existing medications mainly slow myocardial fibrosis and ventricular remodeling, rather than fully reversing established structural damage.
In TCM theory, the pathogenesis of CHF is closely associated with qi-blood dysregulation. The Expert Consensus on TCM Nomenclature of Heart Failure13 defines "Xin Shui" (heart edema) and "Fei Yin" (lung fluid retention) as standardized TCM disease terms for CHF. Both prescriptions warm yang and promote fluid excretion, yet their traditional indications emphasize different disease locations and patterns. Traditionally, Zhenwu Decoction is used to warm yang and remove retained dampness in spleen-kidney yang deficiency. First recorded in Lines 82 and 316 of the Treatise on Febrile Diseases14, the formula was originally used for yang-stage disease complicated by excessive sweating-induced yang impairment and for shaoyin syndrome characterized by yang deficiency and water flooding. The fundamental pathogenesis treated by Zhenwu Decoction is kidney yang insufficiency with diffuse fluid retention. Its traditional actions are described as warming the kidney, strengthening yang, regulating qi, and promoting fluid removal. The Synopsis of Prescriptions of the Golden Chamber14 also records the use of Zhenwu Decoction for overflow fluid retention, because limb heaviness and pain in this condition match the therapeutic scope of the formula. Wuling Powder is recorded in Lines 71, 72, 73, 74, and 141 of the Treatise on Febrile Diseases. It is mainly used for Taiyang bladder water retention syndrome. Its pathogenesis involves unresolved exterior pathogenic factors in the Taiyang stage, water accumulation in the lower jiao, impaired triple-jiao qi transformation, and disordered body fluid distribution. Clinically, these changes manifest as thirst with desire to drink and dysuria. In severe cases, excessive fluid accumulation obstructs the triple jiao and overflows, producing water counterflow with vomiting after drinking. Accordingly, Wuling Powder is used to restore qi transformation and facilitate water excretion.
Pharmacological research by Zheng Minghao et al. on Zhenwu Decoction for CHF15 reported higher LVSP and lower LVEDP after aconitine/mesaconitine exposure, findings interpreted as improved systolic and diastolic performance. In CHF rats, paeoniflorin was associated with modulation of TGF-β1/Smad signaling, less remodeling, and better cardiac function. Atractylenolide III and kaempferol have been linked to reduced cardiomyocyte apoptosis, while poricoic acid and gingerol are reported to show anti-inflammatory and antioxidant actions. Higenamine and paeoniflorin may also improve abnormal calcium cycling by reducing intracellular calcium concentration. Chen Jiye et al.16 reported that the main bioactive components of Wuling Powder, hederagenin and β-sitosterol, confer cardiovascular protection by lowering cholesterol, regulating endothelial function, enhancing antioxidant capacity, and reducing inflammation. Patients with end-stage CHF often show intermingled deficiency and excess patterns. Heart-kidney yang deficiency represents the root pathogenesis, whereas severe fluid retention represents the branch manifestation. When retained fluid spreads through the triple jiao, invasion of the upper jiao, heart, and lung causes palpitations, cough, and dyspnea. In severe cases, fluid overwhelming the heart and lung leads to orthopnea. Fluid accumulation in the middle jiao disrupts spleen-stomach transportation and transformation, causing anorexia and gastric distension. Fluid retention in the lower jiao causes ankle edema and dysuria. This pattern provides the TCM rationale for considering the combination as addressing both root deficiency and branch fluid retention. Accumulating evidence suggests that Chinese herbal formulas may treat CHF by regulating multiple pathways and targets, including mitochondrial function and myocardial energy metabolism16, as well as the TGF-β17 and NF-κB18 signaling pathways.
The formula-compatibility rationale is pharmacological and TCM-theoretical. The present computational workflow did not test synergy, establish novel pharmacological effects of the combination, or compare the formula with guideline-directed medical therapy. It also did not evaluate herb-drug interactions, exposure-response relationships, or off-target toxicity. These boundaries prevent the present results from supporting treatment substitution or combination recommendations.
The present study suggests that Zhenwu Decoction combined with Wuling Powder may influence CHF-related processes through the predicted coordinated effects of multiple bioactive constituents, including β-sitosterol (BS), alisol C, benzoylnapelline, dihydrocapsaicin (DHC), and kaempferol (KAE). BS is a phytosterol widely distributed in medicinal herbs and is derived in this formula from Paeoniae Radix Alba, Zingiberis Rhizoma Recens, and Cinnamomi Ramulus19. Because its structure resembles cholesterol, BS competes with cholesterol for binding sites, reduces serum free cholesterol, and promotes lipolysis20. It also has anti-atherosclerotic, antioxidant, anti-inflammatory, and antibacterial activities21. The database record assigned dihydrocapsaicin to Zingiberis Rhizoma Recens, and previous studies22,23 support its anti-inflammatory, anti-apoptotic, and ischemia-reperfusion injury-mitigating properties. Chen YM et al.24 identified Raf-1 as a direct dihydrocapsaicin target and linked Raf-1/ASK1 complex formation to lower oxidative stress and cardiomyocyte apoptosis after acute myocardial infarction. Kaempferol is a major bioactive ingredient of Paeoniae Radix Alba. Existing studies suggest that KAE protects cardiomyocytes against excessive autophagy by upregulating the PI3K/Akt/mTOR cascade25, suppressing intracellular calcium channel protein expression26, and inhibiting the MAPK/ERK signaling pathway27. MOL002410 was identified as benzoylnapelline. The cited study of benzoylaconine28 does not experimentally support the distinct docked benzoylnapelline record. Together, these components may contribute to CHF treatment through anti-inflammatory, antioxidant, and lipid-lowering mechanisms. This supports the multi-pathway and multi-target regulatory profile of Zhenwu Decoction combined with Wuling Powder.
Processed aconite root can contain aconitine-type alkaloids, but this study did not quantify constituent exposure, dose-response relationships, or toxicity. Consequently, the predicted therapeutic network cannot be interpreted as a safety assessment, and possible off-target effects remain unresolved.
Degree ranking in the PPI network placed these five candidates at the top: AKT1, IL6, TNF, SRC, and ESR1. AKT1, a central node in the PI3K/Akt/mTOR cascade, was among the highest-degree candidates. The cascade participates in proliferation, angiogenesis, and glycolipid handling29. Wang X et al.30 detected higher AKT1 expression in heart failure rats than in healthy control mice. Lou WZ et al.31 reported that kaempferol and related ingredients suppress the PI3K/Akt pathway through the key node AKT1, thereby inhibiting cardiac fibroblast proliferation and delaying CHF progression and ventricular remodeling. IL-6 and TNF are classical inflammatory cytokines. Previous research32 has linked inflammatory cytokines and chemokines with ventricular remodeling and myocardial dysfunction across heart-failure phenotypes. In a cohort of 1,086 patients, Berger et al.33 linked higher IL-6 concentrations with adverse cardiovascular outcomes and increased NT-proBNP. TNF is closely related to angiogenesis and thrombosis, both of which contribute to cardiac and ventricular remodeling. TNF may serve as a biological marker of CHF onset34, and its overexpression is associated with adverse cardiovascular events, myocardial injury risk stratification, and prognosis. SRC is involved in cell adhesion, proliferation, and reactive oxygen species generation35. Evidence indicates that SRC overexpression amplifies beta-adrenergic receptor (β-AR) signaling, activates the β-AR/Src/ERK cascade, and mediates ventricular remodeling36. Other studies have proposed SRC as a candidate target for cardiovascular disease intervention37. Estrogen is widely recognized as a cardioprotective factor with anti-inflammatory, antioxidant, and anti-atherosclerotic properties38. ESR1, which encodes estrogen receptor alpha, is therefore a potential therapeutic target for cardiac protection. Fukuma N et al.39 clarified the cardioprotective effects of estrogen receptors by selectively blocking non-genomic estrogen receptor alpha signaling in mice. Unlike studies focused on a single compound or pathway, the present workflow cross-referenced formula-derived target coverage with a disease PPI network and myocardial transcriptomic context. This integration narrows candidate priorities, but it remains associative. The hub-gene criterion identifies highly connected candidates for follow-up rather than proving causal importance.
The shared-target KEGG profile was dominated by MAPK, PI3K-Akt, lipid/atherosclerosis, TNF, Toll-like receptor, and AGE-RAGE signaling terms. Together, these pathways map onto processes central to CHF, including hypertrophy, fibrosis, inflammation, oxidative stress, and ventricular remodeling. MAPK signaling coordinates proliferative, apoptotic, inflammatory, and fibrotic responses40. Excess MAPK activity can promote myocardial fibrosis and accelerate ventricular remodeling41 and worsen heart failure. PI3K-Akt signaling is involved in cell growth, apoptosis, migration, and angiogenesis. Its role in cytoskeletal remodeling has also made this pathway a candidate target in cancer biology42. Under physiological conditions, the PI3K-Akt pathway protects the heart by improving mitochondrial function, reducing oxidative stress, and inhibiting cardiomyocyte apoptosis. Published studies43 have reported suppressed PI3K-Akt activity in cardiomyocytes during heart failure, which may trigger mitochondrial dysfunction and impaired energy metabolism. Inhibition of this pathway can also activate profibrotic cascades such as TGF-β signaling and apoptosis-related caspase pathways, thereby promoting ventricular remodeling and cardiomyocyte loss. Dyslipidemia is linked to coronary heart disease, a frequent underlying cause of clinical heart failure. The 2024 Chinese heart-failure guideline lists both dyslipidemia and coronary heart disease among shared CHF risk factors44. It gives early lipid-lowering therapy a Class IA recommendation for prevention. Follow-up studies by Li Tingting and Zhou Li et al.45,46, involving 70 and 150 patients with heart failure, respectively, reported a progressive fall in serum HDL-C with worsening cardiac function. However, serum lipid variation was not significantly correlated with prognosis. This suggests that dyslipidemia may not directly damage cardiomyocytes or impair cardiac function. The lipid and atherosclerosis pathway may therefore be more relevant to CHF prevention and etiological interpretation than to direct myocardial injury. TNF-α is a pivotal inflammatory cytokine and a key driver of CHF initiation and progression34. Elevated TNF-α concentrations suppress myocardial contractility and are positively associated with all-cause mortality47. The sympathetic nervous system is an important neurohumoral mediator of ventricular remodeling. Excessive TNF-α upregulation can impair sympathetic nerve function, induce β-receptor dysfunction, stimulate catecholamine release48, and aggravate ventricular remodeling. Toll-like receptor pathways detect PAMPs and DAMPs and thereby initiate innate immune signaling49. Persistent activation can promote inflammation and myocardial injury. Ye S et al.50 reported that cardiomyocyte TLR2 deficiency attenuated Ang II-driven inflammation, hypertrophy, and interstitial fibrosis. The improvement coincided with weaker downstream NF-κB/MAPK activation and less myocardial injury. AGE-RAGE biology is also relevant outside diabetes. Under aging, ischemic, pressure-overload, or inflammatory cardiac stress, AGEs can accumulate and engage RAGE, amplifying oxidative stress, inflammation, and fibrosis that contribute to ventricular remodeling and CHF51. Network pharmacology captures the breadth of formula-derived component-target coverage, whereas GEO provides disease-tissue context. Their intersection is therefore useful for hypothesis prioritization in complex TCM formula research, but it should not be described as transcriptomic or pharmacological validation.
Limitations: In addition to the absence of in vitro and in vivo validation, this study used a single discovery microarray dataset and relied on database annotations and screening thresholds. Broad receptor-encompassing docking grids support exploratory ranking rather than binding-site confirmation, and exact package patch versions were not retained. In addition, pose-output PDBQT files were retained for only five HSP90AA1-compound pairs; pose-output files for the remaining 30 target-compound pairs were not retained. The GO-CC analysis used a 60-gene hit list rather than the 143-gene input used for BP/MF/KEGG; these categories were therefore not quantitatively pooled. No independent transcriptomic validation set or molecular-dynamics simulation was available.
Future directions: Future work should validate HSP90AA1, STAT1, and the prioritized compounds in cardiomyocyte hypoxia/reoxygenation models and appropriate animal models, compare the formula with guideline-directed therapies, assess herb-drug interactions and aconite-related toxicity, and test docking predictions with orthogonal biochemical or cellular assays.
In summary, integration of network pharmacology, myocardial transcriptomic data, enrichment analysis, and molecular docking prioritized candidate constituents, targets, and pathways potentially associated with Zhenwu Decoction combined with Wuling Powder in CHF. The convergence of formula-related target predictions with disease-associated expression changes identified HSP90AA1 and STAT1 as candidates for further investigation, while the docking analysis prioritized selected constituent-target pairs for experimental testing. These findings provide a hypothesis-generating framework rather than evidence of clinical efficacy or a validated molecular mechanism and require confirmation in independent experimental systems.
Disclosures
The authors report no competing interests related to this study.
Acknowledgements
Not applicable.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| AutoDock Vina | CCSB-Scripps | v1.2.6 | Command-line version used; current official release v1.2.7; configurations used CLI defaults exhaustiveness 8 and num_modes 9. https://github.com/ccsb-scripps/AutoDock-Vina/releases |
| AutoDockTools | The Scripps Research Institute | v1.5.7 | Receptor/ligand preparation; version used in analysis. https://autodock.scripps.edu/ |
| Bioconductor | Bioconductor Project | 3.16 compatibility release | R 4.2-compatible environment; current release 3.23. https://bioconductor.org/about/release-announcements/ |
| Cytoscape Desktop | Cytoscape Consortium | v3.7.1 | Network visualization/analysis version used; current release v3.10.4. https://cytoscape.org/download.html |
| DisGeNET | MedBioinformatics Solutions | v25.4 | CHF-associated gene retrieval; searched 2026-02-10. https://disgenet.com/ |
| DrugBank | OMx Personal Health Analytics | v6.0 | CHF-associated gene retrieval; searched 2026-02-12. https://go.drugbank.com/ |
| GeneCards | Weizmann Institute of Science | Web database | CHF-associated gene retrieval; searched 2026-02-10. https://www.genecards.org/ |
| GEO / GSE5406 | NCBI | GSE5406; GPL96 | RMA-normalized human left-ventricular microarray series. https://www.ncbi.nlm.nih.gov/geo/query/acc.cgi?acc=GSE5406 |
| hgu133a.db | Bioconductor | Bioconductor 3.16 environment | Affymetrix Human Genome U133A probe annotation; exact patch version not retained. https://bioconductor.org/packages/hgu133a.db/ |
| limma | Bioconductor | Bioconductor 3.16 environment | Differential-expression analysis; exact patch version not retained. https://bioconductor.org/packages/limma/ |
| MacBook | Apple | M4 processor | Local computational workstation; memory specification not retained. https://www.apple.com/mac/ |
| Metascape | Metascape | v3.5 | GO/KEGG enrichment; exact access timestamp not retained. https://metascape.org/ |
| Microsoft Excel | Microsoft | Desktop application | Data curation/export; application build not retained. https://www.microsoft.com/microsoft-365/excel |
| OMIM | Johns Hopkins University | Web database | CHF-associated gene retrieval; searched 2026-02-10. https://www.omim.org/ |
| Open Babel | Open Babel Project | Version not retained | Structure conversion in docking workflow. https://openbabel.org/ |
| PharmGKB | PharmGKB | Web database | CHF-associated gene retrieval; searched 2026-02-12. https://www.pharmgkb.org/ |
| PubChem | NCBI | Web database | SMILES and structure completion. https://pubchem.ncbi.nlm.nih.gov/ |
| PyMOL | Schrödinger | Version not retained | Protein preprocessing and pose visualization. https://www.pymol.org/ |
| R | R Foundation | 4.2.0+ | Version family recorded for analysis; current release 4.6. https://www.r-project.org/ |
| RCSB Protein Data Bank | RCSB PDB | Web archive | Protein crystal structures. https://www.rcsb.org/ |
| RStudio | Posit | 2026.04.0+526 | Analysis IDE recorded in revision note. https://posit.co/download/rstudio-desktop/ |
| STRING | STRING Consortium | Web service | Homo sapiens; confidence >0.9; release/session metadata not retained. https://string-db.org/ |
| SwissADME | SIB Swiss Institute of Bioinformatics | Web service | ADME and Lipinski-rule screening; local version not applicable. https://www.swissadme.ch/ |
| SwissTargetPrediction | SIB Swiss Institute of Bioinformatics | 2019 major update | Homo sapiens; probability >0.02; searched 2026-02-10. https://www.swisstargetprediction.ch/ |
| TCMSP | Northwest A&F University | v2.3 | Compound retrieval; searched 2026-02-07. https://tcmsp-e.com/ |
| TTD | Therapeutic Target Database | 2026 release | CHF-associated gene retrieval; searched 2026-02-12. https://ttd.idrblab.cn/ |
| UniProtKB | UniProt Consortium | Release 2026_01 | Reviewed Homo sapiens gene-symbol standardization. https://www.uniprot.org/ |
| Venny | CNB-CSIC | v2.1.0 | Target-set intersection visualization. https://bioinfogp.cnb.csic.es/tools/venny/ |
References
- McDonagh TA, et al. 2021 ESC Guidelines for the diagnosis and treatment of acute and chronic heart failure. Eur Heart J. 2021;42(36):3599-3726.
- Yang X, et al. The evolving burden of heart failure in China: a 34-year subnational analysis of trends and causes from the Global Burden of Disease Study 2023. Mil Med Res. 2025;12(1):65.
- Tang KH. Study on Zhenwu Decoction combined with Wuling Powder in the treatment of heart failure with yang deficiency and water flooding syndrome. Chin Med Guide. 2024;22(14):153-155.
- National Pharmacopoeia Commission. Pharmacopoeia of the People's Republic of China. 2025 ed. China Medical Science Press; Beijing; 2025.
- Daina A, Michielin O, Zoete V. SwissADME: a free web tool to evaluate pharmacokinetics, drug-likeness and medicinal chemistry friendliness of small molecules. Sci Rep. 2017;7:42717.
- Ru J, et al. TCMSP: a database of systems pharmacology for drug discovery from herbal medicines. J Cheminform. 2014;6:13.
- Daina A, Michielin O, Zoete V. SwissTargetPrediction: updated data and new features for efficient prediction of protein targets of small molecules. Nucleic Acids Res. 2019;47(W1):W357-W364.
- Zhou Y, et al. Metascape provides a biologist-oriented resource for the analysis of systems-level datasets. Nat Commun. 2019;10:1523.
- Hannenhalli S, et al. Transcriptional genomics associates FOX transcription factors with human heart failure. Circulation. 2006;114(12):1269-1276.
- Shahzadi Z, et al. Network pharmacology and molecular docking: combined computational approaches to explore the antihypertensive potential of Fabaceae species. Bioresour Bioprocess. 2024;11:53.
- Wang JX, Zhang S. Correlation between medication adherence, coping styles and depression in patients with chronic heart failure. J Int Psychiatry. 2026;53(1):225-228.
- National Center for Cardiovascular Diseases, Heart Failure Professional Committee of National Cardiovascular Experts Committee, Heart Failure Committee of Chinese Medical Doctor Association, et al. 2023 National guidelines for heart failure. Chin J Heart Fail Cardiomyopathies. 2023;7(4):215-311.
- Dong GJ, Wei Y. Expert consensus on TCM disease nomenclature of heart failure. Chin Arch Tradit Chin Med. 2025;43(7):253-258.
- Zhang ZJ. Treatise on Febrile Diseases. Qian CC, collator. People's Medical Publishing House; Beijing; 2005. p. 22-23.
- Zheng MH, Guo D. Research progress on active ingredients and mechanism of Zhenwu Decoction in the treatment of chronic heart failure. China J Tradit Chin Med Pharm. 2024;39(11):6007-6011.
- Chen L, Yu D, Ling S, Xu JW. Mechanism of tonifying-kidney Chinese herbal medicine in the treatment of chronic heart failure. Front Cardiovasc Med. 2022;9:988360.
- Wang Y, et al. A review of Chinese herbal medicine for the treatment of chronic heart failure. Curr Pharm Des. 2017;23(34):5115-5124.
- He Y, et al. Clinical evidence and potential mechanisms of traditional Chinese medicine for the treatment of chronic gastritis: an updated systematic review and meta-analysis. J Herb Med. 2023;42:100761.
- Wang H, et al. β-Sitosterol as a promising anticancer agent for chemoprevention and chemotherapy: mechanisms of action and future prospects. Adv Nutr. 2023;14(5):1085-1110.
- Dwivedi J, et al. Aspects of β-sitosterol's pharmacology, nutrition and analysis. Curr Pharm Biotechnol. 2025;26(14):2234-2256.
- Khan Z, et al. Multifunctional roles and pharmacological potential of β-sitosterol: emerging evidence toward clinical applications. Chem Biol Interact. 2022;365:110117.
- Jittiwat J, Suksamrarn A, Tocharus C, Tocharus J. Dihydrocapsaicin effectively mitigates cerebral ischemia-induced pathological changes in vivo, partly via antioxidant and anti-apoptotic pathways. Life Sci. 2021;283:119842.
- Lai Y, et al. Dihydrocapsaicin suppresses the STING-mediated accumulation of ROS and NLRP3 inflammasome and alleviates apoptosis after ischemia-reperfusion injury of perforator skin flap. Phytother Res. 2024;38(5):2539-2559.
- Chen Y, et al. Dihydrocapsaicin attenuates oxidative stress and apoptosis in acute myocardial infarction via promoting Raf-1/ASK1 complex formation. Phytomedicine. 2025;146:157126.
- Li YX, Liu SY. Kaempferol alleviates myocardial injury in rats with coronary heart disease via regulating the PI3K/AKT/mTOR pathway. Chin J Histochem Cytochem. 2025;34(5):439-445.
- Wu JP, Chen JJ, Yuan Q, et al. Effects and mechanisms of kaempferol on cardiomyocyte apoptosis induced by hypoxia/reoxygenation injury. Shaanxi Med J. 2024;53(1):3-7,18.
- Chen MJ, Li XD, Wang NN. Effects and mechanisms of kaempferol on cardiac function in rat models of chronic heart failure. Prog Anat Sci. 2023;29(1):18-20,24.
- Zhou WM, Lang SK, Ge X, et al. Benzoylaconine alleviates oxygen-glucose deprivation/reoxygenation-induced cardiomyocyte injury via the phosphatidylinositol 3-kinase/protein kinase B pathway. Chin J Geriatr Heart Brain Vessel Dis. 2025;27(2):211-216.
- Brand CS, Lighthouse JK, Trembley MA. Protective transcriptional mechanisms in cardiomyocytes and cardiac fibroblasts. J Mol Cell Cardiol. 2019;132:1-12.
- Wang X, Chen ZQ, Li L, et al. Effects of Zhenwu Decoction on cardiomyocyte apoptosis and PI3K-AKT pathway in heart failure rats. Chin J Comp Med. 2022;32(7):27-33,57.
- Lou WZ, Huang SS, Chen BS. Mechanism analysis of Ginkgo biloba leaves against chronic heart failure. Zhejiang Clin Med J. 2026;28(1):32-37.
- Hanna A, Frangogiannis NG. Inflammatory cytokines and chemokines as therapeutic targets in heart failure. Cardiovasc Drugs Ther. 2020;34(6):849-863.
- Berger M, et al. IL-6 and hsCRP predict cardiovascular mortality in patients with heart failure with preserved ejection fraction. ESC Heart Fail. 2024;11(6):3607-3615.
- Zhang H, Dhalla NS. The role of pro-inflammatory cytokines in the pathogenesis of cardiovascular disease. Int J Mol Sci. 2024;25(2):1082.
- Wu PL, Wei M, Zhu W. Src signaling pathway and its role in the pathophysiology of heart failure. Int J Cardiovasc Dis. 2013;40(1):6-8,15.
- Li W, et al. Src tyrosine kinase promotes cardiac remodeling induced by chronic sympathetic activation. Biosci Rep. 2023;43(10):BSR20231097.
- Zhai Y, et al. Src-family protein tyrosine kinases: a promising target for treating cardiovascular diseases. Int J Med Sci. 2021;18(5):1216-1224.
- Qian C, Liu J, Liu H. Targeting estrogen receptor signaling for treating heart failure. Heart Fail Rev. 2024;29(1):125-131.
- Fukuma N, et al. Estrogen receptor-α non-nuclear signaling confers cardioprotection and is essential to cGMP-PDE5 inhibition efficacy. JACC Basic Transl Sci. 2020;5(3):282-295.
- Sun Y, et al. Signaling pathway of MAPK/ERK in cell proliferation, differentiation, migration, senescence and apoptosis. J Recept Signal Transduct Res. 2015;35(6):600-604.
- Zhang Z, et al. Targeting MAPK-ERK/JNK pathway: a potential intervention mechanism of myocardial fibrosis in heart failure. Biomed Pharmacother. 2024;173:116413.
- Deng S, et al. PI3K/AKT signaling tips the balance of cytoskeletal forces for cancer progression. Cancers (Basel). 2022;14(7):1652.
- Ghafouri-Fard S, et al. Interplay between PI3K/AKT pathway and heart disorders. Mol Biol Rep. 2022;49(10):9767-9781.
- Cardiovascular Branch of Chinese Medical Association, Cardiovascular Physicians Branch of Chinese Medical Doctor Association, Heart Failure Professional Committee of Chinese Medical Doctor Association, et al. 2024 Chinese guidelines for the diagnosis and treatment of heart failure. Chin J Cardiovasc Dis. 2024;52(3):235-275.
- Li TT, et al. Correlations of BNP, Hcy and blood lipid levels with cardiac function and prognosis in elderly patients with chronic heart failure. Chin J Evid Based Cardiovasc Med. 2021;13(9):1050-1053.
- Zhou L. Clinical study on TCM syndrome types, blood lipid levels and cardiac function in 150 patients with chronic heart failure. Guide China Med. 2024;22(12):77-79.
- Müller-Ehmsen J, Schwinger RH. TNF and congestive heart failure: therapeutic possibilities. Expert Opin Ther Targets. 2004;8(3):203-209.
- Arvunescu AM, et al. Inflammation in heart failure—future perspectives. J Clin Med. 2023;12(24):7738.
- Yu L, Feng Z. The role of Toll-like receptor signaling in the progression of heart failure. Mediators Inflamm. 2018;2018:9874109.
- Ye S, et al. Toll-like receptor 2 signaling deficiency in cardiac cells ameliorates Ang II-induced cardiac inflammation and remodeling. Transl Res. 2021;233:62-76.
- Vianello E, et al. The advanced glycation end-products (AGE)-receptor for AGE system (RAGE): an inflammatory pathway linking obesity and cardiovascular diseases. Int J Mol Sci. 2025;26(8):3707.