This case describes synchronous glomus tumors in different fingers, with one lesion remaining asymptomatic for several years. Serial magnetic resonance imaging (MRI) revealed its prolonged silent course, while targeted imaging, surgical excision, and pathological confirmation helped distinguish the new primary lesion from local recurrence.
Case Report
Multifocal Glomus Tumors in Different Fingers with Metachronous Clinical Presentation: A Case Report
* These authors contributed equally
In This Article
Summary
Abstract
Glomus tumors are benign neoplasms arising from the glomus body. They commonly occur in the distal fingers and subungual region and typically present with severe localized paroxysmal pain, point tenderness, and cold sensitivity. Although the lesions are small, they can cause long-standing and marked pain.
An adult woman presented in 2018 with localized pain in the pulp of the left ring finger. Ultrasonography and contrast-enhanced MRI identified a small lesion, which was surgically excised and histopathologically confirmed as a glomus tumor. Importantly, the same magnetic resonance imaging (MRI) examination also demonstrated a separate enhancing lesion in the distal left index finger, although this lesion was clinically asymptomatic at that time. Approximately seven years later, the patient developed localized pain in the distal index finger. Repeat MRI demonstrated a lesion in the same anatomical region, and surgical excision followed by histopathological examination again confirmed a glomus tumor. These findings support synchronous glomus tumors in different fingers, with delayed symptomatic presentation of the index-finger lesion.
In patients with well-localized and recurrent digital pain, even when there is a history of glomus tumor, diagnosis and management should follow the principle of relocalizing a new lesion. Combined assessment with ultrasonography and contrast-enhanced MRI may improve the localization accuracy of small lesions and guide surgical strategy.
Introduction
Glomus tumors are benign neoplasms arising from the glomus body. Although they are uncommon in the overall spectrum of soft-tissue tumors, they are relatively recognizable at the fingertip, particularly in the subungual region. Their classic pain triad (paroxysmal pain, point tenderness, and cold sensitivity) provides an important diagnostic clue1. Literature reviews suggest that glomus tumors account for only a small proportion of hand tumors, but they often lead to repeated medical visits because of severe pain. However, the lesions are usually only a few millimeters in size, and local external signs are not always typical; they may therefore be mistaken for periungual inflammation, neurogenic pain, or tendon-sheath/cystic lesions, resulting in misdiagnosis and diagnostic delay1. Classic physical examinations, such as Love's pin test, the Hildreth test, and the cold sensitivity test, are useful for suggesting the diagnosis. However, when signs are atypical, or the lesion is located outside the classic subungual region, their positivity and interpretability may decrease; targeted imaging and pathological confirmation are still required to complete the diagnostic pathway1. In addition, glomus tumors can also occur outside the subungual region of the finger (extradigital/atypical locations), where clinical manifestations are more likely to be misinterpreted; greater awareness of these subtypes and their imaging localization is therefore needed2.
In terms of imaging, high-frequency ultrasonography can rapidly identify superficial millimeter-sized nodules in the outpatient setting, allow dynamic correlation with the tender point, and evaluate vascularity. Contrast-enhanced magnetic resonance imaging (MRI) is more useful for delineating lesion borders, enhancement patterns, and anatomical relationships with the nail bed, distal phalanx, and neurovascular bundles. The combination of both modalities can improve preoperative localization certainty and guide the choice of surgical approach3,4,5. Rare complications of glomus tumors, such as rupture or secondary infection, have also been reported, indicating that persistent pain or local abnormalities should be recognized early and managed appropriately4,5,6.
Case presentation:
A 23-year-old woman presented in 2018 with a 2-year history of localized stabbing pain and a small palpable mass in the pulp of the distal phalanx of the left ring finger. Ultrasonography showed a 4.3 × 2.5 mm hypoechoic subcutaneous nodule, and contrast-enhanced MRI demonstrated a 3.2 × 3.5 mm homogeneously enhancing lesion. The same MRI examination also revealed a separate enhancing nodule measuring approximately 8 × 4 mm in the distal phalanx of the left index finger (Figure 1); however, the patient had no pain or other symptoms in the index finger at that time. The symptomatic ring-finger lesion was completely excised on July 23, 2018 (Figure 2), and histopathological examination confirmed a glomus tumor.
Approximately 7 years later, the patient developed localized stabbing pain in the distal left index finger. Repeat MRI demonstrated a lesion in the same anatomical region as the asymptomatic index-finger lesion identified in 2018. On December 2, 2025 (Figure 3), the lesion was excised through a nail-bed approach, and histopathological examination again confirmed a glomus tumor (Figure 4 and Figure 5). Retrospective comparison of the 2018 and 2025 imaging indicated that the surgically treated index-finger lesion corresponded to the lesion already visible in 2018. The findings therefore supported synchronous glomus tumors in different fingers, with delayed symptomatic presentation of the index-finger lesion. At approximately 2 weeks after surgery, the incision had healed well without infection or wound complications, sensation and range of motion were preserved, and the preoperative focal pain had resolved.
Diagnosis, Assessment, and Plan:
At the first presentation, high-frequency ultrasonography showed a hypoechoic subcutaneous nodule measuring approximately 4.3 mm × 2.5 mm in the left ring finger, with a small amount of internal blood-flow signal. Contrast-enhanced MRI showed a small, round subcutaneous lesion measuring approximately 3.2 mm × 3.5 mm at the distal phalanx of the left ring finger, with obvious homogeneous enhancement. MRI also suggested a small nodular enhancing lesion measuring approximately 8 mm × 4 mm beneath the skin of the distal phalanx of the left index finger; however, the patient’s main symptoms were located in the left ring finger. Complete excision of the symptomatic ring-finger lesion and pathological examination were planned.
On November 14, 2025, repeat plain and contrast-enhanced MRI of the left hand showed a nodule at the distal phalanx of the left index finger, suggesting a possible glomus tumor. In view of the new localized pain, imaging findings, involvement of a different finger and anatomical layer, in view of the previous MRI finding in the same anatomical region of the left index finger in 2018, the 2025 lesion was considered a previously existing but clinically asymptomatic lesion that had subsequently become symptomatic, rather than a newly developed primary tumor or a recurrence of the ring-finger lesion.
Protocol
This protocol was reviewed and approved by the Human Research Ethics Committee of the First Affiliated Hospital of Zhejiang University (IIT20240869A). All procedures performed in this study complied with institutional guidelines and adhered to the principles of the Declaration of Helsinki. Written informed consent was obtained from the patient for participation and publication of clinical data and images.
1. Patient assessment and precise symptom localization
- It was confirmed that the patient had reproducible focal pain in a finger. The affected finger, anatomical location (volar, dorsal, periungual, or subungual), symptom duration, pain characteristics, cold sensitivity, previous finger surgery, trauma, infection, and relevant systemic diseases were recorded.
- The finger was inspected for nail discoloration or deformity, swelling, erythema, ulceration, drainage, and a visible or palpable mass. The affected finger was compared with the contralateral side.
- The distal phalanx was palpated systematically from proximal to distal and from radial to ulnar. The point of maximal tenderness was identified and marked with a standard skin marker. Whether the tender point was located in the pulp, periungual region, nail bed, or another anatomical layer was recorded.
- Active and passive interphalangeal joint motion, capillary refill, skin temperature, light-touch sensation, and two-point discrimination were assessed when indicated. Any neurological or vascular abnormality was documented before surgery.
- Love's pin test, the Hildreth test, and a cold sensitivity test were performed when clinically appropriate7. The same marked tender point was used for subsequent ultrasound and MRI correlation.
2. High-frequency ultrasonographic localization
- The patient was seated or positioned supine, and the hand was supported on a stable examination surface. The affected finger was kept in a comfortable neutral position, and rings or other objects that might interfere with scanning were removed.
- A routinely available ultrasound system fitted with a 12–18 MHz high-frequency linear transducer was used. A generous layer of standard ultrasound gel was applied, and the transducer was placed lightly on the skin to avoid compressing a small superficial lesion.
- The transducer was centered over the marked tender point, and scanning was performed in longitudinal and transverse planes. The examination was extended proximally and distally to assess the nail bed, flexor and extensor tendons, distal phalanx, and digital neurovascular bundles.
- The lesion was measured in three orthogonal dimensions, and its echogenicity, margins, depth from the skin or nail plate, and relationship to adjacent structures were recorded.
- Color or power Doppler was activated with a low-flow preset. A pulse repetition frequency of approximately 0.5–1.0 kHz, a wall filter of approximately 50–100 Hz, and a gain setting of approximately 60%–70% were used. Excessive transducer pressure was avoided, and the presence or absence of internal vascular signals was recorded.
- Labeled longitudinal, transverse, and Doppler images were saved. The projected center of the lesion was marked on the skin, and its distance from a fixed landmark, such as the nail edge, distal interphalangeal crease, or fingertip, was recorded.
3. Magnetic resonance imaging and operative mapping
- Dedicated MRI of the symptomatic finger or hand was performed using a routinely available 1.5 T or 3.0 T scanner and a small surface or extremity coil. The hand was immobilized with foam pads or folded towels to reduce motion.
- A small field of view of approximately 8–12 cm and a slice thickness of 2–3 mm with no gap or a gap of no more than 0.3 mm was used. Axial, coronal, and sagittal T1-weighted images and fluid-sensitive fat-suppressed images, such as fat-suppressed T2-weighted or short-tau inversion recovery images, were obtained.
- When contrast-enhanced MRI was clinically indicated, a standard gadolinium-based contrast agent was administered intravenously at 0.1 mmol/kg, and fat-suppressed T1-weighted images were obtained in at least two orthogonal planes after injection.
- The lesion was measured in three dimensions, and its signal intensity, enhancement pattern, cortical erosion or intraosseous extension, and relationships with the nail bed, distal phalanx, tendons, and neurovascular structures were documented.
- The MRI lesion was correlated with the marked tender point and ultrasound findings. Any additional imaging lesions were recorded separately and were not considered the pain-generating lesion unless they corresponded to the clinical localization.
- A direct volar approach was selected for a pulp lesion, whereas a transungual or nail-bed approach was selected for a dorsal subungual lesion. The planned incision was marked before anesthesia, and informed consent regarding the risks of nail deformity, sensory disturbance, incomplete excision, recurrence, infection, and bone involvement was documented.
4. Excision of a volar pulp lesion
- The patient's identity, affected finger, marked tender point, and imaging findings were verified. A standard digital or peripheral nerve block, with intravenous anesthesia if required, was provided according to the institutional anesthesia protocol.
- The upper limb was positioned on a standard hand table. The skin was prepared with a routinely used antiseptic solution, the hand was draped, and a standard digital or upper-arm tourniquet was applied when necessary. The tourniquet location, pressure, and duration were recorded.
- A standard hand-surgery instrument set, including a No. 15 scalpel blade, fine-toothed forceps, small scissors, mosquito forceps, small retractors, and 2.5–3.5× surgical loupes, was used. The incision was centered over the marked lesion, and layer-by-layer dissection was performed while the digital nerve branches and vessels were protected.
- The small, well-circumscribed, reddish or hemangioma-like nodule was identified. The lesion was dissected circumferentially without crushing it, and was removed completely in one piece whenever possible.
- The specimen was measured in three dimensions, photographed beside a ruler, labeled according to the anatomical site, and submitted for histopathological examination. The operative bed was inspected under magnification for residual nodular tissue.
- The wound was irrigated with 50–100 mL of sterile normal saline. The tourniquet was released, hemostasis was achieved, and capillary refill was confirmed. The skin was closed with a commonly available 5-0 or 6-0 monofilament suture, and a nonadherent dressing with sterile gauze was applied.
5. Reassessment of a previously detected or newly symptomatic lesion after glomus tumor excision
- When new focal pain occurred after previous surgery, it was determined whether the painful point was in the same finger, quadrant, and anatomical layer as the original lesion. Pain in a different finger or layer was not labeled as recurrence before a new localization assessment had been completed.
- The examination described in section 1 was repeated, and the current point of maximal tenderness was re-marked. High-frequency ultrasonography and contrast-enhanced MRI were repeated using the workflow described in sections 2 and 3.
- Current and previous imaging studies were compared to determine whether the symptomatic lesion corresponded to a previously documented lesion. A lesion already visible on earlier imaging but previously asymptomatic was classified as a pre-existing synchronous lesion with delayed clinical manifestation rather than as a newly developed metachronous tumor.
- Histopathological examination was used for final confirmation.
6. Excision of a dorsal subungual lesion with bone involvement
- The affected finger and dorsal distal-phalanx target were verified against the current MRI. A standard peripheral nerve block combined with intravenous anesthesia was provided as clinically indicated and according to the institutional anesthesia protocol.
- The upper limb was positioned on a hand table, the hand was prepared and draped, and a standard tourniquet was applied. The tourniquet location, pressure, and duration were recorded.
- A small periosteal elevator or fine hemostat from the standard hand-surgery set was used to elevate and remove the nail plate without damaging the germinal matrix. The nail plate was placed in sterile normal saline if replacement was planned.
- A longitudinal nail-bed incision was made directly over the imaging-defined lesion using a No. 15 blade. The incision was extended only as required to expose the tumor while the germinal matrix and lateral nail folds were preserved.
- The soft-tissue component was circumferentially dissected and completely excised with fine scissors and forceps. When cortical or intraosseous involvement was present, the involved bone was removed with a small curette or rongeur from the routine hand-surgery set until no gross tumor remained.
- The specimen was measured, photographed, and labeled. Soft-tissue and bony components were submitted separately when their anatomical origin needed to be distinguished. The cavity and nail bed were inspected under magnification for residual tumor.
- The wound was irrigated with 50–100 mL of sterile normal saline, and hemostasis was obtained. The nail bed was repaired with 5-0 polypropylene sutures, as documented in the case. Distal perfusion was confirmed, and a nonadherent sterile dressing was applied without excessive compression.
7. Histopathological confirmation
- The specimen was immediately placed in 10% neutral buffered formalin at a specimen-to-fixative volume ratio of at least 1:10 and was fixed for 6–24 h. If a bony component was present, it was decalcified using the pathology laboratory's routine validated decalcification method before processing.
- The specimen was processed using routine paraffin embedding, sections approximately 4 µm thick were cut, and standard hematoxylin and eosin staining was performed.
- The sections were examined for uniform round glomus cells arranged around vascular lumina, eosinophilic cytoplasm, and uniform nuclei. Margin status and bone involvement were recorded. Immunohistochemistry was used only when routine morphology was equivocal.
8. Postoperative care and outcome assessment
- Immediately after surgery, capillary refill, skin temperature, sensation, active finger motion, wound status, and pain were documented using the same pain scale that had been used before surgery.
- Routine postoperative analgesia was provided according to the institutional protocol. Antibiotics were not administered solely for an uncomplicated clean excision unless another clinical indication was present.
- The dressing was kept clean and dry. It was changed every 2–3 days, or sooner if wet or contaminated, using sterile normal saline, a nonadherent wound-contact layer, and sterile gauze.
- Before discharge, the pain score, distal perfusion, neurological status, wound condition, and any complications were recorded.
- The patient was reviewed approximately 2 weeks after surgery to assess wound healing, nail-bed repair, infection, sensory change, range of motion, and relief of the original point pain.
- Clinical follow-up was continued, and imaging was repeated only when focal pain persisted or recurred.
9. Critical quality-control points
- A sequential evidence chain of symptom localization, ultrasound, MRI, intraoperative findings, and histopathology was maintained. This evidence chain was rebuilt when pain occurred in a different finger or anatomical layer.
- Excessive ultrasound transducer pressure was avoided, and a small MRI field of view was used because both factors affected the detection of millimeter-sized lesions.
- The digital neurovascular structures and nail matrix were protected, lesion rupture was avoided, and the operative bed was inspected under magnification for residual tissue before closure.
Results
The first lesion was excised on July 23, 2018. Intraoperatively, nodular hemangioma-like tissue was identified on the volar aspect of the distal phalanx of the left ring finger. The lesion was completely removed without perioperative complications, and pathological examination confirmed a glomus tumor. The original localized pain resolved after surgery (Figure 1 and Figure 2).
The second lesion was excised on December 2, 2025. The operation lasted 45 min, estimated blood loss was approximately 2 mL, and no intraoperative complications occurred. Histological examination showed tumor cells arranged around vascular lumina, with round cells, eosinophilic cytoplasm, and uniform nuclei, confirming a glomus tumor (Figure 3, Figure 4, and Figure 5).
The patient recovered uneventfully and was discharged on December 3, 2025, with a pain score of 1. At the approximately 2-week postoperative follow-up, the incision had healed well without evidence of infection or wound complications. Sensation and range of motion of the affected finger were preserved, and the preoperative focal pain had resolved. No early postoperative complications were observed. The different affected fingers, anatomical locations, serial imaging findings, and pathological confirmation supported the presence of synchronous glomus tumors in different fingers rather than local recurrence. The index-finger lesion had already been visible on MRI in 2018 but was clinically asymptomatic at that time and became symptomatic several years later, representing a delayed or metachronous clinical manifestation of a pre-existing lesion.
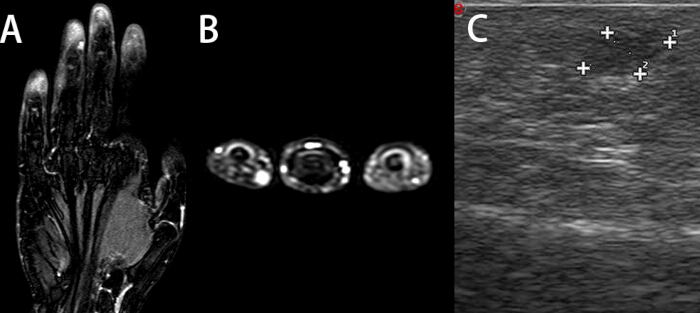
Figure 1: Imaging evaluation before the first presentation in 2018. (A,B) Contrast-enhanced MRI (coronal and axial) showed a small, round subcutaneous lesion with homogeneous enhancement at the distal phalanx of the left ring finger. (C) High-frequency ultrasonography showed a subcutaneous hypoechoic nodule in the pulp of the left ring finger, with a small amount of internal blood-flow signal. Please click here to view a larger version of this figure.
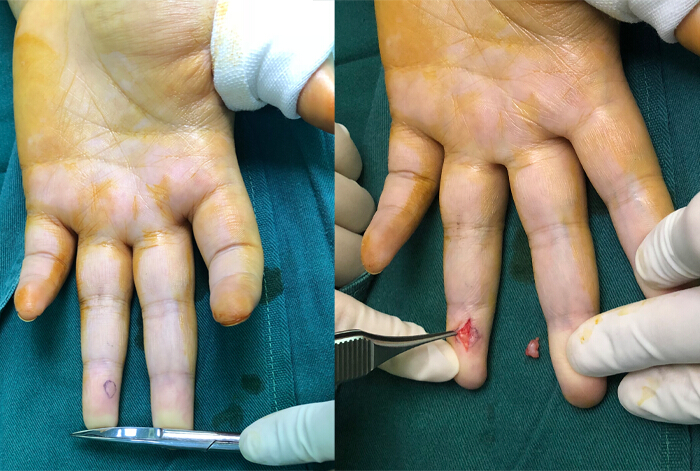
Figure 2: Intraoperative findings and specimen from the first surgery in 2018. Intraoperative exposure of the lesion in the pulp of the left ring finger revealed nodular hemangioma-like tissue (Left). Gross appearance of the completely excised specimen (Right). Please click here to view a larger version of this figure.
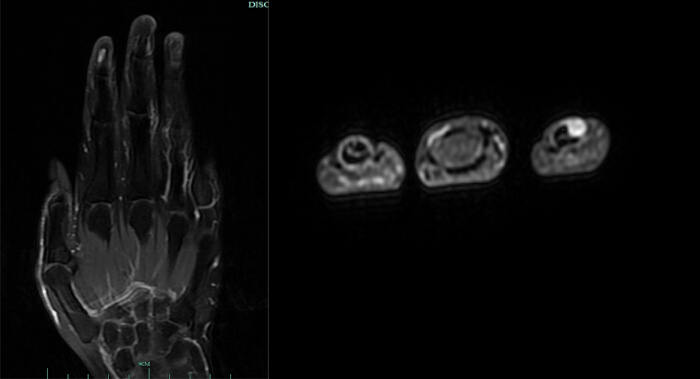
Figure 3: Imaging evaluation before the second presentation in 2025. Contrast-enhanced MRI showed a nodular enhancing lesion on the dorsal side of the distal phalanx of the left index finger, consistent with imaging features of a glomus tumor. Please click here to view a larger version of this figure.
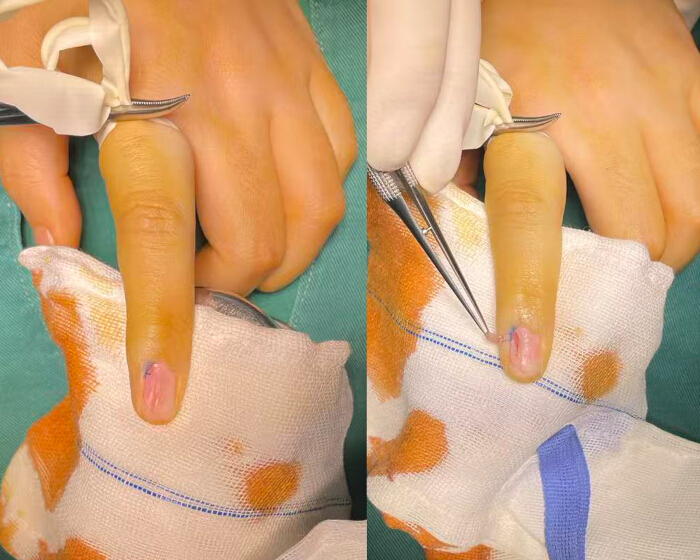
Figure 4: Intraoperative findings and specimen from the second surgery in 2025. Through nail-plate removal and a nail-bed incision approach, the tumor located on the dorsal side of the distal phalanx was exposed and excised. Please click here to view a larger version of this figure.
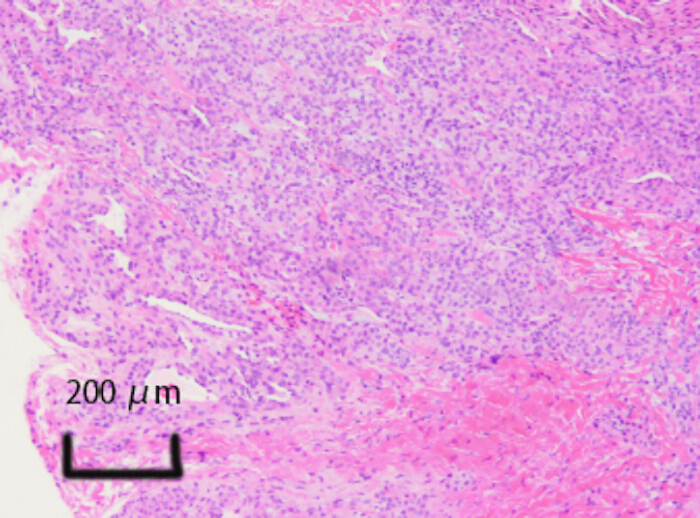
Figure 5: Pathological examination after the second surgery in 2025. Hematoxylin and eosin staining showed typical histological features of a glomus tumor: tumor cells were arranged around vascular lumina, with round cells, eosinophilic cytoplasm, and uniform nuclei. Scale bar = 200 µm. Please click here to view a larger version of this figure.
Discussion
From the perspectives of epidemiology and routine management, glomus tumors account for only a small proportion of hand tumors. However, because their pain is highly characteristic and markedly affects quality of life, they are clinically important and are often associated with misdiagnosis and diagnostic delay when the external appearance is atypical1,4. For localization, high-frequency ultrasonography is suitable for rapid outpatient screening and correlation with the tender point, whereas contrast-enhanced MRI has advantages in soft-tissue contrast, delineation of borders, enhancement characteristics, and assessment of relationships with the nail bed, distal phalanx, and neurovascular bundles. Their combined use may improve diagnostic certainty and reduce unnecessary tissue injury associated with unguided surgical exploration3.
The most important feature of this case is that the index-finger lesion was already radiologically detectable in 2018, despite being clinically asymptomatic. Retrospective comparison of the 2018 and 2025 MRI examinations showed that the lesion excised from the distal left index finger in 2025 corresponded anatomically to the enhancing nodule identified during the initial presentation. Therefore, the index-finger tumor should not be regarded as a newly developed metachronous lesion. Instead, the findings are more consistent with synchronous glomus tumors involving different fingers, with delayed symptomatic presentation of the index-finger lesion. The ring-finger lesion was symptomatic and treated in 2018, whereas the index-finger lesion remained clinically silent for several years before becoming symptomatic and requiring surgical excision in 2025.
This observation highlights an important distinction between radiological presence and clinical manifestation. A glomus tumor may be detectable on imaging before symptoms become apparent and may remain clinically silent for a prolonged period. In patients with multiple lesions identified on imaging, careful documentation of asymptomatic lesions and comparison with previous imaging are therefore important when new symptoms subsequently develop. Such a longitudinal comparison may help distinguish a pre-existing synchronous lesion from local recurrence or a genuinely newly developed tumor. In the present case, comparison of the serial MRI findings was essential for recognizing that the symptomatic index-finger lesion in 2025 represented the delayed clinical manifestation of a lesion already present in 2018. The presence of radiologically detectable lesions in more than one finger as early as 2018 also raises the possibility of an underlying multifocal predisposition. Germline loss-of-function variants in GLMN, which encodes glomulin, have been associated with inherited glomuvenous malformations and may result in multiple or multifocal lesions with variable expressivity and incomplete penetrance8,9. Although the patient reported no known family history of glomus tumors, glomuvenous malformations, or other vascular anomalies, the absence of a positive family history does not completely exclude an inherited predisposition. Genetic testing for GLMN variants was not performed in this patient. Therefore, a hereditary or multifocal predisposition cannot be definitively excluded, and the lesions should not be assumed to represent two completely independent sporadic primary tumors.
Regarding imaging, ultrasonography and MRI have complementary advantages and limitations in diagnosing glomus tumors. Ultrasonography is sensitive for superficial small lesions and can be correlated with the tender point in real time, but its performance is influenced by operator experience as well as lesion depth and location. Contrast-enhanced MRI can more consistently show lesion extent and enhancement characteristics; however, false-negative MRI findings may occur, especially when the lesion is atypically located or when the scanning field does not match the pain localization3,10,11.
The second lesion was located in the dorsal distal subungual region of the index finger, an area in which both appearance traps and site traps are common. The appearance trap is that subungual glomus tumors are not always accompanied by typical nail discoloration or visible elevation; the site trap is that the pain may be localized to the periungual or dorsal region and may be misinterpreted as paronychia, periungual soft-tissue inflammation, or a periarticular problem. In this scenario, reproducible point tenderness and cold sensitivity should be regarded as important clinical cues for targeted imaging, and the complementary strengths of ultrasonography and contrast-enhanced MRI should be used whenever possible to improve localization certainty1,3,6.
From the perspective of limb and hand tumor differential diagnosis, painful digital nodules require systematic evaluation, particularly when the location is atypical or physical signs are subtle. Osseous lesions of the distal phalanx, such as enchondroma, can also cause fingertip symptoms and need to be distinguished from soft-tissue tumors; this highlights the need to assess cortical bone, medullary cavity changes, and relationships with surrounding soft tissues, and to complete the diagnostic loop by pathological confirmation when necessary12. In addition, glomus tumors can occur in rarer anatomical layers; for example, cases arising within digital nerve fascicles and presenting with multifocal distribution suggest that such tumors may have a close anatomical relationship with nerve fascicles, further emphasizing the importance of preoperative layer assessment and intraoperative protection of critical structures1,4,13.
Disclosures
The authors have nothing to disclose and declare no competing interests.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 0.9% sodium chloride irrigation, USP, 1000 mL | Baxter Healthcare Corporation, Deerfield, IL, USA | 2B7124X | Sterile saline used for intraoperative wound irrigation. |
| 10% neutral buffered formalin | Sigma-Aldrich, Merck KGaA, Darmstadt, Germany | HT501128-4L | General-purpose histological fixative used for excised tumor specimens. |
| 3.0 T magnetic resonance imaging system | Siemens Healthineers, Erlangen, Germany | MAGNETOM Vida | Used for small-field-of-view MRI of the symptomatic hand or finger. |
| Adaptic non-adhering dressing, 7.6 × 7.6 cm | 3M, St. Paul, MN, USA | 2012 | Nonadherent wound-contact layer applied over the repaired skin or nail bed. |
| BD ChloraPrep Clear 10.5 mL applicator | Becton, Dickinson and Company, Franklin Lakes, NJ, USA | 930700 | Single-use preoperative skin preparation applicator used before surgical incision. |
| Diagnostic ultrasound system | GE HealthCare, USA | LOGIQ E10s | Used for high-resolution grayscale and color Doppler examination of the symptomatic finger. |
| Eosin Y solution, aqueous, 0.5%, 500 mL | Sigma-Aldrich, Merck KGaA, Darmstadt, Germany | HT110216-500ML | Cytoplasmic counterstain used for routine hematoxylin and eosin staining. |
| Gadavist (gadobutrol) injection, 1 mmol/mL | Bayer HealthCare Pharmaceuticals Inc., Whippany, NJ, USA | A9585 | Gadolinium-based contrast agent used for contrast-enhanced MRI; A9585 is the commonly used product/billing identifier and the package code varies by market. |
| High-frequency linear ultrasound transducer | GE HealthCare, USA | ML6-15-D | Used for superficial imaging and localization of millimeter-sized digital lesions. |
| HistoCore BIOCUT manual rotary microtome | Leica Biosystems, Nussloch, Germany | 149BIO000C1 | Used to cut approximately 4-µm paraffin sections. |
| Mayer's hematoxylin solution, 1 L | Sigma-Aldrich, Merck KGaA, Darmstadt, Germany | MHS32-1L | Progressive nuclear stain used for routine hematoxylin and eosin staining. |
| No. 15 sterile stainless-steel scalpel blade | Swann-Morton Ltd., Sheffield, UK | 0305 | Used for precise skin and nail-bed incisions. |
| Paraplast Plus paraffin | Leica Biosystems, Nussloch, Germany | 39602004 | Used for routine tissue infiltration and paraffin embedding. |
| Prolene polypropylene suture, 5-0, blue | Ethicon, Inc., Raritan, NJ, USA | 8556H | Nonabsorbable monofilament suture used for fine wound or nail-bed repair. |
| Sterile Aquasonic 100 ultrasound gel, 20 g | Parker Laboratories, Inc., Fairfield, NJ, USA | 01-01 | Sterile, single-use ultrasound transmission gel used for diagnostic ultrasonography. |
| Sterile nonwoven gauze sponge, 4 × 4 inch, 4-ply | Medline Industries, LP, Northfield, IL, USA | NON21444 | Used as an outer sterile dressing and for routine wound care. |
| Sterile surgical skin marker | Viscot Medical, LLC, USA | 1400 | Used to mark the point of maximal tenderness and the projected lesion center before imaging or surgery. |
References
- Hazani R, Houle JM, Kasdan ML, Wilhelmi BJ. Glomus tumors of the hand. Eplasty. 2008;8:e48.
- Takei TR, Nalebuff EA. Extradigital glomus tumour. J Hand Surg Br. 1995;20(3):409-12.
- Chen L, et al. Diagnosis of subungual glomus tumors with 18 MHz ultrasound and CDFI. Sci Rep. 2020;10(1):17848.
- Wang H, et al. Ten years' experience with diagnosis and treatment of non-subungual glomus tumor in the fingers. Technol Cancer Res Treat. 2024;23:15330338241287087.
- Maxwell GP, Curtis RM, Wilgis EF. Multiple digital glomus tumors. J Hand Surg Am. 1979;4(4):363-7.
- Lu H, Chen LF, Chen Q. Rupture of a subungual glomus tumor of the finger. BMC Cancer. 2018;18(1):505.
- Bhaskaranand K, Navadgi BC. Glomus tumour of the hand. J Hand Surg Br. 2002;27(3):229-31.
- Brouillard P, et al. Mutations in a novel factor, glomulin, are responsible for glomuvenous malformations ("glomangiomas"). Am J Hum Genet. 2002;70(4):866-74.
- Brouillard P, et al. Four common glomulin mutations cause two thirds of glomuvenous malformations ("familial glomangiomas"): evidence for a founder effect. J Med Genet. 2005;42(2):e13.
- Dahlin LB, Besjakov J, Veress B. A glomus tumour: classic signs without magnetic resonance imaging findings. Scand J Plast Reconstr Surg Hand Surg. 2005;39(2):123-5.
- Trehan SK, et al. Characteristics of glomus tumors in the hand not diagnosed on magnetic resonance imaging. J Hand Surg Am. 2015;40(3):542-5.
- Lu H, Chen Q, Yang H, Shen H. Enchondroma in the distal phalanx of the finger: an observational study of 34 cases in a single institution. Medicine (Baltimore). 2016;95(38):e4966.
- Wang Y, Lu H. Multiple intraneural glomus tumors in different digital nerve fascicles. BMC Cancer. 2019;19(1):888.