This case report describes a 6-week seated modified Liuzijue training program in a stroke patient with respiratory impairment. Changes were observed in pulmonary function and quality-of-life outcomes, and routine laboratory monitoring showed abnormalities in some parameters without clinical symptoms. However, these uncontrolled single-case findings require confirmation in controlled studies.
تقرير حالة
Seated Modified Liuzijue Training for Rehabilitation of a Patient with Respiratory Impairment During the Recovery Phase of Stroke: A Case Report
* These authors contributed equally
في هذه المقالة
ملخص
الملخص
Patients in the recovery phase after stroke may present with respiratory impairment and abnormal breathing patterns, which can limit exercise tolerance and affect quality of life. This case report describes a 6-week seated modified Liuzijue breathing training program implemented in a patient with respiratory impairment during the recovery phase of stroke. Considering the patient’s post-stroke motor dysfunction and balance limitations, the traditional standing Liuzijue protocol was adapted to a seated format, with simplified upper-limb movements and individualized breathing rhythm. The patient completed the 6-week training program in conjunction with conventional rehabilitation. Pre- and post-intervention assessments included pulmonary function parameters, respiratory-related quality of life, general health-related quality of life, and routine laboratory monitoring. After the intervention, tidal volume (TV), vital capacity (VC), and forced vital capacity (FVC) increased relative to baseline. The post-intervention changes in St George’s Respiratory Questionnaire (SGRQ) and 36-Item Short Form Health Survey (SF-36) scores suggested an improvement in the patient’s perceived respiratory-related and overall quality of life. This case primarily demonstrates that a seated modified Liuzijue protocol was feasible to implement and was well tolerated throughout the 6-week intervention in this individual patient, without clinically relevant training‑related adverse events. However, because this was an uncontrolled single-case observation conducted during the stroke recovery phase and the patient received concurrent conventional rehabilitation, the observed pre-post changes cannot be attributed specifically to seated modified Liuzijue. These findings should be regarded as preliminary evidence of procedural feasibility and clinical changes that warrant confirmation in controlled studies with larger samples and direct physiological measurements.
المقدمة
Stroke is the second leading cause of death and the third leading cause of disability worldwide1. Respiratory muscle dysfunction is a common complication after stroke. Some patients suffer from reduced strength and atrophy of respiratory muscles, raising the incidence of pulmonary infection and mortality risk2. Studies have verified that breathing training effectively improves respiratory muscle strength and core pulmonary function in patients with stroke during the recovery phase and significantly enhances activities of daily living and quality of life3. Therefore, targeted respiratory rehabilitation training bears important clinical value. Conventional breathing training mainly consists of simple diaphragmatic breathing, pursed‑lip breathing, and respiratory muscle resistance training. Although it can improve pulmonary function indicators to a certain extent, it has limitations, including monotonous training patterns, insufficient engagement, and poor patient adherence. Furthermore, such training mostly focuses merely on respiratory function improvement, lacking comprehensive regulation of patients’ physical and mental status, limb movements, and overall quality of life4,5. Therefore, it is of great significance to explore a distinctive respiratory-rehabilitation protocol that is safe, effective, and associated with good patient adherence, and can address both local respiratory function and holistic physical-mental rehabilitation.
Liuzijue is a characteristic rehabilitation exercise integrating breathing and limb movements6. Combining diaphragmatic breathing and pursed-lip breathing, Liuzijue training coordinates gentle upper-limb movements with phonatory exhalation. It is easy to operate and matches the rehabilitation demands of patients in the stroke recovery phase7. However, Liuzijue differs from conventional breathing training. Centered on phonatory exhalation, Liuzijue emphasizes respiratory rhythm and exhalation modulation to achieve breathing characterized by “subtlety, depth, prolongation, and evenness.” It combines prolonged exhalation with physical adjustment, mental regulation, and guided limb movements. By contrast, conventional breathing training mostly focuses on simple diaphragmatic‑movement exercises8. Previous studies suggest that the sustained gentle airflow and coordinated movements used in Liuzijue may contribute to respiratory muscle engagement and may also help alleviate negative emotional states such as anxiety and depression9,10.
This case report describes one patient with post-stroke respiratory impairment who underwent a 6-week specialized respiratory rehabilitation program using seated modified Liuzijue. By documenting changes in pulmonary function parameters and patient-reported quality-of-life measures before and after the intervention, this case was intended to explore the clinical feasibility of the seated modified Liuzijue program and to describe the associated short-term changes observed during rehabilitation.
This seated modified Liuzijue may be considered for stroke patients in the recovery phase who are able to maintain a seated position independently or with limited caregiver assistance and who can tolerate low-intensity guided breathing and phonatory-exhalation training. It may not be appropriate for patients with severe cardiopulmonary disease, marked limb spasticity, impaired consciousness, or inability to cooperate with the breathing and phonation instructions. Given the single-case design, these considerations should be regarded as practical conditions derived from this case rather than formal eligibility criteria for broader clinical application. The present case primarily aimed to document the feasibility and short-term tolerability of seated modified Liuzijue and to provide a preliminary clinical reference for individualized traditional Chinese medicine-based rehabilitation during the stroke recovery phase.
Case Presentation
A 54-year-old male experienced acute-onset right-sided limb weakness and gait instability without obvious precipitating factors on 23 June 2023. He presented with a left-deviating gait requiring physical assistance for ambulation, accompanied by dizziness, nausea, vomiting of coffee-ground gastric contents, transient confusion, and conjugate left-eye deviation. Peripheral oxygen saturation decreased in the emergency department, and oxygen therapy was administered. The patient had a 5-year history of hypertension with regular antihypertensive medication, and type 2 diabetes mellitus was newly diagnosed during this illness episode.
Emergency cranial computed tomography (CT) ruled out intracranial hemorrhage. He was admitted to the Neurology Department with a provisional diagnosis of cerebral infarction and received comprehensive medical treatment, including infection control, blood pressure management, fluid resuscitation, and bowel care. Following treatment, the patient’s condition gradually stabilized, yet residual motor dysfunction of the right-sided limbs persisted. He was subsequently transferred to the Rehabilitation Department for further rehabilitative intervention.
On admission to the Rehabilitation Department, his body temperature was 36.3 °C and blood pressure was 105/80 mmHg. He was conscious, with intact orientation and appropriate verbal responses. The thorax was symmetrical, percussion revealed bilateral resonant notes, and breath sounds were clear without obvious rales. Cardiac rhythm was regular, and abdominal examination was unremarkable. Neurological examination demonstrated right-sided limb muscle strength of approximately 4/5, with positive Babinski and Chaddock signs bilaterally. Bedside clinical observation showed that the patient could maintain an independent seated position, whereas standing stability remained limited.
Diagnosis, Assessment, and Plan
To characterize the intracranial lesions and assess cerebrovascular pathology, cranial CT, brain magnetic resonance imaging (MRI), and computed tomography angiography (CTA) of the brain and neck were performed on 23 June 2023. Cranial CT revealed multiple lacunar infarcts in the bilateral basal ganglia and centrum semiovale, together with periventricular ischemic white matter changes and cerebral atrophy (Figure 1A). Brain MRI further demonstrated an acute lacunar infarction in the left medulla, as well as multiple lacunar infarcts in the bilateral basal ganglia and centrum semiovale. Brain and neck CTA showed cerebral atherosclerosis and focal stenosis of the left posterior cerebral artery, with compensatory enlargement of the left posterior communicating artery (Figure 1B).
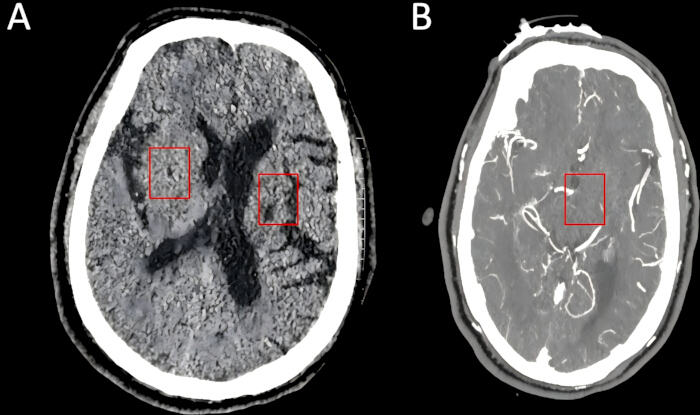
Figure 1: Cranial imaging findings. (A) Cranial computed tomography showing multiple lacunar infarcts in the bilateral basal ganglia and centrum semiovale, with periventricular ischemic white-matter changes and cerebral atrophy. The red boxes indicate representative lacunar infarcts. (B) Cranial computed tomography angiography showing focal stenosis of the left posterior cerebral artery, indicated by the red box. Please click here to view a larger version of this figure.
A differential diagnostic evaluation was performed to exclude other causes of unilateral limb weakness, including intracerebral hemorrhage, intracranial space-occupying lesions, and spinal cord pathology. Based on the clinical manifestations, upper motor neuron signs, and characteristic neuroimaging findings, the patient was diagnosed with ischemic stroke and incomplete hemiparesis.
After his clinical condition stabilized, the patient was transferred from the Neurology Department to the Rehabilitation Department on 11 July 2023, and conventional rehabilitation therapy was initiated on the following day, including motor training, gait training, and swallowing rehabilitation.
During rehabilitation, the patient continued to receive standard secondary‑prevention and medical management for stroke, including antiplatelet, lipid-modifying, gastroprotective, neurotrophic, antihypertensive, and glucose-lowering agents, specifically aspirin enteric-coated tablet (dose not documented), rosuvastatin calcium tablet (dose not documented), rabeprazole sodium enteric-coated tablet (dose not documented), rebamipide (dose not documented), citicoline sodium tablet (dose not documented), mecobalamin tablet (dose not documented), telmisartan 40 mg orally once daily, amlodipine 5 mg orally once daily, and insulin glargine (pre-filled pen) 22 international units subcutaneously once daily. Routine nutritional therapy was also provided throughout the rehabilitation stay.
Concurrently with conventional rehabilitation, a 6-week seated modified Liuzijue breathing training protocol was implemented on 17 July 2023. Baseline assessments, including routine blood and biochemical parameters, pulmonary function tests, and health-related quality of life questionnaires, were completed immediately before the intervention began. The intervention was delivered five days per week for six consecutive weeks and was completed on 25 August 2023. All outcome measures were initially assessed within 3 days after completion of the intervention. Selected outcome parameters were additionally reassessed within several days after the initial post-intervention assessment. Throughout training, the patient maintained an independent seated position, with family caregivers providing only backup postural support when needed.
During the rehabilitation course, the patient’s functional status gradually improved. He initially walked slowly with a walking aid and subsequently could take a few steps without assistance. Right-sided limb strength remained approximately 4/5, and swallowing dysfunction persisted. The clinical timeline is shown in Figure 2.
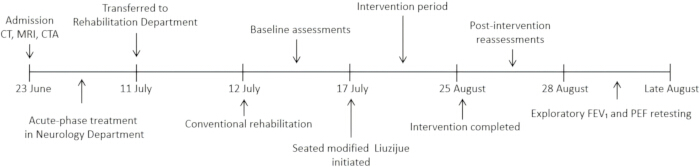
Figure 2: Clinical timeline of the case. The timeline summarizes admission and neuroimaging on 23 June 2023, acute-phase treatment, transfer to the Rehabilitation Department, initiation of conventional rehabilitation, baseline assessments, the 6-week seated modified Liuzijue intervention, post-intervention reassessment, and exploratory retesting. Abbreviations: CT = computed tomography; MRI = magnetic resonance imaging; CTA = computed tomography angiography; FEV₁ = forced expiratory volume in 1 s; PEF = peak expiratory flow. Please click here to view a larger version of this figure.
البروتوكول
The intervention protocol for this case was reviewed and approved by the Medical Ethics Committee of Nanping First Hospital (ethics approval No. NPSY202209002; project No. 2023J011858). Written informed consent was obtained from the patient and family members prior to the intervention. They agreed that medical records, rehabilitation training logs, pulmonary function test data, and relevant imaging materials could be used for publication in a case report. All clinical data were de-identified to protect patient privacy.
Details of the equipment, consumables, and assessment instruments used in this study are provided in the Table of Materials.
1. Intervention implementation conditions
- Scheduling
The seated modified Liuzijue training was scheduled from Monday to Friday for six consecutive weeks, with two sessions per day, one in the morning and one in the afternoon. A therapist provided one-to-one supervision throughout all training sessions. The therapist avoided scheduling training immediately after a heavy meal, and all training sessions were performed 1–2 h after meals. If the patient experienced acute physical discomfort, such as marked fatigue, dizziness, or chest discomfort, the therapist rescheduled training to another time.
In each training session, the patient completed six sets of seated modified Liuzijue exercises. One set consisted of sequential performance of the six phonatory exercises in the fixed order: Xu-He‑Hu-Si-Chui-Xi. Each sound was performed once within one set; accordingly, each phonatory movement was executed six times in a single training session. After each phonatory expiration, the therapist allowed the patient to complete 1–2 spontaneous respiratory cycles before proceeding to the next sound. Upon finishing one full set, the therapist instructed the patient to rest in a seated position for 30 s. The therapist extended the rest period as needed until the patient’s respiratory rhythm returned to a comfortable and stable state. - Training environment
The patient underwent the training in a quiet, spacious, and well-ventilated therapy room. This was to ensure that the patient could clearly hear the verbal instructions given by the therapist and had sufficient space to carry out the movements. - Equipment preparation
The therapist prepared a stable chair with an appropriate height, which allowed the patient to maintain an upright seated position with both feet placed flat on the floor. The therapist also assembled all monitoring and timing equipment, including an automated sphygmomanometer for blood‑pressure measurement, a fingertip pulse oximeter to monitor peripheral oxygen saturation (SpO₂) and heart rate, and a timer for observing inspiratory and expiratory duration. The therapist ensured that the patient wore loose-fitting clothing without constriction around the neck, chest, and abdomen, so as not to restrict thoracic and abdominal movements. - Training personnel
- Therapist
The therapist provided one-on-one guidance to the patient, using unified verbal instructions to explain and demonstrate in detail the essential movement techniques, breathing rhythm, and pronunciation methods of the Liuzijue training. During the training process, the therapist needed to observe the patient's movement performance in real time and promptly correct any incorrect postures. In addition, the therapist had to closely monitor the patient's physical condition, including physiological indicators such as facial color, breathing rhythm, and heart rate. This was done to promptly detect any potential fatigue or discomfort, and to adjust the training intensity or pause the training based on the actual situation, thereby ensuring the patient's safety. - Family caregiver
The patient was able to maintain an independent seated position throughout training. Family‑caregiver assistance was available only as backup: if the patient drifted out of proper sitting alignment, the caregiver offered minor postural support to help maintain an upright, relaxed trunk and shoulder position, so as to prevent falls and guarantee the patient’s safety during the whole training process.
- Therapist
- Pre-training safety assessment for each session
Before each formal training session, the therapist allowed the patient to rest adequately in a seated position until spontaneous breathing became stable. The therapist evaluated the patient’s facial color, level of consciousness, heart rate, and respiratory rhythm, and asked the patient about subjective symptoms, including dizziness, chest tightness, dyspnea, palpitations, and excessive fatigue. The therapist measured and documented the patient’s blood pressure, respiratory rate, SpO₂, and heart rate.
The therapist initiated each training session only when the patient remained clinically stable and reported no obvious respiratory or systemic discomfort. If the patient developed marked fatigue, abnormal breathing, dizziness, chest discomfort, or other clinically significant symptoms before training, the therapist either postponed the session or reduced the training intensity based on clinical judgment.
2. Practical procedure of the seated modified Liuzijue
Traditional Liuzijue is generally performed in a standing position and combines six phonated expiratory sounds with coordinated whole-body and upper-limb movements. Considering the patient’s impaired postural control, right-sided limb weakness, reduced exercise tolerance, and risk of losing balance after stroke, the traditional protocol was modified to improve safety and feasibility. First, all exercises were performed in a seated position instead of standing. Second, complex upper-limb movements were simplified, and a Bobath hand clasp was used when bilateral upper-limb movement was required to facilitate participation of the affected limb. The original sequence of the six sounds—“Xu”, “He”, “Hu”, “Si”, “Chui”, and "Xi”—was retained.
- Pre-training preparation
- Patient positioning
The patient was assisted into an upright seated position on a stable chair. The trunk was maintained as vertically as possible, both shoulders were relaxed, and both feet were placed flat on the floor approximately shoulder-width apart. When the patient was unable to maintain an upright sitting posture independently, a family caregiver provided light support to stabilize the trunk without restricting thoracic movement. - Breathing preparation
Before formal training, the therapist instructed the patient to breathe naturally and quietly. Formal training was started after the breathing rhythm became stable and the patient reported no obvious dizziness, chest tightness, shortness of breath, or excessive fatigue.
- Patient positioning
- Formal training
- Starting posture
The patient maintained an upright sitting position with both feet flat on the floor and approximately shoulder-width apart. The shoulders and upper limbs were relaxed, and natural breathing was maintained before beginning the first sound.
The therapist stood beside the patient throughout the procedure and provided standardized verbal cues for inhalation, expiration, phonation, and upper-limb movement. - “Xu” sound
The patient placed both hands in a Bobath hand clasp in front of the chest. After a comfortable inhalation through the nose, the patient slowly exhaled while continuously producing the sound “Xu”.
Expiration was performed gently and continuously without forced expiration. The phonation ended when a comfortable expiration was completed. - “He” sound
The patient raised both hands, maintained in a Bobath hand clasp, to approximately chest level during inhalation. During expiration, the patient slowly lowered the upper limbs while continuously producing the sound “He”.
The therapist ensured that the movement remained slow and within the patient’s comfortable range and avoided excessive shoulder elevation or compensatory trunk movement. - “Hu” sound
The patient placed both hands lightly at the sides of the waist. After natural inhalation, the patient slowly exhaled while continuously producing the sound “Hu”.
The patient was instructed to maintain an upright trunk and relaxed shoulders throughout the expiration and to avoid forcefully and rapidly emptying the lungs. - “Si” sound
During inhalation, the patient raised both hands in a Bobath hand clasp to approximately chest level. During expiration, the patient slowly lowered the hands toward the abdomen while continuously producing the sound “Si”.
When excessive trunk flexion, shoulder compensation, or rapid expiration was observed, the therapist corrected the patient’s posture or breathing pattern. - “Chui” sound
The patient placed both hands lightly over the lower back. After a comfortable inhalation, the patient slowly exhaled while continuously producing the sound “Chui”.
The phonation was maintained throughout comfortable expiration without breath-holding or forceful expiratory effort. - “Xi” sound
The patient raised both hands with the palms facing upward to approximately chest level during inhalation. During expiration, the patient slowly lowered the hands toward the lower abdomen while continuously producing the sound “Xi”.
After completing the expiration, the patient returned both upper limbs to a relaxed position and resumed natural breathing.
- Starting posture
- Respiratory rhythm and standardized inspiratory-expiratory ratio parameters
The seated modified Liuzijue training adopted a slow and comfortable breathing pattern individualized according to the patient’s respiratory function and exercise tolerance. Nasal inspiration was maintained for approximately 3–4 s, followed by gentle and continuous phonatory expiration lasting approximately 6–8 s, with an inspiratory-to-expiratory ratio of approximately 1:2. A breathing pattern of approximately 3 s of inspiration followed by 6 s of phonatory expiration was used as the primary training rhythm. The expiratory duration could be gradually prolonged to 7–8 s when the patient demonstrated good tolerance without dizziness, chest tightness, dyspnea, obvious fatigue, or disruption of the breathing rhythm. The patient was not required to achieve the target duration by breath-holding, maximal inspiration, or forceful expiration. - Monitoring during training
Throughout each training session, the therapist continuously observed the patient’s condition. Monitoring items included facial color, level of consciousness, respiratory rhythm, continuity of phonation, and heart rate. The therapist also assessed trunk‑shoulder compensatory movements, movement execution quality, and the patient’s subjective level of fatigue.
The therapist actively asked the patient about the presence of dizziness, chest tightness, palpitations, dyspnea, limb soreness, and other discomforts. Once the therapist detected disrupted respiratory rhythm, markedly increased work of breathing, or substantial subjective fatigue in the patient, the therapist immediately stopped the current phonatory exercise and guided the patient to resume natural breathing. Training was resumed only after the patient’s respiratory rhythm and general physical condition returned to stability. - Post‑training observation
Upon completion of a single training session, the therapist instructed the patient to remain seated and maintain natural breathing until the breathing pattern roughly returned to the pre‑training level. The therapist re‑evaluated the patient’s heart rate and respiratory rhythm, re‑measured SpO2, and inquired about discomforts such as dizziness, chest tightness, palpitations, dyspnea, limb soreness, and excessive fatigue. The therapist regarded the session as completed only when the patient was clinically stable and free of obvious discomfort.
The therapist kept detailed training records, which covered the training date, actual number of completed sets, instances of training interruption, all reported symptoms, adverse events, and every adjustment made to training intensity. The on-site training procedure is shown in Figure 3.

Figure 3: Seated modified Liuzijue training. The therapist demonstrated the seated modified Liuzijue movements while the patient performed the exercise under supervision. A family caregiver provided backup postural support. Faces were obscured to protect participant privacy. Please click here to view a larger version of this figure.
3. Criteria for terminating training
Predefined criteria for early withdrawal from the intervention were established. The rehabilitation training was terminated if any of the following occurred.
- Termination due to training-related discomfort
Training was to be terminated if the patient developed dizziness, chest tightness, palpitations, or other discomfort during training and the symptoms did not resolve after 30 min of rest. - Termination due to severe complications
The intervention was to be discontinued if a serious complication occurred, including severe pneumonia, recurrent stroke, septic shock, or severe arrhythmia. - Termination due to poor adherence
The patient was to be withdrawn if the patient or family demonstrated poor adherence or refused to continue the rehabilitation program.
4. Pulmonary function testing (PFT)
PFT is widely regarded as a standard clinical method for evaluating ventilatory function, identifying ventilatory dysfunction, and assessing the effectiveness of respiratory rehabilitation interventions. It can objectively quantify maximal lung expansion capacity, airway patency, and changes in breathing patterns, and is widely used for disease severity grading and treatment response monitoring in respiratory diseases11.
TV refers to the total volume of air inhaled or exhaled in each breath during quiet breathing. VC reflects the total volume of air the lungs can hold and expel without limitation by expiratory speed. FVC is the total volume of air that can be exhaled as forcefully and as rapidly as possible after maximal inspiration. Forced expiratory volume in 1 s (FEV₁) is the volume of air exhaled in the first second of a forced expiratory maneuver after maximal inspiration. Peak expiratory flow (PEF) is the highest instantaneous airflow achieved during a rapid, forceful exhalation after deep inspiration12.
PFT was initially performed at two prespecified time points: before the intervention and on the day after completion of the six-week intervention. Measurements were performed using the spirometer module integrated into the cardiopulmonary exercise testing system. The spirometer module was used to measure routine static and forced ventilatory parameters, including TV, VC, FVC, FEV₁, and PEF. Because FEV₁ and PEF were lower at the initial post-intervention assessment, these two parameters were additionally reassessed within several days after the initial post-intervention assessment using the same equipment, testing procedure, and quality-control criteria. This exploratory retest was not a prespecified endpoint in the original protocol. In addition to the measured values, the corresponding predicted values and percentages of predicted values (% predicted) were recorded. Predicted values were automatically generated by the PFT system using the reference equations incorporated into the device software, based on the patient’s demographic characteristics, including sex, age, and height.
Before each testing session, the investigators inspected and calibrated the spirometer module in accordance with the manufacturer’s operating instructions. Formal testing commenced only after the calibration results fell within the permissible range specified by the manufacturer.
Prior to formal testing, the patient sat quietly for approximately 5 min. Testing started after the patient’s spontaneous respiratory rhythm became largely stable. During testing, the patient wore a nose clip to prevent nasal air leakage and tightly sealed the disposable mouthpiece connected to the spirometer module with both lips.
For TV measurement, the investigators instructed the patient to maintain calm and natural breathing through the mouthpiece. TV data were recorded once the breathing rhythm stabilized. For VC measurement, the investigators guided the patient to inhale fully to the maximal inspiratory level, and then exhale slowly, continuously and as completely as possible following prompts from the test operator and the device.
For measurements of FVC, FEV₁ and PEF, the investigators first instructed the patient to take a full inspiration close to total lung capacity. Immediately afterward, the patient exhaled as rapidly, forcefully and completely as possible until no further gas could be expelled. The same test operator provided standardized verbal encouragement and movement guidance throughout the whole procedure.
The investigators obtained at least three technically acceptable expiratory maneuvers. A 10–20 s rest interval was provided between maneuvers, and the operator extended the rest period according to the patient’s condition. The test was repeated if quality-compromising events occurred, such as coughing, air leakage around the mouthpiece, insufficient inspiration, premature termination of expiration, or other technical artifacts. The best‑quality value that met quality‑control criteria was selected for final analysis.
5. St George’s Respiratory Questionnaire
The SGRQ is a standardized self-reported questionnaire used to assess health impairment and perceived quality of life in patients with airway diseases. It consists of 76 items covering three subscales: symptoms, activity, and impacts on daily life13.
In this study, all questionnaire contents were verbally described by the patient and filled out by his family members to ensure accurate and complete data collection. All responses were scored strictly in accordance with the standard scoring instructions of the scale. Subscale scores and the total score were calculated via the weighted scoring algorithm, with higher scores representing poorer health status and more severe impairment of health-related quality of life. Questionnaires with missing or invalid responses were processed following the official scoring manual. The patient completed the questionnaire assessment at two time points: before and after the intervention.
6. 36-Item Short Form Health Survey
The SF-36 is a health-status questionnaire comprising eight domains: physical functioning, social functioning, role physical, bodily pain, mental health, role emotional, vitality, and general health14.
Consistent with the SGRQ assessment, the patient verbally described his health status, and family members assisted in recording the responses. Each domain score was calculated according to the standard SF-36 scoring procedure. Raw item scores were recoded as required and linearly converted to a scale of 0–100 for each domain; higher scores indicated better health-related quality of life. Missing data were handled according to the official SF-36 scoring guidelines. The SF-36 was administered before and after the intervention.
7. Complete blood count (CBC) and serum biochemical tests
CBC and serum biochemical tests are essential routine monitoring indices during stroke rehabilitation. By continuously comparing relevant parameters before and after the intervention, these tests can sensitively evaluate whether interventions such as rehabilitation training and medications are effective and can also provide important prognostic clues for long-term functional recovery15.
Blood sampling time points were set at pre-intervention and on the morning after completion of the intervention under fasting conditions. Peripheral venous blood was collected via aseptic venipuncture of the median cubital vein into two tubes. The first sample was collected into an ethylenediaminetetraacetic acid anticoagulant vacuum tube, gently inverted to mix, and used for CBC. The second sample was collected into a serum separator tube containing clot activator and allowed to clot at room temperature for approximately 30 min. The tube was then centrifuged at 1,500 × g for 10 min at room temperature to separate the serum for biochemical analysis. Standardized procedures were followed throughout to minimize hemolysis. All samples were processed and delivered to the clinical laboratory for testing within 1 h after collection.
النتائج
The single participant enrolled in this study demonstrated good adherence and completed the entire 6-week Liuzijue breathing rehabilitation intervention in conjunction with conventional rehabilitation therapy. During the rehabilitation period, clinical observations revealed subjective improvements in limb and trunk motor performance, joint range of motion, gait stability, walking endurance, activities of daily living, and social participation. No clinically relevant training‑related adverse events were observed.
Figure 4 presents the pre- and post-intervention measurements of TV, VC, and FVC. The predicted values for TV, VC, and FVC were 0.78 L, 4.09 L, and 3.17 L, respectively. TV increased from 0.61 L at baseline (78.21% of predicted) to 0.71 L after the intervention (91.03% of predicted) (Figure 4A). VC increased from 3.55 L (86.80% of predicted) to 3.82 L (93.40% of predicted) (Figure 4B), while FVC increased from 2.76 L (87.07% of predicted) to 2.89 L (91.17% of predicted) (Figure 4C). Both the absolute values and percentages of predicted values of TV, VC, and FVC were higher at the post-intervention assessment than at baseline.
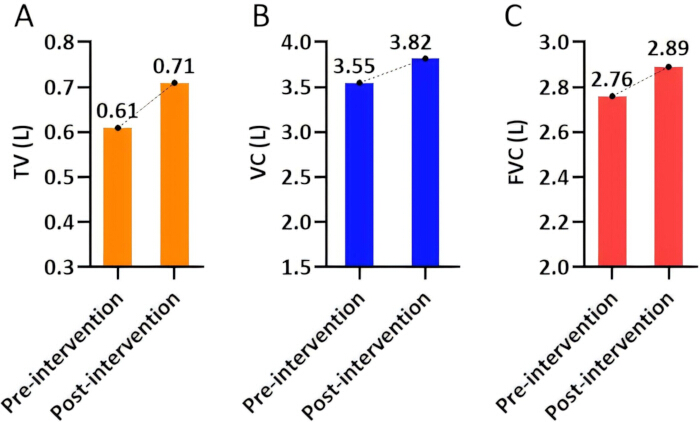
Figure 4: Pulmonary volume indices before and after the intervention. Individual measurements from the patient are shown for (A) Tidal volume. (B) Vital capacity. (C) Forced vital capacity. The dotted lines connect the pre- and post-intervention measurements. Abbreviations: TV = tidal volume; VC = vital capacity; FVC = forced vital capacity. Values are presented in liters. No error bars or inferential statistical analyses are applicable because this was a single-case observation. Please click here to view a larger version of this figure.
Figure 5 presents FEV₁ and PEF values at baseline, post-intervention, and exploratory retesting. The predicted values for FEV₁ and PEF were 3.17 L and 8.14 L/s, respectively. FEV₁ decreased from 2.51 L at baseline (79.18% of predicted) to 2.11 L on the day after the intervention (66.56% of predicted) and subsequently increased to 2.65 L on retesting (83.60% of predicted) (Figure 5A). PEF decreased from 3.31 L/s at baseline (40.66% of predicted) to 2.77 L/s on the day after the intervention (34.03% of predicted) and then increased to 3.37 L/s on retesting (41.40% of predicted) (Figure 5B).
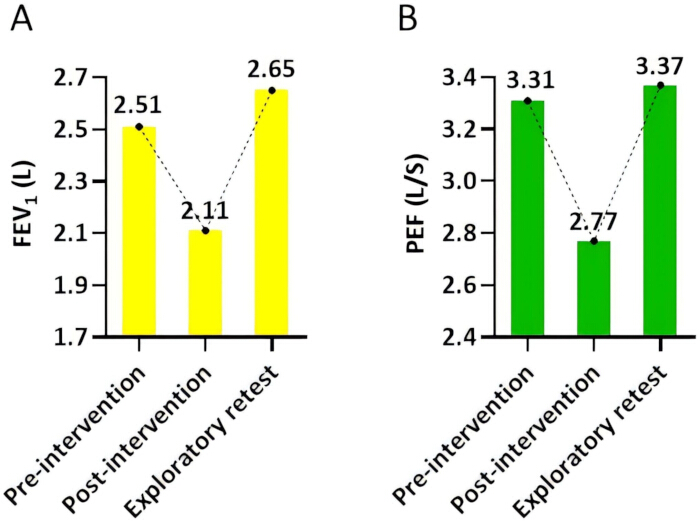
Figure 5: Expiratory pulmonary function indices before and after the intervention and at exploratory retesting. Individual measurements from the patient are shown for (A) Forced expiratory volume in 1 s. (B) Peak expiratory flow at baseline, immediately after the 6-week intervention, and during exploratory retesting. The dotted lines connect measurements across the three assessment time points. Abbreviations: FEV₁ = forced expiratory volume in 1 s; PEF = peak expiratory flow. FEV₁ is presented in liters, and PEF is presented in liters per second. No error bars or inferential statistical analyses are applicable because this was a single-case observation. Please click here to view a larger version of this figure.
Table 1 presents the SGRQ scores at baseline and after the intervention. The patient’s total SGRQ score decreased from 86.82 at baseline to 8.28 after the intervention. The Symptoms domain score decreased from 38.02 to 2.32, indicating a marked reduction in the patient-reported burden of respiratory symptoms. The Activity domain score decreased from 35.70 to 18.47, suggesting fewer perceived limitations in daily physical activities related to respiratory problems. The Impacts domain score decreased from 30.33 to 0.00, indicating that the patient reported no perceived respiratory-related impact in this domain at the post-intervention assessment. As the SGRQ is a patient-reported outcome measure, these findings reflect changes in the patient’s subjective perception of respiratory-related health status.
| Group | Symptoms | Activities | Impacts |
| Pre-intervention | 38.02 | 35.70 | 30.33 |
| Post-intervention | 2.32 | 18.47 | 0.00 |
Table 1: St George’s Respiratory Questionnaire domain scores before and after the intervention. Symptoms, Activity, and Impacts domain scores are presented for the single patient before and after the 6-week intervention. Scores range from 0–100, with higher scores indicating greater respiratory-related health impairment.
Table 2 summarizes the SF-36 domain scores before and after the intervention. Role physical increased from 25.00 to 75.00. Role emotional increased from 66.67 to 100.00. Social functioning increased from 50.00 to 75.00. Bodily pain increased from 88.00 to 100.00. Physical functioning increased from 90.00 to 95.00, and mental health increased from 60.00 to 68.00. Vitality and general health remained unchanged at 80.00 and 45.00, respectively. Overall, six of the eight SF-36 domains increased after the intervention, whereas Vitality and General Health remained unchanged.
| Group | Physical functioning | Role physical | Role emotional | Social functioning | Bodily pain | Vitality | Mental health | General health |
| Pre-intervention | 90.00 | 25.00 | 66.67 | 50.00 | 88.00 | 80.00 | 60.00 | 45.00 |
| Post-intervention | 95.00 | 75.00 | 100.00 | 75.00 | 100.00 | 80.00 | 68.00 | 45.00 |
Table 2: 36-Item Short Form Health Survey domain scores before and after the intervention. Scores for the eight SF-36 domains are presented for the single patient before and after the 6-week intervention. Each domain is scored from 0–100, with higher scores indicating better health-related quality of life.
Table 3 summarizes the pre- and post-intervention CBC and serum biochemistry results together with the corresponding reference ranges. Carbon dioxide (CO₂) increased from 23.78 mmol/L to 24.39 mmol/L (normal: 21.00–29.00 mmol/L), white blood cell (WBC) count increased from 4.97 × 10⁹/L to 5.28 × 10⁹/L (normal: 3.97–9.15 × 10⁹/L), neutrophil percentage (NEUT%) increased from 58.80% to 62.40% (normal: 45.00–77.00%), lymphocyte percentage (LYMPH%) increased from 24.30% to 27.70% (normal: 20.00–40.00%), total protein (TP) decreased from 70.66 g/L to 68.36 g/L (normal: 60.00–86.00 g/L), albumin (ALB) decreased from 39.45 g/L to 38.64 g/L (normal: 30.00–55.00 g/L). All of the above indices remained within their respective normal values before and after the intervention. Monocyte percentage (MONO%) decreased from 10.90% to 7.40% (normal: 3.00–10.00%), and eosinophil percentage (EOS%) decreased from 5.60% to 2.10% (normal: 0.50–5.00%). Both parameters were mildly elevated at baseline and returned to within the normal range after the intervention. In contrast, glucose (GLU) decreased from 3.92 mmol/L to 2.88 mmol/L (normal: 3.90–6.10 mmol/L), and hemoglobin decreased from 129.00 g/L to 110.00 g/L (normal: 131.00–172.00 g/L). GLU was within the normal limits at baseline and dropped below the lower limit after the intervention, whereas hemoglobin was already below the lower limit of normal at baseline and further decreased following the intervention.
| Group | CO2 (mmol/L) | WBC (109/L) | NEUT% (%) | LYMPH% (%) | MONO% (%) | EOS% (%) | TP (g/L) | ALB (g/L) | GLU (mmol/L) | Hb (g/L) |
| Pre-intervention | 23.78 | 4.97 | 58.80 | 24.30 | 10.90 | 5.60 | 70.66 | 39.45 | 3.92 | 129.00 |
| Post-intervention | 24.39 | 5.28 | 62.40 | 27.70 | 7.40 | 2.10 | 68.36 | 38.64 | 2.88 | 110.00 |
| Normal range | 21.00–29.00 | 3.97–9.15 | 45.00–77.00 | 20.00–40.00 | 3.00–10.00 | 0.50–5.00 | 60.00–86.00 | 30.00–55.00 | 3.90–6.10 | 131.00–172.00 |
Table 3: Complete blood count and serum biochemical parameters before and after the intervention. Values obtained from the single patient before and after the 6-week intervention are presented with the corresponding laboratory reference ranges. Abbreviations: CO₂ = carbon dioxide; WBC = white blood cell count; NEUT% = neutrophil percentage; LYMPH% = lymphocyte percentage; MONO% = monocyte percentage; EOS% = eosinophil percentage; TP = total protein; ALB = albumin; GLU = glucose; Hb = hemoglobin.
المناقشة
Since 2015, stroke has become one of the leading causes of death and disability in China16. Respiratory muscle dysfunction is a frequent post‑stroke complication, which may lead to respiratory muscle atrophy, higher risk of pulmonary infection and impaired activities of daily living2. Compared with conventional breathing training, Liuzijue combines limb movements with respiratory regulation and has shown favorable adherence and safety profiles17. Given this patient’s post-stroke motor and balance limitations, traditional standing Liuzijue was modified into a seated protocol, upper-limb movements were simplified, and respiratory rhythm was adjusted according to individual tolerance. This case demonstrates that seated modified Liuzijue was feasible and well tolerated in this patient with stroke in the recovery phase. However, the independent therapeutic effect of Liuzijue cannot be established.
Patients in the post-stroke recovery phase often present with reduced diaphragmatic excursion and a rapid, shallow breathing pattern18. Previous studies suggest that Liuzijue may improve respiratory muscle endurance, thoracic volume, and diaphragmatic excursion19,20. After the 6-week intervention, TV increased from 0.61 L (78.21% predicted) to 0.71 L (91.03% predicted), VC increased from 3.55 L (86.80% predicted) to 3.82 L (93.40% predicted), and FVC increased from 2.76 L (87.07% predicted) to 2.89 L (91.17% predicted). The improvement in lung‑volume‑related indices may be related to chest‑wall stretching induced by upper‑limb‑raising movements. Nevertheless, direct measurements of diaphragmatic and chest-wall mobility were not performed; therefore, this causal link cannot be confirmed. FEV₁ decreased from baseline 2.51 L (79.18% predicted) to 2.11 L (66.56% predicted), and PEF decreased from 3.31 L/s (40.66% predicted) to 2.77 L/s (34.03% predicted) immediately after intervention. In an exploratory, non-prespecified retest, FEV₁ increased to 2.65 L (83.60% predicted), and PEF increased to 3.37 L/s (41.40% predicted). FEV₁ and PEF are highly effort‑dependent spirometric indices. The immediate post-intervention decrease may have resulted from test‑time fatigue, insufficient expiratory effort, or poor transition between Liuzijue‑related slow breathing and burst‑type forced expiration for spirometry. Several plausible hypotheses can explain the rebound: relief of transient respiratory‑muscle fatigue, better adaptation to two breathing patterns, and possible minor true improvement in ventilatory reserve. Given methodological limitations, this rebound can only be regarded as a suggestive signal and cannot be specifically attributed to seated modified Liuzijue training.
The total SGRQ score decreased from 86.82 to 8.28, with marked reductions in the Symptoms, Activity, and Impacts domains. Respiratory training may improve respiratory-related quality of life by relieving subjective dyspnea and mitigating negative emotions21, which provides a plausible explanation for the observed change. However, SGRQ is a patient‑reported outcome reflecting subjective perception rather than objective physiological function. An Impacts score of 0 only reflects the patient’s self‑report at that assessment and does not indicate complete resolution of disease‑related burden. The prominent SGRQ improvement was discordant with modest changes in objective spirometry. Baseline symptom over-reporting, psychological relief, and expectation effects accumulated during rehabilitation could contribute to the large score reduction, which is an inherent limitation of single‑case self‑reported questionnaires. Accordingly, SGRQ serves only as an exploratory outcome and cannot be treated as direct evidence that seated modified Liuzijue improves objective respiratory function. After the intervention, six of the eight SF-36 domains showed an increase, whereas Vitality and General Health remained unchanged. According to prior mechanistic hypotheses, rhythmic nasal inspiration and oral expiration in Liuzijue may activate respiratory muscles and proprioceptors and facilitate neuroplastic remodeling of trunk neuromotor pathways22. However, autonomic function and neuroplasticity were not measured, and anxiety and depression scales were not administered. Together with concurrent conventional rehabilitation and spontaneous post‑stroke recovery, changes in SF‑36 cannot be specifically attributed to Liuzijue.
Laboratory parameters were interpreted descriptively. CO₂, WBC, NEUT%, LYMPH%, TP, and ALB remained within their respective reference ranges at both assessments. MONO% and EOS% were mildly elevated at baseline and decreased to within their reference ranges after the intervention. However, because specific inflammatory cytokines and airway-related biomarkers were not measured, these changes cannot be interpreted as evidence of improved airway inflammation or respiratory immune function. GLU decreased from 3.92 mmol/L to 2.88 mmol/L, falling below the lower reference limit after the intervention. Hemoglobin decreased from 129 g/L to 110 g/L; the baseline value was already below the normal reference range, and the post-intervention value remained below this range. Although these laboratory abnormalities were identified, the patient was closely monitored throughout the training period, and no clinical manifestations suggestive of hypoglycemia or anemia were observed. Under routine nutritional therapy for stroke rehabilitation, close clinical observation was maintained, and no targeted interventions were implemented for these abnormalities. The CBC test was performed under fasting conditions, whereas all training sessions were conducted 1–2 hours after meals, suggesting that the noted hypoglycemia-related laboratory finding might be associated with the fasting state rather than the intervention. In contrast, the anemia-related findings were considered pre-existing rather than attributable to the intervention. These findings indicate potential nutritional and metabolic concerns during rehabilitation. Following clinical evaluation by the attending clinician, which took into account the patient's dysphagia, type 2 diabetes mellitus, dietary status, concomitant medications, and other clinical factors, the underlying causes of these abnormalities could not be determined from this single case, and a direct relationship with seated modified Liuzijue training could not be established. No clinically relevant training‑related adverse events were observed during the 6‑week intervention, which supports the short-term tolerability of the protocol in this individual patient. However, the laboratory abnormalities warrant clinical attention, and data from a single case are insufficient to draw broader conclusions regarding the safety of seated modified Liuzijue in patients with stroke.
This study has several inherent limitations. First, this was a single-case pre–post observation without a parallel control group. The respective contributions of seated modified Liuzijue, spontaneous stroke recovery, and concomitant conventional rehabilitation cannot be disentangled. Second, direct objective measurements, including respiratory muscle strength, diaphragmatic displacement, and chest-wall expansion, were not obtained; therefore, the proposed physiological mechanisms could not be directly evaluated. Third, the retest for FEV₁ and PEF was an exploratory, non-prespecified assessment, introducing interpretive uncertainty. Fourth, SGRQ and SF-36 are subjective patient-reported outcomes. Response bias, baseline recall bias, test-day mood, and expectation effects may have confounded the results. The discordance between the subjective and objective outcomes further cautions against overinterpretation. Fifth, only immediate post-intervention data and one exploratory retest were collected. Long-term follow-up was lacking, and the sustainability of the observed changes remains unknown.
This case demonstrates only that seated modified Liuzijue could be completed over 6 weeks and was feasible and well tolerated in this patient during the recovery phase of stroke. Changes in selected pulmonary function indices and patient-reported quality-of-life outcomes were observed between the pre- and post-intervention assessments. Nevertheless, due to the absence of a control group, concomitant conventional rehabilitation, spontaneous post‑stroke recovery, and lack of mechanistic biomarkers, the independent therapeutic effect of seated modified Liuzijue cannot be confirmed, nor can the proposed mechanisms, including respiratory muscle strengthening and increased diaphragmatic excursion, be verified. Mechanisms proposed in previous literature may plausibly explain the observed findings. However, this case generates hypotheses rather than testing them. Future controlled studies incorporating objective indicators such as maximal inspiratory pressure, maximal expiratory pressure, diaphragmatic ultrasonography, chest‑wall kinematics, and standardized spirometry quality‑control are warranted to further explore the potential value and mechanisms of seated modified Liuzijue for post‑stroke respiratory rehabilitation.
الإفصاحات
The authors declare that the research was conducted in the absence of any commercial or financial relationships that could be construed as a potential conflict of interest. The authors have nothing to disclose.
شكر وتقدير
This work was supported by the Joint Innovation Fund of Health Commission of Chengdu and Chengdu University of Traditional Chinese Medicine (Grant No. WXLH202501380) and Natural Science Foundation of Fujian Province (Grant No. 2023J011858).
المواد
| الاسم | الشركة | رقم فهرسي | التعليقات |
|---|---|---|---|
| Automatic biochemical analyzer | Beckman Coulter | AU5800 | Used for biochemical assays |
| Automatic blood cell analyzer | Mindray | BC6900 | Used for complete blood count |
| Cardiopulmonary exercise testing system | Shenzhen Miraclink Medical Technology | 300 12-019-55 | Used for pulmonary function testing |
| Computed tomography scanner | Siemens Healthineers | SOMATOM Force | Used for brain and chest CT plain scan |
| CT angiography system | Siemens Healthineers | SOMATOM Force | Used for craniocervical CT angiography |
| EDTA anticoagulant blood collection tube | BD Vacutainer | 367525 | Used for complete blood count (CBC) |
| Serum separator tube | BD Vacutainer | 367955 | Used for biochemical tests |
| St George’s Respiratory Questionnaire | Original developer: St George’s, University of London | N/A | Used to assess respiratory-related quality of life |
| 36-Item Short Form Health Survey | RAND Corporation | N/A | Used to assess general health-related quality of life |
المراجع
- Somogyi P et al. Pulmonary consequences of experimentally induced stroke: differences between global and focal cerebral ischemia. Front Physiol. 2024;15:1511638.
- Chen M et al. Brain regulation of pulmonary dysfunction induced by stroke. Brain. 2025;148(12):4562-77.
- Sutbeyaz ST, Koseoglu F, Inan L, Coskun O. Respiratory muscle training improves cardiopulmonary function and exercise tolerance in subjects with subacute stroke: a randomized controlled trial. Clin Rehabil. 2010;24(3):240-50.
- Huang H et al. Digital gamification-based pursed lip breathing exercises driven by Behaviour Change Wheel in patients with COPD: a feasibility trial protocol using pre-post study design. BMJ Open. 2025;15(3):e090832.
- Pulmonary Rehabilitation Group (Preparatory) of Chinese Thoracic Society, Chinese Pulmonary Rehabilitation Society of Chinese Association of Rehabilitation Medicine, Chinese Association of Chest Physician. Guidelines for pulmonary rehabilitation of chronic respiratory diseases in China (2026 edition). Zhonghua Yi Xue Za Zhi. 2026;106(8):703-32.
- Zhang ML. Key points and practical skills for practicing Chinese Health Qigong: Liu Zi Jue. General Administration of Sport of China, Health Qigong Management Center; 2018. https://www.sport.gov.cn/qgzx/n5407/c878295/content.html.
- Xu S et al. Efficacy of Liuzijue Qigong in patients with chronic obstructive pulmonary disease: a systematic review and meta-analysis. Complement Ther Med. 2022;65:102809.
- Gong T et al. Effects of Liuzijue Qigong posture on aerodynamics of phonation in healthy volunteers. J Voice. 2024;38(4):967.e1-7.
- Lee K, Cho JE, Hwang DY, Lee W. Decreased respiratory muscle function is associated with impaired trunk balance among chronic stroke patients: a cross-sectional study. Tohoku J Exp Med. 2018;245(2):79-88.
- Chen DS, Lin FY, Wang W. To explore the effect of six-character formula on motor function and negative emotion of patients with sequelae of cerebral infarction. Chin Manip Rehabil Med. 2022;13(11):18-20.
- Maldonado-Franco A et al. The challenges of spirometric diagnosis of COPD. Can Respir J. 2023;2023:6991493.
- Graham BL et al. Standardization of spirometry 2019 update: an official American Thoracic Society and European Respiratory Society technical statement. Am J Respir Crit Care Med. 2019;200(8):e70-88.
- Jones PW, Quirk FH, Baveystock CM, Littlejohns P. A self-complete measure of health status for chronic airflow limitation: the St. George's Respiratory Questionnaire. Am Rev Respir Dis. 1992;145(6):1321-7.
- Ware JE Jr, Sherbourne CD. The MOS 36-item short-form health survey (SF-36): I. Conceptual framework and item selection. Med Care. 1992;30(6):473-83.
- Gittler M, Davis AM. Guidelines for adult stroke rehabilitation and recovery. JAMA. 2018;319(8):820-1.
- Tu WJ, Wang LD, Special Writing Group of China Stroke Surveillance Report. China stroke surveillance report 2021. Mil Med Res. 2023;10(1):33.
- Zhao JJ, Liu HR, Shan XY, Dong Q. Research of the respiratory rehabilitation and TCM exercises combined with conventional western medicine therapy on the lung function for the patients with COPD. Int J Tradit Chin Med. 2018;40(8):710-4.
- Voyvoda N et al. An evaluation of diaphragmatic movements in hemiplegic patients. Br J Radiol. 2012;85(1012):411-4.
- Li D et al. Effect of weight-bearing Liuzijue Qigong on cardiopulmonary function. Medicine (Baltimore). 2023;102(8):e33097.
- Xiao L et al. A systematic review and meta-analysis of Liuzijue in stable patients with chronic obstructive pulmonary disease. BMC Complement Med Ther. 2020;20(1):308.
- Bai YL, Luo WP, Qi LM, Wei CH. Theoretical mechanism exploration of the six-character formula in emotional health preservation. J Sichuan Tradit Chin Med. 2025;43(1):60-2.
- Filippi GM et al. Plastic changes induced by muscle focal vibration: a possible mechanism for long-term motor improvements. Front Neurosci. 2023;17:1112232.