The protocol presents a luminol-based chemiluminescent assay developed to detect fecal occult blood in various murine models of intestinal pathologies, providing a sensitive and non-invasive method.
方法文章
Non-Invasive and Cost-Effective Fecal Occult Blood Detection for Colon Cancer Prognosis in Murine Models
本文内容
摘要
摘要
Fecal occult blood testing is a widely used diagnostic method for the early detection of colorectal cancer and the assessment of gastrointestinal pathologies in humans. For preclinical research purposes, we developed a cost-effective, non-invasive luminol-based chemiluminescent assay to detect fecal occult blood in murine feces that can function as a predictive tool, with sufficient sensitivity to correlate with disease severity. Fecal samples were collected and weighed, solubilized in a sodium hydroxide solution, then combined with luminol and hydrogen peroxide and immediately analyzed using a luminometer. Luminol reacts with the iron in hemoglobin to produce a measurable chemiluminescent signal; therefore, known hemoglobin concentrations from mouse blood, quantified using a hemoglobinometer, were used to generate a standard curve along with feces from naïve mice. The method was validated against standard Guaiac paper slide tests for accuracy. We demonstrated a strong correlation with disease severity metrics, including colonoscopy findings and tumor burden in multiple models of colon cancer, offering an accessible, non-invasive, and inexpensive alternative for routine monitoring of disease progression. The application of this technique can be broadened to other murine models of gastrointestinal pathologies, such as peptic ulcers, inflammatory bowel disease, Crohn's disease, and gastritis.
引言
Colorectal cancer (CRC) is one of the most prevalent cancers in humans, with nearly 2 million new cases and over 900,000 deaths annually, making it a leading cause of cancer-related mortality worldwide1. Mouse models are critical for studying CRC due to their ability to mimic key features of the disease, including tumor immunity, development, progression, and response to therapies2,3. Commonly used models include chemically-induced colon cancer (e.g., azoxymethane/dextran sodium sulfate), transgenic mouse models (e.g., COX2 knockout, ApcMin/+ mice), which replicate the mutational landscape and inflammatory conditions, and transplantation models (xenografts), which are particularly useful for metastasis studies4,5,6. Colon disease progression in mice is assessed through colonoscopy, which requires anesthesia and induces physiological stress on the colon; histological analysis, which is usually terminal and prevents longitudinal monitoring; and imaging techniques like MRI or ultrasound, which are costly and require anesthesia7,8,9,10.
One of the most accessible and informative markers of CRC progression is fecal occult blood (FOB), which arises from bleeding lesions in the gastrointestinal tract11. Monitoring FOB directly from excreted feces in mouse models serves as a non-invasive proxy for disease severity and tumor burden, enabling researchers to track disease progression without the need for repeated invasive procedures. However, traditional FOB test methods, such as guaiac-based tests, are limited by poor sensitivity, dietary interference, and inconsistent results12,13. FOB detection using luminol is available, but it is typically included in specialized kits, which can be costly14. These kits have not been validated against guaiac-based or fecal immunochemical tests, nor have they been assessed for correlation with disease activity or tumor burden. To address these limitations, we developed a sensitive and cost-effective luminol-based chemiluminescent assay tailored to detect FOB in murine models with potential prognostic value in assessing disease severity and progression. The collection method involves only brief manual scruffing and uses only 1–2 fecal pellets per assay (about 10–30 mg), although multiple collection points at different times of the day to account for variation in the presence of FOB and fecal output are recommended.
Luminol is a chemical commonly used in forensic science to detect trace amounts of blood, as the iron in hemoglobin catalyzes its chemiluminescent reaction15. When luminol, dissolved in an alkaline solution like sodium hydroxide (NaOH), reacts with hydrogen peroxide (H₂O₂), it emits blue light due to oxidation. NaOH creates the alkaline environment needed to deprotonate luminol into its reactive dianion form, while H₂O₂ provides reactive oxygen species for the reaction15,16,17,18. The reaction is very sensitive, where mM concentrations of luminol can detect as low as one part per million of hemoglobin19. The emitted blue light indicates the presence of blood, even in trace amounts.
The luminol-based assay relies on the chemiluminescent reaction between luminol and hemoglobin, producing a quantifiable signal that reflects blood presence in fecal samples14. Compared to guaiac-based methods, this approach is more specific, removes inter-observer interpretations, and offers a broader dynamic range for detecting occult blood20. Additionally, while advanced molecular techniques can be used to detect cancer markers in humans, their complexity, high cost, and instrumentation requirements make them impractical for routine monitoring in mouse studies, especially if these assays are performed using tissue or serum that can only be harvested by inducing high levels of stress to the mice, or at the time of sacrifice, posing a challenge to real-time or continuous disease progression tracking21,22. The luminol assay bridges this gap by providing a non-invasive method for assessing CRC progression in preclinical models.
In the context of CRC research, this luminol-based assay provides a valuable tool for researchers studying tumor biology, therapeutic efficacy, and the impact of genetic or environmental factors on cancer progression. Its application extends beyond CRC to other gastrointestinal diseases where FOB is a diagnostic marker, such as inflammatory bowel disease and ulcerative colitis23,24,25,26. By enabling non-invasive, longitudinal monitoring of disease severity, this method is an important addition to the toolkit for preclinical studies.
方案
All animal experiments were conducted in accordance with the guidelines and with the approval of the Tel Aviv University Animal Care and Use Committee (Protocols 01-18-059, 01-18-060, and 01-21-010). Mice were bred on a C57Bl/6J genetic background in the specific pathogen-free (SPF) animal facility in Tel Aviv University. All mice were housed as per the institutional animal care and use committee (IACUC) guidelines in temperature-controlled rooms with a 12-h light cycle and were given water and pelleted chow ad libitum.
NOTE: This protocol is designed to detect FOB in a variety of murine models of colon cancer with potential application in other gastrointestinal pathologies. For long-term experiments, feces should be collected for two or three consecutive days and/or at multiple times of day (early morning, afternoon, and evening) to account for variation. Mice treated with a substance that may interfere with the luminol reaction should be compared with control mice treated with an interfering substance to establish a baseline. A naïve wildtype mouse (feces and blood from the facial vein) should be used to generate a standard curve.
1. Murine models
- In the azoxymethane/dextran sodium sulfate (AOM/DSS)-induced mouse model of colitis-associated colorectal cancer, give 6-week-old female WT and systemic cannabinoid receptor 2 knockout (CB2−/−) mice a single intraperitoneal injection of AOM (12 mg/kg body weight)27,28. At 3 days after the AOM injection, give the mice 2.5% DSS in their drinking water for 7 days in weeks 1, 4, and 728.
- Monitor cancer progression in all mice using body weight, fecal occult blood testing, and colonoscopy. Perform a colonoscopy (by a veterinarian) in week 7 before the administration of DSS cycle 3. To assess the predictive value of the fecal occult blood test for disease severity, collect fecal samples immediately before colonoscopy.
- Inject 5-week-old male and female ApcMin/+ mice with 700 ng osteogenic growth peptide (OGP) weekly or with a vehicle control for 4 weeks. Collect fecal samples 1 day before sacrifice at 9 weeks of age, and perform adenoma count immediately post-sacrifice.
NOTE: ApcMin/+ mice, a well-established genetic model of colon cancer (modeling familial adenomatous polyposis in humans), were obtained from the Jackson Laboratory and subsequently bred in-house using heterozygous males on a C57BL/6J background29.
2. Feces collection and preparation
CAUTION: All procedures must be performed wearing appropriate personal protective equipment, including a lab coat, nitrile gloves, and eye protection. Work with chemical reagents and biological samples should occur in a fume hood or biosafety cabinet, respectively.
- Record the weight of each 2 mL tube prior to feces collection. In a biosafety hood, collect feces in pre-weighed tubes, placing the tube towards the rectum of the mouse to allow the fecal matter to fall into the tube. To reduce stress, place the mouse in a clean, empty cage to collect feces.
CAUTION: Handling of feces and blood (Biological Hazard, BSL-2): Mouse feces and mouse blood must be treated as potentially infectious materials. Avoid aerosol generation during feces collection, vortexing, mixing, and pipetting. Surfaces contaminated with biological material should be disinfected immediately using an approved solution followed by 70% ethanol. All biological waste—including feces, contaminated gloves, wipes, capillary tubes, and blood-contaminated consumables—must be disposed of in a designated biohazard waste container and autoclaved before final disposal. Sharps (needles, capillary tubes) must be discarded directly into an approved sharps container. - Weigh the tubes again to determine the weight of the feces by subtracting the weight of the empty tube from that of the tube with feces.
- Add 2 mL of 0.03 M NaOH and vortex thoroughly for 5 min. Centrifuge at 500 × g for 5 min at room temperature. Be careful not to disturb the fecal matter at the bottom of the tube and dilute it into a new 1 mL tube for a final concentration of 1 mg feces/mL.
CAUTION: Sodium hydroxide is corrosive and can cause burns to skin and eyes. Wear gloves and eye protection while preparing and handling the NaOH solution. Dispose of NaOH-containing liquid waste in a clearly labeled alkaline waste container. Preparation of the 0.03 M NaOH solution from a more concentrated solution or crystals must be done in a fume hood. - Standard curve: Create a standard curve by combining blood with a known hemoglobin concentration with feces, both from a naïve wildtype mouse. Determine the hemoglobin concentration of the blood by using a hemoglobinometer.
- Using a 25 G needle, puncture the facial vein slightly behind the mandible—in line with the angle of the oral commissure—anterior to the ear canal.
- Collect about 10 µL of blood using a capillary tube, then test immediately by placing the capillary tube on a hemoglobin test strip pre-loaded into the hemoglobinometer, and record the hemoglobin concentration.
- Collect 20–90 µL of blood in a heparin or ethylenediaminetetraacetic acid (EDTA)-coated blood collection tube. Apply mild pressure with sterile gauze if needed to stop the bleeding from the facial vein.
- Dilute the blood to a hemoglobin concentration of 10,000 ng/mL in the luminol working solution (10-2 M luminol, 0.03 M NaOH) to create a hemoglobin solution.
NOTE: Standard curve values can be adjusted by increasing or decreasing the dilution of the blood to accommodate very high or low fecal occult blood. Because the reaction occurs rapidly, the standard curve should be performed in duplicate, and read on the luminometer in two parts, reading only nine wells (one complete standard curve and a blank) per read. - Place 100 µL of the 10,000 ng/mL hemoglobin solution (1000 ng of hemoglobin) in the first well and 50 µL of luminol working solution into the remaining wells of a black, flat-bottom 96-well plate.
NOTE: Black plates are recommended as they reduce reflection, background noise, and enhance signal strength. Clear, flat-bottom 96-well plates (as shown in Supplementary Figure 1) also proved successful for ApcMin/+ mice, as their FOB is typically high. The signal strength for the luminol reaction of the samples was high enough that background noise did not seem to alter the signal between samples. This could also be because minimal samples were run in each read. In Supplementary Figure 1, the reaction is shown in wells A1–A8: wells B1–B8 and A9 had a negligible chemiluminescence value that was not above 2 ng of hemoglobin according to the standard curve. Therefore, if low hemoglobin values are expected, then it is best to use a black plate. It is important to validate the signal strength of the chemiluminescence values and of the experimental wells and surrounding wells to determine if a clear plate can be used. - Perform a 1:2 decreasing factor serial dilution consisting of seven concentrations and a zero concentration. The content of hemoglobin in the standard curve is: 500 ng, 250 ng, 125 ng, 62.5 ng, 31.25 ng, 15.625 ng, 7.81 ng, 0 ng hemoglobin. The final concentrations of the hemoglobin (ng)/microgram (µg) of feces are 100, 50, 25, 12.5, 6.25, 3.125, and 1.56 if 5 µg of feces are added to each well.
NOTE: If working with an alternate model, an initial validation to determine the maximum of the standard curve should be performed. - Be sure to leave the 8th well without the hemoglobin solution, meaning the well should only contain 50 µL of luminol working solution at this stage. This will act as the negative hemoglobin control, containing feces and no hemoglobin.
- Add 5 µg of feces from a naïve wildtype mouse to all standard curve wells and mix well. Include a blank well that does contain feces (50 µL of luminol working solution only). This will act as a negative control/blank, to be sure there is no contamination in the luminol or hydrogen peroxide (next step) solutions that could lead to false positives.
- Immediately before reading, add 50 µL of 0.03% hydrogen peroxide (H2O2) to each well, including the blank, using a multichannel pipettor and mix by pipetting up and down 2×–3×.
- Ensure the time between adding hydrogen peroxide and reading does not exceed 1 min. The final concentration of the first well of the standard curve after adding the hydrogen peroxide solution is 100 ng of hemoglobin/microgram (µg) of feces, decreasing by 1:2 (Figure 1).
CAUTION: Hydrogen peroxide may cause irritation to the skin and eyes. Store away from heat and light; open containers carefully to avoid pressure release. Small volumes used in this protocol can be disposed of in a labeled chemical waste container according to local chemical waste guidelines. Do not mix with incompatible chemicals.
- Ensure the time between adding hydrogen peroxide and reading does not exceed 1 min. The final concentration of the first well of the standard curve after adding the hydrogen peroxide solution is 100 ng of hemoglobin/microgram (µg) of feces, decreasing by 1:2 (Figure 1).
- Determine the chemiluminescence signal as the ratio to the blank to eliminate the background signal. Analyze the plate, one column or row per read, at 425 nm on a luminometer or spectrophotometer with a luminescence setting. The emission is typically centered at 415 nm up to 455 nm due to the presence of iron30.
- Calculate the standard curve equation (linear regression) using nanogram (ng) of hemoglobin/microgram (µg) feces as the x-axis and chemiluminescence (output from luminometer) as the y-axis.
3. Sample analysis
- In a 96-well plate, combine 5 µg of feces from the 1 mg/mL 0.03 M NaOH solution into 50 µL of luminol working solution (10-2 M luminol 0.03 M NaOH). Run samples in duplicates or triplicates. Include a blank (50 µL of luminol working solution) in each read.
- Immediately before reading the plate, add 50 µL of 0.03% H2O2 using a multichannel pipettor and mix by pipetting up and down 2×–3× with caution to avoid formation of bubbles. Ensure that the time between adding the hydrogen peroxide and reading the plate does not exceed 1 min.
NOTE: The reaction occurs rapidly; it is mandatory to use a multichannel pipettor to add the 0.03% H2O2 to all wells simultaneously. Reading only one column or row per measurement ensures that all samples undergo the reaction for the same amount of time. Set a timer to determine the time between first adding the hydrogen peroxide solution and the read on the luminometer to be sure each read has been undergoing the reaction for the same amount of time. If the luminometer has a plate reading compartment that allows access to the wells, pipette the 0.03% H2O2 into the wells with the plate inserted into the plate reading compartment/drawer so that the time between the reaction and reading is as short as possible. - Read the plate on a luminometer or spectrophotometer with a luminescence setting at 425 nm. Calculate the concentration of hemoglobin (ng) per feces (µg) in the experimental samples based on the standard curve linear equation. An example sample curve is shown in Figure 1.
结果
Wildtype (WT) and systemic cannabinoid receptor 2 knockout (CB2-/-) mice received azoxymethane (AOM) and dextran sodium sulfate (DSS) to induce colorectal cancer. One day before the colonoscopy, feces were collected and analyzed for FOB (Figure 2). The disease activity index (DAI) determined by colonoscopy was compared with the FOB luminol protocol to assess their correlation (Figure 3). Disease activity scores were given for the transparency of the colonic wall, the looseness of feces, blood vessel organization, granulation, fibrin deposition, and weight loss. The results of the FOB test were found to correlate with the DAI, showing that this method can be used to assess disease progression with relatively high accuracy.
We previously published that CB2-/- mice have increased colon cancer frequency and severity. In addition to correlation with the DAI, the FOB test results generally corroborate the greater number of polyps seen in the large intestines of CB2 -/- mice treated with AOM/DSS31.
Similarly, ApcMin/+ mice, a genetic model of colon cancer, were treated with osteogenic peptide (OGP), a CB2 agonist, or a vehicle control for 4 weeks from 5 weeks of age. These mice were assessed for fecal occult blood at 9 weeks of age, when adenoma count is expected to be 30+ (Figure 4)32.
ApcMin/+ mice of varying age (6–16 weeks), disease progression, and treatment were sacrificed 2 days after feces collection, and the adenomas were counted: adenoma burden was evaluated in relation to FOB test results and demonstrated a significant linear correlation (Figure 5). We previously found that mice receiving OGP had a lower incidence of adenomas and longer colon lengths (decreased colon length is a marker for colon cancer progression)32. The FOB test results reflect these findings, wherein mice receiving OGP had lower FOB measurements.
Fecal samples from these same ApcMin/+ mice, collected in sufficient quantity from a single collection (collections occurred throughout their lifespan), were used to compare the FOB luminol protocol described here with the guaiac-based smear test, a routine screening method for FOB in humans. FOB scores were determined using the Hemoccult kit, a guaiac-based assessment, and were blindly given a score from 0 to 3 according to the manufacturer's instructions (see Supplementary Figure 2). In short, the feces were collected, smeared on the guaiac card, and the provided solution was added. The cards were then read blindly and given a score based on the intensity of the developed blue color, ranging from 0 to 3. Guaiac-based FOB test scores were compared to the results of feces from the same collection time using the luminol protocol to assess the validity of this method against an industry standard (Figure 6). The guaiac-based methods appear to be less sensitive and susceptible to human error, as they require visual interpretation of the blue intensity on the guaiac paper and are only semi-quantitative in nature, although the results from the two methods clearly coincide.
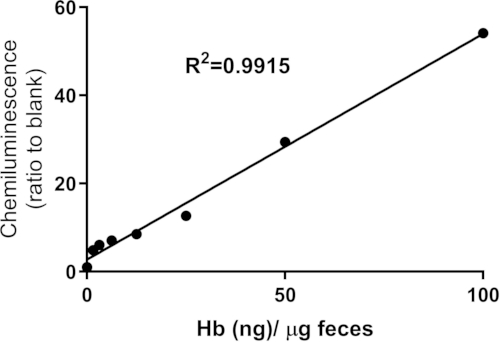
Figure 1: Hemoglobin standard curve. Standard curve of hemoglobin concentration per µg of feces generated using blood taken from naïve mice with a known hemoglobin (Hb) value as measured by a hemoglobinometer and distributed at the indicated concentrations onto 5 µg of feces (from the same naïve mice) dissolved in a luminol solution. A reaction solution containing hydrogen peroxide was added immediately before reading on a luminometer. Chemiluminescence values were determined as the ratio to the blank. Linear regression was performed to determine the linear equation (y = 0.512X + 2.761) and R2 value. This figure was reproduced with permission from Iden et al.32 under the Creative Commons Attribution 4.0 International License (CC BY 4.0; https://creativecommons.org/licenses/by/4.0/). Please click here to view a larger version of this figure.
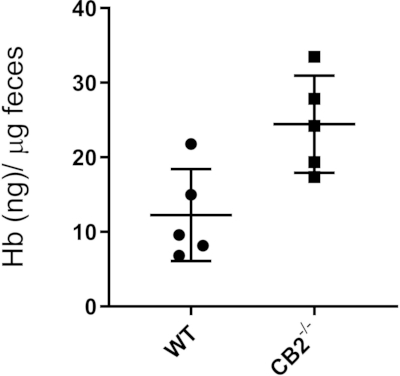
Figure 2: Fecal occult blood test. The results from mice treated with AOM/DSS using a luminol-based protocol. Wildtype (WT) and CB2 knockout (CB2-/-) were given a single intraperitoneal injection of AOM (12 mg/kg body weight). At 3 days after the AOM injection, the mice were given 2.5% DSS in their drinking water for 7 days in weeks 1 and 4. Fecal samples were taken during week 6, the day preceding the colonoscopy. Student's t-test, n = 5 per group, p < 0.01. Data are shown as mean ± standard deviation. Please click here to view a larger version of this figure.
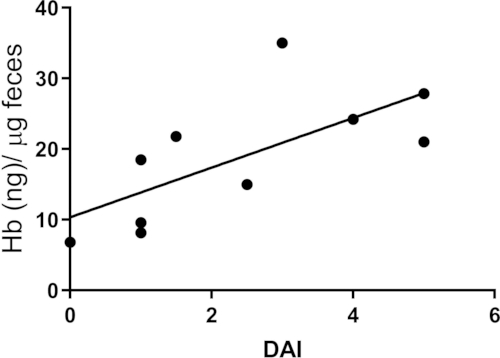
Figure 3: Fecal occult blood concentration vs disease activity index (DAI) in mice treated with AOM/DSS. Disease activity scores (0–2) were determined by a veterinarian during colonoscopy for each of the following parameters: colonic wall transparency, fecal consistency, blood vessel organization, granulation, and fibrin deposition. Spearman's rank correlation analysis, r = 0.7878, p = 0.009, n = 10. Please click here to view a larger version of this figure.
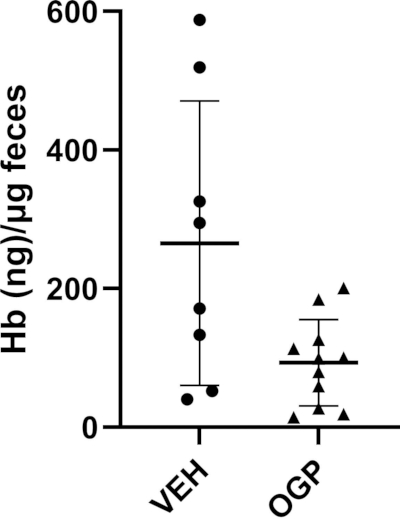
Figure 4: Fecal occult blood test in ApcMin/+ mice. The results from 5-week-old male and female ApcMin/+ mice treated with one injection of 700 ng OGP/week or vehicle control (VEH) for 4 weeks. Fecal samples were taken at 9 weeks of age (when 30+ adenomas are expected). Student's t-test, n ≥ 8 per group, p < 0.05. Data are shown as mean ± standard deviation. Please click here to view a larger version of this figure.
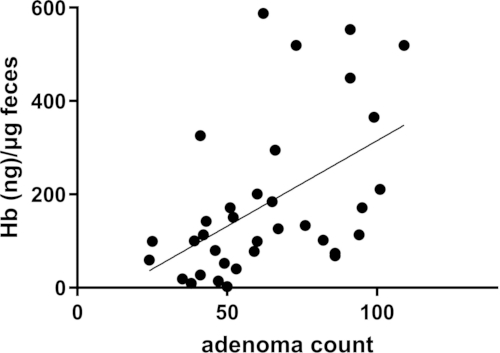
Figure 5: Fecal occult blood concentration vs adenoma burden in ApcMin/+ mice. Fecal samples were collected 2 days before sacrifice. Small and large intestines were harvested and flushed with PBS until clean. Adenoma count was performed using a dissection microscope at 7× magnification (Nikon SMZ 745T). Pearson correlation, r = 0.5070, p = 0.0019, n = 35. Please click here to view a larger version of this figure.
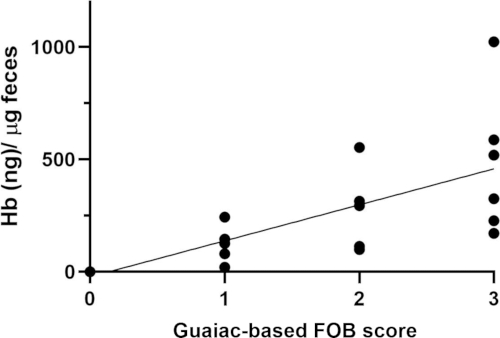
Figure 6: Fecal occult blood concentration vs guaiac-based smear test score. Feces were collected from ApcMin/+ mice of varying ages (6–16 weeks). Between 6 and 16 weeks of age, these mice develop multiple adenomas in the small and large intestine. The same sample collections were assessed for fecal occult blood using the luminol-based protocol and the Guaiac-based smear test score (determined blindly). Spearman's rank correlation analysis, r = 0.8230, p < 0.0001, n = 20. Please click here to view a larger version of this figure.
Supplementary Figure 1: Representative luminol chemiluminescent reaction results. Immediately after the addition of hydrogen peroxide for 2000 ng of hemoglobin and 5 µg of feces (400 ng of hemoglobin/microgram [µg] of feces) in a clear, flat-bottom plate, the reaction was analyzed. Light blue color represents the confirmed presence of fecal occult blood.Please click here to download this file.
Supplementary Figure 2: Representative guaiac-based assessment for fecal occult blood using fecal smears from ApcMin/+ mice. Please click here to download this file.
讨论
The luminol-based chemiluminescent assay presented in this study provides a sensitive, non-invasive, and cost-effective method for detecting FOB in murine models of intestinal pathology. Traditional FOB tests, such as guaiac-based methods, have been widely used in clinical and research settings but suffer from limitations including dietary interference, low sensitivity, and reliance on subjective colorimetric interpretation13,20. Unlike clinical FOB tests designed for binary screening in humans, this luminol-based assay facilitates longitudinal disease monitoring in murine models. It provides a dynamic measure of disease progression rather than a binary positive or negative result, presenting a lower risk of a false negative where the levels of blood are very low and cannot be detected using guaiac-based methods. This limitation has been reported in clinical settings12. In a diagnostic accuracy test, fecal immunochemical tests (FITs) missed 24% of cases, while they missed 61%, highlighting the lower sensitivity20. In a theoretical cohort of 10,000 screened individuals, guaiac-based FOB tests failed to detect 85% of cases with large polyps, CRC, or both, compared to 67% with FITs, while both tests resulted in unnecessary colonoscopies20.
The results of this study demonstrate that luminol-based FOB detection offers a more quantitative and objective approach to assessing intestinal bleeding, correlating well with disease severity and adenoma burden in murine models. A key advantage of the luminol assay is its broad dynamic range, allowing for the detection of varying hemoglobin concentrations in fecal samples. The standard curve generated from known hemoglobin concentrations in naïve mice provides accurate quantification and flexibility, making this method reproducible and reliable across different experimental conditions. The maximum value of the standard curve can be scaled up or down depending on the expected levels of FOB. We did not use commercially available hemoglobin to generate a standard curve, but rather blood with a known hemoglobin concentration determined using a hemoglobinometer combined with feces from naïve mice. The nature of this method was to create the conditions for determining chemiluminescence values as close as possible to the experimental samples, meaning it is not known if the presence of blood (rather than hemoglobin alone) or the presence of pure hemoglobin will significantly alter the manifestation of chemiluminescence in the standard curve compared to experimental samples. However, if a hemoglobinometer or murine blood draws are not accessible, commercially available hemoglobin could be considered for the standard curve.
This assay was validated against the guaiac-based test, revealing that the latter is less sensitive and prone to subjectivity due to its reliance on visual interpretation of color changes. This concept is particularly relevant in the analysis of human samples, where a positive or negative result allows for clinical decision-making, in contrast to murine studies, where the specific pathology is typically known, and the objective of the FOB test is continuous monitoring of disease progression and severity.
Unlike invasive procedures such as colonoscopy, this luminol-based FOB assay enables longitudinal monitoring of disease progression without subjecting animals to repeated anesthesia or surgical interventions. This is particularly beneficial for preclinical studies that aim to evaluate therapeutic interventions over extended periods, thereby minimizing fatalities and stress.
Despite its advantages, several factors must be considered when implementing this assay. The chemiluminescent signal is highly dependent on the reaction conditions, including the precise timing of measurements. As the luminol reaction occurs rapidly upon exposure to hydrogen peroxide, standardizing reaction timing is critical to ensure consistency across samples15. Additionally, although this method effectively quantifies FOB in murine models, its direct applicability to human samples requires separate validation. Another important consideration includes the hemoglobin concentration of the experimental mice, as treatments that induce or prevent anemia or cause other changes in hemoglobin levels could affect assay results, necessitating the measurement of hemoglobin concentration for each mouse to normalize the concentration of hemoglobin. While ApcMin/+ mice can develop anemia33, in part due to blood loss from intestinal bleeding (thus high FOB), we found that this did not significantly impact FOB measurements, as the FOB levels were sufficiently high to override small variations in hemoglobin concentration. After testing individual hemoglobin levels, we observed that values remained comparable across mice32 and normalization to each mouse's hemoglobin concentration ensured that anemia did not confound the results. In preliminary experiments, the intervention and/or model should be assessed if alterations in hemoglobin are anticipated.
The findings presented here align with previous studies that emphasize the need for more precise and reproducible methods for monitoring CRC progression in animal models3,7,8. Given its ability to detect blood at low concentrations, this assay may also have potential applications in other gastrointestinal pathologies, such as inflammatory bowel disease or Crohn's disease, where occult bleeding serves as an indicator of disease severity34. Overall, the luminol-based chemiluminescent assay represents a significant advancement in the non-invasive monitoring of CRC in preclinical settings. By providing a sensitive and scalable alternative to conventional FOB detection methods, this assay enhances the ability to track disease progression and evaluate therapeutic interventions in murine models of colon cancer. Further validation in additional disease models and potential adaptation for human clinical use may broaden its applicability in translational and clinical research.
披露
There are no conflicts of interest to declare.
致谢
This work was carried out in partial fulfillment of the requirements for a Ph.D. degree for JAI from the Faculty of Medicine, Tel Aviv University, Tel Aviv, Israel. This research was funded by the Emerson Collective Cancer Research Fund and the Israel Science Foundation (grant numbers 1086/17 and 1906/21) to YG.
材料
| 姓名 | 公司 | 目录编号 | 评论 |
|---|---|---|---|
| 96-well Solid Black Flat Bottom Polystyrene Non-treated Microplates | Corning | 3694 | White plates are preferable, but it is possible to use clear plates if FOB content is high |
| Azoxymethane 25 mg | Santa Cruz Biotechnology | 25843-45-2 | |
| Dextran sodium sulfate | MP Biomedicals | 9011-18-1 | |
| Hemoccult Single Slides Kit | Beckman Coulter | 60151 | |
| Hemoglobinometer and accompanying test strips | Mission Inc. | C111-3021 | |
| Hydrogen Peroxide 30% | BioLab Ltd. | 05-084 | |
| Luminol | Sigma | A8511-5G | |
| Luminometer/ spectrophotometer: SpectraMax i3x Multi-Mode Microplate Reader | Molecular Devices | i3x | |
| Sodium hydroxide | BioLab Ltd. | 1908059100 |
参考文献
- Klimeck L, Heisser T, Hoffmeister M, Brenner H. Colorectal cancer: A health and economic problem. Best Pract Res Clin Gastroenterol. 2023;66:101839.
- Bürtin F, Mullins CS, Linnebacher M. Mouse models of colorectal cancer: Past, present and future perspectives. World J Gastroenterol. 2020;26(13):1394.
- Karim BO, Huso DL. Mouse models for colorectal cancer. Am J Cancer Res. 2013;3(3):240.
- Dzhalilova D, Zolotova N, Fokichev N, Makarova O. Murine models of colorectal cancer: The azoxymethane (AOM)/dextran sulfate sodium (DSS) model of colitis-associated cancer. PeerJ. 2023;11:e16159.
- Neto Í, Rocha J, Gaspar MM, Reis CP. Experimental murine models for colorectal cancer research. Cancers. 2023;15(9):2570.
- Li C, Lau HCH, Zhang X, Yu J. Mouse models for application in colorectal cancer: Understanding the pathogenesis and relevance to the human condition. Biomedicines. 2022;10(7):1710.
- Young MR, et al. Monitoring of tumor promotion and progression in a mouse model of inflammation-induced colon cancer with magnetic resonance colonography. Neoplasia. 2009;11(3):237-IN231.
- Han Z, et al. In viv.o staging the progression of colitis and associated cancer by concurrent microimaging of key biomarkers. Anal Chem. 2023;95(27):10298-10308.
- Ileva LV, et al. In vivo. MRI virtual colonography in a mouse model of colon cancer. Nat Protoc. 2014;9(11):2682-2692.
- Freeling JL, Rezvani K. Assessment of murine colorectal cancer by micro-ultrasound using three-dimensional reconstruction and non-linear contrast imaging. Mol Ther Methods Clin Dev. 2016;5:16070.
- Bull-Henry K, Al-Kawas FH. Evaluation of occult gastrointestinal bleeding. Am Fam Physician. 2013;87(6):430-436.
- Kaur K, Zubair M, Adamski JJ. Fecal Occult Blood Test. StatPearls Publishing, Treasure Island, FL (2023).
- Park DI, et al. Comparison of guaiac-based and quantitative immunochemical fecal occult blood testing in a population at average risk undergoing colorectal cancer screening. Am J Gastroenterol. 2010;105(9):2017-2025.
- Park AM, Tsunoda I. Forensic luminol reaction for detecting fecal occult blood in experimental mice. Biotechniques. 2018;65(4):227-230.
- Rose AL, Waite TD. Chemiluminescence of luminol in the presence of iron(II) and oxygen: Oxidation mechanism and implications for its analytical use. Anal Chem. 2001;73(24):5909-5920.
- Kulmala S, et al. Chemiluminescence of luminol induced by dissolution of oxide-covered aluminum in alkaline aqueous solution. Anal Chim Acta. 2002;453(2):253-267.
- Tawa R, Sakurai H. Determination of four active oxygen species such as H₂O₂, •OH, •O₂⁻, and 1O₂ by luminol- and CLA-chemiluminescence methods and evaluation of antioxidative effects of hydroxybenzoic acids. Anal Lett. 1997;30(15):2811-2825.
- White EH, Zafiriou O, Kagi HH, Hill JH. Chemiluminescence of luminol: The chemical reaction. J Am Chem Soc. 1964;86(5):940-941.
- Wykoff A. Qualitative analysis of luminol efficacy on bleach-cleaned and paint-concealed blood. Themis Research Journal of Justice Studies and Forensic Science. 2020;8(1):1.
- Schreuders EH, et al. Guaiac-based faecal occult blood tests versus faecal immunochemical tests for colorectal cancer screening in average-risk individuals. Cochrane Database Syst Rev. 2022;(6).
- Lansdorp-Vogelaar I, et al. Cost-effectiveness of high-performance biomarker tests vs fecal immunochemical test for noninvasive colorectal cancer screening. Clin Gastroenterol Hepatol. 2018;16(4):504-512.e511.
- Teilmann A, Kalliokoski O, Sørensen DB, Hau J, Abelson KS. Manual versus automated blood sampling: Impact of repeated blood sampling on stress parameters and behavior in male NMRI mice. Lab Anim. 2014;48(4):278-291.
- Kuriyama M, et al. Prediction of flare-ups of ulcerative colitis using quantitative immunochemical fecal occult blood test. World J Gastroenterol. 2010;16(9):1110.
- Lee MW, Pourmorady JS, Laine L. Use of fecal occult blood testing as a diagnostic tool for clinical indications: A systematic review and meta-analysis. Am J Gastroenterol. 2020;115(5):662-670.
- Foell D, Wittkowski H, Roth J. Monitoring disease activity by stool analyses: From occult blood to molecular markers of intestinal inflammation and damage. Gut. 2009;58(6):859-868.
- Kok L, et al. Diagnostic accuracy of point-of-care fecal calprotectin and immunochemical occult blood tests for diagnosis of organic bowel disease in primary care: The cost-effectiveness of a decision rule for abdominal complaints in primary care (CEDAR) study. Clin Chem. 2012;58(6):989-998.
- Schmöle AC, et al. Cannabinoid receptor 2 deficiency results in reduced neuroinflammation in an Alzheimer's disease mouse model. Neurobiol Aging. 2015;36(2):710-719.
- Thaker AI, Shaker A, Rao MS, Ciorba MA. Modeling colitis-associated cancer with azoxymethane (AOM) and dextran sulfate sodium (DSS). J Vis Exp. 2012;67:4100.
- Moser A, et al. ApcMin: A mouse model for intestinal and mammary tumorigenesis. Eur J Cancer. 1995;31(7-8):1061-1064.
- Khan P, et al. Luminol-based chemiluminescent signals: Clinical and non-clinical application and future uses. Appl Biochem Biotechnol. 2014;173(2):333-355.
- Iden JA, et al. The anti-tumorigenic role of cannabinoid receptor 2 in colon cancer: A study in mice and humans. Int J Mol Sci. 2023;24(4):4060.
- Iden JA, et al. Immunomodulatory function of cannabinoid receptor 2 and its agonist osteogenic growth peptide in health and cancer: A study in mice and humans. Oncogene. 2025:1-11.
- Wang J, Fernald AA, Anastasi J, Le Beau MM, Qian Z. Haploinsufficiency of APC leads to ineffective hematopoiesis. Blood. 2010;115(17):3481-3488.
- Fu Y, et al. Comparison of non-invasive biomarkers faecal BAFF, calprotectin and FOBT in discriminating IBS from IBD and evaluation of intestinal inflammation. Sci Rep. 2017;7(1):2669.
重印与许可
本文已发表
视频即将推出