This methodological study develops a pharmacy-led framework for root cause analysis of medication safety events. It integrates the Fishbone Diagram and the 5Whys systems engineering initiative for patient safety (SEIPS) into a four-stage closed-loop management framework, uses two cases to illustrate practical application, and discusses requirements for subsequent framework validation.
研究文章
Development of a Pharmacy-Led Root Cause Analysis Framework for Medication Safety Events
本文内容
摘要
摘要
Medication-related safety events are a key concern in healthcare quality. Their systemic nature demands effective analytical approaches. Root cause analysis (RCA) is vital for identifying system flaws and preventing recurrence, yet traditional methods often lack comprehensiveness, necessitating a more systematic framework. From a pharmacy perspective, this study developed a closed-loop management framework with four stages: preparation, cause analysis, solution implementation, and outcome evaluation. It innovatively proposes a three-dimensional "Fishbone Diagram-5Why-SEIPS" model. By integrating panoramic scanning, in-depth excavation, and system positioning, it balances analytical breadth and depth for systematic medication safety analysis. Pharmacy departments play four core RCA roles: technical expert/analyst, communication coordinator, system improvement driver, and safety culture advocate. This evolution reflects a shift from "product-centered" to "patient-centered" pharmacy services. The study provides methodological guidance for pharmacy-led safety improvement, supporting a shift from passive response to active prevention in medication safety. Healthcare institutions should recognize the strategic value of pharmacy in quality management to build a safer medication environment.
引言
Medication safety is fundamental to patient care, yet medication-related safety events remain a major global healthcare challenge1. The WHO estimates that medication errors cost up to $42 billion annually—reflecting not only economic loss but also a serious threat to patient well-being2. Such events rarely stem from individual negligence or a single failure; rather, they result from breaches across multiple layers of defense within a complex healthcare system. Thus, assigning blame to individuals is neither fair nor effective in preventing recurrence. Root cause analysis (RCA), adapted from high-risk industries, is a structured method for examining why a system permitted an event rather than stopping at the person closest to it3,4. In medication safety, RCA can connect proximal actions with latent weaknesses in task design, technology, workflow, environment, and governance. A pharmacy perspective is methodologically useful because medication use crosses prescribing, procurement, storage, dispensing, administration, monitoring, and governance, while pharmacy maintains visibility across much of this pathway5,6. Pharmacists contribute drug-specific knowledge, access to dispensing and prescribing information, familiarity with medication workflows, and routine links with clinical, nursing, information-technology, and quality-management teams. These capabilities support both causal analysis and the translation of findings into formulary, packaging, storage, decision-support, education, and monitoring changes.
Existing literature describes general RCA processes, individual tools, human factors models, and medication-event cases7. However, practical guidance remains limited on how a pharmacy team should order and integrate complementary methods, distinguish evidence from hypotheses, translate verified causes into interventions, and evaluate whether improvements are sustained. This study, therefore, aimed to develop an operational pharmacy-led RCA framework for medication safety events. The objectives were to: (1) define a four-stage closed-loop process; (2) integrate Fishbone analysis, Five Whys, and SEIPS into a reproducible sequence; (3) demonstrate the sequence using domestic and international medication-safety cases; (4) map pharmacy functions across the process; and (5) specify limitations and a prospective validation plan. Literature was used as a narrative methodological support, not as a systematically selected sample of studies.
方案
Methodological framework development
This study describes the development of a methodological framework for root cause analysis of medication safety events. Framework design was guided by a targeted narrative review of literature in root cause analysis, medication safety, pharmacy practice, and human factors. The study focused on structuring a complete and operational RCA workflow, including defined stages, decision points, analytical components, and evaluation mechanisms.
Design requirements
The framework was constructed to meet five requirements relevant to pharmacy practice: multidisciplinary participation; traceable use of event evidence; sufficient breadth to avoid premature fixation; sufficient depth to reach modifiable system conditions; and a feedback mechanism linking interventions with predefined measures. These requirements were translated into four stages: preparation and initiation, cause analysis, plan development and implementation, and effect evaluation and feedback (Figure 1)8,9,10. Evidence Inputs and Team Formation: Once an event is selected for RCA, a multidisciplinary team should be formed promptly and include a leader, pharmacists, involved staff, relevant clinical and nursing representatives, information technology or equipment expertise when required, and a manager authorized to authorize change. Pharmacy coordinates a structured evidence inventory covering medicines and packaging, prescriptions and dispensing records, administration documentation, relevant policies, interviews, environmental observations, and electronic audit trails11,12. Each item is recorded as a verified fact, an unresolved inconsistency, or a hypothesis requiring confirmation.
Analytical architecture
The three tools were assigned non-duplicative functions. Fishbone analysis provides a broad scan of potential contributors; Five Whys examines selected causal chains in depth; and SEIPS checks the identified conditions against interacting work-system dimensions and supports intervention design13,14,15,16,17,18. The tools are used sequentially but iteratively: SEIPS mapping may reveal a missing Fishbone branch or require another causal question. Step 1 Event Definition and Fishbone Scan: The team writes a neutral problem statement specifying the observed event, expected process, setting, time, and immediate consequence. Candidate contributing factors are then organized under personnel, method, material, machine or technology, environment, and management categories (Figure 2). Each proposed factor was linked to the available evidence and classified as either verified or requiring further investigation.
Five whys and step 3 SEIPS validation
Priority Fishbone branches are selected according to evidentiary support, causal proximity, severity, and modifiability. Repeated why-questions continue until the team reaches a correctable system condition, evidence no longer supports another step, or the issue falls outside the organization's reasonable control. Multiple chains may be retained. Candidate causes are then mapped to the SEIPS dimensions of person, tasks, tools and technology, physical environment, and organization. Candidate causes were retained only when they were supported by the available evidence and consistent with the reconstructed event process17,18.
Intervention design
Verified system conditions are translated into actions at the corresponding system level. Stronger actions that redesign storage, workflow, technology, standardization, or governance are prioritized when feasible; education or reminders are used as supporting measures rather than the sole response to structural causes19,20,21. Potential unintended consequences and resource requirements are considered before implementation.
Implementation specification
Each action is documented with an owner, responsible departments, completion date, required resources, implementation-fidelity measure, outcome measure, balancing measure, and review date22. The pharmacy coordinates technical content and cross-departmental agreement, while hospital management provides authority and resources for system-level changes.
Evaluation and feedback
Process indicators may include completion of storage separation, barcode scanning, alert acceptance, teach-back use, or independent-check compliance. Outcome indicators may include medication-error and near-miss rates defined with stable denominators. Balancing measures monitor workload, alert burden, delays, workarounds, and unintended risk transfer. Failure to meet a predefined target returns the team to evidence review and causal analysis, thereby closing the loop.
Case-based demonstration
Two contrasting medication-safety cases were selected to demonstrate the application of the framework. The domestic insulin-use case represents a recurrent medication-use and patient-education problem, whereas the published Italian heparin case represents a high-harm event involving packaging, storage, checking, and governance. The published Italian heparin case illustrates a high-harm event involving packaging, storage, checking, and governance23. For each case, the demonstration records the event, Fishbone domains, selected Five Whys chain, SEIPS mapping, interventions, and available outcome information. The two cases were analyzed using the same framework to demonstrate its application across medication-safety events with different characteristics and levels of severity.
Framework outputs and validation plan
The expected outputs are a verified evidence inventory, a causal map, one or more evidence-supported causal chains, a SEIPS work-system map, an action register, and an evaluation dashboard. Future validation should assess usability, completion time, agreement between independent RCA teams, completeness of factor identification, proportion of actions directed at system conditions, implementation fidelity, event outcomes, balancing measures, and transferability across hospital settings.
结果
Framework outputs and case demonstration
The development process produced a four-stage cycle and six operational steps. The method requires the team to retain a traceable link between evidence, candidate factors, causal chains, SEIPS dimensions, actions, and measures. The following cases show how that record can be constructed; they do not test comparative effectiveness.
Domestic insulin use example
The Fishbone scan identified candidate factors relating to patient knowledge, education tasks, insulin-pen materials, demonstration tools, the discharge environment, and organizational ownership. A priority chain began with incorrect pen use: why was the device used incorrectly, why was the misunderstanding not identified, why was teaching provided without standardized demonstration and teach-back, and why were resources and accountability for medication education insufficient? This chain shifted the analytical endpoint from patient error to modifiable education design and governance conditions. SEIPS mapping located the conditions across person (health literacy and prior experience), tasks (preparation and administration steps), tools and technology (limited visual or video aids), environment (time-limited discharge teaching), and organization (non-standard education and unclear ownership). Corresponding actions included standardized illustrated and video instructions, teach-back, and access to pharmacy consultation. The available case description reported improvement after six months but did not provide a denominator, sample size, comparator, or statistical analysis; no effect estimate is therefore claimed.
Published Italian heparin case
Fishbone analysis identified similar packaging, adjacent storage of concentrations, ineffective checks, and vulnerabilities spanning procurement to administration23. Five Whys linked selection and detection failures to absent separation standards, weak forcing functions, and fragmented governance. SEIPS mapping placed the conditions in tools and technology, tasks, physical environment, and organization rather than attributing the event to a single operator. The mapped conditions support layered actions such as physical separation and standardization of high-alert medicines, barcode medication administration, unit-dose dispensing, and formal pharmacy-nursing governance. These actions demonstrate cause-to-intervention alignment, but the published event investigation does not isolate the independent effect of each intervention.
Cross-case methodological findings
In both demonstrations, Fishbone analysis expanded the search space, Five Whys developed selected causal chains, and SEIPS exposed interactions and guided system-level action. The examples also identified a reporting requirement for the framework: when denominators, sample sizes, comparator data, or implementation measures are unavailable, the limitation must be recorded rather than replaced with an unsupported quantitative claim.
Pharmacy Functions Within the Framework
Four pharmacy functions were mapped to the framework: technical analysis, multidisciplinary coordination, system-improvement delivery, and safety learning. These functions are methodological role assignments intended to clarify responsibility at each stage. They are not presented as roles derived from a systematic synthesis or as empirically proven determinants of outcome24,25.
Pharmacist as technical expert and analysis leader
This foundational RCA role requires pharmacists to move beyond traditional information consultation to become architects of the analytical process and arbiters of technical drug-related issues. Specifically, they must clarify all medication details—standard and maximum doses, pharmacological properties, compatibility, and administration routes26. These judgments form the cornerstone for correct analysis, preventing unfounded discussions. Regarding methodology, pharmacists should be skilled in guiding teams through the creation of Fishbone Diagrams, applying the Five Whys, and explaining SEIPS system concepts. Crucially, they must use specialized knowledge in pharmacokinetics and pharmacodynamics to assess event likelihood and causality, providing a scientific basis for the analysis.
Communication coordinator and team builder
The pharmacy department’s unique position naturally bridges multiple stakeholders. Through daily collaboration with clinical, nursing, and management teams, pharmacists often serve as team facilitators. This role requires strong communication skills—translating clinical issues for clinicians, while framing improvement proposals in terms of risk control and cost-effectiveness for management27. When interdepartmental disagreements arise, pharmacists can leverage their relatively neutral standing to steer discussions toward objective data and standard procedures, fostering consensus28. Moreover, they should model a non‑punitive safety culture by avoiding blame‑oriented language and promoting an open, system‑focused team environment through professional demeanor29.
System improvement designer and driver
This role marks the pharmacist's transition from analyst to implementer30. Pharmacists must move beyond problem identification to become solution architects and project managers for the improvement process. They are required to translate RCA findings into actionable changes—for instance, advancing P&T Committee decisions on packaging, revising SOPs for process flaws, or developing alert systems and training for knowledge gaps. Crucially, pharmacists must proactively coordinate resources across departments to optimize IT systems, workflows, and policies. This involves collaborating with IT on prescription rules, co-designing high-alert medication processes with nursing, and proposing medication safety metrics for performance reviews. Throughout, pharmacists must track implementation, overcome resistance, and ensure measures are effectively executed and deliver intended results31.
Safety culture advocate and educator
In this role, pharmacists transform individual incident knowledge into institutional wisdom. They are tasked with converting RCA insights into educational content—such as integrating case studies into training programs, sharing lessons via pharmacy bulletins and internal platforms, and establishing medication safety alerts. Through new-employee orientation, continuing education, and inter-departmental exchanges, these efforts help prevent similar errors elsewhere and nurture an open, learning-oriented safety culture across the hospital. By consistently educating and advocating, pharmacists turn one-time RCA outcomes into a sustained driver of organizational improvement, ultimately reshaping the institution’s safety ecosystem.
In summary, the four pharmacist roles in RCA form a progressive path from technical core to strategic leader. This model demands that modern pharmacists possess not only expert knowledge but also systems thinking, change management, communication, and leadership skills. By fulfilling this evolution, the pharmacy department can solidify its indispensable value within healthcare quality and safety systems, thereby offering stronger protection for patient safety32.
DATA AVAILABILITY:
All data generated or analyzed during this study are available at the URL: https://zenodo.org/records/23027239.
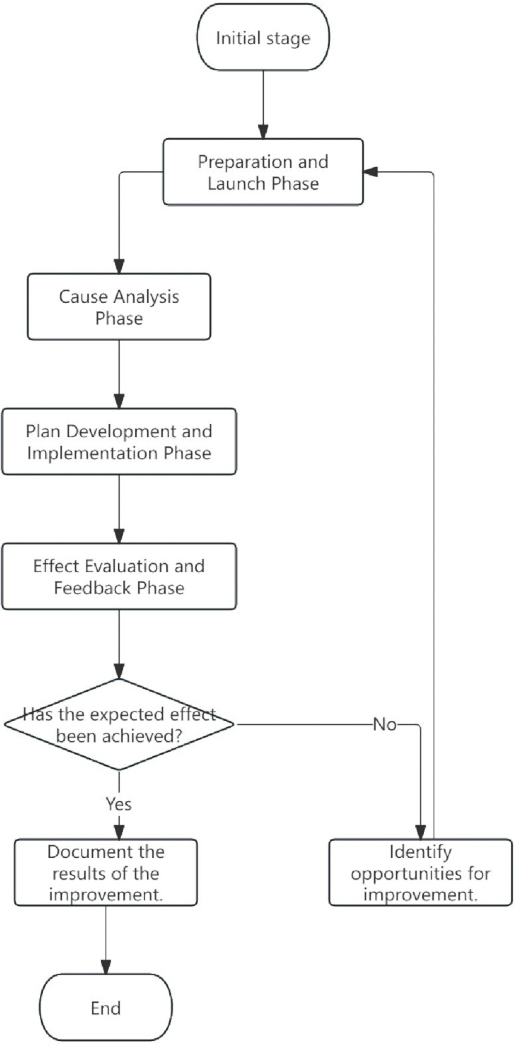
Figure 1: Four-stage closed-loop management framework for pharmacy-led root cause analysis of medication safety events. The process begins at the Initial stage and proceeds through the preparation and launch phase, cause analysis phase, plan development and implementation phase, and effect evaluation and feedback phase. If the expected effect has been achieved (Yes), the results of the improvement are documented, and the process ends. If the expected effect has not been achieved (No), opportunities for improvement are identified, and the process returns to the Preparation and Launch Phase, forming a continuous improvement cycle. Please click here to view a larger version of this figure.
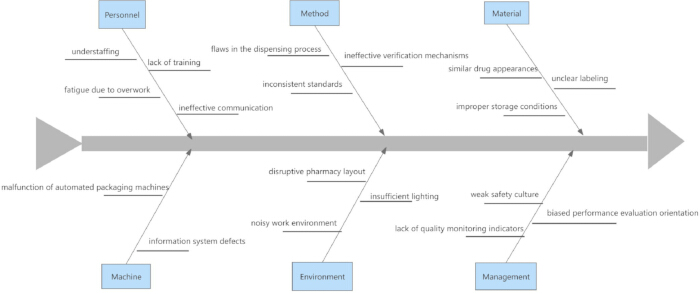
Figure 2: Fishbone diagram for organizing candidate contributing factors to medication safety events. Factors are grouped into six categories: Personnel (understaffing, lack of training, fatigue due to overwork, and ineffective communication), Method (flaws in the dispensing process, inconsistent standards, and ineffective verification mechanisms), Material (similar drug appearances, unclear labeling, and improper storage conditions), Machine (malfunction of automated packaging machines and information system defects), Environment (disruptive pharmacy layout, insufficient lighting, and noisy work environment), and Management (weak safety culture, biased performance evaluation orientation, and lack of quality monitoring indicators). The central arrow represents the medication-use process, and the other arrows indicate the potential influence of these factors on medication safety events. Please click here to view a larger version of this figure.
讨论
This study developed an operational method for pharmacy-led RCA of medication safety events. Its principal contribution is the explicit connection between evidence collection, complementary causal tools, intervention design, and outcome feedback. Narrative literature and two cases supported conceptual development and demonstration, but they were not used as a systematic evidence sample.
The Fishbone-Five Whys-SEIPS sequence addresses complementary analytical needs. Fishbone analysis promotes breadth, Five Whys develops depth along selected chains, and SEIPS tests whether candidate causes and solutions account for interactions within the work system33,34,35,36,37. The sequence may improve transparency by requiring each proposed action to be traced back to evidence and a mapped system condition. However, the present study does not establish superiority over other RCA frameworks. The four pharmacy functions organize responsibility across the method. Technical analysis anchors medication-specific judgments; coordination supports multidisciplinary evidence review; improvement delivery converts findings into operational change; and safety learning carries results into monitoring, education, and governance. This mapping is a design output that requires empirical evaluation, not a definitive taxonomy derived from systematic coding.
Despite RCA’s recognized value, pharmacy departments face multiple practical challenges38,39,40, including resource constraints (limited time, tools, and training), interdepartmental communication barriers, and institutional perceptions that confine pharmacy to traditional service roles. To address these, the authors recommend a tiered strategy: organizationally, integrate pharmacy into the core safety management structure with clear leadership in medication events; operationally, allocate dedicated time and resources for quality improvement; and professionally, enhance pharmacist training in systems thinking, change management, and quality leadership.
Advancing medical digitalization offers important opportunities for methodological and technological innovation in RCA. Big data analytics will play an increasingly vital role in medication safety risk prediction, shifting the focus from reactive response to proactive prevention through mining and analyzing large-scale medical data. Artificial Intelligence (AI) can support the RCA process, using natural language processing (NLP) to parse event reports and machine learning (ML) to detect risk patterns—improving analytical efficiency and accuracy. The evolution of intelligent pharmacy management systems will also provide more technical solutions for system improvement, such as real-time intelligent prescription review and automated medication processes. These technologies will not only reshape RCA implementation but also expand the scope of pharmacy's role in patient safety, warranting proactive attention and planning by the profession. This study has several limitations. Framework construction involved conceptual synthesis and case demonstration rather than a formal consensus process or prospective trial. The cases were heterogeneous and were not selected as a representative sample. The domestic example lacked a reported denominator, sample size, comparator, and statistical analysis, while the international event report could not isolate the effects of individual interventions. The framework's usability, reproducibility, completeness, and effect on medication-safety outcomes therefore remain uncertain.
Prospective validation should proceed in stages. First, multidisciplinary users should assess clarity, feasibility, completion time, and missing content. Second, independent teams analyzing the same standardized cases should be compared for agreement in factor identification, causal chains, SEIPS mapping, and action strength. Third, multicenter implementation studies should prespecify event definitions, denominators, follow-up periods, implementation-fidelity measures, medication-error and near-miss outcomes, and balancing measures. Comparative studies should then examine whether the integrated method offers advantages over existing RCA procedures.
This methodological study developed a pharmacy-led RCA framework that integrates Fishbone analysis, Five Whys, and SEIPS within a four-stage improvement cycle. Two cases demonstrate how the method links event evidence to system conditions, actions, and evaluation measures. The framework and mapped pharmacy functions are development outputs rather than evidence of effectiveness. Their value depends on disciplined documentation, multidisciplinary participation, local adaptation, and explicit measurement. Prospective usability, reproducibility, and outcome studies are required before comparative benefit can be claimed. Until then, the framework should be used as a structured method for local testing and refinement.
披露
None of the authors has any personal, financial, commercial, or academic conflicts of interest.
致谢
This work was supported by "Shandong Pharmaceutical Association – Tianqing 'Making a Difference in Pharmaceuticals' Academic Research Grant". Project Title: Research on the Design and Implementation of an Automated Adverse Drug Reaction Early Warning System Based on Clinical Data. (No. Kjyw 2024-21)
材料
| 姓名 | 公司 | 目录编号 | 评论 |
|---|---|---|---|
| Fishbone Diagram (Cause-and-Effect Diagram) | Union of Japanese Scientists and Engineers (JUSE) / Kaoru Ishikawa | Ishikawa K. Guide to Quality Control. 1986 | |
| Five Whys (5 Whys) Analysis | Toyota Motor Corporation | Ohno T. Toyota Production System. 1988 | |
| SEIPS Model | University of Wisconsin–Madison | Carayon et al. Qual Saf Health Care. 2006;15(Suppl 1):i50-8. doi:10.1136/qshc.2005.015842 | |
| SEIPS 2.0 Framework | University of Wisconsin–Madison | Holden et al. Ergonomics. 2013;56(11):1669-86. doi:10.1080/00140139.2013.838643 | |
| Pharmacy-led RCA Framework | Authors of the present study | This manuscript | |
| Illustrated medication-use instructions | Authors’ institution | Institutionally developed | |
| Video medication-use instructions | Authors’ institution | Institutionally developed |
参考文献
- Han JM et al. Medication-related incidents in acute care hospitals among different age groups: an analysis of national patient safety report data. Pharmacoepidemiol Drug Saf. 2024;33(6):e5819.
- World Health Organization. WHO calls for urgent action by countries for achieving Medication Without Harm. Geneva: World Health Organization; 2022 Sep 16. Available from: https://www.who.int/news/item/16-09-2022-who-calls-for-urgent-action-by-countries-for-achieving-medication-without-harm
- Srinivasaragavan D, Ramalingam K, Ramani P. Root cause analysis: unraveling common laboratory challenges. Cureus. 2024;16(2):e53393.
- Johna S, Tang T, Saidy M. Patient safety in surgical residency: root cause analysis and the surgical morbidity and mortality conference--case series from clinical practice. Perm J. 2012;16(1):67-69.
- Ferreira-Alfaya FJ, Cura Y, Zarzuelo-Romero MJ. Advancing pharmaceutical practice: promoting organizational health literacy to improve medication use through an intersectoral model based on the preventive medicine framework. Res Social Adm Pharm. 2025;21(12):1096-1105.
- Ryan M, Zapata EH, Weru I, Cracknell ANV. Global oncology pharmacy service levels and knowledge requirements: a review by the International Society of Oncology Pharmacy Practitioners. J Oncol Pharm Pract. 2025;31(7):1104-1114.
- Barreto EDG et al. Root cause analysis of safety incidents in antineoplastic use in children. Rev Bras Enferm. 2024;77(Suppl 3):e20230139.
- Genet A, Bogner K, Goertz R, Böhme S, Leverkus F. Safety analysis of new medications in clinical trials: a simulation study to assess the differences between cause-specific and subdistribution frameworks in the presence of competing events. BMC Med Res Methodol. 2023;23(1):168.
- Holle LM et al. International Society of Oncology Pharmacy Practitioners (ISOPP) position statement: role of the oncology pharmacy team in cancer care. J Oncol Pharm Pract. 2021;27(4):785-801.
- Osae SP, Rotelli A. Pharmacist-led annual wellness visits: a review. J Pharm Pract. 2021;34(2):295-305.
- Pérez-Encinas M et al. 2019 SEFH National Survey: service portfolio, care activities, education and research in Spain's hospital pharmacy departments. Farm Hosp. 2021;45(1):32-40.
- Hearn EB et al. Evaluation of a novel process for selecting advanced pharmacy practice experiences. Curr Pharm Teach Learn. 2021;13(10):1300-1305.
- Pradhan SK, Jans M, Martin N. Getting the data in shape for your process mining analysis: an in-depth analysis of the pre-analysis stage. ACM Comput Surv. 2025;57(6):159.
- Al-Rifai M. Unlocking insights: evaluating 5Whys methodology for root cause analysis and employee problem-solving skills in 91 case studies. Int J Lean Six Sigma. 2025;16(5):1276-1304.
- Shore S et al. Non-patient factors associated with infections in LVAD recipients: a scoping review. J Heart Lung Transplant. 2022;41(1):1-16.
- Cooper JB, Lee S, Jeter E, Bradley CL. Mindset and team communication in pharmacists: examination of pharmacist's self-views. J Am Pharm Assoc (2003). 2022;62(1):55-62.
- Holden RJ et al. SEIPS 2.0: a human factors framework for studying and improving the work of healthcare professionals and patients. Ergonomics. 2013;56(11):1669-1686.
- Carayon P et al. Work system design for patient safety: the SEIPS model. Qual Saf Health Care. 2006;15(Suppl 1):i50-i58.
- Wang H, Tao D, Yan M. Effects of text enhancement on reduction of look-alike drug name confusion: a systematic review and meta-analysis. Qual Manag Health Care. 2021;30(4):233-243.
- Alshahrani F, Marriott JF, Cox AR. A qualitative study of prescribing errors among multi-professional prescribers within an e-prescribing system. Int J Clin Pharm. 2021;43(4):884-892.
- Gjone H et al. Exploring the time required by pharmacists to prepare discharge medicine lists: a time-and-motion study. Int J Clin Pharm. 2022;44(4):1028-1036.
- Shafiee Hanjani L, Apostolidis A, Winckel K, Burrows JA. An evaluation of the utilisation of the Medication Action Plan form in a tertiary hospital: what is the impact of the pharmacist? J Pharm Pract Res. 2017;47(4):257-262.
- Di Fazio N et al. Fourteen deaths from suspected heparin overdose in an Italian primary-level hospital. Diagnostics (Basel). 2023;13(21):3361.
- Holdsworth MT, Bond R, Parikh S, Yacop B, Wittstrom KM. Root cause analysis design and its application to pharmacy education. Am J Pharm Educ. 2015;79(7):99.
- Misko J, Rawlins MDM, Jenkins B. Scoping research output from tertiary hospital pharmacy departments: suggestions for improvement. J Pharm Pract Res. 2022;52(5):402-403.
- Mononen N et al. A national approach to medicines information research: a systematic review. Res Social Adm Pharm. 2018;14(12):1106-1124.
- Dietrich SK, Bushong BT, Schneider-Smith EA, Mixon MA. Emergency medicine pharmacist interventions reducing exposure to costs (EMPIRE-C). Am J Emerg Med. 2022;54:178-183.
- Setia S, Ryan NJ, Nair PS, Ching E, Subramaniam K. Evolving role of pharmaceutical physicians in medical evidence and education. Adv Med Educ Pract. 2018;9:777-790.
- Baker S, Lee YP, Hattingh HL. An evaluation of the role of practice pharmacists in Australia: a mixed methods study. Int J Clin Pharm. 2019;41(2):504-515.
- Roman C, Edwards G, Dooley M, Mitra B. Roles of the emergency medicine pharmacist: a systematic review. Am J Health Syst Pharm. 2018;75(11):796-806.
- Nchinech N, Bousliman Y. Intégration du pharmacien clinicien dans un service médical, c’est du classique ! Et si on inversait les rôles ? PhaCli. 2024;59(2):e136.
- Hazen ACM et al. Learning through boundary crossing: professional identity formation of pharmacists transitioning to general practice in the Netherlands. Acad Med. 2018;93(10):1531-1538.
- Miller KS. Comparing the effects of traditional education and root-cause analysis on nursing students' attitudes about safety culture and knowledge of safe medication administration practices: an experimental study. Nurse Educ. 2022;47(3):139-144.
- Kumah A et al. Cause-and-effect (fishbone) diagram: a tool for generating and organizing quality improvement ideas. Glob J Qual Saf Healthc. 2024;7(2):85-87.
- Saad M, de Medeiros R. Programs of religious/spiritual support in hospitals - five "Whies" and five "Hows". Philos Ethics Humanit Med. 2016;11(1):5.
- Strauven G et al. Development of a process-oriented quality improvement strategy for the medicines pathway in nursing homes using the SEIPS model. Res Social Adm Pharm. 2020;16(3):360-376.
- Steele ML, Talley B, Frith KH. Application of the SEIPS model to analyze medication safety in a crisis residential center. Arch Psychiatr Nurs. 2018;32(1):7-11.
- Mair A, Wilson M, Dreischulte T. Addressing the challenge of polypharmacy. Annu Rev Pharmacol Toxicol. 2020;60:661-681.
- Ranchon F et al. Oncology pharmacy practice: key insights, challenges, and perspectives - a position paper from the French Society for Oncology Pharmacy (SFPO). Ann Pharm Fr. 2025;83(6):1040-1052.
- Bondi DS et al. Addressing challenges of providing remote inpatient clinical pharmacy services. J Am Coll Clin Pharm. 2021;4(12):1594-1600.