This study assessed the association between adjunctive butylphthalide plus antiplatelet therapy after intravenous thrombolysis and functional recovery in acute ischemic stroke. Combination therapy was associated with better 90-day functional outcomes, with no significant between-group difference in the assessed adverse events.
研究文章
Association of Butylphthalide Combined with Antiplatelet Therapy with Functional Recovery After Intravenous Thrombolysis in Acute Ischemic Stroke
本文内容
摘要
摘要
Intravenous thrombolysis (IVT) is an established treatment for acute ischemic stroke, but functional outcomes remain suboptimal, and real-world evidence regarding adjunctive butylphthalide therapy is limited. This single-center retrospective observational study evaluated the association between adjunctive butylphthalide plus antiplatelet therapy and functional recovery after IVT in 118 patients with acute ischemic stroke treated between January 2024 and December 2025. Patients were classified by post-thrombolysis treatment: 62 received butylphthalide plus standard antiplatelet therapy, and 56 received standard antiplatelet therapy alone. After propensity score matching, 52 patients were retained in each group. The primary outcome was 90-day functional prognosis, with a modified Rankin Scale score of 0–2 defined as a favorable outcome. Secondary outcomes included National Institutes of Health Stroke Scale (NIHSS) score, infarct volume, cerebral blood flow (CBF) perfusion recovery, serum high-sensitivity C-reactive protein (hs-CRP), plasma D-dimer (D-D), Barthel Index (BI) score, and adverse events. Multivariable logistic regression was used to identify factors associated with poor 90-day functional prognosis. Baseline characteristics were balanced between the matched groups (all P > 0.05). At 90 days, the butylphthalide combination group had a higher rate of favorable functional prognosis than the antiplatelet-only group (73.1% vs. 48.1%, P = 0.009). The combination group also had lower NIHSS scores, smaller infarct volumes, lower hs-CRP and D-D levels, better CBF perfusion recovery, and higher BI scores (all P < 0.05). Adverse event rates did not differ significantly between groups (P = 0.631). Multivariable analysis identified the treatment regimen as independently associated with 90-day functional prognosis (P = 0.009). Adjunctive butylphthalide plus antiplatelet therapy after IVT was associated with better 90-day functional recovery in this retrospective cohort; however, the observational design does not permit causal inference, and the safety findings are limited to the prespecified events reported here.
引言
Acute ischemic stroke (AIS) is a leading cause of mortality and long-term disability worldwide and imposes an increasing burden on public health systems1. According to the World Health Organization, more than 12 million new stroke cases occur globally each year, with AIS accounting for approximately 85% of all cases2. The incidence of stroke has also shown an increasing trend among younger populations. In China, stroke is a leading cause of death and long-term disability, resulting in substantial health, social, and economic burdens3. Intravenous thrombolysis (IVT) is an established early reperfusion strategy for AIS. Recombinant tissue plasminogen activator (rt-PA) promotes thrombus dissolution and restoration of blood flow in occluded cerebral vessels. However, favorable outcomes are not achieved in all patients receiving standardized IVT4. Nearly half of treated patients do not regain functional independence at 90 days, and early neurological deterioration occurs in approximately 20% of cases, limiting the overall clinical benefits of conventional thrombolytic therapy5.
Poor functional recovery following thrombolytic therapy is associated with multiple pathophysiological processes, including cerebral ischemia-reperfusion injury6, the no-reflow phenomenon, inflammatory responses, oxidative stress, blood-brain barrier disruption, and secondary microthrombosis. The neurovascular unit concept has shifted research toward integrated protection of neurons, vascular endothelial cells, glial cells, and the extracellular matrix. Restoration of cerebral perfusion alone may not prevent progression of the ischemic penumbra to the infarct core7. Neuroprotective therapies administered after thrombolysis are intended to preserve ischemic penumbral tissue, reduce reperfusion-associated injury, and support neurological recovery and have therefore become an important area of stroke research8.
Antiplatelet therapy is a key component of secondary prevention after AIS and reduces the risk of recurrent vascular occlusion by inhibiting platelet aggregation9. However, antiplatelet therapy alone may have limited effects on ischemia-reperfusion injury, microcirculatory disturbances, and neuroinflammatory responses after thrombolysis10. Consequently, the combination of neuroprotective therapy with IVT and antiplatelet treatment has received increasing clinical attention. DL-3-n-butylphthalide is a neuroprotective agent that acts through multiple biological pathways11. Experimental studies indicate that butylphthalide may improve cerebral microcirculation, preserve mitochondrial function, modulate inflammatory responses, reduce oxidative stress, promote collateral circulation, and inhibit platelet aggregation12. These effects may contribute to improved cerebral blood flow (CBF) and reductions in infarct volume and cerebral edema. Randomized controlled trials have reported improvements in neurological deficits and higher rates of functional independence at 90 days among patients receiving butylphthalide13,14. However, many previous studies have included patients who did not receive thrombolytic therapy or have evaluated butylphthalide as an ultra-early intervention15. Evidence regarding early adjunctive butylphthalide administration after IVT, including its clinical outcomes and prespecified adverse events, therefore, remains limited.
Most studies evaluating butylphthalide in combination with IVT have been conducted as randomized controlled trials. The strict eligibility criteria and standardized treatment conditions used in such studies may differ from those in routine clinical practice16. Patients treated in real-world settings frequently have multiple comorbidities, receive concomitant therapies, and exhibit differences in treatment adherence. Studies specifically evaluating concurrent butylphthalide and standard antiplatelet therapy after IVT remain limited, and evidence from real-world clinical datasets is particularly scarce17. Antiplatelet therapy is commonly initiated after IVT in patients with AIS when clinically appropriate; however, the outcomes associated with adjunctive neuroprotective therapy under routine clinical conditions remain incompletely characterized18. Furthermore, few studies have simultaneously evaluated multidimensional outcomes, including infarct volume, CBF perfusion, inflammatory markers, and coagulation-related biomarkers. This evidence gap limits a comprehensive assessment of the clinical outcomes associated with combined treatment.
To address these clinical and research gaps, this single-center retrospective observational study evaluated real-world clinical data from patients with AIS who underwent IVT. The primary objective was to assess the association between adjunctive butylphthalide plus standard antiplatelet therapy and 90-day functional recovery. Secondary outcomes included neurological impairment, infarct volume, CBF perfusion, inflammatory markers, coagulation-related biomarkers, and prespecified adverse events. Multivariable logistic regression was used to identify factors independently associated with poor functional prognosis after thrombolysis. The study was designed to provide real-world evidence regarding post-IVT treatment strategies and to inform future prospective investigations. Given the observational design, causal relationships cannot be established, and the observed associations require validation in prospective randomized trials.
方案
All research procedures were performed in accordance with the principles of the Declaration of Helsinki. This retrospective study was reviewed and approved by the Xi'an Gaoxin Hospital Ethics Committee (Ethics approval No. GXYYEC-KTSB-2026-3-12). Because the study used de-identified retrospective clinical data, the ethics committee formally waived the requirement for written informed consent.
Study design
This single-center retrospective observational study screened clinical records of patients diagnosed with acute ischemic stroke (AIS) who received intravenous thrombolysis (IVT) at the study hospital between January 2024 and December 2025. A total of 122 patients were initially screened; 4 were excluded per the predefined exclusion criteria, leaving 118 patients eligible for analysis. Patients were classified into two cohorts according to the adjunctive treatment received after thrombolysis. The combination group comprised 62 patients who received butylphthalide plus standard antiplatelet therapy, whereas the antiplatelet-only group comprised 56 patients who received standard antiplatelet therapy alone. Propensity score matching (PSM) was performed to balance baseline characteristics. During matching, 10 patients from the combination group and 4 from the antiplatelet-only group were excluded because no suitable matches within the predefined caliper of 0.05 were identified in the opposite cohort. After PSM, 52 patients were retained in each group for subsequent analyses (Figure 1).
Inclusion criteria
Patients were included if they met the diagnostic criteria for AIS specified in the 2023 Chinese Guidelines for the Diagnosis and Treatment of AIS19. Acute ischemic lesions were confirmed by cranial computed tomography (CT) or magnetic resonance imaging (MRI), and hemorrhagic stroke was excluded. The interval from symptom onset to IVT had to be within 4.5 h, and standardized thrombolytic therapy had to be completed at the study hospital. Eligible patients were 18–85 years of age, with no restriction based on sex. Patients were required to have no contraindications to antiplatelet therapy after thrombolysis, with standard antiplatelet therapy initiated within 24 h after IVT. Patients were classified into the butylphthalide plus standard antiplatelet group or the antiplatelet-only group according to the treatment documented in the clinical records. Complete and traceable medication records, baseline data, and follow-up information were required. Patients with severe concurrent systemic diseases that could interfere with the evaluation of 90-day functional outcomes were not included.
Exclusion criteria
Patients were excluded if cranial CT or MRI confirmed intracerebral hemorrhage, subarachnoid hemorrhage, tumor-associated stroke, ruptured vascular malformation, or another hemorrhagic cerebrovascular disorder. Neurological deficits attributable to nonischemic causes, including intracranial tumors, intracranial infections, craniocerebral trauma, or demyelinating lesions, were also exclusion criteria. Patients were excluded if the interval from symptom onset to thrombolysis exceeded 4.5 h or if standardized thrombolytic therapy was not completed. Patients who subsequently underwent endovascular thrombectomy, stent implantation, or another revascularization procedure because of vascular reocclusion within 24 h after thrombolysis, as well as those whose thrombolytic treatment was discontinued because of severe adverse reactions, were excluded20. These criteria may have introduced substantial post-treatment selection bias. Because exclusion was applied after treatment-related events had occurred, patients with symptomatic intracranial hemorrhage, severe early neurological or systemic complications, discontinuation of thrombolysis, or the need for rescue revascularization were systematically removed from the analytical cohort. Such events are strongly associated with poor functional outcome and with adverse safety profiles; their exclusion can therefore preferentially remove poor outcomes, artificially inflate the observed rate of favorable functional recovery in both groups, and materially bias the estimated treatment effect and safety profile. In addition, because the likelihood of these events may differ between treatment arms, this selection mechanism could bias the between-group comparison in either direction rather than merely reducing precision. The treatment-effect estimates reported here should therefore be interpreted as associations observed in a selected survivor cohort rather than as unbiased estimates of the effect of adjunctive butylphthalide in all patients undergoing IVT.
Patients with severe hepatic or renal dysfunction were also excluded. Severe hepatic dysfunction was defined as transaminase levels exceeding three times the upper limit of normal, and severe renal dysfunction was defined as an estimated glomerular filtration rate lower than 30 mL·min⁻1 .1.73 m⁻2. Additional exclusion criteria included New York Heart Association (NYHA) class IV heart failure, severe pulmonary infection, and respiratory failure. Patients who developed symptomatic intracranial hemorrhage according to the European Cooperative Acute Stroke Study (ECASS) III criteria within 24 h after IVT or life-threatening systemic hemorrhagic complications requiring immediate discontinuation of antiplatelet therapy, butylphthalide were excluded21. Patients who developed severe cerebral edema, cerebral herniation, or other life-threatening complications within 72 h after thrombolysis were excluded. Severe cognitive impairment, persistent psychiatric disorders, advanced malignant tumors, multiple-organ failure, critical systemic infection, pregnancy, and lactation were additional exclusion criteria.
Data collection
Study variables were retrospectively retrieved from electronic medical records and standardized follow-up records. Baseline demographic and clinical information, National Institutes of Health Stroke Scale (NIHSS) scores, cranial CT or MRI findings, and routine laboratory results were collected within 24 h after hospital admission, and for all patients, prior to the initiation of antiplatelet therapy or butylphthalide treatment. Information related to IVT was collected within 24 h after completion of thrombolysis. Because antiplatelet therapy was initiated within 24 h after completion of thrombolysis, and butylphthalide was started after thrombolysis, all variables designated as baseline in this study were ascertained before the first dose of either adjunctive treatment; the timing of baseline measurement relative to treatment initiation was therefore uniform across patients. Treatment regimens were determined from inpatient medication records and medical orders.
Outcome data included the 90-day modified Rankin Scale (mRS) score, infarct volume assessed using diffusion-weighted imaging (DWI) and fluid-attenuated inversion recovery (FLAIR) sequences on follow-up MRI, cerebral blood flow (CBF) perfusion recovery, and the 90-day Barthel Index (BI) score. Prespecified adverse events were identified from inpatient records and follow-up documentation. No patients in the matched cohort were lost to follow-up; all 104 patients who completed PSM underwent the scheduled 90-day assessments, and complete outcome data were available for analysis.
Treating physicians were not blinded to the treatment received because of the retrospective study design. However, neurologists responsible for assessing the 90-day mRS, NIHSS, and BI outcomes were independent of the clinical treatment team and remained blinded to treatment-group status during outcome assessment. Standardized follow-up forms and predefined scoring criteria were used. Statistical analysts were also blinded to group allocation during data cleaning and preliminary analyses.
Therapeutic regimens
Treatment strategies were determined in accordance with routine clinical practice, applicable guideline recommendations, and individual clinical characteristics. All patients received adjunctive clinical management following standardized IVT.
Intravenous thrombolytic therapy
Thrombolytic therapy was administered intravenously at 0.9 mg/kg body weight, with a maximum dose of 90 mg. Ten percent of the total dose was administered as an intravenous bolus within 1 min, and the remaining 90% was infused over 60 min22.
Standard antiplatelet therapy
Standard antiplatelet therapy was initiated within 24 h after completion of thrombolysis. Single- or dual-agent antiplatelet therapy was administered according to individual clinical indications. Aspirin was administered orally at 100 mg once daily, and clopidogrel was administered orally at 75 mg once daily. When dual antiplatelet therapy was used, both agents were administered concurrently for at least 3 months23. The inclusion of both single- and dual-agent regimens introduced treatment heterogeneity and potential residual confounding, as these strategies differed in pharmacological intensity and risk profiles and were not evaluated separately in the primary model.
Butylphthalide intervention
Patients in the combination group received butylphthalide in addition to standard antiplatelet therapy. Butylphthalide was administered intravenously at 25 mg twice daily for 14 consecutive days. Treatment was subsequently transitioned to oral butylphthalide at 0.2 g three times daily, guided by clinical recovery, with a total treatment duration of at least 3 months. Patients in the antiplatelet-only group did not receive butylphthalide during the observation period24.
Primary outcome measure
Functional outcome was assessed using the mRS at 90 days after IVT. The mRS ranged from 0 to 6, with lower scores indicating less disability. Scores of 0–2 were classified as a favorable functional outcome, whereas scores of 3–6 were classified as a poor functional outcome25.
Secondary outcome indicators
NIHSS scores were obtained within 24 h after admission and again 90 days after IVT. The NIHSS assessed neurological impairment across major domains and ranged from 0 to 42, with higher scores indicating greater impairment25.
Infarct volume was assessed within 24 h after admission and at the 90-day follow-up. Brain MRI was performed using a 3.0-T system with DWI and FLAIR sequences. For DWI, the repetition time was 2,000 ms, the echo time was 80 ms, the slice thickness was 5 mm, and the interslice gap was 1 mm. For FLAIR, the repetition time was 8,000 ms, the echo time was 120 ms, the inversion time was 2,000 ms, the slice thickness was 5 mm, and the interslice gap was 1 mm. After image acquisition, lesion boundaries were delineated using image-analysis software, and infarct volume was calculated in cubic centimeters26.
CBF perfusion was evaluated within 24 h after admission and at 90 days after IVT using CT perfusion imaging. Scanning parameters included a tube voltage of 120 kV, tube current of 250 mA, slice thickness of 5 mm, and whole-brain coverage. Perfusion data were postprocessed to calculate regional cerebral blood flow (rCBF), cerebral blood volume (CBV), and mean transit time (MTT). Satisfactory CBF perfusion recovery was defined as ipsilateral rCBF ≥70% of that in the contralateral normal hemisphere. CBV and MTT were calculated as descriptive perfusion parameters but were not used to classify perfusion recovery. Patients who did not meet the rCBF criterion were classified as having poor perfusion recovery27.
For high-sensitivity C-reactive protein (hs-CRP) measurement, 3 mL of fasting venous blood was collected within 24 h after admission and at the 90-day follow-up. Samples were collected in serum separator tubes without anticoagulant and centrifuged at 3,000 × g for 10 min. Serum hs-CRP concentrations were measured using immunoturbidimetry, with a reference range of 0–3 mg/L28.
D-dimer (D-D) was measured at the same time points as hs-CRP. Blood was collected into EDTA-containing tubes and centrifuged to obtain plasma. D-D concentrations were measured using latex-enhanced immunoturbidimetry, with a reference range of 0–500 ng/mL FEU (0–0.5 mg/L FEU)28.
BI scores were assessed at baseline and 90 days after IVT. The assessment included feeding, grooming, dressing, toileting, mobility, stair climbing, urinary continence, and fecal continence. The total score ranged from 0 to 100, with higher scores indicating greater independence in activities of daily living29.
Prespecified adverse events were monitored from completion of IVT through the 90-day follow-up. Assessed events included elevated liver enzymes, allergic skin reactions, gastrointestinal discomfort, dizziness or headache, and total adverse events. Bleeding complications and serious adverse events were not systematically assessed or reported separately13. Consequently, the safety evaluation in this study is restricted to the prespecified events listed above, and the study cannot establish the overall safety of adjunctive butylphthalide after IVT, particularly with respect to hemorrhagic risk, which is of particular relevance in patients receiving thrombolysis followed by antiplatelet therapy. Any statement regarding safety in this manuscript should therefore be understood as referring only to these prespecified events and not to overall drug safety.
Sample size estimation
An a priori sample size calculation was performed during study planning based on previously published randomized controlled trials13. Favorable 90-day functional outcome rates of 65%–75% have been reported in intervention groups, compared with approximately 40%–50% in patients receiving antiplatelet therapy or IVT without adjunctive butylphthalide30. The expected favorable outcome rates were prespecified as 70% for the combination group and 45% for the antiplatelet-only group. With a two-sided α of 0.05 and 80% statistical power, the calculation indicated that at least 46 patients were required per group. Allowing for an anticipated data-loss rate of 10%–15%, the target sample size was 50–60 patients per group. After 1:1 PSM, 52 patients were retained in each group. A post hoc calculation based on the observed data yielded a power of 85.2%. This estimate was considered descriptive and not interpreted as evidence of sample-size adequacy, given the retrospective observational design and limited sample size.
Statistical analysis
PSM was performed using 1:1 nearest-neighbor matching without replacement and a caliper of 0.05. A logistic regression model was used to estimate individual propensity scores, with receipt of adjunctive butylphthalide as the dependent variable. Covariates included age, sex, baseline NIHSS score, time from symptom onset to thrombolysis, total thrombolytic dose, hypertension, diabetes mellitus, atrial fibrillation, previous stroke, and antiplatelet regimen. A common support restriction was applied. Covariate balance after matching was evaluated using standardized mean differences (SMDs), with an SMD <0.10 considered indicative of acceptable balance.
Normality was assessed using the Shapiro-Wilk test, and homogeneity of variance was evaluated using Levene's test. Normally distributed continuous variables with homogeneous variances were expressed as mean ± standard deviation (SD). Between-group comparisons were performed using independent-samples t-tests, and within-group longitudinal comparisons were performed using paired t-tests. Non-normally distributed continuous variables were expressed as median (interquartile range), M (Q1, Q3). Between-group comparisons were performed using the Mann-Whitney U test, and within-group comparisons were performed using the Wilcoxon signed-rank test. Categorical variables were expressed as n (%) and compared using the chi-square test. No outcome data were missing among the 104 matched patients; therefore, no missing-data imputation was performed.
Binary logistic regression was performed to identify factors associated with poor 90-day functional outcomes, with a poor functional outcome coded as 1 and a favorable functional outcome as 0. Baseline demographic, clinical, laboratory, and treatment-related variables with P < 0.10 in univariate analyses were entered as candidate predictors in the multivariable model. Post-treatment outcomes, including the 90-day NIHSS score, 90-day BI score, final infarct volume, 90-day hs-CRP concentration, and 90-day D-D concentration, were excluded to reduce overadjustment and potential adjustment for mediators. The matched cohort contained 41 poor-outcome events and 10 candidate predictors, corresponding to approximately four events per predictor. Because this ratio increased the risk of model overfitting, the multivariable findings were considered exploratory and hypothesis-generating.
One-way analysis of covariance (ANCOVA) was additionally performed to account for potential residual baseline imbalance in continuous outcomes after PSM. The treatment group was entered as the fixed factor, and the corresponding baseline value of each outcome measured within 24 h after admission was included as a covariate. Adjusted between-group analyses were performed for 90-day NIHSS score, BI score, infarct volume, serum hs-CRP concentration, and plasma D-D concentration. Consistency between the ANCOVA results and the corresponding independent-samples t-test or Mann-Whitney U test results was evaluated as part of the sensitivity assessment. All statistical tests were two-sided, and P < 0.05 was considered statistically significant. No adjustment for multiple comparisons was performed for secondary outcomes; therefore, these analyses were considered exploratory and require confirmation in independent datasets.
结果
Baseline clinical characteristics
After propensity score matching (PSM), 104 eligible participants were included: 52 in the butylphthalide combination group and 52 in the antiplatelet-only group. Baseline characteristics are presented in Table 1. In the combination group, the mean age was 64.50 ± 15.15 years, body mass index was 25.40 ± 1.46 kg/m2, time from symptom onset to thrombolysis was 180.54 ± 29.05 min, and total thrombolytic dose was 63.68 ± 8.75 mg. The corresponding values in the antiplatelet-only group were 64.46 ± 16.04 years, 25.41 ± 1.44 kg/m2, 180.13 ± 28.52 min, and 63.87 ± 8.52 mg, respectively. The corresponding P values were 0.990, 0.968, 0.943, and 0.913, and both Cohen's d and standardized mean differences (SMDs) were close to zero. Male patients accounted for 57.7% and 53.8% of the combination and antiplatelet-only groups, respectively. No statistically significant between-group differences were observed in the prevalence of hypertension, diabetes mellitus, atrial fibrillation, previous stroke or transient ischemic attack, smoking history, or the proportions receiving single- or dual-agent antiplatelet therapy (all P > 0.05). Overall, the measured baseline demographic characteristics, vascular risk factors, thrombolysis-related variables, and antiplatelet regimens were well balanced after PSM. However, PSM could account only for measured confounders. Unmeasured factors, including physician treatment decisions, socioeconomic status, and medication affordability, may have influenced treatment allocation and introduced residual confounding.
Favorable functional prognosis at 90 days
Functional outcomes at 90 days are presented in Table 2. A modified Rankin Scale (mRS) score of 0–2 was defined as a favorable functional outcome, whereas a score of 3–6 was defined as a poor functional outcome. In the combination group, 38 of 52 patients (73.1%) achieved a favorable functional outcome, compared with 25 of 52 patients (48.1%) in the antiplatelet-only group. Poor functional outcomes occurred in 14 patients (26.9%) and 27 patients (51.9%), respectively. The favorable functional outcome rate differed significantly between groups (χ2 = 6.804, P = 0.009; φ = 0.256). Thus, adjunctive butylphthalide therapy was associated with a higher rate of favorable 90-day functional outcomes after IVT.
CBF reperfusion rate
Cerebral blood flow (CBF) perfusion outcomes are presented in Table 3. Satisfactory CBF perfusion recovery was defined as ipsilateral regional CBF (rCBF) reaching ≥70% of that in the contralateral normal hemisphere. At 90 days, satisfactory CBF perfusion recovery was observed in 37 of 52 patients (71.2%) in the combination group and 25 of 52 patients (48.1%) in the antiplatelet-only group. The between-group difference was statistically significant (χ2 = 5.751, P = 0.016; φ = 0.235). Adjunctive butylphthalide therapy was therefore associated with a higher rate of satisfactory CBF perfusion recovery at 90 days.
Incidence of adverse events
Prespecified adverse events are presented in Table 4. In the combination group, elevated liver enzymes occurred in 5 patients (9.6%), allergic skin reactions in 1 patient (1.9%), gastrointestinal discomfort in 4 patients (7.7%), and dizziness or headache in 2 patients (3.8%). In the antiplatelet-only group, the corresponding frequencies were 2 (3.8%), 1 (1.9%), 4 (7.7%), and 3 (5.8%), respectively. Fisher's exact tests showed no statistically significant between-group differences in elevated liver enzymes (P = 0.437), allergic skin reactions (P = 1.000), gastrointestinal discomfort (P = 1.000), or dizziness or headache (P = 1.000). The overall incidence of assessed adverse events was 23.1% (12/52) in the combination group and 19.2% (10/52) in the antiplatelet-only group (χ2 = 0.231, P = 0.631; φ = 0.047). Thus, no statistically significant between-group difference was observed in the assessed adverse events. These results pertain only to the prespecified events listed in Table 4. Because bleeding complications and serious adverse events were not systematically assessed or reported separately, no conclusion can be drawn regarding the overall safety of adjunctive butylphthalide therapy after IVT; the absence of a between-group difference in the prespecified events should not be interpreted as evidence of overall safety.
Comparison of NIHSS score, BI score, and infarct volume
Neurological function, activities of daily living, and infarct volume are presented in Table 5. Within 24 h after admission, baseline National Institutes of Health Stroke Scale (NIHSS) scores, Barthel Index (BI) scores, and infarct volumes did not differ significantly between groups (all P > 0.05), and the absolute Cohen's d values were small. At 90 days, both groups showed improvements in these measures. Between-group comparisons showed lower NIHSS scores, higher BI scores, and smaller infarct volumes in the combination group than in the antiplatelet-only group (all P < 0.001). Cohen's d values were −2.065 for NIHSS score, 2.605 for BI score, and −1.637 for infarct volume, and the corresponding 95% confidence intervals (CIs) for the mean differences excluded zero. Adjunctive butylphthalide therapy was therefore associated with lower neurological deficit scores, greater independence in activities of daily living, and smaller infarct volumes at 90 days.
Comparison of hs-CRP and D-D levels
Inflammatory and coagulation-related biomarkers are presented in Table 6. Within 24 h after admission, serum high-sensitivity C-reactive protein (hs-CRP) and plasma D-dimer (D-D) levels did not differ significantly between groups (P = 0.961 and P = 0.929, respectively), and Cohen's d values were close to zero. At 90 days, hs-CRP and D-D levels decreased significantly from baseline in both groups (all P < 0.05). Between-group comparisons showed lower 90-day hs-CRP and D-D levels in the combination group than in the antiplatelet-only group (all P < 0.05). Cohen's d was −1.248 for hs-CRP and −0.664 for D-D, and the corresponding 95% CIs for the mean differences excluded zero. Adjunctive butylphthalide therapy was therefore associated with lower hs-CRP and D-D levels at 90 days.
Univariate logistic regression analysis of factors associated with poor 90-day functional prognosis
Univariate logistic regression was performed to identify baseline demographic, clinical, laboratory, and treatment-related variables associated with poor 90-day functional prognosis, as presented in Table 7. Butylphthalide combination therapy was associated with lower odds of poor functional outcome (OR = 0.340, 95% CI: 0.148–0.781, P = 0.011). Several baseline variables met the prespecified screening threshold of P < 0.10, including age (OR = 1.045 per 1-year increase, P = 0.067), body mass index (OR = 0.948 per 1 kg/m2 increase, P = 0.082), time from symptom onset to thrombolysis (OR = 1.009 per 1-min increase, P = 0.091), total thrombolytic dose (OR = 0.973 per 1-mg increase, P = 0.073), baseline NIHSS score (OR = 1.074 per 1-point increase, P = 0.062), baseline BI score (OR = 0.973 per 1-point increase, P = 0.077), initial infarct volume (OR = 1.014 per 1-cm3 increase, P = 0.085), baseline hs-CRP (OR = 1.096 per 1-mg/L increase, P = 0.069), and baseline D-D level (OR = 1.250 per 1-ng/mL FEU increase, P = 0.096). Sex, hypertension, diabetes mellitus, atrial fibrillation, previous stroke or transient ischemic attack, and smoking history did not meet the screening threshold (all P ≥ 0.10). In accordance with the prespecified statistical analysis, post-treatment variables, including 90-day NIHSS score, 90-day BI score, final infarct volume, 90-day hs-CRP, and 90-day D-D levels, were excluded from the candidate predictors to reduce overadjustment and to account for potential mediators.
Multivariable logistic regression analysis of factors associated with poor 90-day functional prognosis
Variables meeting the prespecified screening threshold of P < 0.10 in the univariate analysis were entered into the multivariable logistic regression model, as presented in Table 8. These variables included age, body mass index, time from symptom onset to thrombolysis, total thrombolytic dose, baseline NIHSS score, baseline BI score, initial infarct volume, baseline hs-CRP, baseline D-D level, and treatment regimen. Post-treatment outcome variables were excluded from the model. Treatment regimen remained independently associated with poor 90-day functional outcome after adjustment for the measured covariates (B = −1.115, OR = 0.328, 95% CI: 0.142–0.758, P = 0.009). Specifically, adjunctive butylphthalide therapy was associated with lower odds of poor 90-day functional outcome. Age, body mass index, time from symptom onset to thrombolysis, total thrombolytic dose, baseline NIHSS score, baseline BI score, initial infarct volume, baseline hs-CRP, and baseline D-D level were not independently associated with poor functional outcome in the multivariable model (all P > 0.05). However, given the observational study design and the limited number of poor-outcome events compared with the number of candidate predictors, the regression findings were exploratory and subject to residual confounding and potential model overfitting.
DATA AVAILABILITY:
The de-identified data supporting the findings of this study are provided in Supplementary File 1.
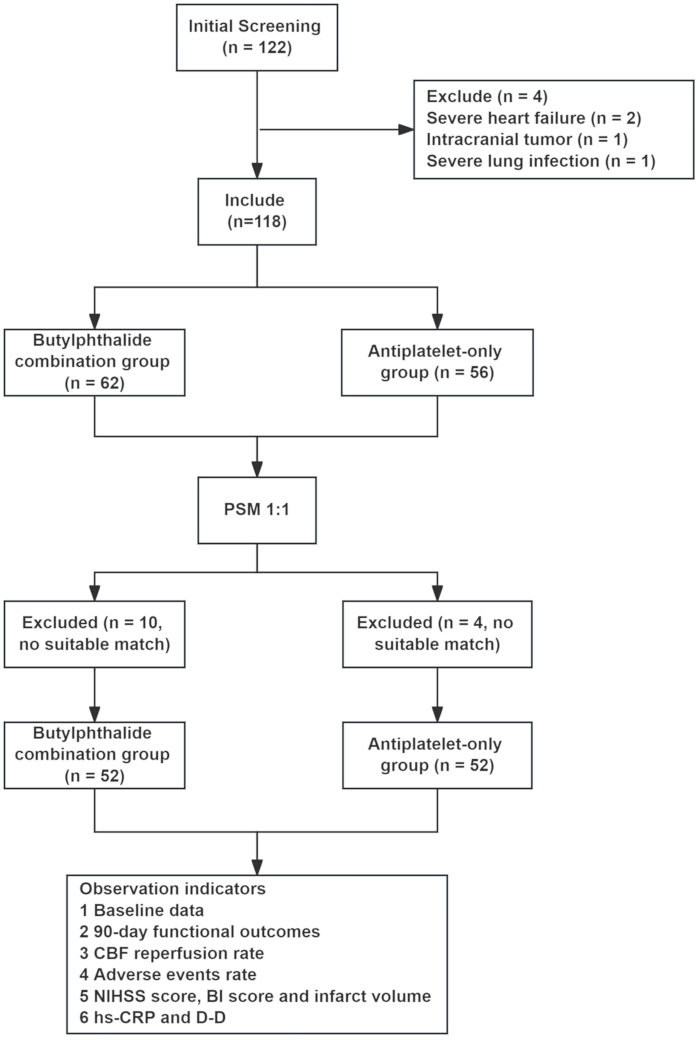
Figure 1: Study flow chart. Of the 122 patients with AIS who underwent initial screening, four were excluded: two with severe heart failure, one with an intracranial tumor, and one with severe pulmonary infection. A total of 118 eligible patients were subsequently classified according to treatment regimen into the butylphthalide combination group (n = 62) and the antiplatelet-only group (n = 56). PSM was performed at a 1:1 ratio to balance baseline characteristics. Of the 62 patients in the combination group, 10 were excluded because no suitable match was identified within the predefined caliper. Of the 56 patients in the antiplatelet-only group, four were excluded for the same reason. After PSM, 52 patients were retained in each group. Abbreviations: AIS = acute ischemic stroke; PSM = propensity score matching; CBF = cerebral blood flow; NIHSS = National Institutes of Health Stroke Scale; BI = Barthel Index; hs-CRP = high-sensitivity C-reactive protein; D-D = D-dimer. Please click here to view a larger version of this figure.
Table 1: Baseline clinical data. All baseline data were collected within 24 h after admission. Continuous variables are presented as mean ± SD, and categorical variables are presented as n (%). Between-group differences were assessed using the independent-samples t-test for continuous variables and the chi-square test for categorical variables. SMD and Cohen's d were calculated for continuous variables, whereas φ coefficients were calculated for categorical variables to quantify between-group effect sizes. SMD and Cohen's d values <0.2 indicated negligible between-group differences and acceptable baseline balance after PSM. Abbreviations: BMI = body mass index; PSM = propensity score matching; SMD = standardized mean difference; SD = standard deviation; rt-PA = recombinant tissue plasminogen activator; TIA = transient ischemic attack. Please click here to download this Table.
Table 2: Comparison of 90-day functional outcomes [n (%)]. Outcomes were assessed at the 90-day follow-up after stroke onset. Categorical variables are presented as n (%). Between-group comparisons were performed using the chi-square test, and the φ coefficient was calculated as the effect size for the between-group difference. A favorable functional outcome was defined as an mRS score of 0–2, whereas a poor functional outcome was defined as an mRS score of 3–6. Abbreviations: mRS = modified Rankin Scale. Please click here to download this Table.
Table 3: Comparison of CBF perfusion recovery rate [n (%)]. Cerebral perfusion was assessed at the 90-day follow-up. Categorical variables are presented as n (%). Between-group comparisons were performed using the chi-square test, and the φ coefficient was calculated to quantify the between-group effect size. Satisfactory CBF perfusion recovery was defined as ipsilateral rCBF ≥70% of that in the contralateral normal hemisphere. Abbreviations: CBF = cerebral blood flow; rCBF = regional cerebral blood flow. Please click here to download this Table.
Table 4: Comparison of adverse event rates [n (%)]. Adverse events were recorded throughout the 90-day follow-up period after stroke onset. Categorical variables are presented as n (%). Fisher's exact test was used for comparisons involving small cell counts, as indicated by an asterisk (*), and the chi-square test was used to compare total adverse events. The φ coefficient was reported as the effect-size measure for between-group comparisons. Please click here to download this Table.
Table 5: Comparison of NIHSS score, BI score, and infarct volume (mean ± SD). Measurements were obtained at two time points: within 24 h after admission (baseline) and 90 days after IVT. Continuous variables are presented as mean ± SD. The independent-samples t-test was used for baseline comparisons between groups. ANCOVA was used for 90-day between-group comparisons after adjustment for the corresponding baseline values. Cohen's d was reported as the effect-size measure. P < 0.05 versus the value obtained within 24 h after admission in the same group. Abbreviations: NIHSS = National Institutes of Health Stroke Scale; BI = Barthel Index; CI = confidence interval; IVT = intravenous thrombolysis; ANCOVA = analysis of covariance. Please click here to download this Table.
Table 6: Comparison of hs-CRP and D-D levels (mean ± SD). Biomarker measurements were obtained at two time points: within 24 h after admission (baseline) and 90 days after IVT. Continuous variables are presented as mean ± SD. The independent-samples t-test was used for baseline comparisons between groups. ANCOVA adjusted for the corresponding baseline values was used for between-group comparisons at the 90-day follow-up. Cohen's d was reported as the effect-size measure. P < 0.05 versus the value obtained within 24 h after admission in the same group. Abbreviations: hs-CRP = high-sensitivity C-reactive protein; D-D = D-dimer; FEU = fibrinogen equivalent units. Please click here to download this Table.
Table 7: Univariate logistic regression analysis of factors associated with poor 90-day functional prognosis. The dependent variable was poor 90-day functional prognosis, defined as mRS 3–6 = 1, whereas a favorable functional prognosis (mRS 0–2) was coded as 0. All independent variables were baseline measurements obtained within 24 h after admission. Binary variables were coded as follows: treatment regimen, butylphthalide combination therapy = 1 and antiplatelet-only therapy = 0; sex, male = 1 and female = 0; and hypertension, diabetes mellitus, atrial fibrillation, previous stroke/TIA, and smoking history, yes = 1 and no = 0. Continuous variables were analyzed per unit increment, as specified in the table. B represents the regression coefficient. Abbreviations: mRS = modified Rankin Scale; TIA = transient ischemic attack; OR = odds ratio. Please click here to download this Table.
Table 8: Multivariable logistic regression analysis of factors associated with poor 90-day functional prognosis. The dependent variable was poor 90-day functional prognosis, defined as mRS 3–6 = 1, whereas a favorable functional prognosis (mRS 0–2) was coded as 0. All covariates included in the model were baseline parameters collected within 24 h of admission. Treatment regimen was coded as butylphthalide combination therapy = 1 and antiplatelet-only therapy = 0. Continuous covariates were interpreted per unit increment, as specified in the table. B represents the regression coefficient. Abbreviations: mRS = modified Rankin Scale. Please click here to download this Table.
Supplementary File 1: De-identified data supporting the findings of this study.Please click here to download this file.
讨论
This single-center retrospective study of 104 propensity-score-matched patients with AIS after IVT (52 per group) showed that adjunctive butylphthalide plus standard antiplatelet therapy was associated with a higher rate of favorable 90-day functional outcome than antiplatelet-only therapy (mRS 0–2: 73.1% vs. 48.1%, P = 0.009). Adjunctive butylphthalide therapy was also associated with lower 90-day NIHSS scores, smaller final infarct volumes, higher BI scores, a higher rate of satisfactory CBF perfusion recovery (71.2% vs. 48.1%, P = 0.016), and lower hs-CRP and D-D levels. The overall incidence of the prespecified adverse events assessed in Table 4 was similar between groups (23.1% vs. 19.2%, P = 0.631). Multivariable logistic regression showed that adjunctive butylphthalide therapy was independently associated with lower odds of poor 90-day functional outcome (OR = 0.328, 95% CI: 0.142–0.758, P = 0.009). Given the observational design, these findings represent associations and do not establish causal effects.
These findings were broadly consistent with previous evidence. The TRACE-2 randomized trial reported a favorable 90-day outcome rate of 56.7% with butylphthalide compared with 44.0% with placebo among patients with AIS receiving reperfusion therapy, with comparable rates of severe adverse events13. A preliminary study of severe AIS after IVT also reported a higher clinical response rate with adjunctive butylphthalide than with thrombolytic therapy alone (96.08% vs. 76.47%), along with improvements in cerebral blood flow velocity and coagulation parameters31. Potential mechanisms underlying these associations include improved ischemic penumbra perfusion and collateral circulation, attenuation of oxidative stress and inflammatory responses, reductions in hs-CRP and D-D levels, modulation of platelet aggregation, and preservation of neuronal mitochondrial function, which may collectively limit infarct expansion and support neurological recovery18,31,32. Differences in effect magnitude between the present findings and those of TRACE-2 may reflect differences in study design, eligibility criteria, baseline risk, and background therapies.
From a clinical perspective, early adjunctive butylphthalide after IVT may represent a potential strategy for improving functional recovery without increasing the prespecified drug-related adverse events assessed in the present study. However, the safety assessment was restricted to the prespecified events reported in Table 4 and was incomplete. Bleeding complications and serious adverse events were not systematically assessed or reported separately, even though the study evaluated a treatment administered after intravenous thrombolysis and in combination with antiplatelet therapy, a setting in which hemorrhagic risk is of particular clinical concern. The present study, therefore, cannot establish the overall safety of adjunctive butylphthalide after IVT, and no conclusion can be drawn regarding bleeding risk or other serious adverse events. The observed absence of a between-group difference in the prespecified events should not be interpreted as evidence of safety for these outcomes. Confirmation in prospective studies is required before the routine use of adjunctive butylphthalide after IVT can be supported.
Several limitations should be considered when interpreting these findings. The single-center retrospective design and sample size of 52 patients per matched group limited the generalizability of the findings. PSM could account only for measured confounders, and confounding by indication may have remained because treatment allocation could have been influenced by physician judgment, stroke severity, patient or family preferences, affordability, and temporal changes in institutional treatment protocols. Concomitant statins, antihypertensive agents, and glucose-lowering therapies were not systematically collected or matched. The antiplatelet-only group included both single- and dual-agent antiplatelet regimens, introducing additional treatment heterogeneity. Furthermore, exclusion of patients who experienced post-thrombolysis complications or required rescue endovascular therapy introduced substantial post-treatment selection bias. Because these exclusions were applied after treatment-related events, and because symptomatic intracranial hemorrhage, severe early complications, discontinuation of thrombolysis, and rescue revascularization are all strongly associated with poor 90-day outcome, the analytical cohort was preferentially enriched for patients with a more favorable early course. This can inflate the observed favorable outcome rate in both groups and materially bias both the treatment-effect estimate and the safety assessment, such that the reported association likely represents an optimistic estimate of the treatment effect and may not apply to the full spectrum of patients receiving IVT. Bleeding complications and serious adverse events were not systematically assessed or reported separately; therefore, the study cannot establish overall safety, and only the prespecified adverse events in Table 4 can be discussed. Because these events do not include hemorrhagic complications, which are the most clinically relevant safety concern after thrombolysis combined with antiplatelet therapy, the safety data presented here should be regarded as exploratory. Additional limitations included a lack of blinding of treating physicians, a 90-day follow-up period, the absence of dose-response analyses, limited advanced neuroimaging assessments, and the inclusion of 10 predictors for 41 poor-outcome events in the multivariable model, which increased the risk of overfitting33.
Future multicenter prospective randomized controlled trials should validate these findings and determine the optimal dose, duration, and timing of butylphthalide administration after IVT. Future studies should also account for concomitant medications and distinguish between single- and dual-agent antiplatelet regimens. Longer follow-up periods, multimodal neuroimaging, and biomarker- or genotype-defined subgroup analyses may further clarify potential mechanisms and identify patient populations most likely to benefit.
In conclusion, early adjunctive butylphthalide plus standard antiplatelet therapy after IVT was associated with better 90-day functional recovery, lower neurological deficit scores, smaller infarct volumes, improved activities of daily living, and no significant increase in the prespecified adverse events assessed in this single-center retrospective cohort. However, residual confounding, confounding by indication, substantial post-treatment selection bias arising from the exclusion of patients with early treatment-related complications or requiring rescue revascularization, and the observational study design precluded causal inference. Prospective randomized controlled trials are required to validate these associations and define the clinical role of adjunctive butylphthalide therapy after IVT for AIS.
披露
The authors declare no financial conflicts of interest.
AUTHOR CONTRIBUTIONS:
Jingxue Cui developed and planned the study, performed the statistical analysis, interpreted the results, and edited and refined the manuscript with a focus on critical intellectual contributions. Xiaojie Dai and Chenyang Liu participated in data collection, assessment, and interpretation, and made significant contributions to data interpretation and manuscript preparation. Xiangbin Li provided substantial intellectual input during the drafting and revision of the manuscript.
材料
| 姓名 | 公司 | 目录编号 | 评论 |
|---|---|---|---|
| Aspirin | Bayer | SIM-ASP-100; LOT-ASP-2024A | Model: Aspirin Protect 100 mg; simulated lot: LOT-ASP-2024A. Used as part of standard antiplatelet therapy after IVT; single- or dual-antiplatelet regimen initiated within 24 h after thrombolysis. |
| Butylphthalide injection | CSPC Enbipu Pharmaceutical | SIM-NBP-INJ-25; LOT-NBPINJ-2024A | Model: 25 mg/5 mL; simulated lot: LOT-NBPINJ-2024A. Intravenous infusion at 25 mg twice daily for 14 consecutive days. |
| Butylphthalide soft capsules | CSPC Enbipu Pharmaceutical | SIM-NBP-CAP-01; LOT-NBPCAP-2024A | Model: 0.1 g/capsule; simulated lot: LOT-NBPCAP-2024A. Oral administration, 2 capsules three times daily; total treatment duration no fewer than 3 months. |
| Centrifuge | Eppendorf | SIM-EPP-5810R; SN-5810R-2024-001 | Model: 5810R; simulated serial number: SN-5810R-2024-001. Samples centrifuged at 3000 rpm for 10 min to separate serum/plasma. |
| Clopidogrel | Sanofi | SIM-CLO-75; LOT-CLO-2024A | Model: Plavix 75 mg; simulated lot: LOT-CLO-2024A. Used as part of standard antiplatelet therapy after IVT; single- or dual-antiplatelet regimen initiated within 24 h after thrombolysis. |
| EDTA anticoagulant tubes | BD | SIM-BD-EDTA-5; LOT-BDEDTA-2024A | Model: Vacutainer K2 EDTA 5 mL; simulated lot: LOT-BDEDTA-2024A. Used for venous blood collection for hs-CRP and D-D measurements. |
| G*Power | Heinrich-Heine-Universität Düsseldorf | SIM-GPOWER-3.1.9.7; LIC-GPOWER-2024-001 | Version 3.1.9.7; simulated license number: LIC-GPOWER-2024-001. Used for post-hoc statistical power analysis. With expected favorable prognosis rates of 70% vs 45%, two-sided α = 0.05, and power = 80%, at least 46 participants per group were required. After 1:1 PSM, 52 participants per group were retained; final post-hoc power was 85.2%. |
| IBM SPSS Statistics | IBM Corp. | SIM-SPSS-26.0; LIC-SPSS-2024-001 | Version 26.0; simulated license number: LIC-SPSS-2024-001. Used for propensity score matching, Shapiro-Wilk test, Levene test, independent-samples t-test, paired t-test, Mann-Whitney U test, Wilcoxon signed-rank test, chi-square test, and multivariate logistic regression analysis. |
| ImageJ 1.8.0 | National Institutes of Health (NIH) / ImageJ | SIM-IMAGEJ-180; IMJ-1.8.0-2024 | Version: ImageJ 1.8.0; simulated version identifier: IMJ-1.8.0-2024. Used to outline lesion boundaries and calculate infarct volume. |
| Philips Brilliance 64-slice spiral CT device | Philips Healthcare | SIM-CT-BR64; SN-BR64-2024-001 | Model: Brilliance 64; simulated serial number: SN-BR64-2024-001. Used for cerebral CT perfusion scanning: 120 kV, 250 mA, 5 mm slice thickness, full cerebral coverage. |
| Roche Cobas 8000 fully automatic biochemical analyzer | Roche Diagnostics | SIM-COBAS8000; SN-COBAS8000-2024-001 | Model: cobas 8000; simulated serial number: SN-COBAS8000-2024-001. Used for quantitative hs-CRP detection by immunoturbidimetry; normal reference range 0–3 mg/L. |
| rt-PA / Actilyse | Boehringer Ingelheim | SIM-RTPA-50; LOT-RTPA-2024A | Model: Actilyse 50 mg/vial; simulated lot: LOT-RTPA-2024A. Administered by intravenous infusion to all subjects: 0.9 mg/kg, maximum 90 mg; 10% as a rapid bolus within 1 min, remaining 90% infused over 60 min. |
| Siemens Prisma 3.0T MRI system | Siemens Healthineers | SIM-MRI-PRISMA; SN-PRISMA-2024-001 | Model: MAGNETOM Prisma 3.0T; simulated serial number: SN-PRISMA-2024-001. Used for DWI and FLAIR sequences and infarct volume assessment. DWI: TR 2000 ms, TE 80 ms, slice thickness 5 mm, gap 1 mm. FLAIR: TR 8000 ms, TE 120 ms, TI 2000 ms. |
| Sysmex CA-7000 automatic coagulation analyzer | Sysmex Corporation | SIM-CA7000; SN-CA7000-2024-001 | Model: CA-7000; simulated serial number: SN-CA7000-2024-001. Used for D-Dimer detection by latex-enhanced immunoturbidimetry; normal reference value 0–0.5 mg/L. |
参考文献
- Sharma R, Lee K. Advances in treatments for acute ischemic stroke. BMJ. 2025;389:e076161. doi:10.1136/bmj-2023-076161.
- Ho JP, Powers WJ. Contemporary management of acute ischemic stroke. Annu Rev Med. 2025;76(1):417-429. doi:10.1146/annurev-med-050823-094312.
- Majoie CB et al. Value of intravenous thrombolysis in endovascular treatment for large-vessel anterior circulation stroke: individual participant data meta-analysis of six randomised trials. Lancet. 2023;402(10406):965-974.
- Kristoffersen ES, Seiffge DJ, Meinel TR. Intravenous thrombolysis and mechanical thrombectomy in acute stroke patients on direct oral anticoagulants. J Neurol. 2024;272(1):82.
- Qiao Y et al. Intravenous thrombolysis with urokinase for acute ischemic stroke. Brain Sci. 2024;14(10):989. doi:10.3390/brainsci14100989.
- Zheng W et al. Intravenous thrombolysis prior to endovascular treatment for acute ischemic stroke: a meta-analysis. Neurol Sci. 2022;43(10):5993-6002.
- Xiao H et al. Butylphthalide enhances neurorestoration following ischemic stroke by restructuring microvasculature through vimentin modulation. J Adv Res. Published online December 7, 2025. doi:10.1016/j.jare.2025.11.068.
- Du H et al. Intravenous thrombolysis before mechanical thrombectomy for acute ischemic stroke: a meta-analysis. J Am Heart Assoc. 2021;10(23):e022303.
- Zeng J et al. Dual antiplatelet therapy after intravenous thrombolysis for patients with minor ischemic stroke: a meta-analysis. Clin Neurol Neurosurg. 2024;238:108176.
- Qin B et al. Intravenous thrombolysis versus dual antiplatelet therapy for patients with acute minor ischaemic stroke: a systematic review and meta-analysis. Front Pharmacol. 2024;15:1377475.
- Dammavalam V et al. Neuroprotection during thrombectomy for acute ischemic stroke: a review of future therapies. Int J Mol Sci. 2024;25(2):891. doi:10.3390/ijms25020891.
- Yu Q et al. Synthesis of novel 3-butylphthalide derivatives containing isopentenylphenol moiety as potential antiplatelet agents for the treatment of ischemic stroke. Chem Biodivers. 2023;20(1):e202201002.
- Wang A et al. Efficacy and safety of butylphthalide in patients with acute ischemic stroke: a randomized clinical trial. JAMA Neurol. 2023;80(8):851-859.
- Li Y et al. Neuroprotection in the early window: a randomized controlled trial of butylphthalide initiation within 3 hours in acute ischemic stroke. BMC Med. Published online August 15, 2026. doi:10.1186/s12916-026-05130-1.
- Xin-Shuai L et al. Meta-analysis of the efficacy and safety of Ginkgolide Meglumine Injection combined with Butylphthalide in the treatment of Acute Ischemic Stroke. PLoS One. 2024;19(1):e0296508.
- Wang Z et al. Impact of NBP on acute ischemic stroke: tracking therapy effect on neuroinflammation. Int Immunopharmacol. 2024;143(Pt 1):113217.
- Yang L et al. Efficacy of sequential N-butylphthalide therapy on psychiatric and behavioral functions in acute ischemic stroke. Medicine (Baltimore). 2021;100(46):e27860.
- Li Y, Wang H, Zhao J, Xia L, Xiong K, Zhong H. Effects of butylphthalide on cerebral vascular circulation, coagulation function, and neurological function in patients with acute severe ischemic stroke following intravenous thrombolysis: a preliminary study. Int J Neurosci. 2025;135(3):367-374. doi:10.1080/00207454.2023.2301424.
- Peng B, Wang YJ. Chinese guidelines for diagnosis and treatment of acute ischemic stroke 2023. Chin J Neurol. 2023;57(6):523-559.
- Qin M et al. Antiplatelet therapy versus intravenous thrombolysis for mild acute ischaemic stroke: a living systematic review and meta-analysis. Stroke Vasc Neurol. 2025;10(2):e003097. doi:10.1136/svn-2024-003097.
- Duan C et al. Intravenous thrombolysis versus antiplatelet therapy in minor stroke patients with large vessel occlusion. CNS Neurosci Ther. 2023;29(6):1615-1623.
- Grotta JC. Intravenous thrombolysis for acute ischemic stroke. Continuum (Minneap Minn). 2023;29(2):425-442.
- Lee TL, Chang YM, Sung PS. Clinical updates on antiplatelet therapy for secondary prevention in acute ischemic stroke. Acta Neurol Taiwan. 2023;32(3):138-144.
- Liu S et al. Efficacy and safety of 3-n-butylphthalide combined with endovascular treatment in acute ischemic stroke due to large vessel occlusion. CNS Neurosci Ther. 2022;28(12):2298-2307.
- Rinkel LA et al. Comparing early National Institutes of Health Stroke Scale versus 90-day Modified Rankin Scale outcomes in acute ischemic stroke trials: a systematic review and analysis. J Am Heart Assoc. 2025;14(9):e040304.
- Rafael-Patino J et al. Diffusion imaging protocol heterogeneity biases ischemic core volume, location, and clinical associations in acute stroke. Stroke. 2025;56(4):915-925.
- Thirugnanachandran T et al. Assessing the diagnostic accuracy of CT perfusion: a systematic review. Front Neurol. 2023;14:1255526.
- Billoir P et al. C-reactive protein and D-dimer in cerebral vein thrombosis: relation to clinical and imaging characteristics as well as outcomes in a French cohort study. Res Pract Thromb Haemost. 2023;7(3):100130.
- Wei X, Sun S, Zhang M, Zhao Z. A systematic review and meta-analysis of clinical efficacy of early and late rehabilitation interventions for ischemic stroke. BMC Neurol. 2024;24(1):91.
- Chen HS et al. Dual antiplatelet therapy vs alteplase for patients with minor nondisabling acute ischemic stroke: the ARAMIS randomized clinical trial. JAMA. 2023;329(24):2135-2144.
- Li J, Cao W, Zhao F, Jin P. Cost-effectiveness of edaravone dexborneol versus dl-3-n-butylphthalide for the treatment of acute ischemic stroke: a Chinese health care perspective. BMC Public Health. 2024;24(1):436.
- Wang H, Ye K, Li D, Liu Y, Wang D. DL-3-n-butylphthalide for acute ischemic stroke: An updated systematic review and meta-analysis of randomized controlled trials. Front Pharmacol. 2022;13:963118. doi:10.3389/fphar.2022.963118.
- Yu Q et al. Novel 1,3,4-oxadiazole hybrids of 3-n-butylphthalide derivatives as potential anti-ischemic stroke agents. Bioorg Chem. 2024;143:107034.