We present a new dissection method to extract the vestibular ganglion and all five vestibular organs (utricle, saccule, and three cristae: lateral/horizontal, anterior, and posterior) as one whole-mount vestibular complex. Confocal imaging allows visualization of vestibular neuron cell bodies for quantification, as well as neuronal projections to the sensory epithelia.
方法文章
Whole-Mount Dissection of the Vestibular Complex and Quantification of Vestibular Ganglion Neurons in Mice
本文内容
摘要
摘要
The vestibular system is crucial for our sense of balance, for detecting head movements, and for regulating gaze and posture. There are five vestibular organs located inside the temporal bone, including two otolith organs (utricle and saccule), which detect linear movement, and three cristae (lateral/horizontal, anterior, and posterior), which detect rotational movement. Each organ contains a sensory epithelium with hair cells that detect head movements and supporting cells that provide structural support, release growth factors and cytokines, and phagocytose dying hair cells. The neurons that make synapses with hair cells project from the vestibular ganglion (also called Scarpa’s ganglion), which is located on the surface of the temporal bone. Most previous studies of the vestibular ganglion have used sectioning methods to visualize these cells, which have several limitations. Here, we describe a method to dissect the mouse vestibular ganglion and its connecting organs (saccule, utricle, and three cristae) as a whole mount, enabling more detailed analysis of neuronal cell bodies and their dendritic projections to the sensory epithelia. These methods include fixation, decalcification, dissection, immunofluorescent staining, confocal imaging, and three-dimensional quantification of vestibular neurons.
引言
The temporal bone houses the cochlea, as well as the five vestibular organs (utricle, saccule, and three cristae: lateral/horizontal, anterior, and posterior). Each of these organs contains mechanosensory hair cells that detect sound waves or head movements, resulting in synaptic transmission to their innervating neurons. The sensory epithelium, also called the macula, of both the utricle and saccule is covered by otoconia, which are small calcium carbonate crystals embedded in a gelatinous layer. They allow hair cells to detect gravitational forces and linear movements. In contrast, the three cristae detect angular acceleration using the movement of the endolymph within the semicircular canals. When acceleration occurs, the endolymphatic fluid moves, displacing the cupula, a gelatinous structure that encases the cristae, which in turn deflects the stereocilia bundles located on the apical surface of hair cells. The anterior crista detects up and down movement (nodding), while the posterior and lateral/horizontal cristae detect side-to-side tilting (shaking one’s head no). The lateral/horizontal crista also detects rotational movements in the horizontal plane (turning of the head to look)1,2,3.
The neurons that innervate vestibular hair cells are called vestibular ganglion cells, which merge to form Scarpa’s ganglion. Their axons project to the vestibular nuclei in the brainstem as well as to the cerebellum4,5. The ganglion is a dumbbell-shaped structure with a superior and inferior division. The neurons in the superior region innervate the lateral/horizontal crista, anterior crista, and utricle, while neurons in the inferior region innervate the posterior crista and the saccule6. While much research has been conducted on vestibular hair cells, the vestibular ganglion has received far less attention. Many previous studies have investigated the vestibular ganglion using cross-sections, which limit the sampling size for quantification of neuron numbers and impede the view of neuronal connectivity to vestibular organs7,8,9. Whole-mount dissection of the utricle, saccule, and cristae only allows visualization of the dendritic terminals that make contact with hair cells within the sensory epithelia; the vestibular neuron cell bodies are not present10,11,12,13,14. We have developed a method to excise the entire vestibular complex from mice (aged 2 weeks or older) via whole-mount dissection, in which the vestibular ganglion and the vestibular organs it innervates remain intact as a single structure. However, axonal projections from the vestibular ganglion to the vestibular nucleus or cerebellum are not preserved. These axons are severed close to the vestibular ganglion when the temporal bone is removed from the skull. After immunofluorescent staining with an antibody that labels neurons, the whole-mounted vestibular complex can be imaged with confocal microscopy to visualize dendritic projections to vestibular organs, measure ganglion size, and quantify neuronal cell bodies within a three-dimensional cube. These additional metrics will provide valuable information to increase our understanding of the development, damage, and aging of the vestibular system.
方案
Procedures involving animal subjects have been approved by the Institutional Animal Care and Use Committee at Southern Illinois University School of Medicine.
1. Extraction of Temporal Bones
- After using an IACUC accepted euthanasia method, decapitate the mouse and use standard surgical scissors to cut the skin and skull through the midline, from the brainstem to the eyes. Make a second cut perpendicular to the midline behind the eyes.
NOTE: Cardiac perfusion could be done, but is not required. - Gently remove the brain using a spatula.
NOTE: Exercise caution when removing the brain, as this step can damage the vestibular ganglion. - Locate the temporal bones in the base of the mouse skull. Place one thumb at the tip of the otic capsule and press down on the posterior semicircular canal with the thumb from the other hand to separate the encapsulated temporal bone from the base of the skull.
- Free the bottom half of the temporal bone from the skull manually with the thumb and index finger or by using 10.5 cm fine scissors.
NOTE: Steps 1.3-1.4. will sever the axons of the vestibular nerve that project to the brainstem, leaving the vestibular ganglion attached to the temporal bone.
2. Fixation of Temporal Bones
- Place both temporal bones from one mouse into a 2 mL microcentrifuge tube containing 1 mL 4% paraformaldehyde (PFA) diluted in 10 mM phosphate-buffered saline (PBS), pH 7.4, and incubate at room temperature for 20–24 h. For some antibodies, a shorter fixation and/or fixation at 4 °C is needed.
NOTE: Using these fixation conditions, the temporal bone does not need to be opened to obtain good fixation.
CAUTION: Paraformaldehyde is toxic and a suspected carcinogen. Handle in a fume hood, wearing gloves and a lab coat. PFA waste should be collected and sent to the University Environmental Health and Safety office for disposal.
3. Decalcify Temporal Bones
- After fixation, use a pipette to remove the PFA and replace it with 120 mM ethylenediaminetetraacetic acid (EDTA). It is important to fill the entire tube with EDTA (slightly more than 2 mL) to prevent air bubbles when the tube is closed.
- If not decalcifying immediately, replace PFA with 10 mM PBS, pH 7.4, and store samples at 4°C.
NOTE: After fixation, temporal bones can be stored at 4°C before decalcification. However, the storage duration depends on the antibodies planned for immunostaining. - Place tubes on an end-over-end rotator and rotate at 4 rpm at room temperature.
- Change the EDTA solution once a day, about 24 h apart for at least 3 days.
NOTE: The tissue needs to be slightly more decalcified than for the cochlear dissection described previously15. Decalcification time may vary slightly depending on the animal's age. To speed up the decalcification process, EDTA can be changed twice a day, or the tissue can be placed in a larger tube containing a higher volume of EDTA. - To determine if the sample is adequately decalcified, place the temporal bones on a silicone elastomer-coated dissection dish15 and gently press the forceps onto the vestibule. If the tissue is spongy, then decalcification is complete.
- Once decalcification is complete, use a pipette to remove the EDTA and add 500–1,000 µL of 10 mM PBS, pH 7.4. Store samples at 4ºC until ready to dissect.
NOTE: Decalcified tissue has a limited shelf life and will disintegrate if too much time elapses.
4. Dissection
- Fill a silicone elastomer-coated dissection dish two-thirds full with 10 mM PBS, pH 7.4, and place one decalcified temporal bone in the dish. Use a stereo-dissection microscope for the following steps.
- Use step 4 or 5 straight jeweler's forceps and 5 mm ultrafine microsurgical spring scissors to gently remove any excess muscle tissue remaining on the temporal bone.
- Hold the temporal bone on the outside edges with No. 4 or 5 straight jeweler's forceps with the cochlea facing down, and use another pair of No. 4 or 5 straight jeweler's forceps to grab and gently peel off the thin piece of bone that runs perpendicular to the vestibule.
- Use 5 mm ultrafine microsurgical spring scissors for the following steps:
- Cut off the superior portion of the anterior semicircular canal area and gently remove any excess brain tissue.
- Cut off the apical/middle portion of the cochlea, leaving only the basal turn.
NOTE: Cutting too much of the basal turn in this step can cause damage to the inferior vestibular ganglion and projections. At least half of the basal turn should be left (~1.5 mm) in this step. - Place one blade inside the temporal bone and cut along the vestibular endolymphatic duct, continuing the cut through the cochlea.
- Place one blade inside the vestibular endolymphatic duct and start another cut in the bone along the anterior side of the vestibule.
- Cut off the membranous labyrinth covering the utricle.
NOTE: In non-albino strains, this membrane has small brown spots, called dark cells, which can obscure light from the confocal microscopy.
- Use curved 2.5 mm Vannas spring scissors to trim the rest of the temporal bone that covers the top of the three cristae.
- Slowly coax each of the cristae out of the bone casing using a blunt 26 G needle attached to a 1 mL insulin syringe (serving solely as a handle for the comfort of the user), and then use 5 mm ultrafine microsurgical spring scissors to cut off the bone that once held the cristae.
NOTE: The saccule is located between the posterior crista and the utricle, at a 90° angle. It is also connected to the inferior vestibular ganglion with a very thin piece of bone in between. Because of this location, no special steps are needed for the dissection. However, do not attempt to remove this thin bone during dissection, as it will damage the ganglion. - Use curved 2.5 mm Vannas spring scissors to trim the basal turn of the cochlea and any other tissue/bone remaining around the vestibular complex.
5. Immunostaining with Fluorescently Tagged Antibodies
NOTE: The immunostaining process described below follows the same procedure described in15 with a slight modification in volume per well.
- After dissection, store each vestibular complex in a separate well in a 48-well plate (or chamber slide), submerged in ~500 µL of 10 mM PBS, pH 7.4.
- Keep the vestibular complex submerged in the solution. For each of the following steps, do not allow the tissue to float to the surface or stick to the side of the well.
NOTE: When removing liquid from each well, it is easy to lose or suck up the tissue in the pipette tip. Changing solutions with a 200 µL pipette tip using a dissection scope will help prevent this.- Using a pipette, remove PBS from each well and replace with ~200–300 µL per well of blocking/permeabilization solution (1% Trition X-100, 1% bovine serum albumin (BSA), and 10% normal goat serum (NGS) diluted in 10 mM PBS, pH 7.4).
NOTE: If any primary antibody used was made in a goat host, normal horse serum should be used as a replacement for NGS to prevent cross-reactivity with anti-goat secondary antibodies. - Incubate 1 h at room temperature on a 3D rotator.
- Remove blocking/permeabilization solution using a pipette and replace with ~110 µL per well of the primary antibody solution (0.1% Triton X-100, 1% BSA, and 5% NGS diluted in 10 mM PBS, pH 7.4). The dilution factor for each primary antibody varies. Here, rabbit anti-myosin VIIa was used at 1:200 and mouse IgG2a anti-β-III tubulin (neuron-specific class III β-tubulin; clone β-III tubulin) at 1:500.
- Incubate at least 14 h at 4 ºC on a 3D rotator.
NOTE: If more than one primary antibody is used, they can all be combined into a single incubation solution; each primary antibody should be from a different host. - Remove the primary antibody solution using a pipette and perform 3 washes of 10 mM PBS, pH 7.4, at ~500 µL per well. Each wash is incubated for at least 5 min at room temperature on a 3D rotator.
- Remove the last PBS wash using a pipette and replace with ~110µL per well of the secondary antibody solution (0.1% Triton X-100, 1% BSA, and 5% NGS diluted in 10 mM PBS, pH 7.4).
NOTE: The dilution factor for each fluorescently tagged secondary antibody should usually be 1:500 or 1:1,000. Here, donkey anti-rabbit (H+L; heavy and light chain) conjugated to Alexa 568 dye and goat anti-mouse IgG2a conjugated to Alexa 488 dye were used, both at a 1:1,000 dilution. - Place the 48-well plate in a black box to protect fluorescently tagged secondary antibodies from light. Incubate 2–3 h at room temperature on a 3D rotator.
NOTE: If more than one secondary antibody is needed, they can be combined in a single solution for incubation. There should be no possibility of cross-labeling (e.g., using goat anti-rabbit and chicken anti-goat secondary antibodies). - Remove the secondary antibody solution using a pipette and perform 3 washes of 10 mM PBS, pH 7.4 at ~500 µL per well. Incubate each wash for at least 5 min at room temperature on a 3D rotator. Keep the 48-well plate in a black box to protect it from light.
- Using a pipette, remove PBS from each well and replace with ~200–300 µL per well of blocking/permeabilization solution (1% Trition X-100, 1% bovine serum albumin (BSA), and 10% normal goat serum (NGS) diluted in 10 mM PBS, pH 7.4).
6. Mounting the Vestibular Complex on slides
- Label the slides with the needed information, including sample identification and antibodies used.
- Place an imaging spacer that is 13 mm in diameter × 0.12 mm in depth.
- Pipette ~20 µL of mounting media onto each slide. Pipette slowly to prevent bubbles in the mounting media.
- While observing through a stereo-dissection microscope, use a No. 4 or 5 straight jeweler's forceps to pick up the tissue by one of the membranous labyrinths connected to one of the cristae.
- Place the tissue on the slide in the middle of the spacer.
NOTE: Due to limitations in confocal imaging of the z-plane, sample mounting is influenced by your primary objective. For the best view of the vestibular ganglion, mount with the utricular sensory epithelium facing up. For the best view of the neuronal projections, mount with the utricular sensory epithelium facing down. - Gently cover the tissue with a number 1.5 coverslip.
- Place the slide in a slide holder and let it cure for at least 14 h.
NOTE: It is important for the slide to lie flat and be in a dark location. - The next day, use clear nail polish to seal and secure the coverslip to the slide. Slides can be stored in a slide folder or a slide box.
NOTE: Slides can be stored long-term at −20 ºC to maintain fluorescence for several months.
7. Confocal Imaging
- Low Magnification
- Use the 10x objective to locate the tissue.
- Adjust the brightness and contrast of the desired wavelength using the imaging software provided by the confocal vendor.
NOTE: The specific settings for the confocal software will vary depending on the vendor, model, antibodies used, and length of time the tissue was stored after fixation. - Adjust the scan area, image speed, resolution, and bits per pixel to the desired settings.
- Use a tile scan image with a Z stack to capture the entire structure in one image.
- High Magnification
- Use the 40x objective to locate the tissue.
- Adjust the brightness and contrast of the desired wavelength using the imaging software provided by the confocal vendor.
NOTE: The specific settings for the confocal software will vary depending on the vendor, model, antibodies used, and length of time the tissue was stored after fixation. - Adjust the scan area, image speed, resolution, and bits per pixel to the desired settings.
- Complete a Z stack of at least 40 slices with a step size of 1 µm.
NOTE: Since this tissue is thicker, the amount of light that can penetrate decreases with increasing depth. The channel settings may need to be turned up mid-image.
8. Quantification of vestibular neurons in a three-dimensional cube
- Open the image taken at 40x, where a neuronal marker such as β-III tubulin was used, using the imaging software provided by the confocal vendor.
- Draw one or more 50 µm × 50 µm boxes in the desired area to be quantified, ensuring that neurons are present throughout the entire tissue depth.
NOTE: The location of the box or boxes can be random or standardized. - Use the events tool to count neuronal nuclei. Begin counting at the appearance of the first neuron, which is defined as a ring of β-III tubulin staining surrounding a nucleus.
- Continue to count the neuronal nuclei for the next 39 consecutive slices (for a total of 40 slices or 40 µm).
NOTE: Neurons whose nuclei are at least 50% inside the 50 µm × 50 µm box should be counted.
结果
Here we present a whole-mount dissection method to excise the entire vestibular complex (Figure 1A,B), which contains the vestibular ganglion, subdivided into the superior and inferior regions, as well as the sensory epithelia of the utricle, saccule, and three cristae. Figure 2A,B shows the intact, undissected temporal bone and provides anatomical descriptors and landmarks used within the dissection protocol. Figure 3 highlights landmarks for key dissection steps. Excision of the entire vestibular complex allows visualization of the vestibular ganglion, when mounted with the utricular sensory epithelium facing up (Figure 4), as well as the neuronal projections to each vestibular organ, when mounted with the utricular sensory epithelium facing down (Figure 5). This dissection method allows for the neurons to be counted in a three-dimensional cube (50 µm × 50 µm × 40 µm) when imaged at 40× magnification (Figure 6A) (or, in theory, all neurons could be counted), as well as tracing of the neuronal projections (Figure 6B).
There are a few issues that can arise during the dissection and tissue mounting. While dissecting, it is important not to pull or tear pieces off (except the bone piece in dissection step 4.3). The dumbbell shape of the vestibular ganglion makes a natural weak point, which can cause the superior and inferior regions to rip apart (Figure 7). In addition, making the cut to remove the apical and middle turns of the cochlea increases the risk of damage to the vestibular ganglion. If too much of the basal turn is cut off at this time, a sizable chunk will be taken out of the ganglion. Half of the basal turn (~1.5 mm) should be kept to prevent damage to the ganglion. Another issue that can arise during mounting is that, since the saccule sits at a 90° angle to the utricle, it tends to fold over the vestibular ganglion (Figure 8). This will obstruct the view of the neuronal cell bodies when using β-III tubulin staining because the neurons labeled in the saccular sensory epithelium lie directly over the ganglion.
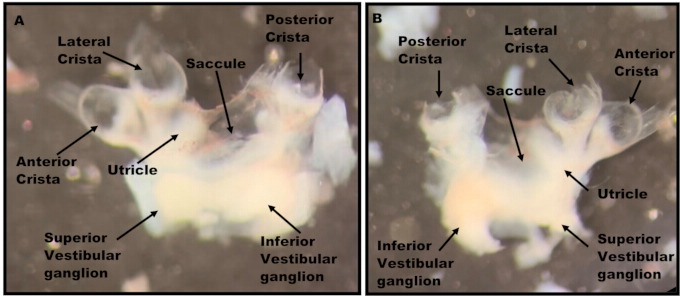
Figure 1: Whole-mount dissection of the vestibular complex. Light microscopy image of the dissected tissue with arrows labeling the structures. (A) Utricular sensory epithelium facing up. (B) Utricular sensory epithelium facing down. Please click here to view a larger version of this figure.
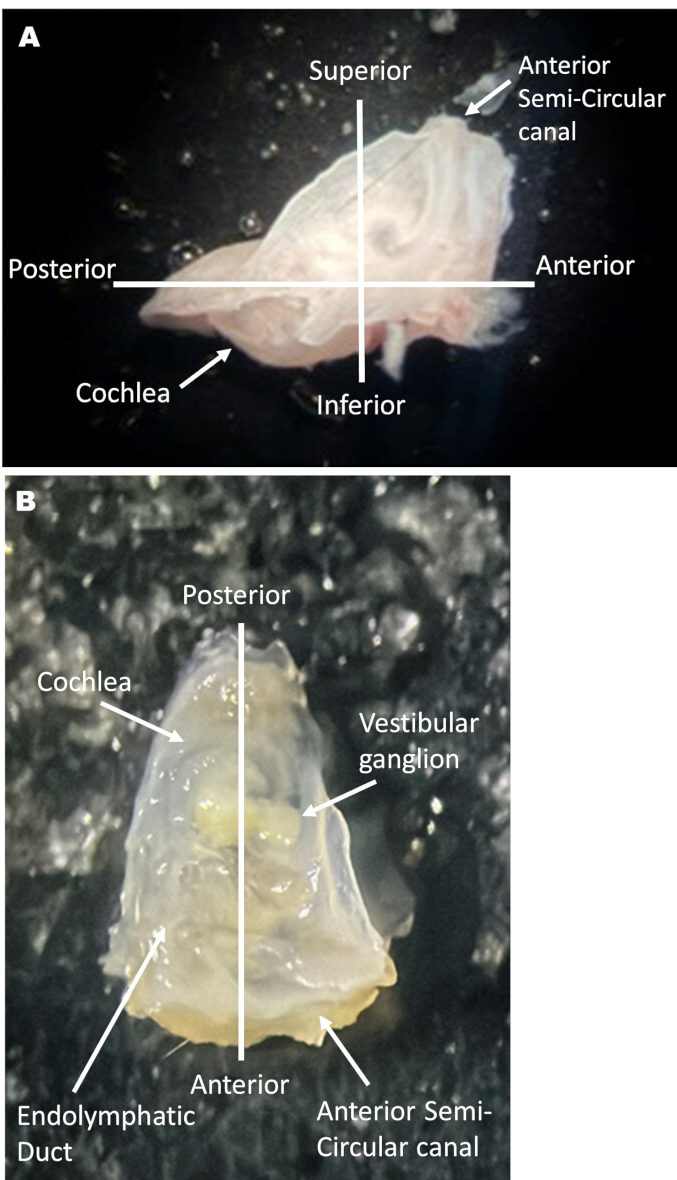
Figure 2: Undissected temporal bone with anatomical labels. Light microscopy image of the intact temporal bone with landmarks and anatomical positions labeled. The orientation labels were applied to the temporal bone after its removal from the skull to guide the reader during the dissection procedure. Anterior denotes the anterior semicircular canal. Posterior denotes the apical tip of the cochlea. (A) Side view; (B) Top view. Please click here to view a larger version of this figure.
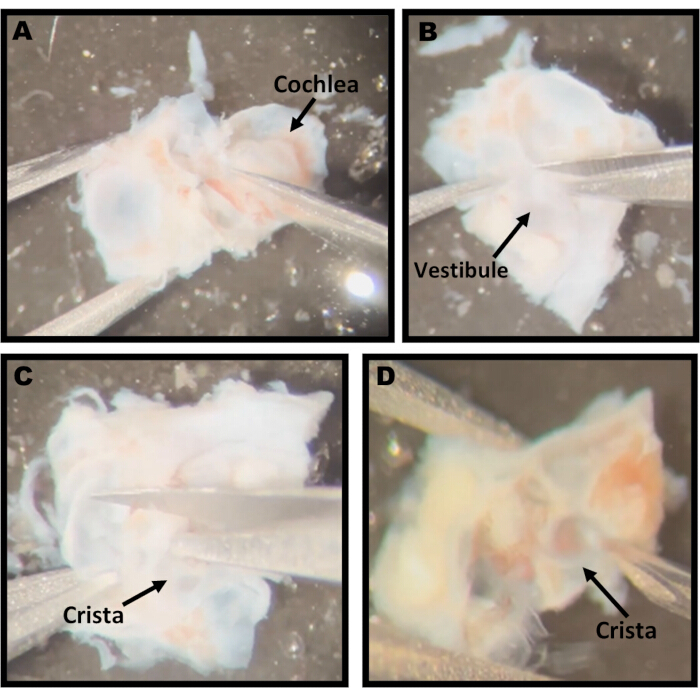
Figure 3: Important steps in the dissection method. Light microscopy images visualizing tissue landmarks for important steps in the dissection process. The structure relevant to each step is labeled with black arrows. (A) Image showing the scissor placement to cut off the apical and middle turns of the cochlea in step 4.4.2. (B) Image shows cutting along the anterior side of the vestibular endolymphatic duct for step 4.4.3. (C) Image shows trimming the bone over the cristae in step 4.5. (D) Image showing the use of a blunt 26 G needle to coax the crista out of the bone for step 4.6. Please click here to view a larger version of this figure.
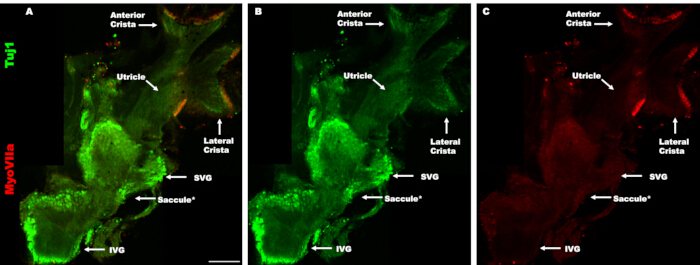
Figure 4: The vestibular complex as a whole-mount to visualize the ganglion. (A–C) Maximum intensity confocal projection image showing the vestibular complex at low magnification, with the tissue mounted with the utricular sensory epithelium facing up. (A) Merged channels. Vestibular hair cells were labeled using myosin VIIa (red) (C), and neurons were labeled using β-III tubulin (green) (B). *The saccule is at a deeper location because it is tucked under the vestibular ganglion and is not shown in this image to allow a full view of the vestibular ganglion. SVG: superior vestibular ganglion IVG: inferior vestibular ganglion. Scale bar: 200 µm applies to all panels. Please click here to view a larger version of this figure.
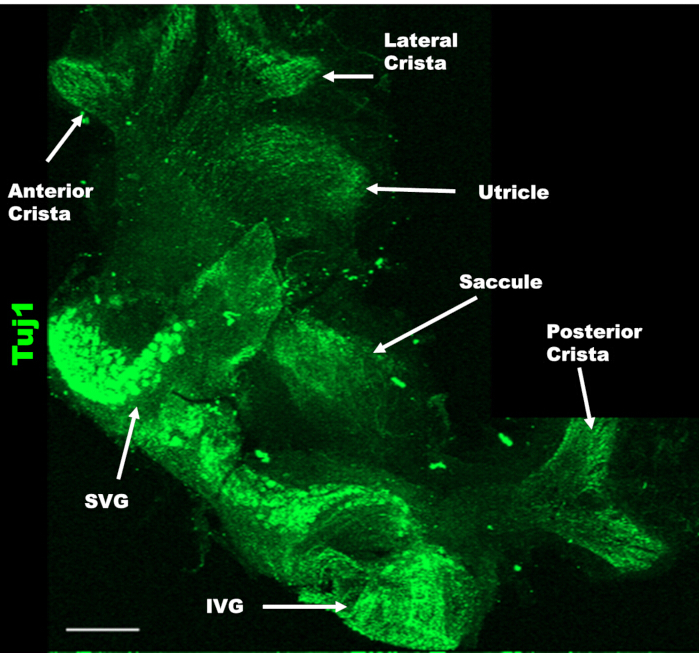
Figure 5: Vestibular complex as a whole-mount to visualize neuronal projections to vestibular organs. Maximum intensity confocal projection image showing the vestibular complex at low magnification, with the tissue mounted with the utricular sensory epithelium facing down. The utricle, anterior and lateral/horizontal cristae can be seen, with neuronal connections to the superior vestibular ganglion (SVG) with neurons labeled with β-III tubulin (green). The saccule and posterior crista have neuronal connections to the inferior vestibular ganglion (IVG). Each of these organs was identified by its unique innervation pattern and location relative to the SVG and IVG. Scale bar: 200 µm. Please click here to view a larger version of this figure.
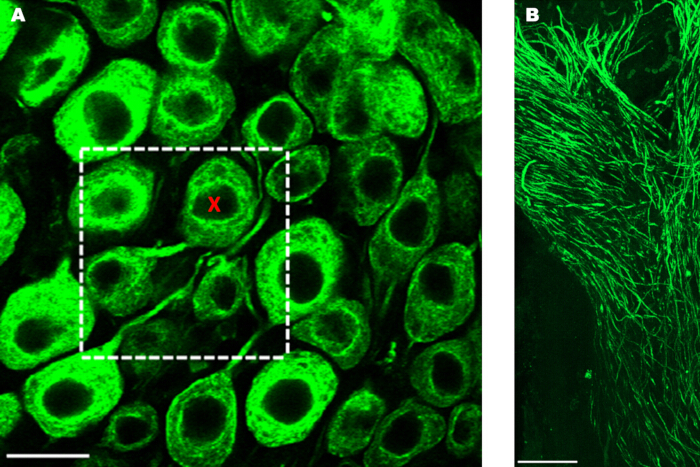
Figure 6: Counting method for vestibular ganglion neurons and image of neuronal projections. (A) Confocal z-slice image showing the superior vestibular ganglion neurons at 40x magnification (labeled with β-III tubulin in green). Neurons can be counted using the events tool in the confocal imaging software (red X) within a 50 µm × 50 µm area (white box) in 40, 1 µm slices (40 µm depth), giving a three-dimensional cube sample. (B) Maximum intensity confocal projection image showing neuronal projections to the posterior crista at 40x magnification (labeled with β-III tubulin in green). Scale bar: A, 20 µm; B, 50 µm. Please click here to view a larger version of this figure.
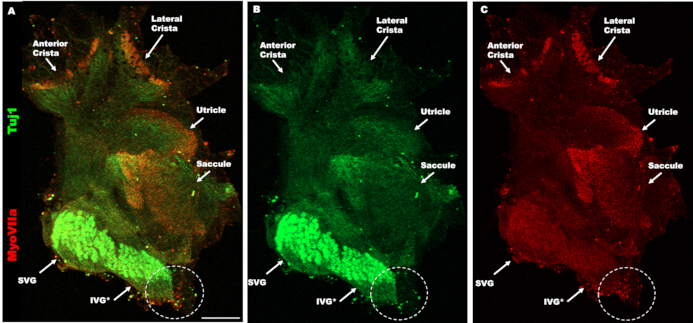
Figure 7: Common error during dissection. (A-C) Maximum intensity confocal projection image showing the vestibular complex, where part of the inferior vestibular ganglion (IVG), as well as the posterior crista, was torn off during dissection (circled). Vestibular hair cells were labeled using myosin VIIa (red) (C), and neurons were labeled using β-III tubulin (green) (B). Superior vestibular ganglion (SVG). Scale bar: 200 µm. Please click here to view a larger version of this figure.
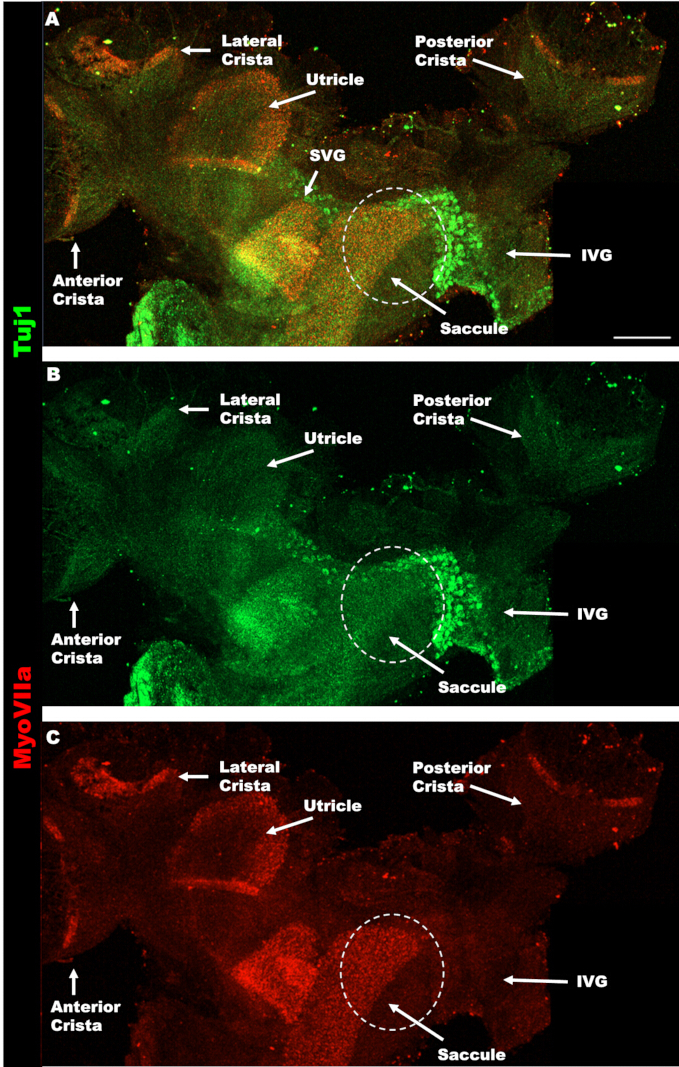
Figure 8: Common error during mounting. (A-C) Maximum intensity confocal projection image showing the vestibular complex, where part of the saccule has folded over and covered the vestibular ganglion during mounting (white circle). Vestibular hair cells were labeled using myosin VIIa (red) (C), and neurons were labeled using β-III tubulin (green) (B). Superior vestibular ganglion (SVG); inferior vestibular ganglion (IVG). Scale bar: 200 µm. Please click here to view a larger version of this figure.
讨论
There are major gaps in the understanding of vestibular development, damage, and dysfunction, as well as a few clinical trials addressing vestibular problems16. While several groups have extracted vestibular organs as a whole-mount structure for immunostaining10,11,12,13,14. These methods only preserved the sensory epithelia. Here, we present a new dissection method using juvenile or adult mice that includes the vestibular ganglion attached to the five vestibular organs. Bernd Fritzsch and colleagues have used a similar method with embryonic or neonatal samples5. The method presented here will be a useful tool for increasing knowledge of vestibular innervation and the vestibular ganglion.
Having the vestibular ganglion intact is an improvement over sectioning methods, where the sample size for quantification of neuron numbers is limited7,8,9. This whole-mount method allows the quantification of most vestibular neurons or sampling in a three-dimensional cube, separating the superior and inferior regions. However, we have not compared the number of vestibular neurons present in this whole-mount vestibular complex with previous quantifications done using other methods. It is also likely that there is variability in the amount of ganglion preserved between operators, and improvement can be achieved with practice. In addition, this method allows visualization of the neuronal connections between the vestibular ganglion and the vestibular organs, providing an opportunity to study innervation during development, aging, or after damage. In the future, a glial marker could be used for immunostaining, enabling visualization and quantification of Schwann cells along the vestibular dendrites and satellite cells in the ganglion.
Despite its potential to deepen our understanding of the vestibular system, this method is difficult and involves several steps where problems can arise. First, when decalcifying the tissue, the level of decalcification is very important. The tissue must be sufficiently decalcified for the scissors to cut through the bone easily. If the dissection is started and cutting the superior part of the anterior semicircular canal seems difficult, further decalcification is needed. In contrast, there is also the potential to over-decalcify the tissue, and decalcified tissue has a limited storage life. Either of these factors can make the tissue very fragile, causing it to disintegrate during dissection. These errors can be prevented by regularly checking the sample during decalcification. Based on this laboratory's experience, decalcifying no more than 6 months prior to dissection will prevent the tissue from disintegrating during dissection.
The second difficulty is holding the tissue during dissection. Once the cochlea has been removed (step 4.4.2), the tissue cannot really be “held” with the forceps. Instead, the forceps are closed and used to pin the tissue by pressing it into the silicone dish to prevent it from floating away. As the vestibular ganglion rests on the surface of the temporal bone, it allows this structure to be visible during all parts of the dissection. If stress or pulling of the tissue is noticed, readjustments can be made before damage occurs or worsens. Also, after the dissection is complete, the tissue can only be handled using the portion of the membranous labyrinth connected to one of the three cristae. Grabbing any other portion will cause damage to the corresponding organ.
Another issue that may arise during mounting is tissue folding. The whole-mount vestibular complex has many structures with different orientations and the propensity to twist or fold. To help prevent this, do not just drop the coverslip onto the tissue; instead, place one side of the coverslip on the slide and slowly angle it down. When placing the coverslip, orient the tissue so that the three cristae are pointing in the opposite direction from the side of the coverslip that will be lowered. This will cause the mounting media to push the organs away from the ganglion.
Lastly, confocal imaging of the vestibular complex can also be challenging due to tissue thickness and reduced light penetration in deeper slices. If the neuronal cell bodies appear too faint in deeper slices, the channel laser settings can be increased during imaging. It is helpful to note the slice(s) where the image darkens, and then make the appropriate channel adjustment(s) before starting the z-stack. Another potential alternative would be thin-sheet laser imaging microscopy (TSLIM), which has better resolution17.
While the dissection method presented here is challenging, most can learn with practice. The preservation of most of the vestibular ganglion, as well as the dendritic projections to vestibular organs, offers new opportunities to advance research questions in the field. This method could be used to address questions about neuronal differentiation during development, changes in neurons or neuronal projections during aging, and alterations to vestibular neurons or innervation patterns after noise trauma or traumatic brain injury7.
披露
B. Cox is a consultant for Turner Scientific, LLC.
致谢
We thank Rahilla Tarfa from the University of Washington for helpful discussion. This work was supported in part by a grant from the National Institute on Aging R01 AG073151. The Southern Illinois University School of Medicine Research Imaging Facility is supported by the Office of Naval Research Grant N00014-15-1-2866.
材料
| 姓名 | 公司 | 目录编号 | 评论 |
|---|---|---|---|
| 10.5cm Bonn-Gawenda Scissors | Fine Science Tools | 14854-10 | |
| 1mL Insulin Syringe with Slip Tip | Becton Dickinson (BD) | 22-253-260 | |
| 2.5mm Vannas-Tübingen Spring Scissors | Fine Science Tools | 15000-08 | |
| 26 gauge PrecisionGlide Hypodermic Needles | Becton Dickinson (BD) | 14-826-48 | |
| 3D rotator | MidSci | R3D-710 | |
| 48-well plates | Fisher | 08-772-52 | |
| 5mm Vannas-Tübingen Spring Scissors | Fine Science Tools | 15003-08 | |
| 8-well chamber slides | Fisher | 1256518 | |
| BSA, fraction V | Fisher | BP1605 | |
| cardboard slide folder | Fisher | 12-587-10 | |
| clear nail polish | Local drug store | ||
| donkey anti-rabbit (H+L) conjugated to Alexa 568 | Invitrogen | A10042 | red-emitting fluorophore |
| Dumont #4 Forceps | Fine Science Tools | 11241-30 | |
| Dumont #5 Forceps | Fine Science Tools | 11255-20 | |
| End over end rotator | Fisher | 05-450-127 | |
| Ethylenediaminetetraacetic acid disodium salt dihydrate | Millipore Sigma | E4884 | |
| Formaldehyde 16%. EM grade | Polysciences, Inc | NC1040701 | |
| goat anti-mouse IgG2a conjugated to Alexa 488 | Invitrogen | A21131 | green-emitting fluorophore |
| Mouse IgG2a anti-Tuj1 | BioLegend | 801201 | |
| Normal goat serum | Vector labs | S-1000 | |
| Normal horse serum | Vector labs | S-2000 | |
| Phosphate buffered saline | Millipore Sigma | P3813 | |
| plastic slide box | Fisher | 03-448-10 | |
| Premium Microcentrifuge Tubes: 2.0mL | Fisher | 05-408-138 | |
| ProLong Gold Antifade Mountant | Invitrogen | P36930 | mounting media |
| Rabbit anti-myosin VIIa | Proteus BioSciences | 25-6790 | |
| Richard-Allan Scientific Cover Glass | Epredia | 22-050-235 | |
| SS1X13 Imaging spacer | Grace Bio Labs Inc | NC0840392 | imaging spacer |
| Standard surgical scissors | Fine Science Tools | 14002-12 | |
| Superfrost Plus Microscope Slides | Fisher | 12-550-15 | |
| Triton X-100 | Sigma | X100-500 | nonionic detergent octylphenol ethoxylate |
| Western blot incubation box XL | Licor | 929-97401 | |
| LSM800 confocal laser scanning microscope | Zeiss | confocal microscope | |
| Zen blue software | Zeiss | free to download | confocal imaging/analysis software |
| Tuj1 antibody | BioLegend | anti-β-III tubulin (neuron-specific class III β-tubulin; clone Tuj1) | |
| Vannas-Tubingen spring scissors | Vannas-Tubingen | ultra-fine microsurgical 5 mm straight spring scissors |
参考文献
- Burns JC, Stone JS. Development and regeneration of vestibular hair cells in mammals. Semin Cell Dev Biol. 2017;65:96-105.
- Eatock RA, Songer JE. Vestibular hair cells and afferents: two channels for head motion signals. Annu Rev Neurosci. 2011;34:501-34.
- Dickman JD. The vestibular system. In: Haines DE, Mihailoff GA, editors. Fundamental Neuroscience for Basic and Clinical Applications. 5th ed. Philadelphia: Elsevier; 2018.
- Büttner-Ennever JA. Patterns of connectivity in the vestibular nuclei. Ann N Y Acad Sci. 1992;656:363-78.
- Maklad A, Fritzsch B. Development of vestibular afferent projections into the hindbrain and their central targets. Brain Res Bull. 2003;60(5-6):497-510.
- Khan S, Chang R. Anatomy of the vestibular system: a review. NeuroRehabilitation. 2013;32(3):437-43.
- Richter E. Quantitative study of human Scarpa’s ganglion and vestibular sensory epithelia. Acta Otolaryngol. 1980;90(1-6):199-208.
- Bäurle J, Guldin W. Unbiased number of vestibular ganglion neurons in the mouse. Neurosci Lett. 1998;246(2):89-92.
- Park JJ, Tang Y, Lopez I, Ishiyama A. Unbiased stereological quantification of neurons in the human vestibular ganglion. Neuroreport. 2000;11(4):853-7.
- Balmer TS, Trussell LO. Vestibular organ dissection and whole-mount immunolabeling in mouse. Bio Protoc. 2022;12(10):e4416. doi:10.21769/BioProtoc.4416.
- Li A, Xue J, Peterson EH. Architecture of the mouse utricle: macular organization and hair bundle heights. J Neurophysiol. 2008;99(2):718-33.
- Lysakowski A, et al. Molecular microdomains in a sensory terminal, the vestibular calyx ending. J Neurosci. 2011;31(27):10101-14.
- Golub JS, et al. Hair cell replacement in adult mouse utricles after targeted ablation of hair cells with diphtheria toxin. J Neurosci. 2012;32(43):15093-105.
- Hoffman LF, Choy KR, Sultemeier DR, Simmons DD. Oncomodulin expression reveals new insights into the cellular organization of the murine utricle striola. J Assoc Res Otolaryngol. 2018;19(1):33-51.
- Montgomery SC, Cox BC. Whole mount dissection and immunofluorescence of the adult mouse cochlea. J Vis Exp. 2016;(107):53561. doi:10.3791/53561.
- Ratzan EM, Davis W, Brodsky JR. Investigation of vestibular dysfunction requires renewed research enthusiasm. J Assoc Res Otolaryngol. 2026;27(1):25-36.
- Johnson SB, Schmitz HM, Santi PA. TSLIM imaging and a morphometric analysis of the mouse spiral ganglion. Hear Res. 2011;278(1-2):34-42.
重印与许可
本文已发表
视频即将推出