In this retrospective study of 150 patients with cognitive impairment associated with neurological disorders, integrated collaborative nursing combining cognitive rehabilitation, nutritional management, activity of daily living (ADL) training, family participation, and post-discharge follow-up was associated with better cognitive, nutritional, functional, and continuity-of-care outcomes.
研究文章
Collaborative Nursing Integrating Cognitive Rehabilitation and Nutritional Management for Cognitive Impairment Associated with Neurological Disorders
本文内容
摘要
摘要
This retrospective study aimed to examine whether receipt of an integrated collaborative nursing model centered on multidimensional cognitive rehabilitation was associated with cognitive, nutritional, and functional outcomes among patients with cognitive impairment due to neurological disorders. A total of 150 patients admitted between May 2024 and May 2026 were retrospectively included. According to the nursing model actually received during hospitalization, patients were classified into an observation group of 69 patients, who received integrated collaborative nursing centered on cognitive rehabilitation and integrated with nutritional risk management, daily living task training, family collaboration, and continued post-discharge follow-up, and a control group of 81 patients, who received routine neurological nursing. Implementation indicators were higher in the observation group, including cognitive training completion (88.41% vs. 56.79%) and post-discharge follow-up completion (86.96% vs. 67.90%). After adjustment for age, sex, education level, primary neurological diagnosis, disease course, cognitive impairment severity, and the corresponding baseline outcome, the observation group had higher post-intervention Montreal Cognitive Assessment (adjusted mean difference, 2.26 points; 95% CI, 1.68–2.84), Mini Nutritional Assessment-Short Form (MNA-SF) (1.22 points; 95% CI, 0.88–1.55), and Barthel index scores (9.62 points; 95% CI, 7.15–12.10), p < 0.001; adjusted Mini-Mental State Examination (MMSE), instrumental activities of daily living (IADL), and functional independence measure (FIM) outcomes showed the same direction of association. These findings indicate short-term associations between the receipt of the integrated collaborative nursing model and improvements in implementation, cognitive, nutritional assessment, functional, and continuity-of-care outcomes; the retrospective, non-randomized design does not establish causality.
引言
Cognitive impairment associated with neurological disorders is a common and complex functional problem during rehabilitation in patients with stroke, Parkinson's disease, traumatic brain injury, epilepsy, and other chronic neurological disorders. This type of impairment is not confined to cognition itself; it may also affect patients' understanding and execution of disease-related knowledge, medication requirements, nutritional management, and rehabilitation training content1. According to the World Health Organization, approximately 57 million people worldwide were living with dementia in 2021, with nearly 10 million new cases occurring each year2. In stroke-related populations, the incidence of post-stroke cognitive impairment is approximately 39%–47%, and some studies have suggested that cognitive impairment within 1 year after stroke may affect up to 60% of patients3. Impaired cognitive function weakens patients' initiative and continuity in rehabilitation participation and increases the risks of falls, aspiration, readmission, and care dependence, making it a key issue that cannot be ignored in functional recovery after neurological diseases4. However, existing rehabilitation nursing usually targets a single functional deficit, such as cognitive training, limb function training, or nutritional education. These measures have value in specific links of care, but for patients with cognitive impairment associated with neurological disorders, a single intervention often cannot cover their multidimensional and continuous rehabilitation needs5. In clinical practice, cognitive decline, nutritional risk, and impaired ability to perform daily living tasks often coexist and overlap, gradually forming a vicious cycle6. Therefore, the nursing needs of patients with cognitive impairment associated with neurological disorders cannot be fully addressed by cognitive training alone. Cognitive rehabilitation, nutritional support, life-function training, and continuing nursing care need to be integrated into a more continuous intervention system.
It is observed that existing studies often describe intervention content in relatively general terms and lack clear implementation procedures, intervention frequency, responsibility assignment, and quality control requirements, which limits the replication and promotion of nursing programs across different clinical settings7. At the same time, studies tend to focus more on post-intervention changes in scale scores, while the implementation of the intervention process itself is not sufficiently presented, such as whether cognitive training is completed as planned, whether nutritional nursing measures are carried out, whether family members truly participate, and whether post-discharge follow-up is sustained8. In addition, previous outcome evaluations have often focused on cognitive change, whereas nutritional status, activities of daily living, implementation processes, and safety outcomes have been evaluated less often together, making it difficult to characterize rehabilitation across multiple domains9,10.
Based on this, this study constructed an integrated collaborative nursing model guided by multidimensional cognitive rehabilitation. Starting from a comprehensive admission assessment, the model incorporated cognitive rehabilitation nursing, nutritional risk screening and support, activity of daily living (ADL) training, family collaborative nursing, and continued post-discharge follow-up, and its associations with process and clinical outcomes were evaluated in patients with cognitive impairment associated with neurological disorders. Its core idea was to extend cognitive rehabilitation from a single training program to a continuous nursing process covering both hospitalization and the post-discharge period, so that patients could receive targeted support at different rehabilitation stages; at the same time, nutritional management and daily living task training were incorporated into a cognitive rehabilitation-oriented nursing framework, and process quality indicators were combined with multidimensional clinical outcomes to present the implementation pathway and effects of the nursing model more completely. The findings may provide a practical reference for prospective evaluation of integrated cognitive rehabilitation, nutritional management, ADL training, family participation, and post-discharge nursing in this population.
方案
This study was approved by the Ethics Committee of Affiliated Nanjing Brain Hospital, Nanjing Medical University (approval No. 2024k021; Date: May 16, 2024). Because the study involved only anonymized retrospective data and no direct patient contact, the Ethics Committee waived the requirement for informed consent.
Study subjects
Potentially eligible admissions between May 2024 and May 2026 were identified retrospectively from the available hospital records. The final analytic cohort comprised 150 patients who met all eligibility criteria; however, because a complete prescreening log was not retained, the total number initially screened, and the number excluded for each reason could not be reconstructed reliably. This limitation is acknowledged explicitly in the Discussion. The May 2024–May 2026 period refers to the admission window rather than the end of outcome ascertainment. Follow-up continued until each included patient had completed the planned 4-week post-discharge assessment, including patients admitted in May 2026, and the database was locked in August 2026, only after the final eligible patient had completed this follow-up. According to the nursing model actually received during hospitalization and traceably recorded in nursing documents, the patients were divided into an observation group and a control group. The observation group included 69 patients and received the integrated collaborative nursing model guided by multidimensional cognitive rehabilitation; the control group included 81 patients and received routine neurological nursing. Both groups received standardized diagnosis and treatment for their primary neurological diseases, and the difference in nursing models was regarded as the main exposure factor in this study. The diagnoses were pooled because the nursing model targeted shared rehabilitation needs, including cognitive impairment, nutritional risk, impaired ADL performance, and caregiver-supported continuity of care, rather than disease-specific pathophysiology. Primary neurological diagnosis was therefore treated as a potential confounder in adjusted analyses, and diagnosis-specific effects were not inferred from the pooled cohort. Among the included patients, 21 were recorded under the combined category “epilepsy or other neurological disorders”; more granular diagnostic coding within this low-frequency category was not consistently available for retrospective reclassification. All data were obtained from the hospital electronic medical record system, laboratory information system, and other relevant sources. The research team had no contact with the patients and did not perform any intervention. All data were anonymized before processing; therefore, informed consent was waived.
Inclusion and exclusion criteria
Inclusion criteria: age ≥18 years; hospitalization for stroke, Parkinson's disease, traumatic brain injury, epilepsy, or other neurological diseases, with varying degrees of cognitive decline during the disease course; cognitive impairment identified within 24 h after admission by a trained neurology nurse using the Montreal Cognitive Assessment (MoCA)11 or the Mini-Mental State Examination (MMSE)12; for the MoCA, a score <26 indicated cognitive impairment after adding 1 point for patients with ≤12 years of education, whereas the education-adjusted MMSE thresholds were ≤17 for illiterate patients, ≤20 for those with primary-school education, and ≤24 for those with junior-high-school education or above; relatively stable vital signs and ability to complete basic cognitive, nutritional, and daily living ability (ADL) assessments; and basically complete nursing records, rehabilitation records, laboratory examinations, and follow-up data during hospitalization.
Exclusion criteria: a definite diagnosis of severe dementia, schizophrenia, bipolar disorder, or other severe psychiatric disorders before admission; severe disturbance of consciousness, severe aphasia, obvious hearing or visual impairment, or other conditions that made scale assessment impossible; concomitant end-stage malignant tumor, severe cardiac, hepatic, or renal failure, active infection, or other diseases that could substantially affect nutritional status and functional outcomes; death during hospitalization, discharge against medical advice, or transfer to another specialty, resulting in missing major outcome data; and missing key variables that could not be supplemented through electronic medical records, nursing records, rehabilitation records, or follow-up data. Pre-existing mild or moderate dementia or mild cognitive impairment was not an automatic exclusion criterion provided that the patient could complete the required assessments and met all other eligibility criteria.
Routine nursing
Nursing care started after admission and continued until discharge and was implemented by the responsible nurse under the supervision of the head nurse. After admission, the responsible nurse completed vital signs monitoring, condition observation, fall-risk assessment, pressure-injury risk assessment, medication guidance, basic nursing care, dietary education, and safety education in accordance with routine departmental practice. For patients with limited limb activity, decreased swallowing function, or reduced self-care ability, nurses provided position management, turning and back-patting, feeding assistance, bedside activity guidance, and complication prevention according to medical orders and the patient's actual condition. Before discharge, the responsible nurse provided routine discharge education to patients and family members, including medication use, follow-up time, dietary precautions, basic rehabilitation training, and home safety protection.
Integrated collaborative nursing model guided by multidimensional cognitive rehabilitation
In this model, the responsible nurse served as the primary implementer, the head nurse was responsible for quality control, and neurologists, rehabilitation therapists, nutritionists, and the main caregivers participated jointly according to the patient's functional status. Nursing was initiated within 24 h after admission, continued throughout hospitalization, and extended to 4 weeks after discharge. The implementation personnel, main content, frequency, and quality control points are shown in Table 1.
(1) Within 24 h after admission, the responsible nurse completed a comprehensive nursing assessment. If the patient had relatively evident cognitive impairment, increased nutritional risk, or reduced ability to perform activities of daily living, the responsible nurse reported the assessment results to the head nurse and, when necessary, invited a rehabilitation therapist or nutritionist to participate in developing the nursing plan. The individualized nursing focus was usually formed within 48 h after admission and recorded in the nursing plan or specialized nursing record.
(2) Cognitive rehabilitation nursing usually began after the patient had stable vital signs, clear consciousness, and the ability to follow basic instructions, most often within 24–48 h after admission. This part was performed by the responsible nurse or a trained rehabilitation nurse, with training suggestions provided by the rehabilitation therapist. Training was generally performed once daily, 20–30 min each time; for patients with fatigue, dizziness, emotional resistance, or disease fluctuation, a single session could be shortened to 10–15 min and, if necessary, completed in divided sessions. Training content was selected according to the patient's main cognitive deficits and included reality orientation, attention, memory, and executive function training.
(3) The responsible nurse completed Mini Nutritional Assessment-Short Form (MNA-SF)-based nutritional screening within 24 h after admission and assessed swallowing status from routine bedside swallowing evaluation and documented clinical signs, including choking, wet voice, and pharyngeal residue. For patients with nutritional risk, insufficient intake, dysphagia, or weight loss, the responsible nurse developed a dietary nursing plan with physicians and nutritionists; daily intake was reviewed against individualized energy and protein requirements, food texture and meal frequency were adjusted according to swallowing tolerance, and nutritional status was reassessed at least weekly or whenever the clinical condition changed. Oral nutritional supplements or enteral nutrition, when clinically indicated, followed the physician or nutritionist prescriptions and were implemented and monitored by nursing staff rather than being standardized components of the nursing exposure. For patients at risk of aspiration, nurses assisted them in eating in a sitting or semi-recumbent position, controlled eating speed, observed choking, wet voice, pharyngeal residue sensation, and other manifestations, and reported abnormal conditions to physicians in a timely manner.
(4) Training in daily living tasks was carried out after the patient's condition was stable and basic activity safety conditions were met, with the responsible nurse, rehabilitation therapist, and main caregiver participating together. For patients with cognitive impairment, nurses used task decomposition, repeated prompting, visual cues, and fixed-order training to assist them in completing tasks. For example, medication management training included identifying drug names or colors, repeating medication times, using pill boxes for classification, and simulating medication-taking procedures with family assistance; eating training emphasized pre-meal preparation, use of tableware, swallowing safety, and oral cleaning after meals; dressing and transfer training focused on action sequence, postural stability, and fall prevention.
(5) Family collaborative nursing ran through the hospitalization and discharge preparation stages. Within 72 h after admission, the responsible nurse identified the main caregiver and conducted the first nursing communication, which included the characteristics of the patient's cognitive impairment, staged rehabilitation goals, nutritional risks, key points of life care, and safety risks; during hospitalization, nurses encouraged the main caregiver to participate in cognitive training, eating observation, and ADL training, so that they could understand the patient's specific needs for prompting, assistance, and supervision. At 24–48 h before discharge, the responsible nurse provided centralized discharge guidance, focusing on home-based cognitive training methods, dietary management, medication supervision, fall and aspiration prevention, recognition of abnormal symptoms, and follow-up requirements.
(6) Post-discharge continuity of care was handled by the responsible nurse, and the head nurse regularly checked follow-up completion. Follow-up was usually scheduled at week 1, week 2, and week 4 after discharge and could be completed by telephone or online. Follow-up content included completion of cognitive training, food intake, and body weight changes, adverse events, and whether unplanned readmission occurred; if interrupted training, insufficient nutritional intake, medication errors, or increased safety risk was identified during follow-up, the responsible nurse provided targeted guidance and reported the issue to the neurologist, rehabilitation therapist, or nutritionist according to the problem type.
Evaluation of intervention implementation quality and adherence
Process indicators during hospitalization and post-discharge follow-up were extracted, including cognitive training completion rate, nutritional nursing plan implementation rate, ADL training completion rate, family participation rate, and post-discharge follow-up completion rate. The prespecified core components comprised daily dietary-intake review, ADL training (once daily for 20–30 min), caregiver education during hospitalization and again before discharge, and nurse follow-up at weeks 1, 2, and 4 after discharge. These core nursing procedures were routinely scheduled for eligible patients, whereas specialist consultation, modification or division of training sessions, oral nutritional supplementation, enteral nutrition, and other condition-specific measures were optional and were used only when clinically indicated; caregiver participation in individual bedside training sessions was encouraged when feasible rather than required at every session. For reporting purposes in this retrospective analysis, the between-group difference in MoCA was designated as the primary outcome. MMSE, MNA-SF, Barthel index, instrumental activities of daily living (IADL), functional independence measure (FIM) motor and cognitive scores, and medication-management ability were treated as secondary outcomes; cognitive-domain measures, biochemical and hematologic parameters, implementation and adherence measures, cognitive-training process measures, and continuity-of-care measures were considered exploratory. For Montreal Cognitive Assessment (MoCA), Mini-Mental State Examination (MMSE), Mini Nutritional Assessment-Short Form (MNA-SF), body mass index (BMI), albumin (ALB), prealbumin (PA), hemoglobin (HGB), Barthel index, instrumental activities of daily living (IADL), and Functional Independence Measure (FIM) outcomes, baseline was defined as the first eligible assessment obtained after admission and before implementation of the individualized nursing plan, whereas the final assessment was the corresponding evaluation at completion of the 4-week post-discharge follow-up. Cognitive-rehabilitation process measures were extracted from the first and final documented inpatient training sessions; medication-management ability was assessed during discharge preparation, and safety and continuity-of-care outcomes were ascertained from discharge through the end of the 4-week follow-up. Safety outcomes were analyzed separately as described below.
Evaluation of cognitive function
Global cognitive function was assessed using the standard Montreal Cognitive Assessment (MoCA) and Mini-Mental State Examination (MMSE), both established cognitive screening instruments scored from 0 to 30, with higher scores indicating better cognitive performance11,12. The MoCA attention subscore (0–6 points) and delayed-recall subscore (0–5 points) were extracted as domain-specific measures, with higher scores indicating better performance. Executive task performance was additionally assessed using the classification-switching task employed in the rehabilitation program, for which completion time was recorded in seconds and a shorter time indicated better performance; this task was a locally used rehabilitation performance measure rather than a separately validated cognitive scale.
Evaluation of cognitive rehabilitation process performance
Process performance during cognitive rehabilitation training was extracted to reflect patients' recovery in specific training tasks, including memory task accuracy, attention task completion rate, digit span or sequence repetition performance, classification-switching task completion time, and number of cognitive training interruptions.
Evaluation of nutritional status
Nutritional status was assessed primarily with the MNA-SF13, with body mass index (BMI) recorded as an anthropometric measure. Albumin (ALB) and prealbumin (PA) were analyzed as supportive biochemical parameters rather than direct or independent markers of nutritional status because they are influenced by systemic illness and inflammatory status; hemoglobin (HGB) was included as a supportive hematologic parameter because anemia may coexist with inadequate intake and chronic disease, but it was not treated as a nutrition-specific marker.
Evaluation of the ability to perform daily living tasks
The ability to perform daily living tasks was evaluated from four aspects: basic activities of daily living, instrumental activities of daily living, functional independence, and specific life-task execution ability; basic activities of daily living were evaluated using the Barthel index14, including eating, bathing, grooming, dressing, bowel control, bladder control, toileting, bed-chair transfer, walking on level ground, and stair climbing; the Instrumental Activities of Daily Living (IADL) scale15 was used to evaluate patients' task-processing ability in more complex living scenarios; the motor and cognitive dimensions of the Functional Independence Measure (FIM) scale16 were used to reflect patients' level of functional independence; medication-management ability was assessed by the responsible nurse during discharge preparation using nursing and discharge-guidance records together with a structured teach-back and simulated medication-taking task. The denominator comprised all patients in each group with a prescribed discharge medication regimen (69 in the observation group and 81 in the control group); “correctly repeat and carry out the medication regimen” required the patient to correctly identify the prescribed medications, state the prescribed timing and dose, repeat the complete regimen, and demonstrate the medication-taking sequence without corrective prompting from the nurse.
Safety and continuity-of-care outcomes
Individual safety outcomes included falls, aspiration or aspiration pneumonia, and unplanned readmission occurring from hospital discharge through completion of the 4-week post-discharge follow-up; events occurring during the index hospitalization were not included in these follow-up safety outcomes. A post hoc exploratory composite was defined as the occurrence of at least one of these three events during follow-up; because the components have different mechanisms and risk factors, the composite was used only as a summary exploratory measure. Continuity-of-care outcomes included post-discharge follow-up completion and completion of nursing-plan adjustment during follow-up.
Data quality control
To reduce information bias in this retrospective study, the research team standardized variable definitions and developed a standardized data extraction form prior to data extraction. Two trained researchers independently extracted the data and cross-checked key variables; when discrepancies occurred, a third researcher made the decision based on original medical records, nursing records, and laboratory system records. All 150 included patients had complete data for the primary and secondary outcomes, and no imputation was performed. General implementation and adherence indicators, including cognitive-training completion, nutritional-plan implementation, ADL-training completion, family participation, and post-discharge follow-up completion, were available from routine nursing documentation in both groups. In contrast, the detailed task-level cognitive rehabilitation performance variables, memory task accuracy, attention task completion rate, digit span/sequence repetition performance, classification-switching task completion time, and number of training interruptions, were systematically recorded only for the 69 observation-group patients and therefore were not compared between groups. Dysphagia severity, route of nutritional intake, and comorbidity burden were not consistently available as structured variables and therefore could not be included as baseline covariates.
Statistical analysis
All commercial software and materials used in this study, including statistical analysis software, are presented in the Table of Materials. Continuous variables were tested for normality; normally distributed variables were expressed as mean ± standard deviation and compared between groups using the independent-samples t test, whereas non-normally distributed variables were expressed as median (interquartile range) and compared using the Mann-Whitney U test. Within-group pre-post comparisons were performed using the paired-samples t test when appropriate. Categorical variables were expressed as counts and percentages and compared using the chi-square test or Fisher's exact test. For key comparisons, effect estimates were reported as mean differences or odds ratios (ORs) with 95% confidence intervals (CIs). To address measured confounding, multivariable linear regression models were fitted for post-intervention MoCA, MMSE, MNA-SF, Barthel index, IADL, FIM motor, and FIM cognitive scores, with the nursing model as the main exposure and adjustment for age, sex, education level, primary neurological diagnosis, disease course, cognitive impairment severity, and the corresponding baseline outcome. A sensitivity analysis restricted to patients with stroke was performed for MoCA, MNA-SF, and Barthel index. Because one primary outcome was specified for analytical reporting and the remaining outcomes were secondary or exploratory, no formal multiplicity adjustment was applied to the latter analyses, whose P values were interpreted descriptively. All tests were two-sided, and P < 0.05 was considered statistically significant for the primary analysis.
结果
Comparison of baseline data
No statistically significant between-group differences were detected in the measured baseline characteristics, including baseline MoCA, MMSE, MNA-SF, Barthel, IADL, and FIM scores (all P > 0.05); these comparisons were used descriptively and were not interpreted as evidence of baseline equivalence (Table 2). Stroke was the most frequent diagnosis (82/150, 54.67%), followed by Parkinson's disease (30/150, 20.00%), traumatic brain injury (17/150, 11.33%), and epilepsy/other neurological disorders (21/150, 14.00%).
Intervention implementation quality and adherence
Among the routinely documented implementation and adherence indicators available in both groups, cognitive-training completion, nutritional-plan implementation, ADL-training completion, family participation, and post-discharge follow-up completion favored the observation group (Table 3).
Changes in cognitive function
After intervention, cognitive function improved in both groups compared with admission, but the observation group showed a greater magnitude of improvement (P < 0.001); further analysis of cognitive dimensions showed that the improvements in attention and delayed recall in the observation group exceeded those in the control group (P < 0.001), while the decrease in executive function completion time was also greater (P < 0.001), suggesting more sufficient improvement in task-processing efficiency (Figure 1).
Cognitive rehabilitation process performance
Because complete records of cognitive rehabilitation process indicators were available only in the observation group, this part compared the observation group before and after training. At the final training stage, memory task accuracy increased from 55.20 ± 14.40% to 70.80 ± 13.60%, and the attention task completion rate increased from 61.39 ± 15.20% to 78.61 ± 13.09% (P < 0.001). The digit span/sequence repetition score was higher than that at the initial training stage, while the classification-switching task completion time decreased from 96.07 ± 23.83 s to 80.42 ± 21.19 s (P < 0.001). In addition, the number of cognitive training interruptions decreased (P < 0.001) (Table 4).
Changes in nutritional status
Changes in nutritional assessment and related biochemical measures generally favored the observation group. Compared with the control group, the observation group showed greater increases in MNA-SF (between-group mean difference in change, 1.24 points; 95% CI, 0.88–1.60; P < 0.001), ALB (1.70 g/L; 95% CI, 0.95–2.45; P < 0.001), PA (20.99 mg/L; 95% CI, 11.79–30.20; P < 0.001), and HGB (3.79 g/L; 95% CI, 1.31–6.27; P = 0.003). The between-group difference in BMI change was smaller but remained statistically significant (0.49 kg/m2; 95% CI, 0.11–0.88; P = 0.012) (Figure 2).
Changes in the ability to perform daily living tasks
The Barthel index increased by 19.64 ± 7.09 points in the observation group and by 9.99 ± 8.28 points in the control group, corresponding to a between-group mean difference in change of 9.65 points (95% CI, 7.14–12.16; P < 0.001). The corresponding between-group differences were 1.09 points for IADL (95% CI, 0.78–1.41), 6.56 points for the FIM motor score (95% CI, 4.15–8.97), and 2.76 points for the FIM cognitive score (95% CI, 1.84–3.68), with all P < 0.001. After intervention, 43 of 69 patients (62.32%) in the observation group and 34 of 81 patients (41.98%) in the control group could correctly repeat and carry out the medication regimen (OR, 2.29; 95% CI, 1.19–4.41; P = 0.013) (Table 5).
Adjusted analyses and sensitivity analysis
After adjustment for age, sex, education level, primary neurological diagnosis, disease course, cognitive impairment severity, and the corresponding baseline outcome, receipt of the integrated collaborative nursing model remained associated with higher post-intervention MoCA, MMSE, MNA-SF, Barthel, IADL, FIM motor, and FIM cognitive scores (all P < 0.001; Table 6). In the sensitivity analysis restricted to patients with stroke (n = 82), the adjusted between-group differences were 2.17 points for MoCA (95% CI, 1.35–3.00), 1.39 points for MNA-SF (95% CI, 0.89–1.89), and 12.39 points for the Barthel index (95% CI, 8.51–16.27), with all P < 0.001.
Safety and continuity-of-care outcomes
During follow-up, falls occurred in 2 of 69 patients in the observation group and 8 of 81 patients in the control group (OR, 0.27; 95% CI, 0.06–1.33; P = 0.109), aspiration or aspiration pneumonia occurred in 3 of 69 and 10 of 81 patients, respectively (OR, 0.32; 95% CI, 0.09–1.22; P = 0.083), and unplanned readmission occurred in 4 of 69 and 12 of 81 patients, respectively (OR, 0.35; 95% CI, 0.11–1.15; P = 0.075); none of these individual comparisons reached statistical significance. In the post hoc exploratory composite, 6 of 69 patients (8.70%) in the observation group and 17 of 81 patients (20.99%) in the control group experienced at least one event (OR, 0.36; 95% CI, 0.13–0.97; P = 0.037). Completion of nursing-plan adjustment during follow-up was 69.57% versus 46.91% (OR, 2.59; 95% CI, 1.32–5.07; P = 0.005) (Table 7).
DATA AVAILABILITY:
Raw data from this study have been uploaded as Supplementary File 1.
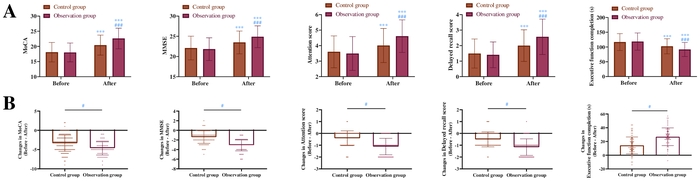
Figure 1: Cognitive function and task-processing efficiency before and after intervention. (A) Between-group comparison of MoCA score, MMSE score, attention score, delayed recall score, and executive function completion time before and after intervention; (B) Between-group comparison of change values in MoCA score, MMSE score, attention score, delayed recall score, and executive function completion time. vs before ***P < 0.01; vs after ###P < 0.01. Abbreviations: MoCA, Montreal Cognitive Assessment; MMSE, Mini-Mental State Examination. Please click here to view a larger version of this figure.
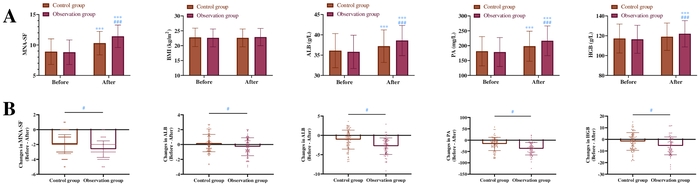
Figure 2: Nutritional status before and after intervention. (A) Between-group comparison of MNA-SF score, BMI, ALB, PA, and HGB before and after intervention; (B) Between-group comparison of change values in MNA-SF score, BMI, ALB, PA, and HGB. vs before ***P < 0.01; vs after ###P < 0.01. Abbreviations: MNA-SF, Mini Nutritional Assessment-Short Form; BMI, body mass index; ALB, albumin; PA, prealbumin; HGB, hemoglobin. Please click here to view a larger version of this figure.
Table 1: Delivery framework of the integrated collaborative nursing model. This table summarizes the personnel responsible for each component, intervention timing and frequency, principal nursing procedures, individualized adjustments, and quality-control requirements used throughout hospitalization and the 4-week post-discharge period. Please click here to download this Table.
Abbreviations: ADL, activities of daily living; MoCA, Montreal Cognitive Assessment; MMSE, Mini-Mental State Examination; MNA-SF, Mini Nutritional Assessment-Short Form; IADL, instrumental activities of daily living; FIM, Functional Independence Measure; BMI, body mass index; ALB, albumin; PA, prealbumin; HGB, hemoglobin; h, hours; min, minutes.
Table 2: Baseline demographic and clinical characteristics of the study groups. This table presents demographic characteristics, primary neurological diagnoses, disease-related variables, and baseline cognitive, nutritional, and functional assessments in the control and observation groups. Please click here to download this Table.
Abbreviations: BMI, body mass index; MoCA, Montreal Cognitive Assessment; MMSE, Mini-Mental State Examination; MNA-SF, Mini Nutritional Assessment-Short Form; IADL, instrumental activities of daily living; FIM, Functional Independence Measure.
Table 3: Implementation and adherence indicators documented in both nursing groups. This table compares routinely documented cognitive-training completion, nutritional-plan implementation, ADL-training completion, family participation, and post-discharge follow-up completion between the control and observation groups.
Abbreviations: ADL, activities of daily living; OR, odds ratio; CI, confidence interval. Please click here to download this Table.
Table 4: Cognitive rehabilitation performance during inpatient training in the observation group. This table presents within-group changes in memory task accuracy, attention task completion, digit span or sequence repetition, classification-switching task completion time, and cognitive-training interruptions between the initial and final documented training stages. Please click here to download this Table.
Table 5: Changes in daily living performance and functional independence. This table compares baseline and final Barthel index, IADL, and FIM outcomes between the control and observation groups and presents medication-management performance at the prespecified assessment time point.
Abbreviations: IADL, instrumental activities of daily living; FIM, Functional Independence Measure. Please click here to download this Table.
Table 6: Adjusted associations between nursing model and post-intervention outcomes. This table presents adjusted between-group differences in post-intervention cognitive, nutritional, and functional outcomes after controlling for age, sex, education level, primary neurological diagnosis, disease course, cognitive impairment severity, and the baseline value of the corresponding outcome.
Abbreviations: MoCA, Montreal Cognitive Assessment; MMSE, Mini-Mental State Examination; MNA-SF, Mini Nutritional Assessment-Short Form; IADL, instrumental activities of daily living; FIM, Functional Independence Measure; CI, confidence interval.
NOTE: Adjusted mean differences compare the observation group with the control group. Models were adjusted for age, sex, education level, primary neurological diagnosis, disease course, cognitive impairment severity, and the baseline value of the corresponding outcome. Please click here to download this Table.
Table 7: Safety events and continuity-of-care outcomes during the 4-week follow-up. This table presents falls, aspiration or aspiration pneumonia, unplanned readmission, the exploratory composite safety outcome, and completion of nursing-plan adjustment during the post-discharge follow-up period.
Abbreviations: OR, odds ratio; CI, confidence interval. Please click here to download this Table.
Supplementary File 1: Raw data for this study. This file contains the de-identified patient-level data used for the retrospective analyses, including demographic and clinical characteristics, cognitive, nutritional, functional, implementation, adherence, safety, and continuity-of-care outcome variables.Please click here to download this file.
讨论
Based on retrospective data, this study analyzed the application of an integrated collaborative nursing model guided by multidimensional cognitive rehabilitation in patients with cognitive impairment associated with neurological disorders. The results suggested that, compared with routine nursing, receipt of the integrated collaborative nursing model was associated with better nursing implementation, cognitive, nutritional-assessment, functional, and some short-term continuity-of-care outcomes. However, because this study was not a randomized controlled study, these results should be interpreted as an association between this nursing model and improved rehabilitation outcomes, rather than as a direct effect of a single nursing measure.
From the perspective of process indicators, the observation group had higher cognitive training completion, nutritional nursing plan implementation, ADL training completion, family participation, and post-discharge follow-up completion rates than the control group. This pattern is clinically understandable. Although routine nursing covers condition observation, medication guidance, basic care, discharge education, and other content, if sufficient reporting of implementers, intervention dose, individualized adjustment, and follow-up methods is lacking, its reproducibility and clinical implementation may be limited17,18. The collaborative nursing model used in this study integrated admission assessment, inpatient training, nutritional management, training in daily living tasks, family education, and post-discharge follow-up into a continuous process, clarifying nursing goals and record content. Evidence from stroke rehabilitation suggests that caregiver and family support may contribute to rehabilitation participation and recovery-related outcomes; this diagnosis-specific evidence supports the rationale for caregiver involvement but should not be generalized automatically to all neurological disorders included in the present cohort19.
Cognitive improvement was one of the principal associations observed in this study; however, reality orientation, attention training, individualized adjustment of task difficulty, nutritional management, and family support were delivered concurrently, so the present design cannot determine the independent contribution of any component or establish a specific mechanism. Evidence supporting reality orientation is derived in part from patients with Parkinson’s disease dementia, whereas broader cognitive rehabilitation evidence includes other neurological populations; these studies support the clinical plausibility of individual components but should not be interpreted as demonstrating the same response across stroke, traumatic brain injury, epilepsy, and other neurological disorders20,21. In the stroke-restricted sensitivity analysis, the adjusted between-group difference in MoCA was 2.17 points; a stroke-rehabilitation study estimated the MoCA minimal clinically important difference at 1.22 points using an anchor-based approach and 2.15 points using a distribution-based approach, suggesting that the observed magnitude may be clinically relevant in the stroke subgroup, although this benchmark cannot be generalized to the entire heterogeneous cohort22.
Changes in nutritional status provided another analytical perspective on the comprehensive effect of the nursing model. Diagnosis-specific evidence, particularly from stroke populations, indicates that dysphagia and reduced intake can complicate nutritional management; these findings support the rationale for swallowing and nutritional surveillance, although their applicability may differ across the neurological diagnoses represented in this cohort23,24. In the observation group, nutritional risk screening, daily food intake recording, food texture adjustment, aspiration risk observation, and family guidance were incorporated into the nursing process, which may have increased the chance that nutritional risks were identified and handled in a timely manner. Among the nutritional outcomes, MNA-SF provides the most direct assessment of nutritional status in the present study. ALB and PA were interpreted only as supportive biochemical findings because both are influenced by systemic inflammation, acute illness, hepatic function, hydration status, and other clinical factors; consistent with the ASPEN position paper, neither was considered a direct or independent marker of nutritional improvement25; HGB was likewise interpreted as a nonspecific hematologic parameter because anemia has multiple nutritional and non-nutritional determinants. By contrast, although BMI showed a between-group difference, the magnitude of change was small, presumably because weight-related indicators are affected by baseline body size, fluid status, activity level, and observation time26, and therefore should not be used as the sole basis for short-term nutritional improvement.
The larger changes in Barthel, IADL, and FIM scores in the observation group were consistent with better short-term functional performance, although the multicomponent design does not allow these associations to be attributed separately to cognitive training, functional training, or family support. In the stroke-restricted analysis, the adjusted between-group difference in the Barthel index was 12.39 points on the 100-point scale; for context, Hsieh et al. estimated a minimal clinically important difference of 1.85 points for the 20-point Barthel Index in patients with stroke, equivalent by linear rescaling to 9.25 points on a 100-point scale, although this threshold remains diagnosis- and setting-specific27. However, safety and continuity-of-care outcomes should be interpreted with greater caution. In this study, the incidence rates of falls, aspiration or aspiration pneumonia, and unplanned readmission in the observation group were lower than those in the control group, but single events did not reach statistical significance. This may be related to the limited sample size, low event rates, and short follow-up time. The post hoc composite event rate was lower in the observation group; however, because this exploratory measure combined clinically distinct outcomes with different mechanisms and was not specified as a confirmatory endpoint before the analysis, it should be interpreted cautiously and does not establish a protective effect of the nursing model on safety outcomes. For such low-incidence outcomes, larger samples and longer follow-up periods are still needed for verification.
Several limitations should be acknowledged. First, this was a single-center retrospective study in which exposure to the nursing model was not randomly assigned; selection bias and residual confounding therefore remain possible despite multivariable adjustment, and the absence of statistically significant baseline differences should not be interpreted as evidence of group equivalence. A reliable count of records excluded before cohort construction solely because of incomplete documentation could not be reconstructed, which may further contribute to selection bias. Second, the cohort combined several neurological diagnoses with different pathophysiology, disease trajectories, nutritional risks, and rehabilitation potential; although primary diagnosis was included in the adjusted models and a stroke-restricted sensitivity analysis showed consistent findings, the pooled estimates should not be interpreted as diagnosis-specific effects. Third, dysphagia severity, route of nutritional intake, and comorbidity burden were not consistently available as structured variables, while cognitive rehabilitation process measures were routinely documented only in the observation group; these limitations prevented adjustment for several clinically relevant factors and direct between-group comparison of the process measures. Finally, follow-up was limited to 4 weeks after discharge, so the findings describe short-term associations and cannot establish sustained cognitive, nutritional, functional, safety, or readmission-related benefits. Receipt of the integrated collaborative nursing model centered on multidimensional cognitive rehabilitation was associated with better nursing implementation and with short-term cognitive, nutritional assessment, and functional outcomes. Because the study was retrospective, non-randomized, clinically heterogeneous, and limited to 4 weeks of post-discharge follow-up, these findings do not establish causal or sustained effectiveness.
披露
The authors declare no conflicts of interest.
材料
| 姓名 | 公司 | 目录编号 | 评论 |
|---|---|---|---|
| Aspiration risk observation checklist | Local hospital nursing department | Local aspiration-risk nursing checklist | Used to record eating posture, eating speed, choking, wet voice, pharyngeal residue sensation, and other swallowing-related abnormalities. |
| Attention training materials | Local hospital rehabilitation/nursing department | Number search, color recognition, simple calculation, and target-search sheets | Used to train sustained attention and selective attention during cognitive rehabilitation. |
| Barthel Index | Mapi Research Trust ePROVIDE / published clinical scale | Barthel Index, 10-item ADL assessment form | Used to evaluate basic activities of daily living (ADL), including eating, bathing, grooming, dressing, bowel control, bladder control, toileting, transfer, walking, and stair climbing. |
| Body mass index (BMI) assessment | Local hospital system | Height and weight records from local anthropometric equipment | Used to calculate BMI from height and body weight records for nutritional status evaluation. |
| Cognitive rehabilitation task materials | Local hospital rehabilitation/nursing department | Local cognitive rehabilitation task set | Used for reality orientation, attention, memory, and executive function training during daily cognitive rehabilitation nursing. |
| Electronic medical record system | Local hospital system | Local EMR system | Used to retrieve demographic data, diagnoses, hospitalization records, medical records, and outcome-related information. |
| Executive function training materials | Local hospital rehabilitation/nursing department | Classification, sequencing, step-planning, and simple problem-solving sheets | Used to train task switching, planning, categorization, sequencing, and simple problem solving. |
| Family education record form | Local hospital nursing department | Local health education signature form | Used to document family participation, caregiver training, discharge guidance, and caregiver understanding of nursing instructions. |
| Food intake record sheet | Local hospital nursing department/nutrition department | Daily food intake record form | Used to record food intake and support evaluation of energy and protein intake during nutritional nursing. |
| Functional Independence Measure (FIM) | Uniform Data System for Medical Rehabilitation / Netsmart | FIM instrument; motor and cognitive domains | Used to evaluate functional independence through motor and cognitive dimensions. |
| Hemoglobin test record | Local clinical laboratory; analyzer/reagent vendor not reported | Routine hematology test record for HGB | Used to retrieve HGB results from the LIS for nutritional status evaluation. |
| Instrumental Activities of Daily Living (IADL) scale | Mapi Research Trust ePROVIDE / Lawton-Brody scale | IADL clinical assessment form | Used to evaluate task-processing ability in more complex daily living scenarios. |
| Laboratory information system | Local hospital system | Local LIS system | Used to retrieve laboratory indicators, including albumin (ALB), prealbumin (PA), and hemoglobin (HGB). |
| Memory training materials | Local hospital rehabilitation/nursing department | Picture recall cards, word repetition sheets, event recall prompts, and daily object cards | Used to train immediate recall, delayed recall, recognition, and memory retrieval. |
| Mini Nutritional Assessment-Short Form (MNA-SF) | Nestlé / Mapi Research Trust ePROVIDE | MNA-SF 6-item short form | Used to evaluate nutritional risk and screen for malnutrition or risk of malnutrition. |
| Mini-Mental State Examination (MMSE) | Psychological Assessment Resources, Inc. | Standard 30-point MMSE assessment form | Used to evaluate orientation, memory, attention and calculation, recall, and language function. |
| Montreal Cognitive Assessment (MoCA) | MoCA Cognition | Standard 30-point MoCA assessment form | Used to evaluate global cognitive function, including visuospatial/executive function, naming, attention, language, abstraction, delayed recall, and orientation. |
| Nursing documentation system | Local hospital nursing department | Local nursing record system | Used to extract admission nursing assessments, risk assessments, intervention implementation records, family education records, discharge guidance, and follow-up-related nursing information. |
| Nutritional nursing plan form | Local hospital nursing department/nutrition department | Local nutritional nursing plan template | Used to document nutritional risk, dietary guidance, food texture adjustment, intake monitoring, and nursing recommendations. |
| Online follow-up platform | Local hospital follow-up center | Local online follow-up platform | Used as an alternative follow-up method for post-discharge assessment, nursing guidance, and risk feedback. |
| Pill organizer | Local hospital nursing department/supply office | Weekly pill box | Used in medication-management training to help patients classify medications and simulate medication-taking procedures. |
| Post-discharge follow-up record form | Local hospital nursing department/follow-up center | Local telephone or online follow-up form | Used to record follow-up completion at weeks 1, 2, and 4 after discharge, adverse events, readmission, and nursing plan adjustment. |
| Prealbumin test record | Local clinical laboratory; analyzer/reagent vendor not reported | Routine clinical chemistry test record for PA | Used to retrieve PA results from the LIS for nutritional status evaluation. |
| Reality orientation cue materials | Local hospital rehabilitation/nursing department | Date, place, person, and hospitalization-context cue cards | Used to support orientation to time, place, person, and hospitalization context. |
| Rehabilitation training record form | Local hospital rehabilitation/nursing department | Local standardized rehabilitation training form | Used to record cognitive rehabilitation tasks, task completion, accuracy, number of prompts, interruptions, and training tolerance. |
| Serum albumin test record | Local clinical laboratory; analyzer/reagent vendor not reported | Routine clinical chemistry test record for ALB | Used to retrieve ALB results from the LIS for nutritional status evaluation. |
| Standardized data extraction form | Study team | Retrospective data extraction form | Used by two trained researchers to extract and cross-check variables from EMR, LIS, nursing records, rehabilitation records, and follow-up data. |
| Statistical analysis software | IBM | SPSS Statistics 26.0 | Used for normality testing, independent-samples t tests, Mann–Whitney U tests, chi-square tests, Fisher’s exact tests, and multivariable statistical analyses. |
| Telephone follow-up system | Local hospital follow-up center | Local telephone follow-up workflow | Used to complete follow-up at weeks 1, 2, and 4 after discharge. |
参考文献
- Cramer SC, Richards LG, Bernhardt J, Duncan P. Cognitive deficits after stroke. Stroke. 2023;54(1):5–9.
- World Health Organization. Dementia. World Health Organization. 2026. Available from: https://www.who.int/news-room/fact-sheets/detail/dementia. Accessed September 3, 2026.
- Ma Y, et al. Prevalence and risk factors of poststroke cognitive impairment: a systematic review and meta-analysis. Public Health Nurs. 2025;42(2):1047–1059.
- El Husseini N, et al. Cognitive impairment after ischemic and hemorrhagic stroke: a scientific statement from the American Heart Association/American Stroke Association. Stroke. 2023;54(6):e272–e291.
- O'Donoghue M, et al. Rehabilitation of cognitive deficits poststroke: systematic review and meta-analysis of randomized controlled trials. Stroke. 2022;53(5):1700–1710.
- Assis APM, et al. The association between nutritional status, advanced activities of daily living, and cognitive function among Brazilian older adults living in care homes. Geriatr Nurs. 2020;41(6):899–904.
- Signal N, Gomes E, Olsen S, Alder G. Enhancing the reporting quality of rehabilitation interventions through an extension of the Template for Intervention Description and Replication (TIDieR): the TIDieR-Rehab checklist and supplementary manual. BMJ Open. 2024;14(11):e084320.
- Skivington K, et al. A new framework for developing and evaluating complex interventions: update of Medical Research Council guidance. BMJ. 2021;374:n2061.
- Gibson E, et al. Occupational therapy for cognitive impairment in stroke patients. Cochrane Database Syst Rev. 2022;3(3):CD006430.
- Shimazu S, et al. Frequent and personalized nutritional support leads to improved nutritional status, activities of daily living, and dysphagia after stroke. Nutrition. 2021;83:111091.
- Wei X, et al. MoCA and MMSE for the detection of post-stroke cognitive impairment: a comparative diagnostic test accuracy systematic review and meta-analysis. J Neurol. 2025;272(6):407.
- Zhu Y, et al. Evaluation of the Mini-Mental State Examination and the Montreal Cognitive Assessment for predicting post-stroke cognitive impairment during the acute phase in Chinese minor stroke patients. Front Aging Neurosci. 2020;12:236.
- Krishnamoorthy Y, Vijayageetha M, Saya GK. Validation and reliability assessment of the Mini-Nutritional Assessment-Short Form questionnaire among older adults in South India. Indian J Community Med. 2021;46(1):70–74.
- Aminalroaya R, et al. The validation study of both the modified Barthel and Barthel Index, and their comparison based on Rasch analysis in the hospitalized acute stroke elderly. Int J Aging Hum Dev. 2021;93(3):864–880.
- Isik EI, Yilmaz S, Uysal I, Basar S. Adaptation of the Lawton Instrumental Activities of Daily Living Scale to Turkish: validity and reliability study. Ann Geriatr Med Res. 2020;24(1):35–40.
- Peleg DA, Justo D. [Functional Independence Measure scale scores in severely dependent older adults upon rehabilitation completion following stroke]. Harefuah. 2024;163(6):359–364. Hebrew.
- Cao L, et al. Evaluating intervention reporting in nursing journal RCTs using the TIDieR checklist: a cross-sectional study. J Adv Nurs. 2025;81(9):5963–5972.
- Rhon DI, et al. TIDieR-telehealth: precision in reporting of telehealth interventions used in clinical trials – unique considerations for the Template for the Intervention Description and Replication (TIDieR) checklist. BMC Med Res Methodol. 2022;22(1):161.
- Okwaraji G, et al. The role of family social support in stroke recovery and desired rehabilitation outcomes in U.S. adults: a scoping review. Top Stroke Rehabil. 2026;33(2):208–220.
- Camargo CHF, et al. The effectiveness of reality orientation therapy in the treatment of Parkinson disease dementia. Am J Alzheimers Dis Other Demen. 2019;34(2):124–130.
- Cicerone KD, et al. Evidence-based cognitive rehabilitation: systematic review of the literature from 2009 through 2014. Arch Phys Med Rehabil. 2019;100(8):1515–1533.
- Wu CY, et al. Responsiveness, minimal clinically important difference, and validity of the MoCA in stroke rehabilitation. Occup Ther Int. 2019;2019:2517658.
- Liu T, et al. Influence of nutritional status on prognosis of stroke patients with dysphagia. Altern Ther Health Med. 2022;28(7):26–33.
- Braun RG, Arata J, Gonzalez-Fernandez M. Dysphagia and enteral feeding after stroke in the rehabilitation setting. Phys Med Rehabil Clin N Am. 2024;35(2):433–443.
- Evans DC, et al. The use of visceral proteins as nutrition markers: an ASPEN position paper. Nutr Clin Pract. 2021;36(1):22–28.
- Wu Y, Li D, Vermund SH. Advantages and limitations of the body mass index (BMI) to assess adult obesity. Int J Environ Res Public Health. 2024;21(6):757.
- Hsieh YW, et al. Establishing the minimal clinically important difference of the Barthel Index in stroke patients. Neurorehabil Neural Repair. 2007;21(3):233–238.