Diese bibliometrische und visualisierte Analyse veranschaulicht die Entwicklung der Forschung zur Unterdruckwundtherapie (NPWT) von 1991 bis 2026. Sie fasst Publikationsmuster, Kooperationsnetzwerke, einflussreiche Quellen sowie thematische Übergänge von mechanistischen Studien hin zur Wundversorgung, Wundauflagen, Infektionsprävention und Bewertung klinischer Ergebnisse zusammen.
Forschungsartikel
Forschung zur Vakuumtherapie bei Wunden: Eine bibliometrische und visualisierte Analyse der Web of Science Core Collection
* These authors contributed equally
In diesem Artikel
Zusammenfassung
Zusammenfassung
Die Vakuumtherapie bei Wunden (NPWT) wird in der Chirurgie und Wundversorgung häufig eingesetzt, doch ihre langfristige intellektuelle Struktur und die Muster wissenschaftlicher Zusammenarbeit sind bislang unvollständig beschrieben. Wir durchsuchten 5.957 Datensätze aus der Web of Science Core Collection und führten eine bibliometrische sowie visualisierte Analyse von 4.063 eingeschlossenen Artikeln und Übersichtsarbeiten durch. Die Datensätze wurden unabhängig voneinander von zwei Forschern geprüft, und Uneinigkeiten wurden im Konsensverfahren gelöst. Mithilfe von VOSviewer, CiteSpace und ergänzenden statistischen Werkzeugen wurden Publikationstrends, Kooperationsnetzwerke, Schlüsselwort-Ko-Occurrence, Zitierungsanstiege und länderübergreifende Muster analysiert. Die Publikationsaktivität stieg deutlich nach 2004 an. Die Vereinigten Staaten und China erwiesen sich als die produktivsten Länder, während europäische und US-amerikanische Institutionen zentrale Positionen in den Kooperationsnetzwerken einnahmen. Der thematische Schwerpunkt verlagerte sich von der Untersuchung des subatmosphärischen Drucks, der Perfusion und mechanistischen Forschung hin zur Wundversorgung, Wundauflagen, chirurgischen Wundinfektionen, diabetischen Fußulzera und der Wirksamkeit der Therapie. Diese Ergebnisse beschreiben die Entwicklung der NPWT-Forschung und identifizieren Prioritäten für multizentrische klinische Studien, mechanistische Untersuchungen, Materialinnovationen und internationale Zusammenarbeit.
Einleitung
Die Vakuumtherapie bei Wunden (NPWT) ist eine weit verbreitete klinische Methode, die die Wundheilung fördert, indem lokal ein Unterdruck erzeugt wird, um Gewebeödeme zu reduzieren, Exsudat zu entfernen und die Infektionskontrolle zu unterstützen. Sie wurde bereits bei diabetischen Fußulzera1,2, offenen Bauchwunden3,4, traumatischen Weichteifdefekten und orthopädischen Wunden5,6 angewandt. Pionierhafte experimentelle und klinische Berichte aus dem Jahr 1997 legten die biologische Grundlage und klinische Machbarkeit der vakuumunterstützten Wundverschließung fest7,8. Vorgeschlagene Wirkmechanismen umfassen mikrodeformationsinduzierte Zellproliferation9, Angiogenese10 und eine verbesserte lokale Perfusion. In den letzten drei Jahrzehnten hat sich der klinische Anwendungsbereich der NPWT in Richtung individualisierter Therapieansätze und gerätebasierter Innovationen erweitert, darunter die NPWT mit Instillation11.
Trotz ihrer weiten Verbreitung bleibt unklar, wie stark die klinischen Belege für die Vakuumtherapie (NPWT) sind12. Eine Cochrane-Übersichtsarbeit aus dem Jahr 2014 fand keine ausreichenden Hinweise auf klare Vorteile bei operativen Wunden, die primär heilen, und wies auf den möglichen Einfluss kommerzieller Förderung hin13. Eine spätere Aktualisierung der Cochrane-Analyse berichtete über Unsicherheiten hinsichtlich mehrerer klinisch wichtiger Ergebnisse, obwohl NPWT in bestimmten Anwendungsbereichen möglicherweise die Rate von Operationsstelle-Infektionen senken kann14. Daher sind ausreichend große, unabhängig finanzierte Studien erforderlich, insbesondere bei chirurgischen Patientengruppen mit hohem Risiko. Auch die optimalen Druckeinstellungen, die Auswahl der Verbände, standortspezifische Protokolle sowie langfristige prognostische Faktoren sind noch nicht vollständig definiert. Die Forschungstätigkeit ist geografisch ungleich verteilt. Grundlegende experimentelle und klinische Studien zur NPWT wurden von US-amerikanischen Forschungsgruppen durchgeführt, und nachfolgende globale Analysen zeigen, dass Institutionen aus den USA und Europa zu führenden Beiträgern im Forschungs- und Kooperationsnetzwerk des Fachgebiets wurden7,8,15. Chinesische Forschungsgruppen haben inzwischen einen wachsenden Bestand an klinischen Belegen zu diabetischen Fußulzera1, Verbrennungen16 und orthopädischen sowie offenen Frakturwunden beigetragen17. In dem vorliegenden Datensatz wurden chinesische Publikationen jedoch häufiger innerhalb einlandischer Forschungsnetzwerke erstellt, und die Beteiligung an multinationalem Austausch war geringer als bei mehreren etablierten US-amerikanischen und europäischen Gruppen. Diese Ergebnisse verdeutlichen Möglichkeiten, die multinationale Zusammenarbeit sowie die mechanistisch ausgerichtete Forschung zur NPWT zu stärken.
Die bibliometrische Analyse bietet einen quantitativen Rahmen, um Publikationstrends, Kooperationsnetzwerke, einflussreiche Beiträger, Kernzeitschriften, vielzitierte Studien und aufkommende Themen abzubilden. Obwohl bereits eine bibliometrische Analyse der NPWT veröffentlicht wurde15, bleibt eine umfassende Bewertung der Publikationstrends, Kooperationsnetzwerke, einflussreichen Quellen und der thematischen Entwicklung begrenzt. Die vorliegende Studie kartierte daher die Publikationstrends, Kooperationsnetzwerke, einflussreichen Quellen und die thematische Entwicklung in der NPWT-Forschung.
Protokoll
Der vollständige bibliometrische Workflow umfasst die Literatursuche, die Beurteilung der Eignung, die Überprüfung auf Duplikate und verschiedene Versionen, die unabhängige Relevanzprüfung, die Standardisierung der Daten, die deskriptive Analyse, die Netzwerkanalyse und die Visualisierung. Die Rohdatensätze, die Entscheidungen zur Studienauswahl und das Paket für die reproduzierbare Analyse sind in Supplemental File 1, Supplemental File 2 und Supplemental File 3 enthalten.
Datenquelle und Suchstrategie
Die bibliometrische Analyse wurde mithilfe der Web of Science Core Collection (WoSCC) durchgeführt, wobei der Science Citation Index Expanded (SCI-EXPANDED/SCIE) als Datenquelle ausgewählt wurde. Der Publikationszeitraum war auf den 1. Januar 1991 bis zum 30. Juni 2026 beschränkt; daher repräsentiert der Publikationskohorte des Jahres 2026 ein unvollständiges Jahr, da das Suchfenster am 30. Juni 2026 endete.
Es wurde die folgende Suchstrategie angewendet: TS=("negative pressure wound therapy" OR "vacuum assisted closure" OR "vacuum sealing drainage") AND DOP=(1991-01-01/2026-06-30). Das Feld „Thema“ (TS) wurde verwendet, um Titel, Abstracts, Autoren-Schlüsselwörter und Keywords Plus zu durchsuchen, während das Feld „Veröffentlichungsdatum“ (DOP) dazu diente, den Publikationszeitraum einzuschränken.
Bei der Datensatzabfrage wurden keine Sprach- oder Dokumenttypbeschränkungen angewendet. Die Eignungsbeurteilung erfolgte nach dem Datenexport, um einen vollständigen und nachvollziehbaren Prozess der Datensatzauswahl zu gewährleisten. Die endgültige WoSCC-Suche wurde am 23. Juli 2026 durchgeführt und ergab 5.957 Datensätze, die am 24. Juli 2026 exportiert wurden. Die vollständige Suchstrategie, Informationen zu Datenbank und Index, der Datumsbereich, Such- und Exportdaten sowie der Eignungsworkflow sind in Abbildung 1 zusammengefasst und weiter dokumentiert in der Datei README Reproducible Workflow.md, die in Zusatzdatei 3 enthalten ist.
Datensatzexport und erste Datenüberprüfung
Die abgerufenen Datensätze wurden aus der Web of Science Core Collection mit ausgewähltem Vollständiger Datensatz und Zitierte Referenzen als Datensatzinhalt und Klartextdatei als Exportformat exportiert. Da der Gesamtdatensatz die maximal pro Export erlaubte Anzahl an Datensätzen überschritt, wurden die 5.957 Datensätze in 12 aufeinanderfolgenden Chargen heruntergeladen, die jeweils die Datensätze 1–500, 501–1.000, 1.001–1.500, 1.501–2.000, 2.001–2.500, 2.501–3.000, 3.001–3.500, 3.501–4.000, 4.001–4.500, 4.501–5.000, 5.001–5.500 und 5.501–5.957 umfassten.
Nach dem Export wurden die Datensätze überprüft, um sicherzustellen, dass die wichtigsten bibliographischen Felder, die für nachfolgende Analysen erforderlich sind, vorhanden waren, einschließlich der Zugangsnummer (UT), DOI, Titel, Autoren, Affiliationen, Quellzeitschrift, Erscheinungsjahr (PY), Veröffentlichungsdatum (PD), Dokumentart (DT), Sprache, Zusammenfassung, Autoren-Schlüsselwörter, Keywords Plus, Gesamtanzahl der Zitierungen (TC), Nutzungsanzahlen (U1 und U2) sowie zitierte Referenzen (CR). Die ursprünglichen Exportdateien im Nur-Text-Format wurden unverändert aufbewahrt und sind als ergänzende Datei 1 verfügbar.
Da der Nur-Text-Export von WoSCC weder die Suchverlauf-Seite noch ein dediziertes exportiertes Feld für das Veröffentlichungsdatum (DOP) beibehält, wurden der ursprüngliche Suchbegriff und das Suchdatum in Abbildung 1, dem Manuskript und der Datei README Reproducible Workflow.md dokumentiert, die in Zusatzdatei 3 enthalten ist. Die ursprüngliche DOP-Beschränkung, die während des Datenbankabrufs angewendet wurde, blieb erhalten und wurde nicht durch eine nachträgliche Filterung basierend auf dem Publikationsjahr (PY), dem Veröffentlichungsdatum (PD) oder dem Early-Access-Datum (EA) ersetzt.
Dokumenttyp-Prüfung und Rückzugsbewertung
Die 5.957 abgerufenen Datensätze wurden in den Screening-Datensatz zur Eignungsbeurteilung importiert. Ursprüngliche Forschungsartikel und Übersichtsartikel wurden ohne Anwendung sprachlicher Einschränkungen beibehalten. Dazu geeignete Web-of-Science-Dokumenttyp-Klassifikationen umfassten Artikel, Artikel; Konferenzbeitrag, Artikel; Frühveröffentlichung, Übersicht und Übersicht; Frühveröffentlichung. Frühveröffentlichung wurde als Indexierungsstatus und nicht als unabhängiger Publikationstyp behandelt, um eine doppelte Zählung derselben Publikation zu vermeiden.
Während der Screening-Phase wurden 1.078 Datensätze mit inakzeptablen Dokumenttypen ausgeschlossen, gefolgt vom Ausschluss von 59 Datensätzen, die Rückzüge betrafen. Nach der Prüfung der Dokumenttypen und der Bewertung von Rückzügen verblieben 4.820 Datensätze vom Typ Artikel und Übersichtsartikel für die Identifizierung von Duplikaten und Versionen. Die ausgeschlossenen Datensätze sowie die jeweiligen spezifischen Gründe sind in den Arbeitsblättern DT_Exclusions_1078 und Retraction_Exclusions_59 der ergänzenden Datei 2 enthalten.
Bewertung von Duplikaten und publikationsfähigen Versionen
Die Identifizierung von Duplikaten und die Bewertung der Publikationsversion erfolgte unter Verwendung der Web-of-Science-Zugangsnummer (UT) als primärer Datensatzkennung. Wenn bei Duplikaten oder verwandten Datensätzen unterschiedliche Zugangsnummern vorlagen, wurden diese anhand von DOI, normalisiertem Titel, Autoren, Quellzeitschrift, Erscheinungsjahr, Band, Ausgabe, Seitenzahlen, Abstract, Dokumenttyp und Informationen zur Publikationsversion verglichen. Für jeden Satz verwandter Datensätze wurde die endgültige oder am besten geeignete Publikationsversion beibehalten, und die Beziehung zwischen den beibehaltenen und ausgeschlossenen Datensätzen wurde dokumentiert.
Insgesamt wurden 23 doppelte oder durch neuere Versionen ersetzte Datensätze entfernt, darunter neun veraltete Cochrane-Übersichtsversionen sowie 14 verifizierte Doppeleinträge, Nachdrucke, doppelt indizierte Einträge, Übersetzungen oder sonstige verwandte Versionen. Nach der Prüfung auf Duplikate und Publikationsversionen verblieben 4.797 eindeutige Datensätze zur Bewertung der thematischen Relevanz. Die Zugangsnummern der beibehaltenen und ausgeschlossenen Datensätze, die Kriterien zur Duplikatprüfung sowie die datensatzspezifischen Begründungen sind im Arbeitsblatt Duplicate_Exclusions_23 der ergänzenden Datei 2 enthalten.
Unabhängige thematische Relevanzprüfung
Die thematische Relevanzprüfung wurde unabhängig voneinander von zwei geschulten Forschern an den 4.797 eindeutigen Datensätzen durchgeführt. Jeder Gutachter bewertete Titel, Zusammenfassung, Autoren-Schlüsselwörter und Keywords Plus jedes Datensatzes und dokumentierte eine unabhängige Entscheidung zur Aufnahme oder Ausschluss sowie eine datensatzspezifische Begründung, bevor eine Abstimmung erfolgte.
Aufzeichnungen wurden als geeignet betrachtet, wenn eine Therapie mit Unterdruck (NPWT), eine vakuumunterstützte Verschlussbehandlung (VAC) oder eine Vakuumversiegelungsdrainage (VSD) die Hauptintervention oder der Vergleichsmaßstab, die zu evaluierende Technik, ein primäres klinisches Ergebnis, Gegenstand einer mechanistischen Untersuchung, ein Leitlinien- oder Konsenspunkt oder eine wesentliche Komponente des Wundmanagementwegs darstellte. Aufzeichnungen wurden ausgeschlossen, wenn NPWT, VAC oder VSD lediglich als Hintergrundinformation erwähnt wurden, nur in einer Liste von Behandlungsoptionen enthalten waren, ausschließlich als zuvor erfolglos angewandte Behandlung oder Nichtanwendung berichtet wurden, nur als zufällige Rettungsmaßnahme verwendet wurden, lediglich als Komplikation oder Kovariate beschrieben wurden, außerhalb des Hauptthemas der Studie lagen oder nur als falsch-positiver Keywords-Plus-Begriff auftauchten.
Die unabhängigen Ausschlussentscheidungen wurden verglichen, wobei zunächst eine Übereinstimmung bei 4.782 Datensätzen erzielt wurde und Uneinigkeit bei 15 Datensätzen festgestellt wurde. Alle Unstimmigkeiten wurden durch Diskussion geklärt und gegebenenfalls durch einen dritten Forscher geschlichtet. Für jeden umstrittenen Datensatz wurden die endgültige Entscheidung und die zugrundeliegende Begründung dokumentiert. In dem überprüften Datensatz wurden letztlich alle 15 umstrittenen Datensätze ausgeschlossen, und es blieben keine ungeklärten Uneinigkeiten zurück.
Nach der Prüfung der thematischen Relevanz wurden 734 Datensätze ausgeschlossen und 4.063 Datensätze für die bibliometrische Analyse beibehalten. Ergänzende Datei 2 enthält die Entscheidungen beider Gutachter, gutachterspezifische Begründungen, Indikatoren für Uneinigkeit, endgültige Aufnahmementscheidungen, unterstützende Belege sowie den endgültigen Datensatz mit 4.063 Datensätzen.
Der endgültige Prozess zur Auswahl der Datensätze wurde intern überprüft und bestätigte, dass die 5.957 abgerufenen Datensätze 1.137 aufgrund von Dokumentart oder Rückzugsstatus ausgeschlossene Datensätze, 23 doppelte oder veraltete Datensätze, 734 bei der Relevanzprüfung ausgeschlossene Datensätze sowie 4.063 in die endgültige bibliometrische Analyse einbezogene Datensätze umfassten (5.957 = 1.137 + 23 + 734 + 4.063). Abbildung 1 zeigt ein PRISMA-artiges Flussdiagramm, das den Prozess der bibliografischen Datensatzauswahl veranschaulicht. Da diese Studie eine bibliometrische Analyse und keine systematische Übersichtsarbeit darstellt, wurde keine Bias-Risikobewertung auf Volltextebene durchgeführt.
Abschließende Datensatzkonstruktion und Integration zitierter Referenzen
Der endgültige Datensatz mit 4.063 Einträgen wurde am 24. Juli 2026 abgeschlossen und für alle anschließenden deskriptiven, zitatanalytischen, netzwerkbasierten und Visualisierungsanalysen verwendet. Alle enthaltenen Einträge wurden dahingehend überprüft, dass sie eindeutige Web-of-Science-Zugangsnummern (UTs) enthalten.
Um Zitatanalysen zu ermöglichen, wurden die Zitatquellenfelder (CR) aus dem vollständigen Export der Vollständigen Aufzeichnung und Zitatquellen mit 5.957 Datensätzen abgerufen und durch exakte Übereinstimmung der UT-Kennungen in den endgültigen Datensatz integriert. Dieser Integrationsprozess erfolgte, ohne die Zugehörigkeit zum Datensatz oder die mit dem ursprünglichen Export verknüpfte Momentaufnahme von Zitierungen und Nutzungsanzahlen zu verändern.
Nach der Integration wurde bestätigt, dass 4.048 aufgenommene Datensätze mindestens ein exportiertes Zitierungsreferenzfeld (CR) enthalten, während 15 Datensätze keine Zitierungsreferenzliste im Export der Web of Science Core Collection enthielten. Das Skript zur Integration der Zitierungsreferenzen und der entsprechende Prüfbericht sind in Zusatzdatei 3 enthalten.
Datenbereinigung und deskriptive Analyse
Autorennamen, institutionelle Namen, Zeitschriftentitel, zitierte Referenzen, Länder/Regionen und Schlüsselwörter wurden mithilfe einheitsspezifischer Thesauri standardisiert. Für jede analytische Einheit kamen separate Thesauri zum Einsatz, und die Thesauri für Autoren, Organisationen, Länder, Schlüsselwörter, Zeitschriften und zitierte Referenzen wurden während des Standardisierungsprozesses nicht kombiniert.
Die jährliche Publikationszahl wurde entsprechend dem in der Web of Science Core Collection erfassten Publikationsjahr (PY) gruppiert. Jahre ohne Publikationen zwischen 1991 und 2026 blieben in der Analyse enthalten und als Nullwerte dargestellt, um eine kontinuierliche Zeitreihe sicherzustellen. Die Dokumenttypen wurden in fünf sich gegenseitig ausschließende Kategorien eingeteilt, wobei Early Access als Indexierungsstatus und nicht als eigenständiger Publikationstyp betrachtet wurde, um Doppelzählungen zu vermeiden.
Die Gesamtanzahl der Zitierungen (TC), Nutzungsanzahlen der letzten 180 Tage (U1) und Nutzungsanzahlen seit 2013 (U2) wurden nach Publikationsjahr aggregiert. Da TC, U1 und U2 dynamische Indikatoren in der Web of Science Core Collection sind, repräsentieren diese Metriken den am 24. Juli 2026 exportierten Datenbankschnappschuss.
Die Datenverarbeitung, das Management der Screening-Logs, deskriptive statistische Analysen sowie die Erstellung von Abbildung 2A,B und Abbildung 3A–C wurden mit Python 3.12.10 unter Verwendung der Bibliotheken pandas 3.0.3, openpyxl 3.1.5 und matplotlib 3.11.0 sowie mit Microsoft Excel durchgeführt.
Netzwerkanalysen mit VOSviewer
Bibliometrische Netzwerkanalysen wurden mit VOSviewer Version 1.6.21 durchgeführt. Der endgültige Klartext-Datensatz der Web of Science Core Collection wurde als bibliographische Datenbankdatei importiert. Für alle Analysen wurde die vollständige Zählung angewandt, und die Normalisierung nach Assoziationsstärke wurde verwendet, um die bibliometrischen Netzwerke zu erstellen und zu visualisieren.
Einheitenbezogene Thesauri wurden entsprechend der jeweils untersuchten Analyseeinheit angewendet. Die Schlüsselwort-Ko-Okkurrenz-Analyse wurde unter Verwendung von Alle Schlüsselwörter mit einer Mindestanzahl von 30 Vorkommen durchgeführt und ergab ein Netzwerk mit 158 Knoten und 6.468 Kanten (Abbildung 4A). Die Analyse der Autorenkollaboration wurde mithilfe der Einheit Autoren mit einer Mindestschwelle von sechs Dokumenten pro Autor durchgeführt und ergab ein Netzwerk mit 51 Knoten und 134 Kanten (Abbildung 5A). Die Analyse der institutionellen Zusammenarbeit wurde mit der Einheit Organisationen und einer Mindestschwelle von 10 Dokumenten pro Organisation durchgeführt und lieferte 109 Knoten und 351 Kanten (Abbildung 5B). Bei der Länderkollaborationsanalyse wurde die Einheit Länder mit einer Mindestschwelle von sieben Dokumenten pro Land verwendet und ein ergänzendes Netzwerk mit 50 Knoten und 438 Kanten generiert. Die bibliographische Kopplungsanalyse der Quellenzeitschriften wurde mit der Einheit Quellen und einer Mindestschwelle von 20 Dokumenten pro Quelle durchgeführt und resultierte in 39 Knoten und 741 Kanten (Abbildung 6A). Die Ko-Zitierungsanalyse der zitierten Referenzen wurde mit der Einheit Zitierte Referenzen und einer Mindestschwelle von 68 Zitaten pro Referenz durchgeführt und ergab ein Netzwerk mit 91 Knoten und 3.626 Kanten (Abbildung 6C).
Die VOSviewer-Kartendateien und die entsprechenden Netzwerkdateien, die für jede Analyse erstellt wurden, wurden aufbewahrt, um die Reproduzierbarkeit sicherzustellen. Alle vollständigen Kartierungsparameter, Schwellenwerte, Thesauri, Kartierungsaudits sowie die gespeicherten VOSviewer-Karten- und Netzwerkdateien sind in Supplemental File 3 enthalten.
CiteSpace-Schlüsselwort-Burst- und Zeitschriften-Dual-Map-Analysen
Die Erkennung von Stichwort-Bursts und die Analyse von Zeitschriften-Dual-Maps wurden mit CiteSpace-Version 7.0.R0 (64-Bit, Advanced) unter Verwendung des endgültigen, eingefrorenen Datensatzes der Web of Science Core Collection durchgeführt. Die Stichwort-Burst-Analyse wurde über einen Zeitraum von 1991–2026 mit Jahresschnitten durchgeführt. Begriffe wurden aus Titel, Zusammenfassung, Autorenstichworten und den Keywords Plus extrahiert. Stichwort wurde als Knotentyp ausgewählt, das Auswahlkriterium wurde auf Top N = 50 pro Zeitscheibe festgelegt, und es wurde keine Bereinigung vorgenommen.
Die Analyse von Zitierungsanstiegen wurde mithilfe der Burstness-Funktion durchgeführt, und die 25 Schlüsselwörter mit den stärksten Zitierungsanstiegen wurden für die Darstellung in Abbildung 4B beibehalten. Da die Literatursuche nur Veröffentlichungen bis zum 30. Juni 2026 umfasste, wurden Zitierungsanstiege, die im Jahr 2026 endeten, so interpretiert, dass sie bis zum Ende des unvollständigen Suchzeitraums reichten, anstatt eine Aktivität über ein vollständiges Kalenderjahr darzustellen.
Eine duale Journal-Kartenübersicht wurde aus dem gleichen eingefrorenen Web of Science-Datensatz erstellt, um Zitierpfade zwischen zitierenden und zitierten Fachgebieten darzustellen (Abbildung 7). Die vollständigen CiteSpace-Parametereinstellungen und die gespeicherten Ergebnisse der Top-25-Schlüsselwort-Bursts sind in Zusatzdatei 3 enthalten.
Institutionelle, zeitschriftenspezifische und länderübergreifende Visualisierungen
Institutionelle, zeitschriftenspezifische und länderbezogene bibliometrische Visualisierungen wurden mithilfe von bibliometrix und ergänzender Visualisierungssoftware erstellt. Institutionelle Namen wurden anhand der oben beschriebenen standardisierten Affiliationsdaten harmonisiert. Anschließend wurde das Kooperationsnetzwerk basierend auf Ko-Autorschaftsbeziehungen zwischen Institutionen aufgebaut, die die vorab festgelegte Publikationsschwelle erreichten. Knoten repräsentieren Institutionen, Verbindungen bezeichnen kooperative Beziehungen, und dickere Verbindungen weisen auf eine intensivere Zusammenarbeit hin.
Um die Zitierbeziehungen zwischen den produktivsten Zeitschriften zu untersuchen, wurden die 15 Zeitschriften mit der höchsten Publikationszahl identifiziert. Gerichtete Zitierverbindungen wurden von zitierenden zu zitierten Zeitschriften aufgebaut, nachdem Selbstzitierungen ausgeschlossen wurden. Das resultierende Netzwerk umfasste 15 Knoten und 200 gerichtete, nicht-selbstzitierende Kanten. Zur Visualisierung wurden nur die 56 Zitierverbindungen mit einem Gewicht von mindestens 45 in Abbildung 6B dargestellt. Dieses Netzwerk zeigt direkte Zitierbeziehungen zwischen den 15 produktivsten Zeitschriften und stellt keine Bradford-Kernanalyse oder eine bibliographische Verknüpfungskarte dar.
Länder- und Regionalanalysen wurden unter Verwendung einer vollständigen Zählung aller Autorenaffiliationen durchgeführt, wobei jedes Land pro Veröffentlichung nur einmal beigetragen hat. Veröffentlichungen wurden als Einzelandveröffentlichungen (SCP) oder Mehrlandveröffentlichungen (MCP) klassifiziert, basierend auf dem Land des korrespondierenden Autors und darauf, ob die Gesamtheit der Autorenaffiliationen ein oder mehrere Länder repräsentierte. Für Analysen auf Länderebene wurden Taiwan, Hongkong und Macao unter China zusammengefasst, während die ursprünglichen Institutsnamen und Adressangaben beibehalten wurden.
Die Länder-/Regionalanalysen und SCP-/MCP-Visualisierungen in Abbildung 8A,B wurden mit R-Version 4.6.1 unter Verwendung der Pakete bibliometrix (v5.4.1) und ggplot2 (v4.0.3) sowie SCImago Graphica-Version 1.0.55 erstellt.
Reproduzierbarkeit und Datenverifikation
Die Reproduzierbarkeit und technische Validierung wurden durch drei ergänzende Zusatzdateien unterstützt. Zusatzdatei 1 enthält den unveränderten Rohexport aus der Web of Science Core Collection (WoSCC), der als primäre Datenquelle verwendet wurde. Zusatzdatei 2 dokumentiert alle Entscheidungen bezüglich Dokumenttyp, Rückzüge, Duplikate/Versionen der Veröffentlichung sowie die thematische Relevanz und ermöglicht eine vollständige Nachvollziehbarkeit des Auswahlprozesses der Studien.
Zusatzdatei 3 enthält die Materialien, die zur Reproduktion der Datensäuberungsverfahren, der Integration zitierter Referenzen, der deskriptiven Analysen, der Netzwerkanalysen mit VOSviewer, der CiteSpace-Schlüsselwort-Burst-Analysen, des institutionellen Kooperationsnetzwerks, des direkten Zitationsnetzwerks zwischen Zeitschriften sowie der technischen Validierungsverfahren erforderlich sind. Die reproduzierten Ergebnisse wurden mit den archivierten Knotenzahlen, Kantenanzahlen, Gesamtzahlen der Screening-Ergebnisse, der Abdeckung zitierter Referenzen und den Audit-Dateien zu den Abbildungsquellen verglichen, um die analytische Konsistenz zu überprüfen.
Es wurde bestätigt, dass alle Analysen denselben gefrorenen Datensatz mit 4.063 Datensätzen sowie denselben Zitations- und Nutzungsanzahl-Abgleich vom 24. Juli 2026 verwendeten. Konsolidierte Softwareversionen und wichtige analytische Parameter sind in der Tabelle der Materialien angegeben.
Ergebnisse
Basic publication output and annual trend analysis
A total of 4,063 NPWT-related publications were included: 3,563 Articles (87.7%) and 500 Reviews (12.3%). These totals classify Early Access as an indexing status rather than a separate document type. Annual publication output is shown in Figure 2A, and the plotting categories used to display document types and Early Access status are shown in Figure 2B.
Publication output was minimal from 1991 to 2003 and began to rise in 2004. Growth accelerated after 2019, and output remained high during 2021–2025. This trajectory indicates sustained international interest in NPWT.
Figure 2B uses five mutually exclusive display categories to show Early Access status: Article (n = 3,340; 82.2%), Article Proceedings Paper (n = 203; 5.0%), Article Early Access (n = 20; 0.5%), Review (n = 492; 12.1%), and Review Early Access (n = 8; 0.2%). Thus, 3,340 + 203 + 20 = 3,563 Articles and 492 + 8 = 500 Reviews; the five plotting categories sum to the same 4,063 records included in the PRISMA flow diagram.
Citation and usage trend analysis
Citation and usage patterns were evaluated by publication year. U1 was defined as the 180-day recent usage count, and U2 was defined as cumulative usage since 2013. Aggregate U1 and U2 values are influenced by the number and age of publications in each annual cohort. Results are shown in Figure 3.
As shown in Figure 3A, the annual total citation count reached its highest level of 5,265 in 2017, followed by 5,117 in 2013, 4,818 in 2008, 4,810 in 2011, and 4,714 in 2014. In contrast, the cumulative citation counts for articles published from 2024 to 2026 appeared comparatively lower; however, this observation should be interpreted with caution, as it may reflect a restricted citation window rather than an intrinsic decline in scholarly influence. Regarding citation performance per publication, the highest average was recorded for papers published in 1997 (1,681 citations per paper); however, this value was based on only two highly cited foundational publications and was therefore strongly influenced by the small cohort size. Mean and median citation counts should be considered when comparing citation performance across publication-year cohorts.
Figure 3B presents the recent usage count (U1) of publications by publication year over the past 180 days. The U1 metric reflects recent platform activity associated with published articles. It should be noted that the total U1 counts are inherently affected by the number of publications per year. Across all included records, the total U1 count was 1,507. Publications from 2025 recorded the highest U1 count (372), followed by those from 2023 and 2024 (167 each), 2021 (140), and the partial 2026 cohort (121). These findings indicate relatively high recent platform activity for newer NPWT publication cohorts. However, U1 should not be interpreted as a direct measure of full-text downloads, readership, or scholarly impact.
Cumulative usage since 2013 (U2) reflects longer-term platform activity. As shown in Figure 3C, publications from 2017 recorded the highest cumulative usage count (3,284), followed by those from 2021 (2,502), 2014 (2,166), 2020 (2,080), and 2015 (1,953). The total U2 count across all included records was 31,766. Notably, publications from 2021 demonstrated considerable cumulative usage despite their relatively shorter availability period. All U1 and U2 usage data were exported from the Web of Science Core Collection on 24 July 2026, and the temporal availability of these metrics should be taken into account when interpreting recent publication cohorts. For publications issued before 2013, U2 includes only usage recorded since 2013 and therefore does not represent lifetime usage.
Keyword co-occurrence and burst analysis
Following the identification of overall publication output and trend dynamics, this study further recognized research hotspots and frontier evolution in the field through keyword co-occurrence and burst analyses, with the results presented in Figure 4.
A minimum occurrence threshold of 30 was applied to improve network readability. A total of 158 connected keywords were retained to construct the co-occurrence network, which contained 6,468 links and was divided into 6 clusters (Figure 4A). Cluster 1 (red cluster) primarily focused on the core technologies, mechanisms, and reconstructive applications of NPWT. The most prominent keywords included “negative pressure wound therapy,” “reconstruction,” “trial,” “dressings,” and “device,” representing research focusing on equipment, mechanisms and reconstructive applications. Other highly associated terms included “skin,” “VAC,” “wounds,” “wound control,” “system,” “flap,” “defects,” “fractures,” and “repair,” reflecting research related to NPWT techniques, underlying mechanisms, and wound management.
Cluster 2 (green cluster) was mainly associated with wound healing and diabetic foot ulcers. The central keyword was “wound healing,” accompanied by terms such as “diabetic foot ulcers,” “multicenter,” “ulcers,” “wound,” “care,” “debridement,” and “instillation.” This cluster primarily represented clinical investigations evaluating the therapeutic efficacy of NPWT in chronic wounds, particularly diabetic foot ulcers.
Cluster 3 (blue cluster) focused on surgical complications, outcomes, and infection prevention. The core keyword was “complications,” “surgery,” “surgical site infection,” “prevention,” and “outcomes.” This cluster reflected the application of NPWT in perioperative complication management, surgical site infection prevention, and outcome evaluation.
The remaining clusters further complemented the knowledge structure of the NPWT field. Cluster 4 (yellow) was related to open-abdomen and trauma management, with “management,” “open abdomen,” “trauma,” “closure,” and “abdominal compartment syndrome.” as representative keywords. Cluster 5 (purple) focused on infection and cardiothoracic surgical applications, centered on “infection,” “mediastinitis,” “cardiac surgery,” “risk factors,” and “poststernotomy mediastinitis.” Cluster 6 (light blue) represented complex infections and their clinical outcomes, centered on “mortality,” “necrotizing fasciitis,” “Fournier’s gangrene,” “diagnosis,” and “case report.” Collectively, these six clusters provide a comprehensive overview of the major research directions and knowledge structure within the NPWT field.
Keyword burst analysis revealed the temporal characteristics of the top 25 keywords with the strongest citation bursts from 1991 to 2026 (Figure 4B). The three keywords with the highest burst strengths were “wound control” (strength = 41.68, 1999–2011), “subatmospheric pressure” (strength = 32.63, 2001–2014), and “wound care” (strength = 28.20, 2021–2026). During the early period (1999–2014), research primarily focused on the fundamental principles of negative pressure technology, represented by “wound control,” “subatmospheric pressure,” “topical negative pressure,” “wound closure,” “fascial closure,” and “VAC therapy.”
During the intermediate period (2007–2018), research directions gradually shifted toward specific clinical applications, including soft tissue injury, poststernotomy mediastinitis, abdominal compartment syndrome, and randomized controlled trials. In recent years, research hotspots have further evolved toward “surgical site infection” (2019–2026), “risk” (2019–2026), “diabetic foot ulcer” (2020–2026), and “wound care” (2021–2026), highlighting the growing emphasis on wound management, infection prevention and control, and diabetic foot ulcer treatment. Furthermore, the emergence of “case report” (2021–2026) and “efficacy” (2024–2026) as burst keywords indicates that clinical outcome evaluation and the accumulation of clinical evidence from case-based studies have become emerging frontiers in this field.
Interdisciplinary characteristics
To further illustrate the distribution patterns of source and cited journals, a dual-map overlay analysis was performed, as shown in Figure 7. The citing journals are displayed on the left side of the map, whereas the cited journals are presented on the right side. The labels represent the major disciplinary areas covered by the journals, and the colored curves indicate the major citation pathways from citing journals to cited journals.
Several prominent citation pathways were identified in the current map. The most significant pathway originated from “Medicine, Medical, Clinical” on the left and extended toward “Health, Nursing, Medicine” on the right, indicating that NPWT studies published in clinical medical journals primarily drew upon knowledge from health, nursing, and medicine journals. In addition, citation links were observed from “Medicine, Medical, Clinical” toward “Molecular Biology, Genetics” and “Dermatology, Dentistry, Surgery,” reflecting the interdisciplinary connections between NPWT research and molecular biology, surgical science, and related clinical specialties. Overall, these citation patterns demonstrate the interdisciplinary nature of NPWT research, with citation links spanning clinical medicine, nursing and health sciences, molecular biology, dermatology, dentistry, and surgery.
Author and institutional collaboration networks
As shown in Figure 5A, analysis of the author collaboration network based on 4,063 included publications revealed a multi-centric collaborative landscape comprising five major clusters, with 51 connected authors and 134 collaborative links. The green cluster, centered around Ingemansson R with Malmsjö M and Lindstedt S as co-core authors, represented the largest collaborative team in the field, predominantly from Lund University, Sweden. The red cluster was centered on Gabriel A, Kim PJ, and Attinger CE and also included Gupta S and Stannard JP, bringing together major clinical investigators from North America and Europe. The blue cluster, centered on Orgill DP and Horch RE, was primarily associated with plastic and reconstructive surgery. The yellow cluster, led by Lavery LA, Armstrong DG, and Kirsner RS, concentrated on diabetic foot and wound management. The purple cluster was centered on Sjögren J and included Hetzer R, Petzina R, and Gustafsson L, reflecting collaboration in cardiothoracic surgery and mediastinitis management.
According to Price’s Law, the core author threshold was calculated as M = 0.749 × √Nmax, where Nmax = 60 and M was approximately 5.80. Authors with at least 6 publications were classified as core authors. A total of 212 authors met this threshold, representing 1.3% of the 16,615 authors in the dataset. Figure 5A shows collaboration among these core authors; isolated nodes and some labels may not be displayed. The most prolific authors were Ingemansson R (60 publications), Malmsjö M (54), Orgill DP (39), Horch RE (34), Lindstedt S (29), Armstrong DG and Gabriel A (21 each), and Attinger CE, Liu Y, and Yu AX (20 each). These publication counts are summarized in Table 1.
Regarding institutional collaboration, as shown in Figure 5B, the network revealed a multi-centric landscape comprising nine major clusters, with prominent hubs in Europe and the United States and a distinct cluster of Chinese institutions. The red cluster included Harvard University, Harvard Medical School, Brigham and Women’s Hospital, Heidelberg University, Duke University, and the University of Utah. The green cluster was centered on Lund University, Lund University Hospital, and Skåne University Hospital and included Griffith University, Uppsala University, the University of Queensland, Ghent University, the University of Amsterdam, and the University of Helsinki. The blue cluster consisted primarily of Chinese institutions, including Shanghai Jiao Tong University, Zhejiang University, Soochow University, Shandong University, Sun Yat-sen University, and Sichuan University. The yellow cluster included the University of Oxford, the University of Manchester, Karolinska Institutet, University College London, and the University of Warwick. The purple cluster comprised the University Hospital Zurich, Mayo Clinic, Hannover Medical School, and the medical universities of Vienna and Graz. The light-blue cluster included Wake Forest University, the University of Miami, Georgetown University, the University of Arizona, MedStar Georgetown University Hospital, and the University of Toronto. The remaining orange, brown, and pink clusters represented additional collaborative groups centered on institutions such as Chang Gung University, the University of São Paulo, the University of Pisa, the University of Maryland, Johns Hopkins University, and the Cleveland Clinic.
In the institutional network visualization, node size was proportional to institutional publication output, edges denoted collaborative relationships with line thickness reflecting collaboration intensity, and node color represented cluster affiliation. Lund University exhibited a notably large node size within the network, while MedStar Georgetown University Hospital occupied a relatively central position within its respective cluster. It should be noted that due to potential differences in institutional name standardization between the network visualization and the publication count statistics, node sizes should not be directly equated with rankings in Table 2. Cross-regional edges among different clusters indicated the presence of inter-regional collaborations in NPWT research. Overall, the author and institutional collaboration networks consistently demonstrated prominent European and U.S. research hubs with substantial participation from Asian institutions, while highlighting the pivotal roles of Swedish and American scholars in driving the field’s collaborative framework.
Core journals and highly cited papers
After identifying the core research contributors, this study further analyzed the publication platforms and milestone achievements in the NPWT field, as shown in Figure 6A. Node size corresponded to the number of publications in the NPWT field, with larger nodes indicating higher publication output; colors represented different journal clusters; and edges denoted bibliographic coupling relationships among journals based on shared references. The network comprised five major clusters. The green cluster represented the core wound care and plastic surgery cluster, with the International Wound Journal as the largest node, and also included the Journal of Wound Care, Wounds-A Compendium of Clinical Research and Practice, Plastic and Reconstructive Surgery, and Ostomy Wound Management, among other wound care and plastic surgery specialty journals. The blue cluster focused on orthopedics, trauma, and general clinical medicine, with Medicine as its largest node. The red cluster centered on general surgery and surgical infection, anchored by the Journal of Clinical Medicine. The purple cluster specializes in plastic, thoracic, and cardiothoracic surgery, with the Annals of Plastic Surgery as its core. The yellow cluster covered wound care, burns, plastic surgery, and pediatric surgery, with Advances in Skin & Wound Care as its largest node. Overall, wound care journals exhibited the greatest concentration of large nodes and closely interconnected relationships within the network.
As shown in Table 3, among the top 15 most productive journals, the International Wound Journal ranked first with 265 publications, followed by Wounds-A Compendium of Clinical Research and Practice with 192, and the Journal of Wound Care with 153. These three journals together contributed 610 publications, accounting for 15.0% of all included literature. The top five also included Plastic and Reconstructive Surgery (88) and the Annals of Plastic Surgery (82). In terms of disciplinary distribution, the top 15 journals were predominantly wound care and plastic surgery journals, with wound care journals collectively contributing 872 publications (21.5%), representing the primary publication channels for NPWT research. Regarding journal publication-country distribution, among the top 15 journals, 2 were published in the United Kingdom, while the United States accounted for 10 journals, reflecting that U.S.-based journals constituted the largest share of these publication venues. Figure 6B illustrates the direct citation relationships among these core journals.
In addition to journal-level metrics, the most influential individual publications were further examined. As shown in Table 4, the most highly cited paper was the clinical study by Argenta LC et al. (1997) published in the Annals of Plastic Surgery (TC = 1,708), which introduced vacuum-assisted closure as a new method for wound control and treatment. The second most cited work was the foundational animal study by Morykwas MJ et al. (1997), also published in the Annals of Plastic Surgery (TC = 1,654), which investigated the basic mechanisms underlying vacuum-assisted closure. The third to fifth most cited papers were published in Advances in Therapy (2017, TC = 1,641), Intensive Care Medicine (2013, TC = 1,033), and The Lancet (2005, TC = 700), covering chronic wound management, clinical practice guidelines for intra-abdominal hypertension and abdominal compartment syndrome, and NPWT after partial diabetic foot amputation, respectively. The publication years of highly cited papers ranged from 1997 to 2021, with the most recent paper addressing moist wound healing using commonly available dressings. Collectively, these findings suggested that NPWT research was anchored in a core group of wound care journals, while the most influential works span both foundational experimental and clinical studies, reviews, randomized controlled trials, and clinical guidelines that have shaped the field’s knowledge base.
As shown in Figure 6C, the co-citation network of cited references was categorized into five clusters. The red cluster, positioned mainly on the left and in the center of the network, was anchored by the 1997 study by Morykwas MJ et al., which represented one of the foundational works in the field with a notably large node size; the cluster predominantly included foundational experimental and early clinical studies, with a focus on the mechanistic basis and clinical applications of NPWT. The green cluster, situated from the center to the upper-right, encompassed research on the mechanisms and wound-repair effects of NPWT, with the 2004 study by Wackenfors A et al. as a core node, along with a series of publications by Kim PJ. The yellow cluster, located in the lower-left region, was centered on cardiothoracic applications of NPWT, with a focus on the management of sternal wound infections. The purple cluster was distributed throughout the lower part of the network and included studies on temporary abdominal closure and open-abdomen management. The blue cluster, distributed mainly on the right and lower-right, was built around the body of work by Stannard JP et al., focusing on traumatic surgical scenarios, including open fractures and surgical site infections. Overall, the network exhibited a temporal evolution from fundamental mechanistic principles toward specialized clinical applications in wound repair, trauma, cardiothoracic surgery, and open-abdomen management.
Country/region output and collaboration landscape
Country and regional outputs are shown in Figure 8. Figure 8A uses countries identified from all contributing authors' affiliations, allowing a single publication to be attributed to multiple countries. The United States ranked first, followed by China, Germany, the United Kingdom, Italy and Japan. Figure 8B uses the corresponding author’s country and classifies records as Single-Country Publications (SCP) or Multi-Country Publications (MCP). The United States led both SCP and MCP output. China ranked second in total output but had a substantially lower MCP share, indicating a comparatively low proportion of internationally coauthored publications. European and selected Asian countries produced fewer publications but were also represented among the leading countries with corresponding authors.
Because Figure 8A uses all-author affiliations and Figure 8B uses the corresponding author’s country, country totals differ between panels. SCP denotes publications whose authors were affiliated with one country; MCP denotes publications involving authors from more than one country.
Data availability
The raw Web of Science Core Collection export (Supplemental File 1), record-level screening log (Supplemental File 2), and reproducible workflow, code, and analysis-output package (Supplemental File 3) are provided with the paper. Supplemental File 3 contains the software environment, analysis parameters, scripts, unit-specific thesauri, derived data tables, saved VOSviewer and CiteSpace outputs, and figure-source and audit files. Public redistribution and reuse of proprietary Web of Science records remain subject to Clarivate’s applicable licensing terms.
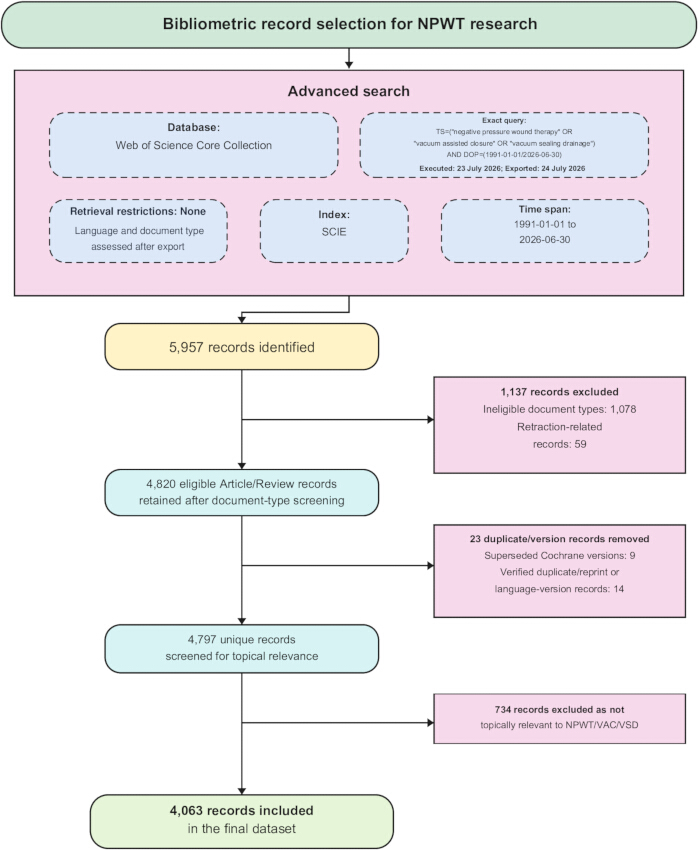
Figure 1. PRISMA-style flow diagram for the NPWT bibliometric analysis. PRISMA was used solely to display the record-selection process; this study was not conducted as a systematic review. The diagram summarizes record identification, document-type screening, topic-relevance screening, and final inclusion. The WoSCC search was conducted on 23 July 2026, and the records were exported on 24 July 2026; Early Access records were assigned to their underlying document type. Abbreviations: NPWT = negative pressure wound therapy; PRISMA = Preferred Reporting Items for Systematic Reviews and Meta-Analyses; WoSCC = Web of Science Core Collection; VAC = vacuum-assisted closure; VSD = vacuum sealing drainage. Please click here to view a larger version of this figure.
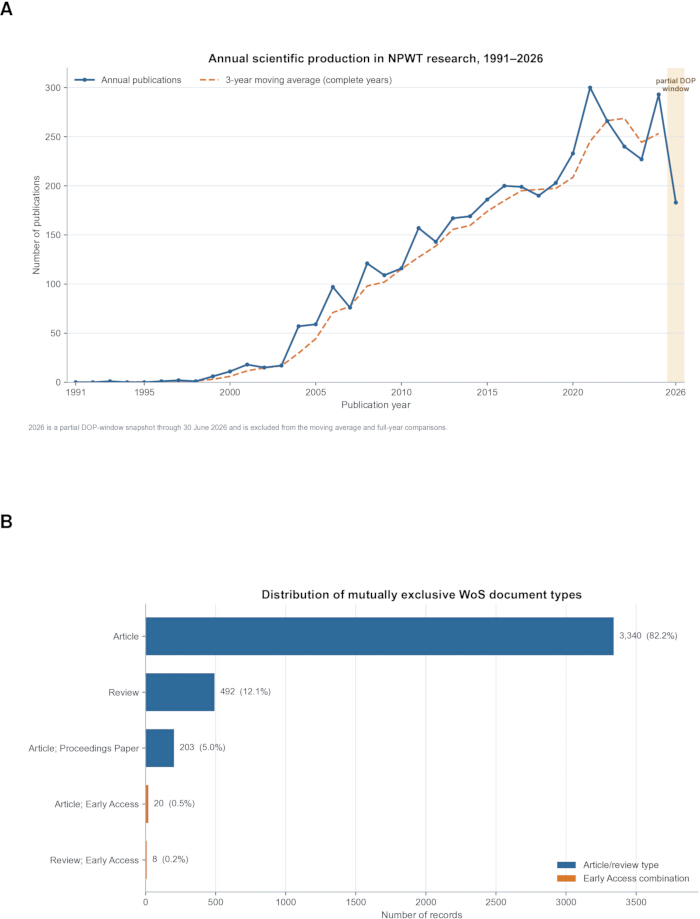
Figure 2. Annual publication output and document-type distribution of NPWT publications from 1991 to 2026. (A) Annual publication volume. (B) Article and Review categories, with Early Access status shown separately. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.
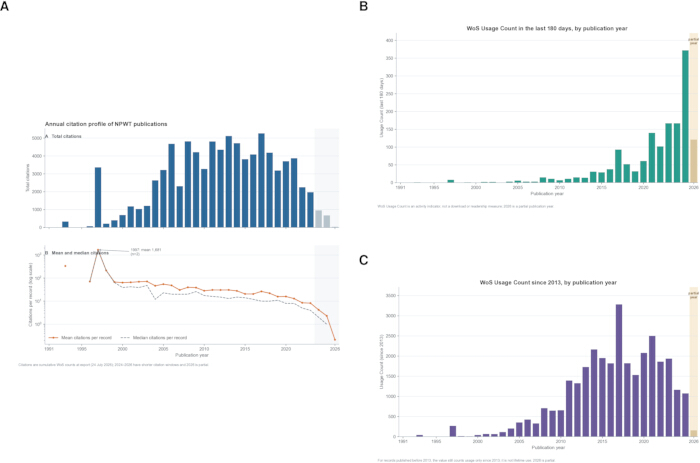
Figure 3. Citation and usage trends of NPWT publications. (A) Total, mean, and median citations by publication year. (B) Recent usage over 180 days. (C) Cumulative usage since 2013. Data were exported from WoSCC on 24 July 2026; recent cohorts have shorter citation and usage windows. Abbreviations: NPWT = negative pressure wound therapy; U1 = 180-day recent usage count; U2 = cumulative usage count since 2013; WoSCC = Web of Science Core Collection. Please click here to view a larger version of this figure.
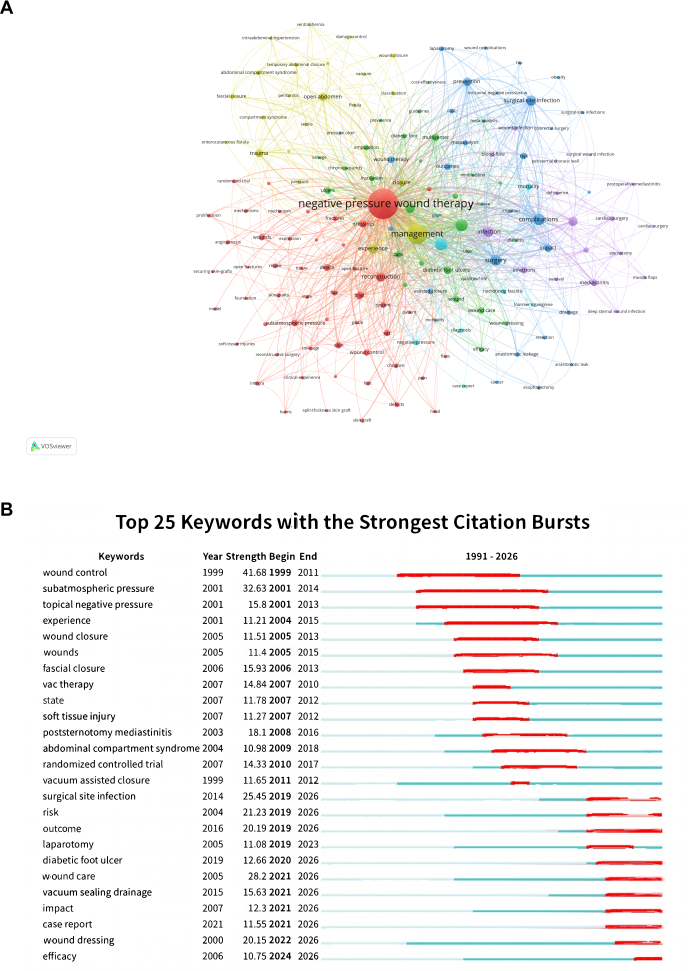
Figure 4. Keyword co-occurrence network and the top 25 burst keywords. (A) Keyword co-occurrence network using a frequency threshold of ≥30. (B) Temporal map of the 25 keywords with the strongest citation bursts. Please click here to view a larger version of this figure.
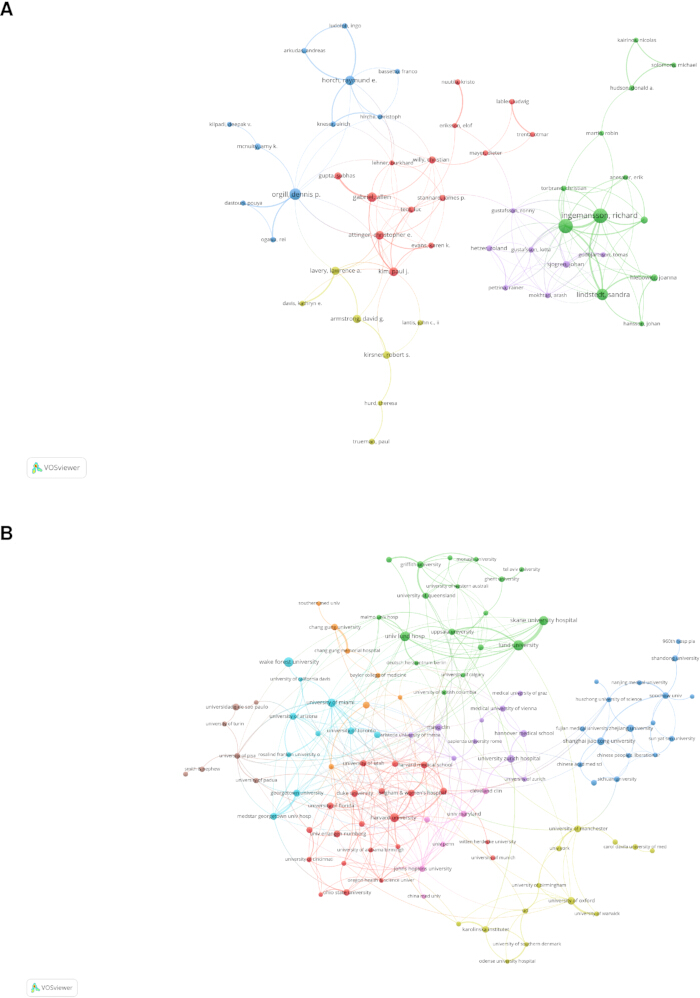
Figure 5. Author and institutional collaboration networks. (A) Core-author collaboration network, with node size proportional to publication count. (B) Institutional collaboration network. Please click here to view a larger version of this figure.
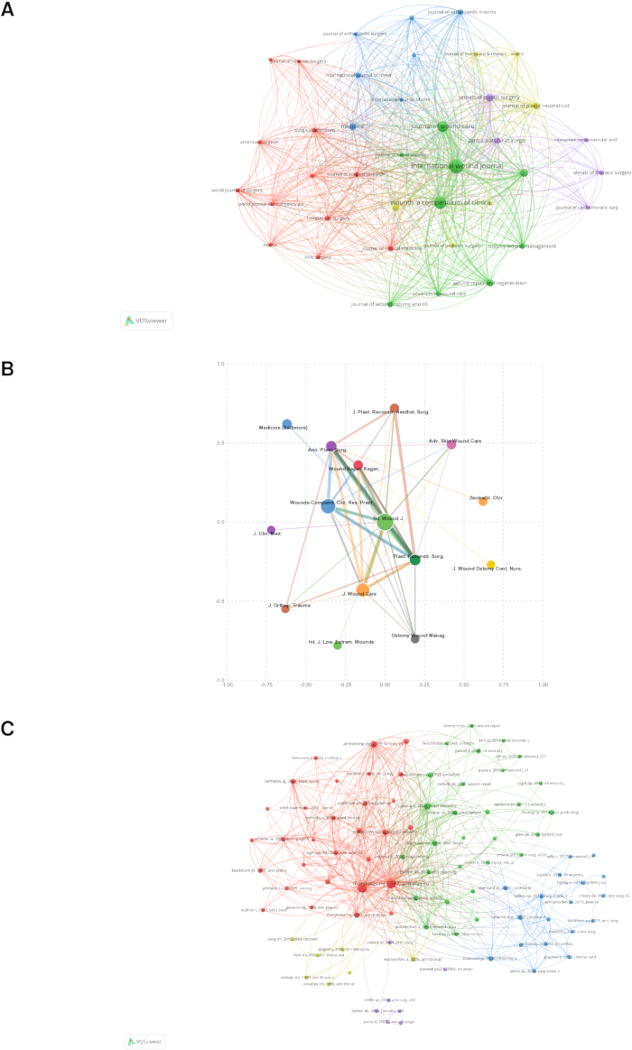
Figure 6. Publication journals and core-literature citation characteristics in NPWT research. (A) Journals with ≥20 NPWT publications. (B) Citation network of the 15 most productive journals. (C) Co-citation network of cited references. Network maps were generated using full counting. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.

Figure 7. Dual-map overlay analysis of journals in NPWT research. The left side represents citing journals, and the right side represents cited journals. Curves indicate major citation pathways; curve width reflects citation-flow strength. Abbreviation: NPWT = negative pressure wound therapy. Please click here to view a larger version of this figure.
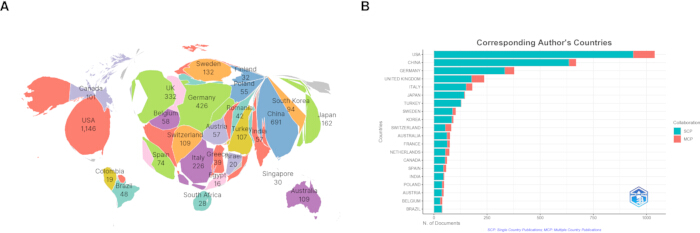
Figure 8. Global country/region output and international collaboration. (A) Publication distribution based on all author affiliations. (B) SCP and MCP distributions based on the corresponding author's country. Abbreviations: MCP = multi-country publications; SCP = single-country publications. Please click here to view a larger version of this figure.
| Rank | Author | Publications | Citations | Country |
| 1 | Ingemansson, Richard | 60 | 2747 | Sweden |
| 2 | Malmsjö, Malin | 54 | 2215 | Sweden |
| 3 | Orgill, Dennis P. | 39 | 3149 | United States |
| 4 | Horch, Raymund E. | 34 | 724 | Germany |
| 5 | Lindstedt, Sandra | 29 | 319 | Sweden |
| 6 | Gabriel, Allen | 21 | 962 | United States |
| 7 | Armstrong, David G. | 21 | 1494 | United States |
| 8 | Liu, Y | 20 | 285 | China |
| 9 | Yu, AX | 20 | 452 | China |
| 10 | Attinger, Christopher E. | 20 | 1662 | United States |
Table 1: Top 10 authors by publication output in NPWT research. The table presents publication and citation counts for the 10 most prolific authors. Abbreviations: NPWT = negative pressure wound therapy.
| Rank | Institution | Publications | Citations | Country |
| 1 | Lund University | 99 | 4291 | Sweden |
| 2 | Skane University Hospital | 94 | 4139 | Sweden |
| 3 | Harvard University | 83 | 5271 | United States |
| 4 | Harvard University Medical Affiliates | 77 | 5085 | United States |
| 5 | University of Texas System | 72 | 2540 | United States |
| 6 | University System of Ohio | 62 | 1339 | United States |
| 7 | Wake Forest University | 53 | 2975 | United States |
| 8 | Harvard Medical School | 52 | 3608 | United States |
| 9 | Brigham & Women's Hospital | 49 | 4127 | United States |
| 10 | University of California System | 46 | 1459 | United States |
Table 2: Top 10 institutions by publication output in NPWT research. The table presents publication and citation counts for the 10 most productive institutions. Abbreviation: NPWT = negative pressure wound therapy.
| Rank | Journal | Publications | Share |
| 1 | International Wound Journal | 265 | 6.52% |
| 2 | Wounds-A Compendium Of Clinical Research And Practice | 192 | 4.73% |
| 3 | Journal Of Wound Care | 153 | 3.77% |
| 4 | Plastic And Reconstructive Surgery | 88 | 2.17% |
| 5 | Annals Of Plastic Surgery | 82 | 2.02% |
| 6 | Medicine | 66 | 1.62% |
| 7 | Wound Repair And Regeneration | 64 | 1.58% |
| 8 | Advances In Skin&Wound Care | 61 | 1.50% |
| 9 | Journal Of Plastic Reconstructive And Aesthetic Surgery | 58 | 1.43% |
| 10 | Zentralblatt Fur Chirurgie | 51 | 1.26% |
| 11 | Journal Of Wound Ostomy And Continence Nursing | 48 | 1.18% |
| 12 | Ostomy Wound Management | 46 | 1.13% |
| 13 | International Journal Of Lower Extremity Wounds | 43 | 1.06% |
| 14 | Journal Of Clinical Medicine | 42 | 1.03% |
| 15 | Journal Of Orthopaedic Trauma | 41 | 1.01% |
Table 3: The 15 main journals publishing NPWT research. The table presents publication counts and shares of the complete dataset. Abbreviation: NPWT = negative pressure wound therapy.
| Rank | Title | Year | Journal | First author | Total citations | ||
| 1 | Vacuum-assisted closure:A new method for wound control and treatment:Clinical experience | 1997 | Annals Of Plastic Surgery | Argenta, LC | 1708 | ||
| 2 | Vacuum-assisted closure:A new method for wound control and treatment:Animal studies and basic foundation | 1997 | Annals Of Plastic Surgery | Morykwas, MJ | 1654 | ||
| 3 | Chronic Wound Healing:A Review of Current Management and Treatments | 2017 | Advances In Therapy | Han, G | 1641 | ||
| 4 | Intra-abdominal hypertension and the abdominal compartment syndrome:updated consensus definitions and clinical practice guidelines from the World Society of the Abdominal Compartment Syndrome | 2013 | Intensive Care Medicine | Kirkpatrick, AW | 1033 | ||
| 5 | Negative pressure wound therapy after partial diabetic foot amputation:a multicentre,randomised controlled trial | 2005 | Lancet | Armstrong, DG | 700 | ||
| 6 | Update on management of diabetic foot ulcers | 2018 | Annals Of The New York Academy Of Sciences | Everett, E | 671 | ||
| 7 | Pathogenesis and Treatment of Impaired Wound Healing in Diabetes Mellitus:New Insights | 2014 | Advances In Therapy | Baltzis, D | 587 | ||
| 8 | Vacuum-assisted closure:Micro deformations of wounds and cell proliferation | 2004 | Plastic And Reconstructive Surgery | Saxena, V | 545 | ||
| 9 | Moist Wound Healing with Commonly Available Dressings | 2021 | Advances In Wound Care | Nuutila, K | 516 | ||
| 10 | Comparison of negative pressure wound therapy using vacuum-assisted closure with advanced moist wound therapy in the treatment of diabetic foot ulcers:A multicenter randomized controlled trial | 2008 | Diabetes Care | Blume, PA | 451 | ||
Table 4: The 10 most-cited records included in the NPWT bibliometric dataset. Citation counts were exported from the Web of Science Core Collection on 24 July 2026. Abbreviation: NPWT = negative pressure wound therapy.
Supplemental File 1. Raw Web of Science Core Collection export. The records were retrieved using the reported search strategy on 23 July 2026 and exported as plain text on 24 July 2026.Please click here to download this file.
Supplemental File 2. Literature screening log for the NPWT bibliometric dataset. The spreadsheet provides record-level inclusion and exclusion decisions for the retrieved literature. Abbreviation: NPWT = negative pressure wound therapy.Please click here to download this file.
Supplemental File 3. Reproducible workflow, code, and analysis outputs for the NPWT bibliometric dataset. The ZIP archive contains the software environment, analysis parameters, data preparation and validation scripts, unit-specific thesauri, derived data tables, saved VOSviewer and CiteSpace outputs, and figure-source and audit files. Abbreviation: NPWT = negative pressure wound therapy.Please click here to download this file.
Diskussion
Die Analyse ergab eine anhaltende Ausweitung der Forschung zur Vakuumtherapie (NPWT) und einen deutlichen thematischen Wandel von grundlegenden Mechanismen hin zur klinischen Optimierung18Frühe Studien betonten den Unterdruck, die Gewebedurchblutung und biologischen Reaktionen. Beispielsweise fanden Morykwas et al. (1999), dass die Anwendung von Unterdruck bei partiell tiefen Brandwunden in Schweinemodellen eine Vertiefung der Wunde verhinderte, wobei sich ein Behandlungsfenster von 12 Stunden nach der Verletzung zeigte, wobei bereits 6 Stunden Anwendung ausreichten, um die Progression der Verletzung zu stoppen.19. Spätere Arbeiten befassten sich ebenfalls mit Wundversorgungswegen, Operationsstelle-Infektionen, diabetischen Fußgeschwüren und fortgeschrittenen Verbänden20und Applikation21,22. Die Übereinstimmung zwischen der Schlüsselwort-Clustering-Analyse und der Burst-Erkennung untermauert einen sequenziellen Fortschritt der Forschung – von der mechanistischen Erforschung und klinischen Translation hin zur Optimierung der Wundauflagen, der Infektionsprävention und der Bewertung klinischer Ergebnisse 15. Methodisch offenbart das Clustering die statische Wissensstruktur des Forschungsfeldes, während die Burst-Erkennung dynamische thematische Verschiebungen erfasst; die Übereinstimmung dieser beiden Dimensionen stärkt die Validität der beobachteten Entwicklung. Inhaltlich ist dieser Fortschritt in der Literatur verankert: Die frühe Forschung zur NPWT konzentrierte sich auf die Untersuchung der Wirkmechanismen, wie beispielsweise in der grundlegenden Arbeit von Morykwas und Argenta (1997) gezeigt. Spätere Studien befassten sich zunehmend mit den Eigenschaften der Wundauflagen – beispielsweise der Porengröße des Schaumstoffs (400–600 µm– beeinflussen Mikrodeformationen und zelluläre Reaktionen sowie vergleichende Bewertungen von Einweg- gegenüber herkömmlichen kanisterbasierten Systemen23. Das gegenwärtige mechanistische Verständnis hat sich von einem vereinfachenden Ansatz aus erweitert "erhöhte Perfusion" Modell hin zu präziseren Rahmenbedingungen der Mechanotransduktion und Einflusszonen-Effekten24Eine bibliometrische Visualisierung der NPWT durch Deng et al. (2024) bestätigte ebenfalls diese inhaltliche Verschiebung von grundlegenden Mechanismen hin zu klinischen Anwendungen und der Optimierung von Materialien, was den Befunden in der Verbrennungsmedizinforschung entspricht, wo die NPWT über einen Zeitraum von 22 Jahren zunehmend in die Rangliste der häufigsten Schlüsselwörter aufstieg.25,26Somit konvergieren sowohl die thematischen Strukturen auf Basis von Clustern als auch die burst-erfassten aufkommenden Forschungsfelder auf einen klaren evolutionären Pfad – von der Aufklärung von Mechanismen hin zur Optimierung von Anwendungen und der Weiterentwicklung materialbasierter Interventionen.15.
Aufgrund der bibliometrischen Ergebnisse zeigten sich deutliche geografische Unterschiede. China leistete einen erheblichen Beitrag zum Publikationsumfang und profitierte von großen klinischen Populationen sowie vielfältigen Wundversorgungssituationen, was mit jüngsten bibliometrischen Analysen übereinstimmt, die Chinas führende Produktivität in der Wundheilungsforschung belegen, wie von Xing et al. (2025) in einer bibliometrischen Analyse des Einsatzes von Gewebeengineering in der Wundheilung berichtet wurde 27. Allerdings wurde die Publikationsleistung Chinas vorwiegend durch einlandische klinische Studien (SCP) geprägt, während multinationale Kooperationen, grundlegende mechanistische Forschung, Biomaterialentwicklung und international koordinierte Studien vergleichsweise begrenzt blieben. Im Gegensatz dazu nahmen US-amerikanische und europäische Forschungsgruppen zentrale Positionen in langjährigen, überinstitutionellen Netzwerken ein und leisteten umfangreichere Beiträge zu mechanistischen Untersuchungen, der Entwicklung von Geräten sowie multizentrischen Studien. Hervorzuheben ist, dass bibliometrische Daten zum Gewebeengineering in der Wundheilung zeigen, dass das Verhältnis von SCP zu MCP in China (1.708/343) darauf hinweist, dass multinationale Kooperationen nur einen geringen Anteil der gesamten Publikationsleistung ausmachen, während die US-amerikanischen Publikationen einen höheren Anteil an internationalen Kooperationspublikationen aufweisen 27. Vor diesem Hintergrund hat China dennoch Fortschritte bei der Innovation von NPWT-Geräten und dem Zugang zum internationalen Markt erzielt. Foryou Medical Electronics erhielt 2013 die Zulassung gemäß U.S. FDA 510(k) für sein NPWT-Gerät (K113236)28Im Jahr 2024 berichtete der Hersteller, dass seine NPWT-Pumpen und Wundauflage-Kits die Zertifizierung gemäß der Verordnung der Europäischen Union über Medizinprodukte (MDR) durch SGS erhalten hatten.29Die Umsetzung dieser regulatorischen Meilensteine in multinationale klinische Untersuchungen stellt eine wichtige Richtung für die zukünftige Entwicklung dar.
Die institutionelle Analyse ergab, dass die wichtigsten Beiträge zur NPWT-Forschung auf Schweden und die Vereinigten Staaten konzentriert waren. Die Analyse der Autorenproduktivität identifizierte Ingemansson R (60 Publikationen) und Malmsjö M (54 Publikationen) als die beiden produktivsten Autoren, gefolgt von Orgill DP (39 Publikationen). Diese Ergebnisse unterstreichen die bedeutenden Beiträge schwedischer und US-amerikanischer Forschungsgruppen für den Bereich der NPWT.
Die Zeitschriftenanalyse zeigte, dass die NPWT-Forschung auf Fachzeitschriften für Wundversorgung, plastische Chirurgie und verwandte klinische Bereiche konzentriert war. Das International Wound Journal, Wounds-A Compendium of Clinical Research and Practice und das Journal of Wound Care waren die produktivsten Publikationsorgane. Die meisten der 15 meistpublizierenden Zeitschriften hatten ihren Sitz in den Vereinigten Staaten oder im Vereinigten Königreich, was die herausragende Rolle dieser Länder bei der Verbreitung von NPWT-Forschung widerspiegelt. Diese Ergebnisse können Forschern helfen, Zeitschriften zu identifizieren, die regelmäßig Arbeiten zu diesem Fachgebiet veröffentlichen, obwohl bei der Zeitschriftenauswahl auch Umfang, Studiendesign und Zielgruppe berücksichtigt werden sollten.
Die am häufigsten zitierten Publikationen befassten sich mit der Behandlung chronischer Wunden, fortschrittlichen Wundauflagen, dem abdominellen Kompartmentsyndrom, diabetischen Fußulzera und den klinischen Anwendungen der NPWT. Dieses Muster zeigt, dass die wissenschaftliche Grundlage des Fachgebiets über gerätespezifische Studien hinausgeht und die gesamte Biologie der Wundheilung, klinische Leitlinien sowie die multidisziplinäre Wundbehandlung umfasst. Obwohl grundlegende Protokolle für die NPWT etabliert sind, bestehen weiterhin Unsicherheiten hinsichtlich der Auswahl der Wundauflage, der optimalen Druckparameter und der standardisierten Anwendung an bestimmten anatomischen Stellen.
Die Stichwortergebnisse bestätigten dieselbe Entwicklungssequenz. Unterdruck, Perfusion und randomisierte Studien prägten frühere Phasen; Wundversorgung, Wundauflagen, Operationsstelle-Infektionen, diabetische Fußulzerationen und Wirksamkeit rückten später in den Vordergrund. Diese Verschiebung deutet darauf hin, dass sich das Forschungsfeld von der Nachweisführung des Wirkmechanismus hin zur standardisierten klinischen Anwendung, Materialinnovation und integrierten Wundmanagementstrategien entwickelt.
Die Integration der NPWT mit optimierten Verbänden und standardisierten Wundpflegeprotokollen hat sich zu einer wichtigen klinischen Richtung entwickelt. Schaum- und Gazeverbände weisen jeweils praktische Vorteile und Einschränkungen auf, doch vergleichende Belege hoher Sicherheit, die eine individualisierte Auswahl unterstützen, sind weiterhin begrenzt. Die zukünftige Entwicklung wird voraussichtlich verbesserte Biomaterialien, sensorbasierte Systeme und präzisere Behandlungsprotokolle umfassen, die auf die Wundeigenschaften und das Patientenrisiko zugeschnitten sind.
Die meisten Veröffentlichungen in dem Datensatz konzentrierten sich auf klinische Anwendungen, Behandlungseffektivität, Infektionskontrolle, Komplikationsmanagement und die Optimierung der Wundversorgung. Im Vergleich dazu war die mechanistische Forschung zu zellulären Reaktionen, molekularen Signalwegen und Material-Gewebe-Wechselwirkungen weniger ausgeprägt. Künftige Studien sollten strenge klinische Studien mit experimenteller Forschung kombinieren, um zu klären, wie die NPWT die Wundheilung und Infektionskontrolle beeinflusst. Zu den Prioritäten gehören die Identifizierung früher Biomarker der Therapieantwort, die Entwicklung intelligenter Wundauflagen und die Etablierung individualisierter Behandlungsstrategien durch interdisziplinäre Zusammenarbeit.
Mehrere Einschränkungen sollten berücksichtigt werden. Es wurden nur Publikationen einbezogen, die im Science Citation Index Expanded von WoSCC indiziert sind; es wurde keine Sprachbeschränkung angewandt. Daher könnten relevante Publikationen, die ausschließlich in anderen Datenbanken indiziert sind, übersehen worden sein. Obwohl zwei geschulte Prüfer unabhängig voneinander die Datensätze sichteten und extrahierten, sind verbleibende Klassifizierungsfehler möglich. Variationen in Autoren-, Instituts- und Zeitschriftentiteln könnten die Netzwerkkonstruktion beeinträchtigt haben, trotz Standardisierung. Zitations- und Nutzungsindikatoren sind zeitabhängig und benachteiligen neuere Publikationen. Schließlich beschreiben bibliometrische Indikatoren Publikationsmuster und Einfluss, messen jedoch nicht direkt die methodische Qualität oder klinische Wirksamkeit.
Die Forschung zur NPWT hat sich von grundlegenden Studien zu Druck, Perfusion und Wundheilungsmechanismen hin zur klinischen Wundversorgung, Infektionsprävention, fortschrittlichen Wundauflagen und Ergebnisevaluation entwickelt. Die internationale Zusammenarbeit in der indizierten Literatur konzentrierte sich auf Netzwerke in den USA und Europa. China leistete einen erheblichen Beitrag hinsichtlich der Publikationszahl, während ein vergleichsweise geringerer Anteil der Publikationen mit korrespondierendem Autor aus China internationale Koautorenschaften umfasste. Dieses Ergebnis beschreibt die Kooperationsstruktur der indizierten Literatur und sollte nicht als Bewertung der Forschungsqualität verstanden werden. Zu den zukünftigen Entwicklungsmöglichkeiten im gesamten Forschungsbereich zählen methodisch stringente klinische Studien, translationsorientierte Untersuchungen zu Wirkmechanismen, intelligente Biomaterialien, standardisierte standortspezifische Protokolle sowie eine umfassendere Zusammenarbeit über Regionen hinweg.
Offenlegungen
Die Autoren haben keine Interessenkonflikte anzugeben.
Danksagungen
Diese Studie wurde durch die Nationale Naturwissenschaftliche Stiftung Chinas (Nachwuchsprogramm, Nr. 82305237), den Longyi-Gelehrten (Sämlingsprogramm, Nr. YM2021025), die hochrangige Schwerpunktdisziplin – Stärkung des Aufbaus eines evidenzbasierten Forschungssystems für traditionelle chinesische Medizin (Anorektalmedizin der TCM) sowie das Shanghai-Forschungszentrum für Sinus- und Fistelerkrankungen (Nr. 2023ZZ02003) unterstützt.
Materialien
| Name | Unternehmen | Katalognummer | Kommentare |
|---|---|---|---|
| CiteSpace 7.0.R0 (64-Bit) Advanced | Chaomei Chen, Drexel University, USA | https://citespace.podia.com/ | Wird für die Schlüsselwort-Burst-Analyse und die Dual-Map-Überlagerung verwendet. Einstellungen: 1991–2026, Jahresscheiben, Knotentyp „Schlüsselwort“, Top N = 50 pro Scheibe, keine Bereinigung und die 25 stärksten Burst-Begriffe. |
| Python 3.12.10; pandas 3.0.3; openpyxl 3.1.5; matplotlib 3.11.0; NetworkX 3.6.1; Microsoft Excel 16.0.20131.20154 | Python Software Foundation; Entwicklerteams von pandas, openpyxl, Matplotlib und NetworkX; Microsoft Corporation | https://www.python.org/; https://pandas.pydata.org/; https://openpyxl.readthedocs.io/; https://matplotlib.org/; https://networkx.org/; https://www.microsoft.com/microsoft-365/excel | Wurde zur Screening, Entfernung von Duplikaten, Datenprüfung, deskriptiven Analysen und Erstellung von Abbildungen verwendet. Der endgültige Datensatz enthielt 4.063 Datensätze. NetworkX wurde für das Direktzitierungsnetzwerk der Top-15-Zeitschriften verwendet (15 Knoten; 56 dargestellte Kanten mit Gewichtungen) >=45). |
| R 4.6.1; bibliometrix 5.4.1; ggplot2 4.0.3 | R Foundation for Statistical Computing; Massimo Aria und Corrado Cuccurullo; ggplot2-Entwicklungsteam | https://www.r-project.org/; https://www.bibliometrix.org/; https://ggplot2.tidyverse.org/ | Zur Analyse der Produktivität und Zusammenarbeit nach Land/Region verwendet. Es wurde eine vollständige Zählung für alle Adressen angewandt; bei SCP/MCP wurde das Land des korrespondierenden Autors berücksichtigt. Taiwan, Hongkong und Macao wurden auf Länderebene ausschließlich unter China zusammengefasst. |
| SCImago Graphica 1.0.55 | SCImago Lab | https://graphica.app/ | Wird für das endgültige Layout und die Visualisierung des Direktzitierungsnetzwerks der Zeitschrift sowie der Länder-/Regionalkarten verwendet. |
| VOSviewer 1.6.21 | Centrum für Wissenschafts- und Technologiestudien (CWTS), Universität Leiden, Niederlande | https://www.vosviewer.com/ | Vollständige Zählung mit Normalisierung der Assoziationsstärke. Schwellenwerte und endgültige Netzwerke: Schlüsselwörter >=30 (158 Knoten; 6.468 Kanten); Autoren >=6 Dokumente (51; 134); Institutionen >=10 Dokumente (109; 351); Quellenzeitschriften >=20 Dokumente (39; 741); zitierte Referenzen >=68 Zitierungen (91; 3.626). Einheiten-spezifische Thesauri wurden angewandt. |
Referenzen
- Wu Y, Shen G, Hao C. Negative pressure wound therapy (NPWT) is superior to conventional moist dressings in wound bed preparation for diabetic foot ulcers: a randomized controlled trial. Saudi Med J. 2023;44(10):1020-9.
- Liu Z, Dumville JC, Hinchliffe RJ, Cullum N, Game F, Stubbs N, et al. Negative pressure wound therapy for treating foot wounds in people with diabetes mellitus. Cochrane Database Syst Rev. 2018;10(10):CD010318.
- Bruhin A, Ferreira F, Chariker M, Smith J, Runkel N. Systematic review and evidence-based recommendations for the use of negative pressure wound therapy in the open abdomen. Int J Surg. 2014;12(10):1105-14.
- Cirocchi R, et al. What is the effectiveness of negative pressure wound therapy (NPWT) in patients treated with open abdomen technique? A systematic review and meta-analysis. J Trauma Acute Care Surg. 2016;81(3):575-84.
- Orgill DP, Bayer LR. Negative pressure wound therapy: past, present and future. Int Wound J. 2013;10 Suppl 1:15-9.
- Robert N. Negative pressure wound therapy in orthopaedic surgery. Orthop Traumatol Surg Res. 2017;103(1 Suppl):S99-103.
- Morykwas MJ, Argenta LC, Shelton-Brown EI, McGuirt W. Vacuum-assisted closure: a new method for wound control and treatment: animal studies and basic foundation. Ann Plast Surg. 1997;38(6):553-62.
- Argenta LC, Morykwas MJ. Vacuum-assisted closure: a new method for wound control and treatment: clinical experience. Ann Plast Surg. 1997;38(6):563-76.
- Saxena V, et al. Vacuum-assisted closure: microdeformations of wounds and cell proliferation. Plast Reconstr Surg. 2004;114(5):1086-96.
- Normandin S, et al. Negative pressure wound therapy: mechanism of action and clinical applications. Semin Plast Surg. 2021;35(3):164-70.
- Kim PJ, et al. Negative pressure wound therapy with instillation: international consensus guidelines update. Int Wound J. 2020;17(1):174-86.
- Yamashiro T, et al. Negative-pressure wound therapy: what we know and what we need to know. In: Adv Exp Med Biol. 2023;1436:131-52.
- Webster J, Scuffham P, Stankiewicz M, Chaboyer WP. Negative pressure wound therapy for skin grafts and surgical wounds healing by primary intention. Cochrane Database Syst Rev. 2014;(10):CD009261.
- Norman G, et al. Negative pressure wound therapy for surgical wounds healing by primary closure. Cochrane Database Syst Rev. 2022;4(4):CD009261.
- Deng K, Yuan Z, Li D. Academic visualization and trend analysis of negative-pressure wound therapy from a global perspective. Asian J Surg. 2024;47(10):4449-51.
- Liu C, et al. Clinical study of early rehabilitation training combined with negative pressure wound therapy for the treatment of deep partial-thickness hand burns. Front Surg. 2023;10:1040407.
- Qian H, Lei T, Hu Y. Negative pressure wound therapy versus gauze dressings in managing open fracture wounds of the lower limbs: a meta-analysis of randomized controlled trials. Foot Ankle Surg. 2022;28(7):1120-8.
- Miller-Mikolajczyk C, Beach K, Silverman RP, Cooper ML. The evolution of commercial negative pressure wound therapy systems over the past three decades. Adv Wound Care (New Rochelle). 2024;13(8):375-90.
- Morykwas MJ, et al. Use of subatmospheric pressure to prevent progression of partial-thickness burns in a swine model. J Burn Care Rehabil. 1999;20(1 Pt 1):15-21.
- Tang L, et al. A biodegradable Janus sponge for negative pressure wound therapy. Biomacromolecules. 2024;25(4):2542-53.
- Agarwal P, Kukrele R, Sharma D. Vacuum-assisted closure (VAC)/negative pressure wound therapy (NPWT) for difficult wounds: a review. J Clin Orthop Trauma. 2019;10(5):845-8.
- Apelqvist J, et al. EWMA document: negative pressure wound therapy. J Wound Care. 2017;26 Suppl 3:S1-S154.
- Malmsjö M, Huddleston E, Martin R. Biological effects of a disposable, canisterless negative pressure wound therapy system. Eplasty. 2014;14:e15.
- Orgill DP, Bayer LR. Update on negative-pressure wound therapy. Plast Reconstr Surg. 2011;127 Suppl 1:105S-15S.
- Li Y, et al. Metabolic response to burn injury: a comprehensive bibliometric study. Front Med (Lausanne). 2024;11:1451371.
- Zhou Y, et al. Frontiers and hotspots in burn wound healing: a visualized bibliometric analysis. Regenesis Repair Rehabil. 2026;2(1):54-64.
- Xing Y, Huang Z, Cao L. Application of tissue engineering in wound healing: a 20-year bibliometric and visualized study. Medicine (Baltimore). 2025;104(35):e43008.
- U.S. Food and Drug Administration. 510(k) Premarket Notification K113236: Foryou NPWT Device. Updated February 12, 2013. Cited 2026 Jul 26. Available from: https://www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfPMN/pmn.cfm?ID=K113236
- 4L Health Co. Ltd., Foryou Medical Electronics Co. Ltd. The first in China: Foryou NPWT entire product line for the EU market has obtained MDR certification. Updated July 2, 2024. Cited 2026 Jul 26. Available from: https://foryounpwt.com/NewsEvents/News_20240702.html