Molecular profiling improves the classification of pancreatic cystic lesions but should not serve as an isolated indication for surgery. Integrating molecular findings with imaging, clinical risk factors, comorbidities, and operative tolerance may refine resection thresholds, reduce overtreatment, and support appropriate surveillance.
レビュー記事
Molecular Profiling in Mucinous Pancreatic Cystic Neoplasms: Implications for Surgical Decision-Making — A Narrative Review
この記事について
サマリー
要約
Pancreatic cystic lesions (PCLs) represent a heterogeneous group ranging from benign cysts to lesions with malignant potential. Despite advances in imaging and endoscopic evaluation, determining which lesions warrant surgical resection remains a major challenge in hepatobiliary and pancreatic surgery. Overtreatment exposes patients to substantial operative morbidity, whereas delayed intervention may permit progression to invasive cancer. Cyst-fluid molecular profiling can improve the classification of mucinous cysts and intraductal papillary mucinous neoplasms and may reduce diagnostic uncertainty during preoperative risk stratification. However, improved diagnostic classification does not necessarily establish an indication for surgery. KRAS and GNAS mutations primarily provide information about cyst identity and should not be interpreted as independent markers of malignant transformation. Conversely, negative molecular findings should not provide reassurance when radiologic or clinical features indicate substantial risk. Molecular results are therefore best considered within a multidimensional framework that incorporates imaging characteristics, cytology, clinical risk factors, patient comorbidities, and operative fitness. Additional alterations associated with advanced neoplasia may further modify risk when interpreted alongside established clinical and radiologic findings. Prospective validation and outcome-based modeling are needed to determine whether molecularly informed management reduces unnecessary surgery, improves detection of clinically significant disease, and ultimately improves patient outcomes.
概要
Pancreatic cystic lesions (PCLs) are increasingly identified during routine imaging, yet their management remains challenging. The central clinical question is not simply lesion detection but determining which cysts require surgical resection and which can be safely monitored. Pancreatic resection carries substantial morbidity, whereas delayed intervention may allow malignant progression1,2. Conventional diagnostic approaches, including cytology and cyst-fluid carcinoembryonic antigen (CEA) measurement, have limited sensitivity and specificity in indeterminate cases3,4. Against this background, cyst-fluid molecular profiling has emerged as an adjunct that may improve preoperative classification and refine risk assessment.
Recurrent KRAS and GNAS mutations in mucinous pancreatic cysts, particularly intraductal papillary mucinous neoplasms (IPMNs), have contributed to a more detailed understanding of their molecular characteristics5,6. Next-generation sequencing (NGS) of cyst fluid can improve discrimination between mucinous and non-mucinous lesions and may outperform conventional diagnostic modalities in selected settings7–9. However, improved cyst classification does not necessarily establish malignant potential or translate directly into improved clinical outcomes. Molecular findings must therefore be interpreted alongside imaging characteristics, cytology, clinical risk factors, patient comorbidities, and operative fitness. This review examines the role and limitations of cyst-fluid molecular profiling and considers how molecular information may be integrated with established clinical and radiologic factors to inform surgical decision-making and recalibrate operative thresholds.
レビューと展望
Molecular identity versus malignant potential
KRAS mutations are common early oncogenic events in mucinous cystic neoplasia, whereas GNAS mutations show strong specificity for intraductal papillary mucinous neoplasms (IPMNs)10–12. These alterations can support the identification of mucinous lineage but do not independently indicate invasive transformation. Many mucinous cysts harbor KRAS or GNAS mutations without progressing to carcinoma. Malignant progression is more frequently associated with additional genetic alterations, including TP53, SMAD4, CDKN2A, and RNF43, supporting a multistep model of neoplastic progression7,13–15. This distinction is clinically important. KRAS and GNAS alterations primarily help define cyst identity, whereas later driver alterations may provide additional information about progression toward advanced neoplasia. Mutation positivity should therefore not be interpreted as an independent indication for surgery, because doing so risks conflating molecular identity with malignant potential. For clinical decision-making, these biological differences support a tiered interpretation of molecular findings. A lineage-defining alteration may strengthen the diagnosis of a mucinous lesion, but should not, in isolation, warrant resection in an otherwise low-risk patient. Conversely, combinations of alterations associated with advanced neoplasia may increase concern when they occur alongside mural nodules, main-duct dilation, suspicious cytology, or interval growth7,13–15. The clinical value of molecular testing, therefore, depends on how substantially the result modifies the pretest probability established by imaging and clinical assessment.
Negative molecular findings also require cautious interpretation. A negative result may reflect a lower molecular burden but can also result from low DNA yield, sampling error, or an assay panel that does not include the relevant alteration. The absence of KRAS or GNAS alterations should therefore not override convincing radiologic or clinical warning signs. Molecular identity and malignant potential represent related but distinct dimensions that should be interpreted within the overall clinical risk profile.
Diagnostic performance and its boundaries
Next-generation sequencing (NGS)-based mutation analysis demonstrates high specificity and can improve sensitivity compared with cytology and Sanger sequencing7,8. High sensitivity for mucinous cyst classification has been reported in selected cohorts, although diagnostic performance varies according to assay platform, gene panel, cyst type, case mix, and reference standard16. Digital polymerase chain reaction (PCR) may further improve the detection of low-frequency variants in selected settings17. Nevertheless, sensitivity for high-grade dysplasia remains imperfect, and mutation-negative cysts may still harbor advanced disease18,19.
Sampling technique further influences molecular interpretation. Endoscopic ultrasound-guided fine-needle aspiration remains a commonly used approach2, although low DNA yield and limited cellularity can contribute to false-negative results4,20. Cyst-wall microforceps biopsy may increase the quantity of available tissue or DNA but also introduces additional procedural complexity21,22. Molecular heterogeneity within individual cysts can further produce discordant findings depending on the sampling location23–25. These limitations reinforce that molecular testing modifies diagnostic probability rather than establishing certainty.
Reported diagnostic performance is also influenced by case mix and the reference standard. Studies enriched for surgically resected or otherwise high-risk lesions may not reproduce the predictive performance observed in surveillance populations dominated by smaller incidental cysts. Similarly, an assay may perform well at identifying the mucinous lineage while remaining less reliable at detecting high-grade dysplasia or invasive disease. Diagnostic accuracy, prognostic discrimination, and clinical utility should therefore be considered distinct outcomes rather than treated as interchangeable measures.
Pre-analytic and analytic variation further limit direct comparisons across institutions. Cyst-fluid volume, storage conditions, extraction methods, sequencing depth, variant allele frequency thresholds, and panel composition can all influence molecular findings. Clinically useful reports should therefore describe sample adequacy, assay limitations, detected variants, and the evidence linking individual alterations to cyst type or advanced neoplasia. Without this context, positive or negative molecular findings may be overinterpreted during clinical decision-making.
Recalibrating operative thresholds
Current surgical guidelines rely substantially on morphologic features, including cyst size, mural nodules, and main-duct dilation. Although these features reflect structural risk, they do not directly characterize underlying molecular biology. Molecular profiling can refine cyst classification and reduce diagnostic uncertainty, particularly in cases with indeterminate cytology26–28. However, translating mutation detection directly into a surgical indication risk replaces an imaging-driven overtreatment paradigm with a molecular one. Molecular findings should therefore be incorporated into a multidimensional decision framework rather than interpreted in isolation. A molecular profiling-integrated decision model can combine baseline radiologic risk, clinical factors, genomic findings, and operative tolerance to inform surgical thresholds (Figure 1).
Within this framework, structural and molecular risk can be considered complementary dimensions. Concordant high-risk findings may strengthen consideration of resection in an operatively fit patient. Conversely, low-risk morphology accompanied only by lineage-defining mutations generally supports surveillance rather than immediate surgery. Discordant findings require multidisciplinary assessment. High-risk imaging findings should not be dismissed because of negative molecular testing, whereas high-risk molecular findings without corroborating morphologic features may support shorter-interval reassessment, repeat sampling, or referral to an expert center before major surgery is considered.
Patient-level factors further influence the threshold for intervention. Age, frailty, comorbidities, life expectancy, lesion location, and the anticipated extent of resection alter the balance between cancer prevention and procedural harm. The same molecular profile may therefore support surveillance in a frail patient facing pancreaticoduodenectomy but contribute to consideration of resection in a younger, operatively fit patient with corroborating high-risk features. Molecular findings consequently function as risk modifiers rather than universal directives that replace clinical judgment.
Emerging integrated genomic classifiers and combined DNA/RNA platforms have demonstrated improved detection of advanced neoplasia in selected studies9. Radiogenomic models incorporating imaging and molecular features may further refine risk prediction29,30. However, prospective validation remains necessary to determine whether molecularly informed strategies improve clinically meaningful outcomes rather than simply alter the timing of intervention. Prediction models should be calibrated against histopathology when available and against longitudinal outcomes in non-operated patients, because models developed primarily from resected lesions may retain substantial selection bias.
Clinical integration and future directions:
Molecular testing may be particularly useful in indeterminate cases in which imaging and cytology do not provide sufficient diagnostic clarity. In such settings, molecular findings may help refine cyst classification and support individualized surveillance or intervention strategies1. However, variability in assay platforms, reporting thresholds, and incorporation into clinical guidelines currently limits standardized implementation across institutions31. Longitudinal outcome data also remain limited, and the effect of molecularly informed management on survival has not been fully established30. Clinical integration should occur within a multidisciplinary pathway involving radiology, advanced endoscopy, pathology, molecular diagnostics, and surgery while also incorporating patient preferences. The clinical purpose of testing should be defined before molecular analysis, such as clarification of cyst type, estimation of advanced neoplasia risk, or resolution of discordant imaging and cytologic findings. Defining this purpose in advance reduces the likelihood that an unexpected molecular alteration will be interpreted as independently actionable.
Recent prospective and multi-institutional studies provide additional support for integrating cyst-fluid molecular testing into clinical assessment. A prospective study evaluating a 22-gene next-generation sequencing panel across 31 institutions showed that real-time pancreatic cyst-fluid sequencing was feasible and contributed to cyst classification and risk assessment in a large clinical cohort32. More recently, multi-institutional validation of combined DNA/RNA genomic classifiers has demonstrated improved classification of mucinous cysts and detection of advanced neoplasia compared with conventional diagnostic parameters33. These findings strengthen the evidence for integrated molecular approaches but do not establish molecular findings as independent indications for surgery; continued validation against longitudinal clinical outcomes remains necessary.
Future work should focus on standardizing sampling methods, assay validation, variant interpretation, and reporting terminology. Prospective multicenter studies should compare molecularly informed management with guideline-based care using clinically meaningful endpoints, including avoided surgery, delayed cancer diagnosis, procedure-related morbidity, quality of life, and survival. Integrated decision models should also undergo external validation across surveillance populations and healthcare settings before being used to redefine operative thresholds.
Serial assessment may ultimately provide more clinically relevant information than a single molecular measurement. Changes in imaging findings, symptoms, and molecular burden over time could help distinguish stable lineage-associated alterations from evolving high-risk biology. However, this approach requires validated sampling intervals and evidence that repeated procedures provide sufficient clinical benefit to justify their additional risks and burden. Until such evidence is available, molecular findings should complement rather than replace established clinical and radiologic surveillance.
結論
KRAS and GNAS mutation analysis has improved the molecular classification of pancreatic cystic lesions, particularly mucinous cysts and intraductal papillary mucinous neoplasms. However, mutation positivity alone should not determine the need for surgical resection. Lineage-defining alterations can clarify cyst identity, whereas additional genetic changes associated with advanced neoplasia may further modify risk. Neither category is sufficiently informative without consideration of sampling adequacy and the broader clinical context. Molecular findings should therefore be integrated with radiologic features, cytology, clinical risk factors, comorbidities, life expectancy, and operative fitness to support individualized decision-making. In practice, molecular data are best used as probability modifiers within a multidisciplinary framework, particularly when conventional assessment is indeterminate or discordant. Future studies should standardize molecular testing and reporting, externally validate integrated decision models in surveillance populations, and determine whether molecularly informed strategies reduce unnecessary surgery without delaying treatment of clinically significant disease. The objective is not simply to detect additional mutations but to use molecular information appropriately to refine operative thresholds and improve patient outcomes.
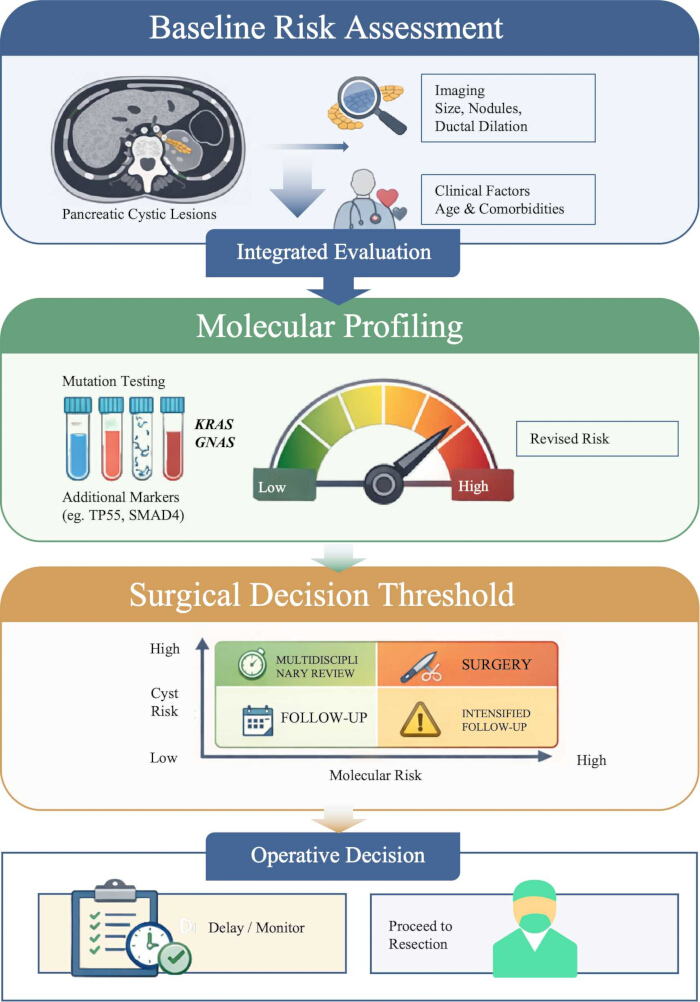
Figure 1: Molecular profiling-integrated decision model for recalibrating surgical thresholds in pancreatic cystic lesions. Baseline risk assessment incorporates imaging features and clinical factors, including age and comorbidities. Cyst-fluid molecular profiling is then used to modify the estimated risk of advanced neoplasia. In the surgical decision matrix, the vertical axis represents cyst or structural risk, and the horizontal axis represents molecular risk. Concordant high-risk findings may support consideration of surgery in an operatively fit patient, whereas low-risk findings generally support surveillance. Discordant findings should prompt a multidisciplinary review rather than automatic resection or observation. The integrated risk estimate should ultimately be interpreted together with operative fitness, life expectancy, and expected surgical benefit to guide surveillance, intensified follow-up, or resection. Please click here to view a larger version of this figure.
開示事項
The authors declare no conflicts of interest.
謝辞
The authors received no specific funding for this work.
参考文献
- Turner RC, et al. Molecular analysis of pancreatic cyst fluid for the management of intraductal papillary mucinous neoplasms. Diagnostics (Basel). 2022;12(11):2573. doi: 10.3390/diagnostics12112573.
- Xia R, et al. The utility of molecular studies on pancreatic cystic lesions: a comprehensive review. Hum Pathol Rep. 2024;36:300741. doi: 10.1016/j.hpr.2024.300741.
- Kwan MC, Pitman MB, Fernandez-del Castillo C, Zhang ML. Revisiting the performance of cyst fluid carcinoembryonic antigen as a diagnostic marker for pancreatic mucinous cysts: a comprehensive 20-year institutional review. Gut. 2024. doi: 10.1136/gutjnl-2023-331138.
- Faias S, et al. Clinical impact of KRAS and GNAS analysis added to CEA and cytology in pancreatic cystic fluid obtained by EUS-FNA. Dig Dis Sci. 2018;63(9):2351–2361. doi: 10.1007/s10620-018-5128-y.
- Wu J, et al. Recurrent GNAS mutations define an unexpected pathway for pancreatic cyst development. Sci Transl Med. 2011;3(92). doi: 10.1126/scitranslmed.3002543.
- Furukawa T, Kuboki Y, Tanji E, et al. Whole-exome sequencing uncovers frequent GNAS mutations in intraductal papillary mucinous neoplasms of the pancreas. Sci Rep. 2011;1:161. doi:10.1038/srep00161.
- Singhi AD, et al. Preoperative next-generation sequencing of pancreatic cyst fluid is highly accurate in cyst classification and detection of advanced neoplasia. Gut. 2018;67(12):2131–2141. doi: 10.1136/gutjnl-2016-313586.
- Schmitz D, et al. KRAS/GNAS testing by highly sensitive deep targeted next-generation sequencing improves the endoscopic ultrasound-guided workup of suspected mucinous neoplasms of the pancreas. Genes Chromosomes Cancer. 2021;60(7):489–497. doi: 10.1002/gcc.22946.
- Nikiforova MN, et al. A combined DNA/RNA-based next-generation sequencing platform to improve the classification of pancreatic cysts and early detection of pancreatic cancer arising from pancreatic cysts. Ann Surg. 2023;278(4):e789–e797. doi: 10.1097/sla.0000000000005904.
- Singhi AD, et al. Preoperative GNAS and KRAS testing in the diagnosis of pancreatic mucinous cysts. Clin Cancer Res. 2014;20(16):4381–4389. doi: 10.1158/1078-0432.ccr-14-0513.
- Lee JH, Kim Y, Choi JW, Kim YS. KRAS, GNAS, and RNF43 mutations in intraductal papillary mucinous neoplasm of the pancreas: a meta-analysis. Springerplus. 2016;5(1). doi: 10.1186/s40064-016-2847-4.
- Frampton AE, et al. Activating mutations of GNAS and KRAS in cystic fluid can help detect intraductal papillary mucinous neoplasms of the pancreas. Expert Rev Mol Diagn. 2015;15(3):325–328. doi: 10.1586/14737159.2015.1002771.
- Amato E, et al. Targeted next-generation sequencing of cancer genes dissects the molecular profiles of intraductal papillary neoplasms of the pancreas. J Pathol. 2014;233(3):217–227. doi: 10.1002/path.4344.
- Papadopoulos N, Hruban RH. Molecular mechanisms of cystic neoplasia. In: The Pancreas: An Integrated Textbook of Basic Science, Medicine, and Surgery. 4th ed. Wiley; 2023. p. 630–637. doi: 10.1002/9781119876007.ch82.
- Chang XY, et al. RNF43 mutations in IPMN cases: a potential prognostic factor. Gastroenterol Res Pract. 2020;2020:1–10. doi: 10.1155/2020/1457452.
- Yang S, Chen T, Cui M, Hu Y. Genomic alterations in pancreatic cystic neoplasms: from molecular characterization to precision clinical management. Int J Surg. 2025;111(10):7053–7071. doi: 10.1097/js9.0000000000002814.
- van Huijgevoort NCM, et al. Detecting KRAS mutations in pancreatic cystic neoplasms: droplet digital PCR versus. targeted next-generation sequencing. HPB (Oxford). 2023;25(1):155–159. doi: 10.1016/j.hpb.2022.10.007.
- Herranz Pérez R, et al. Molecular analysis of pancreatic cystic neoplasm in routine clinical practice. World J Gastrointest Endosc. 2021;13(2):56–71. doi: 10.4253/wjge.v13.i2.56.
- Haeberle L, et al. Molecular analysis of cyst fluids improves the diagnostic accuracy of preoperative assessment of pancreatic cystic lesions. Sci Rep. 2021;11(1). doi: 10.1038/s41598-021-81065-2.
- Jang KT. Recent update in pathologic diagnosis for pancreatic cystic neoplasm. Korean J Pancreas Biliary Tract. 2019;24(4):137–140. doi: 10.15279/kpba.2019.24.4.137.
- Zhang ML, et al. Moray microforceps biopsy improves the diagnosis of specific pancreatic cysts. Cancer Cytopathol. 2018;126(6):414–420. doi: 10.1002/cncy.21988.
- Astbury S, et al. Next-generation sequencing of pancreatic cyst wall specimens obtained using microforceps for improving diagnostic accuracy. Endosc Int Open. 2023;11(10):E983–E991. doi: 10.1055/a-2163-8805.
- Volckmar AL, et al. Next-generation sequencing of the cellular and liquid fraction of pancreatic cyst fluid supports discrimination of IPMN from pseudocysts and reveals cases with multiple mutated driver clones: first findings from the prospective ZYSTEUS biomarker study. Genes Chromosomes Cancer. 2019;58(1):3–11. doi: 10.1002/gcc.22682.
- Rift CV, et al. Molecular heterogeneity of pancreatic intraductal papillary mucinous neoplasms and implications for novel endoscopic tissue sampling strategies. J Clin Pathol. 2021;75(10):681–686. doi: 10.1136/jclinpath-2021-207598.
- Paziewska A, et al. Mutational mosaics of cell-free DNA from pancreatic cyst fluids. Dig Dis Sci. 2020;65(8):2294–2301. doi: 10.1007/s10620-019-06043-1.
- Rosenbaum MW, et al. Next-generation sequencing adds value to the preoperative diagnosis of pancreatic cysts. Cancer Cytopathol. 2017;125(1):41–47. doi: 10.1002/cncy.21775.
- Sakhdari A, et al. Somatic molecular analysis augments cytologic evaluation of pancreatic cyst fluids as a diagnostic tool. Oncotarget. 2019;10(40):4026–4037. doi: 10.18632/oncotarget.26999.
- Zhang ML, Pitman MB. Practical applications of molecular testing in the cytologic diagnosis of pancreatic cysts. J Mol Pathol. 2021;2(1):11–22. doi: 10.3390/jmp2010002.
- Zhou WT, Lou WH. Predictors of malignant intraductal papillary mucinous neoplasm of the pancreas [article in Chinese]. Zhonghua Wai Ke Za Zhi. 2023;61(11):1032–1036. doi: 10.3760/cma.j.cn112139-20230826-00058.
- Hu Y, et al. Molecular pathology of pancreatic cystic lesions with a focus on malignant progression. Cancers (Basel). 2024;16(6):1183. doi: 10.3390/cancers16061183.
- Nikas IP, et al. Evaluating pancreatic and biliary neoplasms with small biopsy-based next-generation sequencing (NGS): doing more with less. Cancers (Basel). 2022;14(2):397. doi: 10.3390/cancers14020397.
- Paniccia A, et al. Prospective, multi-institutional, real-time next-generation sequencing of pancreatic cyst fluid reveals diverse genomic alterations that improve the clinical management of pancreatic cysts. Gastroenterology. 2023;164(1):117–133.e7. doi: 10.1053/j.gastro.2022.09.028.
- Singhi AD, et al. PancreaSeq Genomic Classifier (PancreaSeq GC) improves pancreatic cyst classification and detection of advanced neoplasia: a multi-institutional validation study. Ann Surg Oncol. 2026;33(4):2865–2875. doi: 10.1245/s10434-025-18848-8.