Utero-tubal embryo transfer uses the utero-tubal junction as a barrier to prevent the embryo outflow that may occur when performing uterine transfer. Vasectomized males are required to obtain pseudopregnant recipients for embryo transfer. Both techniques are discussed.
Method Article
Utero-tubal Embryo Transfer and Vasectomy in the Mouse Model
In This Article
Summary
Abstract
The transfer of preimplantation embryos to a surrogate female is a required step for the production of genetically modified mice or to study the effects of epigenetic alterations originated during preimplantation development on subsequent fetal development and adult health. The use of an effective and consistent embryo transfer technique is crucial to enhance the generation of genetically modified animals and to determine the effect of different treatments on implantation rates and survival to term. Embryos at the blastocyst stage are usually transferred by uterine transfer, performing a puncture in the uterine wall to introduce the embryo manipulation pipette. The orifice performed in the uterus does not close after the pipette has been withdrawn, and the embryos can outflow to the abdominal cavity due to the positive pressure of the uterus. The puncture can also produce a hemorrhage that impairs implantation, blocks the transfer pipette and may affect embryo development, especially when embryos without zona are transferred. Consequently, this technique often results in very variable and overall low embryo survival rates. Avoiding these negative effects, utero-tubal embryo transfer take advantage of the utero-tubal junction as a natural barrier that impedes embryo outflow and avoid the puncture of the uterine wall. Vasectomized males are required for obtaining pseudopregnant recipients. A technique to perform vasectomy is described as a complement to the utero-tubal embryo transfer.
Introduction
Embryo transfer is probably the most frequent surgical procedure performed in the mouse model. This technique is essential to obtain offspring from embryos subjected to in vitro manipulation techniques and, therefore, constitutes a necessary step for the development of genetically modified models by pronuclear injection, lentiviral transduction, or chimera formation. Besides, the technique allows the study of the developmental effects of diverse insults occurring during preimplantation development. The use of artificial reproduction techniques1 or the exposure to abnormal concentrations of different substances or metabolites2 may affect embryo development resulting in implantation or placentation failures and long term effects in the offspring. A reliable and reproducible embryo transfer technique is crucial to test the possible negative effects of the experimental treatment on implantation and fetal development in a consistent manner.
Murine preimplantation embryos can be transferred to a recipient female either into the oviduct via the ampullae of 0.5 days post coitum (dpc) pseudopregnant recipients (oviduct transfer)3,4 or into the uterus of 2.5 dpc pseudopregnant recipient (uterine transfer)5,6 depending on their developmental stage. Embryos at the blastocyst stage, such as those used to generate chimeric mice by injection of embryonic or induced pluripotent stem cells, are usually transferred by uterine transfer. Blastocysts can also be transferred to the oviduct of a 0.5 dpc recipient, but it constitutes a less physiological test for developmental disruptors, because the embryo undergoes diapause and has 2 days to recover from the insult before implantation takes place. Uterine transfer involves puncturing the uterine wall with a narrow needle in order to generate an aperture that allows the access of an embryo manipulation pipette into the uterine lumen. Although this technique can yield good results, the survival to term (i.e. the percentage of embryos transferred that develop to a pup) is often low and unpredictable7,8.
The puncture of the uterine wall entails some detrimental side effects. First, myometrium is a highly vascularized tissue and its puncture often results in a small hemorrhage. Blood may block the embryo transfer pipette or invade the uterine lumen causing embryonic death and/or implantation failure. This is particularly relevant when embryos without zona are transferred, as the blood cells and debris can attach to the blastomeres. Second, the opening performed does not seal after the embryos have been transferred, so they can flow back through the orifice and be expelled to the abdominal cavity when a too large volume has been introduce into the uterus. The utero-tubal embryo transfer described herein take advantage of the utero-tubal junction to deliver the embryos into the uterus without the need of puncturing the uterine wall and thereby avoiding its adverse consequences9.
The pseudopregnant recipient females used for embryo transfer are obtained by natural mating with vasectomized males8. The seminal secretions produced by a sterile male are required for the uterus to become receptive to the transferred embryos. To obtain a recipient, a maximum of 2 females of 8 weeks to 6 months of age are placed with a vasectomized male in the afternoon. The following morning, females are checked for the presence of a vaginal copulation plug, a clump of coagulated proteins from the male seminal fluid. As mating usually occurs during midnight, the day of vaginal plug detection is considered to be 0.5 dpc. Although vasectomized males can be purchased from some vendors, the surgical procedure described herein is relatively easy and does not require any additional instruments than required for embryo transfer.
Protocol
All animal experiments were approved by the Beltsville Area Animal Care and Use Comittees (BAACUC 11-015) in accordance with USDA Animal Care and Use Guidelines.
1. Anesthesia and Analgesia (Common for Both Surgical Procedures)
- Weigh the mouse and load the following anesthetics and analgesic in two 1 ml syringes with 27 G needles:
- Ketamine (0.1 mg/g: 0.01 ml/g of a 10 mg/ml solution) and xylazine (0.01 mg/g: 0.005 ml/g of a 2 mg/ml solution).
- Buprenorphine (0.1 μg/g: 0.01 ml of a 0.01 mg/ml solution).
- Immobilize the mouse by picking up the scruff of its neck as close to the jaws as possible with the thumb and index fingers and holding the tail between the little and ring fingers.
- Inject Ketamine-Xylazine mixture intraperitoneally. In order to avoid puncturing internal organs, hold the mouse with its head slightly below the level of its hips (Figure 1A)
- Inject Buprenorphine subcutaneously in the scruff of neck hold between the thumb and index fingers (Figure 1B).
- Leave the mouse in the cage (clean and without any other animal) on a warm stage.
- Once unconscious, check for the absence of rear foot reflex (checked by toe pinch). Apply eye ointment to avoid dryness of the eye and to check for the absence of palpebral reflex (Figure 1C).
- This protocol provides a surgical anesthesia plane for a minimum of 30 min, enough to perform the procedures described below (Protocols 2 and 3). If longer times are required, an additional injection of ketamine + xylazine with half of the dosage described in 1.1.1 can be applied after 30 min. A change in the breathing pattern to a faster and irregular one indicates the loss of the proper anesthesia plane.
2. Vasectomy
- Use a male with a proven mating performance.
- Sterilize surgical instruments, clean the surfaces where surgery will be performed and wipe them with 70% ethanol.
- Perform anesthesia as previously detailed (Protocol 1), checking for loss of reflexes.
- Place the mouse on a warm stage, remove fur with electric clippers from the ventral area between two imaginary transversal lines placed 0.5 cm and 2.5 cm above the penis (Figure 2A).
- Sanitize the shaved area by sequential wiping with 10% povidone iodine and 70% ethanol.
- Place the mouse in supine position with its tail towards the surgeon and cover with a sterile towel with a hole exposing the shaved area. Illuminate the surgical area.
- Perform a 10-15 mm longitudinal skin incision in the medial line of the abdomen, about 1 cm above the penis. Hold the skin with dressing serrated forceps and then cut with scissors (Figures 2A and 2B).
- Perform a 5-10 mm longitudinal incision in the linea alba. Hold the muscle with microdissecting serrated forceps and cut with scissors (Figure 2C).
- Grab the testicular adipose pad of one side with micro dissecting serrated forceps and pull it to expose testis, vas deferens and epididymis. Vas deferens is located medial to the testis and it is a clearly distinguishable free tube (not attached to the testis wall like the epididymis) with a blood vessel running along one side (Figure 2D).
- Holding the vas deferens with a micro dissecting serrated forceps, flame dressing forceps until they turn red (Figure 2E), and then use them to cut and cauterize the vas deferens in two points at once (Figure 2F). The cut should remove a portion of about 5 mm and leave two clearly separated cauterized ends (Figure 2G).
- Move the testicle, epididymis and vas deferens back to the abdominal cavity.
- Proceed from step 9 in the other testicle.
- Suture the muscle with one or two horizontal mattress stitches made with 5/0 absorbable suture (Figure 2H).
- Suture the skin with one or two wound clippers (Figure 2I).
- Identify the vasectomised male (ear ring, finger tattoo…), move it the cage placed on a warm stage and observe until it recovers from anesthesia (conscious and maintain sternal recumbency). A 0.5-1 ml subcutaneous injection of warm saline solution improves recovery. Record the possible incidences occurring during vasectomy transfer, add antibiotic to the drinking water.
- Wound clips can be removed 10 days after vasectomy with a wound clipper remover or a pair of teeth forceps. The vasectomized male will be ready to mate 2 weeks after surgery.
- Test the infertility of the vasectomized male by mating with fertile females before using it to obtain recipients.
3. Utero-tubal Embryo Transfer
- Mouse morulae or blastocysts can be transferred by this technique to a pseudopregnant recipient female at 2.5 dpc.
- Prepare embryo manipulation glass pipette:
- Polish the tips of the glass capillaries in order to avoid damaging the pipette holder.
- Soften a middle portion of the glass capillary by heating with a fine flame while slightly rotating the capillary with both hands synchronously. Once the capillary section becomes soft and malleable (light red color), withdraw it quickly from the flame and pull both ends to narrow its external diameter to 130-150 μm.
- Wait for the glass to cool down and then cut it by lightly scoring the narrow part with a diamond-point pencil, abrasive stone or nail file and pulling from both sides. The break should be clean and perpendicular
- Polish the tip by very quickly flaming, leaving a 100-130 μm aperture. Pipettes can be stored for later use.
- Warm embryo manipulation media (CZBH or M2, see discussion).
- Sterilize surgical instruments, clean the surfaces where surgery will be performed and wipe them with 70% ethanol.
- Perform anesthesia as previously detailed (Protocol 1), checking for loss of reflexes.
- Keeping the mouse on a warm stage, remove fur with electric clippers from the dorsal area between the knees and the distal ribs (Figures 3A and 3B).
- Sanitize the shaved area by sequential wiping with 10% povidone iodine and 70% ethanol.
- Move the embryos from the incubator to the prewarmed embryo manipulation media.
- Move the recipient to a warm stage under the stereomicroscope and place it in prone position laterally to the surgeon (with its head looking to the right or left side of the surgeon).
- Cover the area with a sterile towel with a hole exposing the shaved area and illuminate the surgical area.
- Perform a 1 cm transversal (vertical) incision in the skin in a spot located on the cranial ⅓ of the line between the last rib and the hips and the dorsal ⅓ of the line between the back and the abdomen (Figures 3A and 3B). Hold the skin with dressing serrated forceps and cut with scissors (Figure 3C).
- Once the skin has been cut, ovary (red/orange) or the adipose pad surrounding the ovary (white) can be visualized through the body wall. Perform a 0.3-0.5 cm transversal (vertical) incision in the body wall over the ovary or adipose pad in a spot where the incision does not cut any large blood vessel. Hold the muscle with micro dissecting serrated forceps and cut with scissors (Figure 3D).
- Move the mouse to have its head facing towards the surgeon.
- Load the embryo manipulation pipette (Figure 3E):
- Allow CZBH media to ascend by capillarity through the narrow portion of the manipulation pipette until about 5 mm of the wider part.
- Take up a small air bubble (0.2-0.5 mm).
- Introduce the embryos (5-10) in a minimal amount of media (2-4 mm).
- Take up another small air bubble (0.2-0.5 mm) and a small amount of media (0.5-1 mm).
- Leave the glass pipette attached to the mouth aspirator holder or to the hand-operated device, ready for step 3.17.
- Grab the adipose pad surrounding the ovary with micro dissecting serrated forceps and pull it towards the mouse head to expose the ovary, oviduct, and a small portion of the upper uterus out of the abdominal cavity (Figures 3F and 3G).
- Holding the aspirator mouth piece in the mouth, ready to be used, grab the adipose pad with micro dissecting serrated forceps to move the oviduct and expose the utero-tubal junction (i.e. where the oviduct meets the uterus).
- Keeping the utero-tubal junction accessible, take slight curved micro dissection forceps with your left hand (if right handed) and place them just below the utero-tubal junction grabbing the oviduct about 2 mm above that portion.
- Holding the utero-tubal junction with the slight curved micro dissection forceps, puncture the oviduct section close to the forceps with a 27 G needle (Figure 3H).
- Insert the embryo manipulation pipette into the orifice performed with the needle and advance to the uterus through the utero-tubal junction (Figures 3I and 3J). Once the pipette has passed the utero-tubal junction (Figure 3K) it slides easily. Do not progress very far into the uterus to prevent endometrial damage (no more than 3 mm) and pipette blocking by the debris.
- Release the embryos into the uterus by gently blowing (Figure 3L). Both air bubbles must pass through the uterus. Some of the media above the first bubble may also be released into the uterus, but avoid introducing more air, as it may impede implantation.
- Remove the pipette just after embryos have been released into the uterus.
- Move the oviduct and ovary back to the abdominal cavity by grabbing the adipose pad.
- Suture the muscle with a horizontal mattress stitch with 5/0 absorbable suture (Figure 3M).
- Suture the skin with a wound clipper (Figure 3N).
- Proceed from step 10 on the other side if required.
- Identify the recipient (ear ring, finger tattoo…), move it to its cage (placed on a warm stage) and observe until it recovers from anesthesia (conscious and maintain sternal recumbency).
- Annotate the possible incidences occurring during embryo transfer and add antibiotic to the drinking water. A 0.5-1 ml subcutaneous injection of warm saline solution improves recovery.
- Wound clips can be removed 10 days after embryo transfer with a wound clipper remover or two pairs of forceps (Figure 3O). The recipient can be weighed on that day to assess pregnancy and estimate the number of pups. Provide nestling material to the recipient 15 days after embryo transfer.
Results
Utero-tubal embryo transfer provides a mean to transfer embryos to the uterus avoiding some of the complications associated to the uterine embryo transfer2,9,10. In Table 1 we show some representative result we have obtained transferring CD1 blastocysts subjected to different kinds of manipulations to CD1 recipients following the protocol described. The survival to term (% of embryos resulting in a pup) or survival to E15 (in the case of lentivirus exposed) is similar between embryos simply cultured in vitro from the zygote stage (IVC), embryos subjected to iPSC injection to generate chimeric pups and embryos that had their zona removed and were exposed to lentivirus for 7 hr before embryo transfer. Therefore, utero-tubal embryo transfer is a reliable technique to transfer embryos particularly complicated such as those lacking zona pellucida and incubated with lentivirus.

Figure 1. Injection of anesthetics and analgesics. A) Intraperitoneal injection of Ketamine-Xylazine. B) Subcutaneous injection of Buprenorphine. C) Application of eye ointment.
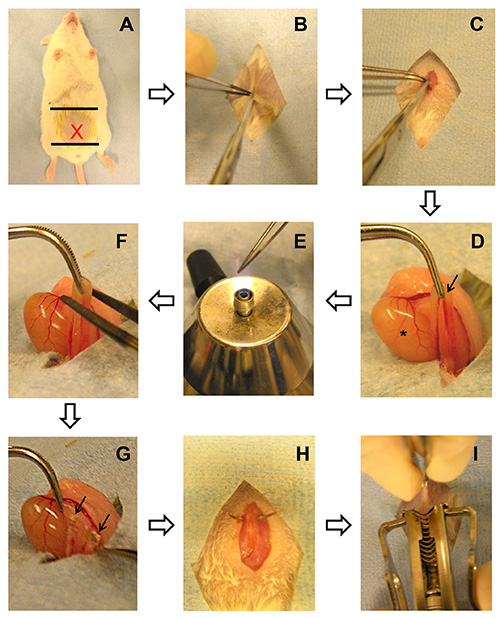
Figure 2. Vasectomy protocol. A) The incision point (depicted with a red "X") is placed about 1 cm above the penis; remove fur from 0.5-2.5 cm above penis (black lines). B) Skin incision. C) Muscle incision. D) Vas deferens (black arrow) and testis (*). E) Flaming of the forceps for cauterization. F) Cauterization of the vas deferens in two points at once. G) Vas deferens clearly separated into two cauterized ends. H) Muscle suture. I) Skin suture. Click here to view larger image.
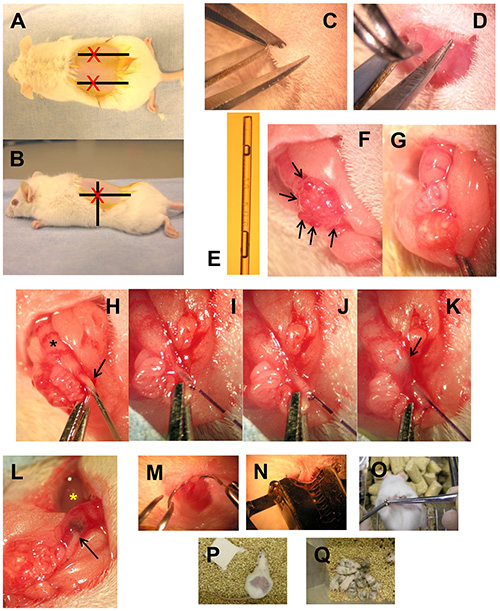
Figure 3. Utero-tubal embryo transfer protocol. A,B) Dorsal and lateral view of the incision point (depicted with a red "X"); black lines between the last rib and hips (A,B) and between back and abdomen (B) serve as a guide. C) Skin incision. D) Muscle incision. E) Embryo manipulation glass pipette loaded with 5 blastocysts ready to be transferred. F,G) Representative ovaries with (F) or without (G) corpora lutea, indicated with black arrows. H-K) For representation purposes, a simulation of utero-tubal embryo transfer was performed loading a glass manipulation pipette with 0.4% trypan blue solution. H) Puncture of the oviduct (black arrow) close to the uterus (*). I) Introduction of the embryo manipulation pipette into the orifice performed previously. J) The embryo manipulation pipette advances through the utero-tubal junction. K) A volume of trypan blue solution equivalent to that released in an embryo transfer has been expelled in the uterine lumen (black arrow). L) To test the efficient closure produced by the utero-tubal junction, all the content of the manipulation pipette was released into the uterus; utero-tubal junction (arrow) impedes the back flow of the trypan blue solution released into the uterus (*). M) Muscle suture. N) Skin suture. O) Clip removal. P) 15 days after embryo transfer provide nestling material to the recipient. Q) Chimeric litter obtained following this technique. Click here to view larger image.
| Treatment | Number of transfers | Embryos transferred | Pups delivered | Survival to term (%) |
| IVC | 11 | 110 | 82 | 74.5 |
| iPSC injection | 3 | 50 | 35 | 70.0 |
| Lentivirus | 6 | 60 | 44 | 73.3 |
Table 1. Representative results obtained after transferring three different groups of manipulated embryos following utero-tubal embryo transfer. 1) Embryos cultured in vitro (IVC) from the zygote stage to the blastocyst stage, 2) In vivo produced blastocysts injected with 10 mouse iPSC to generate chimeric mice, 3) In vivo produced blastocysts that had their zona removed and were incubated for 7 hr with a lentivirus expressing GFP. Data represent the number of pups born out of the number of embryos transferred except for the lentivirus exposed group, where they represent the number of viable fetuses 10 days after embryo transfer, as gestation was not allow to progress further.
Discussion
Vasectomy is a relatively straight forward surgical technique that does not involve major difficulties. When sanitizing with povidone iodine and ethanol make sure that the last wash (with ethanol) removes povidone iodine, as it may irritate the peritoneum. The access to vas deferens can also be achieved by the scrotum or performing a transversal incision in the abdomen8. Scrotal incision has been recommended to transversal abdominal incision due to the comparatively smaller incision needed and slightly better postoperative behavior11. However, we prefer the abdominal incision over the scrotal because it provides an easier and clearer access to the vasa deferentia from both testicles, preventing novice surgeons from cauterizing twice the same vas deferens and leaving a functional vas deferens. Between both abdominal techniques, we favor the longitudinal incision in the linea alba over the transversal because it does not cut any abdominal muscular fiber, avoiding the development of abdominal hernias. However, both vasectomy and utero-tubal embryo transfer protocols can be adapted to the equipment available or to the personal likes of the researcher. For instance, a glass bead sterilizer can be used to heat the forceps used to cauterize the vas deferens. In any case, it is essential to follow an aseptic technique, to provide proper anesthesia and analgesia in order to maximize animal welfare, and to comply with local regulations.
Another aspect susceptible for modifications is the anesthesia protocol. If inhalational anesthesia (isoflurane) is available, we encourage its use instead of parenteral (injectable) anesthesia, as it provides a very stable anesthesia plane and rapid recovery. However, it is important to state that inhalational anesthesia still requires the use of an analgesic for intra- and post-operatory pain, which should be administered before the surgery as premedication. Buprenorphine is an opioid that provide long term analgesia in mouse12. Parenteral anesthesia also provides a good anesthetic plane for short procedures such as vasectomy and embryo transfer. Ketamine-Xylazine is a very reliable combination for mouse surgery13 and we have never observed any anesthetic complications using this combination in conjunction with premedication with buprenorphine. Other parenteral combinations may be used12, but we discourage the use of the narcotic mixture avertin (tribromoethanol), as only a single dose can be administer and multiple articles have reported diverse complications associated with its use such as local irritation, poor analgesia, ileus, fibrous adhesions in the abdominal cavity, necrosis of subperitoneal muscle fibers and abdominal organs surface, and even mortality14-18.
Embryo transfer requires good management of both embryos and recipient. As a general rule for mammalian embryo transfer, the developmental stage of the embryos can be more advanced than the pseudopregnancy stage of the recipient, but not the opposite. In other words, the embryos can wait for the mother, but the mother cannot wait for the embryos, so this technique can be used to transfer morulae or blastocysts, but not earlier stages. Utero-tubal embryo transfer can be performed two days after the detection of the vaginal plug from noon (2.5 dpc) to evening-night (3 dpc), when the utero-tubal junction is open to allow the natural transit of embryos from the oviduct to uterine horns. Considering that the embryos transferred may have already suffered from some kind of manipulation, embryo handling should minimize any further damage. An excellent guide for mouse embryo manipulation can be found in Nagy et al.8 The two most commonly used mouse embryo manipulation media, which hold a physiological pH in regular atmosphere, are CZBH19 and M220. Although in vivo produced mouse embryos can overcome the exposure to cold temperature or abnormal pH for long periods21, manipulation media should be prewarmed. If media is prewarmed in a culture dish, avoid warming for long periods (more than 40 min), as the osmolarity of the media will increase due to water evaporation and that can be more harmful than cold manipulation media. Similarly, the time the embryos spent inside the manipulation pipette should be minimized due to the small volume present in the pipette.
The use of a proper embryo manipulation pipette is crucial for the success of the protocol. Manipulation pipettes can be made from glass capillaries with a thin glass wall. Pasteur pipettes, often used to handle large animal embryos, can also be employed, but due to its shorter distance from the handle to the tip, manipulation pipettes made from glass capillaries are more comfortable to maneuver. The exposure to the flame and speed of pulling determine the wall thickness and inner diameter of the pipette. Although manipulation pipettes can be easily done by hand after some practice, puller and micro-forge may also be used. It is important to invest time in producing several optimal manipulation pipettes. The manipulation pipette aperture should be wider than an embryo to allow a smooth flow, but small enough to easily penetrate and progress through the utero-tubal junction. If zona pellucida has been removed before the transfer, blastocysts usually expand to a larger diameter. In this case, it is advisable to make wider pipettes with a wider aperture (130-180 μm) to avoid any damage to the trophectoderm cells. Tip polish is important to avoid damaging the oviduct, uterine wall and the embryo - especially if zona has been removed, and to avoid the pipette tip from being blocked by debris. However, after polishing, the aperture should not be too small compared with the inner diameter of the pipette, as a sharp decrease in diameter will cause abrupt changes in flow speed. The aspirator mouthpiece provides a more precise flow control as well as a more comfortable hand position compared to hand-controlled devices. Nevertheless, a hand-controlled device may be used if required (for instance when manipulating lentivirus-treated embryos). For an optimal flow and to avoid the transfer of mineral oil, it is also advisable to use a new pipette for embryo transfer instead of that used to move the embryos from the culture media to the manipulation media. Finally, while introducing the pipette through the oviduct, the capillary should be handled directly, i.e. grabbing the glass and not the plastic handle of the aspirator, to obtain a firm grip. The magnification used for embryo transfer is a personal matter that depends on the visual acuity of the surgeon. We prefer to use low magnification to have a wide visual field, so we use a 10X final magnification (10X ocular and 1X objective).
The recipients should be at least 8 weeks old and weigh between 27-40 g. Outbreed mice such as CD1 or Swiss Webster display a good maternal behavior and are excellent recipients. It is advisable to set up breeding to obtain extra recipients, as those not used will recover its normal cycling activity in two weeks. Despite being mated, some females may not have corpora lutea (Figure 3G) and therefore will not be receptive to the transferred embryos. For this reason, ovaries should be checked for the presence of corpora lutea, which at 2.5 dpc can be clearly identified as bright red structures in the ovary (Figure 3F). During the surgery it is important to minimize the contact with the reproductive tract by grabbing ovarian adipose pad instead; excessive manipulation of the ovary and uterus may result in luteolysis. The introduction of the manipulation pipette into the oviduct is the most complicated step of the protocol. In some recipients, the oviduct is very twisted and there is not a 2 mm straight stretch from the junction with the uterus. In that case arrange the oviduct and perform the puncture in the first bend. As detailed above, a nice manipulation pipette really makes a difference. Once the pipette has passed through the utero-tubal junction, it slides easily. If it does not, the pipette may have deviated from the oviduct and not reached the uterine lumen. Once inside the uterus, if the media does not flow, move the pipette slightly out or in and try again. If it still does not flow, the pipette is clogged, take it out from the uterus, release the content in the dish with manipulation media and reload the same or other pipette. Delivery usually takes place 17 days after embryo transfer. To prevent cannibalism, provide nestling material 2 days in advance and do not change the cage during the first days after delivery.
Disclosures
The authors declare no competing financial interests.
Acknowledgements
This work was supported by funds from the Department of Animal and Avian Sciences to BT.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Ketamine | VEDCO | Ketaved ANADA 200-257 | To be ordered by a licensed veterinarian. |
| Xylazine | Lloyd Laboratories | Anased NADA #139-236 | To be ordered by a licensed veterinarian. |
| Buprenorphine | Generic | NDC 400-42-010-01 | To be ordered by a licensed veterinarian. |
| Eye ointment | Novartis | Genteal | |
| Antibiotic | Pfizer | Clavamox NADA #55-101. | Added to drinking water (0.3 mg/ml of amoxicillin trihydrate and 0.075 mg/ml of clavulanate potassium). Add 1.5 ml of the reconstituted 15 ml bottle to 250 ml of water. |
| Dressing serrated forceps | ROBOZ | RS-8120 | Any medium size surgical-grade steel straight forceps will work. |
| Microdissecting serrated forceps | ROBOZ | RS-5137 | These ones are curved at a 90º angle. Straight forceps can be used if preferred. |
| Slight curved micro dissection forceps | ROBOZ | RS-5136 | This model is particularly useful to hold the oviduct. |
| Scissors | ROBOZ | RS-5880 | Any regular surgical grade steel small straight scissors will work. |
| 27 G needles | Beckton-Dickinson | 305136 | Smaller needles (30 G) can be also used. 25 G may be a bit too big. |
| Clip applier | MiKRon | 42763 | |
| 9 mm Clips | MiKRon | 427631 | |
| Clip remover | MiKRon | 7637 | Two pairs of teeth forceps (ROBOZ RS-8160) can be used instead. |
| Suture needle holder | ROBOZ | RS-7820 | |
| Suture | Dowist Gell | 5-0 Dexon S 7204-21 | Can be substituted for any 4-0 to 6-0 absorbable suture with a narrow curved needle. |
| Glass capillaries | VWR | 100 ul calibrated pipettes 53432-921 | It includes a mouth aspirator system that only requires to attach a 0.22 µm filter in the tubing to be ready to use. More information can be obtained in Nagy et al.8 |
| Burner | KISAG AG | Typ 2002 | Gas operated burner, can be charged with Kigas (CH-4512, from the same vendor). Alcohol burners may be also used, but gas provides a higher temperature and this burner provides a small and precise flame. |
| Stereomicroscope | Leica | MZFLIII | This is an expensive estereomicroscope with fluorescence, that can be also used for other purposes. There are cheaper options such as Leica MZ8 or Nikon SMZ-10 or SMZ-2B, to name a few. It is better to use two stereomicroscopes, one for handling the embryos (which does not need to be a very nice one) and another one for the recipient. The one used for the recipient should display a long distance from the stage plate to the objective lense, in order to be able to focus 3-4 cm above the stage plate (where the oviduct will be placed) and still leave some room for the surgeon; most of the stereomicroscopes can do this, but some cannot. |
| Fiber optics ilumination | Dolan Jenner | Fiber lite | To iluminate the surgical area. There are different systems available. |
| Warm stages | American scope | http://store.amscope.com/tcs-100.html | These can be placed over the stage plate of the stereomicroscope. Some modifications (inserting a stick to level the stage) may be needed if it is too short for the stereomicroscope. A big warm stage can be used for warming the cage if it is available. If not, a regular heating pad can be used, but temperature must be checked. |
| Culture dishes for embryo manipulation | Falcon | 353001 | 351008 may be also used; they made narrower drops. |
References
- Fernandez-Gonzalez, R., et al. Long-term effect of in vitro culture of mouse embryos with serum on mRNA expression of imprinting genes, development, and behavior. Proc. Natl. Acad. Sci USA. 101, 5880-5885 (2004).
- Bermejo-Alvarez, P., Roberts, R. M., Rosenfeld, C. S. Effect of glucose concentration during in vitro culture of mouse embryos on development to blastocyst, success of embryo transfer, and litter sex ratio. 79, 329-336 (2012).
- Tarkowski, A. K. Experiments on the development of isolated blastomers of mouse eggs. Nature. 184, 1286-1287 (1959).
- Whittingham, D. G. Fertilization of mouse eggs in vitro. Nature. 220, 592-593 (1968).
- McLaren, A., Biggers, J. D. Successful development and birth of mice cultivated in vitro as early as early embryos. Nature. 182, 877-878 (1958).
- McLaren, A., Michie, D. Studies on the transfer of fertilized mouse eggs to uterine foster-mothers. I. Factors affecting the implantation and survival of native and transferred eggs. J. Exp. Biol. 33, 394-416 (1956).
- Goto, Y., et al. The fate of embryos transferred into the uterus. J. Assist. Reprod. Gen. 10, 197-201 (1993).
- Nagy, A., Gertsenstein, M., Vintersten, K., Behringer, R. Manipulating the Mouse Embryo: A Laboratory Manual. , Cold Spring Harbor Laboratory Press. Cold Spring Harbor, NY. (2003).
- Chin, H. J., Wang, C. K. Utero-tubal transfer of mouse embryos. Genesis. 30, 77-81 (2001).
- Ramirez, M. A., Fernandez-Gonzalez, R., Perez-Crespo, M., Pericuesta, E., Gutierrez-Adan, A. Effect of stem cell activation, culture media of manipulated embryos, and site of embryo transfer in the production of F0 embryonic stem cell mice. Biol. Reprod. 80, 1216-1222 (2009).
- Miller, A. M., Wright-Williams, S. L., Flecknell, P. A., Roughan, J. V. A comparison of abdominal and scrotal approach methods of vasectomy and the influence of analgesic treatment in laboratory mice. Lab. Anim. 46, 304-310 (2012).
- Flecknell, P. A. Laboratory Animal Anaesthesia. , Academic Press. Oxford, UK. (2009).
- Erhardt, W., Hebestedt, A., Aschenbrenner, G., Pichotka, B., Blumel, G. A comparative study with various anesthetics in mice (pentobarbitone ketamine-xylazine,carfentanyl-etomidate). Res. Exp. Med. 184, 159-169 (1984).
- Tarin, D., Sturdee, A. Surgical anaesthesia of mice: evaluation of tribromo-ethanol, ether, halothane and methoxyflurane and development of a reliable technique. Lab. Anim. 6, 79-84 (1972).
- Zeller, W., Meier, G., Burki, K., Panoussis, B. Adverse effects of tribromoethanol as used in the production of transgenic mice. Lab. Anim. 32, 407-413 (1998).
- Lieggi, C. C., et al. Efficacy and safety of stored and newly prepared tribromoethanol in ICR mice. Contemp. Top. Lab. Anim. Sci. 44, 17-22 (2005).
- Lieggi, C. C., et al. An evaluation of preparation methods and storage conditions of tribromoethanol. Contemp. Top. Lab. Anim. Sci. 44, 11-16 (2005).
- Meyer, R. E., Fish, R. E. A review of tribromoethanol anesthesia for production of genetically engineered mice and rats. Lab. Anim. 34, 47-52 (2005).
- Chatot, C. L., Lewis, J. L., Torres, I., Ziomek, C. A. Development of 1-cell embryos from different strains of mice in CZB medium. Biol. Reprod. 42, 432-440 (1990).
- Quinn, P., Barros, C., Whittingham, D. G. Preservation of hamster oocytes to assay the fertilizing capacity of human spermatozoa. J. Reprod. Fertil. 66, 161-168 (1982).
- Dios Hourcade, de, Perez-Crespo, J., Serrano, M., Gutierrez-Adan, A., A,, Pintado, B. In vitro and in vivo development of mice morulae after storage in non-frozen conditions. Reprod. Biol. Endocrinol. 10, 62 (2012).
Reprints and Permissions
