This protocol presents a step-by-step guide for researchers to perform the middle cerebral artery occlusion procedure on mice using the modified Longa external carotid artery method. Modifications presented in this article aim to increase the accuracy of middle cerebral artery occlusion and ensure complete reperfusion.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
Optimization of the Longa Middle Cerebral Artery Occlusion Method for Complete Reperfusion
In This Article
Summary
Abstract
The middle cerebral artery occlusion model serves as the primary animal model for studying ischemic stroke. Despite being used in research for over three decades, its standardization remains inadequate. Predominantly conducted on rats and mice, the procedure poses challenges due to mice's smaller and more fragile nature. Unlike the Koizumi common carotid artery method, the Longa external carotid artery is the sole intraluminal filament stroke model ensuring complete reperfusion post-ischemia. This aspect holds critical significance for studies investigating reperfusion phenomena. The surgical modifications demonstrated in this article ensure continuous blood flow from the common carotid artery throughout the ischemic phase and after the reperfusion onset. The goal of these modifications is to selectively occlude the middle cerebral artery by keeping the perfusion uninterrupted in branches proximal to the middle cerebral artery during the ischemia period. Furthermore, the onset of reperfusion is sudden and can be precisely controlled, thereby modeling endovascular thrombectomy in human medicine more accurately. Our aim in presenting this comprehensive video article is to ease the training of new surgeons and promote the standardization of surgical procedures within the scientific community.
Introduction
Stroke ranks as the second leading cause of death and the third leading cause of death and disability combined1. By its cause, stroke can be ischemic or hemorrhagic, with ischemic stroke being significantly more prevalent in clinical practice. Ischemic stroke arises from a blockage in an artery supplying blood to brain tissue, leading to ischemia, cell death, and inflammation. Since the advent of reperfusion therapies such as thrombolysis and mechanical thrombectomy, a great advancement has been made in the treatment of stroke. However, all reperfusion therapies carry the risk of exacerbating the patient's condition by causing what is commonly referred to as reperfusion injury2. The exact mechanism of reperfusion injury remains unclear, and it is up to preclinical studies to identify potential causes and preventive measures. For that purpose, developing a pertinent animal model for reperfusion injury that follows ischemic stroke becomes crucial.
Middle cerebral artery occlusion (MCAO) is the most commonly used animal model for studying ischemic stroke. It is predominantly conducted in rodents and has many different variants described in scientific literature so far3,4. The two main types, Koizumi and Longa, known as common carotid artery (CCA) and external carotid artery (ECA) variants, technically differ by the arteriotomy site for filament insertion5,6. In our recent article, by in vivo monitoring of vascular perfusion, we showed that only the Longa method can be truly considered a brain ischemia/reperfusion model7. The procedure involves inserting the filament into the ECA, advancing it through the ICA, and securing it at the branching point of the middle cerebral artery (MCA) to induce brain tissue ischemia. Following a predetermined period of ischemia, withdrawal of the filament permits reperfusion, simulating transient brain ischemia. After the stroke onset, the primary outcome variable used in research is most often the volume of the infarcted lesion, which can be measured either using ex vivo histology or in vivo brain scans. Challenges in MCAO models revolve around low reproducibility attributed to inter-variant, inter-operator, and inter-subject variances, with the latter posing a significant limitation in preclinical stroke research4.
Moreover, infarcted regions following MCAO in rodents are massive relative to the size of the rodent brain. In addition, hippocampal posterior regions of the brain often get recruited into the infarct volume despite those regions being primarily dependent on blood flow from the posterior cerebral artery (PCA), and not MCA8. As in both Koizumi and Longa methods described in the literature, the CCA is kept ligated during the ischemia period due to the incomplete patency of the Willis circle in mice, leading to ischemia induction in a much wider region than intended5,6,9. Even in methods where the CCA is reopened or repaired after the ischemia period, the usual 30-60 min of ischemia results in irreversible tissue injury in non-MCA regions10. Furthermore, contrary to expectations, previous research showed the length of the silicon coating of a filament has no impact on the lesion size11. However, the choice of the filament's silicon coating length was addressed solely in models with ligated CCA during the occlusion period.
The goal of this method was to modify the Longa MCAO method in mice to enable uninterrupted blood flow from the CCA during the ischemia period, thereby increasing the selectivity of MCAO, as well as ensuring complete reperfusion of the infarcted region after the procedure. These modifications would greatly benefit longitudinal studies researching ischemia-reperfusion injury in mice by lowering the mortality rate and reducing the inter-subject variance.
Access restricted. Please log in or start a trial to view this content.
Protocol
All animal handling and procedures were approved by the Ethics Licensing Committee of the University of Zagreb School of Medicine and the Ethics Committee for the protection of animals used for scientific purposes of the Ministry of Agriculture of the Republic of Croatia. Experimental procedures were conducted according to Croatian Animal Protection Act (NN 102/17, 32/19), Amendments to the Animal Protection Act (NN 37/13) and the Guidelines on the Protection of Animals Used for Scientific Purposes (NN 55/13) which are in line with the European Guide for the Care and Use of Laboratory Animals (Directive 2010/63/EU).
1. Preparation of the animal and the surgical site
- Place the animal in a knock-out box and induce anesthesia using 5% volume of isoflurane in an oxygen/nitrogen mixture (1:2 ratio).
- After visually inspecting the animal's consciousness status and breathing frequency, bring it to a laboratory scale and weigh it.
- Check the reflex by pinching the interdigital skin of a lower limb to ensure proper anesthesia depth.
- Position the animal on the heated operating table and bring its nose into the anesthesia mask. Set the initial operating table temperature to 36 °C and adjust it to keep the animal's body temperature at 37 °C (measured via a rectal probe introduced in later steps). Throughout all further steps, adjust the volume fraction of isoflurane to keep the respiratory rate of the animal at 100 breaths/min.
NOTE: All surfaces and materials in direct contact with the animal must be disinfected thoroughly before the procedure. - Apply eye ointment to the animal's eyes to protect them from dehydration and isoflurane gas.
- Turn the animal on its back and extend its neck by placing a small pillow made of surgical tape beneath it.
- Secure the animal's limbs in place using surgical tape. Take care not to extend the forelimbs too much so as not to cause shoulder joint dislocation inadvertently.
- Lubricate the rectal probe using petroleum white jelly and insert it into the rectum for continuous body temperature measurement. Secure the probe in place together with the tail using surgical tape.
- Apply a preoperative injection of saline and buprenorphine (0.5 mg/kg) intraperitoneally to keep the animal well hydrated and under analgesia during the procedure.
- Shave the animal's fur in the neck region using a cordless animal clipper. Collect all shaven fur using pieces of surgical tape. Additionally, shave the region with a razor to make it completely free of fur.
- Choose an MCAO filament based on the measured animal's weight and/or age. Bring it out of its container and put it in a Petri dish in a visible place. Put a drop of saline on the silicone part of the filament to keep it clean and dust-free.
NOTE: The thickness of the filament's silicone coating should be chosen according to the manufacturer's official recommendations in the case of a 12-16-week-old mouse. Additionally, the length of the silicone coating should be carefully planned in advance, depending on the size of the irrigation area that is to be occluded (see Discussion). - Place a clean surgical drape over the operating table.
- Apply a drop of Betadine to the animal's shaven skin. Use a cotton swab to rub the disinfectant into the skin in a circular fashion from the inside out. Afterward, do the same with an ethanol-soaked cotton swab. Repeat this step 3 times with a fresh pair of sterile cotton swabs for each repetition.
- Apply a dab of lidocaine gel to the disinfected region of the future incision site for local wound analgesia.
2. Ischemia induction surgery
- Make an initial incision on the disinfected skin using a scalpel. Keep the number of skin incision strokes at a minimum to make the surgical wound heal easier.
NOTE: All instruments must have been previously sterilized. The reader should refer to their institutional guidelines for using sterile or surgical gloves. - Using type 7 and 5 forceps, tear away the superficial fascia and detach the salivary glands from the underlying tissue.
NOTE: Always advance with closed forceps and extend it while moving away to push the tissue away. This way, anatomical spaces can be traversed with minimal tissue trauma. - Place the wire retractor in its initial position while ensuring the salivary glands don't interfere with subsequent steps.
- Remove the deep neck fascia using Type 7 forceps and detach sternocleidomastoid muscles from the carotid region to reposition the retractor.
- Reposition the retractor to reach under the sternocleidomastoid muscles to enable access to the carotid region.
- Resect the omohyoid muscle to allow for a clear visual and easier approach to the carotid region.
- Free the carotid artery and its branches from the carotid vein and the vagus nerve, which are held together in the carotid fascia.
NOTE: This fascia must be removed carefully to avoid injuring the vagus nerve or causing any significant bleeding.- Pinch the carotid fascia on the lateral side of the carotid triad and gently pull it laterally to visually identify the artery, nerve, vein, and all the surrounding blood vessel branches.
- While pulling on the fascia laterally, using Type 5 forceps, separate the CCA from the adjacent nerve and vein up to the branching point and the superior thyroid vein, which crosses over the CCA.
- Completely detach the lower part of CCA from underlying tissue and fascia, using curved Type 7 forceps, making sure it is ready for clamping in future steps.
- Proceeding cranially in the region above the CCA branching point, tear open the carotid fascia using two forceps.
- Similarly, pull the loose end of the carotid fascia medially and laterally to precisely detach the ECA and internal carotid artery (ICA) from the fascia and surrounding tissue, respectively.
- Set the ECA and ICA free from the underlying tissue using curved Type 7 forceps.
- With the CCA carefully prepared with its two respective branches, raise the ECA using curved type 7 forceps and clamp it with type N0 self-closing forceps.
- Lower the type N0 self-closing forceps carefully on the operating table.
NOTE: To reposition the clamping point of ECA, it is sometimes necessary to release the grip slightly and push the ECA branching point caudally. At this point, it's important to ensure that more than 1 mm of ECA remains between the ECA clamping and the branching point. - With the ECA clamped and held securely with type N0 tweezers, introduce two braided silk threads behind the ECA.
NOTE: The cranial thread will make for the ligation knot and must be placed cranially from the clamping site. - Tie down the cranial thread completely, as it is permanent, and clip the excess thread away using scissors.
- Tie the caudal thread into a loose securing knot.
NOTE: It must be put close to the ECA branching point and kept loose for the MCAO filament to pass through. - Using vascular microclips, clamp the CCA and the ICA shut to prevent bleeding after the arteriotomy.
NOTE: It is crucial to ensure that the microclip applied to the CCA has a strong enough grip as the CCA is a pulsating high-throughput artery, and failure to do so can result in profuse bleeding and death of the animal in the later steps. - Using micro-spring scissors, make a small arteriotomy right beneath the ECA clamping site.
NOTE: The arteriotomy needs to be large enough for the silicon part of the filament to go in but not larger than half of the ECA circumference in order not to compromise the tension kept by the type N0 forceps. - With an angle matching that of the ECA, insert the filament into the arteriotomy site in a proximal direction to the CCA, passing through the loose securing knot at the branching site of the ECA and sticking into the lumen of the CCA with the filament.
- Tighten down the securing knot around the silicon part of the filament.
NOTE: Great care is needed at this point as the filament tends to slip out of the ECA halfway through the last maneuver, and putting it back in at that point is very hard. - Carefully open the ICA micro clip and remove it.
- With the filament partially inserted into ECA and secured down, make a complete arteriotomy thereby setting the ECA stump loose with the MCAO filament inside. At this point, release the type N0 self-closing forceps and remove it.
- With one set of type 5 tweezers, firmly pinch the ECA stump and raise it slightly. While holding onto the partially inserted filament with another forceps, lower and gently pull the ECA stump to orient the inner end of the filament towards the ICA. Never pinch the silicone part of the filament.
- With forceps holding onto the filament, slowly advance the filament through the ICA towards the circle of Wills.
NOTE: The first branching point of the ICA is also the only one where the operator can miss the desired MCA branching point. Therefore, a slight lateral angle of advancement is necessary to guide the filament to the MCA branching point. With the slight lateral angle of advancement, the filament curves away from the pterygopalatine artery (PPA) and makes the advancing end more likely to enter the circle of Willis (Figure 1).
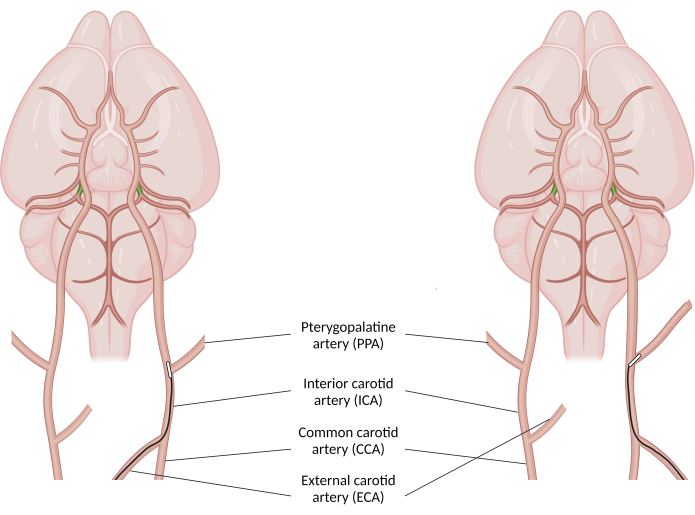
Figure 1: An illustration of middle cerebral artery occlusion filament advancement past the pterygopalatine artery branching point. Proper filament advancement (on the left) is achieved by orienting the MCAO filament in such a way that it backs against the lateral wall of the ICA and curves away from the PPA branching point. Failure to do so (on the right) can result in filament entering the PPA and not causing stroke. In the latter case, the filament won't be able to advance as far as it should and the surgeon should withdraw the filament until its end becomes visible at the ICA branching point and begin to advance the filament again. Green-colored arteries represent posterior communicating arteries (PcomA), mostly non-patent in mice. Created with BioRender.com. Please click here to view a larger version of this figure.
- Slowly advance the MCAO filament through the circle of Willis until a sudden increase in resistance is felt.
NOTE: At this point, it is important to observe the remaining length of the filament. The filament should proceed effortlessly at least 7 mm from the ICA branching point in an adult mouse. - Tighten the securing knot to ensure the filament is not displaced during ischemia.
- Remove the CCA clip and take note of the time.
NOTE: This marks the beginning of the ischemia onset. - Pack the loose end of the MCAO filament in the groove between the carotid triangle and the ipsilateral sternocleidomastoid muscle so it doesn't protrude out of the surgical wound.
- Remove the wire retractor and bring the edges of the surgical wound closer to each other. Let the surgical site settle for a few seconds for the tissue to return to its anatomical position.
- Close the surgical wound using tape wound closures to facilitate faster reopening of the wound after the ischemia period.
NOTE: If a researcher wishes to let the animal awaken during the ischemia period, suturing the wound is recommended to prevent untimely reopening of the wound.
3. Ischemia period
- Validate the success of the surgery using MRI or some other quantitative perfusion measuring method.
NOTE: In case of doing an MRI scan, perfusion-weighted imaging (PWI) should show critical ischemia in the wide MCA region and diffusion-weighted imaging (DWI) should outline the site of reduced apparent diffusion coefficient (ADC) due to cell edema. - Place the animal into a clean cage until the ischemia period ends.
4. Filament withdrawal surgery
- Roughly 5 min before the allotted ischemia time ends, position the animal and secure it on the operating table again.
- Remove the tape wound closures and reopen the surgical wound with the wire retractor.
- Free the loose end of the MCAO filament from surrounding tissue and the ends of the securing knot thread.
- With type N0 forceps, pinch and pull the edge of the ECA stump ventrally to put tension on it. Carefully lower the pinching forceps down, similar to the first surgical procedure.
NOTE: The operator must avoid pinching the securing knot, as that will make the knot unable to untie. - Clamp the CCA again with a microvascular clip.
- Using type 5 forceps, loosen up the securing knot to enable filament withdrawal.
NOTE: The best way to start loosening the knot is to keep pinching it until it separates into individual parts and then push the thread ends toward the knot. - Slowly withdraw the MCAO filament until the silicon part starts to stick out of the ECA stump. Tighten down the securing knot slightly to prepare for complete filament withdrawal.
- When close to the silicon end of the filament, tighten the securing knot so that it pushes out the MCAO filament and closes the ECA stump in a single maneuver. Tighten the knot completely after the filament slips out.
- Open and remove the pinching forceps together with the CCA clip.
NOTE: This marks the end of the ischemia period and the start of the reperfusion process. - Remove the wire retractor and bring the edges of the surgical wound together again.
- Suture down the surgical wound starting from the periphery, closing the wound completely without any underlying tissue visible.
NOTE: The number of sutures required depends on the size of the surgical wound. - Clean and disinfect the surgical site using rubbing alcohol wipes.
5. Postsurgical care
- Place the animal in a clean cage and allow it to awake spontaneously from anesthesia.
- Place pelleted food on the bottom of the cage for easier reach. Soften the food pellets using drinking water. Fill a small Petri dish with drinking water and bring it to the floor of the cage as well.
- In the next 48 h, inject 0.25 mL saline with buprenorphine (0.5 mg/kg) every 24 h intraperitoneally.
Access restricted. Please log in or start a trial to view this content.
Results
Intraoperative or postoperative MRI scans, specifically perfusion-weighted imaging (PWI) and/or diffusion weighted imaging (DWI) scans (Figure 2) can offer definitive proof of a successful procedure. Intraoperative PWI shows critical ischemia in the ipsilateral MCA region thus confirming that the filament placement resulted in complete occlusion. Postoperative PWI of a successful procedure displays hyperperfusion at the lesion core, as well as some degree of reperfusion at the MCA region bor...
Access restricted. Please log in or start a trial to view this content.
Discussion
MCAO is a highly demanding procedure for the operator and a debilitating one for the animal. For this reason, it is of utmost importance for researchers to have a standard operating procedure that minimizes stroke severity, reduces procedural failure, and improves the well-being of the animal post-procedure. This MCAO protocol highlights some of the key aspects of consideration when conducting this procedure on a mouse.
The choice of the MCAO filament influences the size and location of the i...
Access restricted. Please log in or start a trial to view this content.
Disclosures
Authors have no conflicts of interest to disclose. Authors have no affiliation with commercial names and trademarks mentioned in this work.
Acknowledgements
This work was funded by the Croatian Science Foundation project BRADISCHEMIA (UIP-2017-05-8082); GA KK01.1.1.01.0007 funded by the European Union through the European Regional Development Fund and by the European Union through the European Regional development Fund under Grant Agreement No. KK.01.1.1.07.0071, project "SineMozak. The work of doctoral students Rok Ister and Marta Pongrac has been fully supported by the "Young researchers' career development project - training of doctoral students" of the Croatian Science Foundation funded by the European Union from the European Social Fund. The procedure was filmed using an Android smartphone mounted to a surgical microscope using a generic camera mount. Video materials were edited, and voiceover was recorded using the Wondershare Filmora video editor.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Betadine cutaneous solution 10g/100ml | Alkaloid Skopje | N/A | |
| Braided silk suture | Fine Science Tools | 18020-60 | |
| Dafilon suture 5/0 DS16 | B. Braun | C0936154 | |
| Dolokain 20 mg/g gel | Jadran-Galenski Laboratorij | N/A | |
| Dumont #5 forceps | Fine Science Tools | 11251-20 | 2 pieces |
| Dumont #7 forceps | Fine Science Tools | 11271-30 | |
| Dumont N0 self-closing forceps | Fine Science Tools | 11480-11 | |
| Durapore Surgical Tape 1,25cm x 9,1m | 3M | 7100057169 | |
| Durapore Surgical Tape 2,5cm x 9,1m | 3M | 7100057168 | |
| External thermostat | Petnap | 1012536 | |
| Halsey needle holders | Fine Science Tools | 12500-12 | |
| Hot bead sterilizer | Fine Science Tools | 18000-50 | |
| Iris scissors | Fine Science Tools | 14060-10 | |
| Isoflurane USP | Piramal critical care | N/A | |
| Laser Doppler Monitor | Moor | MOORVMS-LDF2 | |
| Metal Pet Heat Pad | Petnap | 1012525 | |
| Micro Vannas spring scissors | Fine Science Tools | 15000-00 | |
| Mini-colibri retractor | Fine Science Tools | 17000-01 | |
| Recugel eye ointment | Bausch&Lomb | N/A | |
| S&T B-1 vessel micro clamp | Fine Science Tools | 00396-01 | 2 pieces |
| S&T micro clamp applying forceps | Fine Science Tools | 00071-14 | |
| Schwartz micro serrefines | Fine Science Tools | 18052-01 | |
| Stemi DV4 Spot stereo microscope | Zeiss | 000000-1018-453 | |
| Steri-Strip Reinforced Adhesive Skin Closures 3 mm x 75 mm | 3M | 7100236545 | |
| Straight tissue forceps | Fine Science Tools | 11023-10 | |
| SZX Stand Arm | Olympus | SZ2-STS | |
| Tec III 300 series calibrated vaporizer | Vaporizer Sales and Service inc. | N/A | |
| Universal Stand Type 2 | Olympus | SZ2-STU2 | |
| VetFlo Six Channel Anesthesia Stand | Kent Scientific | VetFlo-1225 | Modified for O2/N2 mixing |
References
- Feigin, V. L., et al. regional, and national burden of stroke and its risk factors, 1990-2019: a systematic analysis for the Global Burden of Disease Study 2019. The Lancet. Neurology. 20 (10), 1-26 (2021).
- Bai, J., Lyden, P. D. Revisiting cerebral postischemic reperfusion injury: New insights in understanding reperfusion failure, hemorrhage, and edema. Int J Stroke. 10 (2), 143-152 (2015).
- Sommer, C. J. Ischemic stroke: experimental models and reality. Acta Neuropathol. 133 (2), 245-261 (2017).
- Hill, J. W., Nemoto, E. M. Transient middle cerebral artery occlusion with complete reperfusion in spontaneously hypertensive rats. MethodsX. 1, 283-291 (2014).
- Koizumi, J., Yoshida, Y., Nakazawa, T., Ooneda, G. Experimental studies of ischemic brain edema. Nosotchu. 8 (1), 1-8 (1986).
- Longa, E. Z., Weinstein, P. R., Carlson, S., Cummins, R. Reversible middle cerebral artery occlusion without craniectomy in rats. Stroke. 20 (1), 84-91 (1989).
- Justić, H., et al. Redefining the Koizumi model of mouse cerebral ischemia: A comparative longitudinal study of cerebral and retinal ischemia in the Koizumi and Longa middle cerebral artery occlusion models. J Cereb Blood Flow and Metab. 42 (11), 2080-2094 (2022).
- El Amki, M., et al. Hypothalamic, thalamic and hippocampal lesions in the mouse MCAO model: Potential involvement of deep cerebral arteries. J of Neurosci Methods. 254, 80-85 (2015).
- Engel, O., Kolodziej, S., Dirnagl, U., Prinz, V. Modeling Stroke in Mice - Middle Cerebral Artery Occlusion with the Filament Model. J Vis Exp. (47), e2423(2011).
- Trotman-Lucas, M., Kelly, M. E., Janus, J., Gibson, C. L. Middle cerebral artery occlusion allowing reperfusion via common carotid artery repair in mice. J Vis Exp. (143), e58191(2019).
- Morris, G. P., et al. A comparative study of variables influencing ischemic injury in the longa and koizumi methods of intraluminal filament middle cerebral artery occlusion in mice. PLoS One. 11 (2), e0148503(2016).
- Shimamura, N., Matchett, G., Tsubokawa, T., Ohkuma, H., Zhang, J. Comparison of silicon-coated nylon suture to plain nylon suture in the rat middle cerebral artery occlusion model. J Neurosci Methods. 156 (1-2), 161-165 (2006).
- Guan, Y., et al. Effect of suture properties on stability of middle cerebral artery occlusion evaluated by synchrotron radiation angiography. Stroke. 43 (3), 888-891 (2012).
- Yuan, F., et al. Optimizing suture middle cerebral artery occlusion model in C57BL/6 mice circumvents posterior communicating artery dysplasia. J Neurotrauma. 29 (7), 1499-1505 (2012).
- Kitagawa, K., et al. Cerebral ischemia after bilateral carotid artery occlusion and intraluminal suture occlusion in mice: Evaluation of the patency of the posterior communicating artery. J Cereb Blood Flow and Metab. 18 (5), 570-579 (1998).
- McColl, B. W., Carswell, H. V., McCulloch, J., Horsburgh, K. Extension of cerebral hypoperfusion and ischaemic pathology beyond MCA territory after intraluminal filament occlusion in C57Bl/6J mice. Brain Res. 997 (1), 15-23 (2004).
- Li, Y., et al. Distinctions between the Koizumi and Zea Longa methods for middle cerebral artery occlusion (MCAO) model: a systematic review and meta-analysis of rodent data. Sci Rep. 13 (1), 10247(2023).
- Trueman, R. C., et al. A critical re-examination of the intraluminal filament mcao model: impact of external carotid artery transection. Transl Stroke Res. 2 (4), 651-661 (2011).
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
