This protocol describes the ex vivo normothermic machine perfusion of a rat kidney for subsequent transplantation into a recipient rat.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
Normothermic Machine Perfusion of Rat Kidneys for Transplantation
* These authors contributed equally
In This Article
Summary
Abstract
The normothermic machine perfusion (NMP) technique is a promising organ preservation technology that provides an ex-vivo organ evaluation and intervention platform. Because of the limited availability of clinically discarded organs and the high cost of large animal models, the small animal NMP model has been considered a promising alternative for research. Here, we established a standardized NMP and transplantation protocol for rat kidneys, providing a step-by-step guide for kidney procurement, NMP preservation, and transplantation. The NMP details and parameters were recorded. All rat recipients successfully survived with this surgical procedure and NMP technique, and the renal graft function remained normal after transplantation. The survival rate and graft histology of NMP showed no significant difference from that of static cold storage (SCS) on postoperative day 7. This novel NMP strategy in small animal models may benefit basic studies related to organ preservation, assessment, and intervention in the future. Furthermore, this model offers a cost-effective, scalable platform for preclinical testing of therapeutics, imaging techniques, and perfusion-related interventions.
Introduction
End-stage kidney disease (ESKD) is a rapidly growing burden on health and healthcare systems around the world1,2,3. Although dialysis is the predominant therapy for ESKD in most countries, kidney transplantation remains the gold-standard treatment, providing a better quality of life and improving survival and prognosis compared with dialysis1,3,4,5. However, the shortage of donor kidneys limits the further dissemination of kidney transplantation and leads to the increasing use of grafts donated after circulatory death (DCD) or retrieved from extended criteria donors (ECD)6,7,8.
Static cold storage (SCS) is currently the standard method for organ preservation, but prolonged cold ischemia increases the risk of delayed graft function (DGF) and provokes acute and chronic rejection, especially in DCD or ECD grafts9,10,11,12. Therefore, searching for an organ preservation method to minimize cold ischemia damage and enhance graft prognosis is crucial. Normothermic machine perfusion (NMP) is an emerging technique for organ preservation that can mimic physiological conditions by circulating the warmed and oxygenated perfusate through the organ12,13,14,15. This can also maintain a near-physiological metabolic state, making it possible to assess organ viability, ameliorate cold ischemic injury, and even repair organ damage16,17,18,19,20. Compared with SCS, NMP results in a reduced percentage of DGF and a better graft prognosis in both DCD and ECD grafts17,21,22.
The porcine kidneys and clinical human discarded kidneys are currently used in basic NMP research20,23,24. Nevertheless, it should be noted that porcine models face significant limitations, including high husbandry costs, large drug dosage requirements, and scarcity of species-specific reagents25. Moreover, the use of discarded human organs entails limited availability and complex ethical review processes. These constraints collectively restrict their widespread application in basic research. In contrast, rodent small animal models (particularly rat models), though currently underrepresented in the literature, offer substantially lower operational costs and abundant commercially available reagents. These advantages position them as promising platforms for advancing foundational studies26,27,28. Based on this rationale, we developed and validated a rat-based NMP and transplantation model in this manuscript.
This paper shows a detailed protocol for establishing NMP and transplantation in rat kidneys. It includes the preparation of the perfusate and the perfusion system, and a comprehensive description of the surgical procedure for both donor and recipient kidneys. This model demonstrates the potential to be an ideal animal model for studying renal transplantation, particularly as a platform for processing and monitoring the efficacy of relevant medicines19,29,30,31.
Access restricted. Please log in or start a trial to view this content.
Protocol
Animal protocols were approved by the Animal Care and Use Committee of the Laboratory Animal Center of Sun Yat-sen University (No. SYSU-IACUC-2023-000717). All animals in this study were male Sprague–Dawley rats aged 7–8 weeks (250–300 g), Specific Pathogen-Free (SPF), and met the standard requirements for laboratory animal safety (see the pathogen exclusion list in Supplemental Table S1). They were fed a standard diet and housed in a pathogen-free room at the Laboratory Animal Center of Sun Yat-sen University.
Sterilize all surgical instruments via autoclaving (121 °C, 30 min) before experiments. Utilize exclusively single-use sterile consumables throughout procedures and adhere strictly to aseptic protocols during all operations.
1. Preparation of basic perfusate
- Combine 2.5 g of bovine serum albumin (BSA), 50 mL of RPMI 1640, 2% penicillin-streptomycin, and 0.6 mg of creatinine to prepare the basic perfusate (Supplemental Table S2).
- Add 5% sodium bicarbonate solution (0.5-1.2 mL) to adjust the pH to ~7.3 and base excess (BE, an important indicator to measure the acid-base balance of the perfusion system) to ~0, achieving a total volume of ~60 mL.
- Filter the solution through a 0.22 µm filter to remove particulates and bacteria.
NOTE: The complete perfusate requires 50 mL of basic perfusate and 10 mL of donor blood (see step 2.13).
2. Kidney procurement
NOTE: Use 8-0 surgical sutures for all ligations.
- Induce anesthesia with 3% isoflurane inan anesthesia chamber and maintain general anesthesia using 1.5% isoflurane throughout the surgical procedure.
- Preparation before surgery.
- Add 20 mL of precooled saline to a Petri dish for preserving the kidney harvested in step 2.12.
- Fill a syringe with 10 mL of cold hypertonic citrate adenine (HCA) solution and 1,250 U of heparin. Connect the syringe with an infusion extension tube and 24 G indwelling needle.
- Select and anesthetize the donor rat with isoflurane. Confirm sufficient anesthesia depth by verifying the absence of rear-foot reflexes.2.3. After induction of anesthesia, use an electric clipper to shave the abdominal hair (range: from the xiphoid process to the pubic symphysis, both sides to the midaxillary line).
- Use the medical tape to fix the rat supine on a surgery board with a heating pad on it. Disinfect the abdominal skin with an iodine-soaked cotton ball, followed by an alcohol-soaked cotton ball for additional antisepsis. Spread the sterile gauze on the disinfected abdominal skin.
- Use a scalpel and forceps to make a midline incision from the xiphoid process to the bladder (approximately 8 cm in length). Sequentially open the abdominal skin and muscle layers.
NOTE: Clamp the abdominal wall vessels to prevent bleeding if necessary. - Retract the abdominal wall with a pull hook to expose the surgical field.
- Use the microscope forceps to dissect the connective tissue to isolate the left kidney and ureter.
- Place a ligature (Ligature I) around the left ureter. Dissect the left renal ureter 0.5-1.0 cm distal to the renal hilum and catheterize it with a 26 G tube ~0.5 cm long, then tighten ligature I (Figure 1A,B).
- Separate the left renal vessels. Place ligatures on the renal artery (Ligature II) and renal vein (Ligature III) (Figure 1A,B).
- Sequentially tighten the Ligatures II and III. Dissect the blood vessels and ureter distal to the ligation site. Dissect the perirenal connective tissue and transfer the kidney to the prepared Petri dish.
- Cannulate the left renal artery with the preassembled 24 G indwelling needle. Fix the cannula with a ligature (Ligature IV) and perfuse at a flow rate of 100 mL/h until the kidney turns pale (Figure 1A).
NOTE: Prefill the perfusion tube and indwelling needle with solution to avoid air bubbles. - Place the perfused kidney within the Petri dish on ice until NMP initiation (see step 2.1.1).
NOTE: As for the SCS group, the perfused kidneys were preserved in a 15 mL centrifuge tube with HCA solution at 4 °C for 3 h, whereas the kidneys for the NMP group underwent 3 h perfusion. - Inject 1,250 U of heparin from the abdominal aorta using a 24 G indwelling needle connected with a 20 mL syringe. Then, collect 10 mL of heparinized blood using the indwelling needle described above for the subsequent complete perfusate preparation. Euthanize donor rats by exsanguination under maintained gas anesthesia.
NOTE: The complete perfusate maintains hematocrit (HCT) levels at 6-8%.
3. Preparation of the NMP system and perfusion
- Assemble the perfusion system (Figure 2).
- Set the water bath to maintain the organ chamber at 37 °C. Turn on the 90% O2 gas inflow to oxygenate the animal membrane oxygenator.
- Mix 10 mL of donor blood (Step 2.13) with the basic perfusate (Step 1) in the organ chamber after filtration through a cellular sieve to get the complete perfusate. Leave ~2 mL of the mixture specimen as the baseline sample.
- Turn on the peristaltic pump and initiate perfusion (3 mL/min) and fill the perfusion tube with the mixture. Secure a sterile round yarn over the chamber with clamps.
- After the mixture fills the tube and flows out, connect the kidney (Step 2.12) with the perfusion system and start perfusion. Use a clamp to secure the pipeline (Figure 1A,C).
- Connect the ureter cannula with an extension tube. Collect urine in a microcentrifuge tube during perfusion.
- During perfusion, maintain the perfusion pressure at ~80 mmHg and the kidney's temperature at ~37 °C. Monitor and record the perfusion flow, pressure, and vascular resistance (defined as perfusion pressure divided by perfusion flow).
- Add 1.0 mL of sterile water and oxygenate for 20 s (3 L/min, 90% O2) every 30 min, and collect 1 mL of perfusate and urine produced during every hour for retention of samples, as well as measure the blood gases and blood biochemistry of the perfusate.
- At the end of perfusion, measure the blood biochemistry of the perfusate in order to calculate the fractional excretion (FE) of sodium and potassium. The calculation formulas for the aforementioned indices are as follows:
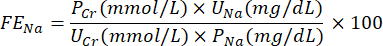
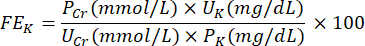
Where PNa represents the sodium concentration in the perfusate. UCr represents the creatinine concentration in the urine. UNa represents the sodium concentration in the urine. PCr represents the creatinine concentration in the perfusate. represents the potassium concentration in the perfusate. UK represents the potassium concentration in the urine.- Monitor the pH during perfusion according to the result of blood gases. Reduce ventilation in the case of respiratory alkalosis (hyperventilation).
- In the case of metabolic acidosis, add an appropriate amount of sodium bicarbonate solution to the perfusate.
- After 3 h of NMP, remove the ureter extension tube and collect the urine sample.
- Remove the kidney from the perfusion system. Connect the indwelling to a micropump. Perfuse the kidney with precooled HCA solution (stored in a refrigerator at 4 °C and only draw the appropriate volume before use) until the kidney turns pale.
- Remove the kidney from the indwelling needle. Store it in HCA solution at 4 °C before transplantation.
4. Rat kidney transplantation
NOTE: Use 8-0 sutures for all ligations and the 11-0 sutures for performing anastomosis of the renal vessel and ureter. Use the 3-0 sutures for performing anastomosis of abdominal skin and muscle.
- One day prior to surgery, inject meloxicam (2mg/kg) into all recipient rats intraperitoneally for analgesia. Induce anesthesia with 3% isoflurane in an anesthesia chamber and maintain general anesthesia using 1.5% isoflurane throughout the surgical procedure. Apply 2% lidocaine spray topically to the abdominal incision site postoperatively for local analgesia.
- Select and anesthetize the recipient rat inthe anesthesia chamber. Confirm sufficient anesthesia depth by verifying the absence of rear-foot reflexes.
- After induction of anesthesia, use an electric clipper to shave the abdominal hair (Range: from the xiphoid process to the pubic symphysis, both sides to the midaxillary line).
- Use the medical tape to fix the rat supine on a surgery board with a heating pad on it. Disinfect the abdominal skin with an iodine-soaked cotton ball, followed by an alcohol-soaked cotton ball for additional antisepsis. Repeat the above disinfection procedure for a total of three times. Spread the sterile gauze on the disinfected abdominal skin.
- Use a scalpel and forceps to make a midline incision from the xiphoid process to the bladder (approximately 8 cm in length). Sequentially open the abdominal skin and muscle layers. Clamp the abdominal wall vessels to prevent bleeding.
- Retract the abdominal wall with a pull hook to expose the surgical field. Isolate and expose the right kidney from connective tissue. Dissociate and ligate the right renal vessels (Ligature V) and ureter (Ligature VI). Excise the right kidney at the distal end of ligature V and the proximal end of ligature VI (Figure 1A,D).
- Isolate and expose the left renal vessels. Then, clamp the left renal artery and vein sequentially with a vascular clamp. Excise the left kidney by cutting the renal vessels and the ureter (Figure 1A,E).
- Completely expose the vascular lumina of both artery and vein. Flush the recipient's left renal artery and vein with heparinized saline (Supplemental Table S2) until there is no residual lumen fluid.
- Transfer the donor's left kidney in Step 3.12 to the recipient's left abdominal cavity. After transferring, apply ice-cold saline irrigation to the kidney every 3-5 min to maintain hypometabolic conditions and mitigate ischemic injury.
- Perform end-to-end anastomosis of renal artery (Anastomosis I) and vein (Anastomosis II) using 11-0 sutures. Irrigate the graft surface with cold saline during the suturing process.
- Make an interrupted closure of both the upper and the lower pole of the renal artery.
- Make a continuous closure of the ventral aspect of the renal artery. Expose the dorsal aspect of the renal artery. Make a continuous closure of the dorsal aspect of the renal artery.
NOTE: Tighten the sutures to make sure there are no gaps in the vessel wall. Ensure full-thickness apposition of the vascular wall with each suture placement while avoiding transmural penetration to the contralateral side. - Make an interrupted closure of both the upper and the lower pole of the renal vein.
- Make a continuous closure of the dorsal aspect of the renal vein. Secure the continuous anastomotic suture before proceeding with the next closure. Make a continuous closure of the ventral aspect of the renal vein.
- Release the vascular clamps and open the renal artery and vein.
NOTE: If there is a small amount of bleeding, use a clean cotton ball to press and stop bleeding. - Insert the 26 G ureteral cannula of the donor's ureter into the recipient's ureter. Secure the ureteral stump on both the right and left sides (Anastomosis III).
- Fix the graft by suturing the connective tissue to the perirenal adipose tissue (Figure 1A,F).
- Check out the appearance of the graft before abdominal closure (Figure 1A,G). After the procedure, suture the abdominal muscle layer and skin layer successively, and close the abdominal cavity. Apply lidocaine spray to the anastomosis. Use a heating pad to maintain the rat's body temperature during recovery and place the rat in a metabolic cage for monitoring once ambulatory.
NOTE: Perform layered closure of the abdominal wall with precise tissue apposition and secure tension in each suture placement. When closing the skin, incorporate a portion of the underlying muscle layer to prevent dead space formation.
5. Perioperative administration and postoperative detection
- Perioperative medication management: The following drugs were administered daily via intraperitoneal injection: Meloxicam at a dose of 2 mg/kg for perioperative analgesia, from 1 day before surgery to 3 days after surgery. Methylprednisolone sodium succinate at a dose of 4 mg/kg for the prevention of allograft rejection, from the day of surgery until postoperative day 7. Monitor and record the survival and daily urine output of the recipient rats after surgery.
- On the seventh postoperative day, anesthetize the rat and collect blood from the abdominal aorta for biochemical measurements. Harvest the renal graft. Euthanize the rats by exsanguination under sustained gas anesthesia after tissue collection.
- Fix kidney samples in 4% paraformaldehyde (PFA) solution, then process them through standard dehydration, clearing, and paraffin embedding (Supplement Table S3). Section the paraffin-embedded blocks at 4 µm thickness. Subsequently, stain with Hematoxylin and Eosin (H&E, Supplement Table S4) and Periodic Acid-Schiff (PAS, Supplement Table S5)) for histological evaluation.
NOTE: The detailed staining procedures are shown in Supplemental Table S3, Supplemental Table S4, and Supplemental Table S5.
Access restricted. Please log in or start a trial to view this content.
Results
With the method described, isolated rat kidneys can remain viable for ex vivo normothermic machine perfusion for at least 3 h. During NMP, the kidneys' perfusion resistance (Figure 3A, the complete underlying dataset of Figure 3 and Figure 4 is available in Supplemental Table S6.) is maintained stably at 5.958 ± 1.106 mmHg/(mL/min), demonstrating the stability of our established perfusion system. The kidney...
Access restricted. Please log in or start a trial to view this content.
Discussion
NMP can reduce the duration of graft ischemia and enable the assessment and treatment of graft quality ex vivo16,17,18,19,20,32,33. However, there is no uniform standard for the NMP of the rat model. In this paper, we developed an animal model for NMP and subsequent transplantation ...
Access restricted. Please log in or start a trial to view this content.
Disclosures
The authors have no conflicts of interest to disclose.
Acknowledgements
This work was supported by funding from the National Natural Science Foundation of China (General Program, Grant No. 82470778); the National Natural Science Foundation of China (Youth Science Foundation Project, Grant No. 82201961); the Natural Science Foundation of Guangdong Province (General Program, Grant No. 2024A1515011447); and the Guangdong Provincial Key Laboratory of Organ Donation and Transplant Immunology (Grant No. 2023B1212060020); the Sun Yat-sen University - ARM Kidney Regeneation & Rebuilding Joint Lab(Grant No. SYSU-50000-20240428-0001).
The authors would like to thank the Laboratory Animal Center of Sun Yat-sen University for providing laboratory animals, premises, and instrumentation. Figure 1 and Figure 2 were prepared using FigDraw; Graphpad Prism offered data graphing services, and Biossci (Hubei) Biotechnologies Company Limited carried out paraffin sectioning and pathological staining.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Alcohol (75 %) | MUSIYAN | JJ-75-1 | |
| Blood transfusion apparatus | Foshan Youzhan Tech Co., Ltd | YZDW-15-5 | |
| Bovine Serum Albumin (BSA) | Aladdin Scientific Corp . | B265991-100g | |
| Cell strainer (70 μm) | Corning Life Science(Wujiang) Co., Ltd | 352350 | |
| Centrifuge tube (1.5 mL) | Corning Life Science(Wujiang) Co., Ltd | MCT-150-C- 1 | |
| Centrifuge tube (15 mL) | ExCell Bio | CS015-0001 | |
| Cotton ball | Henan PiaoAn Group Co., Ltd | Small size | |
| Cotton swab | Foshan Shunde Kangzheng Sanitary Material Co., Ltd | KZ3-12 | |
| Creatinine | Shanghai yuanye Bio-Technology Co., Ltd | S20198-100g | |
| Double circular needle nylon suture (11-0) | Ningbo Medical Needle Co., Ltd | SYZ-11-0 | |
| Electronic scale | SENSSUN | EHA17 | |
| Fluid dispenser | Zhiyu Medical | YZ-00-0231 | |
| Gauze | ZITTAR | C11001-001 | |
| Heating pad | Guangzhou Dewei Biological Technology Co., Ltd | DK0032 | |
| Heparin Sodium Injection (12500 U, 2 mL) | Chengdu Hepatunn Pharmaceutical Co., Ltd | H51021209 | |
| Infrared thermometer | Deli | DL333380 | |
| Injection syringe (1 mL) | Winner Medical (Human) Co, Ltd. | ZT-ZS 1ml | |
| Injection syringe (10 mL) | Winner Medical (Human) Co, Ltd. | ZT-ZS 10ml | |
| Injection syringe (20 mL) | Winner Medical (Human) Co, Ltd. | ZT-ZS 20ml | |
| Isoflurane | RWD Life Science Co., LTD | R510-22-10 | |
| i-STAT 1 blood analyzer | Abbott | 04P75-03 (US) | |
| i-STAT CG4+ Cartridge | Abbott | 03P85-25 | |
| i-STAT CHEM8+ Cartridge | Abbott | 09P31-25 | |
| Liquid extension tube | Jiangxi Hongda Medical Equipment Group LTD | ZJ983 | |
| Micro-1 Rat Oxygenator | Dongguan Kewei Medical Instrument Co-, Ltd | Micro-MO | |
| Micropump | EDCAPTAIN | SYS-3011 | |
| Needle Filter (0.22 μm) | Merck millipore | SLGPR33RB | |
| Organ preservation solution | Yangtze River Pharmaceutical Group | HCA II | |
| Oxygenator | Owgels | OZ-3-02HWO | |
| Penicillin-Streptomycin (10,000 U/mL) | Thermo Fisher Scientific Inc. | 15140122 | |
| Peristaltic Pump | Kamoer Fluid Tech (Shanghai) Co., Ltd. | LLS Plus V2 | |
| Peristaltic pump tube | Foshan Youzhan Tech Co., Ltd | LG-1-14 | |
| Petri dish | BKMAM | BKM001 | |
| Pressure sensor | Edwards Lifesciences Corporation | JIBPT-A-01-EDW | |
| Pressure Sensor Receiver | Singularity Medical | CB-202309001 | |
| RPMI 1640 (1x, 500 mL) | Corning Life Science(Wujiang) Co., Ltd | R10-040-CV | |
| Saline | YXH PHARMACY | A1001346 | |
| SD rats | Laboratory Animal Center of Sun Yat-Sen University | NA | |
| Shaver | Beyotime | FS600 | |
| Single angle needle nylon suture (3-0) | Ningbo Medical Needle Co., Ltd | DJZ-3-0 | |
| Single circular needle Nylon Suture (8-0) | Ningbo Medical Needle Co., Ltd | DYZ-8-0 | |
| Small animal anesthesia machine | RWD Life Science Co., LTD | R500 | |
| Small Animal multi-organ perfusion machine | Life Perfusor Medical | PU-100 | Include Metal dish, Water bath, Heating pump, and Temperature sensor |
| Small Animal Surgery Kit | Beyotime | FS500 | |
| Sodium bicarbonate solution(NaHCO3, 5 %) | Dongguan Puji Medical Technology Co., Ltd | H20064480 | |
| Sterile Surgical Sheet | HengAo Technology | SKR-BY-DD0001 | |
| Sterile water | Haiwang Bio | H35021140 | |
| Straight-handled I.V. Catheter (24 G) | Foshan Youzhan Tech Co., Ltd | 20230816-1 | |
| Surgical operation microscope | Murzider | MSD203 | |
| Tape | Minnesota Mining and Manufacturing Co,. Ltd | 1527C-0 | |
| Tee Connector | Foshan Youzhan Tech Co., Ltd | WGST-10 | |
| Y-type indwelling I.V. Catheter needle (24 G) | JIANGXI FENGLIN | YZDW-7-5 | |
| Y-type indwelling I.V. Catheter needle (26 G) | JIANGXI FENGLIN | YZDW-7-6 |
References
- Collins, A. J., et al. Excerpts from the US Renal Data System 2009 Annual Data Report. Am J Kidney Dis. 55 (1 Suppl 1), A6-A7 A1-A420 (2010).
- Skorecki, K., Chertow, G. M., Marsden, P. A., Taal, M. W., Yu, A. S. L. Brenner & Rector's The Kidney. , 10th ed, Elsevier. Philadelphia, PA. (2016).
- Thurlow, J., et al. Global epidemiology of end-stage kidney disease and disparities in kidney replacement therapy. Am J Nephrol. 52 (2), 98-107 (2021).
- Schnuelle, P., Lorenz, D., Trede, M., Van Der Woude, F. J. Impact of renal cadaveric transplantation on survival in end-stage renal failure: evidence for reduced mortality risk compared with hemodialysis during long-term follow-up. J Am Soc Nephrol. 9 (11), 2135(1998).
- O'Connell, P. J., et al. The role of kidney transplantation as a component of integrated care for chronic kidney disease. Kidney Int Suppl (2011). 10 (1), e78-e85 (2020).
- Wu, D. A., Watson, C. J., Bradley, J. A., Johnson, R. J., Forsythe, J. L., Oniscu, G. C. Global trends and challenges in deceased donor kidney allocation. Kidney Int. 91 (6), 1287-1299 (2017).
- Fang, X., et al. Long-term outcomes of kidney transplantation from expanded criteria donors with Chinese novel donation policy: donation after citizens' death. BMC Nephrol. 23, 325(2022).
- Gill, J., et al. Use and outcomes of kidneys from donation after circulatory death donors in the United States. J Am Soc Nephrol. 28 (12), 3647-3657 (2017).
- Debout, A., et al. Each additional hour of cold ischemia time significantly increases the risk of graft failure and mortality following renal transplantation. Kidney Int. 87 (2), 343-349 (2015).
- Jing, L., Yao, L., Zhao, M., Peng, L., Liu, M. Organ preservation: from the past to the future. Acta Pharmacol Sin. 39 (5), 845-857 (2018).
- Kvietkauskas, M., Leber, B., Strupas, K., Stiegler, P., Schemmer, P. Machine perfusion of extended criteria donor organs: immunological aspects. Front Immunol. 11, 192(2020).
- Hosgood, S. A., Brown, R. J., Nicholson, M. L. Advances in kidney preservation techniques and their application in clinical practice. Transplantation. 105 (11), e202-e214 (2021).
- Hosgood, S. A., Nicholson, M. L. First in man renal transplantation after ex vivo normothermic perfusion. Transplantation. 92 (7), 735-738 (2011).
- Radajewska, A., Krzywonos-Zawadzka, A., Bil-Lula, I. Recent methods of kidney storage and therapeutic possibilities of transplant kidney. Biomedicines. 10 (5), 1013(2022).
- Bellini, M. I., et al. Organ reconditioning and machine perfusion in transplantation. Transpl Int. 36, 11100(2023).
- Hosgood, S. A., Barlow, A. D., Dormer, J., Nicholson, M. L. The use of ex vivo normothermic perfusion for the resuscitation and assessment of human kidneys discarded because of inadequate in situ perfusion. J Transl Med. 13, 329(2015).
- Georgiades, F., Hosgood, S. A., Butler, A. J., Nicholson, M. L. Use of ex vivo normothermic machine perfusion after normothermic regional perfusion to salvage a poorly perfused DCD kidney. Am J Transplant. 19 (12), 3415-3419 (2019).
- He, X., et al. The first case of ischemia-free kidney transplantation in humans. Front Med (Lausanne). 6, 276(2019).
- López-Martínez, S., Simón, C., Santamaria, X. Normothermic machine perfusion systems: where do we go from here. Transplantation. 108 (1), 22(2024).
- Zulpaite, R., et al. Ex vivo kidney machine perfusion: therapeutic potential. Front Med (Lausanne). 8, 808719(2021).
- Elliott, T. R., Nicholson, M. L., Hosgood, S. A. Normothermic kidney perfusion: an overview of protocols and strategies. Am J Transplant. 21 (4), 1382-1390 (2021).
- Hosgood, S. A., et al. Normothermic machine perfusion versus static cold storage in donation after circulatory death kidney transplantation: a randomized controlled trial. Nat Med. 29 (6), 1511-1519 (2023).
- Pool, M. B. F., Hartveld, L., Leuvenink, H. G. D., Moers, C. Normothermic machine perfusion of ischaemically damaged porcine kidneys with autologous, allogeneic porcine and human red blood cells. PLoS One. 15 (3), e0229566(2020).
- Bouari, S., Eryigit, Ö, de Bruin, R. W. F., IJzermans, J. N. M., Minnee, R. C. Optimizing porcine donor kidney preservation with normothermic or hypothermic machine perfusion: a systematic review. Artif Organs. 45 (11), 1308-1316 (2021).
- Wenzel, N., Blasczyk, R., Figueiredo, C. Animal models in allogenic solid organ transplantation. Transplantology. 2 (4), 412-424 (2021).
- Czogalla, J., Schweda, F., Loffing, J. The mouse isolated perfused kidney technique. J Vis Exp. (117), e54712(2016).
- Mahboub, P., et al. The efficacy of HBOC-201 in ex situ gradual rewarming kidney perfusion in a rat model. Artif Organs. 44 (1), 81-90 (2020).
- Czogalla, J., Grahammer, F., Puelles, V. G., Huber, T. B. A protocol for rat kidney normothermic machine perfusion and subsequent transplantation. Artif Organs. 45 (2), 168-174 (2021).
- Thompson, E. R., et al. Novel delivery of cellular therapy to reduce ischemia reperfusion injury in kidney transplantation. Am J Transplant. 21 (4), 1402-1414 (2021).
- Huijink, T. M., et al. Metformin preconditioning and postconditioning to reduce ischemia reperfusion injury in an isolated ex vivo rat and porcine kidney normothermic machine perfusion model. Clin Transl Sci. 14 (1), 222-230 (2021).
- Ferdinand, J. R., et al. Cytokine absorption during human kidney perfusion reduces delayed graft function-associated inflammatory gene signature. Am J Transplant. 21 (6), 2188-2199 (2021).
- Urbanellis, P., et al. Normothermic ex vivo kidney perfusion improves early DCD graft function compared with hypothermic machine perfusion and static cold storage. Transplantation. 104 (5), 947-955 (2020).
- Tingle, S. J., et al. Normothermic and hypothermic machine perfusion preservation versus static cold storage for deceased donor kidney transplantation. Cochrane Database Syst Rev. 7 (7), CD011671(2024).
- Venema, L. H., et al. Effects of oxygen during long-term hypothermic machine perfusion in a porcine model of kidney donation after circulatory death. Transplantation. 103 (10), 2057-2064 (2019).
- Sui, M., et al. A new HC-A II solution for kidney preservation: a multi-center randomized controlled trial in China. Ann Transplant. 19, 614-620 (2014).
- Hamelink, T. L., et al. Renal normothermic machine perfusion: the road toward clinical implementation of a promising pretransplant organ assessment tool. Transplantation. 106 (2), 268(2022).
- Stimmeder, S., Leber, B., Sucher, R., Stiegler, P. Genetic modulation: future trends toward graft optimization during machine perfusion. Transplantation. 108 (3), 614-624 (2024).
- You, H., et al. A rat orthotopic renal transplantation model for renal allograft rejection. J Vis Exp. (180), e63464(2022).
- Shrestha, B., Haylor, J. Review of surgical techniques of experimental renal transplantation in rats. Exp Clin Transplant. 15 (4), 373-380 (2017).
- Ju, C., Xue, L., Cheng, H., Jin, Z. Optimized method to harvest both kidneys from one donor rat for transplantation. BMC Surg. 18, 66(2018).
- Ahmadi, A. R., et al. Orthotopic rat kidney transplantation: a novel and simplified surgical approach. J Vis Exp. (147), e59403(2019).
- Căluşi, T., Sorohan, B., Iordache, A., Purcaru, F. Cold ischemia time as a risk factor for graft dysfunction types in kidney transplant recipients. Chirurgia. 119 (5), 572(2024).
- Gorayeb-Polacchini, F. S., et al. Impact of cold ischemia time on kidney transplant: a mate kidney analysis. Transplant Proc. 52 (5), 1269-1271 (2020).
- Weissenbacher, A., et al. Hemodynamics and metabolic parameters in normothermic kidney preservation are linked with donor factors, perfusate cells, and cytokines. Front Med (Lausanne). 8, 801098(2022).
- Lantinga, V. A., et al. Impact of device variability and protocol differences on kidney function during normothermic machine perfusion: a comparative study using porcine and human kidneys. Artif Organs. 49 (1), 93-107 (2024).
- Fayek, S. A., et al. Ureteral stents are associated with reduced risk of ureteral complications after kidney transplantation: a large single center experience. Transplantation. 93 (3), 304(2012).
- Brubaker, D. K., Lauffenburger, D. A. Translating preclinical models to humans. Science. 367 (6479), 742-743 (2020).
- Mullins, L. J., Conway, B. R., Menzies, R. I., Denby, L., Mullins, J. J. Renal disease pathophysiology and treatment: contributions from the rat. Dis Model Mech. 9 (12), 1419-1433 (2016).
- Gao, S., et al. A rat model of orthotopic kidney transplantation based on nonanastomotic technique. Transplant Proc. 53 (10), 3080-3086 (2021).
- Franzin, R., et al. Renal delivery of pharmacologic agents during machine perfusion to prevent ischaemia-reperfusion injury: from murine model to clinical trials. Front Immunol. 12, 673562(2021).
- Moeckli, B., et al. Evaluation of donor kidneys prior to transplantation: an update of current and emerging methods. Transpl Int. 32 (5), 459-469 (2019).
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
