This study aims to investigate the effects of electroacupuncture on myelin regeneration in a rat model of SCI and to verify whether the Neuregulin1 (NRG1)-ErbB4 signaling pathway plays a role in this process.
Research Article
Neuregulin1-ErbB4 Signaling Involved in Acupuncture Promoting Myelin Regeneration in Spinal Cord Injury Rats
* These authors contributed equally
In This Article
Summary
Abstract
Spinal cord injury (SCI) often results in severe neurological dysfunction, and myelin repair is a critical step in the recovery of neurological function. Electroacupuncture (EA), a therapeutic method that combines traditional acupuncture with electrical stimulation, has been widely applied in the field of nerve repair. However, the specific signaling pathways involved in EA have not been fully elucidated. This study aims to investigate the effects of EA on myelin regeneration in SCI rats and to verify whether the Neuregulin1 (NRG1)-ErbB4 signaling pathway plays a role in this process. SCI rats were induced by aneurysm clip injury at the T10 spinal segment. A polyethylene (PE) catheter was implanted into the vertebral canal between the L5-6 intervertebral spaces and fixed subcutaneously to establish a long-term drug delivery system. Exogenous NRG1 and its antagonist were administered through the PE catheter every other day, with a volume of 20 µL per injection. EA treatment was applied at the Dazhui (GV14) and Mingmen (GV4) acupuncture points every other day, each session lasting 30 min for 4 consecutive weeks. The results showed that EA treatment significantly promoted the expression of myelin basic protein (MBP) in spinal cord tissue and improved hind limb motor function in the rats. Furthermore, exogenous NRG1 produced similar effects to EA. In conclusion, the NRG1-ErbB4 signaling pathway plays an important role in EA-induced myelin regeneration in SCI rats.
Introduction
SCI is a traumatic condition that leads to severe neurological deficits, typically manifested by motor impairment, sensory loss, and autonomic dysfunction, with an annual incidence rate of approximately 40-80 cases per million people globally1,2. Following injury, axonal rupture and myelin loss are the primary pathological features that impede neural signal conduction3. Myelin is formed by oligodendrocytes in the central nervous system (CNS) and Schwann cells in the peripheral nervous system (PNS), and its integrity is crucial for the rapid conduction of nerve impulses4. However, the inflammatory response, oxidative stress, and glial scar formation in the local microenvironment after SCI significantly inhibit myelin regeneration, leading to chronic neurological dysfunction5. At the same time, the death of oligodendrocytes (OLs) after SCI leads to demyelination of axons, a process that develops chronically and persistently. Studies have shown that axonal demyelination in both human and animal models can be effectively repaired through myelin regeneration6. Therefore, exploring strategies to promote myelin repair is one of the key directions in SCI treatment.
Acupuncture, as an ancient traditional medical technique, has been widely applied in clinical practice across multiple countries, including China, Korea, and Japan7,8. EA, which combines traditional acupuncture with electrical stimulation, has been widely adopted in clinical settings. Increasing evidence shows that EA has therapeutic effects on various diseases, particularly in promoting myelin regeneration following spinal cord injury. The selection of acupuncture points is critical during EA treatment, such as GV14 and GV49. GV14 is located below the spinous process of the 7th cervical vertebra, near the midline of the spine, while GV4 is located between the spinous processes of the 2nd and 3rd lumbar vertebrae. Previous studies have shown that inflammatory signaling pathways, oxidative stress, neurotrophic factors, and autophagy play a role in EA-induced myelin repair10,11,12. Furthermore, increasing evidence suggests that specific acupuncture points, such as GV14 and GV4, play an active role in promoting myelin regeneration during EA treatment13,14,15. However, the molecular mechanisms through which EA regulates myelin regeneration after spinal cord injury have not been fully elucidated.
NRG1 is a member of the epidermal growth factor family, and based on its amino-terminal region, it can be classified into six types (I-VI)16. NRG1 and its receptor family, ErbB (ErbB1/2/3/4), play significant roles in the development and repair of the nervous system, including processes such as neuronal migration, differentiation, remyelination, and synaptogenesis. During the development of the PNS, Schwann cells (SCs) proliferate and migrate along the axons of neurons to form myelin, and the NRG1-ErbB4 signaling pathway plays a key role in the maturation of PNS Schwann progenitor cells17,18. Previous studies have shown that the NRG1 signaling pathway is involved in the differentiation of neural stem cells into Schwann cells and promotes myelin repair of neural cells after SCI19. Additionally, one study has shown that following spinal cord injury, the NRG1-ErbB4 signaling pathway promotes the transformation of oligodendrocyte progenitor cells (OPCs) into Schwann-like cells with remyelination potential20. Alex et al. constructed a co-culture system of human induced pluripotent stem cell-derived sensory neurons and rat Schwann cells and found that blocking the NRG1-ErbB signaling pathway with drugs significantly inhibited neuronal myelination, providing direct evidence of this pathway's role in promoting human sensory axon myelination21. Another study has also shown that EA treatment can upregulate the expression of NRG1 in the spinal cord and alleviate inflammatory pain22.
Research on the impact of EA on the NRG1-ErbB4 signaling pathway in SCI is limited, and the underlying mechanisms remain unclear. This study aims to investigate whether EA stimulation at the GV14 and GV4 acupuncture points can regulate NRG1-ErbB4 signal transduction and explore its potential role in promoting myelin regeneration and recovery of neurological function in SCI rats. This is the first study to examine the relationship between the NRG1-ErbB4 signaling pathway and EA-induced myelin regeneration in SCI rats, providing experimental evidence for the development of novel and effective treatment strategies for SCI.
Protocol
All ethical guidelines were adhered to during the experiment to minimize animal suffering. The experimental protocol and design were approved by the Animal Experiment Committee of Kunming Medical University (Approval No. KMMU2021051) and conducted in accordance with the university's animal research guidelines. Adult male Sprague-Dawley rats (8 weeks old, weighing 250-270 g, n = 60) were obtained from Kunming Medical University (Yunnan, China).
Animal preparation
The animals were housed in a controlled environment with constant humidity, a moderate temperature, and a 12 h light/dark cycle. The animals were randomly assigned to 11 groups: Sham operation group (S, n = 6), SCI group (M, n = 6), SCI with EA treatment group (M + EA, n = 6), SCI with NRG-1β treatment group (M + NRG-1β, n = 6), SCI with 5% DMSO solvent group (M + D, n = 6 ), SCI with PD158780 inhibitor and NRG-1β treatment group (M + PD+NRG-1β, n = 6), SCI with PD158780 inhibitor and EA treatment group (M + EA + PD, n = 6), SCI with solvent and EA treatment group (M + EA + D, n = 6), SCI with shRNA and EA treatment group (M + EA + shRNA, n = 6), SCI with lentivirus containing non-targeting shRNA and EA treatment group (M + EA + NC, n = 6), SCI with shRNA treatment group (M + shRNA, n = 6). The current sample size was determined based on our prior experience with similar models and interventions, which have consistently shown significant effects with this number. Furthermore, despite the sample size, we observed statistically robust and significant differences in key outcomes, which strengthens confidence in the reported findings.
SCI rat model
A Yasargil aneurysm clip (titanium, standard closing force of 70 g) was used to establish a rat model of SCI using a clamp-type technique (Figure 1A). The rats were anesthetized with 2% sodium pentobarbital (30 mg/kg, intraperitoneally) and placed on an operating table. A 3-4 cm incision was made in the back skin, followed by layer-by-layer dissection of the subcutaneous tissue and muscle to expose the T9-11 thoracic spinous processes and vertebral arches. A vascular clip was used to remove the T10 thoracic spinous process and vertebral arch, fully exposing the spinal cord. The Yasargil aneurysm clip was positioned vertically over the entire T10 segment and released rapidly after a 60 s dwell time. The model was considered successful if two or more of the following signs were observed: (1) spasmodic tremor of the body, (2) tail-wagging reflex, and (3) visible black pinch marks on the spinal cord. After ensuring adequate hemostasis, the incision was disinfected and sutured. In the sham operation group, the same procedure was performed, except the spinal cord was not clamped. Postoperatively, the rats received normal saline (3 mL, intraperitoneally) for rehydration and penicillin (100,000 units, intraperitoneally) once in the morning and once in the evening for 3 consecutive days to prevent infection. Manual assistance with urination was provided until spontaneous urination was restored (2x daily).
Rat intrathecal tubing and drug delivery
Following the method of Storkson et al.23, a catheter was implanted into the subarachnoid space in rats 1 week prior to SCI model induction. After anesthesia, the rats were fixed on the operating table, and the L5-6 intervertebral space was exposed. A 19G needle was used to vertically penetrate the dura mater and arachnoid membrane. The needle was advanced approximately 1-2 mm, and after breaking through the arachnoid membrane, a sensation of space was felt, followed by the clear flow of cerebrospinal fluid, indicating successful puncture. A PE-10 catheter (polyethylene, inner diameter 0.38 mm, outer diameter 1.09 mm) was inserted into the subarachnoid space along the puncture needle. The catheter was advanced to a length of approximately 3 cm, with the catheter tip positioned near the L3 vertebral body. During insertion, tail flicking and hindlimb twitching were observed in the rats, and cerebrospinal fluid flowed out through the catheter, confirming the catheter's position within the subarachnoid space.
Both NRG-1β and PD158780 were dissolved in dimethyl sulfoxide (DMSO) and subsequently diluted with artificial cerebrospinal fluid (ACSF), ensuring that the final DMSO concentration remained below 0.5%. The final working concentrations were 20 nM for NRG-1β and 20 µM for PD15878024. On the second day post-SCI, rats in the M + NRG-1β group received intrathecal injections of 20 µL of NRG-1β every other day. Rats in the M + EA + PD group were administered 20 µL of PD158780 intrathecally25, 2 h prior to EA treatment.
EA treatment
On the 3rd day post-surgery, rats were fixed on the treatment table for electroacupuncture (EA) therapy at the acupuncture points GV14 and GV4 (Figure 1B). Two acupuncture needles (0.25 mm x 13 mm) were inserted into these points to a depth of 3-4 mm. EA therapy was administered using an electroacupuncture device with a sparse-dense wave pattern (sparse wave at 2 Hz and dense wave at 10 Hz, with a 1:5 frequency ratio)26. The output intensity was set to 5 (approximately 0.5 mA) for 30 min, every other day.
Behavioral assessment
Locomotor function was evaluated using the Basso, Beattie, and Bresnahan (BBB) scale27, which assesses limb movement, gait, coordination, and paw placement at the following time points: 0, 3, 7, 14, 21, and 28 days post-surgery ( Figure 2D) . The BBB scale ranges from 0 (representing complete paralysis) to 21 (indicating normal gait). All assessments were performed independently by two researchers who were blinded to the experimental group assignments.
Sample collection
Following the conclusion of the experiment, anesthetized rats were fixed on a dissection platform for tissue collection. The abdominal cavity was opened to fully expose the diaphragm, which was carefully incised with iris scissors to avoid vascular injury. The rib cage was then cut open along both costal margins to expose the heart, following which a needle was inserted into the left ventricle at the apex and approximately 300-400 mL of pre-chilled PBS was rapidly perfused to clear systemic blood until clear fluid flowed from the right atrium. For molecular protein analysis, perfusion was stopped at this stage, and the spinal column was dissected. After removing adjacent ribs and muscles to expose the vertebrae, the T10 segment was located, and a spinal cord segment approximately 1 cm rostral and caudal to T10 was collected using iris scissors, then snap-frozen in liquid nitrogen and stored at -80 °C. For morphological examination, perfusion was switched to 4% paraformaldehyde after PBS, with successful fixation indicated by muscle contraction and rigidity of the trunk. The same spinal segment was then carefully dissected to preserve tissue architecture and post-fixed in 4% paraformaldehyde at 4 °C for 48 h.
Hematoxylin and eosin staining
The spinal cord paraffin sections were placed in a 60 °C oven for preheating for 30 min. Dewaxing: Xylene I for 15 min followed by Xylene II for 15 min. Rehydration: Treated with 100% ethanol for 2 min, then 95% ethanol for 2 min, next with 80% ethanol for 2 min, followed by 70% ethanol for 2 min, and finally distilled water for 5 min. Hematoxylin staining was done for 7 min, followed by rinsing with distilled water to remove residual staining solution. Differentiation in 1% hydrochloric acid alcohol was carried out for 3 s, followed by rinsing with distilled water to remove residual staining solution. Bluing with 5% ammonia water for 2 min was done, followed by washing off the residual bluing solution. Eosin staining for 30 s was done, followed by rinsing with distilled water to remove residual staining solution. Dehydration of the sections was done with 70% ethanol for 10 s, then 80% ethanol for 10 s, and finally with 100% ethanol for 30 s. Clearing was done by treating with Xylene for 5 min. After mounting, the slides were air-dried, and images were captured after drying.
Luxol fast blue staining
The sections were dewaxed 2x with xylene for 10 min each, then stained with LFB myelin staining solution, and incubated overnight at 37 °C. The following day, excess staining solution was removed using 90% ethanol. The sections were differentiated in Luxol differentiation solution for 10 s (C0631S), followed by immersion in 75% ethanol for 30 s until the gray matter appeared clear. Finally, the sections were counterstained with eosin staining solution for 1 min.
Western blotting
Protein samples were boiled in water for 5 min. A total of 5 µL of protein marker was first loaded into the electrophoresis gel, followed by sequential loading of the test protein samples. Electrophoresis was initiated at 80 V until the marker bands were clearly separated, after which the voltage was increased to 130 V and maintained until electrophoresis was complete. Pre-cut PVDF membranes were activated in methanol for 1 min, then placed on filter paper, and overlaid with the prepared gel. Protein transfer was performed at a constant current of 300 mA, with transfer time adjusted according to molecular weight (± 10 min). After transfer, the PVDF membrane was placed in an incubation box, rinsed with TBST buffer for 5 min, and then blocked with 5% skimmed milk at room temperature on a shaker for 2 h. The membrane was subsequently washed 3x with TBST buffer for 5 min each before incubation with primary antibodies, including GAPDH (1:2000), Tubulin (1:2000), NRG1 (1:1000), ErbB4 (1:1000), and MBP (1:1000), overnight at 4 °C with gentle shaking. On the following day, the membrane was washed 3x with TBST buffer for 5 min each, then incubated with secondary antibody, goat anti-rabbit (1:4000), at room temperature on a shaker for 2 h. After washing with TBST, protein bands were visualized using chemiluminescence. Import the WB image into ImageJ software and perform background subtraction using a rolling ball radius of 50 pixels. For tilted bands, use the Segmented Line tool to straighten the bands. Use the Rectangle tool to select the target bands and generate a density profile by selecting Plot Lanes to visualize the grayscale values of the bands. Use the Magic Wand tool to segment the peaks and extract the grayscale values. After saving the data, use GraphPad Prism software to create bar graphs.
Immunofluorescence
Paraffin sections were dewaxed 2x with xylene for 10 min each and rehydrated through a graded ethanol series. Antigen retrieval was performed by boiling the sections in 5% citric acid solution for 15 min, followed by blocking with 10% goat serum for 2 h. The sections were then incubated overnight at 4 °C with the following primary antibodies: mouse monoclonal NRG-1 (1:200), rabbit monoclonal ErbB4 (1:300), and human monoclonal MBP (1:300). Following three washes with phosphate-buffered saline containing 0.1% Triton X-100 (PBST) for 10 min each, the sections were incubated for 1 h in the dark with the following secondary antibodies: FITC-labeled goat anti-mouse IgG (1:500), FITC-labeled goat anti-rabbit IgG (1:500), and FITC-labeled goat anti-human IgG (1:500). The sections were washed 3x with PBST for 10 min each, then fixed and mounted with antifade reagent to preserve fluorescent signals. The slides were stored at 4 °C in the dark. After locating the target cells under a 10x objective lens using a fluorescence microscope, switch to a 40x lens to capture the fluorescence image.
Real-time Polymerase Chain Reaction (RT-PCR)
Primers for ErbB4 and the reference gene GAPDH were designed using the NCBI website. The sequences of the primers were as follows: ErbB4 forward primer: ACAGCCCTCCTCCTGCCTAC; ErbB4 reverse primer: ATCTCAGCCGTTGCACCCT; GAPDH forward primer: CCCAGCTTAGGTTCATCATCAGGT; GAPDH reverse primer: TACGCCAAATCCGTTCACA. Approximately soybean-sized spinal cord tissue was placed into a 1.5 mL centrifuge tube, and 600 µL of total RNA extraction reagent was added. The tissue was thoroughly homogenized and incubated on ice for 5 min, followed by centrifugation at 12,000 x g for 5 min at 4 °C. The supernatant was transferred to a new 1.5 mL tube, and 400 µL of chloroform was added. The mixture was thoroughly mixed and centrifuged at 12,000 x g for 5 min at 4 °C. The supernatant was transferred again to a new tube, and 400 µL of isopropanol was added. The solution was incubated at room temperature for 10 min, followed by centrifugation at 12,000 x g for 10 min. The supernatant was discarded, and the RNA pellet was washed with 400 µL of 75% ethanol. After centrifugation at 7,500 x g for 5 min at 4 °C, the supernatant was discarded, and the tube was inverted to air-dry on a clean surface. The RNA pellet was dissolved in 60 µL of RNA-free water, mixed thoroughly, and the RNA concentration was measured. The purity and concentration of the RNA were recorded by measuring absorbance at 260 nm and 280 nm, ensuring the 260/280 ratio was around 2.0. For cDNA synthesis, Reaction 1 (containing gDNA Eraser, etc.) and Reaction 2 (containing reverse transcriptase, etc.) were thoroughly mixed, and the mixture was incubated at 95 °C for 15 min. The fluorescence PCR reaction system was prepared according to the cDNA synthesis kit instructions. A 2 µL sample was added to 23 µL of PCR reaction mix, and amplification was performed according to the fluorescence quantitative PCR kit protocol. The annealing temperature was set to 60 °C, and the amplification conditions were as follows: Pre-denaturation: 95 °C for 30 s, 1 cycle; PCR reaction: 95 °C for 3 s, 60 °C for 30 s, 40 cycles; The dissociation curve analysis was performed as follows: 95 °C for 5 s, 60 °C for 30 s, followed by a gradual increase from 60 °C to 95 °C with continuous fluorescence signal acquisition. Ct values were measured and calculated using the Bio-Rad computer software, and relative mRNA levels were determined using the 2-ΔΔCt method.
Safety and handling guidelines
Paraformaldehyde fixation: Use paraformaldehyde exclusively in a well-ventilated fume hood. Always wear appropriate personal protective equipment (PPE), including a mask, gloves, a lab coat, and safety goggles. Store paraformaldehyde solution in a tightly sealed container, away from direct sunlight and heat sources. Dispose of waste paraformaldehyde in accordance with the laboratory safety guidelines of Kunming Medical University by placing it in a hazardous waste container.
DMSO solution: DMSO can be absorbed through the skin and enter the body. Wear appropriate PPE, including gloves and safety goggles, during handling. Store DMSO in a sealed container at room temperature, away from strong oxidizing agents. Dispose of waste DMSO in accordance with the laboratory safety guidelines of Kunming Medical University by placing it in a hazardous waste container.
Pentobarbital anesthesia: Pentobarbital is a controlled substance and should only be handled by authorized personnel. Avoid accidental exposure during handling and ensure proper ventilation while using. Wear appropriate protective equipment. Store pentobarbital in a locked cabinet at room temperature, under the supervision of authorized personnel. Dispose of pentobarbital waste in compliance with Kunming Medical University's guidelines for controlled substances, ensuring proper usage authorization and waste disposal procedures.
General waste disposal: All hazardous chemicals and reagents must be disposed of according to the laboratory management guidelines of Kunming Medical University. Ensure that all waste materials are properly labeled and placed in suitable containers for safe disposal.
Statistical analysis
All experiments were conducted in triplicate or more. The band density values of the target proteins were normalized to those of the control group to facilitate comparisons between groups. Data are presented as median (interquartile range) or mean ± standard deviation, with n representing the number of rats. For normally distributed data, significant differences between groups were assessed using one-way analysis of variance (ANOVA). For non-normally distributed data, the Kruskal-Wallis H test was applied to compare groups. Statistical significance was set at p < 0.05.
Results
H&E staining and BBB scoring demonstrate the protective effects of EA on SCI rats
H&E staining was used to examine the morphology and structure of the posterior horn cells of the spinal cord (Figure 2D). The H&E results revealed that in group S, the posterior horn cells were neatly arranged, with well-defined cell outlines and centrally located nuclei. In contrast, the number of posterior horn cells was reduced in group M, with disorganized cell arrangement, and the formation of vacuoles, glial cell hyperplasia, and spinal cord cavities. Damage and cavitation of the posterior horn morphology were significantly alleviated in the M + EA and M + EA + D groups compared to the M group. However, in the M + EA + PD group, no significant improvement in post-injury cavitation of the posterior horn was observed compared to the M + EA group, with similar morphological damage as seen in the M group.
Recovery of urinary retention in rats after SCI was assessed based on spontaneous urination time. Severe urinary retention was observed in the rats after SCI. The M group regained spontaneous urination after an average of 20 days. In comparison, the M + EA group showed recovery of spontaneous urination in an average of 13 days, which was statistically significant (p < 0.05). Rats in the M + EA + PD group resumed spontaneous urination in an average of 25 days, a significant delay compared to the M + EA group (p < 0.01, Figure 2C).
The BBB score was used to assess hindlimb motor function. Compared with group S, the BBB score in the M group was significantly lower at each postoperative time point (days 1, 3, 7, 14, 21, and 28; p < 0.001). There were no significant differences in BBB scores between the M + EA and M + EA + D groups at days 1, 3, 7, and 14 post-operation (p > 0.05). However, from day 21 onward, the BBB scores in the M + EA and M + EA + D groups were significantly higher than those in the M group (p < 0.05). In contrast, the BBB score in the M + EA + PD group was consistently lower than in the M + EA group at all time points (p < 0.01, Figure 2B). These results suggest that hindlimb motor function showed some degree of self-recovery after SCI, but no significant improvement was noted. However, EA treatment notably promoted recovery of hindlimb motor function in SCI rats.
LFB staining and Western blot demonstrate the promoting effect of electroacupuncture on myelin regeneration in SCI rats
Demyelination in spinal cord neurons was assessed by LFB staining (blue indicates positive expression). Significant demyelination was observed in the M group compared to the S group (p < 0.01, Figure 3A). The degree of demyelination was significantly reduced in the M + EA and M + EA + D groups compared to the M group (p < 0.05). However, the severity of demyelination in the M + EA + PD group was comparable to that in the M group, showing no significant improvement compared to the M + EA group (p < 0.05).
WB analysis revealed a significant decrease in MBP protein expression in spinal cord tissue following SCI. MBP expression was markedly increased in the M + EA and M + EA + D groups compared to the M group. However, PD158780 significantly inhibited the EA-induced upregulation of MBP expression (p < 0.05, Figure 3B,C).
Western blot and immunofluorescence indicate the involvement of ErbB4 receptor in EA-promoted myelin regeneration in SCI rats
To investigate whether NRG1-ErbB4 signaling is involved in EA-promoted myelin regeneration, we intrathecally injected PD158780 following SCI. The expression of ErbB4 protein in spinal cord tissue was assessed at various time points (0.5 h, 2 h, 6 h, and 12 h) after the intrathecal injection of PD158780. WB analysis showed that ErbB4 protein expression began to decrease at 0.5 h, reached a minimum at 2 h, and then gradually increased, returning to baseline levels at 12 h (p < 0.01, Figure 4B,D).
WB analysis demonstrated that the protein levels of NRG-1, ErbB4, and MBP were significantly reduced following SCI. Compared to the M group, the protein expression levels of NRG-1, ErbB4, and MBP were markedly increased in the M + EA and M + EA + D groups (p < 0.05, Figure 3B,C). However, PD158780 inhibited the EA-induced upregulation of ErbB4 and MBP protein expression (p < 0.05, Figure 4C,E).
Furthermore, immunofluorescence analysis revealed that the mean fluorescence intensity of NRG-1- and ErbB4-positive cells in the M group was significantly lower than that in the S group. Compared to the M group, the mean fluorescence intensity of NRG-1- and ErbB4-positive cells in the M + EA and M + EA + D groups was significantly increased (p < 0.05, Figure 4A,F). As an ErbB4 receptor antagonist, PD158780 reduced the mean fluorescence intensity of ErbB4, but did not affect the fluorescence intensity of NRG-1 (p > 0.05, Figure 4H,I).
LFB staining, BBB scoring, and Western blot show that exogenous NRG1 supplementation alleviates myelin loss in SCI rats
To determine whether the upregulation of NRG1 plays a key role in promoting remyelination following SCI, PD158780 was administered intrathecally on the 2nd day after SCI, followed by a subsequent injection of NRG-1β 2 h later. LFB staining revealed significant demyelination in the M group compared to the S group (p < 0.01, Figure 5A). Intrathecal administration of NRG-1β markedly reduced demyelination in the posterior horn of the spinal cord compared to the M group. Regarding motor function, BBB scores in the M + NRG-1β group did not show a significant increase on postoperative days 3 and 7 compared to the M group (p > 0.05); however, a significant improvement was observed on day 14 (p < 0.05, Figure 5B). Notably, the beneficial effects of NRG-1β on remyelination and hindlimb motor function were abolished by PD158780 administration. Consistently, Western blot analysis showed that MBP protein expression was significantly reduced following SCI, whereas MBP levels were markedly elevated in the M + NRG-1β group compared to the M group (Figure 5C). These findings suggest that NRG1 plays a crucial role in regulating remyelination after SCI.
RT-PCR, BBB scoring, and Western blot further confirm the involvement of ErbB4 receptor in the protective effects of EA SCI rats
To further investigate the critical role of the NRG1-ErbB4 signaling pathway in EA-promoted remyelination, we injected a lentivirus into the rat spinal cord. The lentivirus delivered shRNA to knock down the expression of the ErbB4 protein in the spinal cord. At 1 week after injection, an SCI model was established at the site of SCI. As shown in Figure 6, both ErbB4 protein and mRNA expression levels were significantly reduced 1 week after ErbB4 shRNA injection into the rat spinal cord (p < 0.05, Figure 6B,E,F). LFB staining results indicated no significant improvement in demyelination in the M + EA + shRNA group compared with the M + EA and M + EA + NC groups (p < 0.05, Figure 6A,H). Western blotting revealed that MBP protein expression was significantly lower in the M + EA + shRNA group than in the M + EA and M + EA + NC groups (p < 0.05, Figure 6C,G). The BBB score of the M + EA + shRNA group was not significantly different from that of the M group on days 3, 7, and 14 after SCI (p > 0.05, Figure 6D). The BBB scores in the M + EA and M + EA + NC groups significantly increased on day 21 post-surgery (p < 0.05). However, the BBB score of the M + EA + shRNA group was substantially lower than that of the M + EA + NC group (p < 0.05).
In conclusion, this study demonstrates that EA treatment can alleviate spinal cord cavitation and demyelination following spinal cord injury and improve hind limb motor function in SCI rats. Furthermore, the study identifies the NRG-1/ErbB4 signaling pathway as a potential therapeutic mechanism underlying EA-induced myelin regeneration and hind limb motor function recovery in SCI rats.
Data availability:
The raw data for all the figures is provided in Supplementary File 1.
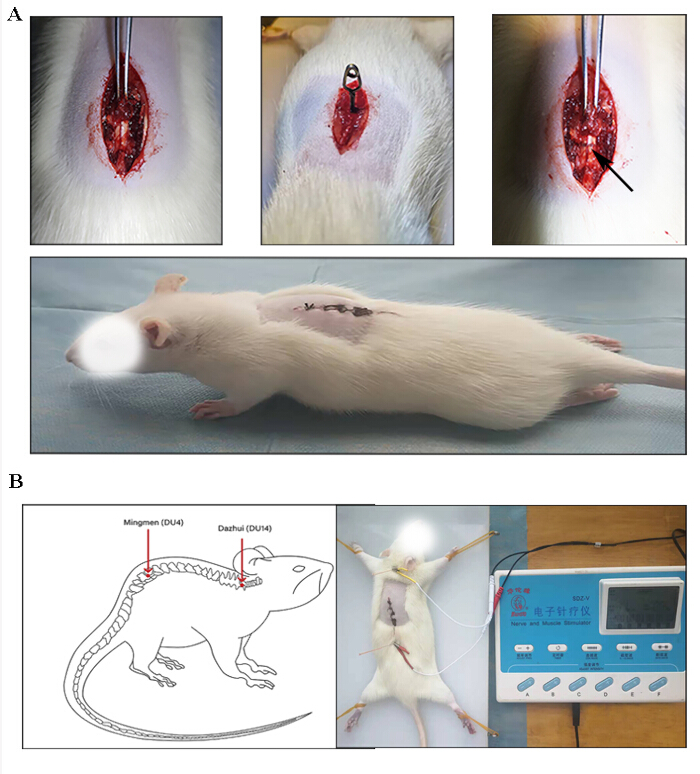
Figure 1: Construction of the SCI rat model and EA treatment. (A) The SCI rat model was established using an aneurysm clip, with the black arrow indicating the site of spinal cord injury. Following the establishment of the model, rats exhibited a loss of motor function in the hind limbs. (B) Electroacupuncture treatment was performed on SCI rats at the GV14 and GV4 acupuncture points using the SDZ-V electroacupuncture device. Please click here to view a larger version of this figure.
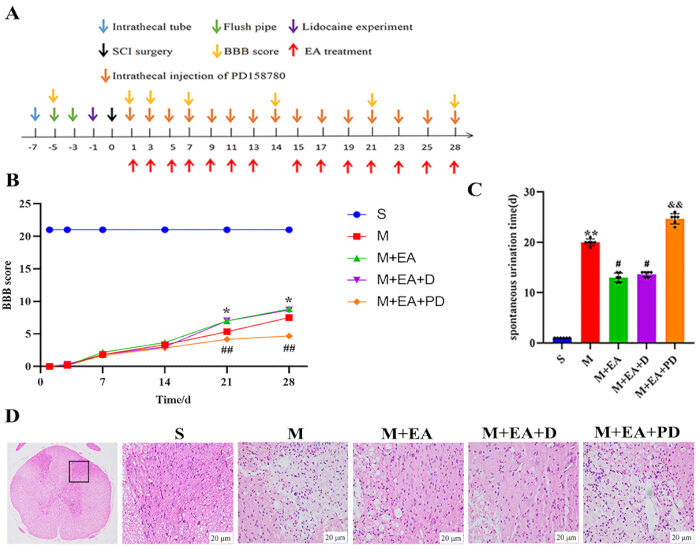
Figure 2: EA alleviates cavitation in spinal cord tissue and improves hind limb motor function and urinary retention in rats. (A) Experimental timeline: Intrathecal catheter implantation was performed one week prior to SCI, followed by injection of the PD158780 blocker and EA treatment 1 day post-SCI. PD158780 was administered 2 h before EA treatment, and the entire experimental protocol lasted 4 weeks. (B) EA improved hind limb motor function in SCI rats, as assessed by the BBB score. Compared with the M group, the M+EA group showed significant improvement in hindlimb function, whereas the M+EA+PD group exhibited no significant improvement. (C) EA treatment reduced the duration of urinary retention in SCI rats. Compared with the M group, urinary retention time was significantly shortened in the M+EA group, whereas it was significantly prolonged in the M+EA+PD group compared to the M+EA group. (D) The effect of EA on tissue structure and neuronal morphology following SCI. Compared with the M group, the M+EA group showed markedly reduced tissue destruction and cavitation in the spinal cord. As shown, EA treatment significantly suppressed tissue damage and cavitation formation. Scale bar = 20 µm. The error bars represent the standard deviation (SD), with a sample size of n = 6. Statistical analysis was conducted using analysis of one-way ANOVA. p < 0.01 versus S group, #p < 0.05 versus M group, &&p < 0.01 versus M + EA group. Please click here to view a larger version of this figure.
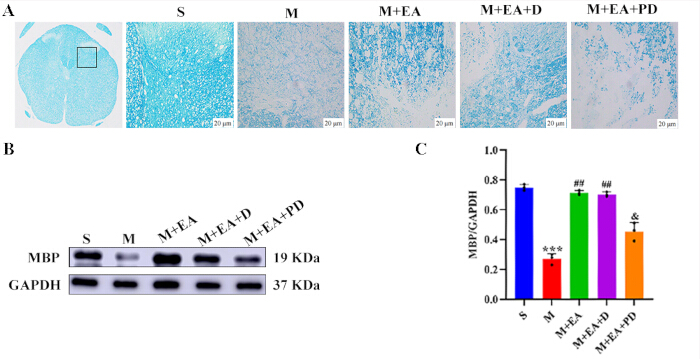
Figure 3: EA alleviates myelin loss and promotes myelin regeneration in the spinal cord of SCI rats. (A) LFB staining showing positive myelin expression (blue). Compared with the S group, the M group exhibited significant demyelination in the spinal cord. In contrast, the M+EA group showed a marked reduction in demyelination compared to the M group. Scale bar = 20 µm. (B) Western blot analysis of MBP protein expression in spinal cordtissue. The expression of MBP was significantly upregulated in the M+EA group compared with the M group. (C) Quantitative analysis of MBP proteins. The error bars represent the SD, with a sample size of n = 3. Statistical analysis was conducted using analysis of one-way ANOVA ***p < 0.001 versus S group, ##p < 0.01 versus M group, &p < 0.05 versus M + EA group. Please click here to view a larger version of this figure.
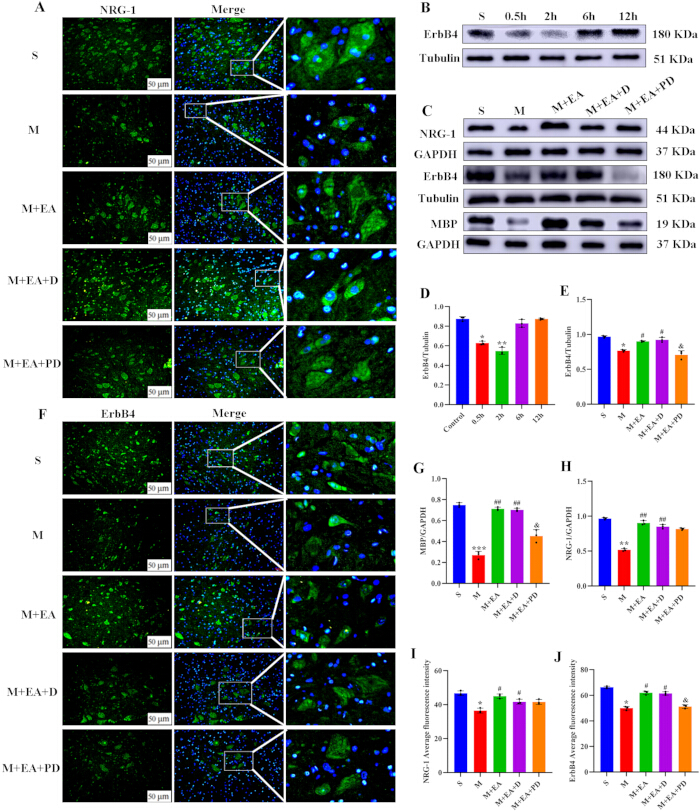
Figure 4: Involvement of the ErbB4 receptor in EA-promoted myelin regeneration in SCI rats. (A), (F) Immunofluorescence staining showing NRG-1 and ErbB4 expression (green). Positive expression of NRG-1 and ErbB4 is indicated within the white box. Scale bar = 50 µm. (B) The ErbB4 receptor antagonist PD158780 effectively suppressed ErbB4 protein expression in rats. Data are expressed as mean ± SD, *p < 0.05, **p < 0.01 versus Control. (C) Compared with the S group, the M group showed significantly downregulated expression of NRG-1, ErbB4, and MBP. In contrast, the M+EA group exhibited markedly upregulated expression of these proteins compared to the M group. However, the M+EA+PD group demonstrated significantly reduced ErbB4 and MBP expression compared to the M+EA group. (D), (E), (G) Quantitative analysis of NRG-1, ErbB4 and MBP protein expression. n = 3. (H), (I) Quantitative analysis of mean fluorescence intensity of positive NRG-1 and ErbB4 expression. n = 3. Scale bar = 50 µm. The error bars represent the SD, with a sample size of n = 3. Statistical analysis was conducted using analysis of one-way ANOVA. *p < 0.05, **p < 0.01, ***p < 0.001 versus S group, #p < 0.05, ##p < 0.01 versus M group, &p < 0.05 versus M + EA group. Please click here to view a larger version of this figure.
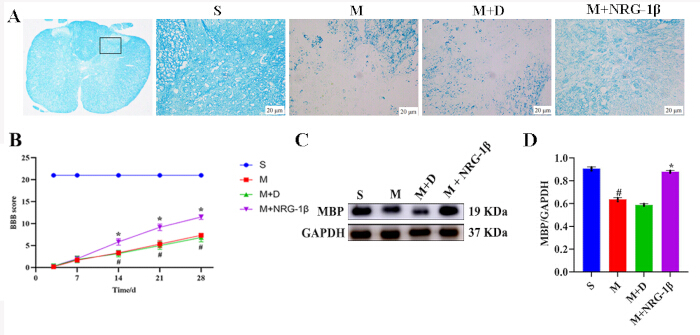
Figure 5: Intrathecal injection of NRG1 alleviates myelin loss, promotes myelin regeneration, and enhances hind limb motor function recovery in SCI rats. (A) LFB staining showing myelin expression (blue). Compared with the S group, the M group exhibited significant demyelination. In contrast, the M+NRG-1β group showed a marked reduction in demyelination compared to the M group. Scale bar = 20 µm. (B) Trend of BBB scores across different groups. Compared to the M group, the BBB scores of the M + NRG-1β group were significantly elevated. (C) Western blot analysis revealed that MBP protein expression was significantly upregulated in the spinal cord tissue of the M+NRG-1β group compared with the M group. (D) Quantitative analysis of MBP protein expression. n = 3. The error bars represent the SD, with a sample size of n = 3. Statistical analysis was conducted using one-way ANOVA. *p < 0.05 versus M group,#p < 0.05 versus S group. Please click here to view a larger version of this figure.
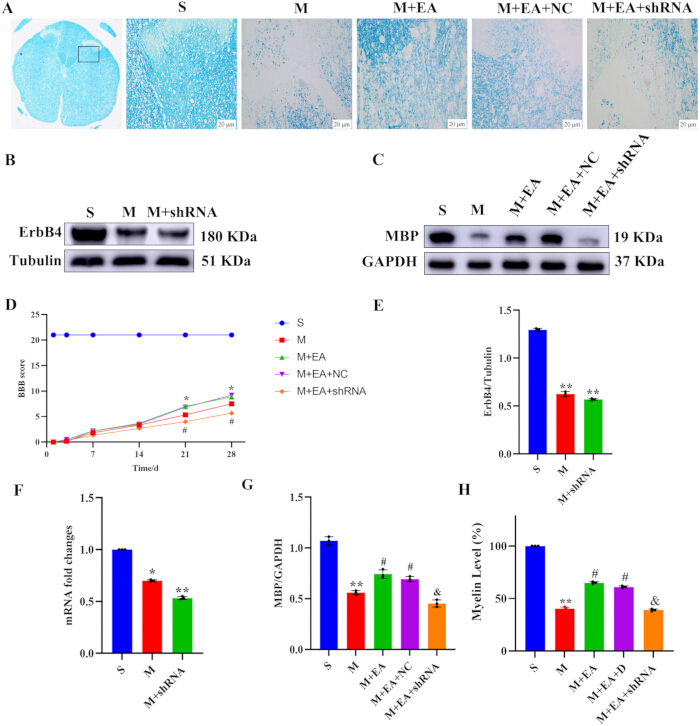
Figure 6: Lentiviral knockdown of ErbB4 expression inhibits the protective effects of EA on demyelination, remyelination, and hind limb motor function. (A) LFB staining showing positive myelin expression (blue). Compared with the M+EA group, the M+EA+shRNA group showed significantly inhibited myelin repair. Scale bar = 20 µm. (B) ErbB4 shRNA significantly suppressed ErbB4 protein expression in the spinal cord. (C) Western blot analysis revealed that MBP protein expression was markedly inhibited in the M+EA+shRNA group compared with the M+EA group. (D) Quantitative analysis of BBB scores in rats after SCI, starting from day 21. Hindlimb motor function recovery was significantly suppressed in the M+EA+shRNA group compared with the M+EA group. (E) Quantification of changes in ErbB4 protein expression. The error bars represent the SD, with a sample size of n = 3. Statistical analysis was conducted using one-way ANOVA. p < 0.01 versus S group. (F) RT-PCR analysis of ErbB4 mRNA expression in spinal cord tissue. The error bars represent the SD, with a sample size of n = 3. Statistical analysis was conducted using one-way ANOVA. *p < 0.05, p < 0.01 versus S group. (G) Quantitative analysis of MBP protein expression changes. (H) Quantitative analysis of the promoting effect of EA on remyelination. The error bars represent the SD, with a sample size of n = 3. Statistical analysis was conducted using one-way ANOVA. *p < 0.05, **p < 0.01 versus S group, #p < 0.05 versus M group, &p < 0.05 versus M + EA group. Please click here to view a larger version of this figure.
Supplementary File 1: Experimental raw data. Please click here to download this file.
Discussion
This study demonstrates that EA treatment alleviates spinal cord cavitation and demyelination after SCI, promoting remyelination through upregulation of MBP protein expression, and consequently improves hindlimb motor function in rats. Furthermore, we identified the NRG-1/ErbB4 signaling pathway as a critical mediator of neuronal remyelination and a potential therapeutic mechanism through which EA promotes remyelination and recovery of hindlimb motor function in SCI rats.
Nerve conduction in SCI is disrupted by various factors, leading to neurological dysfunction at the injury site28. Key pathological changes following SCI, such as neuronal necrosis, demyelination, remyelination, and inflammation, contribute to neurological deficits29,30. Remyelination is a critical factor for the recovery of neurological function in the later stages of SCI and is closely correlated with hindlimb motor function scores in rats31. Studies have shown that the SCI rat model closely mimics human limb movement disorders, demonstrating low variability, good stability, and high reliability32,33. In the present study, SCI rats displayed significant hindlimb dyskinesia, consistent with the reduction in BBB scores and LFB staining.
Myelin is the protective sheath surrounding nerve axons that facilitates proper axonal function, supports tissue structure, and increases nerve conduction velocity34. During CNS myelination, neurotrophic factors stimulate the proliferation and differentiation of oligodendrocyte precursor cells (OPCs) into mature OLs, which then form the myelin sheath around neuronal axons35. After SCI, neurons undergo necrosis and apoptosis due to both direct and indirect damage. Neuronal necrosis, which is irreversible, is often accompanied by OL necrosis, resulting in demyelination. This process is a significant contributor to the severe sequelae observed in most neurological injuries36. Therefore, inhibiting demyelination and promoting remyelination could enhance neurological recovery in SCI patients24. The spinal cord exhibits a certain degree of self-repair after SCI, where OPCs accumulate at the injury site and differentiate into OLs to facilitate myelin repair25. However, this effect is limited, and neurological function does not fully recover. In this study, H&E and staining revealed a disordered arrangement of posterior horn cells, pyknotic nuclei, and neuronal necrosis in the M group compared to the S group. Additionally, LFB staining showed significant demyelination in the M group compared to the S group. As a marker protein for myelinated Ols26, MBP expression was significantly reduced after SCI, and Western blot analysis confirmed that MBP protein expression was significantly lower in the M group than in the S group. Furthermore, the BBB score was significantly decreased in the M group, accompanied by severe hindlimb motor dysfunction. These results suggest that inhibiting neuronal necrosis and promoting remyelination are crucial for the recovery of hindlimb motor function.
EA has been widely used in treating nervous system injuries and has demonstrated promising clinical outcomes. Animal studies have shown that EA plays a key role in promoting remyelination by inhibiting OL necrosis after SCI, as well as promoting OPC proliferation and differentiation37,38. Additionally, EA can further stimulate remyelination by improving the local microenvironment at the injury site, such as reducing inflammation, enhancing collateral circulation, and clearing myelin debris39. Furthermore, EA can promote remyelination through the induction of neurotrophic factors33. Acupuncture points such as GV14 and GV4 are commonly used for SCI treatment, and EA stimulation at these points has been shown to significantly promote myelin sheath regeneration40,41. In the present study, LFB staining and Western blotting demonstrated significant remyelination in the posterior horn of the spinal cord in the M + EA and M + EA + D groups compared to the M group. Immunofluorescence analysis further showed enhanced co-expression of MBP and neuronal markers in the posterior horn of the M + EA and M + EA + D groups. As structural changes in organisms are typically accompanied by functional improvements, our results indicate that myelin sheath regeneration in SCI rats contributes to the recovery of hindlimb motor function. Additionally, the BBB scores of the M + EA and M + EA + D groups were significantly higher than those of the M group, consistent with the observed improvements in hindlimb motor function.
Remyelination is a complex physiological process. Previous studies have shown that intrathecal injection of NRG-1β can convert reactive astrocytes into OL-lineage cells, thereby promoting remyelination23,27,42. Injection of NRG-1β-loaded gel at the SCI site can stimulate the generation and maturation of OLs, while also inhibiting the expression of inflammatory factors at the injury site. Several studies have also indicated that ErbB receptor signaling directly regulates the proliferation and differentiation of OPCs after SCI, thereby facilitating remyelination43,44,45. Moreover, myelin regeneration after SCI is closely associated with the NRG-1/ErbB4 signaling pathway46,47.
In this study, NRG-1 and ErbB4 expression in the spinal cord of SCI model rats increased over time, suggesting a degree of self-repair in the spinal cord after SCI. These self-healing mechanisms activate specific signal transduction pathways and protect gene expression. Western blotting and immunofluorescence analysis revealed that NRG-1 and ErbB4 expression decreased in the M group compared to the S group, while intrathecal injection of NRG-1β and EA significantly upregulated the expression levels of NRG-1 and ErbB4. The ErbB4 receptor antagonist PD158780 and ErbB4 shRNA inhibited ErbB4 expression in spinal cord tissue. As expected, PD158780 and ErbB4 shRNA suppressed remyelination after SCI, further supporting the protective role of the NRG-1/ErbB4 signaling pathway in remyelination. We also explored the relationship between EA-induced remyelination and the NRG-1/ErbB4 signaling pathway. As anticipated, PD158780 and ErbB4 shRNA reversed the effects of EA after SCI, with significantly lower NRG-1 and ErbB4 expression in the M + EA + PD and M + EA + shRNA groups compared to the M + EA group. Additionally, the M + EA + PD and M + EA + shRNA groups exhibited significantly lower BBB scores and hindlimb motor functions compared to the M + EA group.
Limitations
This study provides valuable insights into EA as a treatment for SCI, but several limitations should be considered. The rat SCI model, while commonly used, does not fully replicate human SCI, limiting direct translation of results. Additionally, variability in acupuncture applications, such as differences in acupuncture point location and treatment parameters, could affect the reproducibility of the findings. The molecular complexity of the NRG-1/ErbB4 pathway, which may involve interactions with other signaling pathways, requires further exploration.
To better validate our hypothesis, genetic knockout or overexpression studies, along with pharmacological modulation of the NRG-1/ErbB4 pathway and advanced imaging techniques, should be employed to gain deeper insights. This approach could also be relevant to other conditions like multiple sclerosis and peripheral nerve injuries, where remyelination is crucial.
Future directions
Future studies should assess EA in chronic SCI models and perform long-term behavioral assessments to determine the durability of its effects. Preclinical studies bridging toward clinical trials are essential for evaluating the safety and efficacy of EA as a therapeutic strategy for SCI.
Conclusions
Our study demonstrates that EA treatment promotes remyelination following SCI by activating the NRG-1/ErbB4 signaling pathway. Consequently, EA represents one of the most promising therapeutic strategies for SCI. The NRG-1/ErbB4 signaling pathway may also serve as a potential target for preventing demyelination after SCI. Future studies will further investigate the cellular mechanisms underlying the effects of EA on myelin regeneration and validate these findings through experimental approaches.
Disclosures
The authors declare that they have no competing financial interests.
Acknowledgements
We thank the authors for their contributions to this study. This study was financially supported by the National Natural Science Foundation of China (NSFC 81960817, 82260387) and Basic Research Special Program of the Science and Technology Plan of the Yunnan Provincial Department of Science and Technology (202301AS070020). North Sichuan Medical College Scientific Research and Development Project (CBY22-QNA20)
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| BCA Protein Detection Kit | Beyotime Biotechnology | P0012S | Quantitative protein analysis |
| Electroacupuncture device | Huatuo Electroacupuncture Instrument, SDZ-V, Suzhou | — | Therapeutic equipment |
| FITC-labeled goat anti-human IgG | Beyotime | A0556 | Fluorescent secondary antibody |
| FITC-labeled goat anti-mouse IgG | Beyotime | A0568 | Fluorescent secondary antibody |
| FITC-labeled goat anti-rabbit IgG | Beyotime | A0562 | Fluorescent secondary antibody |
| Fluorescence microscope | Olympus | — | — |
| Human monoclonal MBP | Abcam | ab209328 | specific antibody |
| LFB myelin staining solution | Solarbio | G3240 | myelin sheath staining |
| Millipore ECL | Millipore | WBKLS0100 | Detection reagents |
| Mouse monoclonal NRG-1 | Santa Cruz | SC-57384 | specific antibody |
| Nanodrop ND-1000 | LabTech | — | |
| NRG1-1 beta | Novoprotein Technology Co | C753 | Recombinant human NRG1-1 beta |
| PD158780 | GlpBio Technology | GC15925 | The epidermal growth factor receptor (EGFR) tyrosine kinase inhibitor |
| PE-10 conduit | Becton, Dickinson and Company | 427401 | intrathecal injection |
| Penicillin sodium for injection | Harbin Zhongjing Biotechnology Co | 80451182 | Postoperative anti-infection therapy |
| Rabbit monoclonal ErbB4 | Abcam | ab109273 | specific antibody |
| RNAiso Plus Kit | Takara | 9109 | RT-PCR reagents |
| RT Reagent Kit | Takara | RR037A | RT-PCR reagents |
| Secondary antibody | Beyotime Biotechnology | — | specific antibody |
| Sodium pentobarbital | Sigma-Aldrich | 69020100 | Animal anesthesia |
| Yasargil aneurysm clip | Rebstock Instruments GmbH | — | Construction of a rat spinal cord injury model |
References
- McDonald, J. W., Sadowsky, C. Spinal-cord injury. Lancet. 359 (9304), 417-425 (2002).
- Mohammadi, E., Villeneuve, L. M., Smith, Z. A. Spinal Cord Injury: The Global Incidence, Prevalence, and Disability From the Global Burden of Disease Study 2019. Spine. 48 (24), 1767(2023).
- Anjum, A., et al. Spinal Cord Injury: Pathophysiology, Multimolecular Interactions, and Underlying Recovery Mechanisms. Int J Mol Sci. 21 (20), 7533(2020).
- Fang, M., Chen, L., Tang, T., Qiu, M., Xu, X. The committed oligodendrocyte precursor cell, a newly-defined intermediate progenitor cell type in oligodendroglial lineage. Glia. 71 (11), 2499-2510 (2023).
- Hellenbrand, D. J., et al. Inflammation after spinal cord injury: a review of the critical timeline of signaling cues and cellular infiltration. J Neuroinflammation. 18 (1), 284(2021).
- Pukos, N., et al. Chronic demyelination and myelin repair after spinal cord injury in mice: A potential link for glutamatergic axon activity. Glia. 71 (9), 2096-2116 (2023).
- Birch, S., Robinson, N. Acupuncture as a post-stroke treatment option: A narrative review of clinical guideline recommendations. Phytomedicine. 104, 154297(2022).
- Jiang, K., Sun, Y., Chen, X. Mechanism Underlying Acupuncture Therapy in Spinal Cord Injury: A Narrative Overview of Preclinical Studies. Front Pharmacol. 13, 875103(2022).
- Wang, X., et al. Electroacupuncture at Dazhui (GV14) and Mingmen (GV4) protects against spinal cord injury: the role of the Wnt/β-catenin signaling pathway. Neural Regen Res. 11 (12), 2004-2011 (2016).
- Li, S. S., et al. Electroacupuncture treatment improves motor function and neurological outcomes after cerebral ischemia/reperfusion injury. Neural regen res. 17 (7), 1545-1555 (2022).
- Liu, C., et al. Electroacupuncture promotes oligodendrocyte differentiation and myelin repair in a rat model of vascular dementia: Investigation of the mechanism from NF-κB-mediated inflammation. Neuroscience. 572, 21-34 (2025).
- Tong, T., et al. Electroacupuncture ameliorates chronic unpredictable mild stress-induced depression-like behavior and cognitive impairment through suppressing oxidative stress and neuroinflammation in rats. Brain Res Bull. 206, 110838(2024).
- Ahn, S. M., et al. Electroacupuncture ameliorates memory impairments by enhancing oligodendrocyte regeneration in a mouse model of prolonged cerebral hypoperfusion. Sci Rep. 6, 28646(2016).
- Kong, Y., Yang, J., Fan, Y. Q., Wang, W. S., Zhang, Y. T. "Huayu Tongluo" moxibustion improves learning-memory ability and promotes myelin regeneration by regulating Sonic Hedgehog signaling pathway in vascular dementia rats. Zhen Ci Yan Jiu. 48 (6), 578-584 (2023).
- Chen, W. C., et al. Influence of electroacupuncture of Dazhui (EX-B2) and Mingmen (GV4) on NR2B expression in anterior horns of spinal cord in rats with acute spinal cord injury. Zhen Ci Yan Jiu. 44 (2), 95-101 (2019).
- Mei, L., Nave, K. A. Neuregulin-ERBB signaling in the nervous system and neuropsychiatric diseases. Neuron. 83 (1), 27-49 (2014).
- Birchmeier, C., Bennett, D. L. Neuregulin/ErbB Signaling in Developmental Myelin Formation and Nerve Repair. Curr Top Dev Biol. 116, 45-64 (2016).
- Chen, S., et al. Neuregulin 1-erbB signaling is necessary for normal myelination and sensory function. J Neurosci. 26 (12), 3079-3086 (2006).
- Bartus, K., et al. ErbB receptor signaling directly controls oligodendrocyte progenitor cell transformation and spontaneous remyelination after spinal cord injury. Glia. 67 (6), 1036-1046 (2019).
- Tao, F., et al. Role of neuregulin-1/ErbB signaling in stem cell therapy for spinal cord injury-induced chronic neuropathic pain. Stem cells. 31 (1), 83-91 (2013).
- Clark, A. J., et al. Co-cultures with stem cell-derived human sensory neurons reveal regulators of peripheral myelination. Brain. 140 (4), 898-913 (2017).
- Wan, C., et al. Neuregulin1-ErbB4 Signaling in Spinal Cord Participates in Electroacupuncture Analgesia in Inflammatory Pain. Front Neurosci. 15, 636348(2021).
- Tseropoulos, G., et al. Immobilized NRG1 Accelerates Neural Crest like Cell Differentiation Toward Functional Schwann Cells Through Sustained Erk1/2 Activation and YAP/TAZ Nuclear Translocation. Adv Sci (Weinh). 11 (33), e2402607(2024).
- Luo, M., et al. Neuronal activity-dependent myelin repair promotes motor function recovery after contusion spinal cord injury. Brain Res Bull. 166, 73-81 (2021).
- Hesp, Z. C., Goldstein, E. Z., Miranda, C. J., Kaspar, B. K., McTigue, D. M. Chronic oligodendrogenesis and remyelination after spinal cord injury in mice and rats. J Neurosci. 35 (3), 1274-1290 (2015).
- Levy, G., et al. Gtf2i-encoded transcription factor Tfii-i regulates myelination via Sox10 and Mbp regulatory elements. Nat Commun. 16 (1), 8518(2025).
- Cescon, M., et al. Gut microbiota depletion delays somatic peripheral nerve development and impairs neuromuscular junction maturation. Gut Microbes. 16 (1), 2363015(2024).
- Ayar, Z., et al. The effect of low-level laser therapy on pathophysiology and locomotor recovery after traumatic spinal cord injuries: a systematic review and meta-analysis. Laser Med Sci. 37 (1), 61-75 (2022).
- Ghane, N., Beigi, M. H., Labbaf, S., Nasr-Esfahani, M. H., Kiani, A. Design of hydrogel-based scaffolds for the treatment of spinal cord injuries. J Mater Chem B. 8 (47), 10712-10738 (2020).
- Laskin, J. J., Waheed, Z., Thorogood, N. P., Nightingale, T. E., Noonan, V. K. Spinal Cord Stimulation Research in the Restoration of Motor, Sensory, and Autonomic Function for Individuals Living With Spinal Cord Injuries: A Scoping Review. Arch Phys Med Rehabil. 103 (7), 1387-1397 (2022).
- Li, G., et al. Epidural Spinal Cord Stimulation Promotes Motor Functional Recovery by Enhancing Oligodendrocyte Survival and Differentiation and by Protecting Myelin after Spinal Cord Injury in Rats. Neurosci Bull. 36 (4), 372-384 (2020).
- Csomó, K. B., et al. A Minimally Invasive, Fast Spinal Cord Lateral Hemisection Technique for Modeling Open Spinal Cord Injuries in Rats. J Vis Exp. (181), e63534(2022).
- Li, J. J., et al. Animal Models for Treating Spinal Cord Injury Using Biomaterials-Based Tissue Engineering Strategies. Tissue eng part b-re. 28 (1), 79-100 (2022).
- Coman, I., Barbin, G., Charles, P., Zalc, B., Lubetzki, C. Axonal signals in central nervous system myelination, demyelination and remyelination. J Neurol Sci. 233 (1-2), 67-71 (2005).
- Inouye, H., Kirschner, D. A. Evolution of myelin ultrastructure and the major structural myelin proteins. Brain Res. 1641 (Pt A), 43-63 (2016).
- Chen, X., Li, H. Neuronal reprogramming in treating spinal cord injury. Neural Regen Res. 17 (7), 1440-1445 (2022).
- Huang, S., et al. Protective Effect of Electroacupuncture on Neural Myelin Sheaths is Mediated via Promotion of Oligodendrocyte Proliferation and Inhibition of Oligodendrocyte Death After Compressed Spinal Cord Injury. Mol Neurobiol. 52 (3), 1870-1881 (2015).
- Kang, Z., et al. Electroacupuncture promotes regeneration and repair of myelin sheath of corpus callosum in demyelination mice. Zhen Ci Yan Jiu. 45 (1), 1-7 (2020).
- Zhu, K., et al. Electroacupuncture Promotes Remyelination after Cuprizone Treatment by Enhancing Myelin Debris Clearance. Front Neurosci. 10, 613(2017).
- Lu, J. Y., et al. Effects of electroacupuncture at different acupoints on the histomorphology of neurogenic bladder and the expression of hyperpolarization-activated cyclic nucleotide-gated channels in interstitial cells of Cajal in a rat model of suprasacral spinal cord injury. Ann Palliat Med. 9 (6), 3830-3838 (2020).
- Tu, W. Z., et al. The regulatory effect of electro-acupuncture on the expression of NMDA receptors in a SCI rat model. Life Sci. 177, 8-14 (2017).
- Ding, Z., et al. Neuregulin-1 converts reactive astrocytes toward oligodendrocyte lineage cells via upregulating the PI3K-AKT-mTOR pathway to repair spinal cord injury. Biomed Pharmacother. 134, 111168(2021).
- Kataria, H., et al. Neuregulin-1 promotes remyelination and fosters a pro-regenerative inflammatory response in focal demyelinating lesions of the spinal cord. Glia. 66 (3), 538-561 (2018).
- Schmitd, L. B., et al. Deletion of murine Sarm1 results in a microenvironment that delays peripheral nerve regeneration after injury. Sci Transl Med. 17 (819), eadp9155(2025).
- Hu, X., et al. Pan-ErbB inhibition impairs cognition via disrupting myelination and aerobic glycolysis in oligodendrocytes. Proc Natl Acad Sci U S A. 121 (45), e2405152121(2024).
- Størkson, R. V., Kjørsvik, A., Tjølsen, A., Hole, K. Lumbar catheterization of the spinal subarachnoid space in the rat. J Neurosci Methods. 65 (2), 167-172 (1996).
- Rahimi-Movaghar, V., Jazayeri, S. B. When do we start Basso, Beattie, and Bresnahan assessment after experimental spinal cord injury. Acta Med Iran. 51 (8), 5183(2013).