We provide a minimally invasive protocol for the intramuscular transplantation of human stem cell-derived pancreatic stem cell islets into immunodeficient mice for in vivo implantation and downstream analysis.
Method Article
Intramuscular Transplantation of Human Pluripotent Stem Cell-derived Pancreatic Endocrine Cells in Mice
In This Article
Summary
Abstract
Human pluripotent stem cell (hPSC)-derived pancreatic endocrine cells constitute a promising source for diabetes cell therapy and disease modeling. Although several differentiation protocols have been established, in vivo implantation is commonly required to study maturation and function within a physiological context. Most transplantation approaches rely on sites such as the kidney capsule or subcutaneous space, which may pose technical or physiological limitations. Here, we present a detailed protocol for the intramuscular transplantation of hPSC-derived pancreatic SC-islets into immunodeficient mice. This site allows for straightforward surgical access, reduced invasiveness, and reliable graft retrieval for subsequent analysis. The procedure enables intramuscular implantation of stem cell-derived islets and supports their recovery for downstream assessment of insulin secretion following an oral glucose challenge. The protocol includes steps for cluster preparation and compaction, transplantation surgery, in vivo glucose-stimulated insulin secretion (GSIS), and graft retrieval for histological analysis, providing a reproducible framework for intramuscular transplantation in preclinical mouse models.
Introduction
Diabetes is a heterogeneous metabolic disorder whose prevalence has doubled over the past three decades and is expected to affect 1.3 billion people by 20501. While environmental factors, such as diet and lifestyle, play a significant role in the onset of type 2 diabetes (T2D), genetic predisposition also contributes substantially to its pathogenesis2. Pancreatic β cells are responsible for insulin synthesis and secretion and play a central role in diabetes pathophysiology3. To understand how genetic risk contributes to β-cell dysfunction, human stem cell-derived β cells organized as three-dimensional endocrine clusters (hereafter referred to as SC-islets) provide a highly informative and relevant model system4,5. Recent protocols effectively guide the differentiation of human stem cells into insulin-producing β cells by recapitulating key stages of pancreatic development using specific inhibitors and growth factors6,7.
These systems reliably replicate developmental milestones in a scalable, reproducible manner, overcoming the limitations of donor-derived islets, which do not support developmental modeling and are subject to supply constraints. Murine models have provided valuable insights into pancreatic development, but they often fail to fully reproduce the phenotypic manifestations observed in human patients5. Consequently, the use of a stem cell-based system enables the characterization of genetic variants involved in human pancreatic development and β cell dysfunction8.
Despite these advances, SC-islets generated in vitro remain transcriptomically and functionally immature compared to native adult β cells. They exhibit suboptimal glucose-stimulated insulin secretion and lack expression of mature β-cell markers such as MAFA and G6PC29,10. To bridge this gap, in vivo maturation via transplantation into immunodeficient mice is often employed; this typically improves both insulin secretion dynamics and gene-expression profiles6.
Glucose metabolism is tightly regulated and requires the integration of systemic cues. Transplanted SC-islets are able to integrate signals from multiple organs, providing a more physiologically relevant environment crucial for assessing the functional consequences of genetic variation in human β cells11.
SC-islet transplantation in mice has been performed at different anatomical sites. The conventional site is the kidney capsule, effective for promoting β-cell maturation and reversing diabetes in streptozotocin (STZ)-treated rodents12, but it involves a complex invasive surgery, which limits its implementation across laboratories13. Moreover, this method is not translatable to clinical settings to treat patients with type 1 diabetes due to size and vascularization limitations14. Alternative transplantation sites, such as intramuscular, subcutaneous, and adipose tissue, have been reported, offering less invasive and more clinically applicable routes. Although intramuscular transplantation may present challenges for achieving optimal β-cell maturation and insulin secretion compared with the kidney capsule12, it can nevertheless achieve effective insulin secretion and maintenance of glucose homeostasis, while offering a simpler and more accessible surgical approach15,16.
Therefore, in this protocol, we present an intramuscular transplantation approach that addresses several limitations of other transplantation protocols. This method is minimally invasive and provides a reliable in vivo strategy for maturing SC-islets and investigating genetic variants linked to β-cell dysfunction.
Protocol
All experiments involving pluripotent stem cells (hPSCs) and laboratory animals were approved by institutional, regional, and national ethics committees. The hPSC lines used here were originally derived and distributed in accordance with the appropriate ethical approvals and informed consent procedures at the source institutions. Figure 1 shows the overall workflow, from hPSC maintenance through directed pancreatic lineage differentiation and maturation into SC-islets suitable for transplantation.
1.Differentiation of hPSCs to pancreatic progenitors
NOTE: This protocol builds upon two essential preparatory steps: 1) the maintenance and expansion of hPSCs, and 2) their directed differentiation toward the endocrine pancreas lineage. Both steps have been described in detail7,17. hPSCs are maintained in coated plates with B8 media following the recommendations of Lyria-Leyte et al.17. Harvest hPSCs for differentiation during exponential growth before they become confluent. At the recommended seeding density, they should reach 90-100% confluence the next day, ready to start differentiation. The differentiation toward the endocrine pancreas lineage is performed according to the procedure described by Barsby et al.7. Full details of the media can be found in Table 1.
- Freshly coat the differentiation plates with a basement membrane-derived extracellular matrix.
- Seed 0.16-0.19 million cells/cm2 on Day 0 (1.7 million cells in a well from a 6-well plate). Use 1.5-2x the volume of B8 + CEPT to prevent nutrient depletion (3-4 mL per well in a 6-well plate).
NOTE: When passaging hPSCs or seeding differentiation experiments, we preferentially supplement B8 media with CEPT, a cocktail of chroman 1, emricasan, polyamines, and trans-ISRIB, rather than the conventional ROCK inhibitor Y-27632, due to its proven ability to enhance hPSC survival18. Nonetheless, Y27632 remains a valid alternative for this protocol. - Perform media changes using differentiation media S1 through S4 according to the following schedule: S1 (Days 1-4), S2 (Days 4-7), S3 (Days 7-9), and S4 (Days 9-11).
NOTE: Refer to Table 1 for full media compositions; additional procedural details are described by Barsby et al.7.
2. Generation of 3D clusters and differentiation to insulin-producing cells
NOTE: On day 11, differentiated cells should have developed into pancreatic progenitors. To further promote endocrine differentiation at this stage, the cells transition from planar culture to 3D culture.
- Add 0.5 mL of 5% (w/v) anti-adherence solution (see Table 1 for details) to cover the bottom of a 24-well microwell plate containing inverted pyramidal microwells (400 µm diameter). Centrifuge at 1,300 g for 10 min at room temperature (RT).
NOTE: The anti-adherence solution creates an anti-adherent surface that prevents cells from sticking to the plastic and promotes uniform aggregation. - Examine the microwells under a microscope for air bubbles and re-centrifuge as needed to remove any trapped air (Figure 2A). Aspirate the anti-adherence solution and wash 2x with 0.5 mL of PBS/well. Leave the wells covered in PBS until ready for use.
- Wash the cells with 1 mL of PBS-0.5 mM EDTA, aspirate the PBS-EDTA, and cover the wells with trypsin (1 mL for a well of a 6-well plate). Incubate at 37 ºC for 8-12 min (until tapping causes noticeable detachment).
- Do not remove the trypsin; instead, dilute with 2x volumes of DMEM-F12 or PBS, and gently resuspend by pipetting. Place the suspension in a conical tube and immediately proceed to the next step.
NOTE: It is better to incubate for a longer time in trypsin than to perform a harsh mechanical trituration. - Centrifuge the suspension at 200 g for 3 min at RT. Aspirate the supernatant carefully and resuspend the pellet gently in prewarmed S4 medium (1.25 mL for each well of a 24-well microwell).
- Aspirate the PBS from microwell dishes. Gently, add 1.25 mL of the suspended cells to each well of the microwell plate.
NOTE: Each well of the 24-microwell plate contains 1,200 microwells. The seeding density required to obtain appropriate-sized clusters is 1,500 cells per microwell, corresponding to 1.8 million cells per well. Alternatively, 6-well microwells can be used, adjusting volumes and number of cells (approximately 8.85 million cells in 5 mL of Stage 4 medium). - Centrifuge the plate at 100 g for 3 min at RT to distribute the cells evenly in the microwells. Carefully transfer the microwell plates to a humidified incubator.
- Perform media changes using differentiation media S5 (D14-D18), S6 (D18-D25), and S7 (D25-D46).
NOTE: Full composition details are provided in Table 1, with additional procedural details described by Barsby et al.7.
CEPT cocktail can be used during this step instead of the ROCK inhibitor Y-27632, due to its proven ability to enhance cell survival during organoid formation18. Successful aggregation is indicated by the formation of compact, spherical clusters within 24-48 h (see Figure 2B).
3.Transplantation of SC-islets into the tight muscle of immunodeficient mice
NOTE: SC-islets have been transplanted at various stages of differentiation (from stage 4 to stage 7). While transplantation of differentiated S7 SC-islets represents the optimal strategy for assessing glucose responsiveness6, the transplantation of earlier-stage progenitors (S4-S5) or immature SC-islets (S6) may help reveal differentiation or maturation differences that are masked in vitro by the use of defined culture conditions. However, transplanting less differentiated progenitors carries a heightened risk of teratoma formation, primarily due to residual undifferentiated cell populations.
- Compaction of clusters
- Transfer the appropriate quantity of clusters to a 1.5 mL microcentrifuge tube (see note).
NOTE: Cell dose depends on the experimental goal. For histology, 0.5-1 million cells per mouse are sufficient for reliable graft retrieval, while functional assays or diabetes reversal in STZ-treated mice typically require higher doses, up to 2-5 million cells. Prior to compaction, SC-islets should exhibit a uniform spherical morphology with a target diameter of ~150-250 µm (acceptable range: 100-300 µm). This size range corresponds approximately to ~10³-4 × 10³ cells per cluster, oversized aggregates (>300-400 µm) should be avoided, as they are more susceptible to central necrosis. Cluster size and uniformity are verified before compaction by brightfield or stereomicroscope imaging of representative wells, followed by diameter measurement using standard image analysis software. - Connect a 23 G syringe to the needle-tubing assembly and fill it with S7 medium.
- Aspirate the clusters into the tubing directly from the microcentrifuge tube. Fold the tubing in half and insert the folded section into a 200 µL pipette tip. Insert the tip-tubing-needle assembly in a 15 mL conical tube and secure the ends to the tube's rim using tape.
- Centrifuge the tube at 100 g for 2 min at 4 °C to compact the clusters. Immediately place the tube on ice.
- Transfer the appropriate quantity of clusters to a 1.5 mL microcentrifuge tube (see note).
- Transplantation of clusters into mice
NOTE: All surgical procedures must be performed using appropriate personal protective equipment and in compliance with institutional biosafety and animal welfare regulations. Anesthetic agents and sharps should be handled and disposed of according to approved safety procedures.- Induce anesthesia in NOD-scid-gamma mice using 3-5% isoflurane.
- Shave the medial aspect of the right leg below the knee and disinfect with 70% ethanol.
- Detach the tubing from the pipette tip and connect it to the syringe. Cut the tubing close to the compacted clusters and attach it to the blunt end of the needle. Push the saline until the first cluster reaches the tip of the needle.
- Position the mouse prone, leaning to the right side, and extend the right leg. Insert the needle 4-5 mm deep into the medial compartment of the right thigh, in the region between the adductor and gracilis muscles.
- Inject the clusters, maximum volume of 50 µL, while retracting the needle by ~3 mm. After completing the injection, gently rotate the syringe 180° during needle withdrawal to help release the deposited clusters and minimize reflux of transplanted material.
- Monitor the mouse until fully recovered from anesthesia.
NOTE: For functional characterization (i.e., in vivo GSIS, section 4), SC-islets of a single genotype per mouse must be used; a single transplantation is sufficient. However, for histological or transcriptomic characterization of maturation post implantation, both legs can be used (e.g., one leg bearing SC-clusters derived from hPSCs containing a disease-associated genetic variant, and the other leg with the variant corrected). Correct intramuscular delivery cannot be directly confirmed in vivo immediately after injection. Successful implantation is instead verified retrospectively by macroscopic identification of the graft at the time of retrieval (Figure 3) and by histological analysis (Figure 4).
4. In vivo glucose-stimulated insulin secretion (GSIS)
NOTE In vivo GSIS via oral glucose challenge assesses functional insulin secretion in response to a physiological stimulus. All procedures must follow institutional animal care and use guidelines. Functional responses of transplanted β-cells improve with in vivo maturation: human C-peptide can be detected as early as 2 weeks post transplant, while robust glucose-responsive secretion is typically achieved by 4 weeks. These timelines can vary depending on the developmental stage of the SC-islets at transplantation
- Fast mice for 4-6 h prior to glucose administration, ensuring access to water.
- Prepare a 20% (w/v) D-(+)-glucose solution in water. Sterilize by passing through a 0.22 µm filter and warm to room temperature before use.
- Weigh each mouse and calculate the required glucose dose at 3 g/kg body weight.
- Load the appropriate volume of glucose solution into a 20 G curved gavage needle attached to a 1 mL syringe.
- Gently restrain the mouse and perform oral gavage, ensuring smooth insertion of the gavage needle to avoid tracheal aspiration.
- Collect blood samples via submandibular or tail vein puncture at baseline (0 min) and 15 and 30 min post gavage, using capillary tubes and 1.5 mL microcentrifuge tubes. Allow the blood to clot at room temperature for approximately 15 min, then store the tubes on ice.
- Centrifuge the samples at 1,000 g for 15 min at 4 °C and transfer serum to new tubes. Store at −80 °C until analysis by ELISA.
NOTE: Time points can be adjusted depending on the experimental model. It is critical to use an assay capable of distinguishing between human and mouse insulin or C-peptide to assess graft-derived insulin secretion in xenotransplant models.
5. Retrieval of grafted clusters
- Euthanize the mouse following institutional animal ethics guidelines.
- To minimize tissue contamination with fur, spray ethanol 70% (v/v) over the body.
- Remove the skin to expose the lower limb muscles and locate the grafted clusters using a magnifying glass. Excise graft-containing tissue using scissors and forceps.
- Rinse the tissue once with PBS and transfer it to 4% (w/v) paraformaldehyde (PFA) on ice. Fix the tissue in 4% PFA at 4 °C for 4 h with gentle shaking.
- Wash the sample in PBS for 1 h with gentle shaking. Transfer the tissue to 30% (w/v) sucrose on PBS and incubate overnight at 4 °C.
NOTE: Biological tissues, blood samples, and chemical waste (including fixatives and anesthetic residues) must be disposed of following institutional biosafety and chemical waste management guidelines.
6. Staining of explants
- OCT embedding
- Embed the tissue in a mold filled with Optimal Cutting Temperature (OCT) compound.
- Place the mold in a dry ice-isopropanol bath to flash-freeze the sample. Store at -80 °C until cryosectioning.
- Using a cryostat, cut 5-7 µm sections and store the slides at -80 °C.
- Immunostaining
- Equilibrate the slides at RT for 15 min inside a container to avoid condensation.
- Rinse the slides with PBS for 3 x 5 min.
- Incubate each section with 100 µL of blocking/permeabilization solution for 30 min at RT (0.1% nonionic surfactant in PBS, with 5% serum of the species where the secondary antibody was raised).
- Incubate each section with 50 µL of primary antibody diluted in blocking/permeabilization solution overnight at 4 °C.
- Rinse the slides with PBS for 3 x 5 min.
- Incubate each section with 50 µL of secondary antibody diluted in blocking/permeabilization solution 1 h at RT.
- Rinse the slides with PBS for 3 x 5 min.
- Mount the slides with 15 µL of mounting solution with DAPI and apply a coverslip. Store at 4 °C in the dark until imaging.
Results
The results shown correspond to intramuscular transplantation of Stage 7 SC-islets into immunodeficient mice and analysis performed 6 weeks post transplantation. A limited number of animals bearing representative grafts were analyzed to illustrate the feasibility of the procedure. In this study, a successful outcome is defined as the macroscopic retrieval of the intramuscular graft followed by histological confirmation of survival and endocrine identity of transplanted SC-islets. Figure 1 illustrates the overall differentiation workflow, from hPSC maintenance through directed pancreatic lineage differentiation and maturation into SC-islets suitable for transplantation.
To generate size-controlled 3D aggregates, single-cell suspensions of Stage 4 pancreatic progenitors were seeded into microwell plates (Figure 2A). Within 24-48 h, compact, spherical clusters formed (Figure 2B). Fluorescence microscopy of reporter hPSC lines, such as H1 PDX1C-termEGFP/WT and MEL1 INSGFP/w, confirmed the presence of PDX1 (from Stage 4) and Insulin-expressing cells (from Stages 5--6), respectively (Figure 2C,D).
For transplantation, stage 7 SC-islets were injected into the exposed thigh muscle. After 6 weeks, the graft site could be visualized macroscopically prior to dissection, with islet-like masses clearly identifiable within the muscle (Figure 3A). Following excision, explants were readily identifiable under a stereomicroscope as pale, spherical tissue structures (Figure 3B). In the experiments, intramuscular grafts were consistently retrievable at the 6-week time point, and explants suitable for downstream histological analysis were obtained from all transplanted animals. Robust detection of C-peptide-positive cells was observed in all transplanted animals, confirming the survival of human β-like cells within the intramuscular grafts. Insulin staining further confirmed the presence of human β-like cells, while glucagon- and somatostatin-positive cells indicated preservation of α- and δ-cell populations within the graft (Figure 4A-C), consistent with the engraftment and maintenance of hPSC-derived endocrine tissue in the intramuscular environment.
Functional assays described in the protocol could be used to further characterize SC-islet function after intramuscular transplantation. However, results from these assays are not presented here, and the experiments are discussed only in a methodological context.
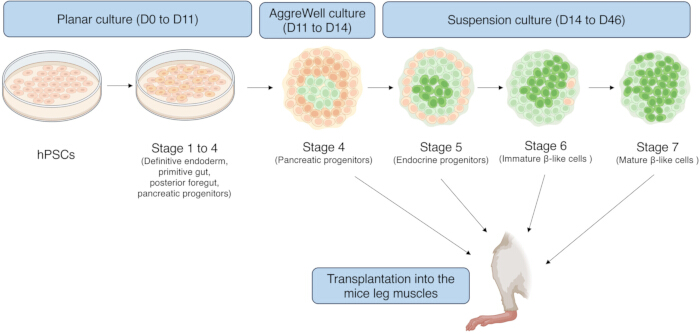
Figure 1: Schematic outline of the stepwise, in vitro differentiation of hPSCs into SC-islets containing β-like cells and other endocrine cells. The diagram illustrates the sequential culture stages guiding cells through definitive endoderm, primitive gut tube, posterior foregut, pancreatic progenitor, and endocrine progenitor phases, culminating in the generation of insulin-producing β-like cells. Key developmental signaling cues are modulated at defined intervals to mimic human pancreatic organogenesis, with final maturation achieved in suspension culture. Pancreatic organoids at Stage 4 can be transplanted into immunosuppressed mice to assess in vivo differentiation; however, more mature SC-islets (Stage 7) are usually associated with better functional outcomes. Abbreviations: hPSCs = human pluripotent stem cells; SC = stem cell. Please click here to view a larger version of this figure.
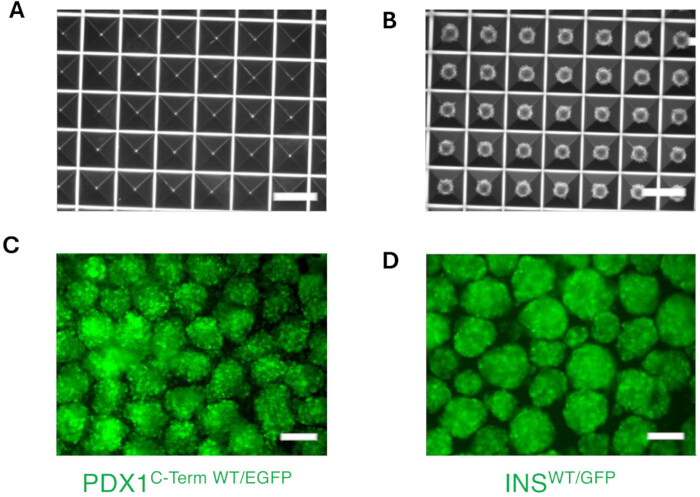
Figure 2: Generation and characterization of size-controlled pancreatic progenitor aggregates. Representative brightfield images showing (A) bubble-free microwells in a microwell plate, and (B) compact, spherical stage 4 clusters formed within 24-48 h. Images acquired with a 4x objective. Scale bars = 500 µm (C) Fluorescence microscopy of reporter signal from H1 PDX1C-termEGFP/WT aggregates at the end of Stage 4 confirms PDX1 expression. (D) MEL1 INSGFP/w reporter cells at Stage 7 reveal insulin-producing cells within the aggregates. Images acquired with a 10× objective. Scale bars = 200 µm. Please click here to view a larger version of this figure.
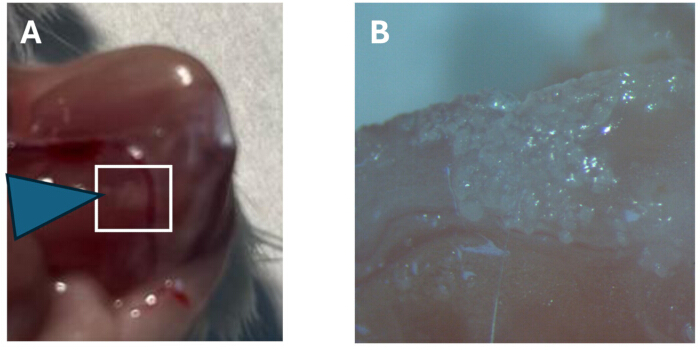
Figure 3: Macroscopic identification of intramuscular grafts. (A) Representative intraoperative image showing the thigh muscle 6 weeks after transplantation of stage 7 SC-islets. The graft site is indicated by a white box and blue arrow, revealing islet-like masses beneath the muscle fascia. (B) Stereomicroscope view of the excised explant, spherical SC-islets. Please click here to view a larger version of this figure.
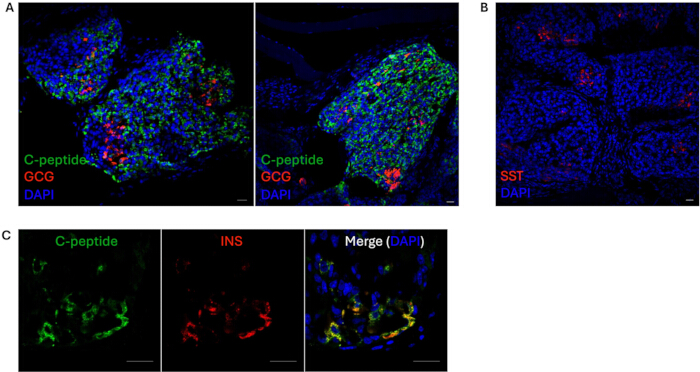
Figure 4: Immunofluorescence characterization of 6-week intramuscular grafts. (A) Confocal images of explant cryosections stained for C-peptide (β cells, green), glucagon (α cells, red), and DAPI (nuclei, blue). (B) Staining for somatostatin (δ cells, red) and DAPI (blue). (C) Staining for C-peptide (green), insulin (red), and merged image with DAPI (blue). Endogenous GFP fluorescence from reporter cell lines is not detectable after fixation under the imaging conditions used; green-channel signals correspond exclusively to antibody-based staining. Images acquired with a 20× (A,B) or 40x (C) objective. Scale bars = 20 µm. Abbreviations: GCG = glucagon; SST = somatostatin; DAPI = 4',6-diamidino-2-phenylindole. Please click here to view a larger version of this figure.
| Media / Solutions | Compound | Concentration |
| B8 medium | DMEM/F12 (Corning) | - |
| Insulin | 20 µg/mL | |
| 2-Phospho-L-ascorbic acid | 200 µg/mL | |
| Transferrin | 20 µg/mL | |
| Sodium selenite | 20 ng/mL | |
| FGFG-G3 | 120 ng/mL | |
| TGF-β1 | 2 ng/mL | |
| NRG1 | 0.25 ng/mL | |
| CEPT cocktail | Chroman 1 | 50 nM |
| Emricasan | 5 µM | |
| Polyamine Supplement | 1X | |
| Trans-ISRIB | 0.7 µM | |
| S1 differentiation medium | MCDB 131 | - |
| L-Alanyl-L-Glutamine | 2 mM | |
| NaHCO3 | 1.5 g/L | |
| BSA fV | 5 g/L | |
| Glucose | 5 mM | |
| Activin A | 100 ng/mL | |
| CHIR 99021 | 3 µM (Day 1), 0.3 µM (Day 2) or 0 µM (Day 3) | |
| S2 differentiation medium | MCDB 131 | - |
| L-Alanyl-L-Glutamine | 2 mM | |
| NaHCO3 | 1.5 g/L | |
| BSA fV | 5 g/L | |
| Glucose | 5 mM | |
| FGF7 | 50 ng/mL | |
| L-ascorbic acid | 0.25 mM | |
| S3 differentiation medium | MCDB 131 | - |
| L-Alanyl-L-Glutamine | 2 mM | |
| NaHCO3 | 2.5 g/L | |
| BSA fV | 20 g/L | |
| Glucose | 5 mM | |
| ITS-X | 1X | |
| FGF7 | 50 ng/mL | |
| L-ascorbic acid | 0.25 mM | |
| S3 supplement | 1X | |
| S4 differentiation medium | MCDB 131 | - |
| L-Alanyl-L-Glutamine | 2 mM | |
| NaHCO3 | 2.5 g/L | |
| BSA fV | 20 g/L | |
| Glucose | 5 mM | |
| ITS-X | 1X | |
| FGF7 | 2 ng/mL | |
| L-ascorbic acid | 0.25 mM | |
| EGF | 100 ng/mL | |
| Activin A | 10 ng/mL | |
| Nicotinamide | 10 mM | |
| S4 supplement | 1X | |
| Y-27632 | 10 µM | |
| CEPT (only during aggregation instead of Y-27632) | 1X | |
| S5 differentiation medium | MCDB 131 | - |
| L-Alanyl-L-Glutamine | 2 mM | |
| NaHCO3 | 1.5 g/L | |
| BSA fV | 20 g/L | |
| Glucose | 15 mM | |
| ITS-X | 1X | |
| Heparin | 10 µg/mL | |
| ZnSO4 | 10 µM | |
| Sobetirome (GC1) | 1 µM | |
| Betacellulin | 20 ng/mL | |
| S5 supplement | 1X | |
| CEPT | 1X | |
| S6 differentiation medium | MCDB 131 | - |
| L-Alanyl-L-Glutamine | 2 mM | |
| NaHCO3 | 1.5 g/L | |
| BSA fV | 20 g/L | |
| Glucose | 15 mM | |
| ITS-X | 1X | |
| Heparin | 10 µg/mL | |
| ZnSO4 | 10 µM | |
| Sobetirome (GC1) | 1 µM | |
| S6 supplement | 1X | |
| S7 differentiation medium | CMRL 1066 | - |
| L-Alanyl-L-Glutamine | 2 mM | |
| BSA fV | 20 g/L | |
| Sodium pyruvate | 0.5 mM | |
| ITS-X | 1X | |
| Heparin | 10 µg/mL | |
| ZnSO4 | 10 µM | |
| Lipid Concentrate | 1.430555556 | |
| Trace Elements A | 1.430555556 | |
| Trace Elements B | 1.430555556 | |
| N-acetylcysteine | 1 mM | |
| T3 | 10 nM | |
| ZM-447439 | 0.5 µM | |
| ITS-X (200X) | PBS | - |
| Insulin | 2 g/L | |
| Transferrin | 1.1 g/L | |
| Sodium Selenite | 1.34 mg/L | |
| Ethanolamine | 0.4 g/L | |
| S3 supplement (2000X) | DMSO | - |
| SANT1 | 0.5 mM | |
| Retinoic Acid | 2 mM | |
| LDN-193189 | 0.2 mM | |
| TPB | 0.4 mM | |
| S4 supplement (2000X) | DMSO | - |
| SANT1 | 0.5 mM | |
| Retinoic Acid | 0.2 mM | |
| LDN-193189 | 0.2 mM | |
| TPB | 0.4 mM | |
| S5 supplement (2000X) | DMSO | - |
| SANT1 | 0.5 mM | |
| Retinoic Acid | 0.1 mM | |
| LDN-193189 | 0.2 mM | |
| Alk5 Inhibitor | 20 mM | |
| DBZ | 0.2 mM | |
| S6 supplement (2500X) | DMSO | - |
| LDN-193189 | 0.25 mM | |
| Alk5 Inhibitor | 25 mM | |
| DBZ | 0.25 mM | |
| 5% Pluronic F-127 | Water | To 100 mL |
| (sterile-filtered) | ||
| Store at r.t. | Pluronic F-127 | 5 g |
Table 1: Full composition details. Please click here to download this Table.
Discussion
In this protocol, we describe intramuscular transplantation of SC-islets as a straightforward, reproducible, and minimally invasive approach for in vivo maturation, with the potential for functional assessment. Although transplantation under the kidney capsule is widely regarded as the "gold standard" for islet or SC-islet engraftment in rodents, it requires greater technical expertise and a longer surgical procedure. In contrast, the intramuscular site offers procedural simplicity and rapid execution, aligning with refinement principles of the 3Rs framework by reducing surgical complexity and perioperative stress. These attributes make it particularly appealing for laboratories seeking to evaluate the outcomes of genetic modifications in SC-islets, where ease of implementation is a priority.
The concept of using skeletal muscle for endocrine tissue engraftment has a long-standing precedent in clinical endocrinology, most notably in parathyroid autotransplantation, which remains in routine use9. This highlights the muscle tissue's capacity to sustain long-term endocrine function. However, muscular tissue is relatively poorly vascularized and exhibits lower angiogenic potential, which can result in a longer time to achieve functional engraftment or require higher cell numbers per graft20. Despite these limitations, intramuscular islet transplantation has repeatedly restored glucose homeostasis in rodent models of diabetes21, although for SC-islets, some studies report lower β-cell maturation marker expression and reduced insulin secretion compared with kidney capsule grafts12. Nonetheless, the trade-off between surgical simplicity and the accessibility of the graft for monitoring has led some laboratories to implement the technique, achieving efficient insulin secretion and β-cell maturation marker expression15,16.
The differentiation stage at the time of transplantation is an important consideration. Less mature progenitors (Stages 4-6) carry a higher risk of teratoma formation, and some evidence suggests site-specific differences in tumorigenic potential, with muscle showing a lower incidence than the kidney22. This may be advantageous in experimental designs focusing on in vivo maturation of earlier-stage SC-islets.
Several steps represent critical points that strongly influence the success and reproducibility of this protocol. Proper formation of SC-islets is critical to ensure successful transplantation and subsequent assessment of maturation. Accordingly, key steps such as the quality of hPSC culture, definitive endoderm induction on day 1, or aggregation of pancreatic progenitors on day 11 require careful control, including adjustment of seeding density at day 0 and gentle cell detachment, respectively. To prevent cluster disaggregation or excessive clumping, media changes in microwell plates should be performed gently, and the rotator speed may need to be adjusted.
Taken together, intramuscular transplantation represents a feasible and technically accessible approach for assessing the survival and maturation of SC-islets in vivo, enabling downstream functional assessments. Looking ahead, this protocol enables detailed mechanistic interrogation of graft-intrinsic maturation programs, host-graft interactions, and environmental influences on endocrine function, while supporting future translational applications such as systematic optimization of transplantation variables, scalability for higher-throughput preclinical studies, and longitudinal, non-terminal assessment of graft performance in vivo.
Disclosures
The authors have no conflicts of interest to declare.
Acknowledgements
We thank Dr. Danwei Huangfu (Memorial Sloan Kettering Cancer Center, New York, USA) for generously providing the hPSC lines used in this study. This work was supported by grants PID2021-122284NA-I00 and CNS2023-145179 from the Spanish Ministry of Science, Innovation and Universities MICIU/AEI/10.13039/501100011033 and Next GenerationEU/PRTR (A.B.), and by the CIBER-Consortium for Biomedical Research in Network, CB07/08/0029 and PID2023-150719OB-I00 (M.V.), Instituto de Salud Carlos III (ISCIII). The Center for Biomedical Research in Diabetes and Associated Metabolic Disorders (CIBERDEM) is an initiative of ISCIII and partially supported by the European Regional Development Fund (FEDER).
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| 2-Phospho-L-ascorbic acid trisodium salt | Sigma Aldrich | 49752 | |
| Activin A | Qkine | Qk001 | |
| AggreWell 400 24-well (microwell plate) | Stemcell | 34415 | |
| Betacellulin | GenScript | Z03102 | |
| Bovine Serum Albumin, Fraction V, Fatty Acid Free | Goldbio | A-421 | |
| CHIR 99021 | LC labs | C-6556 | |
| Chroman-1 | Medchem Express | HY-15392 | CEPT cocktail |
| CMRL-1066 | Pan Biotech | P04-84600 | |
| D-(+)-Glucose | Sigma Aldrich | G7021 | |
| Dibenzazepine (DBZ) | Syncom | Custom product | Gamma-secretase inhibitor |
| Dulbecco's Modified Eagle Medium and Ham’s F12 media (DMEM/F12) | Corning | 15383541 | |
| EGF | Qkine | Qk011 | |
| Emricasan | Medchem Express | HY-10396 | CEPT cocktail |
| Ethanolamine | Sigma Aldrich | E9508 | |
| FGF2-G3 | GenScript | Custom product | |
| FGF7 | GenScript | Z03047 | |
| Heparin | Sigma Aldrich | H3149 | |
| Insulin | Gibco | 30284510 | |
| L-Alanyl-L-Glutamine | Linus | X0551-100 | |
| L-Ascorbic Acid | Santa Cruz | sc-202686 | |
| LDN-193189 | Sigma Aldrich | SML0559 | |
| Lipid Concentrate | Gibco | 11548846 | |
| Matrigel (basement membrane-derived extracellular matrix) | Falcon | 354230 | |
| MCDB 131 | Corning | 15-100-CV | |
| N-acetylcysteine | Thermo Scientific | 10521221 | |
| NaHCO3 | Fisher Scientific | 10553325 | |
| Nicotinamide | Sigma Aldrich | N0636 | |
| NRG-1 | Qkine | Qk045 | |
| Pluronic F-127 (anti-adherence solution) | Sigma Aldrich | 82184 | Used at 5% (w/v) |
| Polyamine Supplement (1000×) | Sigma Aldrich | P8483 | CEPT cocktail |
| RepSox | MedChemExpress | HY-13012 | Alk5 Inhibitor |
| Retinoic Acid | Sigma Aldrich | R2625 | |
| SANT-1 | Selleckchem | S7092 | |
| Sobetirome (GC1) | Sigma Aldrich | SML1900-5MG | Cell-permeable T3 analog |
| Sodium Pyruvate | Corning | 25-000-CI | |
| Sodium Selenite | Sigma Aldrich | S5261 | |
| T3 (3,3′,5-Triiodo-L-thyronine sodium salt) | Sigma Aldrich | T6397 | |
| TGF-β1 | Qkine | Qk010 | |
| TPB | Tocris | 5343 | |
| Trace Elements A | Corning | 15333641 | |
| Trace Elements B | Corning | 15343641 | |
| Trans-ISRIB | Medchem Express | HY-12495 | CEPT cocktail |
| Transferrin | InVitria | 777TRF029 | |
| Triton X-100 (nonionic surfactant) | Thermo Scientific | 11488696 | |
| TrypLE | Gibco | 11538856 | |
| Y-27632 | LC Laboratories | Y-5301 | ROCK inhibitor |
| ZM-447439 | MedChemExpress | HY-10128 | |
| ZnSO4 | Sigma Aldrich | Z0251 | |
| Antibodies | |||
| Rat anti-Human C-peptide (insulin) | DSHB | GN-ID4-s | Used at 150 ng/mL |
| Mouse anti-glucagon | Proteintech | 67286-1-Ig | 1:2000 |
| Rabbit anti-somatostatin | Millipore | AB5494 | 1:500 |
| Goat anti-rat AF488 | Invitrogen | A-11006 | 1:500 |
| Donkey anti-mouse AF488 | Invitrogen | A-21202 | 1:500 |
| Donkey anti-rabbit AF488 | Invitrogen | A-21206 | 1:500 |
References
- Ong, K. L., et al. regional, and national burden of diabetes from 1990 to 2021, with projections of prevalence to 2050: A systematic analysis for the Global Burden of Disease Study 2021. The Lancet. 402 (10397), 203-234 (2021).
- Ismail, L., Materwala, H., Al Kaabi, J. Association of risk factors with type 2 diabetes: A systematic review. Comput Struct Biotechnol J. 19, 1759-1785 (2021).
- Prasad, M. K., Mohandas, S., Ramkumar, K. M. Dysfunctions, molecular mechanisms, and therapeutic strategies of pancreatic β-cells in diabetes. Apoptosis. 28 (7-8), 958-976 (2023).
- Xue, D., et al. Functional interrogation of twenty type 2 diabetes-associated genes using isogenic human embryonic stem cell-derived β-like cells. Cell Metab. 35 (11), 1897-1914.e11 (2023).
- Bartolomé, A. Stem cell-derived β cells: A versatile research platform to interrogate the genetic basis of β cell dysfunction. Int J Mol Sci. 23 (1), 501(2022).
- Balboa, D., et al. Functional, metabolic and transcriptional maturation of human pancreatic islets derived from stem cells. Nat Biotechnol. 40 (7), 1042-1055 (2022).
- Barsby, T., et al. Differentiating functional human islet-like aggregates from pluripotent stem cells. STAR Protoc. 3 (4), 101711(2022).
- Shi, Z. -D., et al. Genome editing in hPSCs reveals GATA6 haploinsufficiency and a genetic interaction with GATA4 in human pancreatic development. Cell Stem Cell. 20 (5), 675-688.e6 (2017).
- Fantuzzi, F., et al. In depth functional characterization of human induced pluripotent stem cell-derived beta cells in vitro and in vivo. Front Cell Dev Biol. 10, e967765(2022).
- Augsornworawat, P., Maxwell, K. G., Velazco-Cruz, L., Millman, J. R. Single-cell transcriptome profiling reveals β cell maturation in stem cell-derived islets after transplantation. Cell Rep. 32 (8), 108850(2020).
- Lin, H., et al. Glucose metabolism and regulation in establishing human stem cell-derived β cell maturation. Cell Rep. 44 (7), 115892(2025).
- Maxwell, K. G., Kim, M. H., Gale, S. E., Millman, J. R. Differential function and maturation of human stem cell-derived islets after transplantation. Stem Cells Transl Med. 11 (3), 322-331 (2022).
- Thévenet, J., Gmyr, V., Delalleau, N., Pattou, F., Kerr-Conte, J. Pancreatic islet transplantation under the kidney capsule of mice: Model of refinement for molecular and ex-vivo graft analysis. Lab Anim. 55 (5), 408-416 (2021).
- Scholl, V. G. S., et al. Assessing implantation sites for pancreatic islet cell transplantation: Implications for type 1 diabetes mellitus treatment. Bioengineering. 12 (5), 499(2025).
- Sui, L., et al. Reduced replication fork speed promotes pancreatic endocrine differentiation and controls graft size. JCI Insight. 6 (5), e141553(2021).
- Lithovius, V., et al. Non-invasive quantification of stem cell-derived islet graft size and composition. Diabetologia. 67 (9), 1912-1929 (2024).
- Lyra-Leite, D. M., Fonoudi, H., Gharib, M., Burridge, P. W. An updated protocol for the cost-effective and weekend-free culture of human induced pluripotent stem cells. STAR Protoc. 2 (1), 100213(2021).
- Chen, Y., et al. A versatile polypharmacology platform promotes cytoprotection and viability of human pluripotent and differentiated cells. Nat Methods. 18 (5), 528-541 (2021).
- Wells, S. A., Ellis, G. J., Gunnells, J. C., Schneider, A. B., Sherwood, L. M. Parathyroid autotransplantation in primary parathyroid hyperplasia. N Engl J Med. 295 (2), 57-62 (1976).
- Kim, H. -I., Yu, J. E., Park, C. -G., Kim, S. -J. Comparison of four pancreatic islet implantation sites. J Korean Med Sci. 25 (2), 203(2010).
- Axen, K. V., Pi-Sunyer, F. X. Long-term reversal of streptozotocin-induced diabetes in rats by intramuscular islet implantation. Transplantation. 31 (6), 439-441 (1981).
- Prokhorova, T. A., et al. Teratoma formation by human embryonic stem cells is site dependent and enhanced by the presence of Matrigel. Stem Cells Dev. 18 (1), 47-54 (2009).
Reprints and Permissions
