In this article, we have described a reproducible, temperature-controlled protocol for ex vivo Phosphorus-31 Magnetic Resonance Spectroscopy, enabling serial, quantitative assessment of myocardial energetics during organ preservation.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Method Article
Phosphorus-31 Magnetic Resonance Spectroscopy for Serial Measurements of Cardiac Energetics During Temperature-Controlled Heart Preservation
* These authors contributed equally
In This Article
Summary
Abstract
Reliable organ preservation is critical to increasing donor availability and improving transplant outcomes. While static storage remains the standard for donor hearts, there is a need for precise methods to monitor myocardial energetics throughout preservation.
Phosphorus-31 Magnetic Resonance Spectroscopy (31P MRS) enables direct, dynamic measurement of key energy metabolites, including Phosphocreatine (PCr), Adenosine TriPhosphate (ATP), inorganic phosphate (Pi), and intracellular pH. This technique allows for longitudinal, quantitative, and precise evaluation of myocardial metabolic status during ex vivo storage. Advantages of MRS include dynamic assessment of energy status and a global assessment of ventricular energy.
The protocol begins with swine donor recovery, cardioplegia administration, and cardiectomy. The aortic arch is cut proximal to the brachiocephalic trunk to maximize the length of the ascending aorta. A ribbed cannula is secured into the distal ascending aorta, the left atrium is marked, and the heart is placed in a cylindrical, insulated container pre-filled with temperature-specific cardioplegia. The lid connects to the cannula, suspending the heart inside, and the container is sealed, maintaining a temperature within 1 °C for 1 h.
The container is placed in a tailored Styrofoam box with an opening for a phosphorus tuned coil, aligning the coil center with the center of the left ventricle (LV). Scout images confirm LV placement near the 31P coil. B0 shimming ensures uniform excitation, followed by acquisition of a non-localized 31P MR spectrum. Post-processing identifies spectral peaks for calculating PCr/ATP, PCr/Pi ratios, and intracellular pH.
In our protocol, 31P MRS is performed at serial timepoints between h 0 to 8. Between timepoints, the heart is stored in a standard storage device at the desired temperature.
31P MRS has allowed us to study time-dependent changes to energy depletion and the role of storage temperature in mitigating energy depletion over time.
Introduction
Heart transplantation remains the definitive treatment for select patients with end-stage heart failure1. However, a persistent shortage of suitable donor organs and the limitations of the current preservation strategies are major barriers to optimal outcomes and expanded transplant availability2,3. Traditionally, donor hearts are preserved using cold static storage, which is straightforward and cost-effective, but is susceptible to subclinical energetic depletion during prolonged transport2,4. As programs increasingly accept higher-risk and geographically distant organs, there is a growing need for objective tools that characterize the metabolic condition of the myocardium during preservation rather than relying solely on ischemic time and gross inspection5,6,7. In addition, myocardial metabolism and ischemic tolerance are strongly influenced by temperature, and both inadequate cooling and excessive hypothermia can worsen energetic depletion and cellular injury during storage. Evaluating donor hearts at multiple, clinically relevant preservation temperatures, therefore, helps identify conditions that best maintain myocardial viability over time3.
Accurate, dynamic assessment of myocardial bioenergetics during storage is essential to improve preservation techniques and maximize organ utilization. Currently, standard practice relies on static cold storage at temperatures in the range of approximately 4-8 °C8. Although this protocol has shown successful outcomes over short storage durations, prolonged storage at this temperature may jeopardize myocardial integrity. Therefore, it is essential to conduct serial measurements of metabolic activity across a range of temperatures and durations to delineate the optimal storage conditions necessary for ensuring successful organ transplantation. Conventional evaluation of preservation injury often relies on histological examination or biochemical assays from myocardial biopsies, which are invasive, destructive, and provide only intermittent, regional snapshots of tissue status9. In contrast, phosphorus-31 magnetic resonance spectroscopy (31P MRS) is a powerful, non-destructive modality that enables direct, serial measurement of key energy metabolites, including phosphocreatine (PCr), adenosine triphosphate (ATP), inorganic phosphate (Pi), and intracellular pH, within intact cardiac tissue6,10,11,12. By permitting repeated measurements in the same organ without additional tissue handling, 31P MRS provides global and longitudinal insights into myocardial energetic status, enhancing experimental precision and reproducibility compared with biopsy-based or serum surrogate approaches6,13.
The assessment of cardiac graft viability with 31P MRS has been reviewed by Bernard et al14. Here, a detailed, temperature-controlled protocol for ex vivo 3 Tesla 31P MRS of the swine heart during preservation is presented. This method provides a practical framework for monitoring substrate depletion, testing storage variables, and validating preservation interventions. The protocol is particularly appropriate for laboratories that seek serial, whole-ventricle measurements during static cold storage, such as studies of temperature-dependent preservation, ischemia-reperfusion injury, or optimization of solutions for marginal and extended-criteria donor hearts.
Access restricted. Please log in or start a trial to view this content.
Protocol
This protocol follows institutional animal care guidelines and was approved by the Johns Hopkins Animal Care and Use Committee (Protocol number SW24M319) for all procedures involving live animals up to and including surgical harvest. All subsequent ex vivo experiments were performed using tissues obtained after euthanasia.
1. Pre-Harvest procedure
- Set the incubator to a temperature that is 2 °C below the target preservation temperature. Allow the incubator to stabilize for at least 2 h.
- Place 6-7 ice packs in the incubator to pre-chill them to the set temperature. Ensure ice packs are sufficient in quantity to maintain temperature during transport.
- Prepare modified Saint Thomas cardioplegia solution:
- In 1 L of Lactated Ringer's solution bag, add
- 30 mL of 8.4% sodium bicarbonate
- 5 mL of 30 mmol/10 mL of potassium chloride
- 2.5 mL of 20 mmol/10mL magnesium sulfate
- 15 mL of 50% dextrose
- 100 mg of 50 mg/10 mL nitroglycerin
- 5000 U of cold erythropoietin
- Prepare a total of 3 L of cardioplegia solution and store the solution in the pre-chilled incubator.
- In 1 L of Lactated Ringer's solution bag, add
- Set aside the insulated cooler with a built-in silicone tubing that allows for optimal positioning of the heart's vertical height. Place a black reference mark on the silicone tubing at the point that lies directly beneath the tip of the opening on the cooler lid.
- Set aside a ribbed cannula for securing and suspending the harvested heart. Place a black reference mark on the outer surface of the cannula to serve as a reproducible alignment point.
2. Harvest procedure
- Sedate the animal using a combination of telazol, ketamine, and xylazine mixed in a single syringe and administered intramuscularly, to minimize the stress and pain associated with multiple injections.
- Telazol (50 mg tiletamine + 50 mg zolazepam) at 4.4 mg/kg for each component.
- Ketamine at 2.2 mg/kg.
- Xylazine at 2.2mg/kg.
- Intubate and anesthetize the animal.
- Tidal volume at 5-10 mL/kg.
- Respiratory rate at 12-15 breaths/min.
- Positive End-Expiratory Pressure at 5 cm H2O.
- Inhaled isoflurane at 0.5-2% with an oxygen flow of 1-2 L/min.
- Place peripheral intravenous lines, perform a sternotomy and open the pericardium15. Administer antiarrhythmics if required.
- Place a cardioplegia needle in the ascending aorta, positioning above the aortic valve but below the aortic arch.
- Spike and connect a 1 L bag of cardioplegia solution to the needle.
- Vent the left atrium, inferior vena cava, and superior vena cava.
- Apply an aortic cross clamp proximal to the arch.
- Initiate cardioplegia flow through the coronaries at a pressure of approximately 75-80 mmHg. Monitor pressure using an in-line gauge.
- Harvest the heart while maintaining anatomical integrity.
- Pour pre-chilled saline over the harvested heart to rapidly cool its surface.
- Place the heart in a bowl filled with cold cardioplegia solution.
- Insert a myocardial temperature probe at the apex of the heart, and a thermometer into the bowl of cardioplegic solution to monitor temperature.
- Separate the aorta from the pulmonary artery (PA).
- Secure the ribbed cannula in the aorta using silk ties and zip ties, ensuring that the marked portion of the cannula corresponds to the position of the left ventricle (LV).
- Fill the cooler with Saint Thomas solution to 60-70% capacity, then transfer the heart and the bowl's solution into the cooler for a total fill, maximizing immersion.
- Measure and document the final solution and tissue temperature.
- Attach the ribbed cannula to the cooler lid with silicone tubing at the predefined mark. Ensure that the marks on the ribbed cannula and the silicone tubing are aligned, so that the LV maintains a consistent orientation relative to the lid when the cooler is closed, ensuring reproducible positioning of the LV for every scan (Figure 1A).
- Deair the organ to ensure optimal MR field homogeneity and good signal-to-noise ratio during MR data collection.
- Secure the cooler lid, ensuring LV alignment.
- Place ice packs and a cooler into a transport bag.
3. Spectroscopy protocol
- This protocol is optimized for a 3T MR scanner. The MR scanner is equipped with a multi-nuclei spectroscopy option, including a 4 kW broadband radiofrequency amplifier and receiver, including the standard vendor provided phosphorus coil (P140). The 31P coil is a 14 cm diameter single loop transmit/ receive coil with two rods for tuning and matching.
- Notify MRI facility staff prior to transport and confirm scan availability.
- Prepare a Styrofoam box with the following external dimensions: length 33.5 cm, width 28 cm (longer edge), width 23 cm (shorter edge), and thickness 4 cm. Make a slit measuring 3.3 cm in width on one side of the box to allow placement of the 31P coil adjacent to the heart (Figure 1B).
- Insert the cooler with the suspended heart adjacent to the coil's central axis, targeting the LV location (Figure 1C). Prepare a cooler that is 25.4 cm high and 11.4 cm wide. The silicone tubing is fixed at a length of 7 cm from the inner surface of the lid, at the point of heart mounting (Figure 1D).
- Place ice packs in gaps around the cooler, taking care to avoid creating space between the cooler and the coil, then tape the box lid to ensure stability during scanning (Figure 1E).
- Center the cooler to the magnet isocenter using the laser guides and centering landmark, to ensure optimal B0 homogeneity (Figure 1F).
- Plug the 31P coil into the scan connector and attach tuning and matching rods to the coil (Figure 1F).
- Acquire tri-plane localizer scout images to verify coil placement and optimal LV proximity to the 31P coil (Figure 2).
- If the LV positioning is incorrect, rotate the cooler lid and rerun the scout scan.
- Acquire a static field B0-map for localized 2nd order shimming16 to ensure a uniform magnetic field across the region of interest required for high spectral quality:
- After the acquisition of the B0-map, a "Shimtool"16 automatically launches with that map loaded (Figure 3).
- Click points of a smoothed polygon outlining the cardiac muscle in all slices (Figure 3A).
- The "Shimtool" then performs a constrained least-squares fit to determine localized resonance frequency and first (x, y, z) and second order (xy, xz, yz, x2-y2, z2-(x2+y2)/2) shim field corrections (Figure 3C). Upload these correction terms to the scanner and apply them to the following scans.
- Prior to 31P MRS acquisition, turn the tuning rods of the coil to ensure optimal tuning of the radiofrequency coil and match its impedance to the MR system, in turn maximizing the efficiency of signal transmission and minimizing reflections in the radiofrequency system (Figure 4).
- Acquire an initial non-localized 31P MR spectra (repetition time [TR]: 10 s, flip angle = 90° using adiabatic B1-Insensitive Rotation-4 (BIR-4) pulses; echo time [TE] = 0.1 ms; bandwidth=3000 hertz (Hz); 1024 spectral points, 5 averages) to determine the resonance frequency at the center between the PCr and γ-ATP peaks. Total acquisition time: 50 s.
- Then acquire fully relaxed non-localized 31P MR spectra after adjusting the offset frequency based on the calculation in 3.12 (TR: 16 s, flip angle = 90° using adiabatic BIR-4 pulses; TE = 0.1 ms; bandwidth = 3000 Hz; 512 spectral points, 20 averages). Total acquisition time: 5 min 20 s.
- After scanning, measure the fluid and myocardial temperatures; ensuring deviation from the target is ≤1 °C.
- Store the heart in the incubator at the desired temperature until the next scheduled scan.
4. Data analysis
- Export the fully relaxed 31P MRS data as .SDAT data files and load into a graphical user interface for processing (Figure 5A)17.
- First, apodize the spectra using a 15 Hz Lorentzian filter (Figure 5B), then apply a 0 and 1st order phase shift, and set the frequency to 0 parts per million (ppm) at the center of the PCr peak (Figure 5C).
- Fit the spectra using the AMARES function18 using the knowledge values listed in Table 1.
- Review the analysis for adequate fitting in the next window (Figure 6), by ensuring that each peak is correctly identified (individual components) and that minimal residual signal remains following analysis (residue).
- Calculate the myocardial metabolite ratios PCr/ATP and PCr/Pi based on the spectroscopic peak amplitude (Figure 7). The γ-ATP resonance is used as a measure of ATP.
- Calculate the intracellular pH based on the chemical shift between Pi and PCr after adjustment, to reflect the temperature condition14.
NOTE: The protocol can be paused after each MRI scan (step 3.15). Ensure temperature control is maintained throughout.
5. Equations
- Calculate the intracellular pH (pHi) as previously described19:
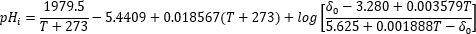
Where T is the temperature in °C, and δ0 is the observed chemical shift difference between the PCr and Pi resonances, in ppm.
Access restricted. Please log in or start a trial to view this content.
Results
The localized 2nd order shimming16 resulted in a more homogenous B0 magnetic field across the region of interest, as indicated by a reduction in the standard deviation at each time point (0 h: 14.0 to 4.0 Hz; 4 h: 17.5 to 3.2 Hz; 8 h: 16.0 to 3.2 Hz). This ensured that excellent spectral quality was achieved at each time point (Figure 7). The myocardial metabolic changes during ex vivo cold storage indicate a rapid depletion of high-ener...
Access restricted. Please log in or start a trial to view this content.
Discussion
This manuscript describes a surgical preparation and a 31P MRS acquisition and analysis protocol for the serial assessment of myocardial energetics during heart preservation. 31P MRS allows for serial, non-destructive assessment of key cardiac metabolites at different cold storage temperatures, which provides novel insights into the metabolic viability of the myocardial tissue. This 31P MRS protocol is relatively fast, requiring minimal scanner time, which allows for the assessment of car...
Access restricted. Please log in or start a trial to view this content.
Disclosures
We do not have any conflict of interest.
Acknowledgements
We wish to acknowledge our team at Johns Hopkins in the cardiac surgery and radiology department to help carry out this research successfully. This study was funded by The American Association for Thoracic Surgery (AATS).
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Incubator | Benchmark Scientific | H2265-HC | MyTemp 65HC Heating Cooling Incubator |
| Insulating cooler | Gatorade | UPC 052000047097 | Gatorade Insulated Sport Beverage Cooler |
| jMRUI version 7.0 | Java | www.jmrui.eu | Graphical user interface for data analysis |
| Myocardial temperature probe | DeRoyal | 81-030415 | DeRoyal 400 series myocardial temperature probe (15mm) |
| Magnetic Resonance Scanner | Philips | https://www.philips.com/healthcare/diagnostic-imaging/magnetic-resonance-imaging | Achieva 3T, Philips Healthcare |
| Single loop phosphorus coil | Philips Healthcare | https://www.philips.com/healthcare/diagnostic-imaging/magnetic-resonance-imaging | P140, Philips Healthcare |
References
- Lechiancole, A., et al. Graft preservation in heart transplantation: current approaches. Front Cardiovasc Med. 10, 1253579(2023).
- Kounatidis, D., et al. Donor heart preservation: current knowledge and the new era of machine perfusion. Int J Mol Sci. 24 (23), 16693(2023).
- Ughetto, A., et al. Heart graft preservation technics and limits: an update and perspectives. Front Cardiovasc Med. 10, 1248606(2023).
- Wang, C. C., et al. Understanding preservation time thresholds in the modern era of heart transplantation. Sci Rep. 15 (1), 1-10 (2025).
- Tang, P. C., et al. Risk factors for heart transplant survival with greater than 5 h of donor heart ischemic time. J Card Surg. 36 (8), 2677-2684 (2021).
- Peterzan, M. A., Lewis, A. J. M., Neubauer, S., Rider, O. J. Non-invasive investigation of myocardial energetics in cardiac disease using 31P magnetic resonance spectroscopy. Cardiovasc Diagn Ther. 10 (3), 625-639 (2020).
- Lerman, J. B., et al. Donor heart recovery and preservation modalities in 2024. JACC Heart Fail. 12 (3), 427-437 (2024).
- Al-Ani, M. A. Z., Farr, M. A., Shah, P. Cold precision: enhancing organ preservation with controlled hypothermia. J Heart Lung Transplant. 43 (9), 1527-1529 (2024).
- Mishra, P. K., et al. Guidelines for evaluating myocardial cell death. Am J Physiol Heart Circ Physiol. 317 (5), H891-H922 (2019).
- Abdurrachim, D., Prompers, J. J. Evaluation of cardiac energetics by non-invasive 31P magnetic resonance spectroscopy. Biochim Biophys Acta Mol Basis Dis. 1864 (5), 1939-1948 (2018).
- Sourdon, J., Lewsey, S. C., Schär, M., Weiss, R. G. Measuring myocardial energetics with cardiovascular magnetic resonance spectroscopy. Heart Fail Clin. 17 (1), 149-156 (2021).
- Samuel, T. J., et al. Myocardial ATP depletion detected noninvasively predicts sudden cardiac death risk in patients with heart failure. JCI Insight. 7 (12), e157557(2022).
- Buchthal, S. D., et al. 31P-magnetic resonance spectroscopy studies of cardiac transplant patients at rest. J Cardiovasc Magn Reson. 2 (1), 51-56 (2000).
- Bernard, M., Kober, F., Caus, T. Assessing cardiac transplant viability with MRS. eMagRes. 4 (3), 627-633 (2015).
- Pla, M. M., et al. A porcine heterotopic heart transplantation protocol for delivery of therapeutics to a cardiac allograft. J Vis Exp. (180), e63114(2022).
- Schär, M., Kozerke, S., Fischer, S. E., Boesiger, P. Cardiac SSFP imaging at 3 Tesla. Magn Reson Med. 51 (4), 799-806 (2004).
- Naressi, A., Couturier, C., Castang, I., De Beer, R., Graveron-Demilly, D. Java-based graphical user interface for MRUI, a software package for quantitation of in vivo/medical magnetic resonance spectroscopy signals. Comput Biol Med. 31 (4), 269-286 (2001).
- Vanhamme, L., Van den Boogaart, A., Van Huffel, S. Improved method for accurate and efficient quantification of MRS data with use of prior knowledge. J Magn Reson. 129 (1), 35-43 (1997).
- Taylor, D. J., Bore, P. J., Styles, P., Gadian, D. G., Radda, G. K. Bioenergetics of intact human muscle: a 31P nuclear magnetic resonance study. Mol Biol Med. 1 (1), 77-94 (1983).
- Kothari, P. Ex vivo preservation of heart allografts-an overview of the current state. J Cardiovasc Dev Dis. 10 (3), 105(2023).
- Kober, F., Caus, T., Riberi, A., Le Fur, Y., Bernard, M. Time course of high-energy phosphate depletion during cold storage of human heart grafts using the Celsior solution. Transpl Int. 37, 12994(2024).
- Tsampasian, V., Cameron, D., Sobhan, R., Bazoukis, G., Vassiliou, V. S. Phosphorus magnetic resonance spectroscopy (31P MRS) and cardiovascular disease: the importance of energy. Medicina (Kaunas). 59 (1), 174(2023).
- Gupta, A. Cardiac 31P MR spectroscopy: development of the past five decades and future vision-will it be of diagnostic use in clinics. Heart Fail Rev. 28 (2), 485-532 (2023).
- Michel, S. G., et al. Preservation of donor hearts using hypothermic oxygenated perfusion. Ann Transplant. 19, 409-416 (2014).
- Caenegem, O. V., et al. Hypothermic continuous machine perfusion enables preservation of energy charge and functional recovery of heart grafts in an ex vivo model of donation following circulatory death. Eur J Cardiothorac Surg. 49 (5), 1348-1353 (2016).
- Spencer, B. L., et al. Extending heart preservation to 24 h with normothermic perfusion. Front Cardiovasc Med. 11, 1325169(2024).
- Iyer, A., et al. Normothermic ex vivo perfusion provides superior organ preservation and enables viability assessment of hearts from DCD donors. Am J Transplant. 15 (2), 371-380 (2015).
- Brouckaert, J., Dellgren, G., Wallinder, A., Rega, F. Non-ischaemic preservation of the donor heart in heart transplantation: protocol design and rationale for a randomised, controlled, multicentre clinical trial across eight European countries. BMJ Open. 13 (12), e073729(2023).
Access restricted. Please log in or start a trial to view this content.
Reprints and Permissions
This article has been published
Video Coming Soon