It is important to be alert for primary hepatic lymphoma (PHL) in patients with hepatocellular carcinoma (HCC) who display atypical clinical features and multiple lymphadenopathies. If lesions exhibit unexpected indocyanine green (ICG) enhancement during surgery, resection should be considered following a thorough evaluation.
Case Report
Primary Hepatic Lymphoma with Hepatocellular Carcinoma: A Case Report
35 views
⸱
September 11th, 2026
* These authors contributed equally
In This Article
Summary
Abstract
This case report highlights the diagnostic challenges associated with PHL and outlines corresponding diagnostic strategies, underscoring the importance of clinicians being vigilant for PHL in patients with HCC, particularly when clinical presentations and imaging features are atypical. Instead of making a decision based only on a positive ICG result, it is advised that clinicians thoroughly assess the features of the newly discovered lesions found through ICG imaging during the procedure, the patient's general condition, and the surgical risks before deciding whether to resect them. We conducted a retrospective analysis of a confirmed case of PHL complicated by HCC. indicates that even when HCC is suspected, the possibility of PHL should not be ruled out when diagnosing liver lesions; therefore, active screening is necessary. ICG imaging can serve as an adjunctive tool to improve the detection rate of lesions during surgery; however, its clinical value is limited for small-volume lesions that are not considered for surgical resection.
Introduction
Primary hepatic lymphoma (PHL) is an extremely rare extranodal lymphoma originating from hepatic lymphoid tissue or residual hematopoietic tissue1, accounting for less than 0.016% of all non-Hodgkin lymphomas2. Due to its diverse imaging manifestations and the lack of specific clinical symptoms, PHL is often misdiagnosed as hepatocellular carcinoma (HCC) or other liver mass lesions2,3. Most patients present with non-specific symptoms such as upper abdominal pain, fever, and weight loss, and common laboratory findings include elevated lactate dehydrogenase (LDH) and alkaline phosphatase (ALP) levels4,5.
The differential diagnosis between PHL and HCC has important clinical implications. HCC is the most common primary liver cancer worldwide. Both HCC and PHL may present on imaging as solitary liver lesions with arterial enhancement, but their treatment regimens are vastly different: HCC is primarily treated with surgical resection, interventional therapy, or targeted therapy, whereas PHL requires systemic chemotherapy6,7. A misdiagnosis can lead to unnecessary invasive treatments or delay the optimal treatment window. Although cases of coexisting PHL and HCC have been reported occasionally, the existing literature primarily focuses on pathological diagnosis, and there remains limited discussion regarding preoperative differential diagnosis strategies, comparisons of imaging features, and clinical decision-making pathways7,8,9.
In recent years, indocyanine green (ICG) fluorescence imaging has become increasingly widespread in liver surgery10. The principle behind this technique is that normal liver cells rapidly excrete ICG via the bile ducts after uptake through the organic anion transport polypeptide (OATP8), whereas tumor tissue retains ICG due to impaired bile excretion, creating a fluorescent contrast11. In HCC, well-differentiated cancer cells partially retain OATP8-mediated uptake but exhibit impaired excretion, resulting in “neoplastic fluorescence”; in contrast, PHL, as a tumor of the lymphohematopoietic system, lacks the hepatocyte-specific ability to take up ICG. Its imaging mechanism may rely on tumor compression of surrounding liver tissue, leading to delayed ICG excretion and the formation of characteristic “ring-shaped fluorescence”12,13.
The core value of ICG technology lies in its ability to detect occult lesions not identified by preoperative imaging. Studies have shown that ICG fluorescence imaging can detect microscopic lesions on the liver surface as small as 2 mm in diameter14. In this study, intraoperative ICG fluorescence imaging successfully identified a PHL lesion missed by conventional imaging, confirming its unique value in detecting rare liver tumors. Although ICG fluorescence imaging is highly sensitive, decisions regarding the resection of fluorescence-positive lesions during surgery should be based on a comprehensive assessment. Resection of typical fluorescence lesions may be considered, whereas the decision to resect atypical fluorescence lesions should be made only after careful evaluation. Additionally, in patients with liver masses accompanied by multiple enlarged lymph nodes, PHL should be included in the differential diagnosis.
This report presents a pathologically confirmed case of HCC coexisting with PHL, focusing on the value of ICG fluorescence imaging in detecting occult lesions and key points for differential diagnosis, to guide the diagnosis and management of similar rare cases.
Case Presentation:
This case analysis involves a 57-year-old male patient admitted to our hospital in July 2024 after a hepatic lesion was identified during routine physical examination. The patient remained asymptomatic, with no fever, chills, cardiovascular symptoms, or gastrointestinal complaints such as nausea, vomiting, or abdominal discomfort. The patient's medical history was notable for primary aldosteronism with secondary hypertension lasting one month, along with a 40-year history of heavy smoking (20 cigarettes/day) and chronic alcohol intake (60 g/day of ethanol).
Diagnosis, Assessment, and Plan:
Enhanced MRI (Figure 1A,B) shows a mass in the V/VIII sector of the liver, measuring approximately 45 mm × 42 mm × 50 mm; its morphological features are consistent with HCC. In addition, there is a mass in the left lateral lobe that does not show significant enhancement on the contrast-enhanced images; enhanced CT scan (Figure 2A,B) shows that the mass in the left lobe of the liver appeared identical to the liver parenchyma during both the venous and arterial phases, with no significant enhancement observed. This confirms the findings of the MRI examination and strongly suggests that the mass located in segments V/VIII of the liver is hepatocellular carcinoma. On physical examinations, the patient’s primary positive finding was mild tenderness in the right upper abdomen; no other significant abnormalities were observed. Laboratory examination results showed tumor markers: carcinoembryonic antigen (CEA) at 6.83 ng/mL and alpha-fetoprotein (AFP) at 6.89 ng/mL. Among liver function markers, alanine aminotransferase (ALT) was 23.9 IU/L, ALP was 110.3 IU/L, and LDH was within normal limits. Renal function parameters showed serum creatinine at 64 µmol/L and an estimated glomerular filtration rate (eGFR) of 119.59 mL/min/1.73 m2; all eight items in the infectious disease screening were negative. (Supplementary Table 1 summarizes the results of the above ancillary tests.)
Based on the above evidence, imaging examinations demonstrated a space-occupying lesion in segments V and VIII of the liver consistent with the characteristics of hepatocellular carcinoma (HCC). Given the patient’s good liver and kidney function, overall good health, and absence of contraindications for surgery, the patient underwent the surgery on August 21, 2024.
Protocol
The operation followed standard procedures and received ethics approval. This study was permitted by the Ethics Committee of Third Affiliated Hospital of Guangzhou Medical University (Approval No. of the Medical Ethics Committee: [2025] No. 038). Informed written consent was obtained from the patient. The research content and methods adhered to medical ethics norms and requirements. The reagents and equipment used in the study are listed in the Table of Materials.
1. Preoperative Preparation:
- Fasting and fluid restriction: Solid food was withheld for 8 h and clear liquids for 2 h before induction to reduce the risk of aspiration pneumonitis15.
- Mechanical bowel preparation: Beginning at 14:00 the day before surgery, 2000 mL of polyethylene glycol-electrolyte solution was ingested until the effluent was clear.
- Skin degreasing and disinfection: Two full-body showers were taken on the evening before surgery and again on the morning of surgery, with particular attention to the umbilicus; a sterile gown was donned in the morning.
- Fluorescent-contrast administration: Two days before surgery, 0.2 mg/kg of indocyanine green was injected intravenously by the ward nurse to ensure adequate near-infrared fluorescence imaging, with emergency resuscitation equipment readily available due to the risk of anaphylaxis16.
- Informed consent: The attending surgeon reiterated the extent of resection, risks of fluorescence navigation, and management of additional lesions; the patient or legal representative then signed the operative consent.
- Pre-entry checks: Removable dentures, watches, necklaces, earrings, and eyeglasses were removed; the bladder was emptied, and the patient was escorted into the restricted surgical zone.
2. Surgical Procedure:
- Anesthesia and positioning.
- General anesthesia with endotracheal intubation.
- Supine, legs apart, 20° reverse-Trendelenburg, 15° left tilt, no kidney bridge.
- Pneumoperitoneum and trocar placement.
- A 12 mm Hg pneumoperitoneum was created via a 1 cm supra-umbilical Veress needle, with intraperitoneal placement confirmed before insufflation to prevent extraperitoneal insufflation17.
- Five ports (5/12 mm) were inserted using a five-trocar technique and connected to a three-way stopcock and insufflation tubing.
- Fluorescence mapping and verification checkpoints: Both intraoperative verification checkpoints (segments V/VIII and segment IV) were prospectively defined prior to surgery based on preoperative imaging findings and were consistently applied during the procedure.
- First verification point (segments V/VIII): a 55 mm × 40 mm area of hypoechoic tissue was identified, consistent with the intense ICG fluorescence typical of HCC. The tissue was firm in consistency. This area was marked with an ultrasonic scalpel for subsequent resection.
- Second verification point (segment IV): a 20 mm × 30 mm area of abnormal fluorescence was incidentally detected, with signal intensity higher than that of the surrounding liver parenchyma, suggesting that the nature of this lesion differs from that of the primary lesion; during surgery, the area was found to be firm and hard to the touch, and it was marked with an ultrasonic scalpel for subsequent resection.
- Visibility criteria: Lesions must be clearly visible to the naked eye in fluorescence mode, with a minimum detectable lesion diameter of ≥20 mm.
- Hepatic inflow control.
- The hepatoduodenal ligament was dissected and encircled with a tape.
- Intermittent Pringle maneuver: 15 min clamp / 5 min release cycles.
- Parenchymal transection.
- Liver parenchyma was sequentially divided with an ultrasonic scalpel plus bipolar cautery, and the liver parenchyma and intrahepatic vessels were transected using a stapler (staple size: 35 mm × 2.5 mm).
- Structures ≥ 2 mm were clamped and ligated with 3-0 suture; those < 2 mm were clipped.
- Specimen retrieval.
- The segment 5/8 specimen was placed in a 130 mL bag, the segment 4 specimen in a 60 mL bag.
- Both were extracted intact through the 12 mm port to avoid wound seeding.
- Raw surface management: Active bleeding was controlled with bipolar electrocautery; larger breaches were closed with barbed sutures and sealed with fibrin glue and absorbable vascular sealing medical adhesive (model: 2 mL).
- Drainage and closure.
- A drainage tube was positioned in the right subhepatic space, and a drainage tube at the segment 4 bed; both exited the right lateral abdominal wall and were secured with 7-0 silk.
- After the instrument and sponge were counted to confirm accuracy, the fascial defects were closed, and the skin was approximated subcutaneously.
- Surgical Parameters Record.
- Total operative time: 300 min.
- Intraoperative blood loss: 200 mL.
- Blood transfusion status: None.
3. Postoperative Care:
- Recovery monitoring.
- 1 h observation in the PACU; returned to the ward when the Steward score ≥4.
- Continuous ECG and SpO₂ monitored for 24 h.
- Drain management.
- Both drains were connected to sterile closed bags; daily output and characteristics were recorded.
- Removal criteria: < 20 mL/day of non-bilious fluid. The 22-Fr drain was removed on POD 5, the 14-Fr drain on POD 6.
- Early mobilization and diet.
- Turned in bed at 6 h; ambulated within 24 h.
- Diet was advanced from clear to full liquids to regular food within 48 h, supplemented with 500 kcal/day of enteral nutrition.
- Laboratory follow-up.
- CBC and liver/renal panels were checked on POD 1, 3, and 5.
- If ALT/AST < 100 U/L, TBil normal, and no infection, discharge work-up began.
- Discharge criteria.
- Afebrile ≥ 72 h, dry incisions, both drains were removed, independent ambulation.
- Discharged on POD 10; sutures removed in the outpatient clinic 7 days later, with medical oncology referral for adjuvant chemotherapy.
4. Postoperative Chemotherapy Regimen:
- First cycle of chemotherapy.
- Day 1: Prior to chemotherapy, verify baseline complete blood count and liver function, as severe neutropenia and diarrhea are dose-limiting toxicities requiring treatment withholding18; then initial catheter-guided peritoneal and hepatic artery angiography + transcatheter arterial chemoembolization (TACE) + hepatic artery catheterization to establish a hepatic artery access route; On the same day, 130 mg of oxaliplatin, 0.65 g of fluorouracil, and 400 mg of calcium folinate were infused via the hepatic artery catheter, and a 48 h continuous infusion of 3.6 g of fluorouracil was initiated.
- Day 2: Continued infusion of fluorouracil via the hepatic artery catheter, completing the total 48 h infusion volume.
- Day 3: Systemic chemotherapy with irinotecan 275 mg administered via peripheral vein.
- Day 4: Sintilimab was administered via a peripheral vein. The interval between cycles was approximately 1 month.
- Second chemotherapy cycle: The complete regimen of the first chemotherapy cycle was repeated.
5. Postoperative CT Follow-up: A CT scan was performed 8 months after surgery.
Results
The protocol was executed as planned. The following results correspond to each major protocol step. Intraoperative fluorescence imaging identified a firm mass measuring 20 x 30 mm at the periphery of the left outer lobe of the liver (Figure 3A,B; see Supplementary Video 1 for the intraoperative procedure). Additionally, a tumor lesion was identified in liver segment V/VIII and was also resected using intraoperative fluorescence guidance. Pathology proved the lesion in liver segments V/VIII to be a moderately differentiated hepatocellular carcinoma, with dimensions of approximately 50 mm x 40 mm x 40 mm (Figure 4A,B,C). Histological types consist of trabecular, which comprises approximately 70%, and pseudo-glandular, which accounts for approximately 30%. Notably, no satellite nodules, microvascular invasion, or nerve invasion were observed. Immunohistochemistry: AFP (−), CD10 (−), CD34 (suggesting capillarization of hepatic sinusoids), GS (focal weak +), GPC-3 (+), HEP-1 (+), HBsAg (−), and Ki-67 index of 60%. A biopsy of one peripheral lymph node showed reactive changes, with no evidence of malignancy (0/1). The margin of the gallbladder neck had no malignancy. The tumor pathological stage was pT1bN0M0.
In the pathological examination results of the extra mass in the left lateral lobe (Figure 5A,B,C), the lymphocytes showed nodular to layered hyperplasia. The lymphocytes were uniformly small. Based on immunohistochemistry findings, the primary concern was indolent B-cell lymphoma/leukemia in the liver. Immunohistochemistry: CD21 (sparse FDC networks +), CD20/CD19/CD79a (diffuse B-cell positivity), CD23 (focal positivity), CD5 (diffuse positivity), CD3/CD43 (T-cell positivity), Kappa (intense), Lambda (scattered positivity), Ki-67 (5% positivity), CD38 (scattered plasma cells +), Cyclin D1 (negative), BCL-2 (positive).
To determine the source of the PHL, FDG-PET imaging demonstrated no increased FDG uptake, and there was no evidence of lymphadenopathy or splenomegaly. The bone marrow puncture examination (Supplementary Figure 1A,B,C) showed that the three lineages of hematopoietic cells (erythroid, myeloid, and megakaryocytic) were actively proliferating, and no evidence of lymphoma cell infiltration or clonal proliferation was observed. B-cell gene rearrangement testing and lymphocyte immunophenotyping on bone marrow aspirate (Supplementary Figure 2 and Supplementary Figure 3A,B) showed no abnormality.
Postoperative drainage outcomes met predefined removal criteria: daily output was < 20 mL and fluids were non-bilious in both drains, allowing removal on postoperative day 5 (22-Fr drain) and day 6 (14-Fr drain) as per protocol.
Postoperative recovery milestones were achieved as per protocol: the patient turned in bed at 6 h, ambulated within 24 h, and advanced diet from clear liquids to regular food within 48 h.
Postoperative CT (Figure 6) showed multiple new hepatic nodules and enlarged confluent hilar lymph nodes with ring enhancement, consistent with tumor metastases. A suspected portal vein tumor thrombus was also noted. These findings indicated a poor prognosis.
Based on these findings, the patient diagnosed with PHL in segment IV and HCC in segments V/VIII. The patient had a poor prognosis and died approximately one year after surgery.
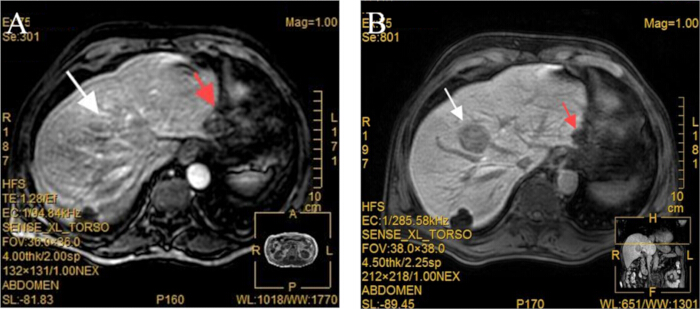
Figure 1: Liver MRI findings in arterial and portal venous phases. (A) The arterial phase image shows a lesion in segments V/VIII (white arrow) that demonstrates arterial phase hyperenhancement. A separate lesion in the left outer lobe (red arrow) shows no enhancement. (B) The portal venous phase image demonstrates rapid washout of the segment V/VIII lesion (white arrow). The left outer lobe lesion (red arrow) remains non-enhancing. Several mildly enlarged lymph nodes were observed in the hilar region and retroperitoneal space. Please click here to view a larger version of this figure.
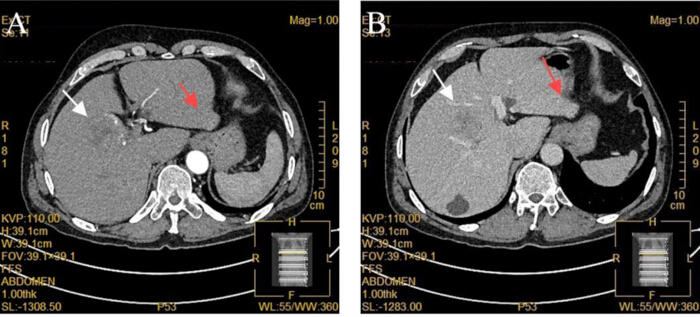
Figure 2: Computed tomography (CT) of the patient. (A) The arterial phase image shows a lesion in segments V/VIII (white arrow) that demonstrates arterial phase hyperenhancement. A separate lesion in the left outer lobe (red arrow) shows no significant enhancement. (B) The portal venous phase image demonstrates rapid washout of the segment V/VIII lesion (white arrow). The left outer lobe lesion (red arrow) remains no significant during the portal venous phase. Please click here to view a larger version of this figure.
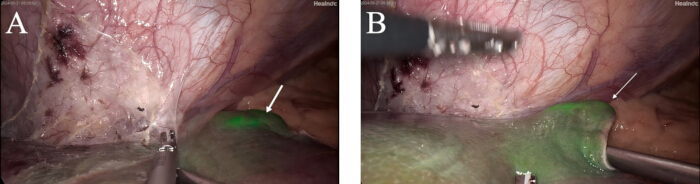
Figure 3: Intraoperative ICG fluorescence imaging. (A) Green fluorescence signals are visible in the surgical field (white arrows). (B) Upon exploration of the fluorescent area, a firm mass is identified at the margin of the left lateral lobe of the liver, corresponding to the fluorescent signal. Please click here to view a larger version of this figure.
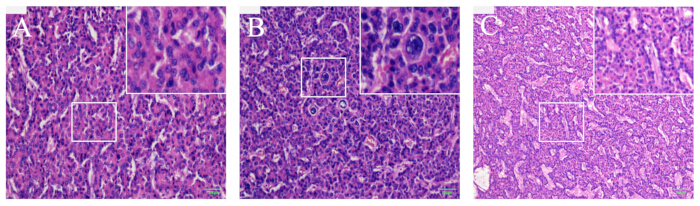
Figure 4: Pathological examination of the tumors in segments V/VIII of the liver as well as the gallbladder. (A) High-power HE staining of the segment V/VIII liver mass shows markedly atypical tumor cells with enlarged hyperchromatic nuclei, prominent nucleoli, and pathological mitotic figures. (B) The mass was diagnosed as moderately to poorly differentiated HCC with fine-beam (70%) and pseudo-glandular (30%) patterns. (C) The liver tissue showed no satellite nodules, nor was there any microvascular or neural involvement. Scale bars are approximate and based on estimated magnification. Please click here to view a larger version of this figure.
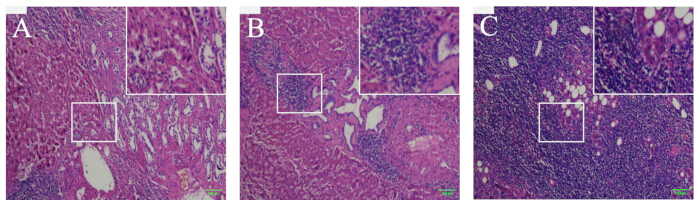
Figure 5: Pathological examination of the additional mass in the left lateral lobe of the liver. (A) HE staining of the liver tissue from the left lateral lobe mass showing the periportal hepatic parenchyma with adjacent bile duct structures and lymphocytic infiltrates. (B) The portal area found multiple clusters of lymphocytes, ranging in size from small nodules to small patches. (C) The lymphocytes in the lymphocytic clusters are small, with a mild morphology, and show no obvious atypia. Scale bars are approximate and based on estimated magnification. Please click here to view a larger version of this figure.
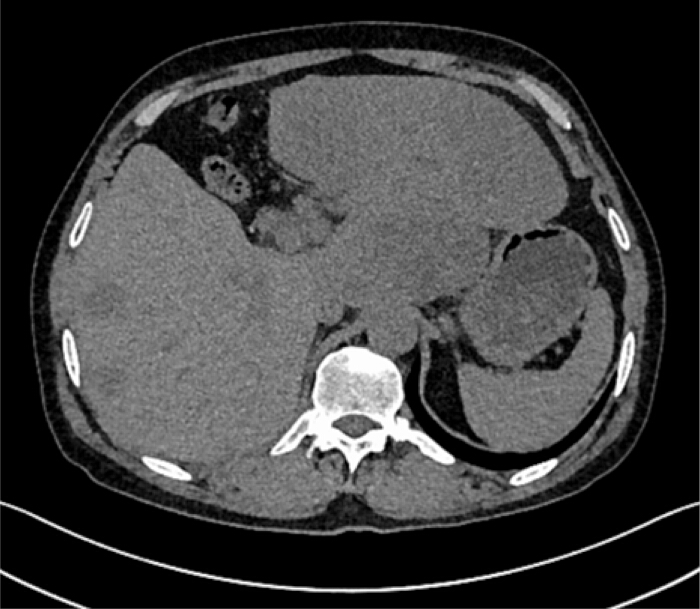
Figure 6: Postoperative CT scans revealed multiple new nodules within the liver, as well as enlarged, fused lymph nodes in the portal vein region and retroperitoneum with ring-like enhancement, suggesting tumor metastasis and a poor prognosis. Please click here to view a larger version of this figure.
Supplementary Figure 1: Bone marrow puncture results. (A) Microscopic examination of the bone marrow aspirate revealed that the hematopoietic zone accounted for approximately 40%; the granulocyte-to-red blood cell ratio was decreased; granulocytes were present at all stages of development (predominantly mature cells); and the erythroid series consisted mainly of mid- and late-stage normoblasts. (B) The number of megakaryocytes is adequate, and they are primarily segmented. (C) Focal lymphocytic proliferation was observed; these lymphocytes were small in size, had indistinct morphological features, and showed no significant atypia. Scale bars are approximate and based on estimated magnification.Please click here to download this file.
Supplementary Figure 2: Lymphocyte immunophenotyping on bone marrow aspirate. Bone marrow flow cytometry showed about 7.1% of CD5-positive, CD10-negative mature monoclonal B cells.Please click here to download this file.
Supplementary Figure 3: B-cell gene rearrangement test results from bone marrow aspirate. (A) IGK gene Vκ-Jκ region: a monoclonal rearrangement is observed at 284 bp; (B) IGK gene Vκ-Kde+intron-Kde region: monoclonal rearrangements are observed at 279 bp and 231 bp.Please click here to download this file.
Supplementary Video 1: ICG Fluorescence-Guided Laparoscopic Hepatectomy. This video demonstrates the key steps of laparoscopic liver resection guided by ICG fluorescence imaging, including fluorescence signal identification, marking of lesion boundaries, and precise resection. Total duration: 11 min and 33 s.Please click here to download this file.
Supplementary Table 1: Auxiliary ExaminationPlease click here to download this file.
Discussion
PHL is extremely rare2. The diagnosis of PHL requires the fulfillment of three criteria: (1) clinical manifestations of liver dysfunction; (2) absence of palpable lymphadenopathy and radiological evidence of distant lymphadenopathy; (3) absence of leukemia in the peripheral blood smear19. It can occur at any age, with a male-to-female ratio of approximately 2–3:1. The pathogenesis of PHL remains elusive, but it is associated with infections including EBV (Epstein-Barr virus), HCV (Hepatitis C virus), HIV (Human Immunodeficiency Virus), and HTLV (Human T-cell Lymphotropic Virus), liver cirrhosis, systemic lupus erythematosus, and immunosuppressive therapy. Notably, HCV infection is particularly associated with PHL20. Studies suggest that the prognosis for patients with PHL is more favorable than previously reported, with a 5-year survival rate of 77–83%21. Poor prognostic factors include extensive liver infiltration, a high proliferation index, advanced age, systemic symptoms, large tumor volume, unfavorable histological subtypes, elevated LDH levels, liver cirrhosis, and increased β2-microglobulin levels22.
PHL exhibits various imaging features. These features are observed on CT (computed tomography) or MRI (magnetic resonance imaging) and include: (1) Solitary (homogeneous or heterogeneous) masses: on CT scans, these exhibit uniform low density. Most lesions demonstrate minimal or no enhancement in all phases, and on contrast-enhanced CT, they appear as relatively low-density masses. (2) Multiple lesions, with or without distinct lesions, may present as a miliary pattern characterized by numerous small discrete nodules. (3) Diffuse infiltration (with or without hepatomegaly): Tumor cell infiltration into portal venous and sinusoids is rare in PHL. Once it occurs, it may indicate a poor prognosis for the patient. (4) Periportal masses: this presentation appears as a soft tissue "mantle" around the portal vein or an ill-defined mass. (5) Rare forms lacking unique imaging modalities, such as masses in the gastric-hepatic region with minimal focal hepatic infiltration and a dominant extrahepatic component, infiltrating the pyloric area of the stomach23,24.
PHL exhibits nonspecific symptoms and requires combining results from multiple indices for comprehensive evaluation. The literature recommends that patients with liver nodules that are FDG-PET-positive and have elevated LDH levels undergo preoperative biopsy to rule out PHL22. However, in this case, the findings were exactly the opposite: FDG-PET showed negative uptake, and serum LDH levels were normal, which did not align with the typical metabolic presentation of PHL. This discrepancy suggests that even in the absence of the typical FDG-PET and LDH markers, PHL should still be considered in cases with multiple liver lesions, normal AFP levels, atypical imaging findings, and hilar lymphadenopathy, and a preoperative biopsy should be actively pursued. A recent study underscores the effectiveness of ultrasound in diagnosing isolated small hepatic lymphomas, highlighting its pivotal role in improving patient care and outcomes25. However, the patient did not present typical clinical manifestations such as nocturnal fever or weight loss; physical examination revealed only mild tenderness in the right upper abdomen. The CT and MRI findings were nonspecific, suggesting HCC in segments V and VIII of the liver. Furthermore, since the patient’s primary purpose for this visit was to address the HCC mass, we did not perform preoperative tests related to PHL, such as a biopsy of the lesion. Nevertheless, the nature of this mass remains unclear, which is a key concern for us. This diagnostic challenge is not unique to this case2. Our protocol, which combines preoperative ICG administration (0.2 mg/kg two days prior to surgery), a two-tiered intraoperative verification process, and decision-making protocols for unexpected fluorescent lesions, can be adapted by other hepatobiliary surgery centers facing similar situations.
In this case, ICG fluorescence imaging demonstrated clear value for surgical navigation. Compared with standard practice, our protocol had four modifications: extended ICG administration to 48 h, introduced two-tiered verification checkpoints, proposed a three-tier decision algorithm for atypical lesions (resect/evaluate/observe), and used ward-based preoperative ICG dosing instead of operating room administration. Following the use of ICG, a lesion in Segment IV with a minimum diameter of 20 mm was successfully detected intraoperatively; the nature of this lesion could not be clearly determined on either the preoperative CT or MRI scans. Key steps included: (1) administration 2 days before surgery to ensure adequate uptake by the liver parenchyma; (2) Intraoperative near-infrared imaging to identify differences in fluorescence signals (absence of fluorescence in segments V and VIII vs. abnormal fluorescence concentration in segment IV); (3) Real-time marking to guide precise resection.
However, ICG fluorescence imaging has limitations in this case. First, the fluorescence signal characteristics of PHL and HCC are not absolute, and the “typical” pattern observed in this case may not be universally applicable. Second, ICG cannot distinguish between benign and malignant tumors; the final diagnosis of the segment IV lesion still relies on postoperative paraffin-embedded pathology. Furthermore, in patients with cirrhosis or hepatic insufficiency, abnormal ICG metabolism may result in excessively strong or weak background fluorescence, impairing lesion identification. Troubleshooting strategies include adjusting the administration timing, switching between near-infrared and white light modes for comparison, and combining the findings with intraoperative ultrasound verification26.
The use of ICG in this case strictly followed the recommendations outlined in the guidelines: (1) Time window: Administer a standard dose of ICG intravenously 2 days before surgery; the timing is appropriate.; (2) Dose standardization: 0.2 mg·kg⁻1 is the standard dose for balancing imaging performance and background interference; (3) Multimodal fusion: Combining preoperative CT/MRI localization with intraoperative real-time fluorescence navigation achieves a "triad of imaging, anatomy, and pathology"; (4) Educational value: Differences in fluorescence signals provide young surgeons with an intuitive correlation between pathology and imaging16.
As illustrated by the hierarchical validation checkpoints described in Protocol 2.3, this example confirms the typical HCC signal at the “first verification point” and identifies an abnormal lesion at the “second verification point”, demonstrating the feasibility of the standardized process.
Compared with conventional intraoperative ultrasound (IOUS), ICG fluorescence imaging has comparable sensitivity for detecting superficial lesions (< 10 mm), but its penetration depth is limited for deep lesions (> 8 cm)27,28. In this case, both lesions were located near the liver surface, resulting in good ICG imaging. For patients with deep lesions or those with a history of cirrhosis, it is recommended to use ICG in combination with IUS to improve detection rates and reduce false negatives.
Unexpected lesions with typical fluorescence patterns should be resected immediately. Pathological studies have confirmed that parenchymal fluorescence is a characteristic feature of hepatocellular carcinoma. A systematic review showed that the overall detection rate of liver tumors using ICG fluorescence imaging reached 87.4%10. Regardless of whether such lesions are visible on preoperative imaging, they should be considered suspicious for malignancy and completely resected.
For incidental lesions with atypical fluorescence patterns, a decision regarding resection should be made only after careful evaluation. Atypical fluorescence patterns include annular fluorescence and faint, mottled signals. Approximately 10.5% of ICG-enhancing lesions are ultimately pathologically confirmed as false positives10. When encountering such lesions, intraoperative ultrasound should be used for further evaluation, while simultaneously reviewing the patient’s tumor markers and lymph node status. Although the ring-shaped fluorescence pattern is observed in PHL, it is more characteristic of liver metastases from colorectal cancer. A study by Piccolo et al. found that all ring-shaped fluorescent lesions were pathologically confirmed to be metastatic tumors29. When staining does not match expectations, it is recommended to make full use of the information provided by ICG fluorescence staining rather than switching directly to white light mode30.
For unexpected lesions with weak fluorescence signals, deep locations, or proximity to critical vascular structures, a watch-and-wait approach may be preferred. Due to the limited tissue penetration depth of ICG fluorescence, the fluorescence signal from deep lesions is often weak, making it difficult to determine their clinical significance in real time. Case reports have indicated that some intraoperative fluorescent areas were pathologically confirmed to be nonspecific fibrous tissue with no evidence of malignancy10,31. Such lesions may be left in situ, but they should be closely monitored in postoperative imaging, and the interval between follow-up examinations should be shortened.
In this case, we opted to resect the mass primarily based on its high-fluorescence appearance, its isolated and superficial location, and the exclusion of typical primary hepatic lymphoma through ancillary tests. However, it must be acknowledged that direct resection is not the most rigorous approach; a standard decision-making process should prioritize a thorough preoperative or intraoperative evaluation.
Future research directions include: (1) establishing a database of PHL-specific ICG fluorescence signals to clarify the imaging characteristics of different pathological subtypes; (2) exploring the use of ICG in combination with other targeted contrast agents to improve the accuracy of differential diagnosis; (3) Developing an AI-assisted fluorescence image analysis system to reduce variability in subjective interpretation; (4) Conducting a prospective study on the impact of ICG-guided biopsy on the preoperative diagnosis rate of PHL.
PHL often presents with clinical manifestations and imaging features, and the risk for misdiagnosis may be increased. Accurate identification of liver lesions is essential and should incorporate both clinical manifestations and laboratory test results. Intraoperative ICG fluorescence imaging has a role in reducing the risk of misdiagnosis. In this case, it successfully detected a 20 mm lesion that had not been identified on preoperative imaging; the two lesions exhibited distinct fluorescence signal characteristics, and postoperative pathology confirmed them to be HCC and PHL, respectively. Therefore, this case provides a transferable framework for addressing similar diagnostic dilemmas in hepatobiliary surgery; prospective, multicenter validation is necessary to further establish its external validity.
Disclosures
All authors declared that there are no conflicts of interest.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Absorbable, regenerated oxidized cellulose hemostatic nonwoven fabric | Ethicon LLC | 2082 | |
| bipolar coagulation | Covidien Ltd. | LF1537 | |
| connecting needle | Zhejiang Sujia Medical Devices Co., Ltd. | Not applicable | |
| connecting pipe | Zhejiang Sujia Medical Devices Co., Ltd. | VL-1.4×500 | |
| endoscope clip | Micro-Tech (Nanjing) Co., Ltd. | ROCC-D-26-195 | |
| fluorescent yarn | Not applicable | Not applicable | |
| drainage tube | Hubei Kangquan Medical Technology Co., Ltd.; Ethicon Endo-Surqery, LLC | F22, F14 | |
| ligating clip | Guona Technology | J10-5 | |
| retrieval bag 130ml | Qingdao Zhonghui Shengxi Bioengineering Co., Ltd. | ZHQWDB-130 | |
| retrieval bag 60ml | Qingdao Zhonghui Shengxi Bioengineering Co., Ltd. | ZHQWDB-60 | |
| absorbable vascular sealing medical adhesive | Saixes Biotechnology Co., Ltd. | 2 mL | |
| stapler35/nail warehouse35*2.5 | Ethicon Endo-Surqery, LLC | CDH35A / VASECR35 | |
| suture | Ethicon, LLC; Covidien LP | PDP148, VCP1603, W8761, VLOCL,CL923 | |
| three-way connector | Hangzhou Jingling Medical Equipment Co., Ltd. | ST02 | |
| ultrasound knife | Houkai (Tianjin) Medical Technology Co., Ltd. | USE36 |
References
- Qiu MJ, Fang XF, Huang ZZ, Li QT, Wang MM, Jiang X, et al. Prognosis of primary hepatic lymphoma: a US population-based analysis. Transl Oncol. 2021;14(1):100931.
- Bohlok A, De Grez T, Bouazza F, De Wind R, El-Khoury M, Repullo D, et al. Primary hepatic lymphoma mimicking a hepatocellular carcinoma in a cirrhotic patient: case report and systematic review of the literature. Case Rep Surg. 2018;2018:9183717.
- Choi WT, Gill RM. Hepatic lymphoma diagnosis. Surg Pathol Clin. 2018;11(2):389-402.
- Lei KI, Chow JH, Johnson PJ. Aggressive primary hepatic lymphoma in Chinese patients: presentation, pathologic features, and outcome. Cancer. 1995;76(8):1336-43.
- Noronha V, Shafi NQ, Obando JA, Kummar S. Primary non-Hodgkin's lymphoma of the liver. Crit Rev Oncol Hematol. 2005;53(3):199-207.
- Zhang Y, Cui J, Ye Z, Li X. CT and MR imaging characteristics of primary hepatic lymphoma. Discov Oncol. 2024;15(1):428.
- Lee MH, Lin YC, Cheng HT, Chuang WY, Huang HC, Kao HW. Coexistence of hepatoma with mantle cell lymphoma in a hepatitis B carrier. World J Gastroenterol. 2015;21(45):12981-6.
- Heidecke S, Stippel DL, Hoelscher AH, Wedemeyer I, Dienes HP, Drebber U. Simultaneous occurrence of a hepatocellular carcinoma and a hepatic non-Hodgkin's lymphoma infiltration. World J Hepatol. 2010;2(6):246-50.
- Kumar T, Kaur H, Singh S, Vemulakonda LA, Bhargava R. Primary hepatocellular carcinoma developing within a B-cell primary hepatic lymphoma in a hepatitis C positive patient. Cureus. 2025;17(7):e88274.
- Avella P, Spiezia S, Rotondo M, Cappuccio M, Scacchi A, Inglese G, et al. Real-time navigation in liver surgery through indocyanine green fluorescence: an updated analysis of worldwide protocols and applications. Cancers (Basel). 2025;17(5):872.
- Ibis C, Albayrak D, Sahiner T, Soytas Y, Gurtekin B, Sivrikoz N. Value of preoperative indocyanine green clearance test for predicting post-hepatectomy liver failure in noncirrhotic patients. Med Sci Monit. 2017;23:4973-80.
- Yu F, Yin S, Zhu J, Sun K. Research landscape of photodynamic therapy for hepatocellular carcinoma: hotspots and prospects from 2012 to 2025. Hereditas. 2025;162(1):174.
- Morales-Conde S, Licardie E, Alarcón I, Balla A. Indocyanine green (ICG) fluorescence guide for the use and indications in general surgery: recommendations based on the descriptive review of the literature and the analysis of experience. Cir Esp (Engl Ed). 2022;100(9):534-54.
- Xiao T, Chen D, Peng L, Li Z, Pan W, Dong Y, et al. Fluorescence-guided surgery for hepatocellular carcinoma: from clinical practice to laboratories. J Clin Transl Hepatol. 2025;13(3):216-32.
- American Society of Anesthesiologists Task Force on Preoperative Fasting and the Use of Pharmacologic Agents to Reduce the Risk of Pulmonary Aspiration. Practice guidelines for preoperative fasting and the use of pharmacologic agents to reduce the risk of pulmonary aspiration: application to healthy patients undergoing elective procedures: an updated report. Anesthesiology. 2017;126(3):376-93.
- Liver Surgery Committee of the Surgical Surgeons Branch CMDA. Chinese expert consensus on the application of indocyanine green fluorescence imaging in hepatic surgery: 2023 edition. Chinese Journal of Practical Surgery. 2023;43(4):371-83.
- Arunakumari PSP, Simpson P, Naaem S, Sundararajan S. Veress needle entry: tips and tricks for residents. Annals of Minimal Access Surgery & Allied Science. 2025;1(2):101-4.
- Lambert A, Gavoille C, Conroy T. Current status on the place of FOLFIRINOX in metastatic pancreatic cancer and future directions. Ther Adv Gastroenterol. 2017;10(8):631-45.
- Taiji R, Marugami N, Marugami A, Itoh T, Shimizu S, Nakano R, et al. Multimodality imaging of primary hepatic lymphoma: a case report and a literature review. Diagnostics (Basel). 2024;14(3):306.
- Mehta N, Jayapal L, Goneppanavar M, Nelamangala Ramakrishnaiah VP. Primary hepatic lymphoma: a rare case report. JGH Open. 2019;3(3):261-3.
- Ugurluer G, Miller RC, Li Y, Thariat J, Ghadjar P, Schick U, et al. Primary hepatic lymphoma: a retrospective, multicenter Rare Cancer Network study. Rare Tumors. 2016;8(3):6502.
- Dantas E, Santos J, Coelho M, Sequeira C, Santos I, Cardoso C, et al. Primary hepatic lymphoma in a patient with cirrhosis: a case report. J Med Case Rep. 2020;14(1):168.
- BS P, Amina N, Anand R, Pathania OP. An unusual presentation of primary hepatic lymphoma. J Gastrointest Abdom Radiol. 2022;5(3):209-12.
- Alves AMA, Torres US, Velloni FG, Ribeiro BJ, Tiferes DA, D'Ippolito G. The many faces of primary and secondary hepatic lymphoma: imaging manifestations and diagnostic approach. Radiol Bras. 2019;52(5):325-30.
- Tang C, Zhang H, Tian M, Peng Y. Contrast-enhanced ultrasound findings of primary hepatic non-Hodgkin's lymphoma: a case report. Front Oncol. 2024;14:1380392.
- Ishizawa T, Fukushima N, Shibahara J, Masuda K, Tamura S, Aoki T, et al. Real-time identification of liver cancers by using indocyanine green fluorescent imaging. Cancer. 2009;115(11):2491-504.
- Hu M, Chen Z, Xu D, Zhang Y, Song G, Huang H, et al. Efficacy and safety of indocyanine green fluorescence navigation versus conventional laparoscopic hepatectomy for hepatocellular carcinoma: a systematic review and meta-analysis. Surg Endosc. 2025;39(3):1681-95.
- Kose E, Kahramangil B, Aydin H, Donmez M, Takahashi H, Acevedo-Moreno LA, et al. A comparison of indocyanine green fluorescence and laparoscopic ultrasound for detection of liver tumors. HPB (Oxford). 2020;22(5):764-9.
- Piccolo G, Barabino M, Ghilardi G, Masserano R, Lecchi F, Piozzi GN, et al. Detection and real-time surgical assessment of colorectal liver metastases using near-infrared fluorescence imaging during laparoscopic and robotic-assisted resections. Cancers (Basel). 2024;16(9):1641.
- Wang X. Unexpected fluorescent staining during laparoscopic anatomical hepatectomy and countermeasures. Chinese Journal of Practical Surgery. 2022;42(9):1001-4.
- Wakabayashi T, Cacciaguerra AB, Abe Y, Bona ED, Nicolini D, Mocchegiani F, et al. Indocyanine green fluorescence navigation in liver surgery: a systematic review on dose and timing of administration. Ann Surg. 2022;275(6):1025-34.