This protocol describes a two-phase surgical method to create a large, resealable, dura-sparing cranial window in mice. This technique enables chronic, multi-modal electrophysiological recordings from distributed, deep-brain networks, such as the Default Mode Network, over several weeks.
Method Article
Surgical Protocol for a Large, Resealable Cranial Window Enabling Longitudinal, Multi-Modal Electrophysiology Recordings of Mouse Default Mode Network
In This Article
Summary
Abstract
The default mode network (DMN) is a central, large-scale brain network implicated in a range of cognitive functions and neuropsychiatric disorders, such as major depressive disorder (MDD). Studying the DMN's complex dynamics in animal models provides invaluable insights into its function in both healthy and pathological states. However, performing stable, long-term, large-scale electrophysiological recordings from the multiple deep and distributed nodes of the DMN in awake, behaving mice remains a significant challenge.
Here, a novel two-phase surgical protocol is presented to create a large (4 mm × 7.6 mm), durable, and resealable cranial window in mice. The procedure is designed to preserve the integrity of the dura mater, which is paramount for long-term brain health and recording stability.
This window enables simultaneous, repeated, longitudinal recordings from over 1,000 electrodes by combining surface-level micro-electrocorticography (µECoG) with two high-density intracranial electrode probes, providing unprecedented access to the DMN. This technique provides a robust platform for multi-modal, multi-scale interrogation of network-wide electrophysiological dynamics over several weeks, opening new avenues for investigating the neuroplastic changes underlying the pathophysiology of brain disorders and for evaluating the chronic effects of novel therapeutics.
Introduction
The Default Mode Network (DMN) was first identified in human brain imaging studies as a constellation of regions consistently suppressed during externally oriented, attention-demanding tasks1. It is now considered to be a fundamental large-scale network supporting internally oriented cognitive processes, such as self-referential thought, autobiographical memory, and planning of future events2,3. In humans, the canonical DMN comprises a set of anatomically connected core regions, including the medial prefrontal cortex (mPFC), posterior cingulate cortex (PCC), inferior parietal lobule (IPL), and the hippocampal formation4. Dysfunction within this network is a key feature of several neuropsychiatric disorders. In major depressive disorder (MDD), the DMN commonly exhibits hyperactivity and altered patterns of functional connectivity, which are thought to underlie core symptoms of MDD, such as rumination and negative self-image5,6.
To study the cellular and circuit mechanisms driving DMN dysfunction, robust animal models are indispensable. A homologous DMN has been reliably identified in rodents, consisting of comparable brain regions such as the mPFC, cingulate cortex, and retrosplenial cortex (RSP), thereby validating the mouse as a translationally relevant model for mechanistic investigation7,8. Furthermore, chronic stress, a key factor in depression, has been shown to alter DMN connectivity in rodents in a manner similar to that observed in human MDD patients9.
Understanding the neuroplastic changes that occur in disease states or in response to chronic therapeutic interventions require longitudinal observation of neural activity, since a single recording session cannot capture the dynamic adaptation of neural circuits over time10. In vivo electrophysiology provides the millisecond-scale temporal resolution required to study neural oscillations and synchrony in the local field potential (LFP). LFP exhibits the summed extracellular signal reflecting synchronized synaptic activity of local neuronal populations, which are the fundamental substrates of network communication11,12. However, performing chronic, large-scale electrophysiological recordings in awake mice remains technically demanding. Conventional chronic cranial windows were developed for optical imaging in the awake mouse and remain the standard preparation for that purpose, where their typical single-hemisphere footprint and transparent glass coverslip are optimal for the intended readout13. They were not, however, designed for awake multi-site electrophysiology, so the working area and the optical interface preclude simultaneous high-density recording from the distributed bilateral nodes of a network such as the DMN14. Chronic electrode implants, in turn, enable longitudinal recordings but elicit progressive foreign-body encapsulation and glial scarring around the permanently positioned shank, reducing signal quality over time15,16.
The two-phase surgical procedure described here directly addresses these limitations. It produces a large, resealable cranial window closed between sessions by a passive polydimethylsiloxane (PDMS) membrane, silicone sealant, and a 3D-printed cap permitting repeated non-terminal insertion of µECoG grids for mesoscale LFP recordings together with multiple high-density intracranial electrode probes for microscale, laminar-resolved single-unit and LFP activity17,18. In contrast to prior chronic approaches, which either rely on permanently implanted electrode arrays that accumulate glial encapsulation of the electrodes over time or require terminal acute craniotomies that preclude longitudinal designs, the window described here preserves an intact dura and avoids permanent foreign-body contact15,16,18. Furthermore, in a validation cohort in which the cranial window was reopened three times (post-operative days 0, 21, 22) without electrophysiological recording, quantitative immunoreactivity of glial fibrillary acidic protein (GFAP) and ionized calcium-binding adapter molecule 1 (IBA1) did not differ significantly from non-surgical controls, suggesting low astrogliosis and microgliosis under the repeated-opening schedule used here. The method is particularly suited to longitudinal, multi-site recordings of distributed cortical networks, including the DMN, combined with laminar high-density intracranial electrode probe access to deep structures in awake head-fixed mice. Its main operational constraints are the microsurgical expertise required for reliable dura-sparing bone-flap removal and its incompatibility with freely moving recordings, since the high-density intracranial electrode probes require head-fixation.
Protocol
All animal experiments were approved by the national Animal Experiment Board in Finland (license number: ESACI/40845/2022) and experiments were conducted in compliance with the directive 2010/63/EU of the European Parliament regarding the protection of animal use for scientific purposes, and with the national guidelines for the care and use of laboratory animals.
NOTE: All surgical procedures are performed inside a laminar-flow surgical hood that has been pre-sterilized by ultraviolet irradiation (minimum 15 min) or by thorough ethanol surface decontamination. Isoflurane waste gas is captured by an activated-charcoal scavenging system mounted inside the hood. The operator wears a disposable hair cover, a surgical face mask, a long-sleeved laboratory coat, and single-layer non-sterile nitrile examination gloves (sprayed with 80% ethanol before entering the hood). A sharps disposal container is placed inside the hood for immediate disposal of scalpel blades and hypodermic needles.
1. Pre-operative preparation and anesthesia
- Use C57BL/6JRj mice, at least 10 weeks old and weighing over 20 g.
- Before surgery, clean all instruments in a warm ultrasonic bath. Rinse, dry, and soak in 70% ethanol for a minimum of 15 min.
- Alternatively, sterilize instruments by a brief passage through a glass-bead or infrared sterilizer immediately before use. Sterile drapes are not used. Between consecutive animals in the same session, return instruments to the ethanol soak for at least 2 min19.
- Weigh each mouse individually on a calibrated scale and calculate volumes of pre-operative drugs.
- Prepare the sterile PDMS membranes in advance (performed once per batch, outside the acute surgical day).
- Cast sterile PDMS membranes from a 10:1 elastomer-to-curing-agent mixture prepared according to the manufacturer's instructions and sheet to a target thickness of approximately 500 µm by sandwiching the uncured mixture between two flat borosilicate glass plates, then cure at 60 °C for at least 2 h.
- Seal the cured sheets in autoclave pouches and sterilize by steam autoclaving. In the pre-sterilized surgical hood, use a sterile #11 scalpel and a small stainless-steel ruler to cut each sheet into rectangular membranes matched to the dimensions of the cranial window.
- Store the pre-cut membranes in sterile labware (e.g., individual wells of a 6-well cell-culture plate) until use.
- Perform hardware quality control before each recording session.
NOTE: No routine impedance check is performed on the µECoG array: reference-wire faults are readily apparent in the raw traces, and impedance testing is invoked only when a hardware issue is suspected. The high-density intracranial electrode probes include built-in impedance and cable-integrity diagnostics accessible through the recording-software graphical user interface; run these when signal quality is demonstrably compromised.
2. Phase 1: Animal preparation and headplate implantation
- Animal preparation
- Anesthetize the mouse with isoflurane (induction: 4%, maintenance: 1.5−2.5%, oxygen flow rate of 0.5 L/min). Confirm the depth of anesthesia by the loss of the toe pinch reflex.
- Shave the fur from the top of the head, approximately from the eyes to the neck.
- Place the animal on a feedback-controlled heating pad equipped with an internal temperature sensor calibrated to hold body temperature at 37 °C throughout the procedure. Apply carbomer eye ointment to prevent corneal drying.
- Secure the mouse in the stereotactic frame using non-rupture ear bars. Adjust the incisor bar so that the skull lies flat, with bregma and lambda at equal dorsoventral height (flat-skull orientation). Maintain anesthesia with isoflurane (1.5–2.5%) delivered through a nose cone at an oxygen flow rate of 0.5 L/min.
- Administer pre-operative analgesics and anti-inflammatory agents via subcutaneous (s.c.) injections: Carprofen (5 mg/kg), Buprenorphine (0.05 mg/kg), and Dexamethasone (2 mg/kg).
- Disinfect the shaved area with povidone-iodine solution.
- Inject lidocaine-epinephrine solution (s.c.) as a local anesthetic under the scalp skin.
- Skull exposure
- Make a small transverse incision at the ear line (approximately 1 cm).
- Enlarge the incision progressively by extending the cut laterally around the ears and along each side of the head toward the eyes, but do not overexceed the cut to the eyes. Complete the exposure by making a diagonal cut on each side toward the midline so that the entire dorsal skull surface is exposed.
- Cleaning of the skull
- Meticulously clean the exposed skull with laboratory-grade acetone. Dip a sterile cotton swab in acetone, get rid of excess solvent (preventing drip onto adjacent tissue), and apply to the bone until all visible periosteum has been removed.
- Use acetone for its ability to dissolve fatty residues and persistent membranous remnants on the bone surface, not as a disinfectant.
NOTE: Complete removal of the periosteum and of lipid residues from the bone surface is critical for strong adhesion of the headplate and dental cement. Because the implant must withstand the mechanical stresses generated by the awake mouse, any residual periosteum or lipid film at the bone adhesive interface becomes a dominant point of failure. - Use a blunt microsurgical (circular) scalpel blade to remove any residual periosteal and connective-tissue fragments that the acetone wash did not fully dissolve. Hold it at approximately 45° to the bone surface and scrape the skull with light, radial strokes directed outward from the bregma–midline junction toward the lateral edges of the exposed bone.
- Continue until the entire exposed bone surface has been traversed at least once and appears uniformly clean and matte.
- Conclude with a final brief cleaning pass using acetone on a cotton-tipped applicator.
- Marking the craniotomy site
- Attach a biocompatible surgical skin marker to the digital stereotactic arm.
- Mark a 4 mm × 7.6 mm rectangular area on the skull relative to the bregma.
- Navigate the marker tip to the bregma and reset the X and Y coordinates on the digital readout to zero.
- Translate the arm to each of the four corners of the planned window, so that the rectangle extends 2 mm laterally from bregma on both sides, 3 mm rostrally, and 4.6 mm caudally, and place a single dot at each corner.
- Mark the two intracranial probe insertion sites on the right hemisphere.
- Mark the rostral probe site at 1.66 mm A/P and 1.95 mm M/L from the bregma.
- Mark the caudal probe site at -2.2 mm A/P and 1.9 mm M/L from bregma.
NOTE: These sites are adjusted to target DMN-specific regions. Insertion sites can be adjusted to multiple different regions with this protocol. - Detach the marker from the stereotactic arm.
- Hold a sterilized flexible straight edge (e.g., a thin plastic card) against the skull and connect the four corner dots with the marker to outline the future cranial window as a continuous rectangle.
- Increasing the surface area for better adhesion
- Conduct all the following steps until section 4 under the binocular microscope.
- Engrave a crisscross pattern over all exposed bone surfaces outside the designated window area using a #11 surgical blade and produce shallow but defined grooves 0.2–0.4 mm deep to form a uniform grid of approximately 1 mm × 1 mm squares.
NOTE: This will increase the effective surface area and therefore the mechanical grip of the overlying adhesive and dental cement. - Create a fine glue applicator by fitting a sterile 30 G needle to the tip of a long-necked cotton swab and bending the needle into a V-shape.
- Dispense cyanoacrylate glue into a disposable plastic weighing boat and dip the applicator into the glue reservoir.
- Deposit glue over every exposed and engraved bone surface, applying no more than a single deposit per site so that coverage is thorough but never excessive. Allow the glue to dry for 7 min.
- Implanting the reference socket
- Select a drilling site over the left cerebellum positioned to avoid visible superficial vessels.
- Mount the dental drill onto a drill holder in the stereotactic arm.
- Drill the pilot hole in 5–10 s bursts using a round steel bur at 20,000–25,000 RPM, retracting the bit between bursts to inspect the site under the binocular.
- Drill until the hole becomes more translucent, revealing a light pink tint and the dura becomes visible through the thinned bone.
- Stop drilling immediately at this point to avoid dural penetration. Size the finished hole to a diameter of approximately 0.5 mm, only marginally larger than the outer diameter of the reference socket.
- Insert the gold-plated reference socket into the pilot hole, secure it with cyanoacrylate glue, and reinforce the junction with UV-curable dental cement. Cure the dental cement with a 405 nm light-emitting diode (LED) curing pen light for 1 min.
- Implanting the headplate
- Place a small quantity of UV-curable dental cement on the apex of the exposed rostral bone (the point nearest the nose) to serve as a leveling support.
- Lay the headplate onto the skull so that one edge rests on the dental cement scaffolding cured around the reference socket (step 2.7.6), and with the opposing edge resting on the fresh rostral cement dab.
- Align the headplate so that its long axis is centered on the sagittal midline and its two fixation handles extend perpendicular (90°) to the midline axis. Cure the composite under the UV light to lock the headplate in place.
- Reinforce the structure by applying successive UV-curable dental cement layers of approximately 1 mm deposited thickness around the base of the headplate, encircling the engraved bone and the reference socket, until a continuous, sealed enclosure is formed around the perimeter of the future cranial window.
- Cure each increment separately with a 405 nm LED curing pen for 40 s at a working distance of 1–2 cm, ensuring complete polymerization before applying the next layer. Ensure the finished cement wall extends flush with the superior surface of the headplate and fully encloses the exposed-bone perimeter without overlapping on the marked window area.
- Allow the mouse to recover from anesthesia. Return the mouse to its home cage for at least 48 h.
- Before proceeding to section 3, verify that the animal has returned to within 5% of its pre-operative body weight and shows no signs of pain on the mouse grimace scale20. If any of these criteria are not met, extend the recovery period until they are satisfied.
NOTE: This staged design with an inter-surgical recovery interval is critical. It allows the animal to recover from the initial physiological stress and inflammation before the craniotomy, which has been found to improve surgical success rates and the long-term health of the implant; a minimum of 48 h is used here, and a staged cranial implant with a multi-day recovery interval between headplate fixation and craniotomy has been shown to reduce peri-operative inflammation and improve long-term preparation quality14.
3. Phase 2: Chronic cranial window creation
- Pre-operative preparation
- Prepare the surgical area and instruments as described in section 1.
- Re-anesthetize the mouse with isoflurane (induction 4%, maintenance 1.5–2.5%)
- Position the mouse in the stereotactic frame as described in step 2.1.4.
- Administer the pre-operative drugs at the same doses described in step 2.1, apart from the lidocaine-epinephrine local anesthetic (the scalp skin has already been removed in Phase A, so it is no longer applicable).
- Drilling the window
- Begin thinning the bone with a dental drill along the rectangle outline marked in Phase 1 (step 2.4). Start at 25,000 RPM with the drilling device held perpendicular (≈ 90 °) to the bone surface and perform one or two slightly deeper passes along the rectangle edges to establish an initial cutting groove.
NOTE: The starting drill speed may be adjusted to the experience level of the operator. - Drill grooves (approximately 0.2–0.3 mm deep) into the bone and dental cement adjacent to the cranial window at the two probe insertion coordinates marked in step 2.5.
NOTE: These grooves serve as persistent visual landmarks that remain visible after the bone flap is removed and are used to reposition the intracranial probes reproducibly in subsequent electrophysiological sessions. - Apply ice-cold sterile artificial cerebrospinal fluid (ACSF; prepared according to the cefazolin-containing recipe of Goldey et al.14) regularly throughout the drilling to prevent thermal damage to the underlying cortex and to minimize bleeding14.
- Reduce the drill speed progressively to 20,000 RPM as the bone thins, and tilt the handpiece to ≈ 45°, allowing the operator to steady the drill against the hand and to transition to gentler, more controlled strokes.
- Begin thinning the bone with a dental drill along the rectangle outline marked in Phase 1 (step 2.4). Start at 25,000 RPM with the drilling device held perpendicular (≈ 90 °) to the bone surface and perform one or two slightly deeper passes along the rectangle edges to establish an initial cutting groove.
- Removing the bone flap (critical step)
- Continue drilling along the rectangle perimeter until the bone within the outline is approximately 90% thinned. Do not drill completely through the skull.
- Confirm the remaining bone thickness using two complementary checks:
- Under the binocular microscope, tap gently on the edge of the thinned bone shelf with a blunt instrument. The magnitude of deflection produced by a light tap provides a direct indication of the residual bone thickness.
- Apply ice-cold ACSF over the drilled window and immediately inspect through the binoculars: for the first 20–30 s, before the ACSF permeates the bone, the fluid layer sharply enhances visual contrast, resolving the underlying cortical capillaries wherever the bone has been thinned close to the dura, while regions of residual thickness remain comparatively opaque beneath the fluid. Once the flap appears uniformly translucent and demonstrably flexible, proceed to step 3.3.3.
- Switch to the fine curved dura hook, which terminates in a 90°-bent tip. Insert the tip under the edge of the thinned bone with extreme caution at an angle of approximately 15° relative to the bone surface and slide the hook along the window perimeter, carefully detaching the bone flap from the surrounding skull and underlying tissue.
- Work progressively from one corner to the other along the lateral sides on both sides, and finally advance from the corners toward the center of the rectangle until the entire perimeter is detached from the underlying dura.
- Do not apply any downward pressure on the dura hook while sliding, and avoid touching the brain.
NOTE: Alternating between diagonally opposite corners at a shallow hook angle distributes mechanical stress evenly around the bone flap. This strategy prevents dural tears and preserves the long-term health of the underlying brain tissue. - Do not force any movement if the hook encounters focal resistance at any corner. Instead, lower the flap and return to step 3.4 to thin the adherent region further.
- If a dural tear occurs, discontinue the procedure for that animal (recognized by a sudden focal bulge, a pink-tinted fluid seepage, or bright-red arterial bleeding that does not subside after flooding the headplate cavity three times with ice-cold ACSF, allowing each wash to sit for 30 s).
NOTE: A successful detachment is indicated by the bone flap becoming uniformly mobile along its full perimeter with no visible dural bulging and only minor capillary bleeding.
- If a dural tear occurs, discontinue the procedure for that animal (recognized by a sudden focal bulge, a pink-tinted fluid seepage, or bright-red arterial bleeding that does not subside after flooding the headplate cavity three times with ice-cold ACSF, allowing each wash to sit for 30 s).
- Lift the successfully detached bone flap carefully with the dura hook in a posterior-to-anterior direction to approximately 35° above the skull surface.
- Grasp the lifted edge with the forceps and sway gently left and right until the plate releases completely. If the plate resists at any corner, lower it back into position and return to step 3.3.4 to thin the adherent region before attempting removal again; such resistance indicates a locally under-thinned section of bone.
- Gently clear the exposed area of coagulated blood with repeated washes of ice-cold ACSF.
- Verify that the dura is intact and transparent before proceeding.
NOTE: Slow, gradual lifting from the posterior edge is essential to minimize the risk of injury to the underlying superior sagittal and transverse venous sinuses and to the cortical surface.
- Sealing the cranial window
- Place a single sterile, pre-cast PDMS membrane (prepared in section 1) directly onto the dural surface once bleeding has subsided. When correctly sized, it will cover the window precisely and adhere passively to the dura, holding it flat against the brain.
- Absorb residual ACSF from the perimeter of the window with a non-fibrous wipe.
NOTE: The wipe must never contact the exposed dura, and strict aseptic technique (sterile operator, tools, and field) must be maintained throughout, because the window is re-opened repeatedly, and any contamination introduced at this step will compromise subsequent longitudinal recordings. - Prepare the two-component silicone elastomer sealant according to the manufacturer's instructions and apply the mixed elastomer within 30 s of dispensing to fill every crevice between the dental-cement enclosure and the inner rim of the headplate, fully surrounding and overlapping the edges of the PDMS membrane.
- Allow the elastomer to cure for approximately 2 min (or the time specified by the manufacturer). Ensure the cured seal is continuous, and liquid-tight yet remains mechanically removable at the start of each recording session.
- Affix a custom 3D-printed protective cap onto the headplate with a small quantity of cyanoacrylate glue to protect the window between recording sessions.
- Allow the mouse to recover from the anesthesia and return the mouse to its home cage for individual housing to prevent damage to the implant.
4. Post-operative care and habituation
- Monitor the mouse's health closely for at least 2 days post-surgery. Administer additional analgesics (s.c.) for 2 days post-surgery if the mouse shows signs of pain based on the mouse grimace scale20.
- Allow the mouse to recover undisturbed for a minimum of 4 days post-operatively. Then, begin a 5-day habituation period of incrementally increasing duration: 5 min on day 1, followed by 15, 30, 45, and 60 min on days 2, 3, 4, and 5, respectively, to accustom the mouse to handling and to the head-fixation recording platform.
NOTE: Post-craniotomy tissue edema and local inflammation are known to persist for up to two weeks21. Where the experimental timeline permits, an extended recovery period before the first recording session is therefore advisable. Before the first recording session, verify that the cranial window appears clear and free of opacity or fibrous tissue under the binocular microscope, and that the animal's weight and behavior are normal.
5. Procedure for longitudinal electrophysiological recordings
- Placing the animal on the recording platform
- Place the mouse on the recording platform and guide the mouse head fixation clamps. Ensure the height has been pre-adjusted to preserve the animal's natural standing posture during head fixation.
NOTE: If the mouse persistently resists head-fixation, do not force the procedure. Return the animal to its home cage and extend the habituation phase (section 4) by one or two additional sessions before reattempting fixation. - Tighten the clamp's locking screws.
- Soak the blunt microsurgical circular blade in 80% ethanol immediately before use.
- Insert the blade between the 3D-printed cap and the superior surface of the headplate, keeping the blade nearly parallel to the headplate surface. Never advance the blade past the inner rim of the headplate aperture, in order to preclude risk of contact with the brain.
NOTE: The cap is intentionally printed in transparent resin so that blade depth remains visible throughout. - Progress around the cap with gentle left-right wiggling motions that cleave the adhesive layer incrementally.
- Use fine dissecting forceps to lift the cap and discard it once it is fully released.
- Grip the outer edge of the silicon elastomer seal and lift it slowly from the caudal side toward the rostral side. The elastomer seal and the underlying PDMS membrane detach together as a single unit, exposing an intact dura.
- Keep the brain moist by applying a few drops of ACSF.
- Place the mouse on the recording platform and guide the mouse head fixation clamps. Ensure the height has been pre-adjusted to preserve the animal's natural standing posture during head fixation.
- Placing the recording devices
- Mount the µECoG array on an articulating arm with a magnetic base; adjust the friction dial of the arm based on the operator's experience, with experienced operators preferring a low-friction setting that preserves fine motor control during positioning.
- Guide the array so that its electrode face lands perpendicular (90°) to the cortical surface along the right edge of the cranial window; once satisfactorily positioned, tighten the friction dial to fix the arm.
- Use a pointed silicone tipping tool to gently tap the flat ribbon cable of the array downward onto the superior surface of the headplate so that the cable snaps into conformation with the headplate and the array itself settles flat against the dura, where residual ACSF provides passive adhesion. Because the cranial window is dimensioned to accommodate the two-subgrid array in a single orientation, coarse alignment is readily detectable.
- Make final fine adjustments with the silicone tool, nudging the array laterally until the sagittal midline is clearly centered within the semi-transparent array.
NOTE: The translucent µECoG grid exposes the sagittal sinus as an unambiguous anatomical alignment cue that remains visible through the array, enabling the same lateral offset to be reproduced across longitudinal sessions. The array is positioned to cover the anterior cingulate cortex (ACC) bilaterally in its rostral half and the retrosplenial cortex (RSP) bilaterally in its caudal half, spanning the DMN nodes targeted in this study. An open-source analysis package (ephy_spatial_fidelity-toolkit, available at https://github.com/RazBalin/ephy_spatial_fidelity-toolkit) quantifies session-to-session grid placement drift from conservative recordings. - Connect the µECoG reference wire to the gold-plated reference socket implanted in step 2.7.
NOTE: As an optional pre-session quality-control check, acquire a brief recording with the probes and array submerged in a 50 mL conical tube of ACSF to confirm that the Faraday cage is effectively attenuating environmental electromagnetic interference before proceeding with the in vivo recording. - Position the caudal high-density intracranial electrode probe on a micromanipulator arm oriented perpendicular (≈ 90°) to the brain surface and the rostral high-density intracranial electrode probe on a second arm tilted at 50°.
- Under the binocular microscope, advance each probe to approximately 1 mm above the dura and align the Y-axis of each probe with the corresponding engraved guide groove milled in step 3.2.4.
- Record by written note or by photograph through the binocular, where the µECoG electrode grid lies immediately adjacent to the planned entry point of each probe.
NOTE: When the surgery is performed properly, and no cortical edema is present, the spacing between the bone edge and the µECoG array is minimal, rendering entry-point selection unambiguous. For maximal spatial precision across longitudinal sessions, capture a photograph of the exposed cortex with the array in place and identify a distinctive pial vessel within the narrow region between the bone edge and the µECoG array. This image, annotated with the reference vessel and its relative position to the µECoG pads, serves as a session-to-session reference map for reproducing the same entry point on subsequent recording days. - Retract each probe upward by approximately 15 mm once the probe-pad correspondence has been recorded to protect the fragile electrode shank during the dural puncture.
- Fabricate the dural-puncture tool by affixing a sterile 30 G hypodermic needle to the tip of a cotton-tipped applicator and bending the needle tip to 90° with non-toothed fine forceps.
- Slowly guide the puncture tool over the headplate. Looking through the binocular, count µECoG electrode pads to align the tool with the recorded entry coordinate. Lower the bent tip to the dural surface so that the cutting tip approaches the dura at 90° while the shaft of the tool is held parallel to the long axis of the mouse's back.
- Advance the tip approximately 1 mm below the dural plane and retract. A minor transient bleed at the puncture is expected; dry it away with the twisted corner of a non-fibrous wipe.
- Lower each high-density intracranial electrode probe to the dural surface under continuous binocular observation immediately after the puncture. If the puncture was precisely placed, the probe glides through the perforation smoothly, without shank deflection.
- Descend each probe gradually to the target depth of 5 mm below the dura at a controlled speed of approximately 0.1 mm/s or slower22.
- Allow the probes to settle mechanically for 10 min before initiating data acquisition.
NOTE: The small dural perforation created by the 30 G needle self-closes within minutes; therefore, probe insertion must follow the puncture without delay.
- Data acquisition
- Begin data acquisition.
NOTE: The µECoG signals are amplified by four 128-channel digital headstages connected via SPI interface cables to an open-source acquisition board, while the two high-density intracranial electrode probes are acquired through a dedicated high-density-probe acquisition module housed in a modular instrumentation chassis alongside multifunction input/output and data-acquisition modules for synchronization and digital signaling. A common TTL master clock is generated by the open-source µECoG acquisition board and distributed as a hardware sync line to the probe-acquisition chassis (via its multifunction I/O module), so that the two acquisition streams share a sample-aligned timebase. All data streams are recorded synchronously through the acquisition system graphical user interface; full hardware models and catalog numbers are listed in the Table of Materials. - At the end of the recording session, dispense 0.5 mL of ACSF on the µECoG grids, then retract each high-density intracranial electrode probe at the same speed used for insertion (≈6 mm/min) and remove the µECoG array gently.
- Clean the probes and array by soaking for 45 min in a freshly prepared 1% (w/v) enzymatic detergent solution.
- Following the enzymatic detergent soak, rinse the electrodes by three sequential dips in reverse-osmosis-purified water, using a new tube for each rinse.
- Replace the PDMS membrane with a fresh sterile sheet as in step 3.4.1.
- Re-apply the elastomer sealant (step 3.4.3–3.4.4) and affix a new 3D-printed protective cap (step 3.4.5).
- Allow the re-sealed assembly to air-dry for 5 min before returning the mouse to its home cage. The procedure may be repeated for multiple recording sessions over several weeks.
- Begin data acquisition.
Results
A successful surgery results in a clear, transparent window over the cortex, with visible vasculature and minimal signs of inflammation or infection. This clarity can be maintained for over 21 days (Figure 1), enabling long-term longitudinal studies. The robustness of the implant is demonstrated by its ability to remain stable even throughout a 21-day chronic corticosterone administration paradigm, a common model for inducing depression-like states in rodents10,23,24. This confirms the suitability of the method for use in chronic disease modeling.
Raw electrophysiological signals recorded through the chronic window retain high quality across the longitudinal timeline. Representative broadband µECoG traces sampled from a posterior retrosplenial grid, and simultaneous intracranial probe local field potential traces sampled from a superficial cortical channel are shown side-by-side for the first recording day (day 0) and 21 days after (day 21) in Figure 2. Day-21 recordings exhibit comparable signal amplitude, spectral content, and absence of motion and noise artefacts relative to day 0 recordings from the same animal, confirming that neither the chronic presence of the PDMS membrane and silicone seal nor the repeated dural punctures introduce detectable degradation of either the surface (µECoG) or the intracranial probe signal quality in superficial cortical layers, where degradation would be expected to emerge first.
The primary validation of this technique is the acquisition of stable, high-quality, multi-modal electrophysiological data over time. The resealable window allows for the repeated insertion of probes to record from the same neuronal populations across weeks. Across the α-band (8–12 Hz), phase-locking-value matrices computed from channels along the caudal high-density intracranial electrode probe show a stable functional architecture between baseline and the day 21 post-treatment session (Figure 3). This shows reproducible re-insertion to the same cortical location rather than formal tracing of the same individual neurons. Although minor inter-session translation of the shank precludes a same-unit claim, the aggregate laminar and regional structure of the α-band interactions is preserved, supporting that the chronic window permits longitudinal sampling of the same functional circuit (Figure 3). This operational reproducibility is the foundation for advanced network analyses, including phase-locking value (PLV) and dynamic functional connectivity (DFC), across chronic experimental timelines.
To directly verify that the chronic window supports reproducible laminar targeting of the same deep structures across sessions, current-source-density (CSD) maps were computed from the probe's LFP channels. Stimulus-evoked CSD profiles show that the expected laminar sink–source signatures, including prelimbic cortex (PL) and anterior cingulate area (ACA), are preserved between sessions. These signatures are preserved between baseline (day 0) and in the recording session, 21 days after. The laminar power-profile overlays between the two sessions are highly similar across sessions (Pearson r = 0.81, Figure 4). The differences observed in the secondary motor cortex (MOs) are likely due to movement differences between recordings. Because CSD plotting carries anatomical information, it can provide a within-session, non-terminal readout of which brain regions each probe is currently sampling, independent of post-mortem tissue staining25.
Reproducibility of surface µECoG placement across sessions is quantified independently of the intracranial CSD readout. Band-limited spatial power maps computed from the µECoG grid on day 0 and day 21 are superimposed, and the pixel-wise correlation of the two maps is computed separately for the rostral and caudal sub-grids (Figure 5). Sub-grid profile correlations remain high (Pearson r > 0.94), and the spatial barcodes of the two sessions visibly co-localize the same cortical power hotspots on both the rostral (ACC) and caudal (RSP) halves of the array. The sagittal-sinus alignment cue visible through the translucent grid, together with the engraved bone grooves at the probe-insertion coordinates, therefore supports millimeter-scale reproducibility of µECoG placement over the 21-day longitudinal interval.
To further validate the technique, immunohistochemical stainings were performed for GFAP and IBA1 in post-mortem brain slices approximately four weeks after the craniotomy surgery. GFAP is expressed by astrocytes, which are upregulated in reactive gliosis, such as brain injury or inflammation. IBA1, on the other hand, is expressed by microglia, which are more active during neuroinflammatory processes. The validation cohort consisted of animals in which the full two-phase surgery was performed, and the cranial window was subsequently reopened three times (post-operative days 0, 21, and 22). However, no µECoG placement nor intracranial probe insertions were performed in this cohort. The window was resealed between sessions during an electrophysiological recording. This cohort, therefore, isolates the inflammatory contribution of the chronic window and repeated dural exposure from any probe-induced tissue damage. No significant differences were observed in either of the markers between the no-surgery control group and the vehicle group that underwent surgery (Figure 6). Representative micrographs in Figure 7 show no qualitative evidence of reactive gliosis or microglial activation in the region directly underlying the window. However, a slight increase of microglial (IBA1) and astrocyte (GFAP) activation was observed adjacent to the probe trajectory and in the hemisphere of probe insertion, respectively, which could likely be a result of the too high insertion speed of the intracranial probe22.
Cohort-level performance of the two-phase procedure across 50 operated C57BL/6J mice was calculated to summarize expected yield of the procedure. Overall peri-operative survival was 85%, with almost all fatalities occurring within the first 24 h after Phase 2 (craniotomy and window placement). Animals that cleared this window uniformly survived through the chronic longitudinal timeline. The survival rate is operator-dependent and improves with experience: novice operators in our hands achieve approximately 65% survival, rising to approximately 85% once the full two-phase procedure has been practiced. Only one animal out of 50 developed a post-operative infection. Dural tears during Phase 2 are the principal intra-operative complication. Small tears close spontaneously and are compatible with continued use of the animal, whereas larger tears are an exclusion criterion, and the animal is sacrificed at the discretion of the operator. Of the animals that cleared both surgical phases, approximately 80% yielded usable chronic electrophysiological recordings, with the remaining loss was driven by non-surgical technical factors (e.g., probe breakage, hardware failure) rather than by the window itself. These numbers define the realistic success envelope of the technique and should be used by adopting laboratories for cohort sizing.
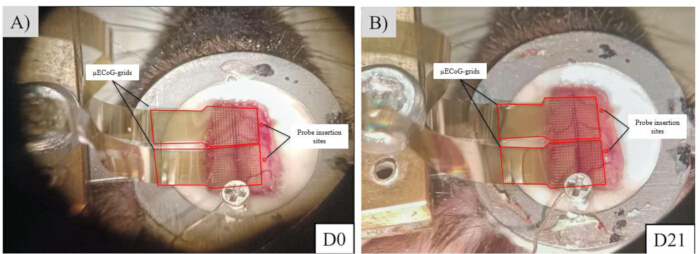
Figure 1: Representative images of a chronic cranial window over 21 days. (A) Condition of the cranial window at baseline recording (day 0) conducted 10 days after the last surgical procedure, (B) Condition of the cranial window in the same animal post-treatment, 21 days after the baseline recording session (day 21). The dura mater remains clear and the underlying vasculature healthy, with no macroscopic signs of inflammation, gliosis, or window opacification. This stability is a direct result of the dura sparing technique and is essential for longitudinal studies. Please click here to view a larger version of this figure.
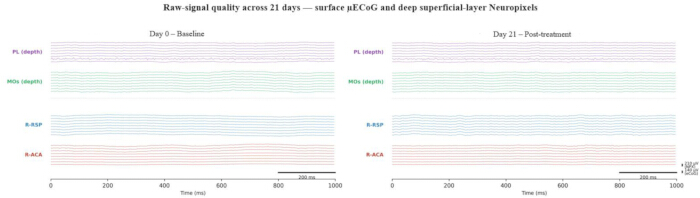
Figure 2: Representative raw electrophysiological signals at baseline (Day 0) and 21 days later (Day 21). Paired broadband traces from µECoG-grid and intracranial probe. Day-0 (left) and Day-21 (right) segments of equal duration are shown: an upper µECoG channel from a posterior retrosplenial pad and a lower intracranial probe LFP channel from a superficial cortical layer. Amplitude calibration and time-scale bars are annotated on each panel. Day-21 traces are qualitatively indistinguishable from Day-0 traces on both modalities, indicating that the chronic window preserves signal quality over the 21-day longitudinal interval. Please click here to view a larger version of this figure.
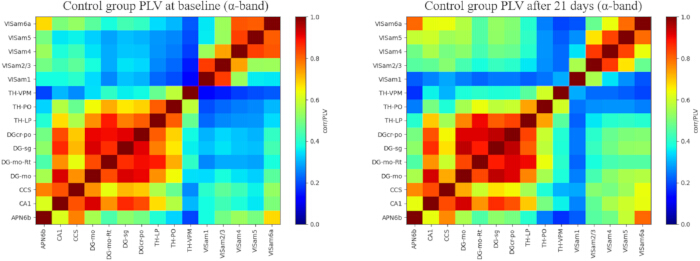
Figure 3: Representative α-band (8–12 Hz) phase-locking-value (PLV) connectivity matrices computed from the caudal high-density intracranial electrode in Control animals. Matrix rows/columns are ordered by anatomical depth along the probe, spanning superficial visual area (VISam1–6a) to thalamus (TH-VPM, TH-PO, TH-LP) to hippocampal formation (DG-mo, DG-sg, DGcr-po, CA1, CCS) and posterior parietal association area APN6b. The aggregate laminar/regional structure of α-band interactions is preserved, supporting that the chronic window permits reproducible sampling of the same functional circuit across sessions rather than same-unit tracking. Left: baseline, Right: 21 days after baseline, (n = 3). Please click here to view a larger version of this figure.
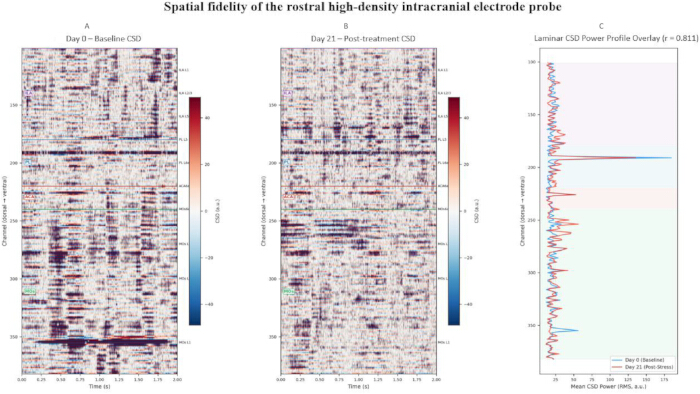
Figure 4: Current-source-density (CSD) verification of reproducible laminar targeting across sessions. Representative laminar CSD maps from separate recordings 21 days apart for one animal are shown. (A) stimulus-evoked CSD profile on the day of probe insertion (Day 0) and (B) after re-insertion 21 days later, both computed from the rostral high-density intracranial electrode probe. Characteristic laminar sink–source signatures, including prelimbic cortex (PL) and anterior cingulate area (ACA), are preserved between sessions. (C) Laminar CSD power-profile overlay comparing Day 0 (blue) and Day 21 (orange); Pearson correlation between the two profiles is r = 0.811 (RB35), r = 0.768 (RB41), and r = 0.771 (RB43), indicating reproducible laminar targeting despite minor inter-session shank translation. Differences can be observed in the secondary motor cortex (MOs), likely due to movement differences between recordings. Please click here to view a larger version of this figure.
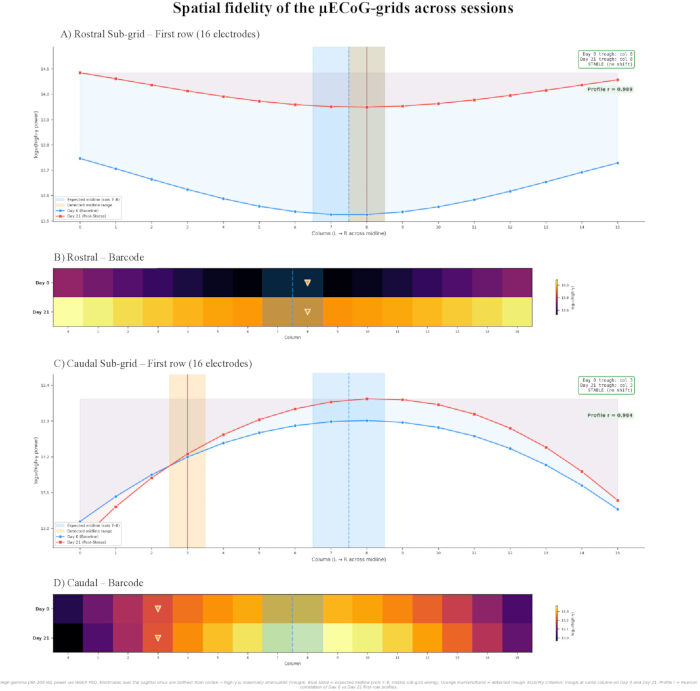
Figure 5: µECoG spatial fidelity across sessions. Band-limited µECoG power maps on Day 0 and Day 21. The rostral (ACC) and caudal (RSP) sub-grid barcodes of the two sessions are shown side-by-side together with the pixel-wise correlation (Pearson r) between the two sessions. Across sessions, the sub-grid correlations remain high (r > 0.94), and cortical power hotspots co-localize between sessions, confirming reproducible placement of the µECoG array across the 21-day longitudinal interval. Please click here to view a larger version of this figure.
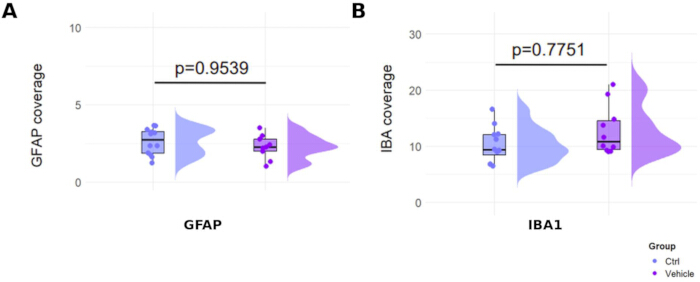
Figure 6: Immunohistochemistry analysis for GFAP (astrocytes) and IBA1 (microglia) from the no-surgery control group, and the vehicle group that underwent surgery. In the expression of GFAP and IBA1, there are no significant differences between control and vehicle groups, suggesting that the surgery does not result in significant inflammation or reactive gliosis in the brain. Each data point represents one brain slice (n = 3). Please click here to view a larger version of this figure.
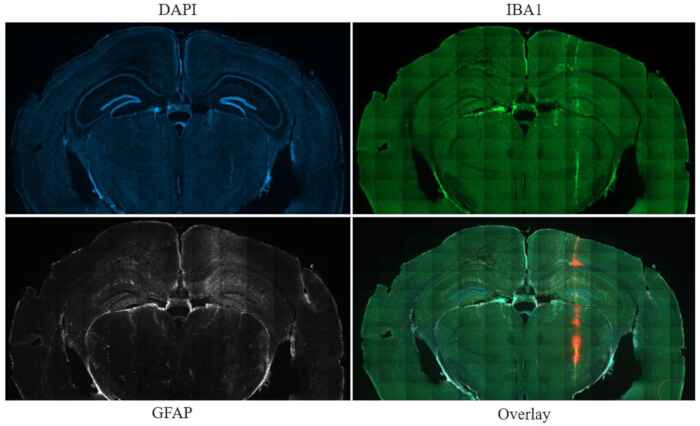
Figure 7: Representative epifluorescence micrographs of the caudal recording site underneath the cranial window, stained for DAPI (nuclei), IBA1 (microglia), and GFAP (astrocytes). The animal underwent the craniotomy surgery and three separate electrophysiological recordings across 22 days with both µECoG-grids and intracranial probes. DiL dye (red) was used in the last recording session to visualize the probe trajectory. No qualitative evidence of reactive gliosis or tissue disruption is visible in the immediate region underlying the window, consistent with the quantitative analysis in Figure 6. Slight microglia and astrocyte activation can be seen next to the probe trajectory, likely resulting from too high insertion speed of the intracranial probe22. Scale bar: 100 µm. Please click here to view a larger version of this figure.
Discussion
This report details a two-phase, dura-sparing surgical protocol that provides a reliable and highly effective method for creating a large, chronic, and resealable cranial window in mice. The significance of this technique extends beyond the size of the window. Its principal advantage is the capacity for simultaneous, multi-scale interrogation of large-scale brain networks over longitudinal timescales. By combining surface µECoG grids (providing mesoscale LFP data) with deep, high-density intracranial electrode probes (providing microscale, laminar-resolved single-unit and LFP data), researchers can directly investigate how specific circuit activity, for example, within the deep DMN nodes, contributes to the emergent network-level dynamics observed on the cortex. Additionally, this method can be suited for any large-scale networks as it provides access to the majority of the mouse brain.
Two aspects of the protocol are fundamental to its success. First, the division of the surgery into two phases separated by a 48-h recovery period is a critical design choice. This strategy minimizes the cumulative physiological stress on the animal, reduces the acute inflammatory response, and allows for initial healing before the more invasive craniotomy. Empirically, this staged design improves the reliability of a healthy long-term implant, consistent with published staged cranial-implant protocols in mice14. Second, the dura-sparing craniotomy technique is the single most critical maneuver. By thinning the bone to approximately 90% of its thickness and then gently lifting the bone flap with a hook, the integrity of the dura mater is preserved. The dura mater is a dense fibrous barrier that normally shields the cortex from mechanical insult, infection, and foreign-body contact. Keeping it intact is essential for preventing the inflammation, glial scarring, and infection that are the primary causes of failure in most chronic window preparations26. This step enables the resealable, truly chronic nature of the window, allowing repeated access to the brain over many weeks with minimal tissue damage.
The presented technique establishes a robust platform for addressing fundamental questions in systems neuroscience that require longitudinal observation. It is particularly well-suited for studying the effects of chronic stress on network plasticity and for modeling neuropsychiatric disorders like depression10,27,28. A key future application is the evaluation of the network-level impact of novel, fast-acting therapeutics. For instance, recent work has shown that antidepressants and psychedelics can induce a state of "juvenile-like" plasticity by directly binding to the TrkB receptor29. This chronic window preparation is an ideal system for tracking how such compounds rewire DMN circuits over the weeks required for their therapeutic effects to manifest.
The primary limitations of this method are its technical demands. The surgery requires significant practice and a high degree of microsurgical skill to perform reliably. Mild brain swelling may occur, particularly following a chronic treatment period, but this does not typically preclude high-quality recordings and can be managed with careful monitoring. While precise stereotactic measurements are crucial, minor variability in probe and grid placement is a potential issue. Therefore, for studies where the precise anatomical location is paramount, post-mortem histological verification of probe tracks is strongly advised. The recommended procedure is to coat each high-density intracranial electrode probe with a lipophilic fluorescent dye (e.g., 1,1’-dioctadecyl-3,3,3',3’-tetramethylindocarbocyanine perchlorate, DiL) prior to the final recording session, perfuse the animal transcardially with 4% paraformaldehyde after the terminal session, post-fix the brain overnight, cryoprotect in 30% sucrose, and cut 50 µm coronal sections on a freezing microtome or cryostat through the span of the probe track. Sections are counterstained with a nuclear dye (e.g., DAPI) to visualize cytoarchitectural boundaries, and the DiL-labeled tracks are imaged on a fluorescence microscope. The labeled tracks are then registered to the Allen Mouse Brain Common Coordinate Framework (CCF v3) by aligning each coronal section to the corresponding Allen reference atlas plate. Open-source tools such as SHARP-Track, the Allen CCF Python toolkit, or brainreg support this registration and yield a voxel-level assignment of each recording channel to an Allen CCF anatomical label, thereby converting the chronic-window recordings into a quantitatively atlas-registered dataset and resolving any residual ambiguity in probe and grid placement.
Two failure modes warrant explicit troubleshooting guidance. Minor dural tears (focal bulge or brief seepage) that resolve with three repeated ice-cold ACSF washes typically heal during the first week of post-operative recovery, and recordings should be deferred until the preparation appears quiescent on visual inspection of the window; animals are retained in the cohort. Substantial tears producing sustained arterial bleeding that does not subside after cold ACSF washes constitute a terminal event, and the animal must be excluded. Protective-cap detachment is the second critical failure because the cap, together with the overlying silicone elastomer and PDMS membrane, provides the hermetic seal that isolates the craniotomy from the external environment between recording sessions. If the cap is lost in the home cage, the seal is broken, and the window is exposed to contamination, so animals found with a detached cap cannot be returned to the longitudinal cohort and must be humanely sacrificed. If the detachment is witnessed in real time, the cap must be re-affixed immediately under strict aseptic conditions and anesthesia, after re-inspecting the underlying PDMS membrane and silicone seal and replacing them if they are damaged.
Relative to established chronic and acute methods, this protocol occupies a distinct operating point. Removable cranial-window preparations developed for long-term optical imaging in awake mice provide excellent optical access but are sealed with a glass coverslip that precludes repeated physical electrode insertion14. The resealable PDMS/3D-cap design described here preserves dura-sparing access while permitting non-terminal physical re-entry on multiple recording sessions. Chronic implantation of high-density intracranial electrode probes achieves chronic single-unit stability in behaving animals but entails permanent indwelling shanks whose peri-electrode gliosis accumulates over weeks, and which are not readily combined with a large µECoG grid over the same cortex16. Acute head-fixed multi-probe high-density intracranial electrode preparations afford the high channel counts and laminar depth coverage but are terminal by design and therefore cannot support within-animal longitudinal studies such as a corticosterone-induced depression trajectory or a single-dose psychedelic time-course17,30. The present preparation unifies these capabilities with large-area mesoscale µECoG, laminar-resolved high-density intracranial electrode recording, and non-terminal longitudinal re-entry in a single implant.
In conclusion, this two-phase surgical protocol overcomes major obstacles in chronic, large-scale electrophysiology. By enabling stable, multi-week, multi-modal recordings from distributed nodes of the DMN, this method provides a powerful platform to link circuit dynamics to complex behavior and pathology, ultimately advancing the ability to understand and treat complex brain disorders.
Disclosures
EC is a co-founder, Board member and recipient of research support from Kasvu Therapeutics, Ltd, and has received a speaker fee from Janssen-Cilag. The other authors have nothing to disclose.
Acknowledgements
This work was supported by the Research Council of Finland grants #327192 and 347358, and the Sigrid Jusélius foundation. The authors thank the members of the Castrén and Palva laboratories for their technical assistance and helpful discussions throughout this project.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| µECoG array — 512-channel custom (2 × 256 ch) | NeuroNexus | E256-200-30-80 | Packaging: IH256. Two 16×16 sub-grids (each 3.3 mm × 3.5 mm); 200 μm pitch; 80 μm electrode diameter. Surface-level DMN recordings. |
| 3-axis left-hand micromanipulator arm | World Precision Instruments (WPI) | 504926 | 10 μm resolution; digital display; used for headplate/probe positioning during surgery |
| 3D-printed protective cap | In-house (Anycubic Photon Mono 4K) | N/A | Custom design; printed in Anycubic High Clear UV resin; STL file available at https://github.com/RazBalin/ProtectiveDMN_Cap |
| Acetone (laboratory grade) | Sigma-Aldrich | 179973 | Skull surface degreasing and periosteum removal prior to adhesive application |
| Adson Dura Hook 5 mm (Fine dura hook) | gSource | gS 25.2570 | Used to detach bone plate from dura along perimeter; fashioned from fine tungsten wire or similar |
| Anycubic High Clear UV Resin | Anycubic | STMGCL-102B | Photopolymer resin used with Anycubic Photon Mono 4K printer for 3D-printed protective caps |
| Anycubic Photon Mono 4K 3D resin printer | Anycubic | PHOTON-MONO-4K | Used to print protective window caps from Anycubic High Clear Resin |
| Anycubic UV Resin Wash & Cure Machine 2.0 | Anycubic | 285-550 | Post-print washing and UV curing of 3D-printed caps |
| Articulating arm with magnetic base (×2) | Haas Tooling | 09-0535 | Used to hold µECoG sub-grids in place on cortical surface during recordings |
| Artificial CSF (aCSF) | In-house preparation | N/A (In-house) | aCSF recipe: 124 mM NaCl, 3 mM KCl, 26 mM NaHCO3, 2 mM CaCl2, 1 mM MgSO4, 1.25 mM KH2PO4, 10 mM D-Glucose; oxygenate with 95% O2 / 5% CO2 immediately after preparation. Catalog numbers listed separately. |
| Blunt microsurgical blade (Circular scalpel) | Iogen | 374769 | Used for skull surface scraping and cap removal |
| Buprenorphine (Temgesic) | Indivior | BE-112515 | Opioid analgesic; 0.05 mg/kg s.c. pre-operatively |
| C57BL/6JRj mice | Janvier Labs | Male or female; minimum 10 weeks old, >20 g body weight at time of surgery | |
| Calcium Chloride dihydrate (CaCl2·2H2O) | Sigma-Aldrich | C-7902 | 2 mM; MW 147.02; 0.29 g/L. Prepared as Ca ×100 stock. Component of in-house aCSF. |
| Carprofen (Rimadyl) | Zoetis Animal Health | RXRIM-INJ | NSAID analgesic; 5 mg/kg s.c. pre-operatively |
| Corticosterone | Sigma-Aldrich | C2505 | Dissolved in drinking water for 21-day chronic stress / depression model |
| Cotton swab | Fisherbrand | 22-363-157 | Serves as handle for 30 G dura puncture device and for degreasing the skull surface with acetone |
| Cyanoacrylate glue — Loctite 401 | Henkel Adhesives | Loctite 401 | Thin-viscosity cyanoacrylate; used for skull surface priming, headplate and cap fixation |
| Dental drill — Foredom K.1070 | Foredom | K.1070 | Flexible-shaft rotary drill; used for craniotomy thinning and pilot hole drilling |
| Dexamethasone | Dopharma | 1DEX004 | Corticosteroid anti-inflammatory; 2 mg/kg s.c. pre-operatively |
| D-Glucose | Sigma-Aldrich | G-7021 | 10 mM; MW 180.20; 1.80 g/L. Prepared as Glucose ×100 stock. Component of in-house aCSF. |
| Drill bit Steel Bur round 1/007W | Hager & Meisinger | 18089 | Used for the reference site and the cranial window |
| Ethanol 80% (v/v) - A12t Dilutus | Berner | 13221132 | Pre-operative soaking of surgical instruments and surgical laminar hood for sterilization |
| Gas Evacuation Apparatus | RWD Life Science | R546W | Scavenges waste anesthetic gases from surgical area |
| Gold-plated reference socket | DigiKey | 310-13-102-41-001000 | Implanted over left cerebellum; serves as ECoG ground/reference |
| GRANT Ultrasonic Cleaner — Model 17002A | GRANT Instruments | 17002A | EAN: 4064343191654. Hot-water ultrasonic bath; used with TICKOPUR TR 3 for instrument cleaning |
| Heating pad — Supertech TMP-5B | Supertech | TMP-5B | Maintains body temperature at 37 °C throughout anesthesia |
| Isoflurane | Piramal Healthcare | 66794-017-25 | Inhalation anesthetic; induction 4%, maintenance 1.5–2.5% |
| Kimtech Science, Precision Wipes (Non-fibrous tissue) | KIMBERLY CLARK | 7552 | Used with pointy tip to dry residual ACSF and assist PDMS membrane adhesion to dura |
| Kwik-Cast Sterile Elastomer Sealant | World Precision Instruments (WPI) | KWIK-CAST-s | Model: KWIK-CAST-S. Biocompatible silicone; used to create removable seal around PDMS membrane. |
| LED UV Curing Pen 405 nm | CureUV | 514424-405 | Used to cure UV-activated dental cement (Total C-Ram) during implantation |
| Lidocaine-epinephrine solution | Orion Pharma | 05 10 31 | Local anesthetic; s.c. injection under scalp skin |
| Magnesium Sulfate heptahydrate (MgSO4·7H2O) | Sigma-Aldrich | M-7774 | 1 mM; MW 246.48; 0.25 g/L. Prepared as Mg ×100 stock. Component of in-house aCSF. |
| Metal headplate — Neurotar Model 13 | Neurotar | Model 13 | Titanium headplate; round opening 11 mm diameter; affixed to skull with cyanoacrylate and dental cement |
| NeuroNexus headstage adapter ) | NeuroNexus | Custom IH256 64×4 Molex | Custom adapter board; sandwiches each µECoG sub-grid between two Intan RHD 128-ch headstages |
| Neuropixels 1.0 probe with metal cap (×2) | IMEC | PRB_1_4_0480_1_C | 960 recording sites; 10 mm shank. One probe targets hippocampal-thalamic-visual column, one targets mPFC column |
| NI PXIe-1083 chassis | National Instruments | PXIe-1083 | 9-slot PXI Express chassis housing Neuropixels module and NI DAQ cards |
| NI PXIe-3839 multifunction I/O module | National Instruments | PXIe-3839 | Installed in NI PXIe-1083 chassis; used for synchronization and auxiliary I/O |
| NI PXIe-6363 multifunction DAQ | National Instruments | PXIe-6363 | Installed in NI PXIe-1083 chassis; analog and digital I/O for synchronization |
| Nova Microcinerator - Infrared Sterilizer | Argos Tech | S3022 | Used for quick sterilization of any instrument that may touch exposed brain tissues |
| Olympus SZ51 stereo binocular microscope | Olympus | SZ51 | Surgical visualization; used throughout craniotomy and implantation steps |
| Open Ephys Acquisition Board (One Box, 1st generation) | Open Ephys | OEPS-9029 | Receives µECoG data streams via SPI; open-source hardware. See open-ephys.org |
| Open Ephys GUI | Open Ephys | N/A (open-source) | Free, open-source electrophysiology acquisition software. Available at: open-ephys.org |
| Potassium Chloride (KCl) | Sigma-Aldrich | P-5405 | 3 mM; MW 74.55; 0.22 g/L. Component of in-house aCSF. |
| Potassium dihydrogen Phosphate (KH2PO4) | Sigma-Aldrich | P-5655 | 1.25 mM; MW 136.09; 0.17 g/L. Component of in-house aCSF (Klebs ×10 stock). |
| Povidone-iodine solution (BETADINE) | Takeda | 45 70 28 | Topical disinfectant for surgical field preparation |
| PXIe acquisition module | Neuropixels | PXIE_1000 | PXI-format module for Neuropixels 1.0 data acquisition; installed in NI PXIe-1083 chassis |
| Reference socket connector | DigiKey | 342-10-102-00-591000 | Corresponding mating connector for reference socket above; confirm part number with DigiKey |
| RHD 128-channel headstage (×4) | Intan Technologies | RHD 128 | Two headstages per µECoG sub-grid; confirm model (e.g., RHD2132 or RHD2164) |
| RHD SPI interface cable, 0.9 m | Intan Technologies / Open Ephys | C3203 | Standard SPI cable connecting RHD headstages to Open Ephys acquisition box |
| RWD Air Pump | RWD Life Science | R510-29 | Provides airflow through anesthesia circuit |
| RWD Animal Anesthesia Vaporizer | RWD Life Science | R5835 | Precision isoflurane vaporizer for induction and maintenance of anesthesia |
| Scalpel Blade #11 | Swann Morton | SM0103 | Used for engraving crisscross pattern on skull surface to enhance adhesive grip |
| Small animals hair trimmer - GT416 | Aesculap Schermaschinen GmbH | D-98528H | Used to trim the animal scalp before surgery |
| Sodium Bicarbonate (NaHCO3) | Sigma-Aldrich | S-5761 | 26 mM; MW 84.01; 2.18 g/L. Component of in-house aCSF. |
| Sodium Chloride (NaCl) | Sigma-Aldrich | S-5886 | 124 mM; MW 58.44; 7.25 g/L. Component of in-house aCSF. |
| SOL-M (Sterile hypodermic needle 30 G) | Sol-Millennium Europe | 113005 | Bent 90° at tip and affixed to cotton swab to create dura puncture device |
| Standard manipulator arm, 3-axis LEFT (Stoelting) | Stoelting Co. | 51604 | Used for Neuropixels probe insertion during recording sessions |
| Standard manipulator arm, 3-axis RIGHT (Stoelting) | Stoelting Co. | 51606 | Used for Neuropixels probe insertion during recording sessions |
| Stereotactic frame — RWD F67001 | RWD Life Science | F67001 | Standard stereotaxic frame; used for head stabilization and coordinate-referenced implant placement |
| Surgical Marker skin pen with ruler (Violet Ink) | Fannin | SM0372 | Biocompatible gentian-violet based surgical skin marker used to outline the planned craniotomy and implant footprint on bone. Resistant to cyanoacrylate priming (Loctite 401) and remains visible through skull degreaseing and headplae fixation, allowing reliable transfer of stereotactic coordinates onto the bone surface. |
| SYLGARD 184 Silicone Elastomer Kit (PDMS) | Dow (Germany) | 1673921 | Polydimethylsiloxane; cast into thin (<1 mm) membranes; placed on dural surface to protect brain |
| Tergazyme enzymatic detergent | Alconox | 1304-1 | Protease-based cleaner used at 1% (w/v) in lukewarm RO water for post-session electrode cleaning (45 min soak, then triple rinse in purified water). |
| Total C-Ram Automix UV Dental Cement (White) | Itena | R301950 | Model: TTCRAM-BLC. UV-curable dental resin; used for headplate reinforcement and socket fixation |
| Ultrasonic Cleaning Solution (TICKOPUR TR 3) | Dr. H. Stamm GmbH | TR-3-913 | Citric-acid-based concentrate; used in ultrasonic bath for post-surgical instrument cleaning |
| Viscotears Eye Gel 2 mg/g | Alcon | 503849 | Carbomer-based lubricating eye ointment; applied to corneas during anesthesia to prevent drying |
| Zeiss Cold Light Source KL1500 LCD | Carl Zeiss | KL1500 LCD | Fiber-optic cold illumination for surgical field; prevents thermal damage |
Reprints and Permissions
