This meta-analysis of 13 studies provides a descriptive synthesis of testicular characteristics, semen parameters, and reproductive hormone profiles in infertile men with testicular microlithiasis.
Research Article
Clinical Characteristics, Semen Parameters, and Reproductive Hormone Profiles in Infertile Men with Testicular Microlithiasis: A Meta-analysis
* These authors contributed equally
In This Article
Summary
Abstract
Testicular microlithiasis (TM) is frequently observed in infertile men, but its clinical significance remains controversial. This study aimed to systematically summarize the testicular characteristics, semen parameters, and reproductive hormone profiles of infertile men with TM and to describe the differences across TM subtypes. A systematic literature search was conducted in PubMed, Embase, Cochrane Library, and Web of Science from inception to November 14, 2025. Eligible studies included infertile male patients with ultrasound-confirmed TM. Data on testicular history, semen parameters, and hormonal profiles were extracted. Pooled prevalence estimates or pooled mean values were calculated using fixed- or random-effects models. Subgroup analyses were performed based on TM classification: classical (CTM) and limited (LTM). Thirteen studies were included. The pooled prevalence estimates of cryptorchidism, testicular cancer, and varicocele in infertile men with TM were 10.0%, 7.0%, and 37.0%, respectively. The pooled prevalence estimates of cryptorchidism, testicular cancer, and varicocele in infertile men with TM were 10.0%, 7.0%, and 37.0%, respectively. The pooled mean sperm concentration was 20.17 × 10⁶/mL. Subgroup analysis showed that CTM was associated with significantly lower sperm concentration than LTM (P = 0.042), whereas no significant differences were observed between CTM and LTM for sperm morphology or gonadotropin levels.. In conclusion, this meta-analysis provides a descriptive synthesis of clinical findings, semen characteristics, and endocrine profiles in infertile men with TM.
Introduction
Testicular microlithiasis (TM) is an ultrasonographic finding characterized by multiple non-shadowing hyperechogenic foci within the seminiferous tubules, typically reflecting intratubular calcifications. The clinical significance of TM remains under debate, particularly because of its proposed association with testicular germ cell tumors (TGCTs)1. Although the prevalence of TM in the general male population is relatively low, usually reported to be less than 5%2,3, its prevalence appears to be higher among infertile men, with recent studies reporting rates exceeding 10%4. TM has also been reported in individuals with underlying testicular pathologies, including cryptorchidism, varicocele, and non-obstructive azoospermia, all of which are commonly considered clinically important in the evaluation of male infertility and testicular health5.
Among these conditions, cryptorchidism is a well-established risk factor for impaired spermatogenesis and TGCT, even after surgical correction6. Varicocele is recognized as the most common surgically correctable cause of male infertility, affecting approximately 35% to 40% of infertile men7,8. Despite these observations, the clinical role of TM remains controversial. It remains unclear whether TM serves as an independent marker of testicular pathology or reflects coexisting subclinical testicular disease. Additionally, the relationship between TM and semen parameters, particularly sperm concentration and morphology, remains equivocal. Some studies have reported poorer semen parameters in men with TM, whereas others have found no significant differences compared with controls9,10,11.
Beyond anatomical abnormalities and semen quality, reproductive hormones provide important information on testicular function and spermatogenic activity. Follicle-stimulating hormone (FSH) and luteinizing hormone (LH) are widely used indicators of germ cell and Leydig cell function, and altered hormone levels may reflect changes in spermatogenesis or in regulation of the hypothalamic-pituitary-gonadal axis. Characterizing endocrine profiles may help clarify whether reproductive hormone patterns differ across TM subtypes or coexist with other testicular findings. Although several studies have evaluated reproductive hormone levels in infertile men with TM, the reported findings have been variable, and the overall endocrine characteristics of this population remain poorly defined12,13. In addition to differences in associated clinical and semen characteristics, TM has been categorized into limited TM (LTM) and classic TM (CTM) based on the number of microliths observed on ultrasound. However, the clinical relevance of this subclassification for reproductive characteristics or testicular pathology has not been systematically evaluated.
Despite increasing interest in the reproductive implications of TM, evidence regarding the clinical characteristics, semen parameters, and reproductive hormone profiles reported in infertile men with TM remains fragmented. In particular, coexisting testicular conditions, including cryptorchidism, varicocele, and testicular cancer, as well as semen and endocrine findings, have not been comprehensively synthesized in this population. Therefore, this systematic review and meta-analysis aims to provide a descriptive synthesis of testicular disorders, semen parameters, and reproductive hormone profiles reported in infertile men with TM. Additionally, we explored whether these characteristics differed between LTM and CTM subgroups.
Protocol
Search strategy and selection criteria
This study conducted a comprehensive literature search across four databases, including PubMed, Embase, Cochrane Library, and Web of Science, covering the period from database inception to November 14, 2025. The search strategy combined Medical Subject Headings (MeSH) and free-text terms related to male infertility and TM and was adjusted according to the indexing system of each database. Representative search terms included "testicular microlithiasis", "microlithiasis", " testicular", and "Infertility, Male". The complete search strategies are provided in Supplemental Table S1.
Studies were included if they met the following criteria: (1) the study population included male patients with infertility; (2) TM was diagnosed by scrotal ultrasound; and (3) the study was an observational study, including a case-control study, cohort study, or single-arm study reporting extractable data on infertile men with TM.
Studies were excluded if they met any of the following criteria: (1) duplicate publications; (2) non-clinical studies, including reviews, expert opinions, case reports, conference abstracts, summaries, letters, editorials, animal studies, etc.; (3) case series/individual cases, or studies that cannot be compared with non-TM controls; (4) studies for which the full text is unavailable or the data were incomplete and could not be extracted or converted; (5) articles not published in English.
Data collection
Two reviewers independently screened titles and abstracts to identify studies that met the inclusion criteria and then reviewed the full texts according to predefined inclusion and exclusion criteria. Disagreements were resolved through discussion or consultation with a third reviewer. For each included study, data were extracted using standardized forms, including first author, publication year, study design, study group, age, history of cryptorchidism, coexisting testicular conditions including testicular cancer and varicocele, presence of a control group, TM classification criteria, sperm concentration, percentage of normal sperm morphology, FSH level, and LH level. Semen parameters were extracted according to the WHO semen analysis criteria used in the original studies (WHO 1999 and WHO 2010)14,15.
Quality assessment
The methodological quality of the studies included was independently assessed by two reviewers using the Newcastle-Ottawa Scale (NOS) for observational studies. The NOS evaluates three main domains: selection of study groups (maximum 4 points), comparability of groups (maximum 2 points), and ascertainment of outcomes (maximum 3 points), with a total possible score of 9. Studies scoring ≥ 6 points were considered to have moderate to high quality. Any discrepancies in scoring were resolved through discussion or consultation by a third reviewer.
Outcome measures
The primary outcome included testicular history and coexisting testicular conditions, semen parameters, and reproductive hormone profiles. For each categorical outcome, including history of cryptorchidism, testicular cancer, and varicocele, data were extracted as event counts and total sample sizes and summarized as pooled prevalence estimates. For continuous outcomes, including sperm concentration, normal sperm morphology, FSH, and LH, data were extracted as means, standard deviations, and sample sizes and summarized as pooled mean values. Subgroup analyses were performed based on the number of microliths observed on ultrasound (LTM and CTM). LTM was defined as <5 microliths, whereas CTM was defined as ≥5 microliths on ultrasound, based on the Bennett classification adopted by the included studies16.
Statistical analysis
Meta-analyses were conducted using random-effects (RE) and fixed-effects (FE) models, calculating pooled prevalence estimates and pooled mean values, along with their 95% confidence intervals (CIs). Statistical heterogeneity was assessed using the I2 statistic, with I2 values of 25%, 50%, and 75% considered low, moderate, and high heterogeneity, respectively. For I2 > 50%, the RE model was used; for I2 < 50%, the FE model was used. Subgroup differences were assessed using interaction p-values. When more than three studies were included, funnel plots were used to qualitatively assess publication bias for each outcome. Egger’s and Begg’s tests were not performed because fewer than 10 studies were included in most analyses.
Results
Study details and demographics
A total of 684 records were initially identified through the database search. After screening and eligibility assessment, 13 studies published between 1998 and 2022 were included in the meta-analysis. The included studies covered multiple geographical regions, including Europe, Asia, the Middle East, and North America4,13,17,18,19,20,21,22,23,24,25,26,27. Sample sizes in the TM cohorts varied considerably, ranging from 4 to more than 200 patients, with patients primarily aged 20–50 years (Figure 1 and Supplemental Table S2). The NOS quality assessment indicated that most studies scored between 5 and 7, indicating moderate methodological quality. However, several studies provided limited information on the outcome of interest at the start of the study and on the adequacy of follow-up, which should be considered when interpreting the findings (Supplemental Table S3).
Cryptorchidism history and coexisting testicular conditions
Three studies reported a history of cryptorchidism in infertile men with TM. The pooled incidence of 10.00% (95% CI: 0.05–0.14), with low heterogeneity (I2 = 0.0%, P = 0.922), indicates good consistency across studies (Figure 2A). Three studies reported testicular cancer in this population, with a pooled prevalence estimate of 7.00% (95% CI: 0.00–0.15). Substantial heterogeneity was observed (I2 = 70.2%, P = 0.018), suggesting variability in the reported prevalence estimates across studies (Figure 2B). For varicocele, six studies were included, with a pooled prevalence estimate of 37.00% (95% CI: 0.27–0.47) and moderate heterogeneity (I2 = 50.0%, P = 0.051) (Figure 2C). Subgroup analysis by TM subtype showed no significant difference in the pooled prevalence estimate of varicocele between LTM and CTM (P = 0.210) (Supplemental Figure S1). Funnel plots for these three outcomes (Figure S2A-C) showed that the study points were generally distributed within the pseudo-95% confidence intervals, with no clear evidence of publication bias.
Semen parameters
Three studies reporting sperm concentration were included, yielding a pooled mean sperm concentration of 20.17 × 10⁶/mL (95% CI: 14.07–26.26). The heterogeneity among studies was moderate (I2 = 60.3%, P = 0.056) (Figure 3A). Visual inspection of the funnel plot did not reveal obvious asymmetry (Supplemental Figure S2D). Subgroup analysis showed a statistically significant difference in sperm concentration between LTM and CTM groups (P = 0.042, Figure 3B). For normal sperm morphology, subgroup analysis yielded a pooled mean value of 3.57% (95% CI: 2.83–4.32), with moderate heterogeneity (I2 = 68.3%, P = 0.024). However, no significant difference in normal sperm morphology was observed between the LTM and CTM groups (P = 0.988, Figure 3C).
Reproductive hormone levels
Reproductive hormone outcomes primarily included FSH and LH levels. Four studies were included in the FSH analysis. The pooled mean FSH level was 11.69 (95% CI: 7.89–15.48), with extremely high heterogeneity (I2 = 97.0%, P < 0.001) (Figure 4A). Visual inspection of the funnel plot showed a dispersed distribution of study points and an asymmetric pattern, which should be interpreted cautiously given the limited number of studies and substantial variation in mean values (Supplemental Figure S2E). The test for subgroup differences between LTM and CTM was not statistically significant (P = 0.069) (Figure 4B).
Four studies were included in the LH analysis. The pooled mean LH level was 4.16 (95% CI: 3.18–5.13), exhibiting high heterogeneity (I2 = 92.7%, P < 0.001) (Figure 5A). Visual inspection of the funnel plot did not reveal obvious asymmetry, although this assessment was limited by the small number of included studies (Supplemental Figure S2F). Subgroup analysis showed no significant difference in LH levels between the LTM and CTM groups (P = 0.387, Figure 5B).
DATA AVAILABILITY:
This study is a systematic review and meta-analysis, and no new primary data were generated. All data analyzed in this study were extracted from previously published articles listed in the References. The search strategy, characteristics of the included studies, and quality assessment are provided in Supplemental Table S1, Supplemental Table S2, and Supplemental Table S3.
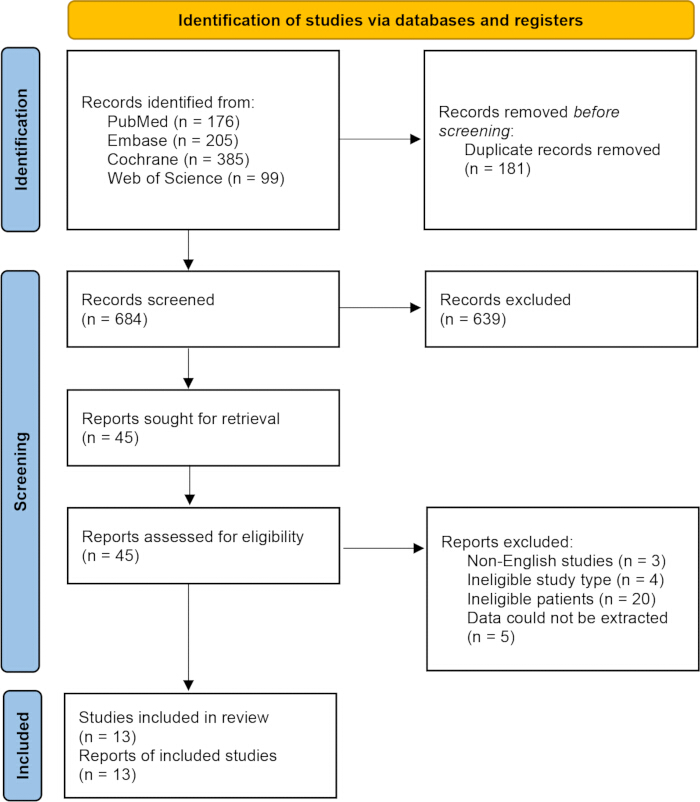
Figure 1. PRISMA flow diagram of study selection. Please click here to view a larger version of this figure.
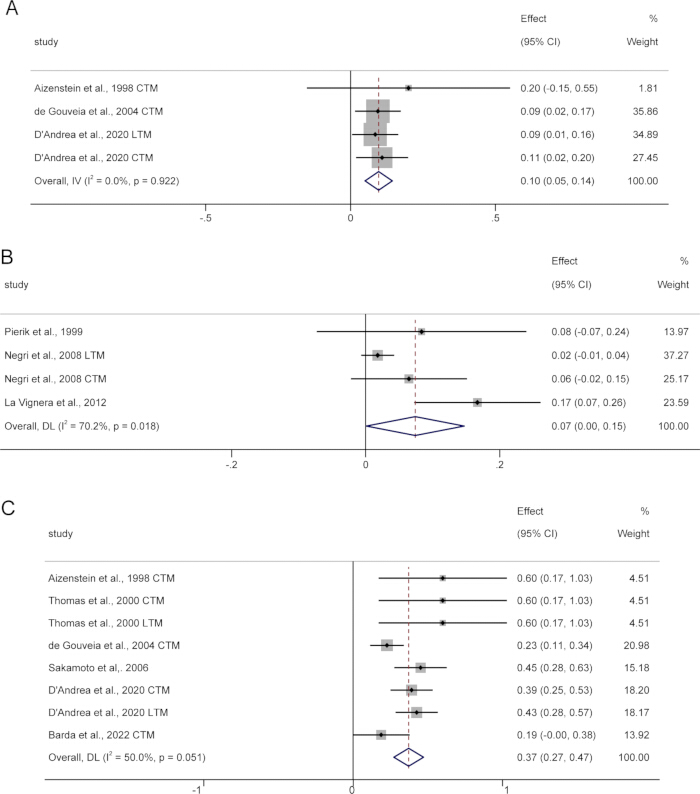
Figure 2. Forest plots of cryptorchidism, testicular cancer, and varicocele in infertile men with testicular microlithiasis. (A) Pooled prevalence estimate of a history of cryptorchidism. (B) Pooled prevalence estimate of testicular cancer. (C) Pooled prevalence estimate of varicocele. Abbreviations: CI = confidence interval; IV = inverse variance; DL = DerSimonian–Laird method; CTM = classical testicular microlithiasis; LTM = limited testicular microlithiasis. Please click here to view a larger version of this figure.
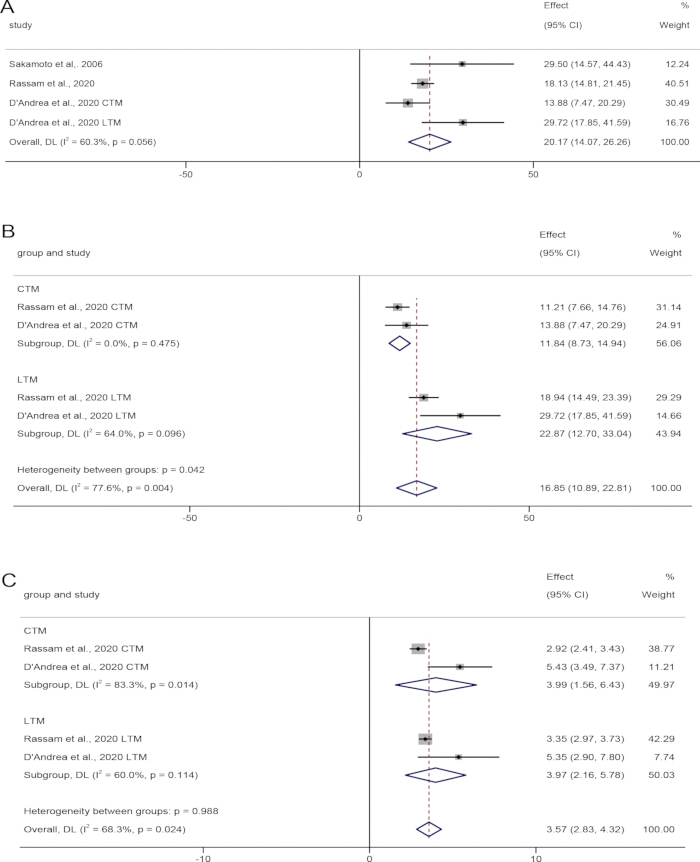
Figure 3. Forest plots of semen parameters in infertile men with testicular microlithiasis. (A) Overall pooled mean sperm concentration. (B) Subgroup analysis of sperm concentration according to TM classification (CTM vs LTM). (C) Subgroup analysis of normal sperm morphology. Abbreviations: CI = confidence interval; DL = DerSimonian–Laird method; CTM = classical testicular microlithiasis; LTM = limited testicular microlithiasis. Please click here to view a larger version of this figure.
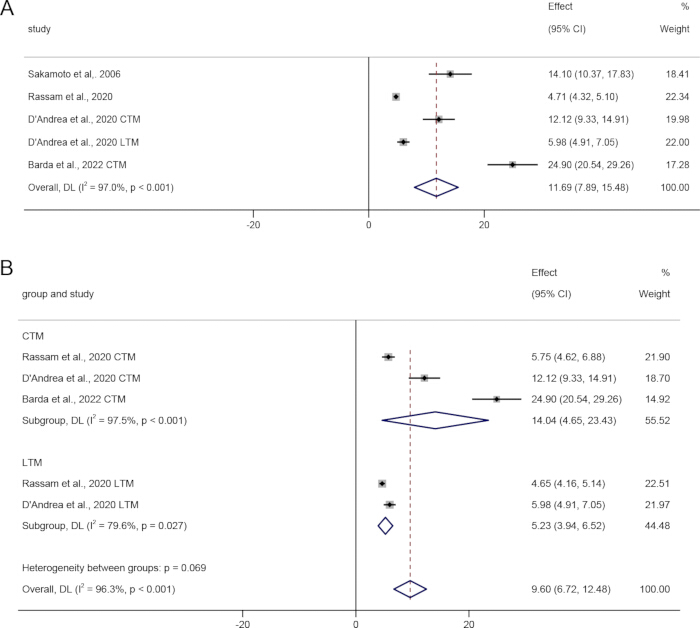
Figure 4. Forest plots of serum FSH levels in infertile men with testicular microlithiasis. (A) Overall pooled mean FSH level. (B) Subgroup analysis of FSH levels according to TM classification (CTM vs LTM). Abbreviations: CI = confidence interval; DL = DerSimonian–Laird method; FSH = follicle-stimulating hormone; CTM = classical testicular microlithiasis; LTM = limited testicular microlithiasis. Please click here to view a larger version of this figure.
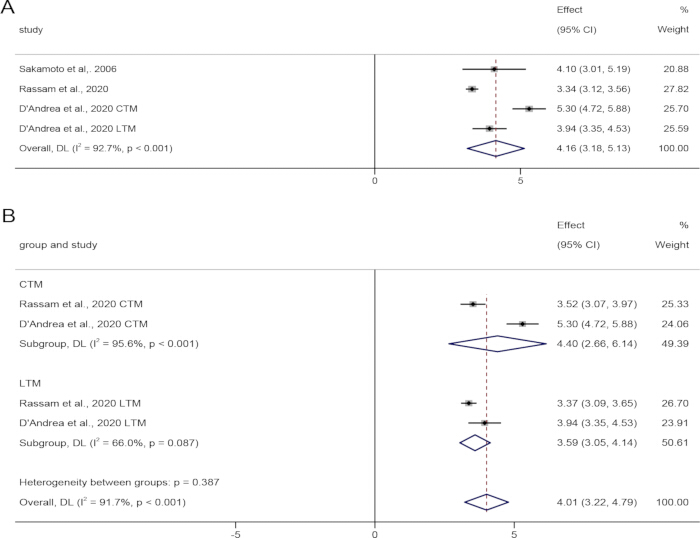
Figure 5. Forest plots of serum LH levels in infertile men with testicular microlithiasis. (A) Overall pooled mean LH concentration. (B) Subgroup analysis of LH levels according to TM classification (CTM vs LTM). Abbreviations: CI = confidence interval; DL = DerSimonian–Laird method; LH = luteinizing hormone; CTM = classical testicular microlithiasis; LTM = limited testicular microlithiasis. Please click here to view a larger version of this figure.
Supplemental Figure S1. Subgroup meta-analysis of varicocele prevalence according to TM classification. Abbreviations: CI = confidence interval; DL = DerSimonian–Laird method; TM = testicular microlithiasis; CTM = classical testicular microlithiasis; LTM = limited testicular microlithiasis.Please click here to download this file.
Supplemental Figure S2. Funnel plots for visual assessment of potential small-study effects or publication bias. (A) History of cryptorchidism. (B) Testicular cancer. (C) Varicocele. (D) Sperm concentration. (E) FSH. (F) LH. Abbreviations: FSH = follicle-stimulating hormone; LH = luteinizing hormone.Please click here to download this file.
Supplemental Table S1. Electronic search strategy.Please click here to download this file.
Supplemental Table S2. General characteristics of the included studies.Please click here to download this file.
Supplemental Table S3. Quality assessment of the included studies using Newcastle-Ottawa Scale.Please click here to download this file.
Discussion
To our knowledge, this is the first meta-analysis specifically focused on infertile men with TM that quantitatively synthesizes semen characteristics, coexisting testicular conditions, and reproductive hormone profiles. Compared with previous evidence syntheses that primarily focused on semen parameters, our study further extends the current evidence by providing pooled estimates of cryptorchidism, varicocele, testicular cancer, and reproductive hormone levels, together with subgroup analyses according to TM subtype11. A previous systematic review indicated that TM does not appear to be associated with pediatric testicular malignancies, whereas its clinical relevance in adults may depend on the presence of additional risk factors28. Our analysis showed that the pooled prevalence estimate of testicular cancer among infertile men with TM was 7.0%, which was broadly consistent with previously reported results29. Varicocele, a common clinical feature in male infertility, was also frequently reported in the included cohorts. Although several hypotheses have been proposed regarding a potential relationship between varicocele and TM, the available evidence remains insufficient to clarify the nature of this relationship30. Taken together, these findings describe a broad spectrum of testicular and reproductive characteristics reported in infertile men with TM and underscore the need for comprehensive clinical assessment in this population.
Regarding semen parameters, the WHO sixth edition reported a lower reference limit of 16 ×106/mL for sperm concentration31. In the present analysis, the pooled mean sperm concentration in infertile men with TM was approximately 20.17 × 10⁶/mL, which was slightly above this lower reference limit. However, this finding should not be interpreted as evidence of normal fertility potential, because infertility may occur despite sperm concentrations above the lower reference limit when abnormalities mainly involve motility, morphology, or other functional sperm parameters. The reference limit also does not represent an individual fertility cutoff32. Subgroup analysis showed that men with CTM had lower sperm concentrations than those with LTM. This finding is consistent with the recent meta-analysis by Wilson et al., which also reported lower sperm concentrations in CTM than in LTM11. Hiramatsu et al. reported a negative correlation between the number of microliths and sperm concentration, indicating less favorable semen profiles in men with a higher microlith burden33. Another retrospective study similarly reported lower sperm counts and smaller testicular volumes in men with more extensive TM13. Taken together, these findings suggest that a greater microlith burden may be accompanied by less favorable semen characteristics, although this observation requires further validation in larger studies. In contrast, we did not observe significant differences in the proportion of normal sperm morphology between TM subtypes. This may partly reflect the sensitivity of morphology assessment to laboratory protocols, staining methods, and observer variability. Moreover, the independent clinical value of sperm morphology in contemporary reproductive medicine remains debated, and morphology is increasingly interpreted as one component of a broader semen profile rather than as a reliable standalone marker for differentiating ultrasound-based TM subtypes34.
With respect to reproductive endocrine findings, FSH and LH levels varied considerably across the included studies. Although no significant differences were observed between the CTM and LTM subgroups, these findings should be interpreted cautiously due to substantial between-study variability. This heterogeneity may reflect differences in study populations, infertility characteristics, ultrasound classification criteria, and hormonal measurement methods. Therefore, the pooled hormonal estimates should be viewed as a descriptive summary of the available evidence rather than definitive indicators of endocrine status in infertile men with TM. Given the very high between-study heterogeneity for both FSH and LH, these pooled hormone estimates should be interpreted only as exploratory descriptive summaries, and no clinical inference should be based on the pooled point estimates alone. Further studies using standardized assessment methods are needed to clarify the potential clinical relevance of endocrine profiles across different TM subtypes.
This study has several limitations. First, although most included studies were of moderate methodological quality according to the NOS, several studies scored poorly in the outcome domain. In particular, many studies did not clearly report whether the outcomes of interest were present before or after TM detection, limiting the ability to assess the temporal relationship between TM and clinical or reproductive outcomes. This limitation makes it difficult to determine whether the observed characteristics were specifically related to TM or reflected pre-existing or coexisting testicular conditions. In addition, inadequate reporting of follow-up completeness and relatively short follow-up durations in some studies may have introduced attrition bias and limited the ascertainment of long-term outcomes, thereby affecting the reliability of pooled estimates. Furthermore, most included studies were retrospective and the overall number of eligible publications was limited, which may restrict the generalizability of the findings. Second, several pooled estimates showed substantial heterogeneity, likely reflecting differences in diagnostic definitions, ultrasound protocols, patient selection criteria, infertility characteristics, and laboratory assessment methods. Third, definitions of TM and its subtypes varied across studies, potentially affecting the comparability of results. Fourth, the absence of a non-TM control group limited the comparability of the study findings. Future prospective studies including appropriate infertile control groups are needed to clarify the clinical significance of TM in male infertility. Finally, reporting on potential confounding factors, such as age, comorbidities, and duration of infertility, was limited across studies, which may have affected the interpretability of subgroup comparisons.
In summary, this meta-analysis provides a descriptive synthesis of the available evidence on testicular microlithiasis in infertile men, offering an overview of their clinical characteristics, semen parameters, and reproductive endocrine profiles. The findings indicate that sperm concentration differed between CTM and LTM, whereas sperm morphology and gonadotropin levels were comparable across TM subtypes. Given the descriptive nature of the available evidence and the lack of appropriate control groups, further well-designed prospective studies are needed to better clarify the clinical significance of TM in male infertility.
Disclosures
The authors have no conflicts to disclose.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Cochrane Library | Cochrane | N/A | Database searched for eligible studies. |
| Embase | Elsevier | N/A | Database searched for eligible studies. |
| Medical Subject Headings (MeSH) | U.S. National Library of Medicine | N/A | Controlled vocabulary used in the search strategy. |
| Newcastle-Ottawa Scale (NOS) | N/A | N/A | Tool used to assess the methodological quality of observational studies. |
| PubMed | U.S. National Library of Medicine | N/A | Database searched for eligible studies. |
| Stata 17.0 | StataCorp LLC | N/A | Software used for statistical analysis. |
| Web of Science | Clarivate | N/A | Database searched for eligible studies. |
| WHO semen analysis criteria/manuals (1999 and 2010) | World Health Organization | N/A | Reference criteria used to extract semen parameters according to the versions reported in the original studies. |
References
- Dinkelman-Smit M. Management of testicular microlithiasis. Eur Urol Focus. 2021;7(5):940-2.
- Anvari Aria S, et al. Testicular microlithiasis on scrotal ultrasound in 4850 young men from the general population: associations with semen quality. Andrology. 2020;8(6):1736-43.
- Serter S, et al. Prevalence of testicular microlithiasis in an asymptomatic population. Scand J Urol Nephrol. 2006;40(3):212-4.
- Barda S, et al. Testicular microlithiasis defines a subgroup of azoospermic men with low rates of sperm retrieval. Int J Urol. 2022;29(1):65-8.
- Zhou J, Hu S, Ouyang Y, Liu M. Testicular microlithiasis and male fertility: a dual perspective integrating imaging and physiological insights. Reprod Biol Endocrinol. 2025;23(1):128.
- Rodprasert W, Virtanen HE, Toppari J. Cryptorchidism and puberty. Front Endocrinol (Lausanne). 2024;15:1347435.
- Huyghe E, Methorst C, Faix A. Varicocèle et infertilité masculine [Varicocele and male infertility]. Prog Urol. 2023;33(13):624-35.
- Fang Y, et al. Varicocele-mediated male infertility: from the perspective of testicular immunity and inflammation. Front Immunol. 2021;12:729539.
- Yee WS, et al. Testicular microlithiasis: prevalence and clinical significance in a population referred for scrotal ultrasonography. Korean J Urol. 2011;52(3):172-7.
- Yilmaz M, Kong CHC, Mostafa T. Diagnostic and prognostic implications of testicular microlithiasis. Arab J Urol. 2025;23(3):210-4.
- Wilson HG, Birch BR, Rees RW. Is testicular microlithiasis associated with decreased semen parameters? A systematic review. Basic Clin Androl. 2024;34(1):23.
- Kobayashi H, et al. Evaluation of testicular microlithiasis in varicoceles. Reprod Med Biol. 2002;1(2):75-9.
- D’Andrea S, et al. Clinical and seminal parameters associated with testicular microlithiasis and its severity in males from infertile couples. Hum Reprod. 2021;36(4):891-8.
- World Health Organization. WHO laboratory manual for the examination and processing of human semen. 5th ed. World Health Organization; Geneva; 2010.
- World Health Organization. WHO laboratory manual for the examination of human semen and sperm-cervical mucus interaction. 4th ed. Cambridge University Press; Cambridge; 1999.
- Bennett HF, Middleton WD, Bullock AD, Teefey SA. Testicular microlithiasis: US follow-up. Radiology. 2001;218(2):359-63.
- Aizenstein RI, Didomenico D, Wilbur AC, O’Neil HK. Testicular microlithiasis: association with male infertility. J Clin Ultrasound. 1998;26(4):195-8.
- de Gouveia Brazao CA, et al. Bilateral testicular microlithiasis predicts the presence of the precursor of testicular germ cell tumors in subfertile men. J Urol. 2004;171(1):158-60.
- La Vignera S, et al. Testicular microlithiasis: analysis of prevalence and associated testicular cancer in central-eastern Sicilian andrological patients. Andrologia. 2012;44(Suppl 1):295-9.
- Mazzilli F, et al. Seminal profile of subjects with testicular microlithiasis and testicular calcifications. Fertil Steril. 2005;84(1):243-5.
- Negri L, et al. Cancer risk in male factor-infertility. Placenta. 2008;29(Suppl 2):178-83.
- Pierik FH, et al. Is routine scrotal ultrasound advantageous in infertile men? J Urol. 1999;162(5):1618-20.
- Qublan HS, Al-Okoor K, Al-Ghoweri AS, Abu-Qamar A. Sonographic spectrum of scrotal abnormalities in infertile men. J Clin Ultrasound. 2007;35(8):437-41.
- Raj V. Role of ultrasonographic findings with clinical and laboratory findings in identification of intra and extra testicular causes of male infertility. J Pharm Negat Results. 2022;13(Spec Issue 5):2404-9.
- Rassam Y, Gromoll J, Kliesch S, Schubert M. Testicular microlithiasis is associated with impaired spermatogenesis in patients with unexplained infertility. Urol Int. 2020;104(7-8):610-6.
- Sakamoto H, et al. Testicular microlithiasis identified ultrasonographically in Japanese adult patients: prevalence and associated conditions. Urology. 2006;68(3):636-41.
- Thomas K, Wood SJ, Thompson AJM, Pilling D, Lewis-Jones DI. The incidence and significance of testicular microlithiasis in a subfertile population. Br J Radiol. 2000;73(869):494-7.
- ’t Hoen LA, et al. The prognostic value of testicular microlithiasis as an incidental finding for the risk of testicular malignancy in children and the adult population: a systematic review. On behalf of the EAU Pediatric Urology Guidelines Panel. J Pediatr Urol. 2021;17(6):815-31.
- Barbonetti A, et al. Testicular cancer in infertile men with and without testicular microlithiasis: a systematic review and meta-analysis of case-control studies. Front Endocrinol (Lausanne). 2019;10:164.
- Finelli R, Leisegang K, Kandil H, Agarwal A. Oxidative stress: a comprehensive review of biochemical, molecular, and genetic aspects in the pathogenesis and management of varicocele. World J Mens Health. 2022;40(1):87-103.
- Björndahl L, Kirkman Brown J, other editorial board members of the WHO Laboratory Manual for the Examination and Processing of Human Semen. The sixth edition of the WHO laboratory manual for the examination and processing of human semen: ensuring quality and standardization in basic examination of human ejaculates. Fertil Steril. 2022;117(2):246-51.
- Boitrelle F, et al. The sixth edition of the WHO manual for human semen analysis: a critical review and SWOT analysis. Life (Basel). 2021;11(12):1368.
- Hiramatsu I, et al. Prevalence of testicular microlithiasis in healthy newlywed men trying for first-time pregnancy. Int J Urol. 2020;27(11):990-5.
- Pelzman DL, Sandlow JI. Sperm morphology: evaluating its clinical relevance in contemporary fertility practice. Reprod Med Biol. 2024;23(1):e12594.