This protocol outlines a procedure for inducing differentiation of human hematopoietic stem and progenitor cells derived from patient bone marrow and peripheral blood mononuclear cells. The assay uses a semisolid culture medium supporting erythroid and myeloid lineage commitment and incorporates standardized metrics for reproducible colony classification for preclinical drug characterization.
Method Article
Colony-Forming Unit Assay Adapted For Patient-Derived Bone Marrow and Peripheral Blood Mononuclear Cells
In This Article
Summary
Abstract
The colony-forming unit (CFU) assay is a foundational technique for studying hematologic diseases, including myelodysplastic syndromes (MDS) and acute myeloid leukemia (AML). This assay employs semisolid media supplemented with defined cytokine combinations to support three-dimensional growth and lineage-specific differentiation of erythroid and myeloid progenitor cells. However, patient-derived peripheral blood and bone marrow samples present technical challenges due to reduced viability, increased sensitivity to handling, and variability in colony growth. Furthermore, existing guidelines for identifying and counting colonies show substantial variability in defining colony size and lineage types, limiting reproducibility across studies. The protocol described herein is optimized for the growth and differentiation of hematopoietic stem and progenitor cells isolated from MDS and AML patient samples. The protocol emphasizes gentle cell handling, sterile processing of patient specimens, optimized culture conditions, and growth durations tailored to patient-derived cells. This protocol provides a practical framework for CFU assays using patient-derived samples and establishes a standard metric for consistent colony counting and analysis in hematologic malignancy research.
Introduction
Hematopoiesis is a tightly regulated process in which hematopoietic stem cells (HSCs) residing in bone marrow niches give rise to all mature blood cell lineages. Through a hierarchical series of differentiation events, HSCs generate multipotent progenitors that progressively commit to erythroid, myeloid, and lymphoid lineages before undergoing terminal maturation into functional circulating blood cells. This process is governed by coordinated signaling within the bone marrow microenvironment and by intrinsic transcriptional and epigenetic regulatory mechanisms. Disruptions to these regulatory pathways, particularly through the accumulation of genetic or somatic mutations in HSCs, can impair normal differentiation and lead to clonal expansion of abnormal progenitors. Such alterations may ultimately result in hematologic disorders characterized by ineffective hematopoiesis and cytopenias, including myelodysplastic syndromes (MDS) and acute myeloid leukemia (AML)1,2,3,4,5.
The colony-forming unit (CFU) assay is a well-established in vitro technique for evaluating the differentiation potential of hematopoietic stem and progenitor cells (HSPCs). Originally developed as a short-term assay to measure the proliferative and differentiation capacity of hematopoietic progenitors6,7,8, the CFU assay has since become a widely used tool in both clinical and experimental hematology9. In preclinical laboratory settings, the assay is frequently used to assess the impact of genetic perturbations or candidate therapeutics on hematopoietic differentiation. Within the context of MDS and AML research, CFU assays provide a functional readout for understanding how molecular and genetic alterations influence the differentiation capacity of patient-derived bone marrow or peripheral blood cells.
The CFU assay involves culturing HSPCs in a methylcellulose-based semisolid medium supplemented with defined growth factors that support lineage-specific expansion and differentiation. Under these conditions, progenitor cells proliferate and give rise to discrete colonies, which can be morphologically classified according to lineage identity. A commercially available methylcellulose-based semisolid medium optimized for erythroid and myeloid differentiation is utilized in this protocol. The medium contains a combination of cytokines, including interleukin-3 (IL-3), interleukin-6 (IL-6), stem cell factor (SCF), erythropoietin (EPO), granulocyte colony-stimulating factor (G-CSF), and granulocyte-macrophage colony-stimulating factor (GM-CSF). Together, these factors support the growth of erythroid progenitors such as colony-forming unit-erythroid (CFU-E) and burst-forming unit-erythroid (BFU-E), myeloid granulocyte-macrophage progenitors (CFU-GM), and multipotent progenitors such as granulocyte, erythrocyte, monocyte, megakaryocyte progenitors (CFU-GEMM)10,11.
Despite its broad utility, the above-mentioned semisolid medium is limited in its differentiation capacity, as it does not adequately support differentiation of megakaryocytes and platelets. For these applications, more specialized formulations containing platelet growth factors are more appropriate; however, they are out of scope for the outlined protocol. Overall, through careful selection of media formulation combined with morphological assessment and downstream analyses such as flow cytometry, researchers can effectively evaluate drug sensitivity through analysis of lineage commitment and differentiation potential12.
In this study, the CFU assay is used to investigate the therapeutic potential of combination therapies for the treatment of relapsed/refractory high-risk MDS. Pyrimethamine is a clinically approved antifolate used to treat toxoplasmosis and parasitic malaria, and has recently been studied as an anti-cancer agent13,14,15. Recent studies have demonstrated that pyrimethamine treatment may act through inhibition of key pathways that regulate de novo pyrimidine synthesis16. Here in this protocol, CFU assays are utilized to investigate the clinical efficacy of pyrimethamine as single-agent therapy and as a combination therapy with Venetoclax, which is a current frontline therapy for MDS and AML treatment17,18.
Despite its widespread utility, the CFU assay presents several technical limitations. Colony identification and classification rely heavily on morphological criteria, which can introduce variability between observers and across research centers6,19,20,21. Additionally, patient-derived samples from individuals with MDS or AML often exhibit reduced cell viability, increased fragility, and heterogeneity, which can complicate colony formation and downstream analyses9. Preparation of colonies for further characterization, including flow cytometry, may therefore require careful handling to preserve cell integrity. The absence of standardized procedures for colony identification, counting, and downstream analysis further contributes to variability across studies. These technical considerations highlight the need for standardized procedures optimized specifically for patient-derived hematopoietic samples.
This protocol outlines an optimized workflow for performing CFU assays using mononuclear cells derived from primary bone marrow or peripheral blood specimens of patients with hematologic malignancies. The approach focuses on practical strategies for handling sensitive patient-derived cells, establishing reliable culture conditions, and implementing consistent criteria for colony identification and quantification. By providing detailed methodological guidance and emphasizing reproducible analysis practices, this protocol aims to facilitate more reliable evaluation of hematopoietic differentiation and therapeutic response in preclinical studies of MDS and AML.
Protocol
This study utilizes de-identified human biospecimens obtained from a biobank under an Institutional Review Board–approved protocol, “Molecular Biology of Benign and Malignant Hematological Disorders” (IRB Protocol #200536), at Albert Einstein College of Medicine/Montefiore Medical Center. All procedures were conducted in accordance with institutional ethics guidelines. All reagents and equipment are listed in the Table of Materials.
1. Preparation of patient-derived bone marrow or peripheral blood mononuclear cells
NOTE: According to common patient-sample handling guidelines, it is recommended to wear a full-length lab coat and tear-resistant laboratory disposable gloves and to work under a laboratory cell culture hood for personal protection from bloodborne pathogen exposure. All pipette tips and serological pipettes that come into contact with patient cells should be soaked in a 10% bleach solution for at least 30 min prior to disposal in biohazard waste.
- Experimental preparation
- Warm IMDM media, fetal bovine serum (FBS), and penicillin-streptomycin (Pen-strep) antibiotics to 37 °C for at least 30 min.
- Thaw semisolid media in 4 °C overnight. On the day of plating, warm the bottle to room temperature (RT) for at least 30 min.
- Sterilize the cell culture hood with UV sterilization for 15 min, then spray the hood surfaces, pipettes, and tube racks with 70% ethanol (EtOH).
- Prepare a waste beaker containing 10% bleach solution large enough to collect contaminated pipette tips and serological pipettes.
- Obtain bone marrow or peripheral blood mononuclear cells isolated through density gradient centrifugation methods. Cells can be used on the same day of collection or from frozen bio-banked samples.
- If samples are frozen, thaw them rapidly in a 37 °C water bath until most of the ice has melted and only a small ice crystal remains. Immediately place the samples on ice after thawing.
NOTE: Patient samples are very sensitive to thawing. It is important to thaw samples as quickly as possible and in batches to minimize cell death. - Suspend cells in 5 mL warmed complete growth media (IMDM media supplemented with 4% FBS and 1% Pen-Strep).
- Determine the cell concentration and viability using AO/PI staining dye and an automated cell counter.
- Centrifuge the cells at 350 x g for 5 min at room temperature to pellet the cells. Discard supernatant.
- Resuspend cells in 5 mL sterile Dulbecco’s phosphate-buffered saline (DPBS). Repeat centrifugation to pellet cells and discard supernatant.
- Suspend cells in complete growth media to a concentration of 2 million live cells/mL. Prepare enough cells for 100K cells/well of a 6-well plate.
2. Drug preparation and treatment administration.
NOTE: Pyrimethamine is obtained as a lyophilized powder and is reconstituted in-house in dimethyl sulfoxide (DMSO) at a concentration of 100 mM; aliquots are stored in −80 °C. Venetoclax is purchased pre-dissolved in DMSO at a concentration of 10 mM and is stored in -20 °C. For this experiment, venetoclax and pyrimethamine are administered as a single dose via free uptake in parallel with a vehicle control DMSO treatment condition.
CAUTION: Pyrimethamine, venetoclax, and DMSO are biohazardous agents. Handle only under the hood, wearing PPE, and use with extra caution.
- On the day of plating, thaw drug aliquot on ice, vortex, and spin down at max-speed on a tabletop mini centrifuge for 30 s.
- Vortex and mix a bottle of semisolid media vigorously until all components are homogenized. Leave undisturbed in the hood at room temperature for 30 min to allow bubbles to rise to the surface.
- Prepare 3 mL aliquots of semisolid media in sterile 15 mL conical tubes. Allow tubes to remain undisturbed for 30 min to allow bubbles to rise to the surface. Extra semisolid media aliquots can be re-frozen and stored in -20 °C for later use.
- Add no more than 10 µL of drug volume to the semisolid media. For this experiment, venetoclax and pyrimethamine concentrations are adjusted according to empirically determined synergistic conditions. To a vehicle control group, add equivalent volumes of DMSO. Prepare duplicate 3 mL aliquots for each condition.
NOTE: It is important to keep the volume of drug added negligible so that it does not affect the final concentration of drug in the semisolid media. - Vortex media in 4–5 short bursts to fully incorporate the drug into the media.
NOTE: Do not hold cell mixture on the vortexor for extended periods of time, as this could cause cell death. - Add 100 µL of cells or an equivalent volume of 2,00,000 cells to the 3 mL aliquots of semisolid media. Vortex mixture in short bursts until fully incorporated/ homogenized.
- Attach a blunt-end 16 G needle to a 3 mL syringe and drop the needle and syringe into the cell mixture. Leave undisturbed for 30 min to allow bubbles to rise to the surface.
3. Plating of drug-treated cell suspension.
- Using a submerged needle and syringe, take up the cell and drug mixture, being careful not to aspirate any air bubbles. Wait 3–5 min, then take up the remaining mixture that has collected on the sides of the 15 mL conical tube.
- In a sterile 6-well plate, add the cell mixture dropwise, alternating large drops between 2 wells of an outer column of the plate. Spread the mixture by gently tilting the plate in circular motions to evenly cover the entirety of the bottom of the wells. These two wells constitute technical replicates.
NOTE: If bubbles form or are accidentally added to the wells, use a pipette filter tip to gently pop or move the bubbles to the plate edge. Any large bubbles left in the plate can affect the growth of colonies. - Add the colony assay mixture only to the outer columns of the 6-well plate. To the center column, add 5 mL of sterile water to each well. Adding water to the wells will ensure that enough moisture is present to keep the semisolid medium from drying up.
- Incubate the plate in a 37 °C incubator with 5% CO2. Monitor cell growth and water levels 2x/week. Cells should form colonies visible by eye at around 7 days post-plating, and plates should reach 75%–80% confluency somewhere between 14–21 days post-plating.
4. Colony imaging and counting
NOTE: This protocol describes parameters that are validated for use on the EVOS M7000 imaging system. These settings may need to be optimized or adapted for compatibility with other plate imaging systems.
- Remove the protective light filter cover from the microscope platform. Turn on the microscope and open the associated software program.
- Insert a light diffuser into the top lens of the microscope apparatus.
- Insert the plate position onto the platform such that well A1 is in the top left corner.
- In the imaging software, input the following focus settings:
- Select the vessel to be imaged. In this protocol, a 6-well plate is used.
- Set the objective to 4X.
- Select the light source as Trans or switch the microscope to brightfield mode.
- Turn on the microscope light and manually adjust the light intensity using the coarse slider. For the instrument used in this protocol, the optimal range for imaging colonies is around 0.03.
- If there is an autofocus feature on the instrument, use it to adjust the focus. If needed, adjust the focus further using the manual fine focus settings.
- Input the following automated image capture settings:
- Select the entire well area to be imaged in each well.
- Select the automated image capture to begin from the center of the well and spiral outward toward the edges of the well.
- Select autofocus settings such that the instrument re-focuses in each well.
- Select for the raw images in each well to be tiled/merged together.
- Select for the images to be inverted horizontally and vertically.
- Select data saving settings to collect “tiled image” and “merged image”
- Run the automated plate scan. The instrument used in this protocol will run at a speed of 1.5 min/well.
- Remove the plate, place the protective filter cover over the microscope platform, switch off the microscope, and close the software.
- Following imaging, count total individual colonies as well as myeloid and erythroid subtypes in each well manually using the tiled merged well images.
- Define colonies according to the following morphology characterization:
- Consider an individual colony or colony cluster distinct when it is far enough from another cell population, a distance equal to its own length. Populations that are within this distance limit are grouped into one colony count.
- Ensure that the erythroid colonies are deeply pigmented and appear dark red in color. These colonies appear as densely growing single populations or clusters with clearly defined edges. Smaller erythroid colonies consisting of slow-growing immature cell populations are classified as CFU-E. Larger colonies with more mature populations are classified as BFU-E.
- Check that the myeloid colonies contain cells that appear more translucent and are lighter in color. Myeloid colonies are more dispersed and do not contain clearly defined edges. Myeloid colonies tend to grow more often as single populations rather than clusters, although occasionally clusters may be seen. In both cases, myeloid colonies are classified as CFU-GM.
- Classify the mixed colonies that contain both erythroid and myeloid subtypes as CFU-GEMM.
5. Cell harvesting and freezing for downstream analysis via flow cytometry
- Perform the steps below prior to starting:
- a. Prepare and warm fluorescence-activated cell sorting buffer (FACS buffer, composed of DPBS/4% FBS) and freezing media (FBS/10% DMSO) in a 37 °C water bath for at least 30 min.
- Add 5 mL of warmed FACS buffer to the surface of each well. Incubate plates for at least 30 min in a 37 °C incubator to dissolve the semisolid media.
- Thoroughly resuspend cells using a 5 mL pipette and transfer to a sterile 50 mL conical tube.
- Using 5 mL of warmed FACS buffer, wash each well 3 times and transfer the entire volume to the 50 mL conical tube.
- Resuspend cells well by vortexing in 4–5 short bursts, then centrifuge at 400 x g for 10 min at RT to pellet cells. If the pellet is not visible after centrifugation, the cells remain suspended in semisolid media. Without aspirating, add an extra 10–15 mL DPBS to the tube to further dilute the semisolid medium and resuspend well. If necessary, incubate at 37 °C for 10–15 min to fully dissolve the media, then pellet cells again.
- Aspirate the supernatant and resuspend the cells in 10 mL FACS buffer. Centrifuge at 400 x g for 10 min at RT to pellet cells.
- Resuspend cells in freezing media and aliquot 3 million cells/cryovial. Freeze vials in a controlled-rate freezing container at -80 °C for 24 h to achieve 1 °C / min cooling rate.
- Transfer cryovials to liquid nitrogen storage as soon as possible.
NOTE: Samples kept at -20 °C for long periods of time will have reduced viability. It is important to move cells to liquid nitrogen for long-term storage.
Results
Figure 1 illustrates the colony assay pipeline from patient sample isolation through analysis of colony counts and colony morphology. Figure 2 displays key settings for imaging colonies on a brightfield microscope. Figure 3 and Figure 4 show representative images of colony formation from a single patient-derived sample at 13 days post-plating. In Figure 3, colonies are imaged using an automated fluorescence imaging system. The images are scored by manually counting colonies according to morphology. Figure 3A shows the comparison of control DMSO-treated cells with pyrimethamine as a single agent, venetoclax as a single agent, and combination treatment conditions. Enumerated counts shown in Figure 3B show fewer overall colonies in the pyrimethamine single-agent treatment and a combinatorial effect with venetoclax, suggesting that monotherapy or combination therapy might be a promising strategy to reduce leukemic blast proliferation and inhibit malignant growth in this individual patient. To validate the combined treatment effects further, multiple patients have similarly been assessed for response to Venetoclax and/or pyrimethamine-based treatment16. Further analysis via flow cytometry can be done to assess the differentiation capacities of the cells that formed colonies to characterize the drugs’ effects in a more granular way. It is important to note that absolute erythroid/myeloid counts can have considerable inter-patient and inter-disease variability. When analyzing colony counts across different patients or disease stages (MDS or AML), it is encouraged to compare the relative changes in erythroid/myeloid colony abundance in drug-treated vs. vehicle control-treated samples rather than comparing absolute counts between patients.
Figure 4A shows representative images of myeloid colonies taken using an inverted fluorescence microscope at 4x magnification. This imaging system provides high-resolution images of single colonies at 4x magnification. For the purposes of this protocol, images from the above imaging system are included solely for illustrative purposes to clearly visualize colony morphology and define subtype characterization methods. Myeloid colonies appear as dispersed clusters without clearly defined edges, and are typically more translucent and less pigmented (Figure 4A). Erythroid colonies appear as more defined, dense colonies or colony clusters with red or dark pigmentation and clear, defined edges (Figure 4B). If colonies overlap, they are categorized as mixed, multipotent progenitor colonies or “GEMM” (Figure 4C). A truly distinct colony should be a distance away from surrounding colonies equal to its own length to be counted. For example, populations in the right-most image in Figure 4C are scored as 2 colonies, while the right-most images in Figure 4A,B are each scored as a singular colony. Using a combined system of colony counting and morphology assessment, it is possible to gather information on the general differentiated state of the erythroid and myeloid progenitors. The left and right images in Figure 4B are larger and/or contain more cell cluster populations than the smaller erythroid colony in the center image; for this reason, they would be scored as burst-forming units, or “BFU-E”. However, the center image in Figure 4B shows a smaller colony, which would be scored as a colony-forming unit or “CFU-E”. Figure 4C represents mixed colonies or “GEMM”. Note that the colonies are closer in distance than their respective sizes to be counted as mixed lineage.
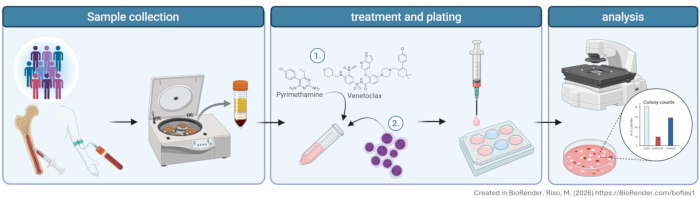
Figure 1: Schematic of patient-derived CFU assay for preclinical drug characterization. This image shows a graphic schematic outlining the protocol. Bone marrow and peripheral blood samples are collected from patients or from a biobank, and mononuclear cells are isolated via gradient centrifugation. Drugs, then cells, are mixed into semisolid media and plated using a blunt syringe in alternating droplets. Following colony formation, colonies are imaged via brightfield microscopy, and erythroid and myeloid colonies are scored and counted. Please click here to view a larger version of this figure.
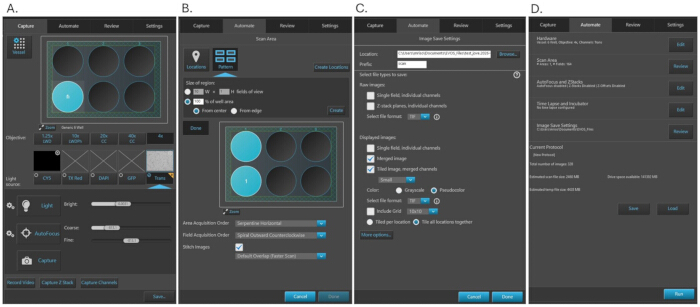
Figure 2: Settings of the fluorescence imaging system. (A) shows focus settings for plate imaging. (B) shows image capture automation settings. (C) shows image saving settings. (D) shows image run and saving settings. Please click here to view a larger version of this figure.
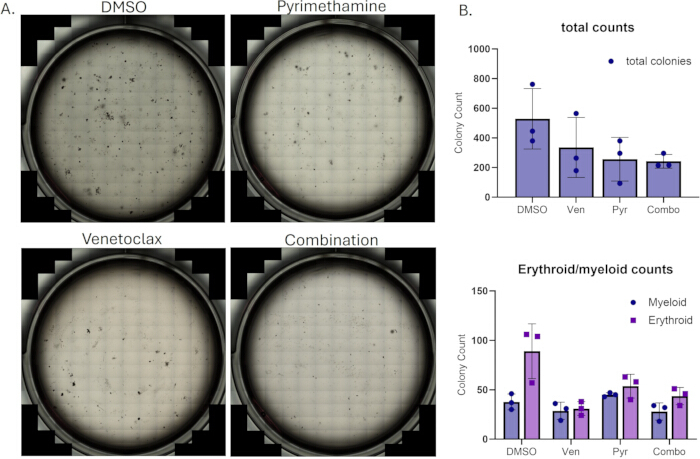
Figure 3: Myeloid/Erythroid colony counting and analysis. (A) shows colony images taken on the fluorescence imaging system. The colony assay was performed using a single MDS patient sample. (B) shows quantification of colony counts from the same experiment. Data are presented as mean ± SD from 3 technical replicates per condition. Statistical analysis was performed using one-way ANOVA on technical replicates from a single representative experiment. The experiment was independently repeated twice (n = 2 biological replicates) with similar results. (B) is adapted from Rivera-Peña16. Please click here to view a larger version of this figure.
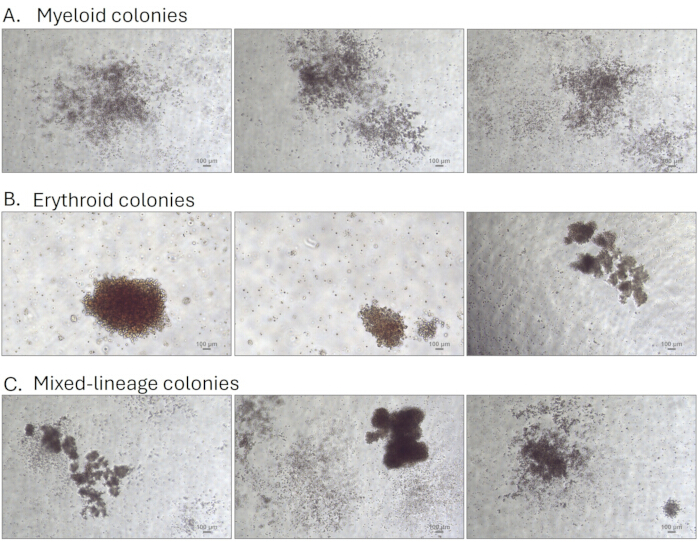
Figure 4: Myeloid/Erythroid colony morphology. (A) shows representative myeloid colony morphology. (B) shows erythroid colony morphology. (C) shows mixed-lineage colony morphology. Scale bars: 100 µm. Please click here to view a larger version of this figure.
Discussion
The protocol described here outlines an optimized workflow for performing CFU assays using primary bone marrow and peripheral blood samples from patients, with particular attention to maintaining cell viability and ensuring reproducible colony growth. Several steps in the protocol are critical for achieving reliable colony formation when working with patient-derived samples. Rapid thawing of cryopreserved mononuclear cells followed by immediate cooling is essential for preserving cell viability, as prolonged thawing can substantially increase cell death in fragile primary samples. Gentle handling during washing and resuspension steps is equally important since excessive mechanical stress can reduce progenitor survival and negatively affect colony formation.
Preparation of methylcellulose-based semisolid media also requires careful handling. Thorough mixing is necessary to homogenize cytokines and supplements within the medium, while allowing the mixture to rest prior to plating helps eliminate bubbles that may interfere with colony growth. In addition, uniform mixing of cells within the semisolid matrix is essential to ensure consistent plating density across technical replicates. Even distribution of cells throughout the medium minimizes variability in colony formation and improves reproducibility between experimental conditions.
Troubleshooting strategies are particularly important when colony formation is suboptimal. Reduced colony numbers may result from low initial cell viability, inaccurate cell counting, or insufficient mixing of cells within the semisolid matrix. In such cases, verifying cell viability prior to plating, adjusting cell density, or repeating the mixing step can improve experimental outcomes. In addition, incomplete dissolution of semisolid media during colony harvesting can interfere with downstream cell recovery; incubation with warmed buffer and gentle mixing can help fully dissolve the matrix prior to centrifugation.
Besides those addressed in this protocol, the CFU assay has other unavoidable limitations that should be considered when interpreting results. CFU assays represent a simplified in vitro system that does not fully recapitulate the complex cellular interactions and microenvironmental cues present within the bone marrow niche22. As a result, colony formation may not always reflect the full spectrum of hematopoietic behavior observed in vivo. Another limitation is the inherent variability of patient-derived samples, which may differ in cellular composition, viability, and colony-forming potential depending on disease type, stage, treatment history, and sample handling conditions1,23. It is important to note that this protocol has provided representative data from a single patient at a single institution; independent validation in additional cohorts is required before reproducibility can be fully assessed.
Nevertheless, CFU assays remain a powerful tool for assessing functional responses of hematopoietic progenitors to experimental perturbations. Compared with alternative approaches such as bulk proliferation assays or short-term viability measurements, CFU assays provide a direct readout of lineage-specific differentiation potential24,25,26. This makes the assay particularly valuable for evaluating therapies aimed at restoring or modifying hematopoietic differentiation programs for myeloid and erythroid lineages. The ability to assess functional responses of patient-derived progenitor cells ex vivo also makes this method especially valuable for preclinical drug evaluation and translational research.
Emerging approaches incorporating automated imaging and artificial intelligence–based analysis have the potential to address limitations of manual counting and scoring by enabling standardized, high-throughput, and reproducible colony detection and classification. Such tools can reduce user bias, improve accuracy, and generate permanent digital records for downstream analysis27. As these technologies continue to advance, integration of AI-assisted workflows may further enhance the scalability and rigor of CFU-based assays in both research and clinical settings.
In this study, the CFU assay is used to assess the effects of a pyrimidine-based therapy as a single agent and in combination with venetoclax. By measuring colony formation following treatment, the assay enables functional evaluation of how novel therapies influence colony viability and progenitor cell differentiation in primary patient samples. Overall, this optimized CFU assay workflow provides a practical framework for studying hematopoietic differentiation in primary patient-derived samples and for evaluating candidate therapeutics targeting hematologic diseases.
Disclosures
The authors have no other conflicts of interest to disclose.
Acknowledgements
This work was supported by a pilot grant from the Einstein-Rockefeller-CUNY Center for AIDS Research, funded by the National Institutes of Health (NIH): P30 AI124414. The Einstein FACS Core Facility and shared instrument usage were supported by the following NIH grants: P30CA013330, S10OD026833, and S10OD032169.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Blunt-End 16 G needles | STEMCELL Technologies | 28110 | for dispensing and plating MethoCult media |
| Cellometer Auto 2000 | Nexelcom Bioscience | 26407 | cell counter |
| CHT4 Counting Chambers (cell counter slides) | Revvity | CHT4-SD100-002 | slides for cell counter |
| Dimethyl sulfoxide | Fisher Bioreagents | BP231-100 | used for drug reconstitution and cell freezing media |
| Dulbecco's Phosphate Buffered Saline | Sigma-Aldrich | D8537 | for cell culture |
| Ethanol 200 proof | Decon Laboratories, Inc. | 2701 | for sterilization of cell culture surfaces |
| EVOS M7000 imaging system | ThermoFisher Scientific | AMF7000 | for colony and plate imaging |
| Fetal bovine serum | BenchMark | 100-106 | media supplement for cell culture and freezing |
| IMDM Modified Culture media | Cytiva | SH30228.01 | enriched culture media suitable for patient sample handling |
| LuerLok Tip 3 mL Syringes | BD | 309657 | for dispensing and plating MethoCult media |
| MethoCult H4435 Enriched | STEMCELL Technologies | 04435 | methylcellulose-based semisolid media for colony assay |
| Multiwell 6-well plate | FALCON | 353046 | for colony assay plating |
| Nikon Eclipse TS2FL Inverted Trinocular Phase Contrast Fluorescence Microscope | Coastal Microscopes | 51623 | For colony morphology imaging and characterization |
| Pen Strep | Gibco | 15140-122 | antibiotic supplement for cell culture |
| pyrimethamine | Sigma-Aldrich | 46706 | FDA-approved antifolate |
| UltraPure Distilled water | Invitrogen | 10977-015 | for colony assay plating |
| venetoclax | Selleck Chemical LLC | 50-136-6419 | FDA-approved chemotherapy |
| ViaStain AOPI Staining Solution | Revvity | CS2-0106 | viability stain for live cell counting |
References
- Papaemmanuil E, Gerstung M, Malcovati L, Tauro S, Gundem G, Van Loo P, et al. Clinical and biological implications of driver mutations in myelodysplastic syndromes. Blood. 2013;122(22):3616-27.
- Desai P, Mencia-Trinchant N, Savenkov O, Simon MS, Cheang G, Lee S, et al. Somatic mutations precede acute myeloid leukemia years before diagnosis. Nat Med. 2018;24(7):1015-23.
- Gaulin C, Kelemen K, Arana Yi C. Molecular pathways in clonal hematopoiesis: from the acquisition of somatic mutations to transformation into hematologic neoplasm. Life (Basel). 2022;12(8):1135.
- Menssen AJ, Walter MJ. Genetics of progression from MDS to secondary leukemia. Blood. 2020;136(1):50-60.
- Fabre MA, de Almeida JG, Fiorillo E, Mitchell E, Damaskou A, Rak J, et al. The longitudinal dynamics and natural history of clonal haematopoiesis. Nature. 2022;606(7913):335-42.
- Purton LE, Scadden DT. Limiting factors in murine hematopoietic stem cell assays. Cell Stem Cell. 2007;1(3):263-70.
- Yusoff NA, Abd Hamid Z, Budin SB, Taib IS. Hematopoietic stem cell discovery: unveiling the historical and future perspective of colony-forming units assay. PeerJ. 2025;13:e18854.
- Franken NAP, Rodermond HM, Stap J, Haveman J, van Bree C. Clonogenic assay of cells in vitro. Nat Protoc. 2006;1(5):2315-9.
- Cho JH, Kim JS, Kim ST, Hong JY, Park JO, Park YS, et al. Selective colony area method for heterogeneous patient-derived tumor cell lines in anti-cancer drug screening system. PLoS One. 2019;14(4):e0215080.
- Mayani H, Dragowska W, Lansdorp PM. Cytokine-induced selective expansion and maturation of erythroid versus myeloid progenitors from purified cord blood precursor cells. Blood. 1993;81(12):3252-8.
- STEMCELL Technologies. Human colony-forming unit (CFU) assays using MethoCult. Technical manual version 4.6.0. Vancouver (BC): STEMCELL Technologies; 2019.
- Gribaldo L, Casati S, Castoldi AF, Pessina A. Comparison of in vitro drug-sensitivity of human granulocyte-macrophage progenitors from two different origins: umbilical cord blood and bone marrow. Exp Hematol. 1999;27(11):1593-8.
- Brown JI, Persaud R, Iliev P, Karmacharya U, Attarha S, Sahile H, et al. Investigating the anti-cancer potential of pyrimethamine analogues through a modern chemical biology lens. Eur J Med Chem. 2024;264:115971.
- Liu H, Qin Y, Zhai D, Zhang Q, Gu J, Tang Y, et al. Antimalarial drug pyrimethamine plays a dual role in antitumor proliferation and metastasis through targeting DHFR and TP. Mol Cancer Ther. 2019;18(3):541-55.
- Khan MW, Saadalla A, Ewida AH, Al-Katranji K, Al-Saoudi G, Giaccone ZT, et al. The STAT3 inhibitor pyrimethamine displays anti-cancer and immune stimulatory effects in murine models of breast cancer. Cancer Immunol Immunother. 2018;67(1):13-23.
- Rivera-Peña B, Chakraborty S, Shi Y, Zhang H, Desai SR, Patel PP, et al. Pyrimethamine overcomes resistance to hypomethylating agents by reducing de novo pyrimidine synthesis. Exp Hematol. 2026;156:105382.
- DiNardo CD, Pratz KW, Letai A, Jonas BA, Wei AH, Thirman M, et al. Safety and preliminary efficacy of venetoclax with decitabine or azacitidine in elderly patients with previously untreated acute myeloid leukaemia: a non-randomised, open-label, phase 1b study. Lancet Oncol. 2018;19(2):216-28.
- Konopleva M, Pollyea DA, Potluri J, Chyla B, Hogdal L, Busman T, et al. Efficacy and biological correlates of response in a phase II study of venetoclax monotherapy in patients with acute myelogenous leukemia. Cancer Discov. 2016;6(10):1106-17.
- Armstrong Lumley M, Burgess R, Billingham LJ, McDonald DF, Milligan DW. Colony counting is a major source of variation in CFU-GM results between centres. Br J Haematol. 1997;97(2):481-4.
- Lamana M, Albella B, Rodríguez F, Regidor C, Bueren JA. Conclusions of a national multicenter intercomparative study of in vitro cultures of human hematopoietic progenitors. Bone Marrow Transplant. 1999;23(4):373-80.
- Moroff G, Eichler H, Brand A, Kekomäki R, Kurtz J, Letowska M, et al. Multiple-laboratory comparison of in vitro assays utilized to characterize hematopoietic cells in cord blood. Transfusion. 2006;46(4):507-15.
- Morrison SJ, Scadden DT. The bone marrow niche for haematopoietic stem cells. Nature. 2014;505(7483):327-34.
- Shlush LI, Zandi S, Mitchell A, Chen WC, Brandwein JM, Gupta V, et al. Identification of pre-leukaemic haematopoietic stem cells in acute leukaemia. Nature. 2014;506(7488):328-33.
- Becker AJ, McCulloch EA, Till JE. Cytological demonstration of the clonal nature of spleen colonies derived from transplanted mouse marrow cells. Nature. 1963;197(4866):452-4.
- Bradley TR, Metcalf D. The growth of mouse bone marrow cells in vitro. Aust J Exp Biol Med Sci. 1966;44(3):287-99.
- Pamphilon D, Selogie E, McKenna D, Cancelas-Peres J, Szczepiorkowski ZM, Sacher R, et al. Current practices and prospects for standardization of the hematopoietic colony-forming-unit (CFU) assay: a report by the Cellular Therapy Team of the Biomedical Excellence for Safer Transfusion (BEST) Collaborative. Cytotherapy. 2013;15(3):255-62.
- Marzec-Schmidt K, Ghosheh N, Stahlschmidt SR, Küppers-Munther B, Synnergren J, Ulfenborg B. Artificial intelligence supports automated characterization of differentiated human pluripotent stem cells. Stem Cells. 2023;41(9):850-61.
Reprints and Permissions
