This protocol describes the development and internal validation of an exploratory nomogram integrating periodontal parameters and conventional risk factors to estimate cerebral small vessel disease burden for individualized risk stratification.
A subscription to JoVE is required to view this content. Sign in or start your free trial.
Research Article
Development and Internal Validation of an Exploratory Nomogram for Cerebral Small Vessel Disease Burden Using Periodontal Parameters
In This Article
Summary
Abstract
Cerebral small vessel disease (CSVD) is a major cause of stroke and cognitive decline, but the contribution of periodontal disease to the overall CSVD burden remains unclear. We aimed to develop and internally validate an exploratory clinical nomogram incorporating periodontal parameters to estimate a high CSVD burden. A total of 234 individuals underwent magnetic resonance imaging (MRI) for assessment of total CSVD burden (score 0–4). Periodontitis severity and retained tooth count were recorded. Optimal predictors selected using the least absolute shrinkage and selection operator (LASSO) regression were entered into multivariable logistic regression to construct the nomogram, which was evaluated for discrimination, calibration, and clinical utility. Restricted cubic spline analysis demonstrated a linear dose-response relationship between tooth loss and high CSVD burden (P for non-linearity = 0.332). Multivariable analysis identified advanced age and hypertension as independent prognostic factors; however, the associations of severe periodontitis (P = 0.580) and severe tooth loss (P = 0.112) were attenuated and were not independently associated with high CSVD burden after adjustment. The nomogram demonstrated modest discrimination (area under the curve = 0.675) and favorable bootstrap-validated calibration (mean absolute error = 0.038). Decision curve analysis suggested potential clinical utility across selected risk thresholds, although interpretation remains exploratory because of the absence of external validation. Although severe periodontitis and tooth loss showed univariable associations with high CSVD burden, they were not independent predictors after multivariable adjustment. This exploratory nomogram provides a preliminary visualization framework for individualized risk stratification and warrants further external validation before clinical implementation.
Introduction
Cerebral small vessel disease (CSVD) is a chronic and insidious microvascular disorder of the brain that is widely recognized as a leading vascular cause of stroke, cognitive decline, and mobility impairment in older adults1. Historically, individual magnetic resonance imaging (MRI) markers of CSVD, including white matter hyperintensities (WMH), lacunar infarcts, cerebral microbleeds (CMBs), and enlarged perivascular spaces (EPVS), were evaluated independently. However, these neuroimaging phenotypes frequently coexist and are driven by shared pathological mechanisms, particularly endothelial dysfunction and microvascular leakage2. Consequently, recent consensus statements advocate the use of a total CSVD burden scoring system3. This integrated metric more comprehensively reflects the cumulative impact of cerebral microvascular injury than individual imaging markers and provides a superior indicator of overall neurological deterioration4.
The etiology of CSVD remains incompletely understood; however, chronic low-grade systemic inflammation is increasingly recognized as a key contributor to cerebral endothelial injury and blood-brain barrier disruption5. Within this context, periodontitis, a highly prevalent dysbiotic biofilm-induced inflammatory disease affecting the tooth-supporting tissues, has emerged as a potentially modifiable risk factor for neurovascular disease within the framework of the oral-brain axis6. Severe periodontitis not only results in progressive alveolar bone destruction and eventual tooth loss but also serves as a persistent reservoir of periodontal pathogens and pro-inflammatory cytokines7. These inflammatory mediators can enter the systemic circulation, thereby contributing to vascular remodeling and atherogenesis8.
Recent epidemiological studies have demonstrated an association between severe periodontitis and an increased risk of ischemic stroke9. Nevertheless, evidence regarding its relationship with the cumulative burden of CSVD remains limited and fragmented. Furthermore, tooth loss, the ultimate clinical consequence of periodontal disease, has been associated with cognitive decline and cardiovascular mortality10. However, the dose-response relationship between tooth loss and cerebrovascular injury remains poorly understood. Specifically, it is unclear whether the risk of CSVD increases after a critical threshold of remaining teeth is reached or follows a continuous linear dose-response pattern.
Although the association between periodontal destruction and cerebral microvascular injury is biologically plausible, the systemic immune-inflammatory mechanisms underlying this relationship require further characterization. Conventional inflammatory biomarkers, including isolated leukocyte subset counts and high-sensitivity C-reactive protein, may not adequately capture the complexity of the host immune-inflammatory response in clinical settings. The Systemic Immune-Inflammation Index (SII), calculated from peripheral platelet, neutrophil, and lymphocyte counts, has recently emerged as a comprehensive inflammatory biomarker11. The SII reflects the balance between systemic inflammatory activity and immune status. Elevated SII levels have demonstrated prognostic value across a range of cerebrovascular disorders by predicting acute stroke severity and poor functional outcomes and have also been associated with overall CSVD burden, cognitive impairment, and the graded diagnosis of periodontitis12,13. Because periodontitis induces chronic systemic inflammation, evaluating the SII together with periodontal parameters may improve the identification of individuals at risk of covert cerebral microvascular injury.
Despite growing interest in the oral-brain axis, the current literature has several methodological limitations. Most studies have focused on individual CSVD imaging markers or single oral health parameters, without integrating periodontitis severity, its ultimate clinical consequence (tooth loss), and systemic immune-inflammatory responses into a unified assessment. More importantly, clinical practice requires practical risk assessment tools, yet visual instruments such as nomograms for identifying patients at high risk of CSVD based on combined oral and systemic inflammatory profiles remain limited. Existing CSVD risk assessment approaches primarily rely on individual biomarkers or conventional demographic factors, which may not adequately capture the multifactorial interactions between systemic inflammation and oral health. Furthermore, the development of reliable prediction models requires robust variable selection methods. Conventional approaches, such as stepwise regression, may be unstable when applied to high-dimensional clinical datasets and can be influenced by correlated predictors. The least absolute shrinkage and selection operator (LASSO) regression approach addresses these challenges by applying coefficient penalization to reduce overfitting and identify the most informative predictors for model development14.
Motivated by these knowledge gaps, this retrospective cross-sectional study was designed with two primary objectives. First, we aimed to characterize the dose-response relationship between retained tooth count and high CSVD burden using restricted cubic spline (RCS) analysis to evaluate potential non-linear threshold effects and linear trends. Second, we sought to develop an exploratory clinical nomogram using LASSO-based variable selection and to evaluate the incremental risk reclassification provided by periodontal parameters beyond conventional risk factors. We hypothesized that integrating periodontal status, tooth loss, and the SII into a multidimensional model could provide an exploratory visualization framework for estimating cumulative CSVD burden and improve individualized risk stratification. In clinical practice, the proposed nomogram is intended as a rapid, non-invasive adjunctive tool to assist neurologists in identifying patients who may benefit from early cerebrovascular evaluation or multidisciplinary dental assessment. However, given its exploratory nature, modest discriminatory performance, and lack of external validation, the nomogram should not be considered a substitute for magnetic resonance imaging (MRI)-based diagnosis. In addition, its application may be limited in patients with active acute infections, severe autoimmune diseases, or recent trauma, as these conditions may substantially influence systemic inflammatory biomarkers and affect risk estimation.
Access restricted. Please log in or start a trial to view this content.
Protocol
This retrospective cross-sectional association study enrolled consecutive patients admitted to the Department of Neurology at Changzhou No. 2 People’s Hospital for dizziness, headache, stroke screening, or cognitive assessment between January 2022 and December 2024. Informed consent was waived because of the retrospective, non-interventional nature of the study and the use of fully anonymized data. The study was approved by the Clinical Medical Technology Ethics Committee of Changzhou No. 2 People’s Hospital (IRB approval ID: [2023] YLJSA069) and was conducted in accordance with institutional guidelines.
Study Design and Patient Population
Initially, 850 patients were evaluated. The exclusion criteria were strictly defined as follows: (1) lack of complete cranial MRI sequences (especially missing susceptibility-weighted imaging [SWI], precluding accurate evaluation of microbleeds); (2) absence of detailed periodontal probing records or full-mouth tooth count data; (3) incomplete blood count data, preventing calculation of the SII; (4) history of massive stroke, brain tumor, traumatic brain injury, or central nervous system infection; and (5) presence of active acute infection, severe autoimmune disease, or malignancy within the past month to minimize confounding effects on systemic inflammatory markers. To ensure data integrity, a complete-case analysis approach was used, whereby individuals missing any core clinicoradiological parameters were excluded. After screening, 234 eligible participants were included in the analysis. This sample, comprising 129 high-burden events, satisfied the events-per-variable (EPV) >10 rule of thumb for stable multivariable modeling.
Assessment of Periodontal Status and Inflammation
Two calibrated periodontists performed all clinical oral assessments using a standardized periodontal probe.
Before the study, both examiners underwent standardization training, and inter-examiner reliability was excellent (Cohen’s κ = 0.82). Probing pocket depth (PPD) and clinical attachment level (CAL) were measured at six sites per tooth. Based on the 2018 classification framework described by Tonetti et al.15, periodontal disease was classified as mild/absent, moderate, or severe. Specifically, participants were categorized as follows: (1) Mild/absent periodontitis (including periodontal health and Stage I periodontitis), defined as interdental clinical attachment level (CAL) at the site of greatest attachment loss of ≤2 mm and probing pocket depth (PPD) ≤4 mm, without periodontitis-related tooth loss; (2) Moderate periodontitis (Stage II periodontitis), defined as interdental CAL of 3–4 mm, maximum PPD ≤5 mm, and no more than four teeth lost because of periodontitis; and (3) Severe periodontitis (Stage III/IV periodontitis), defined as interdental CAL ≥5 mm, PPD ≥6 mm, and/or loss of four or more teeth because of periodontal destruction15.
The number of retained teeth was also documented for every participant. Because maintaining a minimum of 20 functional teeth is a widely accepted clinical benchmark for preserving basic oral function and successful oral aging16,17,18, the raw tooth count was converted into a binary variable: severe tooth loss (<20 teeth) versus non-severe tooth loss (≥20 teeth).
Regarding systemic inflammation, the SII was derived from fasting blood samples collected at admission. Venous blood samples were collected in EDTA tubes and processed according to the hospital’s standard clinical laboratory protocol before analysis using an automated hematology analyzer to obtain neutrophil, lymphocyte, and platelet counts. The index was calculated as:
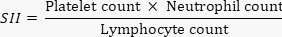
To account for the highly skewed distribution of SII values, a natural logarithmic transformation (Log_SII) was applied before inclusion in the statistical analyses.
MRI Acquisition and Total CSVD Burden
All subjects underwent standardized cranial MRI examinations using a 3.0 T MRI scanner equipped with a standard head coil. The imaging protocol included T1-weighted, T2-weighted, fluid-attenuated inversion recovery (FLAIR), and susceptibility-weighted imaging (SWI) sequences acquired with a slice thickness of 5 mm. Standard imaging parameters were configured as follows: T1-weighted imaging (repetition time [TR] = 2,000 ms, echo time [TE] = 9 ms, field of view [FOV] = 230 × 230 mm2, matrix size = 256 × 256); T2-weighted imaging (TR = 4,500 ms, TE = 85 ms, FOV = 230 × 230 mm2, matrix size = 256 × 256); fluid-attenuated inversion recovery (FLAIR) imaging (TR = 8,500 ms, TE = 120 ms, inversion time [TI] = 2,400 ms, FOV = 230 × 230 mm2, matrix size = 256 × 256); and susceptibility-weighted imaging (SWI) (TR = 28 ms, TE = 20 ms, flip angle = 15°, FOV = 230 × 230 mm2, matrix size = 256 × 256). All sequences were acquired with a slice thickness of 5 mm and an interslice gap of 1.0 mm. The specific scanner is listed in the Table of Materials. The imaging markers of CSVD were independently evaluated by two neuroimaging physicians blinded to the participants’ clinical data. The inter-rater reliability of the total CSVD burden score was high (Cohen’s κ = 0.85). Any discrepancies were resolved by consensus with a third senior physician.
In accordance with established international consensus1,3, the cumulative CSVD burden was quantified on a scale of 0 to 4 by evaluating four neuroimaging features. One point was assigned for each of the following MRI findings: (1) at least one lacunar infarct; (2) one or more cerebral microbleeds (CMBs); (3) moderate-to-severe enlarged perivascular spaces (EPVS) in the basal ganglia (grade ≥2); and (4) severe white matter hyperintensities (WMH), defined as a Fazekas score of ≥2 in the deep white matter or 3 in the periventricular region. The diagnostic definitions strictly adhered to the Standards for Reporting Vascular Changes on Neuroimaging (STRIVE-1) international consensus1. White matter hyperintensities (WMH) were graded using the Fazekas scale19, and enlarged perivascular spaces (EPVS) in the basal ganglia were graded using the validated 4-point visual rating scale described by Potter et al.20. For development of the risk assessment model, patients with a total CSVD burden score of ≥2 were classified as having a high CSVD burden, as this threshold has been consistently associated with accelerated cognitive decline and mortality21,22,23.
Covariates Data Collection
Patient demographic characteristics and clinical history were extracted from institutional electronic health records. The collected variables included age, sex, body mass index (BMI), smoking status, and alcohol consumption. In addition, cardiometabolic and vascular comorbidities, including dyslipidemia, diabetes mellitus, hypertension, coronary artery disease (CAD), history of myocardial infarction (MI), and previous ischemic stroke, were documented for each participant.
All comorbidities were confirmed through review of physician diagnoses documented in the inpatient medical records, medication history, and routine admission laboratory and imaging evaluations, in accordance with established clinical guidelines. Hypertension was defined as a systolic blood pressure of ≥140 mmHg, a diastolic blood pressure of ≥90 mmHg, or current antihypertensive treatment. Diabetes mellitus was defined as a fasting plasma glucose concentration of ≥7.0 mmol/L, glycated hemoglobin (HbA1c) of ≥6.5%, or the use of glucose-lowering medication. Dyslipidemia was defined by fasting serum lipid abnormalities or current lipid-lowering therapy. CAD, history of MI, and previous ischemic stroke were confirmed through documented clinical history and historical neurovascular or cardiac imaging reports available in the electronic health record system.
Statistical Analysis and Model Development
Before statistical analysis, the normality of continuous variables was assessed using the Shapiro–Wilk test. Descriptive statistics for categorical variables were summarized as counts (percentages) and compared using Pearson’s chi-square test or Fisher’s exact test, as appropriate. Continuous variables with a normal distribution were expressed as means ± standard deviations and compared using Student’s t-test, whereas non-normally distributed variables were expressed as medians with interquartile ranges and compared using the Mann-Whitney U test. To investigate potential non-linear dose-response patterns between retained tooth count and the risk of high CSVD burden, an RCS model adjusted for age, hypertension, and Log_SII was constructed using four knots placed at the 5th, 35th, 65th, and 95th percentiles of the tooth count distribution. Formal testing for non-linearity was performed using analysis of variance (ANOVA) to determine whether a threshold effect or a continuous linear trend best explained the observed association.
To perform variable selection in the presence of correlated predictors, all baseline variables were entered into a LASSO regression model. The optimal tuning parameter (λ) was determined using 10-fold cross-validation and selected according to the minimum binomial deviance criterion (λmin). Variables with non-zero coefficients were retained for subsequent analyses. The selected variables were subsequently entered into a multivariable logistic regression model to estimate odds ratios (ORs) and 95% confidence intervals (CIs) for their associations with high CSVD burden. The final multivariable model was then used to construct an exploratory clinical nomogram for individualized risk estimation.
To evaluate the incremental value of the periodontal parameters, a baseline model (including age, hypertension, and Log_SII) was compared with an extended model incorporating periodontitis grade and tooth count. Model performance was assessed using multiple complementary measures. Discrimination was evaluated using the area under the receiver operating characteristic curve (AUC), and differences between models were compared using the DeLong test24. At the optimal cutoff determined by the maximum Youden index, sensitivity, specificity, positive predictive value (PPV), and negative predictive value (NPV) were also calculated. Continuous net reclassification improvement (NRI) and integrated discrimination improvement (IDI) were calculated to quantify the incremental risk reclassification provided by the extended model25. Calibration was assessed using calibration plots generated from 1,000 bootstrap resamples implemented with the rms package, and the mean absolute error between predicted and observed risks was calculated. To account for potential overfitting and provide an unbiased evaluation of model performance, bootstrap validation included optimism correction, with both bias-corrected and apparent model performance reported. Decision curve analysis (DCA) was performed to evaluate potential clinical utility by estimating the net benefit across a range of threshold probabilities. All statistical analyses and visualizations were performed using statistical software and the rms, glmnet, pROC, PredictABEL, and dcurves packages. Statistical significance was defined as a two-sided P value of <0.05.
Access restricted. Please log in or start a trial to view this content.
Results
Study Design and Patient Population
Following the exclusion of 616 individuals because of major confounding illnesses or missing clinicoradiological data, the final analysis included 234 eligible participants admitted for neurological evaluation (Figure 1). Participants were stratified according to their aggregate CSVD scores into high-burden (n = 129) and low-burden (n = 105) groups. The baseline demographic and clinical characteristics of both g...
Access restricted. Please log in or start a trial to view this content.
Discussion
The present study investigated the relationship between periodontal destruction, retained tooth count, and the cumulative burden of CSVD, culminating in the development of an exploratory clinical nomogram. Although univariable analyses demonstrated associations between severe periodontitis, tooth loss, and high CSVD burden, multivariable logistic regression showed that severe periodontitis (P = 0.580) and retained tooth count (P = 0.112) were not independently associated with high CSVD burden after adju...
Access restricted. Please log in or start a trial to view this content.
Disclosures
Conflict of Interest:
The authors declare that they have no conflicts of interest.
Acknowledgements
Not applicable.
Access restricted. Please log in or start a trial to view this content.
Materials
| Name | Company | Catalog Number | Comments |
|---|---|---|---|
| Automated Hematology Analyzer | Sysmex | XN-1000 | Used to obtain peripheral blood cell counts for calculation of the systemic immune-inflammation index (SII). |
| EDTA Blood Collection Tubes (K2 EDTA) | Becton, Dickinson and Company | 367841 | Used for fasting venous blood collection. |
| Electronic Medical Record (EMR) System | Winning Health Technology Group | Winning EMR v6.0 | Used to extract patient demographic and clinical information. |
| Magnetic Resonance Imaging (MRI) Scanner (3.0 T) | Siemens Healthineers | MAGNETOM Prisma 3.0T | Used for standardized cranial magnetic resonance imaging examinations. |
| MRI Head Coil | Siemens Healthineers | 64-channel Head/Neck Coil | Standard head coil used for MRI acquisition. |
| Periodontal Probe (UNC-15) | Hu-Friedy | PCPUNC15 | Used for periodontal probing depth (PPD) and clinical attachment level (CAL) measurements. |
| R Package: dcurves | CRAN | Version 0.4.0 | Used for decision curve analysis (DCA). |
| R Package: glmnet | CRAN | Version 4.1-8 | Used for least absolute shrinkage and selection operator (LASSO) regression and variable selection. |
| R Package: pROC | CRAN | Version 1.18.5 | Used for receiver operating characteristic (ROC) curve analysis and DeLong tests. |
| R Package: PredictABEL | CRAN | Version 1.2-4 | Used to calculate continuous net reclassification improvement (NRI) and integrated discrimination improvement (IDI). |
| R Package: rms | CRAN | Version 6.7-1 | Used for restricted cubic spline (RCS) analysis, nomogram construction, and bootstrap calibration. |
| R Software for Statistical Computing | R Foundation for Statistical Computing | Version 4.3.1 | Statistical computing environment used for all analyses. |
References
- Wardlaw JM, et al. Neuroimaging standards for research into small vessel disease and its contribution to ageing and neurodegeneration. Lancet Neurol. 2013;12(8):822-38.
- Pantoni L. Cerebral small vessel disease: from pathogenesis and clinical characteristics to therapeutic challenges. Lancet Neurol. 2010;9(7):689-701.
- Staals J, et al. Stroke subtype, vascular risk factors, and total MRI brain small-vessel disease burden. Neurology. 2014;83(14):1228-34.
- Amin Al Olama A, et al. Simple MRI score aids prediction of dementia in cerebral small vessel disease. Neurology. 2020;94(12):e1294-302.
- Low A, et al. Inflammation and cerebral small vessel disease: A systematic review. Ageing Res Rev. 2019;53:100916.
- Sanz M, et al. Periodontitis and cardiovascular diseases: Consensus report. J Clin Periodontol. 2020;47(3):268-88.
- Hajishengallis G. Periodontitis: from microbial immune subversion to systemic inflammation. Nat Rev Immunol. 2015;15(1):30-44.
- Leira Y, et al. Association between periodontitis and ischemic stroke: a systematic review and meta-analysis. Eur J Epidemiol. 2017;32(1):43-53.
- Sen S, et al. Periodontal disease, regular dental care use, and incident ischemic stroke. Stroke. 2018;49(2):355-62.
- Peng J, et al. The relationship between tooth loss and mortality from all causes, cardiovascular diseases, and coronary heart disease in the general population: systematic review and dose-response meta-analysis of prospective cohort studies. Biosci Rep. 2019;39(1):BSR20181773.
- Hu B, et al. Systemic immune-inflammation index predicts prognosis of patients after curative resection for hepatocellular carcinoma. Clin Cancer Res. 2014;20(23):6212-22.
- Xiao Y, et al. Systemic immune-inflammation index is associated with cerebral small vessel disease burden and cognitive impairment. Neuropsychiatr Dis Treat. 2023;19:403-13.
- Hu Y, et al. Correlation between systemic immune-inflammatory index and graded diagnosis of periodontitis: a combined cross-sectional and retrospective study. BMC Oral Health. 2024;24(1):1545.
- Tibshirani R. Regression shrinkage and selection via the lasso. J R Stat Soc Series B Stat Methodol. 1996;58(1):267-88.
- Tonetti MS, Greenwell H, Kornman KS. Staging and grading of periodontitis: Framework and proposal of a new classification and case definition. J Periodontol. 2018;89(Suppl 1):S159-72.
- Zhang XM, et al. The association between the number of teeth and frailty among older adults: a systematic review and meta-analysis. Aging Clin Exp Res. 2025;37(1):156.
- Cheng Y, et al. New measure of functional tooth loss for successful oral ageing: a cross-sectional study. BMC Geriatr. 2023;23(1):859.
- Suwanarpa K, et al. How many teeth are needed to maintain healthy oral function in older adults? A cross-sectional analysis. Prosthesis. 2026;8(1):10.
- Fazekas F, Chawluk JB, Alavi A, Hurtig HI, Zimmerman RA. MR signal abnormalities at 1.5 T in Alzheimer’s dementia and normal aging. AJR Am J Roentgenol. 1987;149(2):351-6.
- Potter GM, Chappell FM, Morris Z, Wardlaw JM. Cerebral perivascular spaces visible on magnetic resonance imaging: development of a qualitative rating scale and its observer reliability. Cerebrovasc Dis. 2015;39(3-4):224-31.
- Pasi M, et al. Association of cerebral small vessel disease and cognitive decline after intracerebral hemorrhage. Neurology. 2021;96(2):e182-92.
- Goldstein ED, et al. Cerebral small vessel disease burden and all-cause mortality: Mayo Clinic Florida Familial Cerebrovascular Diseases Registry. J Stroke Cerebrovasc Dis. 2019;28(12):104285.
- Jiang Y, et al. Total cerebral small vessel disease burden is related to worse performance on the Mini-Mental State Examination and incident dementia: a prospective 5-year follow-up. J Alzheimers Dis. 2019;69(1):253-62.
- DeLong ER, DeLong DM, Clarke-Pearson DL. Comparing the areas under two or more correlated receiver operating characteristic curves: a nonparametric approach. Biometrics. 1988;44(3):837-45.
- Pencina MJ, D’Agostino RB Sr, D’Agostino RB Jr, Vasan RS. Evaluating the added predictive ability of a new marker: from area under the ROC curve to reclassification and beyond. Stat Med. 2008;27(2):157-72.
- Meyer J, et al. Periodontal disease independently associated with white matter hyperintensity volume. Neurol Open. 2020;1(4):e000037.
- Charidimou A, Pantoni L, Love S. The concept of sporadic cerebral small vessel disease: a road map on key definitions and current concepts. Int J Stroke. 2016;11(1):6-18.
- Peres MA, et al. Oral diseases: a global public health challenge. Lancet. 2019;394(10194):249-60.
- Han S, et al. Cerebral small vessel disease as a novel risk indicator for periodontitis progression. Int Dent J. 2026;76(2):109414.
- Friedman J, Hastie T, Tibshirani R. Regularization paths for generalized linear models via coordinate descent. J Stat Softw. 2010;33(1):1-22.
- Sauerbrei W, Royston P, Binder H. Selection of important variables and determination of functional form for continuous predictors in multivariable model building. Stat Med. 2007;26(30):5512-28.
- Hajishengallis G, Chavakis T. Local and systemic mechanisms linking periodontal disease and inflammatory comorbidities. Nat Rev Immunol. 2021;21(7):426-40.
- Tonetti MS, et al. Treatment of periodontitis and endothelial function. N Engl J Med. 2007;356(9):911-20.
- Dominy SS, et al. Porphyromonas gingivalis in Alzheimer’s disease brains: evidence for disease causation and treatment with small-molecule inhibitors. Sci Adv. 2019;5(1):eaau3333.
- Wardlaw JM, et al. Blood-brain barrier failure as a core mechanism in cerebral small vessel disease and dementia: evidence from a cohort study. Alzheimers Dement. 2017;13(6):634-43.
- Vickers AJ, Elkin EB. Decision curve analysis: a novel method for evaluating prediction models. Med Decis Making. 2006;26(6):565-74.
- Collins GS, Reitsma JB, Altman DG, Moons KG. Transparent reporting of a multivariable prediction model for individual prognosis or diagnosis (TRIPOD): the TRIPOD statement. BMJ. 2015;350:g7594.
- Kamer AR, et al. Inflammation and Alzheimer’s disease: possible role of periodontal diseases. Alzheimers Dement. 2008;4(4):242-50.
- Steyerberg EW, et al. Assessing the performance of prediction models: a framework for traditional and novel measures. Epidemiology. 2010;21(1):128-38.
- D’Aiuto F, et al. Periodontitis: from local infection to systemic diseases. Int J Immunopathol Pharmacol. 2005;18(3 Suppl):1-11.
- Moldvai J, et al. Oral health status and its associated factors among post-stroke inpatients: a cross-sectional study in Hungary. BMC Oral Health. 2022;22(1):234.
- Jockusch J, et al. Influence of cognitive impairment and dementia on oral health and the utilization of dental services: findings of the Oral Health, Bite Force and Dementia Study (OrBiD). BMC Oral Health. 2021;21(1):399.
- Leira Y, et al. Porphyromonas gingivalis lipopolysaccharide-induced periodontitis and serum amyloid-beta peptides. Arch Oral Biol. 2019;99:120-5.
Access restricted. Please log in or start a trial to view this content.